X-Linked Agammaglobulinemia (Bruton's Agammaglobulinemia)
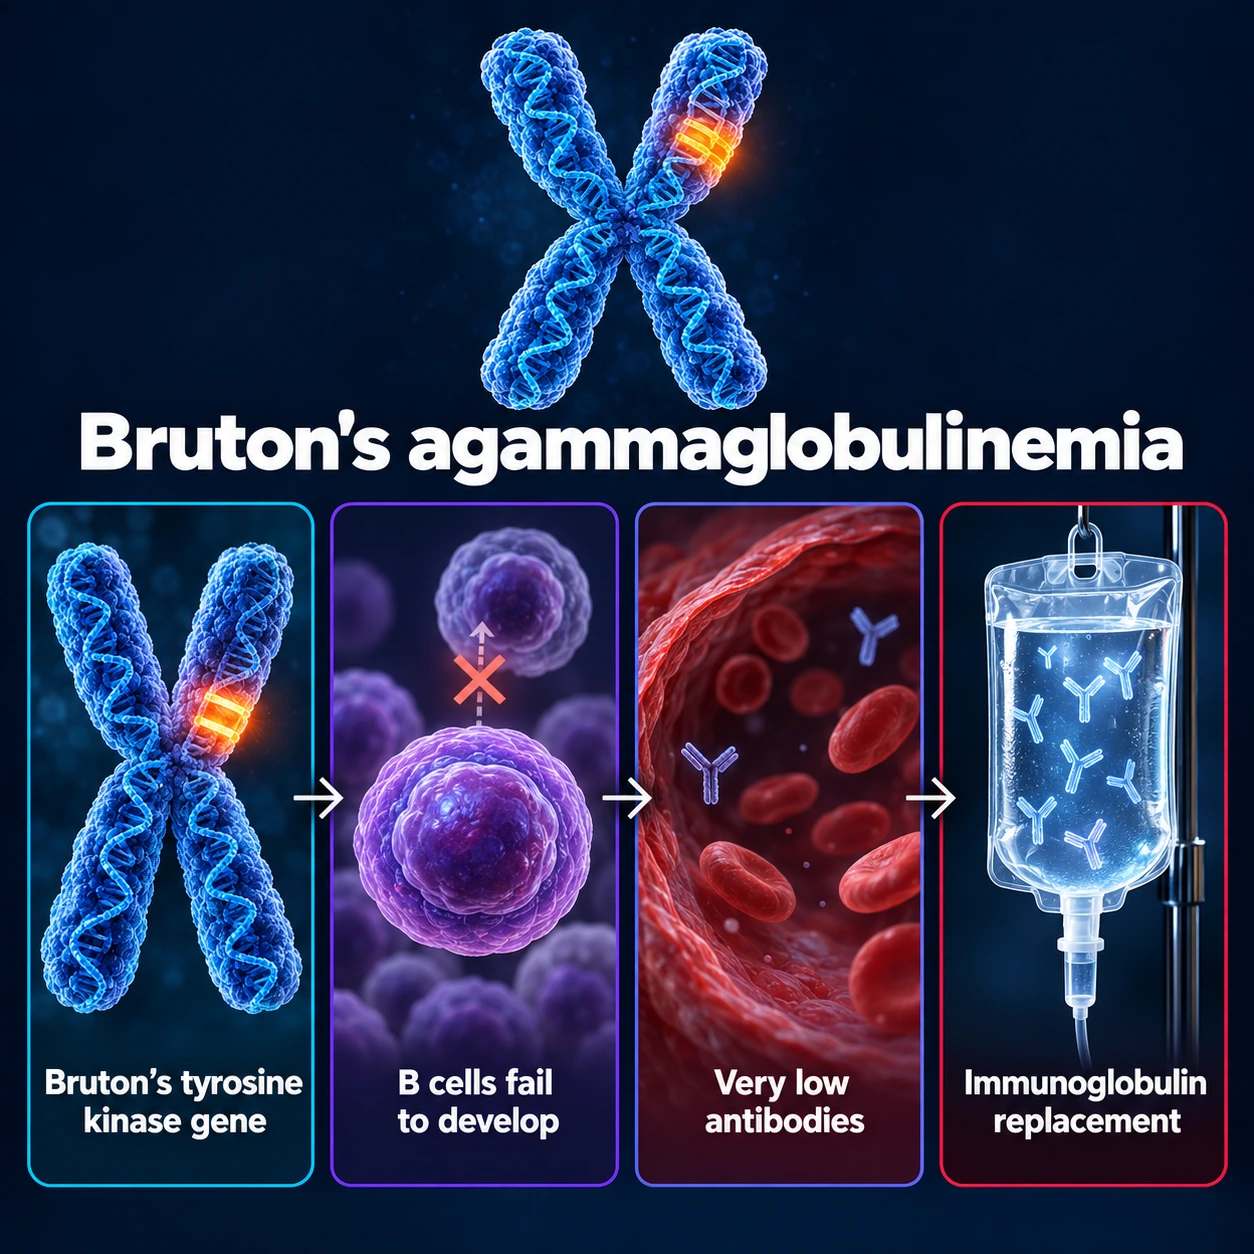
Table of Contents
- What X-Linked Agammaglobulinemia Is
- The BTK Gene and How XLA Develops
- Signs and Symptoms
- Diagnosis: Flow Cytometry and Genetic Testing
- Infections in XLA: What to Expect
- Vaccine Rules and Immunization
- Treatment: Lifelong Immunoglobulin Replacement
- Complications and Long-Term Outlook
- Family Implications: Carrier Detection
- Key Research Papers
- Connections
- Featured Videos
What X-Linked Agammaglobulinemia Is
X-Linked Agammaglobulinemia (XLA) — also called Bruton's Agammaglobulinemia after the American immunologist Ogden Bruton, who first described it in 1952 — is one of the most common and best-characterized primary antibody deficiency diseases. It is caused by mutations in the BTK (Bruton's tyrosine kinase) gene on the X chromosome, which arrests the development of B lymphocytes at an early precursor stage. The result is a near-total absence of circulating B cells and a profound deficiency of all immunoglobulin classes — a state called panhypogammaglobulinemia.
Because it is X-linked recessive, XLA overwhelmingly affects males. Boys carry only one copy of the X chromosome; a single mutated BTK allele is sufficient to cause full disease. Females who carry one mutated and one normal BTK allele are carriers: they are clinically unaffected because their normal X chromosome provides enough functional BTK for adequate B-cell development.
A 2025 review estimates that XLA occurs in between 1 in 100,000 and 1 in 200,000 people; the United States registry of 201 patients estimated a birth rate of 1 in 379,000 for 1988–1997. Recurrent or unusually severe bacterial infections typically begin once protective maternal antibodies — transferred across the placenta during the third trimester — wane at around six to nine months of age. In the US registry, the average age at diagnosis was 2.59 years in boys with a family history of XLA and 5.37 years in boys without one, and only 34.5% of boys with a known family history at birth were diagnosed before symptoms began.
Despite the absence of B cells and antibodies, T-cell immunity remains intact. This is a crucial distinguishing feature: unlike Severe Combined Immunodeficiency (SCID), patients with XLA are not unusually susceptible to fungal, parasitic, or most viral infections. Their vulnerability is specifically to encapsulated bacteria that require opsonizing antibodies for efficient clearance — organisms like Streptococcus pneumoniae and Haemophilus influenzae.
With early diagnosis and regular immunoglobulin replacement therapy, most people with XLA lead full, active lives. The challenge lies in maintaining adequate immunoglobulin G (IgG) trough levels and monitoring for the long-term complications — particularly chronic lung disease from recurrent pneumonias — that can accumulate over decades.
The BTK Gene and How XLA Develops
The BTK gene sits on the long arm of the X chromosome at position Xq21.3–22. It encodes Bruton's tyrosine kinase, a non-receptor tyrosine kinase that belongs to the Tec family of kinases. BTK is expressed in hematopoietic cells at multiple stages of development, but its role is most critical in B-cell maturation.
The normal B-cell development pathway
Under normal circumstances, B-cell precursors in the bone marrow progress through a precise sequence of stages: pro-B cell → pre-B cell → immature B cell → mature naïve B cell. Each transition requires specific signaling events, and BTK is indispensable at the pre-B cell receptor (pre-BCR) checkpoint — the transition from pre-B cell to immature B cell. When the newly assembled pre-BCR successfully signals through BTK, the cell is permitted to continue maturation, rearrange its light chain genes, and eventually emerge as a mature B cell capable of producing antibodies.
What goes wrong in XLA
In XLA, mutations in BTK prevent this signaling step. The block in differentiation occurs at the pre-B cell stage: precursors accumulate in bone marrow but fail to mature. The peripheral blood and secondary lymphoid tissues are therefore almost completely devoid of mature B cells — typically less than 1% CD19+ B cells (normal: 5–20%). Without B cells, there are no plasma cells to produce antibodies. All immunoglobulin isotypes — immunoglobulin G, immunoglobulin A (IgA), immunoglobulin M (IgM), immunoglobulin E (IgE), and IgD — are severely reduced or absent. Immunoglobulin G, which provides most long-term protection against bacterial infections, typically falls below 100 mg/dL (normal adult range: 700–1600 mg/dL).
Mutation spectrum
Over 900 distinct BTK mutations have been catalogued in the BTK mutation database. They include missense mutations, nonsense mutations, frameshift deletions and insertions, splice-site mutations, and large deletions. There is no single founder mutation in most populations, meaning each family typically has its own private variant. Unlike some genetic diseases, there is limited genotype-phenotype correlation: different mutations in the same domain can produce variable clinical severity, and even identical mutations within the same family can present differently in different members. That said, mutations that completely abolish BTK protein expression (detected by monocyte BTK protein flow cytometry) tend to produce the most profound antibody deficiency. A 2025 international study of XLA patients aged 55 or older put numbers on this: BTK protein could still be detected in 83.3% of those with missense mutations (a single changed building block, so some protein is still made) compared with 30% of those with other mutation types, and the group with other mutation types had more infections, more antibiotic use, worse lung function and higher death rates.
Why T cells are unaffected
BTK is expressed in B-cell precursors, monocytes, macrophages, and platelets — but not in T-cell precursors. T-cell development in the thymus proceeds normally in XLA. As a result, patients retain full cellular immunity: they make normal cytotoxic T-cell responses, helper T-cell function, and natural killer cell activity. This is why XLA patients, unlike SCID patients, handle most viral infections normally (with the critical exception of enteroviruses).
Signs and Symptoms
The clinical presentation of XLA follows a predictable timeline shaped by the waning of maternal antibodies in the first year of life and the accumulating burden of infections over subsequent years.
The healthy first six months
Newborn boys with XLA appear entirely healthy at birth. This is because maternal immunoglobulin G crosses the placenta during the third trimester, providing the infant with a temporary reservoir of protective antibodies. This passively acquired immunity is sufficient to protect against most bacterial threats in the first few months of life — the same protection any baby receives, regardless of their own B-cell status. Parents and pediatricians have no reason to suspect anything is wrong during this period.
Onset of symptoms: 6–24 months
As maternal immunoglobulin G is catabolized over the first six to twelve months of life and the infant's own immune system fails to compensate, recurrent bacterial infections begin. The typical age of onset is 6–18 months, though some boys remain protected into the second year if maternal immunoglobulin G levels were particularly high. The infections that characterize early XLA include:
- Otitis media — recurrent middle ear infections, often caused by Streptococcus pneumoniae or Haemophilus influenzae
- Sinusitis — chronic or recurrent sinus infections
- Pneumonia — lung infections that may fail to fully resolve between episodes
- Pharyngitis and tonsillitis — though, importantly, tonsils may be visibly absent or very small (a key diagnostic clue)
Characteristic physical examination findings
A thoughtful physical examination can suggest XLA before any laboratory testing:
- Absent or hypoplastic tonsils — tonsils contain lymphoid follicles with germinal centers that require B cells; in XLA they fail to develop normally and are often visibly absent or reduced to tiny nubs
- No palpable lymph nodes — similarly, peripheral lymph nodes that would normally enlarge during infection appear flat and unpalpable, because their B-cell zones and germinal centers are empty
- Normal-appearing child otherwise — growth and development are normal; there is no rash, no hepatosplenomegaly at presentation in most cases
Older boys and adults
Boys who are diagnosed later (or not treated adequately) may develop more serious manifestations:
- Invasive pneumococcal disease — bacteremia, meningitis, or septic arthritis caused by S. pneumoniae
- Pseudomonas infections — Pseudomonas aeruginosa can colonize the airways and cause progressive bronchiectasis
- Septic arthritis — particularly caused by mycoplasma species or bacteria; a large joint (knee, hip) that is hot, swollen, and tender raises suspicion
- Chronic enteroviral meningoencephalitis — a devastating late complication (see Complications section)
Diagnosis: Flow Cytometry and Genetic Testing
XLA diagnosis rests on demonstrating markedly reduced B cells in the peripheral blood, confirming hypogammaglobulinemia across all isotypes, and identifying the causative BTK mutation. In a boy with recurrent sinopulmonary infections and absent tonsils, clinical suspicion is high and the workup is straightforward.
Immunoglobulin quantification
The first step is measuring serum immunoglobulin levels. In XLA:
- Immunoglobulin G is typically less than 100 mg/dL (normal for age: 500–1200 mg/dL in young children)
- Immunoglobulin A and immunoglobulin M are also profoundly low or undetectable
- Isohemagglutinins (naturally occurring antibodies to blood group antigens) are absent — a useful bedside functional test of B-cell competence
It is important to compare values to age-matched normal ranges, because infants and young children naturally have lower immunoglobulin G than adults.
Flow cytometry: the key confirmatory test
Flow cytometric enumeration of B cells (CD19+ or CD20+ lymphocytes) is the most important diagnostic test. In XLA, circulating B cells are typically less than 2% of total lymphocytes — often less than 1%, and sometimes undetectable. By contrast, patients with Common Variable Immunodeficiency (CVID) — who present similarly with hypogammaglobulinemia — typically have normal or only modestly reduced B-cell numbers. This distinction makes flow cytometry essential: absent B cells point strongly to XLA; present B cells shift the differential toward CVID or other antibody deficiencies.
Monocyte BTK protein expression can also be assessed by intracellular flow cytometry. Because BTK is expressed in monocytes as well as B-cell precursors, absent or markedly reduced BTK staining in monocytes strongly supports a BTK mutation and can yield a result in hours.
BTK gene sequencing
Definitive diagnosis requires BTK gene sequencing — either targeted sequencing of coding exons or, increasingly, next-generation sequencing panels covering all primary immunodeficiency genes simultaneously. Identifying the specific mutation confirms XLA, enables carrier testing of female relatives, and facilitates prenatal/preimplantation diagnosis in future pregnancies.
Differential diagnosis
Conditions to distinguish from XLA include:
- Transient hypogammaglobulinemia of infancy — a temporary physiological dip in immunoglobulin G that resolves spontaneously; B-cell numbers are normal
- CVID — onset usually later (teens/young adults), B cells present, no BTK mutation
- Autosomal recessive agammaglobulinemia — mutations in other B-cell development genes (IGHM, IGLL1, CD79A, CD79B, BLNK, PIK3R1) can produce an identical phenotype in males or females; distinguished by BTK sequencing returning normal
- SCID — absent T cells as well as B cells; much more severely ill at presentation
Newborn screening programs that include lymphocyte enumeration (such as TREC-based SCID screening) may not reliably detect XLA, because T-cell numbers are normal. Dedicated B-cell enumeration (KREC assay) can screen for XLA but is not yet standard in most states.
Infections in XLA: What to Expect
The infection risk in XLA is specific, predictable, and can be substantially mitigated by adequate immunoglobulin replacement. Understanding which pathogens pose the greatest threat — and which ones do not — is essential for parents, patients, and their healthcare providers.
What the United States registry found
In the US registry of 201 patients (2006), infection was the most common first sign (85%), followed by a family history of the disease (41%) and low neutrophil counts (neutropenia, 11%). Seventy percent had had at least one ear infection, 62% at least one pneumonia, 60% sinusitis and 11% meningitis or encephalitis. The most common causes of death were widespread enterovirus infection (6 deaths) and lung failure (5 deaths).
The encapsulated bacterial threat
The bacteria that cause the most serious infections in XLA share a key characteristic: they have thick polysaccharide capsules that make them resistant to phagocytosis unless first coated (opsonized) by antibodies. In the absence of immunoglobulin G, the innate immune system cannot efficiently clear these organisms:
- Streptococcus pneumoniae — the leading cause of pneumonia, otitis media, sinusitis, meningitis, and bacteremia in XLA; before immunoglobulin therapy, pneumococcal meningitis was a major cause of mortality
- Haemophilus influenzae (typeable and nontypeable) — causes otitis media, sinusitis, pneumonia, and occasionally invasive disease
- Staphylococcus aureus — skin infections, septic arthritis, osteomyelitis, and pneumonia
- Pseudomonas aeruginosa — pulmonary colonization and progressive bronchiectasis, particularly in older patients with established lung disease
- Mycoplasma pneumoniae and related species — atypical pneumonia; also causes a distinctive septic-arthritis-like joint disease in XLA that does not respond to standard antibiotics
Enteroviral susceptibility: the critical viral exception
While most viral infections are handled adequately by T-cell immunity, enteroviruses (echoviruses, coxsackieviruses, poliovirus, and parechoviruses) represent a serious and specific threat in XLA. Normally, the antibody response is critical for containing and clearing enteroviruses from the central nervous system. In patients without B cells:
- Enteroviral infections can establish chronic central nervous system (CNS) infection, resulting in a progressive meningoencephalitis that resembles dermatomyositis (skin and muscle inflammation alongside encephalopathy)
- The syndrome is called enteroviral meningoencephalitis or the XLA-associated ECHO-dermatomyositis syndrome
- Symptoms include chronic headache, cognitive decline, personality changes, progressive weakness, and a characteristic skin rash
- This complication was more common before immunoglobulin replacement was widely available and adequately dosed
- Live oral poliovirus vaccine (OPV) is absolutely contraindicated — it contains attenuated live poliovirus capable of causing paralytic polio in immunocompromised patients (see Vaccine section)
Infections XLA patients handle normally
Because T-cell immunity is intact, patients with XLA generally do not develop the opportunistic infections characteristic of T-cell or combined immunodeficiencies:
- No increased risk of Pneumocystis jirovecii pneumonia (PCP)
- No increased risk of candidiasis, aspergillosis, or other fungal infections
- No increased risk of cytomegalovirus (CMV), Epstein-Barr virus (EBV), or herpesvirus disease (except in the context of severe enteroviral encephalitis)
- No increased risk of intracellular mycobacterial infections
This normal response to fungal and intracellular pathogens is what clinically distinguishes XLA from SCID — and it is one reason misdiagnosis happens: a child who handles chickenpox normally but gets repeated pneumococcal pneumonias may seem to have "just bad luck" rather than a recognized immunodeficiency.
Vaccine Rules and Immunization
Vaccination in XLA requires specific precautions. The central rule is absolute: no live vaccines of any kind. However, the recommendation is nuanced depending on vaccine type and the patient's specific situation.
Contraindicated vaccines (live attenuated)
Live vaccines use weakened but replication-competent pathogens. In a patient without functional B cells and unable to mount an antibody response, these pathogens can cause the disease they were designed to prevent:
- Oral polio vaccine (OPV) — absolutely contraindicated; can cause vaccine-associated paralytic polio
- MMR (measles-mumps-rubella) — contraindicated; measles or mumps virus could replicate uncontrolled
- Varicella (chickenpox) vaccine — contraindicated
- MMRV combination vaccine — contraindicated
- Yellow fever vaccine — contraindicated
- Live attenuated nasal influenza vaccine — contraindicated; inactivated injectable influenza vaccine is used instead
- Rotavirus vaccine — contraindicated in established XLA diagnosis
- BCG (tuberculosis) — contraindicated
- Typhoid live oral vaccine — contraindicated
Safe vaccines (inactivated, subunit, conjugate, mRNA)
Non-live vaccines pose no risk of replication or disease. However, patients with XLA cannot mount antibody responses to vaccines on their own. This means vaccines do not provide direct protection in XLA patients the way they do in immunologically normal individuals. Despite this, vaccination of close household contacts and caregivers — the cocoon strategy — is the usual practice because it reduces the chance of introducing pathogens into the patient's environment.
- Inactivated influenza vaccine — safe to administer; will not create protective antibodies in the patient but may prime residual immune cells
- Inactivated poliovirus vaccine (IPV) — safe; used instead of OPV
- Pneumococcal conjugate and polysaccharide vaccines — safe but will not generate protective antibody titers; immunoglobulin replacement provides the necessary anti-pneumococcal antibodies
- COVID-19 mRNA vaccines — safe; immunogenicity is markedly reduced in XLA but household contact vaccination is important
The household contact rule
The usual practice is for family members and close contacts to be up to date on all standard vaccines — including MMR, varicella, and annual influenza — using live vaccines where these are the standard of care for normal individuals. The XLA patient cannot receive these vaccines but benefits enormously from herd protection if those around them are vaccinated. The one exception is oral polio vaccine: if OPV were still in routine use, household contacts would receive IPV instead, as OPV viruses shed in stool and could be transmitted to the immunocompromised patient.
Treatment: Lifelong Immunoglobulin Replacement
The cornerstone of XLA management is immunoglobulin replacement therapy (IgRT) — supplying the missing antibodies from pooled donor plasma. For almost all patients this treatment is lifelong, supplying immunoglobulin G throughout the patient's life.
Stem cell transplantation
Hematopoietic stem cell transplantation (HCT) has been used in only a few people with XLA because of its severe complications. A 2023 international survey collected 22 XLA patients who had received a transplant, most because of recurrent or life-threatening infection (16) or cancer (3). The new stem cells took in 21 (95%); 2-year overall survival was 86% and event-free survival 77%, and 89% had stopped immunoglobulin replacement within 1 year. The survey authors conclude that transplantation "may be an effective and safe alternative treatment option" for XLA patients for whom it is indicated, ideally before organ damage develops. A 2025 review notes that it "has been successful in some XLA patients, but there are still few reports."
Forms of immunoglobulin replacement
Two major delivery routes are available:
- Intravenous immunoglobulin (IVIG) — administered every three to four weeks at doses of 400–600 mg/kg per infusion. Each infusion takes two to four hours and is given in a clinic, infusion center, or hospital. IVIG produces a peak serum immunoglobulin G followed by a gradual decline until the next infusion; the "trough" level just before the next infusion determines the patient's baseline protection.
- Subcutaneous immunoglobulin (SCIG) — administered weekly or biweekly through a small needle inserted into the subcutaneous fat, often self-infused at home. SCIG produces steadier immunoglobulin G levels without peaks and troughs, is associated with fewer systemic side effects, and increasingly preferred for its convenience and quality of life benefits. Some formulations (facilitated SCIG, fSCIG) can be given monthly at IVIG-like doses.
Target Immunoglobulin G trough levels
The goal is to maintain a pre-infusion (trough) immunoglobulin G level above 500–800 mg/dL. Many specialists now target higher troughs — above 800 mg/dL — particularly for patients with established lung disease, recurrent sinusitis, or chronic Pseudomonas colonization. Higher doses are associated with fewer breakthrough infections and slower progression of bronchiectasis. Trough levels are checked every three to six months in stable patients.
It is worth noting that commercial immunoglobulin products contain a broad spectrum of antibodies derived from thousands of donors — providing protection against the full range of circulating bacterial and viral pathogens encountered across that donor pool. Manufacturers test products extensively for bloodborne pathogen safety; no cases of human immunodeficiency virus (HIV), hepatitis B virus (HBV), or hepatitis C virus (HCV) transmission from modern IVIG products have been documented.
Antibiotic prophylaxis and management of acute infections
Some specialists add prophylactic antibiotics — typically amoxicillin or co-trimoxazole — for patients with recurrent sinopulmonary infections despite adequate immunoglobulin G troughs. Acute bacterial infections are treated promptly with antibiotics, guided by culture and sensitivity testing because Pseudomonas and Staphylococcus strains may be resistant.
BTK inhibitors: an important contraindication
Ibrutinib, zanubrutinib, and other BTK inhibitors are widely used in B-cell malignancies (CLL, mantle cell lymphoma). These drugs work by blocking BTK activity — the opposite of what a patient with XLA needs. BTK inhibitors are absolutely contraindicated in XLA: they would further suppress what little residual BTK activity may exist and worsen B-cell signaling. This contraindication is clinically relevant because an XLA patient who later develops a B-cell lymphoma (a recognized long-term risk) could not safely receive standard BTK inhibitor–based chemotherapy regimens.
Gene therapy
Experimental gene therapy approaches for XLA are in early-stage development, aiming to correct the BTK mutation in autologous hematopoietic stem cells. Unlike SCID, where gene therapy has been successfully translated to practice, XLA gene therapy faces additional challenges because BTK requires precisely regulated, lineage-specific expression. Clinical trials are underway as of the mid-2020s but results are not yet mature.
Complications and Long-Term Outlook
The prognosis for XLA has been transformed by immunoglobulin replacement: with adequate treatment initiated early, most patients survive into adulthood and lead productive lives. However, two major long-term complications continue to affect quality of life and, in some patients, survival.
Chronic lung disease and bronchiectasis
Even with adequate immunoglobulin G replacement, recurrent lower respiratory tract infections — especially in the years before diagnosis and in patients with suboptimal trough immunoglobulin G levels — lead to progressive airway damage. Bronchiectasis (permanent, abnormal dilation and scarring of the bronchi) develops in a substantial proportion of adult XLA patients. It manifests as a daily productive cough, recurrent exacerbations, and progressive decline in FEV1 on spirometry.
Management mirrors bronchiectasis from other causes: airway clearance techniques (chest physiotherapy, oscillating positive expiratory pressure devices), optimized antibiotic therapy during exacerbations, and — in Pseudomonas-colonized patients — rotational antibiotic regimens or inhaled antibiotics to suppress bacterial burden. Regular pulmonary function testing (at least annually) and high-resolution computed tomography (CT) imaging every few years are commonly used for long-term monitoring.
Chronic enteroviral meningoencephalitis
As described in the Infections section, echoviruses and coxsackieviruses can establish persistent central nervous system infection in XLA patients. The classic syndrome involves a slow, progressive encephalopathy combined with a dermatomyositis-like inflammatory myopathy and occasionally chronic hepatitis. Diagnosis is confirmed by polymerase chain reaction (PCR) of cerebrospinal fluid (enteroviral RNA). There is no proven effective antiviral therapy: intravenous immunoglobulin (including intrathecal administration) stabilizes some patients but rarely achieves viral clearance. Pleconaril, an experimental enteroviral antiviral, has been used with limited success in compassionate-use settings. This complication is now much less common because higher immunoglobulin G troughs from modern IVIG/SCIG dosing provide substantially better protection against central nervous system enteroviral invasion.
Autoimmune and inflammatory complications
Paradoxically, despite the absence of B cells and antibodies, XLA patients have an elevated risk of certain autoimmune and inflammatory conditions:
- Aseptic (inflammatory) arthritis — may be mediated by mycoplasma or enterovirus rather than autoantibodies; responds to appropriate antimicrobial therapy and immunoglobulin optimization
- Neutropenia — some patients develop autoimmune neutropenia that can further increase infection risk; typically responds to higher-dose IVIG
- Inflammatory bowel disease–like enteropathy — chronic diarrhea and intestinal inflammation resembling Crohn's disease has been reported; mechanism poorly understood
Malignancy risk
Data from the US XLA registry suggest a modestly elevated risk of B-cell lymphoma compared with the general population, though the absolute risk remains low. Whether this represents a direct consequence of BTK deficiency, chronic immune stimulation, or other factors is unclear. Age-appropriate cancer screening is part of usual long-term follow-up.
Overall life expectancy
With modern immunoglobulin replacement and proactive pulmonary management, the majority of XLA patients now survive into middle age and beyond. Early series (pre-IVIG era) reported high mortality from pneumococcal meningitis and enteroviral encephalitis. Contemporary cohorts show that complications are preventable rather than inevitable — the key variables are the age at diagnosis, the quality of immunoglobulin G trough maintenance, and the cumulative burden of lung damage sustained before therapy began.
A 2025 international study looked at 48 people with XLA aged 55 or older. Persistent lower-airway infections were reported in 83.3%, long-term lung disease in 72.9% and gut or liver disorders in 47.9%. Even so, 80.5% of those still living reported good everyday function. People whose BTK mutation was a missense type, where some BTK protein is often still made, had lower death rates and better lung function than those with other mutation types.
Family Implications: Carrier Detection
XLA follows X-linked recessive inheritance, which has specific and important implications for the entire family — not just the affected boy.
How XLA is inherited
The BTK gene is located on the X chromosome. Males (XY) have only one copy; a single mutated BTK allele causes full disease. Females (XX) have two copies; a mutation in one allele is compensated by the normal allele on the other X chromosome. Carrier females are clinically unaffected: their lymphocytes preferentially use the normal X chromosome (a process called skewed X-inactivation), meaning they develop adequate numbers of functional B cells and produce normal immunoglobulin levels.
Recurrence risk
- A carrier mother has a 50% chance with each pregnancy of passing the mutated BTK allele: sons who inherit it will have XLA; daughters who inherit it will be carriers
- The father of an affected boy does not carry the mutation (unless there is a de novo mutation in the mother or son)
- Sisters of an affected boy have a 50% chance of being carriers
- Maternal aunts and their children may also carry the mutation
- Approximately one-third of XLA cases represent de novo mutations — new mutations arising spontaneously in the mother's germline or the affected boy himself. In these families, the recurrence risk for subsequent children is lower.
Carrier testing
Once the specific BTK mutation in the affected family member is known, targeted DNA sequencing can confirm or exclude carrier status in any female relative with certainty. Carrier testing is straightforward and reliable. It is particularly important for sisters of affected boys who are approaching reproductive age, as it enables them to make informed decisions about family planning. Protein-based BTK monocyte testing (flow cytometry) is not reliable for carrier detection — the normal X chromosome provides sufficient BTK expression to produce normal monocyte staining in most carriers.
Prenatal and preimplantation genetic diagnosis
Families with a known BTK mutation have several options for future pregnancies:
- Prenatal diagnosis — chorionic villus sampling (CVS) at 10–12 weeks or amniocentesis at 15–20 weeks can test fetal DNA for the BTK mutation, enabling informed decision-making
- Preimplantation genetic testing (PGT) — embryos created through IVF can be genetically screened before implantation, allowing families to select unaffected embryos
Genetic counseling from an experienced primary immunodeficiency specialist or a clinical geneticist is commonly offered to families with an XLA diagnosis.
Key Research Papers
- Bonilla FA et al. Practice parameter for the diagnosis and management of primary immunodeficiency. J Allergy Clin Immunol. 2015;136(5):1186-1205. — PubMed PMID: 26371839
- Vetrie D et al. The gene involved in X-linked agammaglobulinemia is a member of the src family of protein-tyrosine kinases. Nature. 1993. — PubMed PMID: 8380905
- Tsukada S et al. Deficient expression of a B cell cytoplasmic tyrosine kinase in human X-linked agammaglobulinemia. Cell. 1993;72(2):279-290. — PubMed PMID: 8425221
- Conley ME et al. Primary B cell immunodeficiencies: comparisons and contrasts. Annu Rev Immunol. 2009;27:199-227. — PubMed PMID: 19302039
- Winkelstein JA et al. X-linked agammaglobulinemia: report on a United States registry of 201 patients. Medicine (Baltimore). 2006. — PubMed PMID: 16862044
- Quartier P et al. Early and prolonged intravenous immunoglobulin replacement therapy in childhood agammaglobulinemia. J Pediatr. 1999. — PubMed PMID: 10228295
- Hermaszewski RA et al. Primary hypogammaglobulinaemia: a survey of clinical manifestations and complications. Q J Med. 1993;86(1):31-42. — PubMed PMID: 8438047
- Kainulainen L et al. Recurrent and persistent respiratory tract viral infections in patients with primary hypogammaglobulinemia. J Allergy Clin Immunol. 2010;126(1):120-126. — PubMed PMID: 20541246
- Nishimura A et al. An International Survey of Allogeneic Hematopoietic Cell Transplantation for X-Linked Agammaglobulinemia. J Clin Immunol. 2023;43(8):1827-1839. — PubMed PMID: 37454339
- Kanegane H et al. Revisiting X-linked agammaglobulinemia. J Hum Immun. 2025;1(1):e20250020. — PubMed PMID: 42170232
- Chin AT et al. Clinical and Molecular Characteristics of X-Linked Agammaglobulinemia Patients 55 Years or Older. J Allergy Clin Immunol Pract. 2025;13(10):2806-2816. — PubMed PMID: 40571245
Connections
- Immunology
- Common Variable Immunodeficiency
- Severe Combined Immunodeficiency
- Meningitis
- Leukopenia
- Pediatric Immunology
- Immunoglobulin Lab Tests
- Genetic Susceptibility to Vaccine Adverse Reactions — the antibody defect behind vaccine-derived poliovirus shedding