⚠ Evidence warning: Clinical trials or other evidence do not support the claim that guidelines may consider aspirin to prevent Barrett's esophagus progressing in patients already taking it for cardiovascular indications. This page keeps it as a report of what people, websites or other media say.
Barrett's Esophagus
Interactive Visualization Stomach Acid & proton pump inhibitors (PPIs) — run the proton pump Drive your stomach to pH 2, activate pepsin and free your B12 and iron — then take a proton pump inhibitor (PPI) and watch the pH climb while the nutrients stop being released. Launch →
Table of Contents
- How Barrett's Esophagus Changes the Gullet Lining
- Specialized Intestinal Metaplasia
- Causes and Risk Factors
- Symptoms
- Diagnosis and Prague Classification
- Dysplasia Grading
- Surveillance Intervals
- Treatment: Endoscopic and Medical
- Dietary and Lifestyle Approaches
- Prognosis and Cancer Risk
- How Barrett's Esophagus Can Be Found Without an Endoscopy
- Key Research Papers
- Connections
- Featured Videos
How Barrett's Esophagus Changes the Gullet Lining
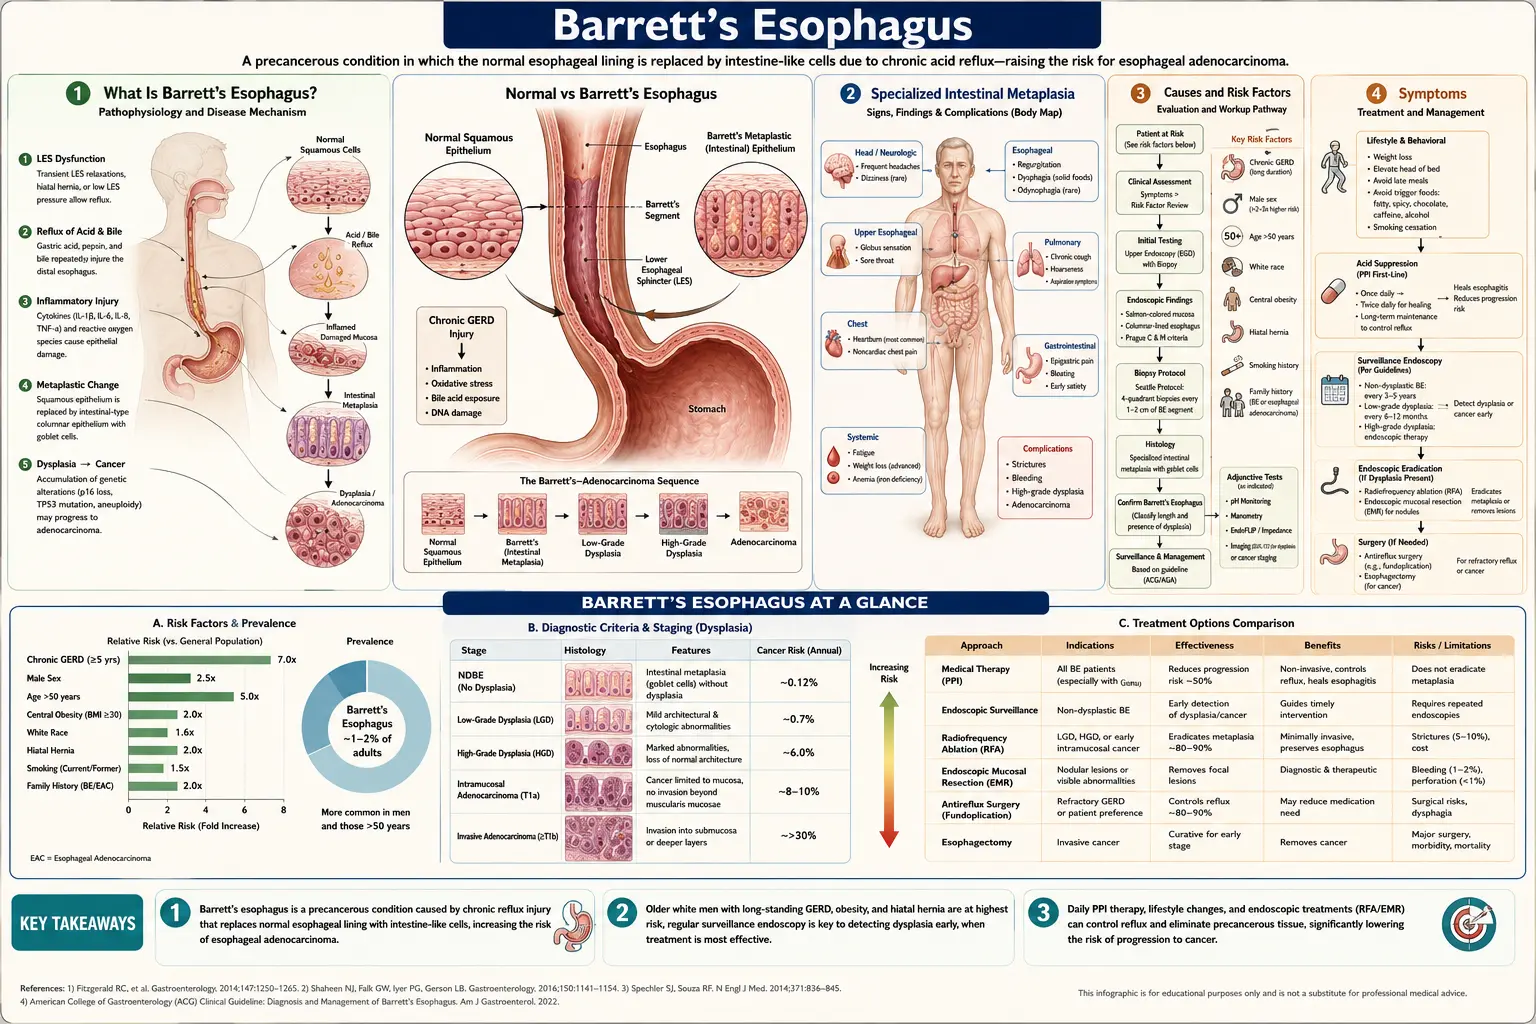
Barrett's esophagus is a condition in which the normal squamous epithelium lining the lower esophagus is replaced by columnar epithelium containing specialized intestinal metaplasia (SIM) — cells that resemble the lining of the small intestine. This transformation, called metaplasia, is the body's response to chronic acid and bile reflux injury. While the metaplastic cells are more resistant to acid damage than normal squamous cells, they carry a significantly elevated risk of progressing to esophageal adenocarcinoma.
Named after British surgeon Norman Barrett, who described the condition in 1950 (though early accounts date to Philip Rowland Allison in 1946), Barrett's esophagus affects an estimated 5–15% of patients with chronic gastroesophageal reflux disease (GERD). It is most common in middle-aged and older white men who have had heartburn symptoms for more than five years. In the United States, roughly 3.3 million adults have been diagnosed with the condition, though many more remain undiagnosed.
Barrett's esophagus matters primarily because it is the only known precursor lesion for esophageal adenocarcinoma — one of the fastest-rising cancers in the Western world. Finding Barrett's and treating dysplasia before it becomes invasive cancer is regarded as one of gastroenterology's main cancer-prevention opportunities.
Specialized Intestinal Metaplasia
The hallmark of Barrett's esophagus is specialized intestinal metaplasia (SIM) — columnar epithelium containing goblet cells. Goblet cells are mucus-secreting cells normally found in the small and large intestine; their presence in the esophagus is abnormal and defines true Barrett's metaplasia (as opposed to simple cardiac-type columnar epithelium, which lacks goblet cells and carries unclear malignant potential).
The molecular changes underlying Barrett's metaplasia involve shifts in transcription factor expression (CDX2, a master regulator of intestinal differentiation, becomes aberrantly expressed in the metaplastic cells) and epigenetic alterations that progressively accumulate over time. These molecular changes prime the cells for the additional mutations — particularly in TP53 and cell-cycle regulators — that drive progression to dysplasia and invasive cancer.
The extent of Barrett's segment is measured by the Prague C&M classification, introduced in 2006 and now standard worldwide. "C" refers to the circumferential extent of visible metaplastic mucosa (in centimeters above the gastroesophageal junction), and "M" refers to the maximum extent (including any tongues or islands extending further). For example, C3M5 indicates 3 cm of circumferential Barrett's with a maximum extent of 5 cm. Longer segments generally carry higher cancer risk, though short-segment Barrett's (C0M<3) is more common and causes the majority of cancers in absolute numbers.
Causes and Risk Factors
- Chronic gastroesophageal reflux disease — the dominant risk factor; weekly heartburn for 5+ years confers a 3–4-fold increased risk of Barrett's compared to individuals without gastroesophageal reflux disease. Both acid and bile components of reflux are injurious.
- Male sex — men are 2–3 times more likely to develop Barrett's than women with equivalent gastroesophageal reflux disease severity. The reason is not fully understood; hormonal differences (estrogen may be protective) and differences in bile composition have been proposed.
- Age over 50 — Barrett's is uncommon before age 40; peak diagnosis is in the 60s.
- Obesity, especially central adiposity — visceral fat increases intra-abdominal pressure, promotes hiatal hernia, and independently drives adipokine signaling that may promote metaplasia.
- White ethnicity — Barrett's and esophageal adenocarcinoma are markedly more common in non-Hispanic whites than in Black, Hispanic, or Asian populations.
- Cigarette smoking — doubles the risk; smoking impairs lower esophageal sphincter pressure and promotes mucosal injury.
- Hiatal hernia — allows the gastroesophageal junction to ride above the diaphragmatic crura, impairing the natural anti-reflux barrier.
- Family history — familial Barrett's esophagus or esophageal adenocarcinoma increases risk 2–3-fold, suggesting genetic susceptibility loci.
- Possible protective factors — aspirin and other nonsteroidal anti-inflammatory drugs (NSAIDs), H. pylori infection (paradoxically, H. pylori reduces gastroesophageal reflux disease by decreasing acid secretion), and high intake of fruits and vegetables have all been associated with reduced Barrett's risk in observational data.
Symptoms
Barrett's esophagus itself causes no unique symptoms. Most patients present with the same symptoms as gastroesophageal reflux disease:
- Heartburn — burning sensation in the chest, typically after eating or when lying down
- Regurgitation — sour or bitter fluid rising into the throat
- Dysphagia — difficulty swallowing, particularly if a stricture has developed
- Chest pain — can feel like heart pain; chest pain is a warning sign that hospitals treat as urgent until a heart cause has been ruled out
- Chronic cough, hoarseness, or laryngitis — from laryngopharyngeal reflux
Paradoxically, some patients with Barrett's have less heartburn than those with uncomplicated gastroesophageal reflux disease, possibly because the columnar mucosa is less sensitive to acid than squamous epithelium. This means absence of heartburn does not rule out Barrett's, and may explain why many cases are diagnosed only when adenocarcinoma has already developed.
Diagnosis and Prague Classification
Diagnosis requires both endoscopic visualization and confirmatory biopsy.
- Upper endoscopy (EGD) — the endoscopist identifies salmon-colored or pinkish columnar-appearing mucosa extending proximally from the gastroesophageal junction (GEJ), which normally presents as a sharp squamocolumnar junction (Z-line or SCJ). Suspicion is raised when the Z-line is irregular or when tongue-like projections extend above the GEJ.
- Prague C&M classification — the endoscopist measures and documents the circumferential (C) and maximal (M) extent of Barrett's mucosa in centimeters, using the GEJ and the diaphragmatic hiatus as landmarks. This standardized description facilitates communication between endoscopists and tracking of segment changes over time.
- Biopsy using the Seattle protocol — four-quadrant biopsies taken every 1–2 cm along the length of the Barrett's segment, plus targeted biopsies of any visible lesions, nodules, or mucosal irregularities. Random biopsies are critical because dysplasia is patchy and invisible to standard white-light endoscopy.
- Histopathology — the pathologist confirms the presence of goblet cells (SIM) and grades dysplasia: no dysplasia, indefinite for dysplasia, low-grade dysplasia (LGD), or high-grade dysplasia (HGD). Dysplasia grading is usually confirmed by a second expert gastrointestinal (GI) pathologist, because agreement between pathologists is low (high interobserver variability).
- Advanced imaging adjuncts — narrow-band imaging (NBI), chromoendoscopy with acetic acid spray, and confocal laser endomicroscopy can improve dysplasia detection beyond standard white-light endoscopy and are increasingly used in high-volume Barrett's centers.
Dysplasia Grading
The natural history of Barrett's esophagus follows a progression from metaplasia through increasing grades of dysplasia to invasive adenocarcinoma. Dysplasia grade is the single most important predictor of cancer risk and determines management:
- Non-dysplastic Barrett's (NDBE) — goblet cells present but no architectural or nuclear atypia. Annual cancer risk approximately 0.1–0.3%. The majority of Barrett's patients remain at this stage indefinitely.
- Indefinite for dysplasia — reactive atypia that cannot be confidently graded due to inflammation, ulceration, or poor tissue orientation. Usual practice is stronger acid suppression and a repeat endoscopy in 3–6 months.
- Low-grade dysplasia (LGD) — mild nuclear enlargement and crowding with preserved architecture. Annual cancer risk approximately 0.5–1.5% per year. Management has shifted toward endoscopic eradication for confirmed LGD due to high rates of under-staging and progression.
- High-grade dysplasia (HGD) — marked nuclear atypia with glandular architectural disarray. Annual cancer risk without treatment approximately 6–10% per year. Essentially all current guidelines recommend endoscopic eradication therapy for confirmed HGD.
Surveillance Intervals
Surveillance endoscopy aims to detect dysplasia and early cancer at treatable stages. ACG, BSG, and AGA guidelines have generally recommended:
- Non-dysplastic Barrett's — repeat endoscopy every 3–5 years (exact interval depends on segment length; shorter for long-segment Barrett's >3 cm)
- Indefinite for dysplasia — proton pump inhibitor therapy optimized, repeat in 3–6 months
- Low-grade dysplasia — confirmed by a second pathologist; either endoscopic eradication or enhanced surveillance every 6–12 months if eradication is declined
- High-grade dysplasia — endoscopic eradication therapy; post-treatment surveillance every 3 months for the first year, then annually if complete eradication is achieved
The 2022 update of the American College of Gastroenterology (ACG) guideline changed several of these points: it accepts nonendoscopic methods for screening, allows longer (liberalized) surveillance intervals for short-segment Barrett's, recommends endoscopic eradication therapy for Barrett's with high-grade and with low-grade dysplasia, proposes structured surveillance intervals after successful ablation based on the original degree of dysplasia, and sets volume criteria for centers that perform endoscopic therapy. It could not make recommendations on chemoprevention or on biomarkers in routine practice because of insufficient data.
The benefit of surveillance is greatest for patients with confirmed dysplasia; for non-dysplastic Barrett's, the absolute cancer reduction from surveillance remains debated, and decisions are often made with the patient, weighing health and preferences.
The first randomized trial of surveillance, BOSS (3,453 people with Barrett's at 109 UK centers, median follow-up 12.8 years), compared endoscopy every 2 years with endoscopy offered only when symptoms appeared. It found no difference in overall survival (333 vs. 356 deaths; hazard ratio 0.95, 95% CI 0.82–1.10), in cancer-specific survival (hazard ratio 1.01), in time to diagnosis of esophageal adenocarcinoma (40 vs. 31 people diagnosed), or in cancer stage at diagnosis. The authors concluded that surveillance did not improve overall or cancer-specific survival and that endoscopy only when needed may be a safe alternative for low-risk patients.
Treatment: Endoscopic and Medical
Endoscopic Eradication Therapy (EET)
Endoscopic therapies have largely replaced surgery for dysplastic Barrett's and are the standard of care for HGD and increasingly for confirmed LGD:
- Radiofrequency ablation (RFA) — the most widely used and best-studied ablative modality. A balloon-based or focal catheter delivers controlled radiofrequency energy to destroy the Barrett's epithelium to a depth of ~0.5–1 mm. Multiple sessions (typically 2–3) are needed. Complete eradication of intestinal metaplasia (CE-IM) is achieved in ~77–90% of patients. The squamocolumnar junction regrows with native squamous epithelium, provided acid suppression is maintained with high-dose proton pump inhibitors.
- Endoscopic mucosal resection (EMR) — visible lesions, nodules, or areas suspicious for submucosal invasion are removed by EMR first, before ablation, to obtain full histological staging. A saline cushion is injected submucosally, the lesion is suctioned into a cap, and a snare is used to resect it.
- Endoscopic submucosal dissection (ESD) — allows en-bloc resection of larger lesions for more accurate staging; technically demanding but increasing in use at expert centers.
- Cryotherapy — liquid nitrogen or carbon dioxide spray freezes and destroys the Barrett's epithelium; an alternative for patients in whom RFA has failed or for circumferential ablation in very long segments.
- Photodynamic therapy (PDT) — now largely replaced by RFA due to higher stricture rates and photosensitivity side effects.
Medical Therapy: Proton Pump Inhibitors and Chemoprevention
- High-dose proton pump inhibitors — twice-daily proton pump inhibitor therapy (e.g., omeprazole 40 mg twice daily) is standard before and after endoscopic eradication to maximize acid suppression and support squamous re-epithelialization. Proton pump inhibitors also appear to reduce cancer progression risk in observational studies, though no randomized trial has definitively confirmed a chemoprevention benefit.
- Aspirin and nonsteroidal anti-inflammatory drugs — multiple observational studies have linked these drugs with less progression. The AspECT trial (2018; 2,557 people with Barrett's in the UK and Canada, median follow-up 8.9 years) measured a combined endpoint: time to death from any cause, esophageal adenocarcinoma or high-grade dysplasia. High-dose esomeprazole (40 mg twice daily) did better than low-dose (20 mg once daily) (time ratio 1.27, p = 0.038). Aspirin (300 mg a day in the UK, 325 mg in Canada) was not significantly better than no aspirin (time ratio 1.24, p = 0.068), although it was when people using other nonsteroidal anti-inflammatory drugs were censored (time ratio 1.29, p = 0.043). High-dose esomeprazole plus aspirin had the strongest effect compared with low-dose esomeprazole without aspirin (time ratio 1.59, p = 0.0068). The numbers needed to treat were 34 for the proton pump inhibitor and 43 for aspirin, and 1% of participants reported serious side effects related to the study treatment. The absolute benefit was modest; current guidelines do not universally recommend aspirin for chemoprevention but may consider it in patients already taking it for cardiovascular indications. The 2022 ACG guideline states that it could not make recommendations on chemoprevention because of insufficient data.
- Surgical fundoplication — laparoscopic Nissen fundoplication corrects gastroesophageal reflux disease mechanically; it may reduce acid reflux more completely than proton pump inhibitors but has not been shown to cause regression of established Barrett's or reduce cancer risk in randomized controlled trials.
Dietary and Lifestyle Approaches
- Weight loss — even modest weight reduction (5–10% of body weight) reduces intra-abdominal pressure and reflux frequency; the most impactful lifestyle change for obese patients with Barrett's.
- Raising the head of the bed 6–8 inches — reduces nocturnal acid exposure, which is particularly relevant because esophageal acid clearance is slowest during sleep. Using a foam wedge under the mattress is more effective than extra pillows.
- Meal timing — usual reflux guidance describes finishing meals at least 2–3 hours before lying down.
- Dietary triggers — alcohol, fatty foods, chocolate, peppermint, coffee, and citrus relax the lower esophageal sphincter or directly irritate the mucosa. Individual tolerance varies; a food-symptom diary helps identify personal triggers.
- Fruits, vegetables, and fiber — epidemiological data consistently associate Mediterranean-style diets with reduced Barrett's progression risk, likely through antioxidant and anti-inflammatory effects.
- Tight clothing and prolonged bending — increase intra-abdominal pressure and promotes reflux episodes.
- Smoking — tobacco use is associated with faster Barrett's progression in several cohort studies.
Prognosis and Cancer Risk
The overall risk of a patient with non-dysplastic Barrett's esophagus developing esophageal adenocarcinoma is approximately 0.1–0.3% per year — considerably lower than historical estimates of 0.5% per year that were derived from referral-center populations. This means that for most Barrett's patients, the condition is managed by surveillance rather than aggressive intervention, and the majority will never develop cancer.
Risk stratification is important:
- Longer segment (C>3 cm) carries 5-fold higher cancer risk than short-segment Barrett's.
- Dysplasia grade is the strongest predictor: LGD raises annual risk to ~0.5–1.5%, HGD to ~6–10%.
- Biomarkers under study — TP53 mutation in biopsies, DNA ploidy analysis, and methylation signatures may help identify which non-dysplastic Barrett's patients are at higher risk, but none are yet in routine clinical use.
Esophageal adenocarcinoma detected within a Barrett's surveillance program has a substantially better prognosis than cancer discovered symptomatically — 5-year survival rates are 50–60% for surveillance-detected stage I cancers vs. 15–20% overall. This has been the rationale for surveillance programs despite the relatively low absolute cancer incidence; the first randomized trial of surveillance (BOSS, 2025), however, found no improvement in overall or cancer-specific survival (see Surveillance Intervals).
How Barrett's Esophagus Can Be Found Without an Endoscopy
A non-endoscopic test, the Cytosponge-TFF3 test, uses a small sponge device on a thread that the person swallows; it collects cells from the lining of the gullet, which are tested for the marker trefoil factor 3 (TFF3). People with a positive result are then offered an endoscopy.
In the BEST3 trial in 109 general practice clinics in England, 13,514 people aged 50 or older who had taken acid-suppressing medicine for reflux for more than 6 months were randomized to usual care or to usual care plus an offer of the test. Over about 12 months, Barrett's esophagus was diagnosed in 140 of 6,834 people in the test group versus 13 of 6,388 with usual care (rate ratio 10.6). Nine people in the test group were found to have dysplasia (4) or stage I cancer (5), against none in the usual-care group. Of 1,750 people who had the procedure, 1,654 (95%) swallowed the device successfully and produced a sample; a sore throat (4%) was the commonest side effect, and in one person the sponge came off its thread and was removed by endoscopy. The authors note that the approach leads to additional endoscopies, with some false-positive results.
The 2022 ACG guideline now includes nonendoscopic methods among acceptable ways to screen for Barrett's esophagus.
Key Research Papers
- Barrett NR. Chronic peptic ulcer of the oesophagus and oesophagitis. Br J Surg. 1950;38(150):175-182. — PubMed PMID: 14791960 · doi:10.1002/bjs.18003815005
- Shaheen NJ, Falk GW, Iyer PG, Souza RF, Yadlapati RH, Sauer BG, Wani S. Diagnosis and Management of Barrett's Esophagus: An Updated ACG Guideline. Am J Gastroenterol. 2022;117(4):559-587. — PubMed PMID: 35354777 · doi:10.14309/ajg.0000000000001680
- Sharma P, Dent J, Armstrong D, et al. The development and validation of an endoscopic grading system for Barrett's esophagus: the Prague C & M criteria. Gastroenterology. 2006;131(5):1392-1399. — PubMed PMID: 17101315 · doi:10.1053/j.gastro.2006.08.032
- Shaheen NJ, Sharma P, Overholt BF, et al. Radiofrequency ablation in Barrett's esophagus with dysplasia (AIM Dysplasia trial). N Engl J Med. 2009;360(22):2277-2288. — PubMed PMID: 19474425 · doi:10.1056/NEJMoa0808145
- Phoa KN, van Vilsteren FG, Weusten BL, et al. Radiofrequency ablation vs endoscopic surveillance for patients with Barrett esophagus and low-grade dysplasia (SURF trial). JAMA. 2014;311(12):1209-1217. — PubMed PMID: 24668102 · doi:10.1001/jama.2014.2511
- Jankowski JAZ, de Caestecker J, Love SB, et al. Esomeprazole and aspirin in Barrett's oesophagus (AspECT): a randomised factorial trial. Lancet. 2018;392(10145):400-408. — PubMed PMID: 30057104 · doi:10.1016/S0140-6736(18)31388-6
- Spechler SJ, Sharma P, Souza RF, et al. American Gastroenterological Association technical review on the management of Barrett's esophagus. Gastroenterology. 2011;140(3):e18-52. — PubMed PMID: 21376939 · doi:10.1053/j.gastro.2011.01.031
- Souza RF, Krishnan K, Spechler SJ. Acid, bile, and CDX: the ABCs of making Barrett's metaplasia. Am J Physiol Gastrointest Liver Physiol. 2008;295(2):G211-218. — PubMed PMID: 18556417 · doi:10.1152/ajpgi.90250.2008
- Hvid-Jensen F, Pedersen L, Drewes AM, et al. Incidence of adenocarcinoma among patients with Barrett's esophagus. N Engl J Med. 2011;365(15):1375-1383. — PubMed PMID: 21995385 · doi:10.1056/NEJMoa1103042
- Fitzgerald RC, di Pietro M, Ragunath K, et al. British Society of Gastroenterology guidelines on the diagnosis and management of Barrett's oesophagus. Gut. 2014;63(1):7-42. — PubMed PMID: 24165758 · doi:10.1136/gutjnl-2013-305372
- Wani S, Falk GW, Post J, et al. Risk factors for progression of low-grade dysplasia in patients with Barrett's esophagus. Gastroenterology. 2011;141(4):1179-1186. — PubMed PMID: 21723218 · doi:10.1053/j.gastro.2011.06.055
- Corley DA, Mehtani K, Quesenberry C, et al. Impact of endoscopic surveillance on mortality from Barrett's esophagus-associated esophageal adenocarcinomas. Gastroenterology. 2013;145(2):312-319. — PubMed PMID: 23673354 · doi:10.1053/j.gastro.2013.05.004
- Old O, Jankowski J, Attwood S, et al. Barrett's Oesophagus Surveillance Versus Endoscopy at Need Study (BOSS): A Randomized Controlled Trial. Gastroenterology. 2025;169(6):1233-1243.e8. — PubMed PMID: 40180292 · doi:10.1053/j.gastro.2025.03.021
- Fitzgerald RC, di Pietro M, O'Donovan M, et al. Cytosponge-trefoil factor 3 versus usual care to identify Barrett's oesophagus in a primary care setting: a multicentre, pragmatic, randomised controlled trial. Lancet. 2020;396(10247):333-344. — PubMed PMID: 32738955 · doi:10.1016/S0140-6736(20)31099-0
PubMed Topic Searches
Curated PubMed topic searches of peer-reviewed literature on Barrett's esophagus. Each link opens a live PubMed query so you always see the most current studies.
- PubMed: Barrett's RFA ablation
- PubMed: Barrett's dysplasia progression
- PubMed: Barrett's surveillance guidelines
- PubMed: Specialized intestinal metaplasia
- PubMed: Esophageal adenocarcinoma Barrett's risk
- PubMed: Prague C&M criteria
- PubMed: PPI chemoprevention Barrett's
- PubMed: EMR for Barrett's esophagus
- PubMed: GERD obesity Barrett's risk
- PubMed: Aspirin Barrett's chemoprevention
Connections
- Gastroenterology
- Stomach Acid, pH & the Proton Pump Inhibitor Trade-off — interactive animation
- Gastroesophageal Reflux Disease
- Gastritis
- Peptic Ulcer Disease
- Pancreatitis
- Gallbladder Disease
- Appendicitis
- Fatty Liver Disease (Non-Alcoholic Fatty Liver Disease/Metabolic Dysfunction-Associated Steatotic Liver Disease)
- Celiac Disease
- Ulcerative Colitis
- Small Intestinal Bacterial Overgrowth
- Irritable Bowel Syndrome
- Vitamin C (antioxidant mucosal protection)
- Licorice Root (DGL)