Hearing Loss
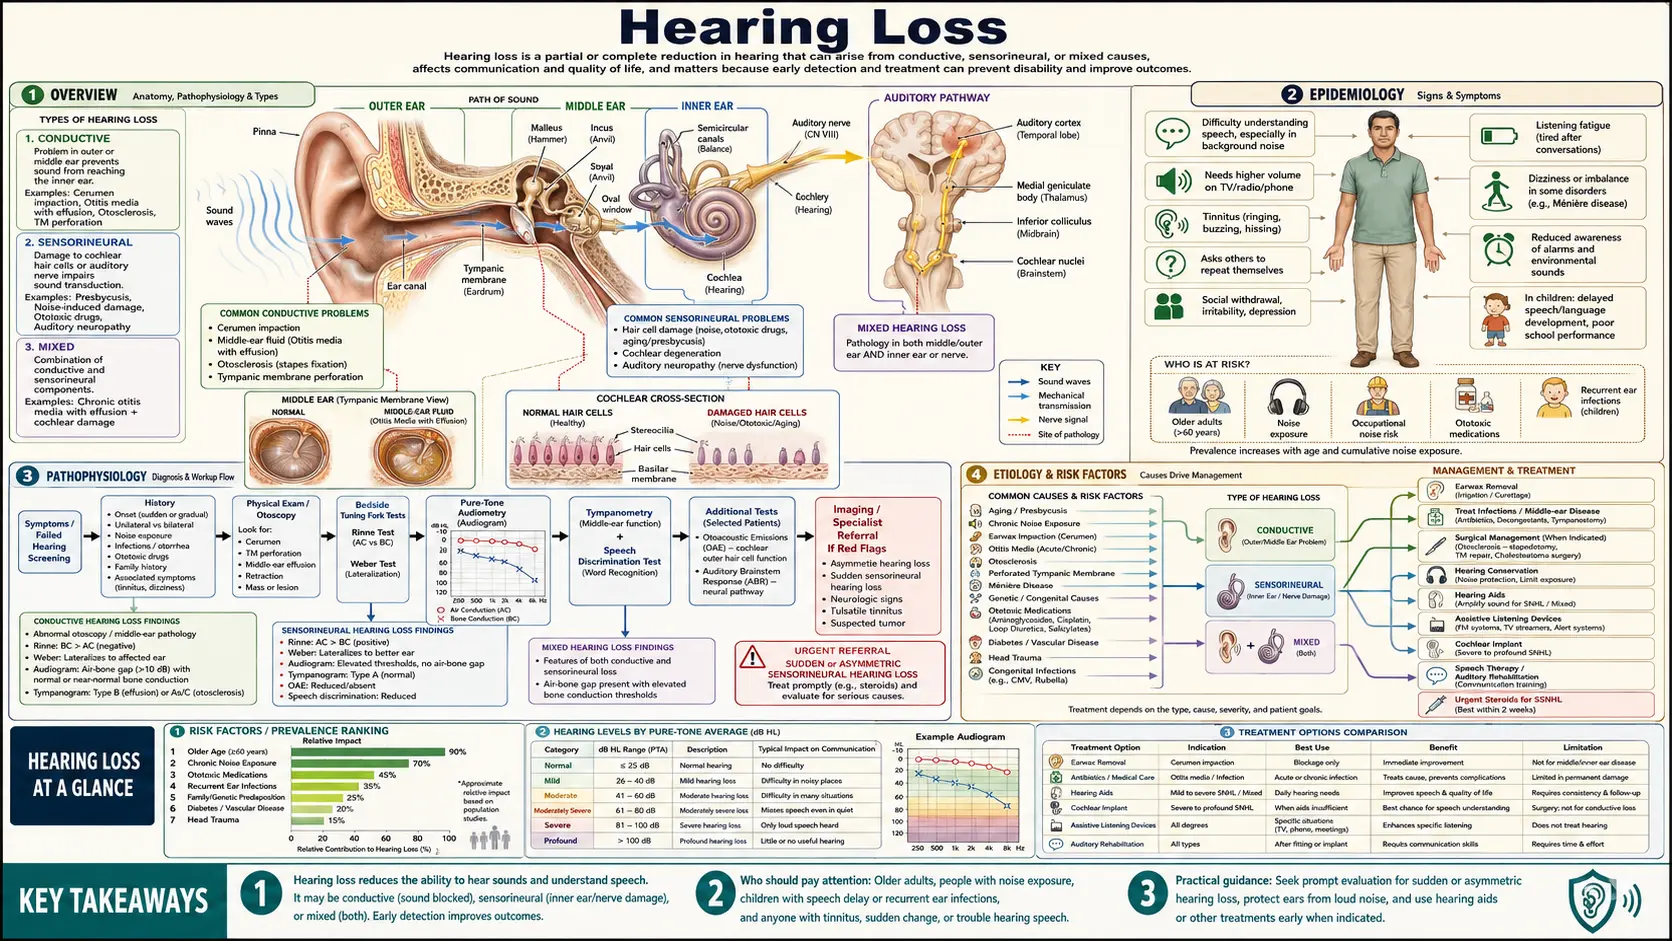
Table of Contents
1. Overview
Hearing loss is one of the most common chronic health conditions in the United States — roughly 15% of American adults report some trouble hearing, and among people over 75, more than half live with measurable hearing loss. Yet it is also one of the most under-treated conditions in all of medicine. People wait an average of 7 to 10 years between first noticing a problem and doing something about it, and during those years the costs quietly pile up: strained relationships, exhausting conversations, social withdrawal, and — as research over the past decade has made increasingly clear — a measurably higher risk of cognitive decline and dementia.
Hearing loss comes in three basic types, and understanding which one you have changes everything about what can be done:
- Conductive hearing loss — something is physically blocking or dampening sound on its way to the inner ear. Think of it as a plumbing problem: impacted earwax, fluid behind the eardrum, a perforated eardrum, or stiffened middle-ear bones (otosclerosis). Conductive loss is often fixable — sometimes in a single office visit.
- Sensorineural hearing loss — the sensory cells of the inner ear (the hair cells) or the auditory nerve itself are damaged. This is the most common type in adults, and it is usually permanent, because human hair cells do not grow back once they die. Age-related hearing loss and noise damage both fall in this category.
- Mixed hearing loss — a combination of both, such as an older adult with age-related inner-ear loss who also has a wax blockage.
The single most important fact on this page: sudden hearing loss in one ear is a medical emergency, not something to "wait out." There is a treatment window of roughly two weeks, and people routinely miss it because they assume the ear is just blocked with wax. That red flag is covered in detail in Clinical Presentation and Treatment below.
The good news in this article: hearing loss is more treatable, and treatment is more affordable, than it has ever been. Since the U.S. Food and Drug Administration's 2022 over-the-counter hearing aid rule, effective devices can be bought without a prescription for a fraction of the traditional price, cochlear implants are covered by Medicare for those who qualify, and a landmark 2023 randomized trial (ACHIEVE) found no overall effect on thinking skills but suggests that treating hearing loss might help protect the aging brain in people at higher risk.
2. Epidemiology
Hearing loss scales steeply with age. In US population data:
- About 15% of adults (roughly 37.5 million people) report at least some difficulty hearing.
- Approximately 1 in 3 adults aged 65–74 has hearing loss on formal testing.
- More than half of adults over 75 have hearing loss significant enough to affect daily communication.
- Men are nearly twice as likely as women to have hearing loss in midlife, partly reflecting occupational and recreational noise exposure.
Globally, the Global Burden of Disease Study estimated that about 1.57 billion people — one in five humans — had some degree of hearing loss in 2019, with over 400 million having loss severe enough to benefit from treatment. The number is projected to approach 2.5 billion by 2050 as populations age.
The treatment gap is the most striking statistic of all. Despite how common and how treatable hearing loss is, fewer than one in three US adults over 70 who could benefit from hearing aids has ever used them, and among adults aged 20–69 the figure drops to roughly one in six. Cost, stigma, denial ("everyone mumbles, my hearing is fine"), and the slow, painless nature of the loss all contribute. Hearing loss rarely hurts — which is exactly why it gets ignored.
3. Pathophysiology
To understand what goes wrong, it helps to follow a sound through the ear. Sound waves are funneled by the outer ear down the ear canal to the eardrum, which vibrates. Three tiny bones in the middle ear — the hammer, anvil, and stirrup (malleus, incus, stapes), the smallest bones in the human body — amplify that vibration and deliver it to the cochlea, a fluid-filled spiral the size of a pea. Inside the cochlea, about 15,000 hair cells convert fluid motion into electrical signals. Each hair cell is tuned to a particular pitch — high frequencies at the base of the spiral, low frequencies at the tip, laid out like a piano keyboard. The auditory nerve carries those signals to the brain, which does the real work of turning them into speech, music, and meaning.
Conductive loss is a failure of the delivery system: wax plugging the canal, fluid or infection behind the eardrum, a hole in the eardrum, or middle-ear bones that no longer move freely. Sound still reaches the cochlea, just muffled — like listening with an earplug in. Because the sensory machinery is intact, fixing the blockage usually restores hearing.
Sensorineural loss is a failure of the sensors themselves. Hair cells are exquisitely sensitive and they are irreplaceable: humans are born with all the cochlear hair cells we will ever have, and once they die they do not regenerate. (Birds and fish can regrow them; mammals lost that ability — which is why hair-cell regeneration is one of the hottest areas of hearing research.) Loud noise physically shears and overworks hair cells; aging, reduced blood flow, certain drugs, and genetics kill them more gradually. High-frequency hair cells, sitting at the base of the cochlea where every sound passes, take the most cumulative abuse — which is why high pitches almost always go first.
Research has also identified a subtler injury called cochlear synaptopathy, or "hidden hearing loss." Kujawa and Liberman showed in a 2009 study in mice that noise exposures once considered safe — because hearing thresholds recovered completely — left the hair cells intact but destroyed the connections between hair cells and the auditory nerve, followed by delayed degeneration of the nerve itself. Conventional threshold testing did not reveal this damage. The authors inferred that in people this loss "should add to difficulties hearing in noisy environments": the audiogram looks normal, but the person struggles to follow speech in noisy rooms. If you "pass" hearing tests yet drown in restaurant chatter, this may be part of the reason, and it is why researchers raise concern even about "temporary" ringing-and-muffled-hearing exposures.
4. Etiology and Risk Factors
Presbycusis (age-related hearing loss)
The most common cause in adults. Decades of cumulative wear — hair-cell loss, stiffening of cochlear structures, declining blood supply, and slower neural processing — produce a gradual, symmetric, high-frequency loss. It typically becomes noticeable in the 60s, though the underlying decline starts decades earlier. Genetics matter: presbycusis runs in families.
Noise-induced hearing loss
The most preventable cause. The National Institute for Occupational Safety and Health (the US occupational safety research agency) sets the safe exposure limit at 85 decibels averaged over an 8-hour day — and because the scale is logarithmic, every 3 dB increase cuts the safe time in half: 88 dB is safe for 4 hours, 94 dB for 1 hour, and 100 dB for only about 15 minutes. For perspective:
- Normal conversation: ~60 dB
- Lawn mower, heavy traffic: 85–90 dB
- Earbuds at maximum volume: roughly 100–110 dB
- Rock concert, nightclub, sporting event: 100–110+ dB
- Gunshot, firecracker at close range: 140–165 dB (instant damage possible from a single exposure)
On a three-hour concert at 105 dB the problem is obvious — a full safe daily dose can be exceeded in the first few minutes. The same applies to earbuds: streaming at full volume on a commute delivers concert-level doses daily. A commonly described habit is the 60/60 rule: volume at or below 60% and a break after 60 minutes. Modern smartphones can display headphone-level warnings and measure room noise. Ears that ring or sound muffled after an event have been injured, even if hearing "comes back" the next day (see hidden hearing loss above).
Earwax impaction
The most common reversible cause, and commonly the first thing ruled out. Earwax (cerumen) is normal and protective; problems arise when it gets packed against the eardrum — very often by the cotton swabs people use to "clean" their ears. Cotton swabs push more wax in than they remove, and professional guidelines explicitly recommend against putting them (or hairpins, or keys) in the ear canal. Ear candling is ineffective and dangerous. Safe options are covered under Treatment.
Ototoxic medications
Several important drugs can damage the inner ear, especially at high doses or in combination:
- Aminoglycoside antibiotics (gentamicin, tobramycin, amikacin) — used for serious infections; can permanently destroy hair cells, and some people carry a mitochondrial gene variant (m.1555A>G) that makes even normal doses dangerous.
- Cisplatin and carboplatin — platinum chemotherapy agents; cisplatin causes permanent hearing loss in a substantial fraction of patients, and hearing is commonly monitored during treatment.
- Loop diuretics (furosemide, especially intravenous (IV) at high doses) — usually temporary, but can be permanent when combined with other ototoxic drugs.
- High-dose aspirin and other salicylates — classically cause reversible hearing loss and ringing at very high doses; ordinary low-dose aspirin is not a concern.
Ringing, fullness, or a change in hearing are the reported early signs of inner-ear damage from these drugs — sometimes a dose or drug can be changed before damage becomes permanent.
Otosclerosis
An abnormal bone remodeling around the stapes (stirrup) bone that gradually freezes it in place, producing a progressive conductive loss, typically starting in a person's 20s–40s. It runs in families, is more common in women, and can worsen during pregnancy. It matters because it is surgically correctable (see Treatment).
Acoustic neuroma (vestibular schwannoma)
A benign, slow-growing tumor on the hearing-and-balance nerve. Rare, but it is the reason doctors take one-sided hearing loss or one-sided tinnitus seriously: asymmetric sensorineural loss warrants a magnetic resonance imaging (MRI) to rule it out.
Other contributors
Diabetes roughly doubles the odds of hearing loss, likely by damaging the cochlea's small blood vessels and nerves. Cardiovascular disease, hypertension, and smoking are all associated with worse hearing — the cochlea's hair cells depend on a rich blood supply from a single small artery, so what harms circulation harms hearing. Chronic middle-ear infections, head injury, Meniere's disease, and autoimmune inner-ear disease account for smaller shares.
5. Clinical Presentation
Gradual hearing loss announces itself through other people long before it shows up in a doctor's office. Classic early signs:
- The sense that "everyone mumbles" — you hear voices fine but can't make out the words. This is the signature of high-frequency loss: vowels (low-pitched, loud) come through, but the consonants that distinguish words — f, s, th, sh, t, k — are high-pitched and quiet, and they vanish first.
- Difficulty following conversation in restaurants and group settings, while one-on-one in a quiet room is fine.
- Trouble hearing women's and children's voices (higher-pitched) more than men's.
- TV volume creeping up; family complaining.
- Exhaustion after social events — straining to decode speech all evening is genuinely fatiguing ("listening fatigue").
- Ringing in the ears (tinnitus), which very frequently accompanies hearing loss.
Red flag: sudden hearing loss is an emergency
Losing hearing in one ear over minutes, hours, or a few days is a sign that hospitals and ear clinics treat as urgent. Waiting to see if it gets better can use up the treatment window. Sudden sensorineural hearing loss typically strikes one ear, sometimes noticed on waking, often with ringing or fullness in the ear, sometimes with dizziness. And here is the trap: it feels exactly like a blocked ear. Most people assume it is wax or congestion from a cold, try drops or yawning, and wait. Weeks later, when it has not cleared, the treatment window has closed.
The evidence-based treatment is corticosteroids (oral or injected through the eardrum), ideally started within days and generally within two weeks of onset. The American Academy of Otolaryngology-Head and Neck Surgery clinical practice guideline emphasizes prompt diagnosis and offering steroids early, because the chance of recovering hearing falls as time passes. A simple in-office tuning-fork test, or urgent audiogram, distinguishes a harmless conductive blockage from true sensorineural loss in minutes. The rule of thumb for patients is blunt: a suddenly deaf ear is a stroke-level urgency for your hearing. Same day or next day is the usual urgency — at an urgent-care visit, an ear, nose and throat (ENT) clinic, or an emergency department. The worst outcome of being wrong is mild embarrassment about earwax; the worst outcome of waiting is permanent deafness in that ear.
6. Diagnosis
Diagnosis starts with an ear exam (otoscopy) to rule out wax, infection, and eardrum problems, followed by formal testing:
- Pure-tone audiometry — the booth-and-headphones test. It measures the softest sound you can hear at each frequency, in each ear, by both air conduction (headphones) and bone conduction (a vibrator on the skull that bypasses the middle ear). The air–bone gap is what separates conductive from sensorineural loss.
- Speech testing — how well you repeat words at comfortable volume; this measures clarity, not just loudness.
- Tympanometry — measures eardrum movement to detect fluid, perforation, or stiff middle-ear bones.
- Magnetic resonance imaging — ordered when loss is clearly asymmetric, to rule out acoustic neuroma.
How to read your audiogram
You will be handed a graph. It is worth two minutes to understand it. The horizontal axis is frequency (pitch), from 250 Hz (low, like a tuba) on the left to 8,000 Hz (high, like birdsong) on the right. The vertical axis is loudness in decibels (dB HL) — but plotted upside-down: 0 dB at the top means you hear the faintest sounds, and the further down the marks go, the louder a sound had to be before you detected it. Right ear is usually plotted as red circles, left ear as blue X's.
- Normal: thresholds at 25 dB or better
- Mild loss: 26–40 dB (you miss soft speech and whispers)
- Moderate: 41–55 dB (normal conversation becomes hard)
- Moderately severe: 56–70 dB
- Severe: 71–90 dB (only loud speech, close up)
- Profound: over 90 dB
Audiologists often overlay the "speech banana" — a banana-shaped zone on the audiogram showing where the sounds of ordinary speech live. Vowels sit in the low-frequency, louder part; consonants like s, f, th sit in the high-frequency, quiet tail. When your threshold line cuts through the banana, you can see exactly which speech sounds you are losing — and why "I hear you, but I can't understand you" is the universal complaint. The typical presbycusis audiogram is a downward slope: normal on the left (low pitch), falling off steeply to the right (high pitch). A noise-damage audiogram often shows a characteristic notch at 4,000 Hz.
7. Treatment
Earwax: the easy win
If wax impaction is the cause, removal restores hearing immediately. Safe approaches: softening drops (mineral oil, carbamide peroxide, or plain water/saline) for a few days, followed if needed by gentle irrigation or manual removal by a clinician. Professional guidelines recommend against cotton swabs inside the canal and against ear candles, and aggressive home irrigation carries added risk for anyone who has had a perforated eardrum or ear surgery. People who wear hearing aids or earplugs daily tend to re-impact and benefit from routine cleanings once or twice a year.
Sudden sensorineural hearing loss: steroids, fast
As emphasized above, sudden sensorineural hearing loss is treated with corticosteroids — a high-dose oral course (typically prednisone for 1–2 weeks) and/or steroid injections through the eardrum (intratympanic dexamethasone), which deliver drug directly to the inner ear and are also used as salvage therapy if oral steroids fail. Treatment works best started within the first days and is generally offered up to about two weeks from onset. Beyond a month, the chance of medication helping is low. This is why it matters that the "is it just wax?" question gets answered the day hearing drops, not a month later.
How high the steroid dose needs to be has now been tested. A 2024 trial randomly assigned 325 people with sudden hearing loss to one of three 5-day courses: 250 mg a day of intravenous prednisolone, 40 mg a day of oral dexamethasone, or 60 mg a day of oral prednisolone followed by 5 more days of tapering doses. Hearing improved by 34.2, 41.4 and 41.0 dB at 30 days, a difference that was not statistically significant, so the high doses did not beat the lower-dose course. Side effects linked to the drug were more common on the high doses (73 and 76 versus 46).
Hearing aids: the honest version
Hearing aids are the mainstay treatment for permanent sensorineural loss, and modern ones are genuinely good — directional microphones, feedback cancellation, Bluetooth streaming, rechargeable batteries. The honest part is the economics:
- Traditional prescription hearing aids cost roughly $2,000–$7,000 per pair, bundled with professional fitting and follow-up.
- Original Medicare does not cover hearing aids. This surprises and angers nearly everyone who discovers it at age 70. Some Medicare Advantage plans, some private insurance, the Veterans Health Administration (which is a major provider of hearing aids to veterans), and state vocational/Medicaid programs offer partial or full coverage, so the cost to the buyer varies widely.
- Warehouse clubs and similar high-volume retailers sell prescription-grade aids with fitting for roughly $1,500–$2,500 per pair, a well-known middle path.
The 2022 U.S. Food and Drug Administration over-the-counter rule
In October 2022, the U.S. Food and Drug Administration (FDA) created a new category of over-the-counter (OTC) hearing aids for adults with perceived mild-to-moderate hearing loss — no prescription, no audiologist visit, no medical exam required. Prices run roughly $200–$1,000 per pair, sold at pharmacies, big-box stores, and online. How these devices are described in practice:
- Over-the-counter aids are designed for people who struggle in groups and with TV but do fine one-on-one in quiet. Not being able to follow loud speech even up close points to a loss likely beyond the over-the-counter category, where a formal audiogram and prescription devices come in.
- A hearing test first is possible even without a prescription (many audiologists offer low-cost testing, and some over-the-counter devices include app-based self-tests). The audiogram also screens for the asymmetric losses and medical causes that need a doctor.
- The legal category is U.S. Food and Drug Administration-registered over-the-counter hearing aids, which is different from unregulated personal sound amplifiers. Features buyers commonly compare are a self-fitting app and a 45-day or longer return window — adjustment takes weeks, and return policies are where cheap devices tend to fall short.
- There is an adjustment period: the brain has not heard high frequencies in years, and at first everything sounds tinny and one's own voice sounds strange. This fades over 2–4 weeks of consistent daily wear. Most people who "tried hearing aids and hated them" wore them an hour a day for a week and quit.
A randomized trial of 64 adults with self-perceived mild to moderate hearing loss compared a self-fitting over-the-counter hearing aid, with remote support, against the same aid fitted by an audiologist. At the end of 6 weeks no meaningful differences were evident on any outcome measure. The authors say these aids "may provide an effective intervention" for mild to moderate loss.
Why waiting 7–10 years is costly
The average person waits the better part of a decade before treating hearing loss, and the wait itself does damage. The brain regions that process sound are use-it-or-lose-it: with years of auditory deprivation, the auditory cortex receives a degraded signal and the brain's ability to decode speech atrophies. Treat early and the brain adapts quickly; treat after fifteen years and even a perfect hearing aid delivers sound to a brain that has partly forgotten what to do with it — speech understanding never fully recovers. Hearing aids are like exercise for the auditory system: the earlier and more consistently used, the better the outcome.
Cochlear implants
When hearing aids no longer provide useful benefit — generally moderate-to-profound sensorineural loss with poor word understanding even when properly aided — a cochlear implant bypasses the dead hair cells entirely, stimulating the auditory nerve directly through an electrode array threaded into the cochlea. Key facts patients are often surprised by:
- Medicare covers cochlear implantation for qualifying candidates, and coverage criteria were expanded in 2022 (sentence-recognition scores up to 60% in the best-aided condition now qualify). Most private insurance covers it as well.
- Age is not a barrier — adults in their 80s and 90s are implanted routinely, and outcomes in healthy older adults are good.
- It is outpatient surgery, typically 1.5–2 hours. The implant is activated a few weeks later, and the brain takes months to learn the new signal; speech understanding typically improves dramatically over the first 6–12 months.
- Far fewer than 10% of US adults who meet candidacy criteria actually have one — largely because neither patients nor primary-care doctors realize they qualify. People who wear powerful hearing aids and still can't use a phone are the group a cochlear-implant evaluation is meant for.
Surgery for conductive losses
Otosclerosis is treated with stapedectomy/stapedotomy — replacing the frozen stirrup bone with a tiny prosthesis — with high success rates in experienced hands. Eardrum perforations can be patched (tympanoplasty), and chronic middle-ear disease has a range of surgical fixes. Bone-anchored hearing systems help some conductive and single-sided losses.
Assistive technology: cheap and underused
- Captions everywhere: live captions are built into modern smartphones (calls and any audio), TVs, and video platforms — free and transformative.
- Captioned telephones for home use are free in the US through a federally funded program for people with documented hearing loss.
- Hearing loops (marked by the ear-with-a-T symbol in theaters, churches, airports) transmit sound directly to hearing aids equipped with a telecoil; the telecoil can be activated at fitting.
- TV streamers, remote microphones, and amplified/flashing alerting devices (doorbell, smoke alarm, baby monitor) round out the toolkit.
8. Complications
The hearing–dementia connection
This is the finding that changed how medicine views hearing loss. In 2011, Frank Lin and colleagues showed that older adults with hearing loss developed dementia at substantially higher rates — risk rising with severity of loss (roughly doubled with mild loss, tripled with moderate, five-fold with severe). The study followed 639 people for a median of 11.9 years and counted 58 dementia cases. The hazard ratios were 1.89, 3.00 and 4.94, and the severe group held only 6 people, so its estimate is very loose (95% confidence interval 1.09 to 22.40). The authors left open whether hearing loss is a marker for early dementia or a risk factor that can be changed. The 2020 Lancet Commission on dementia went further, naming midlife hearing loss the single largest modifiable risk factor for dementia, estimating that around 8% of dementia cases worldwide are attributable to it — more than smoking, hypertension, or physical inactivity. The 2024 update of that report lists 14 modifiable risk factors, hearing loss among them, that together could account for up to 45% of dementia cases. Proposed mechanisms include the constant cognitive load of decoding degraded sound, accelerated brain atrophy in auditory and memory regions, and the social isolation that hearing loss produces.
Association is not proof that treating hearing prevents dementia — which is why the ACHIEVE trial (published in The Lancet, 2023) mattered so much. Nearly 1,000 older adults with untreated hearing loss were randomized to best-practice hearing aids or to a health-education control for three years. Reported honestly, the result has two parts: in the total study population, hearing aids did not significantly slow cognitive decline over three years — the overall primary result was null. But a prespecified sensitivity analysis split the trial by its two recruitment groups and found the effect differed between them. Among the 238 people at higher risk of cognitive decline (older, more risk factors, drawn from the long-running Atherosclerosis Risk in Communities heart-health cohort), hearing intervention was associated with about 48% less 3-year cognitive decline, with no effect among the 739 healthier volunteers. The authors say the intervention "might reduce" cognitive change in people at increased risk. The likely explanation is that the healthier volunteers declined so little in three years that there was nothing to slow. A longer follow-up is underway. The fair summary for patients: hearing aids are not a proven dementia vaccine, but for older adults already at elevated risk, the evidence that treating hearing protects cognition is genuinely encouraging — and hearing aids carry essentially no downside risk.
Longer observational comparisons point the same way but cannot show cause. A 2023 review pooling 8 studies and 126,903 people, with follow-up of 2 to 25 years, found that hearing aid users had a lower hazard of any cognitive decline than people with uncorrected hearing loss (hazard ratio 0.81), and its authors called for randomized trials to test this.
Isolation and depression
Untreated hearing loss reliably erodes social life. Conversation becomes work, group settings become humiliating, and the path of least resistance is to stop going. Population studies link hearing loss to measurably greater social isolation (in one national US survey the link was significant in women aged 60 to 69, with odds of isolation 3.49 times higher per 25 dB of loss, and not in other age and gender groups) and a significantly increased prevalence of depression — a 2020 meta-analysis found roughly 47% higher odds of depression among older adults with hearing loss. Spouses and family members carry a parallel burden of repeated, shouted, abandoned conversations. This cascade — loss → withdrawal → loneliness → depression → cognitive decline — is the real cost of the "I'll deal with it later" decade.
Falls, safety, and money
Even mild hearing loss roughly triples the odds of reported falls, likely through reduced spatial awareness and the cognitive load of straining to hear. Unheard smoke alarms, doorbells, and approaching cars are practical safety issues with cheap fixes (see assistive technology). And untreated hearing loss costs money beyond the obvious: a 10-year claims analysis found older adults with untreated hearing loss generated about 46% higher total health-care costs (roughly $22,000 more over a decade) than matched peers without hearing loss, with more hospitalizations and readmissions.
A US follow-up of 1,863 adults with hearing loss, followed for a median of about 10 years, found lower death rates in regular hearing aid users than in people who never used them (adjusted hazard ratio 0.76), and no difference for occasional users (0.93). This shows an association only; the authors call for more research on whether hearing aids play a protective role.
9. Prognosis
Presbycusis and noise-induced loss are permanent and slowly progressive — but progression is gradual (typically on the order of 1 dB per year in later life), and well-fitted amplification keeps the large majority of people communicating well for life. The trajectory worth fearing is not the audiogram's; it is the social one, and that one is controllable.
Sudden sensorineural hearing loss has a genuinely time-dependent prognosis: roughly one-third to one-half of patients recover substantial hearing spontaneously, prompt steroid treatment improves the odds of meaningful recovery, and low-frequency losses and younger patients do better. Loss accompanied by vertigo, profound loss, and — above all — delayed treatment predict worse outcomes.
Conductive losses have the best prognosis of all: wax removal is curative, infections resolve, and stapes surgery for otosclerosis restores hearing in roughly 90% of well-selected cases.
Cochlear implant recipients typically progress from understanding almost no speech to understanding most conversational speech (often including phone use) within the first year, though outcomes vary and lifelong device use is required. Across every category, the single most prognosis-improving act available to a patient is the same: acting early — on the sudden loss (days), and on the gradual one (years sooner).
10. Prevention
How ears are protected from noise
- Foam earplugs are rated by NRR (Noise Reduction Rating), typically 22–33 dB. The honest caveat: the lab-derived NRR overstates real-world protection — poorly inserted foam plugs may deliver half their rating or less. The usual fitting method is to roll the plug tight, pull the top of the ear up and back, insert it deep, and hold it while it expands. A properly inserted foam plug noticeably muffles the wearer's own voice.
- Musician's earplugs (flat-attenuation filters, ~$15–40 for universal-fit; custom-molded ~$150–250) reduce volume evenly across frequencies, so music and speech stay clear instead of muffled. They are the answer for concertgoers, musicians, and bartenders who "hate how earplugs sound."
- Earmuffs for mowing, power tools, and shooting (for gunfire, doubled up: plugs plus muffs).
- Distance and breaks help: stepping away from the speakers and giving ears quiet recovery time between exposures measurably reduces damage.
Volume habits
Commonly described headphone habits are the 60/60 rule, a phone's headphone-safety limit, and noise-cancelling headphones in loud environments — when the background roar is cancelled, people naturally listen at far lower volumes. Earbuds that someone an arm's length away can hear are commonly taken to be too loud.
How the blood supply affects hearing
The cochlea is fed by a single tiny artery with no backup, so cardiovascular health is hearing health. Controlled cardiovascular risk factors, blood sugar, and blood pressure, physical activity, and not smoking are all associated with better hearing in later life. These are not dramatic effects, but they run in the right direction and the same habits are tied to heart and brain health.
Folate and B12: what the evidence actually says
One well-designed randomized trial (Durga et al., 2007) of 728 older adults found that folic acid supplementation (800 micrograms a day) slowed age-related decline in low-frequency hearing over three years. The effect was small: low-frequency thresholds rose by 1.0 dB with folic acid and 1.7 dB with placebo, a difference of 0.7 dB, and high-frequency hearing did not change. The trial was conducted in the Netherlands at a time when Dutch food was not fortified with folic acid, in adults selected for raised homocysteine (13 micromol/L or greater) and vitamin B12 of 200 pmol/L or greater, whose folate levels at the start were about half of those found in the U.S. population. In the United States, where flour has been folate-fortified since 1998, most people are not folate-deficient and the benefit may not translate. Observational studies similarly link low vitamin B12 and folate levels with worse hearing, but supplementation trials in replete populations are lacking. What this adds up to: correcting a documented deficiency has its own reasons (B12 deficiency is common over 60), while nothing shows that supplements prevent hearing loss in people whose levels are normal.
Practical screening
Practitioners describe a baseline audiogram around age 50 (earlier with noise exposure), rechecked every few years, as the blood-pressure cuff of the ears: cheap, painless, and the only way to catch a slow loss the brain has been quietly compensating for. Validated app-based and telephone hearing screens are a reasonable free first step.
11. Recent Research and Advances
Hearing aids and the aging brain. The ACHIEVE trial's 2023 results (detailed under Complications) made hearing care a legitimate piece of dementia-prevention strategy for at-risk older adults; extended follow-up of the cohort is ongoing and will show whether the protective signal strengthens over longer horizons.
Gene therapy for genetic deafness. In 2024, several small trials in China and the US restored meaningful hearing in children born deaf from otoferlin (OTOF) gene mutations, using a harmless virus to deliver a working copy of the gene into the cochlea — the first time human deafness has been treated at the level of its genetic cause. OTOF deafness is rare, but the proof-of-concept opens the door to treating other genetic forms. In 2026 the work moved from small reports to larger studies and an approval. A study of 12 children with profound deafness found that 9 reached the main goal of hearing sounds at 70 dB or quieter after 24 weeks, and 3 reached normal average hearing sensitivity; 67 adverse events occurred, none of which led anyone to leave the study. A multicentre study of 42 people aged 0.8 to 32.3 years, with no comparison group, reported hearing recovered in 90%, with behavioural hearing tests improving from above 96 dB at the start to 37 dB at 2.5 years and greater gains in those under 18 than in adults. On 23 April 2026 the first otoferlin gene therapy received U.S. approval, for children and adults with severe-to-profound hearing loss from confirmed mutations in both copies of the OTOF gene, working outer hair cells, and no cochlear implant in the same ear.
Hair-cell regeneration. Because birds and fish regrow hair cells, researchers are hunting the molecular switches (Notch signaling, the transcription factor ATOH1) that could coax human supporting cells to do the same. Clinical trials of regenerative drugs injected into the ear have so far been disappointing — early-phase candidates failed to show convincing hearing improvement — but the field is active. No regenerative treatment is available today, and "stem-cell hearing cures" sold by clinics have no such approved treatment behind them.
Protecting hearing during chemotherapy. Sodium thiosulfate is now approved to reduce cisplatin-induced hearing loss in children with certain cancers — a genuine ototoxicity-prevention milestone — and trials in adults continue.
Hidden hearing loss diagnostics. Work continues on tests that detect cochlear synaptopathy in people with normal audiograms but real-world listening difficulty, which would finally give a name and a measurement to "I pass the test but can't hear in restaurants."
The over-the-counter market matures. Since the 2022 U.S. Food and Drug Administration rule, mainstream consumer-electronics makers have entered hearing care — including earbuds with U.S. Food and Drug Administration-cleared hearing-aid software — pushing prices down and, perhaps more importantly, eroding the stigma that kept devices out of ears for decades.
Key Research Papers
- Lin FR, Metter EJ, O'Brien RJ, Resnick SM, Zonderman AB, Ferrucci L. Hearing Loss and Incident Dementia. Archives of Neurology. 2011;68(2):214-220. — doi:10.1001/archneurol.2010.362
- Livingston G, Huntley J, Sommerlad A, et al. Dementia prevention, intervention, and care: 2020 report of the Lancet Commission. The Lancet. 2020;396(10248):413-446. — doi:10.1016/S0140-6736(20)30367-6
- Lin FR, Pike JR, Albert MS, et al. Hearing intervention versus health education control to reduce cognitive decline in older adults with hearing loss in the USA (ACHIEVE): a multicentre, randomised controlled trial. The Lancet. 2023;402(10404):786-797. — doi:10.1016/S0140-6736(23)01406-X
- Chandrasekhar SS, Tsai Do BS, Schwartz SR, et al. Clinical Practice Guideline: Sudden Hearing Loss (Update). Otolaryngology–Head and Neck Surgery. 2019;161(1_suppl):S1-S45. — doi:10.1177/0194599819859885
- GBD 2019 Hearing Loss Collaborators. Hearing loss prevalence and years lived with disability, 1990–2019: findings from the Global Burden of Disease Study 2019. The Lancet. 2021;397(10278):996-1009. — doi:10.1016/S0140-6736(21)00516-X
- Cunningham LL, Tucci DL. Hearing Loss in Adults. New England Journal of Medicine. 2017;377(25):2465-2473. — doi:10.1056/NEJMra1616601
- Goman AM, Lin FR. Prevalence of Hearing Loss by Severity in the United States. American Journal of Public Health. 2016;106(10):1820-1822. — doi:10.2105/AJPH.2016.303299
- Reed NS, Altan A, Deal JA, et al. Trends in Health Care Costs and Utilization Associated With Untreated Hearing Loss Over 10 Years. JAMA Otolaryngology–Head & Neck Surgery. 2019;145(1):27-34. — doi:10.1001/jamaoto.2018.2875
- Schwartz SR, Magit AE, Rosenfeld RM, et al. Clinical Practice Guideline (Update): Earwax (Cerumen Impaction). Otolaryngology–Head and Neck Surgery. 2017;156(1_suppl):S1-S29. — doi:10.1177/0194599816671491
- Mick P, Kawachi I, Lin FR. The Association between Hearing Loss and Social Isolation in Older Adults. Otolaryngology–Head and Neck Surgery. 2014;150(3):378-384. — doi:10.1177/0194599813518021
- Kujawa SG, Liberman MC. Adding Insult to Injury: Cochlear Nerve Degeneration after "Temporary" Noise-Induced Hearing Loss. The Journal of Neuroscience. 2009;29(45):14077-14085. — doi:10.1523/JNEUROSCI.2845-09.2009
- Lawrence BJ, Jayakody DMP, Bennett RJ, Eikelboom RH, Gasson N, Friedland PL. Hearing Loss and Depression in Older Adults: A Systematic Review and Meta-analysis. The Gerontologist. 2020;60(3):e137-e154. — doi:10.1093/geront/gnz009
- Durga J, Verhoef P, Anteunis LJC, Schouten E, Kok FJ. Effects of Folic Acid Supplementation on Hearing in Older Adults: A Randomized, Controlled Trial. Annals of Internal Medicine. 2007;146(1):1-9. — doi:10.7326/0003-4819-146-1-200701020-00003
- Carlson ML. Cochlear Implantation in Adults. New England Journal of Medicine. 2020;382(16):1531-1542. — doi:10.1056/NEJMra1904407
- Plontke SK, Girndt M, Meisner C, et al. High-Dose Glucocorticoids for the Treatment of Sudden Hearing Loss. NEJM Evidence. 2024;3(1):EVIDoa2300172. — doi:10.1056/EVIDoa2300172
- De Sousa KC, Manchaiah V, Moore DR, Graham MA, Swanepoel W. Effectiveness of an Over-the-Counter Self-fitting Hearing Aid Compared With an Audiologist-Fitted Hearing Aid: A Randomized Clinical Trial. JAMA Otolaryngology–Head & Neck Surgery. 2023;149(6):522-530. — doi:10.1001/jamaoto.2023.0376
- Yeo BSY, Song HJJMD, Toh EMS, et al. Association of Hearing Aids and Cochlear Implants With Cognitive Decline and Dementia: A Systematic Review and Meta-analysis. JAMA Neurology. 2023;80(2):134-141. — doi:10.1001/jamaneurol.2022.4427
- Choi JS, Adams ME, Crimmins EM, Lin FR, Ailshire JA. Association between hearing aid use and mortality in adults with hearing loss in the USA: a mortality follow-up study of a cross-sectional cohort. The Lancet Healthy Longevity. 2024;5(1):e66-e75. — doi:10.1016/S2666-7568(23)00232-5
- Livingston G, Huntley J, Liu KY, et al. Dementia prevention, intervention, and care: 2024 report of the Lancet standing Commission. The Lancet. 2024;404(10452):572-628. — doi:10.1016/S0140-6736(24)01296-0
- Valayannopoulos V, Bance M, Carvalho DS, et al. DB-OTO Gene Therapy for Inherited Deafness. New England Journal of Medicine. 2026;394(11):1074-1083. — doi:10.1056/NEJMoa2400521
- Jiang L, Cheng X, Lv J, et al. Multicentre gene therapy for OTOF-related deafness followed up to 2.5 years. Nature. 2026;653(8116):1170-1177. — doi:10.1038/s41586-026-10393-y
- McGuigan A. Lunsotogene Parvec: First Approval. Drugs. 2026;86(10):1747-1751. — doi:10.1007/s40265-026-02361-7
Historical Background
For most of history, the only help for poor hearing was acoustic: ear trumpets and conversation tubes that funneled sound into the canal, fashionable enough by the 19th century to be built into walking sticks and armchairs. The telephone changed everything — its carbon microphone technology produced the first electric hearing aid (the Akouphone, 1898), followed by vacuum-tube aids in the 1920s and then a true revolution: the transistor. Hearing aids were among the very first consumer products to use transistors (1952–53), shrinking from satchel-sized boxes to behind-the-ear devices within a decade. The bolder leap was bypassing the ear entirely: in 1961, William House implanted the first practical single-channel cochlear implant in Los Angeles, and in 1978 Graeme Clark in Melbourne implanted the first multichannel device — the design that finally made implanted patients able to understand open-set speech, earning U.S. Food and Drug Administration approval in the 1980s and reaching hundreds of thousands of users worldwide. The most recent milestone was regulatory rather than technical: the U.S. Food and Drug Administration's 2022 over-the-counter hearing aid rule, which ended the prescription-only era and put effective amplification on pharmacy shelves.
PubMed Topic Searches
Live PubMed searches for the current literature on hearing loss — each link opens the latest indexed studies on that topic:
- PubMed: Presbycusis (age-related hearing loss) treatment
- PubMed: Sudden sensorineural hearing loss & corticosteroids
- PubMed: Noise-induced hearing loss prevention
- PubMed: Hearing aids & cognitive decline (randomized trials)
- PubMed: Hearing loss & dementia risk
- PubMed: Over-the-counter hearing aids — outcomes
- PubMed: Cochlear implant outcomes in adults
- PubMed: Cochlear synaptopathy ("hidden hearing loss")
- PubMed: Drug ototoxicity (cisplatin, aminoglycosides)
- PubMed: Hair-cell regeneration & cochlear gene therapy
- PubMed: Otosclerosis & stapes surgery outcomes
- PubMed: Hearing loss, depression & social isolation
Connections
- ENT
- Hearing & the Cochlea — interactive animation
- Hearing Aids
- Tinnitus
- Vertigo & Meniere's Disease
- Sinusitis
- Dementia
- Alzheimer's Disease
- Depression
- Loneliness
- Concussion
- Cardiovascular Disease
- Diabetes
- Vitamin B12
- Vitamin B9 (Folate)
- Ear Infections
- Bell's Palsy
- Susac Syndrome
- Ginkgo Biloba for Tinnitus
- Discussed in depth on these pages: Tinnitus Causes and Triggers