⚠ Evidence warning: Clinical trials or other evidence do not support the claims that inositol stands apart from other supplements for this condition, that metformin through pregnancy prevents gestational diabetes, that lowering insulin alone quiets the ovary, and that semaglutide brings 10-15% weight loss at 12 months in this condition. This page keeps it as a report of what people, websites or other media say.
Insulin Resistance and Polycystic Ovary Syndrome (PCOS)
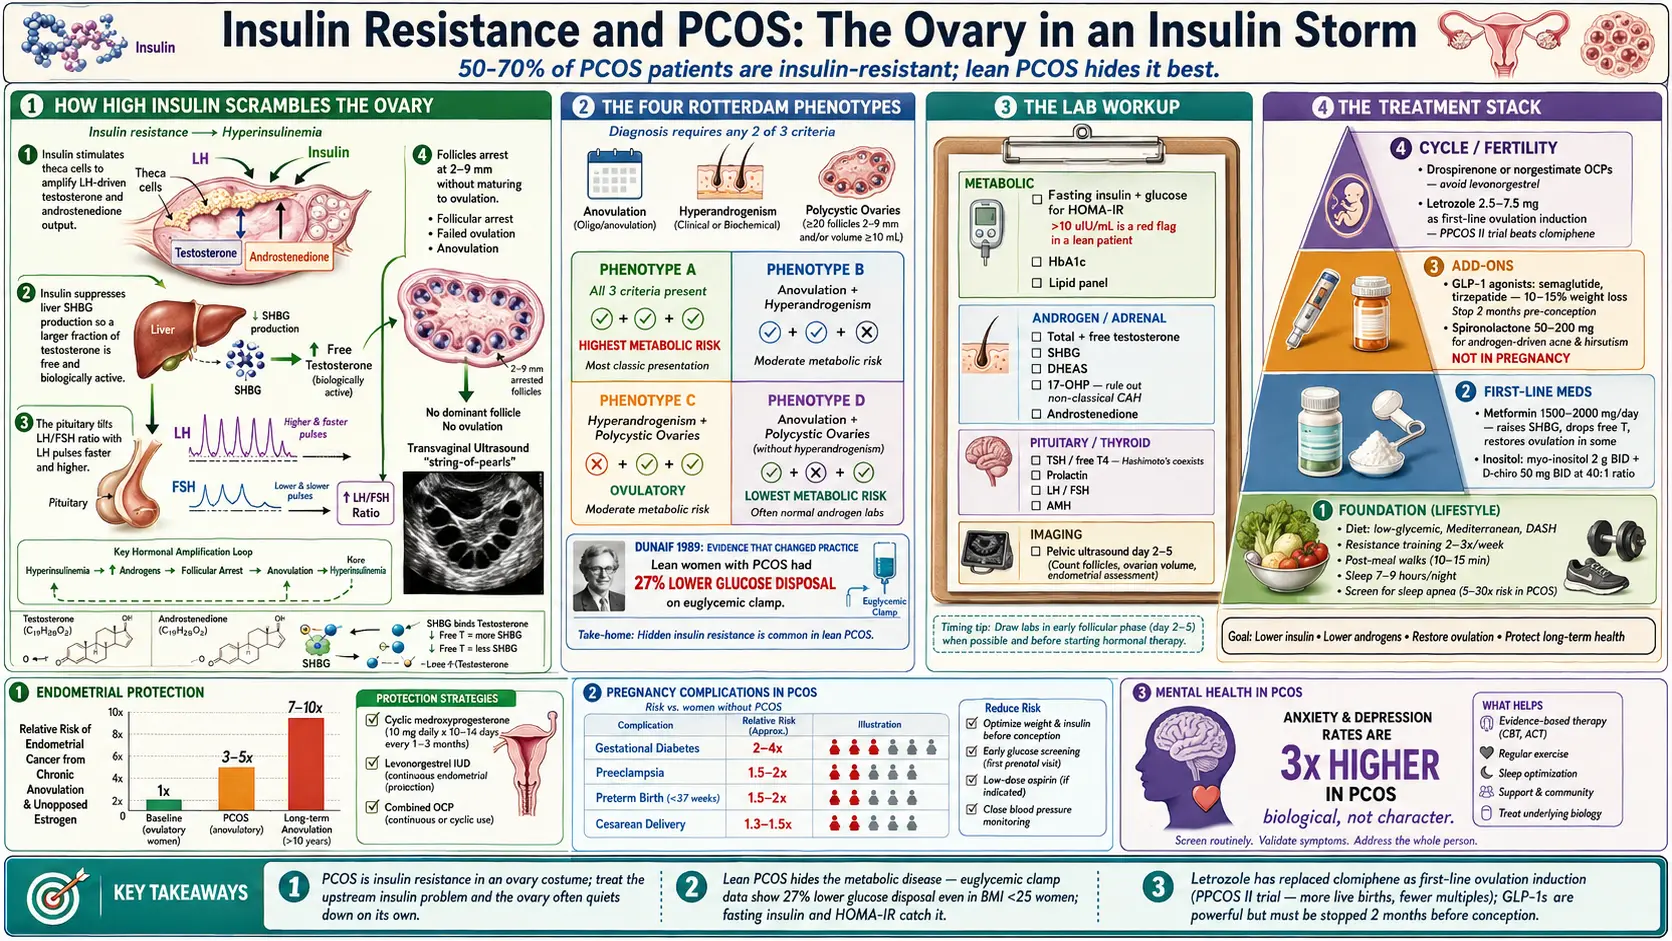
Table of Contents
- Why This Connection Matters
- How Common Insulin Resistance Is in Polycystic Ovary Syndrome
- Lean Polycystic Ovary Syndrome — The Subset That Gets Missed
- The Mechanism: How High Insulin Scrambles Ovaries
- Rotterdam Criteria and the Four Phenotypes
- The Lab Workup: Tests Commonly Ordered
- Metformin — The Workhorse
- Inositol — What the Trials and the 2023 Guideline Report
- Glucagon-Like Peptide-1 Receptor Agonists — The New Wave
- Spironolactone for Androgen Symptoms
- Combined Oral Contraceptives — How the Progestins Differ
- Letrozole for Ovulation Induction
- Diet and Exercise That Actually Work
- Sleep Apnea and Mental Health
- Endometrial Protection
- Fertility Pathway and Pregnancy Risks
- Key Research Papers
- Connections
- Featured Videos
Why This Connection Matters
If you have polycystic ovary syndrome (PCOS), there is a better-than-even chance that insulin resistance is the engine driving your symptoms — whether you are thin, average, or carrying extra weight. This is not a footnote in your chart. It is often the central metabolic problem, and the reason cycles are irregular, hair is growing where it shouldn’t, acne is breaking through, and conception is harder than expected.
Most polycystic ovary syndrome guidance focuses on the ovary. Practitioners who put insulin first call that a mistake. In their account the ovary is usually a bystander reacting to a whole-body insulin problem upstream: fix the insulin signal, and the ovary often quiets down on its own, with androgens falling, periods returning, fertility improving and weight becoming easier to manage. Treating only the ovary, they say, is chasing the fire downstream of the gas line.
In 2026 the condition was given a new name, polyendocrine metabolic ovarian syndrome (PMOS), after a global process that involved 56 academic, clinical and patient organisations and survey replies from 14,360 people with the condition and health professionals. The authors say it affects one in eight women and that the old name wrongly implied ovarian cysts. A transition period is under way, so most papers and clinics still use the old name, as this page does.
This page is for patients who want to understand why their endocrinologist orders certain labs, why metformin keeps coming up even though they “don’t have diabetes,” and what options exist beyond “lose weight and take the pill.”
How Common Insulin Resistance Is in Polycystic Ovary Syndrome
Depending on how it is measured, between 50% and 70% of polycystic ovary syndrome patients have insulin resistance. In a landmark 1989 study by Andrea Dunaif, polycystic ovary syndrome patients were shown to have a substantial defect in insulin action independent of obesity — lean women with polycystic ovary syndrome were insulin-resistant compared with lean controls, and women with obesity and polycystic ovary syndrome were more insulin-resistant than their weight-matched peers without polycystic ovary syndrome. That paper reframed polycystic ovary syndrome as a metabolic disease, not just a reproductive one.
The overlap is so consistent that many endocrinologists treat a new polycystic ovary syndrome diagnosis as a prompt to screen for insulin resistance by default, even in patients who look metabolically healthy. The reason is simple: you cannot reliably predict insulin resistance by looking at someone. A patient with a body mass index (BMI) of 22, normal fasting glucose, and a normal hemoglobin A1c can still have a fasting insulin of 18 micro-international units per milliliter (µIU/mL) and a homeostatic model assessment of insulin resistance (HOMA-IR) of 4. That patient has meaningful insulin resistance that will not show up on any standard primary-care panel.
Lean Polycystic Ovary Syndrome — The Subset That Gets Missed
Roughly 20-30% of polycystic ovary syndrome patients have a body mass index under 25. These women often spend years being told their symptoms can’t be polycystic ovary syndrome because “you’re not overweight.” They also get dismissed from metabolic workup because their fasting glucose is fine and their hemoglobin A1c is 5.2%.
A 2013 study by Stepto and colleagues used the gold-standard euglycemic-hyperinsulinemic clamp — the most accurate way to measure insulin action — and reported a mean glucose infusion rate of 270 mg/min/m² in lean women with polycystic ovary syndrome against 339 mg/min/m² in lean controls (a lower rate means more insulin resistance). Insulin resistance was present in 75% of the lean women and 95% of the overweight women with the condition. In other words, lean polycystic ovary syndrome really does come with real insulin resistance, it is just hidden. The standard fasting glucose test misses it because glucose stays normal for years while insulin climbs to keep it there.
Practitioners who test for insulin resistance describe this workup as more important for lean patients, not less, because weight is hiding the problem rather than signalling it.
The Mechanism: How High Insulin Scrambles Ovaries
Understanding the mechanism makes the treatment logic obvious. Four things happen when insulin runs chronically high:
- Theca cells make more testosterone. Insulin acts directly on ovarian theca cells — the androgen-producing cells — and amplifies their response to luteinizing hormone (LH). More luteinizing hormone stimulation plus more insulin equals more testosterone and androstenedione pouring into circulation.
- Sex hormone-binding globulin drops. The liver makes sex hormone-binding globulin (SHBG), the carrier protein that keeps most circulating testosterone inactive. Insulin suppresses sex hormone-binding globulin production. Less sex hormone-binding globulin means a larger fraction of testosterone is “free” biologically active — even if total testosterone looks only modestly elevated. This is why two women with the same total testosterone can have very different acne and hair growth.
- Luteinizing hormone/follicle-stimulating hormone (FSH) ratio tilts. The pituitary normally pulses luteinizing hormone and follicle-stimulating hormone (FSH) in a balanced rhythm. In polycystic ovary syndrome, luteinizing hormone pulses faster and higher while follicle-stimulating hormone lags. The result is a luteinizing hormone-dominant environment that pushes theca cells to make still more androgen and leaves granulosa cells understimulated.
- Follicle maturation halts. With low follicle-stimulating hormone signaling and high intraovarian androgen, follicles grow partway and stall. They never mature to the dominant follicle that would ovulate. Instead, the ovary accumulates dozens of small 2-9 mm follicles visible on ultrasound — the “polycystic” appearance — and skips ovulation entirely. That is anovulation, which means no progesterone, which means no regular period.
Every arm of polycystic ovary syndrome treatment you will read about below is targeting one of these four steps.
Rotterdam Criteria and the Four Phenotypes
Polycystic ovary syndrome is diagnosed using the Rotterdam criteria (2003), which require two of three features:
- Oligo- or anovulation (fewer than 8-9 periods per year, or cycles longer than 35 days)
- Clinical or biochemical hyperandrogenism (hirsutism, acne, androgenic alopecia, OR elevated total/free testosterone or dehydroepiandrosterone sulfate (DHEAS))
- Polycystic ovaries on ultrasound (≥12 follicles 2-9 mm per ovary, or ovarian volume >10 mL)
Those ultrasound numbers are the 2003 version and have since been updated. The 2023 international guideline sets the threshold in adults at a follicle number per ovary of at least 20 in at least one ovary; with older technology or poor images it uses an ovarian volume of at least 10 mL, or at least 10 follicles per section, in at least one ovary. It also accepts a blood test, anti-Müllerian hormone (AMH), for defining polycystic ovaries in adults, though not as a single test for the diagnosis. It states that there are no definitive ultrasound criteria for adolescents.
Because only two of three are needed, polycystic ovary syndrome splits into four phenotypes:
- Phenotype A — all three features (the “classic” form, highest metabolic risk)
- Phenotype B — anovulation plus hyperandrogenism (no cysts on imaging)
- Phenotype C — hyperandrogenism plus polycystic ovaries but ovulatory cycles (“ovulatory polycystic ovary syndrome”)
- Phenotype D — anovulation plus polycystic ovaries without hyperandrogenism (lowest metabolic risk)
Phenotypes A and B carry the highest insulin resistance burden. Phenotype D is the mildest metabolically. This matters because it explains why two friends with “the same” diagnosis can have very different symptoms and very different long-term risks.
The Lab Workup: Tests Commonly Ordered
Practitioners describe a polycystic ovary syndrome evaluation as more than a pregnancy test and a testosterone level. A full first-visit panel, as they describe it, includes:
- Fasting insulin + fasting glucose — to calculate homeostatic model assessment of insulin resistance (see the fasting insulin and homeostatic model assessment of insulin resistance guide for how to interpret the number). Some practitioners read a fasting insulin above 10 µIU/mL in a lean patient as a warning sign.
- Total testosterone and free testosterone (calculated or direct)
- Sex hormone-binding globulin — often low in insulin-resistant polycystic ovary syndrome and one of the most useful single markers
- Dehydroepiandrosterone sulfate — adrenal androgen; a markedly elevated level raises the question of adrenal sources or late-onset congenital adrenal hyperplasia
- 17-hydroxyprogesterone (17-OHP), fasting, early morning — screens for non-classical congenital adrenal hyperplasia, which mimics polycystic ovary syndrome
- Thyroid-stimulating hormone (TSH), free T4 — rule out thyroid disease (Hashimoto’s and polycystic ovary syndrome coexist more often than chance)
- Prolactin — rule out hyperprolactinemia, which also causes anovulation
- Luteinizing hormone and follicle-stimulating hormone — a luteinizing hormone/follicle-stimulating hormone ratio above 2 is suggestive but not required
- Androstenedione — an upstream androgen often elevated when testosterone is only borderline
- AMH (anti-Müllerian hormone) — often elevated in polycystic ovary syndrome and useful for both diagnosis and fertility planning
- Hemoglobin A1c (HbA1c) and lipid panel — baseline metabolic screen
- Pelvic ultrasound — ideally transvaginal, day 2-5 of the cycle if possible
Any single piece of this panel in isolation can mislead. Interpreted together, they usually give a clear picture.
The 2023 international guideline differs on the first item: it states that clinically available insulin assays are of limited clinical relevance and are not recommended in routine care. It names the 75-g oral glucose tolerance test as the most accurate test of blood-sugar status in polycystic ovary syndrome regardless of body mass index, and says fasting glucose and hemoglobin A1c have significantly reduced accuracy.
Metformin — The Workhorse
Metformin has been used in polycystic ovary syndrome for decades and remains the first-line pharmacologic treatment for the insulin-resistance component. The typical dose is 1,500-2,000 mg per day, usually extended-release, taken with the largest meal to reduce gastrointestinal (GI) side effects. Prescribing usually starts at 500 mg per day and rises over 3-4 weeks.
What metformin does in polycystic ovary syndrome:
- Lowers hepatic glucose output, which lowers insulin demand and circulating insulin
- Modestly improves peripheral insulin sensitivity
- Raises sex hormone-binding globulin over 3-6 months, which lowers free testosterone
- Restores ovulation in a meaningful minority of patients, often within 3-6 months
- Reported to modestly reduce pregnancy complications (gestational diabetes in particular) when continued through pregnancy. The largest trial does not back the gestational diabetes part: in PregMet2 (487 pregnant women), gestational diabetes affected 25% on metformin and 24% on placebo, and the authors concluded metformin does not prevent it. Late miscarriage or preterm birth affected 5% against 10% (p=0.08), and 5% against 10% again when pooled with two earlier trials in an after-the-fact analysis (odds ratio 0.43).
Side effects are primarily gastrointestinal (nausea, loose stools, metallic taste) and resolve for most patients within a few weeks on the extended-release form. Long-term metformin can lower B12; yearly level checks, with supplements when the level is low, are commonly described. See the metformin, berberine, and glucagon-like peptide-1 (GLP-1) receptor agonists (GLP-1s) page for dosing detail and the berberine comparison.
Inositol — What the Trials and the 2023 Guideline Report
Most supplements marketed for polycystic ovary syndrome have weak evidence, and inositol is often described as the exception. The systematic review written for the 2023 international guideline (30 trials, 2,230 participants) reached a more cautious view: it calls the evidence for inositol “limited and inconclusive”. It found benefits for myo-inositol or D-chiro-inositol on some metabolic measures, a possible ovulation benefit from D-chiro-inositol and possibly no effect on other outcomes. Metformin may do better for waist-hip ratio and excess hair growth (hirsutism), while myo-inositol likely causes fewer stomach and bowel side effects than metformin. The guideline itself lists limited clinical benefits, including in ovulation, hirsutism or weight, and says specific types, doses or combinations cannot currently be recommended.
Inositol is a sugar alcohol that participates in insulin signaling inside cells, and in polycystic ovary syndrome the ratio of myo-inositol to D-chiro-inositol in the ovary appears disordered.
The dose most often quoted is myo-inositol 2 g twice daily plus D-chiro-inositol 50 mg twice daily — a 40:1 ratio that mirrors the physiologic blood ratio. A 2017 meta-analysis by Unfer and colleagues (9 randomized trials, 247 women given inositol and 249 controls, searched up to November 2016) found fasting insulin and the homeostatic model assessment index fell. Testosterone showed only a slight trend downward (P=0.099), androstenedione did not change, and sex hormone-binding globulin rose only in studies lasting at least 24 weeks. The paper reports no pooled ovulation or menstrual-regularity result; it calls tolerability “quite agreeable” and says one trial reported side effects at the usual dose. Improvements in ovulation rate and menstrual regularity, with few side effects, are nonetheless widely reported for inositol. Effects are said to take roughly 3 months to appear.
Inositol is available over the counter, does not require a prescription, and costs $20-40 per month. Some practitioners use it first for lean polycystic ovary syndrome patients who are not yet ready for prescription metformin, and it is commonly stacked with metformin in more severe cases. It is also safe in pregnancy — in fact some obstetricians use it for gestational diabetes prevention in high-risk patients.
Glucagon-Like Peptide-1 Receptor Agonists — The New Wave
Glucagon-like peptide-1 receptor agonists (semaglutide, tirzepatide, liraglutide) are approved for type 2 diabetes and obesity, not polycystic ovary syndrome. But their use in polycystic ovary syndrome is growing rapidly off-label because the mechanism is almost purpose-built for the problem: they slow gastric emptying, reduce appetite, lower insulin, and produce meaningful weight loss.
In polycystic ovary syndrome specifically, early trials and real-world practice report:
- 10-15% body weight loss at 12 months on semaglutide, more on tirzepatide, as reported in practice. Published figures differ: a 2026 scoping review of semaglutide gives 7.6-11.5 kg over 3-6 months from predominantly low-quality studies, and a retrospective UK weight-management service reported a 19.40% loss at 10 months on tirzepatide among the 40 women with the condition who reached that point, not significantly different from women without it
- Drops in fasting insulin and homeostatic model assessment of insulin resistance
- Increases in sex hormone-binding globulin and drops in free testosterone
- Restoration of ovulation in a meaningful percentage of previously anovulatory patients
Two important cautions. First, these drugs are not safe in pregnancy. The semaglutide label says to stop at least 2 months before a planned pregnancy because the drug washes out slowly; the tirzepatide label says it may cause fetal harm and to stop when pregnancy is recognized. Ovulation can return during treatment, and the 2026 semaglutide review lists unplanned pregnancy exposure as a safety concern for that reason. The tirzepatide label also warns it can make oral contraceptives less reliable: it tells users to switch to a non-oral method, or add a barrier method, for 4 weeks after starting and for 4 weeks after each dose increase. Second, they are expensive and insurance coverage for polycystic ovary syndrome alone (without documented type 2 diabetes or qualifying body mass index) is inconsistent.
Spironolactone for Androgen Symptoms
Metformin, inositol, and glucagon-like peptide-1 receptor agonists treat insulin. They do not directly block androgen at the skin or hair follicle, which means acne and hirsutism often persist even after cycles regularize. That is where spironolactone comes in.
Spironolactone is commonly described at 50-200 mg per day (usually started at 50 mg and titrated); the 2023 international guideline says 25-100 mg per day appears to have lower risks of adverse effects, and lists anti-androgens, combined with effective contraception, for hirsutism that has not responded well after at least six months of the pill and/or cosmetic therapy. Spironolactone blocks androgen receptors at the skin and hair follicle. It takes 3-6 months for acne to clear and 6-12 months for hair growth to slow. Side effects include increased urination in the first weeks, breast tenderness, and occasional menstrual irregularity.
The critical caveat: spironolactone is not safe to continue while trying to conceive, because it can feminize a male fetus. Patients who want children stop spironolactone and use another method (laser hair removal, electrolysis, topical eflornithine) or live with some androgen symptoms during the months of trying to conceive.
Combined Oral Contraceptives — How the Progestins Differ
Combined oral contraceptives are used for cycle regularity, endometrial protection, and androgen symptom control in polycystic ovary syndrome patients who are not trying to conceive. Some clinicians hold that the choice of pill matters.
Some progestins in older combined oral contraceptives — particularly levonorgestrel — have mild androgenic activity and are described as able to worsen insulin resistance and lipid profiles. The 2023 international guideline does not pick a winner: it says specific types or doses of progestins, estrogens or combinations cannot currently be recommended, and that general-population guidelines apply. Some clinicians still favor formulations with:
- Drospirenone — mild anti-androgenic activity, favored in polycystic ovary syndrome, though carries a slightly higher venous thromboembolism risk than older progestins
- Norgestimate — low androgenicity, good metabolic profile
- Cyproterone acetate (not available in the US but common in Europe) — strong anti-androgen. The 2023 guideline places the 35-microgram ethinyl estradiol plus cyproterone preparation as second-line because of its blood-clot risks, and says cyproterone at 10 mg or more is not advised because of an increased risk including meningioma
Some people on a levonorgestrel-containing pill whose acne, hair, or metabolic labs are worsening raise switching with their prescriber. Those clinicians’ view is that the pill is not one product and the progestin is a meaningful variable.
Letrozole for Ovulation Induction
When polycystic ovary syndrome patients are ready to conceive and ovulation has not returned with lifestyle and metformin/inositol, the first-line ovulation induction drug is now letrozole, not clomiphene citrate.
The shift was driven by the PPCOS II trial (Legro et al., 2014), a large US multicenter randomized study that compared letrozole to clomiphene in polycystic ovary syndrome patients pursuing pregnancy. Letrozole produced more ovulations (61.7% against 48.3% of cycles) and more live births (27.5% against 19.1%) than clomiphene. Twin pregnancies were 3.4% against 7.4%, which was not a significant difference, and there were four major congenital anomalies with letrozole against one with clomiphene (P=0.65). It is now the preferred first-line agent in every major guideline. The 2023 international guideline names it first-line for ovulation induction and notes that its use is still off-label in many countries.
Letrozole is prescribed at 2.5-7.5 mg daily for 5 days beginning on cycle day 3, 4, or 5 of an induced or spontaneous cycle. Most patients respond at 2.5 or 5 mg. If three letrozole cycles do not produce pregnancy, the typical next steps are letrozole plus injectable gonadotropins, letrozole plus intrauterine insemination (IUI), or in vitro fertilization (IVF). See the infertility page for the full treatment ladder.
Diet and Exercise That Actually Work
There is no single “polycystic ovary syndrome diet.” Multiple patterns work if they consistently lower insulin and are sustainable. The evidence-supported options:
- Low-glycemic-index — carbs that raise blood glucose slowly: lentils, beans, steel-cut oats, intact whole grains, most vegetables, lower-sugar fruits. White bread, sugary drinks, and ultra-processed snacks fall outside this pattern.
- Mediterranean — olive oil, fish, nuts, legumes, vegetables, moderate whole grains, limited red meat. Repeatedly associated with improvements in insulin sensitivity and androgen levels in polycystic ovary syndrome cohorts.
- DASH — originally developed for blood pressure, shares the Mediterranean framework and performs well in polycystic ovary syndrome trials.
- Moderate-carb with adequate protein — typically 30-40% of calories from carbohydrate, 25-30% from protein (1.2-1.6 g/kg body weight), with the balance from fat. Protein preserves lean mass during weight loss and improves satiety.
Practitioners treat exercise as a core part of care. The combination they describe as most reliable:
- Resistance training 2-3 times per week. Muscle is the body’s largest glucose sink; more muscle means better insulin disposal. See the exercise and muscle sensitivity page.
- Daily walking, particularly after meals. A 10-15 minute walk after dinner measurably lowers the post-meal glucose curve.
- Moderate cardio on top, 2-3 sessions per week, for cardiovascular fitness.
Sleep Apnea and Mental Health
A figure of 5-30 times higher risk of obstructive sleep apnea (OSA) than the general female population is often quoted for polycystic ovary syndrome. A 2020 meta-analysis found sleep apnea in 35.0% of women with the condition and an odds ratio of 3.83 (95% CI 1.43-10.24) against controls, with rates markedly higher in women with obesity than in lean women; most of its studies were at high risk of selection bias. The 2023 international guideline states the higher prevalence is independent of body mass index. Untreated obstructive sleep apnea drives insulin resistance, hypertension, and fatigue. The guideline lists snoring together with waking unrefreshed, daytime sleepiness or fatigue as the symptoms to assess, followed by a validated screening tool or referral; loud snoring, observed apneas and morning headaches are also classic symptoms, and a home sleep study is one way it is tested. Continuous positive airway pressure (CPAP) treatment of diagnosed obstructive sleep apnea improves insulin sensitivity within weeks.
Mental health deserves the same rigor. Polycystic ovary syndrome patients have roughly 3 times the rate of anxiety and depression of women without polycystic ovary syndrome: a 2018 meta-analysis gave odds ratios of 2.79 for depression and 2.75 for anxiety. This is not a character flaw or only a reaction to appearance changes. Some writers call it a direct biological consequence of the hormonal milieu, but the cause is not settled: a 2017 meta-analysis notes its studies were all cross-sectional, so its authors “can only hypothesize” that the diagnosis comes first, and that age, obesity, high androgens and insulin resistance do not explain the entire link. It is described as responding to the same treatments (therapy, selective serotonin reuptake inhibitors (SSRIs)/serotonin-norepinephrine reuptake inhibitors (SNRIs), exercise) that work in the general population. The 2017 authors suggest that providers consider screening women with the condition for both depression and anxiety.
Endometrial Protection
Chronic anovulation means the uterine lining is exposed to estrogen without the regular shedding that progesterone triggers after ovulation. Over years, that unopposed estrogen increases the risk of endometrial hyperplasia and endometrial cancer. The risk is described as real and meaningful — several-fold higher than baseline — and preventable. A 2014 meta-analysis gave an odds ratio for endometrial cancer of 2.79 at all ages and 4.05 once studies including women over 54 were excluded. Its authors say obesity and selection bias may have exaggerated the increase and that the cancer has a relatively low incidence in the general population; the 2023 international guideline likewise says the overall chance is low and routine screening is not recommended.
For people not trying to conceive, the 2023 guideline lists weight management, cycle regulation and regular progestogen therapy as preventive strategies. The standard progestin options:
- A combined oral contraceptive (daily progestin exposure)
- A levonorgestrel intrauterine device (IUD) — placed once, good for 5-8 years, delivers progestin locally to the endometrium with minimal systemic effect
- Cyclic oral progesterone (e.g., medroxyprogesterone 10 mg for 10 days every 1-3 months) to induce a withdrawal bleed — sometimes called a “progestin challenge”
Practitioners describe a withdrawal bleed at least every 3 months as the usual target for someone on none of these. The guideline lists long-standing untreated absence of periods, higher weight, type 2 diabetes and a persistently thickened lining as added risk factors, and says a biopsy and a withdrawal bleed are indicated when excessive endometrial thickness is found.
Fertility Pathway and Pregnancy Risks
The typical polycystic ovary syndrome fertility ladder looks like this:
- Lifestyle and insulin-resistance treatment first — 3-6 months of diet, exercise, metformin, and/or inositol. A substantial minority resume ovulation on this alone and conceive without further intervention.
- Letrozole ovulation induction — typically 3 cycles
- Letrozole plus IUI — adds intrauterine insemination if ovulation is happening but not resulting in pregnancy
- Gonadotropins — injectable follicle-stimulating hormone, usually with IUI or IVF
- IVF — high success rates in polycystic ovary syndrome because ovarian reserve is generally excellent, though ovarian hyperstimulation syndrome (OHSS) risk is elevated and requires careful protocol choice
Drugs of the glucagon-like peptide-1 type are being studied here too. A 2026 meta-analysis of 3 randomized trials (252 women) compared them with metformin: overall pregnancy was not significantly higher (odds ratio 1.41, 95% CI 0.81-2.45), natural pregnancy was (odds ratio 3.10, 95% CI 1.74-5.49), and in vitro fertilization pregnancy was not (odds ratio 1.01). The authors say larger trials measuring live birth are still needed.
Once pregnant, polycystic ovary syndrome patients have elevated rates of gestational diabetes, preeclampsia, and preterm birth. None of these is inevitable, but they justify earlier and more frequent screening than a standard pregnancy: an early glucose tolerance test (often at 12-16 weeks instead of the standard 24-28), blood pressure vigilance, and in many cases continuation of metformin through pregnancy. The 2023 international guideline says metformin in pregnancy has not been shown to prevent gestational diabetes, late miscarriage, high blood pressure or pre-eclampsia, and may be considered in some circumstances to reduce preterm delivery and limit excess weight gain. It says side effects are mostly mild and that the consequences for the child’s long-term health remain unclear, with a suggestion of increased childhood weight, although causality is not certain.
Key Research Papers
Foundational publications on the insulin resistance / polycystic ovary syndrome axis, the Rotterdam diagnostic consensus, and the major drug trials that shape modern management. Each citation links to the full text via DOI.
- Dunaif A, Segal KR, Futterweit W, Dobrjansky A. Profound Peripheral Insulin Resistance, Independent of Obesity, in Polycystic Ovary Syndrome. Diabetes. 1989;38(9):1165–1174. — doi:10.2337/diab.38.9.1165
- Dunaif A. Insulin Resistance and the Polycystic Ovary Syndrome: Mechanism and Implications for Pathogenesis. Endocrine Reviews. 1997;18(6):774–800. — doi:10.1210/edrv.18.6.0318
- Stepto NK, Cassar S, Joham AE, et al. Women with Polycystic Ovary Syndrome Have Intrinsic Insulin Resistance on Euglycaemic-Hyperinsulaemic Clamp. Human Reproduction. 2013;28(3):777–784. — doi:10.1093/humrep/des463
- Rotterdam ESHRE/ASRM-Sponsored PCOS Consensus Workshop Group. Revised 2003 Consensus on Diagnostic Criteria and Long-Term Health Risks Related to Polycystic Ovary Syndrome. Human Reproduction. 2004;19(1):41–47. — doi:10.1093/humrep/deh098
- Teede HJ, Tay CT, Laven JJE, et al. Recommendations from the 2023 International Evidence-Based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Journal of Clinical Endocrinology & Metabolism. 2023;108(10):2447–2469. — doi:10.1210/clinem/dgad463
- Unfer V, Facchinetti F, Orrù B, Giordani B, Nestler J. Myo-inositol Effects in Women with PCOS: A Meta-Analysis of Randomized Controlled Trials. Endocrine Connections. 2017;6(8):647–658. — doi:10.1530/EC-17-0243
- Legro RS, Brzyski RG, Diamond MP, et al. Letrozole versus Clomiphene for Infertility in the Polycystic Ovary Syndrome (PPCOS II). New England Journal of Medicine. 2014;371(2):119–129. — doi:10.1056/NEJMoa1313517
- Reaven GM. Banting Lecture 1988. Role of Insulin Resistance in Human Disease. Diabetes. 1988;37(12):1595–1607. — doi:10.2337/diab.37.12.1595
- Matthews DR, Hosker JP, Rudenski AS, Naylor BA, Treacher DF, Turner RC. Homeostasis Model Assessment: Insulin Resistance and Beta-Cell Function from Fasting Plasma Glucose and Insulin Concentrations in Man (HOMA). Diabetologia. 1985;28(7):412–419. — doi:10.1007/BF00280883
- Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews. 2018;98(4):2133–2223. — doi:10.1152/physrev.00063.2017
- Knowler WC, Barrett-Connor E, Fowler SE, et al. Reduction in the Incidence of Type 2 Diabetes with Lifestyle Intervention or Metformin (Diabetes Prevention Program). New England Journal of Medicine. 2002;346(6):393–403. — doi:10.1056/NEJMoa012512
- Saltiel AR, Olefsky JM. Inflammatory Mechanisms Linking Obesity and Metabolic Disease. Journal of Clinical Investigation. 2017;127(1):1–4. — doi:10.1172/JCI92035
- Teede HJ, Khomami MB, Morman R, et al. Polyendocrine Metabolic Ovarian Syndrome, the New Name for Polycystic Ovary Syndrome: A Multistep Global Consensus Process. Lancet. 2026;407(10545):2329–2339. — doi:10.1016/S0140-6736(26)00717-8
- Løvvik TS, Carlsen SM, Salvesen Ø, et al. Use of Metformin to Treat Pregnant Women with Polycystic Ovary Syndrome (PregMet2): A Randomised, Double-Blind, Placebo-Controlled Trial. Lancet Diabetes & Endocrinology. 2019;7(4):256–266. — doi:10.1016/S2213-8587(19)30002-6
- Fitz V, Graca S, Mahalingaiah S, et al. Inositol for Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis to Inform the 2023 Update of the International Evidence-based PCOS Guidelines. Journal of Clinical Endocrinology & Metabolism. 2024;109(6):1630–1655. — doi:10.1210/clinem/dgad762
- La Vignera S, Condorelli RA. Efficacy and Safety of Semaglutide in Patients with Polycystic Ovary Syndrome: A Scoping Review. Biomedicines. 2026;14(8):1845. — doi:10.3390/biomedicines14081845
- Clift AK, Reisel D, Johnson H, Sattar N, Huang DR. Weight Loss Outcomes with Tirzepatide in Women with and without Self-Reported Polycystic Ovary Syndrome. Journal of the Endocrine Society. 2026;10(9):bvag177. — doi:10.1210/jendso/bvag177
- Kar E, Yeh J, Efe MA, Çelik HG, Bozdağ G, Baştu E. The Effect of Glucagon-Like Peptide-1 Receptor Agonists versus Metformin on Pregnancy Rates in Women with Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis of Randomized Trials. European Journal of Obstetrics & Gynecology and Reproductive Biology. 2026;327:115499. — doi:10.1016/j.ejogrb.2026.115499
- Kahal H, Kyrou I, Uthman OA, et al. The Prevalence of Obstructive Sleep Apnoea in Women with Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis. Sleep and Breathing. 2020;24(1):339–350. — doi:10.1007/s11325-019-01835-1
- Cooney LG, Lee I, Sammel MD, Dokras A. High Prevalence of Moderate and Severe Depressive and Anxiety Symptoms in Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis. Human Reproduction. 2017;32(5):1075–1091. — doi:10.1093/humrep/dex044
- Brutocao C, Zaiem F, Alsawas M, Morrow AS, Murad MH, Javed A. Psychiatric Disorders in Women with Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis. Endocrine. 2018;62(2):318–325. — doi:10.1007/s12020-018-1692-3
- Barry JA, Azizia MM, Hardiman PJ. Risk of Endometrial, Ovarian and Breast Cancer in Women with Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis. Human Reproduction Update. 2014;20(5):748–758. — doi:10.1093/humupd/dmu012
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: insulin resistance and PCOS
- PubMed: lean PCOS and insulin resistance
- PubMed: metformin and PCOS
- PubMed: myo-inositol in PCOS
- PubMed: GLP-1 agonists and PCOS
- PubMed: letrozole and ovulation induction
- PubMed: spironolactone in PCOS
- PubMed: PCOS and sleep apnea
- PubMed: PCOS and endometrial cancer
- PubMed: PCOS and gestational diabetes
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Infertility
- Exercise and Muscle Insulin Sensitivity
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Hashimoto's Thyroiditis
- Insulin Resistance
- Polycystic Ovary Syndrome
- Reversal Protocol: Diet and Fasting
- Endometriosis
- Obesity
- Inositol
- Glucagon-Like Peptide-1 Receptor Agonists
- Acne
- Testosterone
- Gestational Diabetes
- Fasting Insulin
- Diabetes
- Non-Alcoholic Fatty Liver Disease Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Metformin — the drug page itself: titration schedule, gastrointestinal tolerance, B12 monitoring, and pregnancy safety.