Epigallocatechin Gallate (EGCG) for Heart Health and Cholesterol
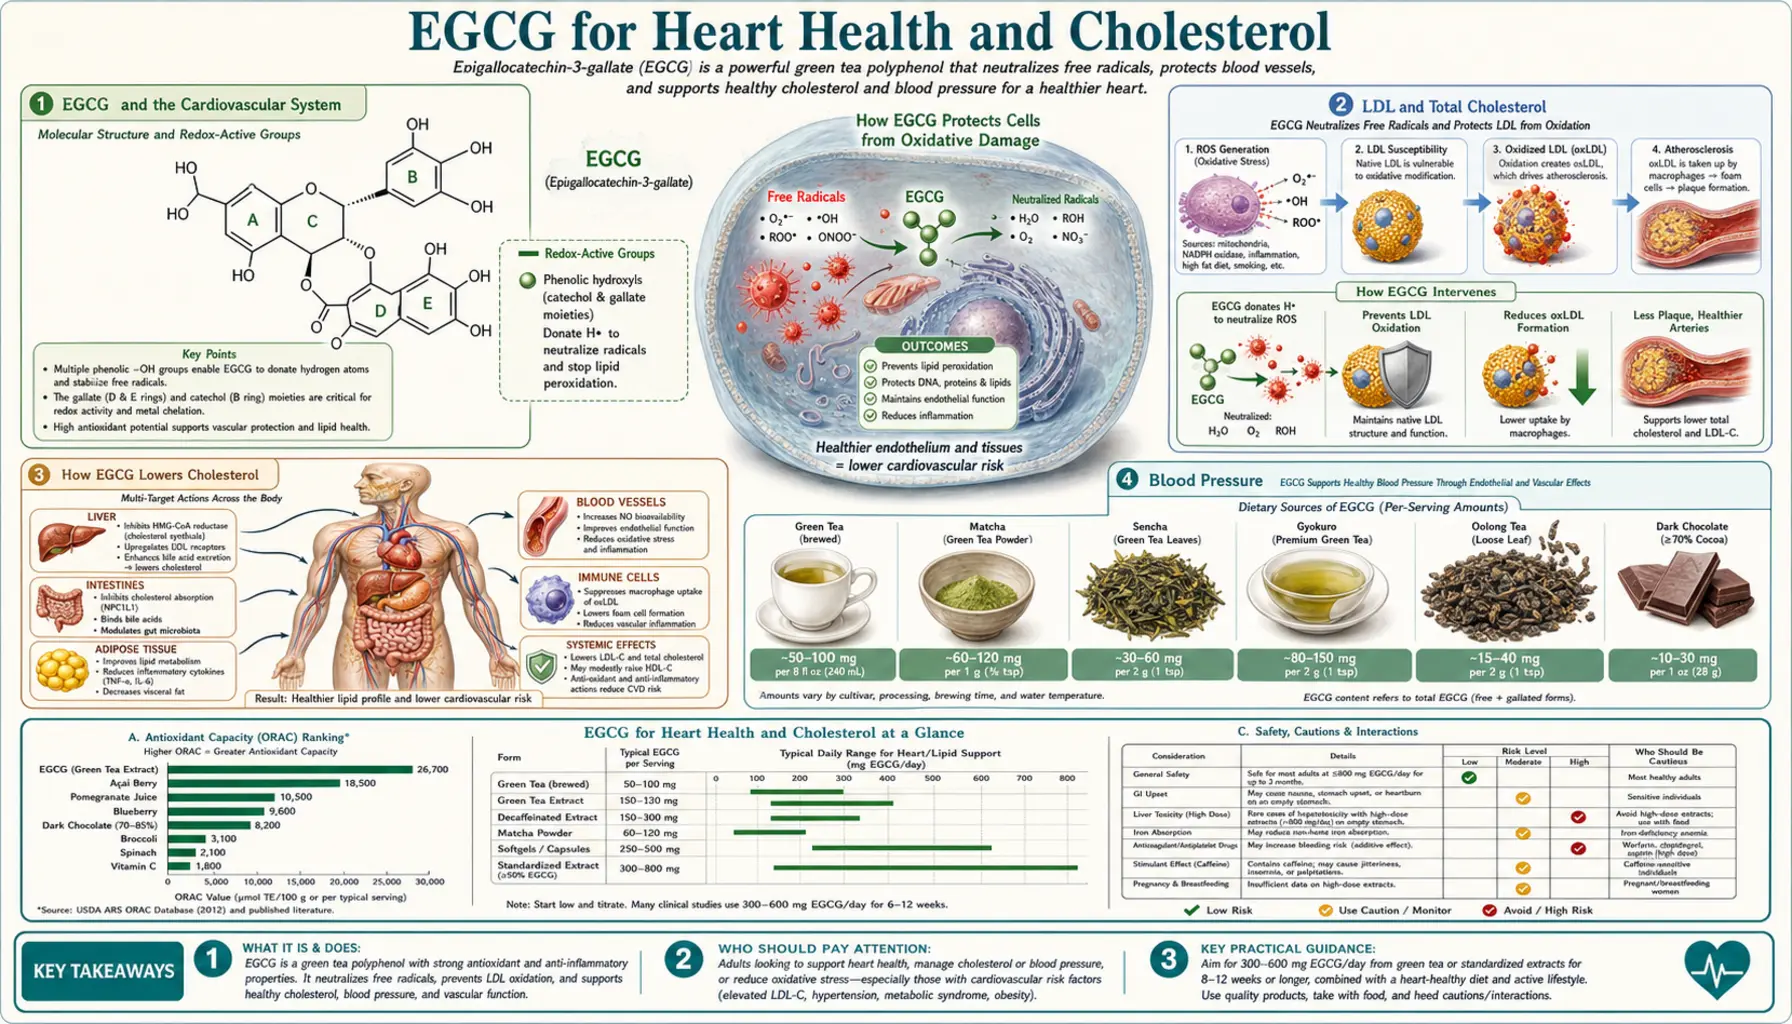
The cardiovascular story is epigallocatechin gallate's strongest and most consistent chapter — though "consistent" still means "small." Pooled randomized trials show green tea catechins nudge low-density lipoprotein (LDL) and total cholesterol down, trim a point or two off blood pressure, and acutely improve the flexibility of blood vessels. In Japan, where green tea is a daily habit, higher intake tracks with lower cardiovascular death. None of these effects is dramatic on its own, but they point in the same protective direction, they are backed by plausible biology, and — when the tea replaces a sugary drink — they come essentially for free. This page lays out what the numbers actually are, how epigallocatechin gallate (EGCG) produces them, and who is most likely to see a benefit.
Table of Contents
- Epigallocatechin Gallate and the Cardiovascular System
- Low-Density Lipoprotein and Total Cholesterol
- How Epigallocatechin Gallate Lowers Cholesterol
- Blood Pressure
- Endothelial Function and Nitric Oxide
- Low-Density Lipoprotein Oxidation and Atherosclerosis
- Population Studies and Cardiovascular Mortality
- Who Is Most Likely to Benefit
- Doses, Extracts and Interactions in the Research
- Key Research Papers
- Connections
- Featured Videos
Epigallocatechin Gallate and the Cardiovascular System
Cardiovascular disease develops through a handful of interacting processes: cholesterol-carrying particles infiltrate and inflame the artery wall, those particles become oxidized and are engulfed by immune cells to form plaque, blood pressure stresses the vessel lining, and the endothelium (the delicate single-cell layer lining every blood vessel) loses its ability to dilate on demand. Epigallocatechin gallate touches several of these processes at once — it lowers circulating low-density lipoprotein a little, reduces low-density lipoprotein oxidation, improves endothelial dilation, and modestly lowers blood pressure. Because it works on multiple small levers rather than one big one, the individual effects are modest but the direction is uniformly favorable.
The important framing, kept honest throughout this page: the human evidence is strongest for surrogate markers — cholesterol numbers, blood-pressure readings, vessel-dilation measurements — and weaker for hard outcomes like heart attacks and deaths, which come mainly from observational cohorts that cannot fully rule out the healthy habits of tea drinkers. The effects measured for epigallocatechin gallate are small next to those of statins, blood-pressure medication or lifestyle change, and the research treats it as an addition to them, not a replacement.
Low-Density Lipoprotein and Total Cholesterol
The cholesterol effect is the best-quantified benefit because it has been pooled across many randomized trials:
- Zheng 2011 (American Journal of Clinical Nutrition) pooled 14 randomized controlled trials and found green tea intake significantly lowered fasting total cholesterol (by roughly 7 mg/dL) and low-density lipoprotein cholesterol (by a few mg/dL), with no meaningful change in protective high-density lipoprotein (HDL).
- Kim 2011 (Journal of the American Dietetic Association) reached the same conclusion in a separate systematic review and meta-analysis of 20 trials (1,415 people): green tea catechins at 145 to 3,000 mg a day, taken for 3 to 24 weeks, lowered total cholesterol by 5.46 mg/dL and low-density lipoprotein cholesterol by 5.30 mg/dL, with no significant change in high-density lipoprotein cholesterol or triglycerides.
- Onakpoya 2014 confirmed the lipid effect alongside a blood-pressure effect in a further meta-analysis.
- Xu 2020 (Nutrition Journal), a larger pooled analysis of 31 randomized trials with 3,321 people, found green tea lowered total cholesterol by 4.66 mg/dL and low-density lipoprotein cholesterol by 4.55 mg/dL compared with control, with no effect on high-density lipoprotein cholesterol or triglycerides, in both normal-weight and overweight or obese people.
A few mg/dL of low-density lipoprotein is a small shift — a statin routinely lowers low-density lipoprotein by 30–50%, many times more. But cholesterol operates on a continuous risk curve, so even a small population-wide reduction is not meaningless, and it stacks with the other cardiovascular effects. The realistic read: in these trials green tea catechins are a minor lipid-lowering nudge, many times smaller than the effect of cholesterol medication. See our Cholesterol Management page for the full picture, and the Lipid Panel page for the blood test that measures these numbers.
How Epigallocatechin Gallate Lowers Cholesterol
Epigallocatechin gallate lowers circulating cholesterol mainly in the gut, before the cholesterol is ever absorbed:
- Interfering with micelle formation — dietary cholesterol must be packaged into tiny fat droplets called micelles to be absorbed across the intestinal wall. Epigallocatechin gallate disrupts micelle formation and precipitates cholesterol, so less is taken up and more passes out in the stool.
- Binding bile acids — catechins bind bile acids in the intestine and promote their excretion. The liver then has to pull cholesterol out of the blood to synthesize replacement bile acids, lowering circulating low-density lipoprotein. This is the same broad mechanism used by bile-acid-sequestrant drugs, though far gentler.
- Upregulating the low-density lipoprotein receptor — in laboratory studies epigallocatechin gallate increases expression of the liver's low-density lipoprotein receptor, the "vacuum cleaner" that clears low-density lipoprotein from the bloodstream.
Because the dominant mechanism happens in the gut, the cholesterol effect depends on catechins being present in the intestine when food is — so tea taken with or around meals puts the catechins where this mechanism works.
Blood Pressure
Green tea catechins produce a small but real reduction in blood pressure:
- Khalesi 2014 (European Journal of Nutrition) pooled 13 randomized trials and found green tea lowered systolic blood pressure by 2.08 mmHg and diastolic by 1.71 mmHg. The falls were larger in studies whose participants started with an average systolic pressure of 130 mmHg or more, and in studies that used green tea extract.
- Peng 2014 (Scientific Reports), a meta-analysis of 13 randomized controlled trials, pooling 1,367 people, found a comparable systolic reduction of 1.98 mmHg and a diastolic reduction of 1.92 mmHg. In its subgroup analyses the effect showed up only in studies using a low dose of green tea polyphenols, in longer studies, or in studies that ruled out the confounding effect of caffeine.
- Bogdanski 2012 found that green tea extract in obese, hypertensive patients reduced blood pressure while also improving inflammatory markers, insulin resistance, and low-density lipoprotein — a nice demonstration of epigallocatechin gallate hitting several risk factors at once in the people most likely to benefit.
A reduction of about 2 mmHg sounds trivial, but at the population level even a 2 mmHg drop in average systolic pressure is associated with a measurable fall in stroke and heart-disease mortality. Again, epigallocatechin gallate is a small lever — not a substitute for antihypertensive medication in someone with established hypertension, but one small part of a whole-diet pattern.
Endothelial Function and Nitric Oxide
Some of the most striking epigallocatechin gallate data come from studies of endothelial function — the ability of an artery to relax and widen when blood flow increases, measured as flow-mediated dilation (FMD) in the brachial artery. Healthy endothelium releases nitric oxide, a gas that signals the vessel to dilate; damaged endothelium cannot, and impaired FMD is an early warning sign of cardiovascular disease.
- Widlansky 2007 (Journal of the American College of Nutrition) gave a single dose of epigallocatechin gallate to patients with established coronary artery disease and found it acutely improved (reversed) their impaired flow-mediated dilation within a couple of hours.
- Alexopoulos 2008 found the same acute improvement in FMD in healthy volunteers after drinking green tea, and showed the effect was specific to the tea rather than its caffeine or water content.
The mechanism is that epigallocatechin gallate increases the activity of endothelial nitric oxide synthase (eNOS), the enzyme that makes nitric oxide, partly by activating the same PI3-kinase/Akt signaling that insulin uses. More nitric oxide means more vessel dilation, lower resistance, and less mechanical stress on the artery wall. These are acute effects — measured hours after a dose — and while they are encouraging mechanistically, whether they translate into fewer long-term events has not been proven in randomized outcome trials.
Low-Density Lipoprotein Oxidation and Atherosclerosis
Low-density lipoprotein cholesterol is far more dangerous once it has been oxidized: oxidized low-density lipoprotein is what immune cells engulf to become the foam cells that build arterial plaque. Epigallocatechin gallate is a potent antioxidant, and one of its plausible cardiovascular contributions is protecting low-density lipoprotein particles from oxidation.
Nagao's 2005 trial measured malondialdehyde-modified low-density lipoprotein — a marker of oxidized low-density lipoprotein — and found it fell in men consuming catechin-rich tea, alongside the reduction in body fat. Lower oxidized low-density lipoprotein should, in principle, slow the earliest steps of atherosclerosis, the plaque-building process that underlies most heart attacks and strokes. This anti-oxidation mechanism overlaps heavily with the cellular-health story covered on the Antioxidant & Cellular Health page; here it is worth noting simply as one more small, biologically-sensible way green tea catechins point in a heart-protective direction.
Population Studies and Cardiovascular Mortality
The largest human signal for green tea and the heart comes not from supplement trials but from population cohorts:
- The Ohsaki Study (Kuriyama 2006, JAMA) followed more than 40,000 Japanese adults (40,530 people aged 40 to 79) for up to 11 years for death from all causes and up to 7 years for cardiovascular death. Those who drank five or more cups of green tea a day had notably lower cardiovascular mortality than those drinking less than one cup — the association was strongest for stroke and was more pronounced in women. Interestingly, green tea was linked to lower cardiovascular death but not to lower cancer death in that cohort.
Cohort studies like this cannot prove cause and effect. Heavy green tea drinkers in Japan may differ in other ways — diet, smoking, activity — and researchers can only partly adjust for that. But the Ohsaki signal is large, biologically consistent with the mechanistic and surrogate-marker data, and reinforced by similar findings in other Japanese and Chinese cohorts. Taken together, the honest conclusion is: regular green tea consumption is associated with better cardiovascular outcomes, the biology supports a genuine contribution, but proof at the level of a randomized outcome trial does not yet exist.
Who Is Most Likely to Benefit
Across the cholesterol, blood-pressure, and endothelial data, one pattern repeats: the benefit is largest in people who start with a problem. The clearest responders are:
- People with elevated low-density lipoprotein or total cholesterol.
- People with high-normal or elevated blood pressure who are not yet on medication (Khalesi 2014 found larger falls in studies whose participants started at an average systolic pressure of 130 mmHg or more).
- People with metabolic syndrome or central obesity, in whom green tea can improve several risk factors at once.
- People replacing sugary drinks with unsweetened green tea — here the benefit is partly the tea and partly the sugar they no longer drink.
In someone who is already lean, with normal blood pressure and healthy cholesterol, there is little to improve, so little measurable cardiovascular change is expected from adding epigallocatechin gallate. That is not a failure of the compound; it is the expected shape of a small, corrective effect.
Doses, Extracts and Interactions in the Research
- The beverage. Three to five cups of unsweetened green tea a day delivers a meaningful catechin dose with essentially no safety concern, and matches what the cardiovascular cohort data actually studied.
- Extracts — the cardiovascular gain from high-dose extracts taken on an empty stomach is marginal while the liver risk rises; liver-injury reports involve concentrated extracts, mostly taken fasting (see Safety & Liver).
- Blood-pressure and heart medications — green tea can interact with the beta-blocker nadolol (reducing its effect) and, in vitamin-K-containing preparations, with the anticoagulant warfarin.
- Prescribed therapy. Epigallocatechin gallate is complementary. In established coronary artery disease or diagnosed hypertension or high cholesterol, the effects measured for green tea are small next to those of proven treatment; the research treats it as an add-on, not a replacement.
- Caffeine. Green tea's caffeine can raise heart rate or disturb sleep in some people. A shorter steep and cooler water give a lower-caffeine cup, while a caffeine-free extract also strips part of the benefit.
Key Research Papers
- Zheng XX et al. (2011). Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am J Clin Nutr — PubMed PMID: 21715508
- Kim A et al. (2011). Green tea catechins decrease total and low-density lipoprotein cholesterol: a systematic review and meta-analysis. J Am Diet Assoc — PubMed PMID: 22027055
- Onakpoya I et al. (2014). The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis — PubMed PMID: 24675010
- Khalesi S et al. (2014). Green tea catechins and blood pressure: a systematic review and meta-analysis of randomised controlled trials. Eur J Nutr — PubMed PMID: 24861099
- Peng X et al. (2014). Effect of green tea consumption on blood pressure: a meta-analysis of 13 randomized controlled trials. Sci Rep — PubMed PMID: 25176280
- Bogdanski P et al. (2012). Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, hypertensive patients. Nutr Res — PubMed PMID: 22749178
- Widlansky ME et al. (2007). Acute EGCG supplementation reverses endothelial dysfunction in patients with coronary artery disease. J Am Coll Nutr — PubMed PMID: 17536120
- Alexopoulos N et al. (2008). The acute effect of green tea consumption on endothelial function in healthy individuals. Eur J Cardiovasc Prev Rehabil — PubMed PMID: 18525384
- Kuriyama S et al. (2006). Green tea consumption and mortality due to cardiovascular disease, cancer, and all causes in Japan: the Ohsaki study. JAMA — PubMed PMID: 16968850
- Nagao T et al. (2005). Ingestion of a tea rich in catechins leads to a reduction in body fat and malondialdehyde-modified LDL in men. Am J Clin Nutr — PubMed PMID: 15640470
- Xu R et al. (2020). Effect of green tea consumption on blood lipids: a systematic review and meta-analysis of randomized controlled trials. Nutr J — PubMed PMID: 32434539
- Hodgson JM et al. (2013). Short-term effects of polyphenol-rich black tea on blood pressure in men and women. Food Funct — PubMed PMID: 23038021
PubMed Topic Searches
External Resources
Connections
- Epigallocatechin Gallate Overview
- Epigallocatechin Gallate Benefits Hub
- Epigallocatechin Gallate for Metabolism & Weight
- Epigallocatechin Gallate Antioxidant & Cellular Health
- Epigallocatechin Gallate Safety & Liver
- Green Tea
- Cholesterol Management
- Hypertension
- Atherosclerosis
- Coronary Artery Disease
- Lipid Panel
- High-Sensitivity C-Reactive Protein
- Anthocyanins
- Hesperidin
- All Antioxidants