Lycopene for Prostate Health
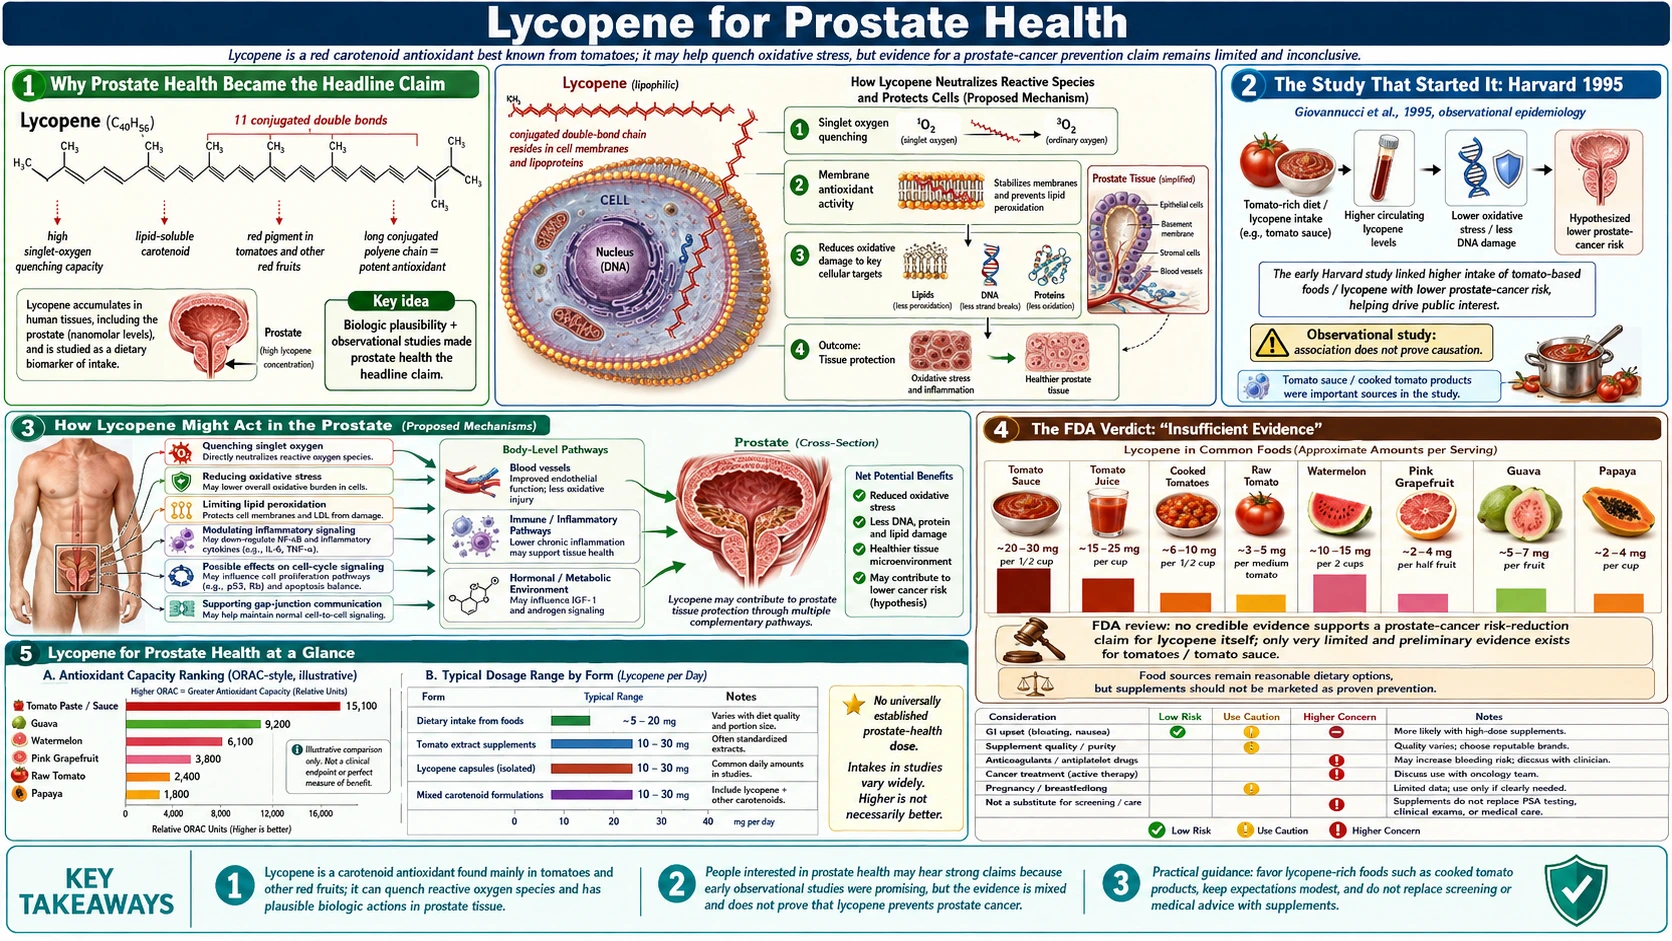
Prostate health is where lycopene became famous — and where the gap between hype and proof is widest. The story began with a genuinely striking 1995 Harvard cohort finding that men who ate the most tomato products had a lower risk of prostate cancer. Two decades of follow-up research told a more complicated story: pooled observational studies report a modest association, the U.S. Food and Drug Administration's evidence review (published in 2007) found no credible evidence linking lycopene intake to lower prostate-cancer risk and only very limited evidence for tomatoes, a large study of serum lycopene within the Prostate Cancer Prevention Trial found no association, and the few randomized trials are too small to settle the question. This page sets out that mixed evidence.
Table of Contents
- Why Prostate Health Became the Headline Claim
- The Study That Started It: Harvard 1995
- How Lycopene Might Act in the Prostate
- The FDA Verdict: “Insufficient Evidence”
- Serum Lycopene in the Prostate Cancer Prevention Trial: A Null Result
- What the Meta-Analyses Actually Show
- Benign Prostatic Hyperplasia and Urinary Symptoms
- Whole Tomatoes vs Lycopene Pills
- Summary of the Evidence
- Key Research Papers
- Connections
- Featured Videos
Why Prostate Health Became the Headline Claim
Prostate cancer is the most commonly diagnosed non-skin cancer in men in the United States, and lycopene is, with all-trans beta-carotene, one of the two predominant carotenoids found in human prostate tissue (Clinton and colleagues, 1996). Those two facts made the prostate an obvious place to look for a lycopene effect, and through the late 1990s a growing body of epidemiology and laboratory work drew wide public attention to tomatoes and lycopene.
The uncertainty covered on this page is narrower than it may first appear. Tomatoes are low-calorie whole foods that form part of Mediterranean-style, plant-forward dietary patterns; the open question is specifically whether isolated lycopene, or lycopene as a measurable biomarker, independently prevents or slows prostate cancer. On that narrow question, the evidence is mixed.
The Study That Started It: Harvard 1995
In 1995, Edward Giovannucci and colleagues published an analysis of the Health Professionals Follow-Up Study — a large prospective cohort of nearly 48,000 U.S. male health professionals whose diets had been tracked since 1986. Among 46 fruits and vegetables examined, tomato-based foods stood out. Of the 46, four were significantly associated with lower prostate-cancer risk, and three of those — tomato sauce, tomatoes and pizza — were primary sources of lycopene. Of the carotenoids measured, only lycopene intake was related to lower risk (relative risk 0.79 for the highest versus lowest fifth of intake). Combined intake of tomatoes, tomato sauce, tomato juice and pizza, which supplied 82% of lycopene intake, was associated with lower risk of prostate cancer (relative risk 0.65 for more than 10 versus fewer than 1.5 servings a week) and of advanced prostate cancer (0.47). The authors concluded that lycopene or other compounds in tomatoes may reduce prostate-cancer risk.
This large prospective cohort study launched an entire research field. What a study like this can and cannot show matters here. It is observational: it shows an association between a dietary pattern and an outcome, not that lycopene caused the lower risk. Men who eat a lot of tomato sauce may differ in dozens of other ways — overall diet quality, exercise, body weight, screening behavior — and while good cohort studies statistically adjust for many of these, they cannot rule out all of them. The 1995 finding was a compelling reason to investigate further, not a proof of benefit.
How Lycopene Might Act in the Prostate
Laboratory research has proposed several plausible mechanisms by which lycopene could influence prostate biology. These are real, published findings from cell and animal models — but a mechanism that works in a petri dish is a hypothesis about humans, not a demonstration.
- Antioxidant protection of DNA — oxidative damage to prostate-cell DNA is one route to malignant transformation. In a whole-food intervention without a control group, 32 men with localized prostate cancer ate tomato-sauce pasta dishes (30 mg of lycopene a day) for three weeks before prostatectomy; oxidative DNA damage in their white blood cells fell from before to after, and their prostate tissue showed less oxidative DNA damage than tissue from seven randomly selected prostate-cancer patients who had not taken part (Chen L et al., 2001). The authors called for a larger study with a control group.
- IGF-1 signaling — insulin-like growth factor 1 is a growth-promoting hormone linked to prostate cancer risk. In 112 hospitalized men in Athens without cancer, eating more cooked tomatoes was associated with lower serum IGF-1 (Mucci and colleagues, 2001).
- Androgen and growth-factor signaling — in a rat prostate-tumor model, lycopene supplementation down-regulated 5-alpha-reductase (the enzyme that activates testosterone in the prostate), androgen-responsive genes, and local IGF-1 and interleukin-6 expression (Siler and colleagues, 2004); that was an animal study. Reviews also describe cell experiments in which lycopene induced cell death and slowed the growth of cancer cells (van Breemen and Pajkovic, 2008).
- Anti-angiogenesis — tumors need new blood vessels to grow. A 2014 analysis of 49,898 men in the Health Professionals Follow-Up Study (Zu K et al.) found that higher lycopene intake was associated with lower risk of lethal prostate cancer (hazard ratio 0.72, top versus bottom fifth) and with prostate tumors showing less angiogenic (blood-vessel-forming) potential; the authors suggested lethal disease may be the more relevant outcome for lycopene.
An important nuance comes from animal work. In a 2003 rat study designed to test the prostate hypothesis rigorously, Boileau and colleagues fed rats either tomato powder, purified lycopene, or a control diet during chemically-induced prostate carcinogenesis. Rats fed tomato powder had a lower risk of death with prostate cancer than controls; rats fed purified lycopene did not differ from controls. The authors suggested that tomato products contain compounds besides lycopene that affect prostate carcinogenesis. That was an animal study, but it is often cited when whole tomatoes and isolated lycopene are compared.
The FDA Verdict: “Insufficient Evidence”
In 2004, the U.S. Food and Drug Administration received two petitions for qualified health claims linking tomatoes and lycopene to reduced risk of some cancers. The FDA carried out an evidence-based review, and in 2007 Kavanaugh, Trumbo, and Ellwood published the agency's findings in the Journal of the National Cancer Institute.
The FDA found no credible evidence to support an association between lycopene intake and reduced risk of prostate, lung, colorectal, gastric, breast, ovarian, endometrial, or pancreatic cancer. It also found no credible evidence for an association between tomato consumption and reduced risk of lung, colorectal, breast, cervical, or endometrial cancer, and very limited evidence for an association between tomato consumption and reduced risk of prostate, ovarian, gastric, and pancreatic cancers. The agency's November 2005 letters on the two petitions accordingly covered only heavily qualified tomato claims.
In plain terms: the U.S. food regulator reviewed the evidence available at the time and concluded it did not support a claim that lycopene lowers cancer risk.
Serum Lycopene in the Prostate Cancer Prevention Trial: A Null Result
Some of the strongest evidence against an independent lycopene effect came in 2011 from Kristal and colleagues, who ran a nested case-control study (1,683 cases and 1,751 controls) within the Prostate Cancer Prevention Trial — a placebo-controlled trial of finasteride in which cancer was confirmed by biopsy — to test whether serum lycopene concentration (an objective blood biomarker, not a diet questionnaire) predicted prostate cancer risk. Blood biomarkers avoid much of the recall error and confounding that weakens food-frequency studies.
The result was null: there was no association between serum lycopene and prostate cancer risk, for low-grade or high-grade (Gleason 7–10 and 8–10) disease. The authors concluded that the study does not support a role for lycopene in prostate cancer prevention, and that early studies linking dietary lycopene with lower risk had not been replicated in studies using serum biomarkers.
What the Meta-Analyses Actually Show
Meta-analyses pool many studies to find the average signal. For lycopene and prostate cancer they have produced a mixed picture:
- Etminan et al. (2004) pooled 21 observational studies and found a modest reduction in prostate cancer risk with high intake of tomato products — relative risk 0.81 for cooked tomato products and 0.89 (confidence interval reaching 1.00) for raw tomato; the authors described the effect as modest and restricted to high intakes.
- Cochrane Review, Ilic et al. (2011) — a systematic review limited to randomized controlled trials — found three trials with 154 participants in total, two of them at high risk of bias, and concluded that there was insufficient evidence to either support or refute lycopene for the prevention of prostate cancer.
- Chen P et al. (2015) pooled 26 studies; across all of them, higher lycopene intake showed only a non-significant trend toward lower risk (P = 0.078), which became significant when one study was removed or only high-quality studies were analyzed. Higher circulating lycopene was significantly associated with lower risk, and the dose-response analysis found a linear association for intake between 9 and 21 mg a day.
- Rowles et al. (2017) pooled 42 studies and found higher dietary lycopene and higher circulating lycopene each associated with lower prostate cancer risk (relative risk 0.88 for each), but no association with advanced prostate cancer.
- Rowles et al. (2018), a separate dose-response meta-analysis of 30 studies of tomato foods by the same group, found higher total tomato consumption associated with lower prostate cancer risk (relative risk 0.81), and likewise for cooked tomatoes and sauces (0.84), but no association for raw tomatoes (0.96).
Taken together: pooled observational studies associate higher intake of tomato products and higher dietary or blood lycopene with modestly lower prostate cancer risk, though not lower risk of advanced disease in the 2017 analysis; one large biomarker study within a randomized trial found no association; and randomized trials of lycopene are too few and too small to show whether it prevents prostate cancer. None of these studies establishes that lycopene itself is the cause.
Benign Prostatic Hyperplasia and Urinary Symptoms
Prostate cancer is not the only prostate concern. Benign prostatic hyperplasia (BPH) — the non-cancerous enlargement of the prostate that causes urinary frequency, weak stream, and nighttime urination in many older men — has been studied as a separate lycopene target.
In a randomized pilot trial of 40 men with BPH (Schwarz and colleagues, 2008), 15 mg/day of lycopene for six months lowered PSA while it did not change in the placebo group; the prostate enlarged in the placebo group but not in the lycopene group, and urinary symptom scores improved in both groups, more so with lycopene. A 2023 review (Natali et al.) describes a tomato-based supplement enriched with olive polyphenols that the authors themselves developed (two of them declared a financial interest); it reports that the preparation improved urinary symptoms in placebo-controlled studies in men with BPH. The BPH evidence is smaller and less mature than the cancer literature — preliminary rather than proven.
Whole Tomatoes vs Lycopene Pills
Direct human comparisons of whole tomato foods with isolated lycopene supplements are scarce. The findings usually cited in favor of whole foods are:
- The Boileau rat study: tomato powder lowered the risk of death with prostate cancer; purified lycopene did not (an animal study).
- The Chen whole-food intervention: men eating tomato-sauce dishes before surgery had lower oxidative DNA damage in white blood cells afterward, and less in prostate tissue than non-participating patients (an uncontrolled study using food, not a supplement comparison).
- Meta-analyses (Etminan 2004; Rowles 2018) find the association with lower risk for cooked tomato products, and a weaker one (Etminan) or none (Rowles 2018) for raw tomatoes.
Boileau and colleagues (2003) and Giovannucci (1999) suggested that other compounds in tomatoes, possibly acting together, may contribute; and processing and dietary fat change how much lycopene is absorbed (see the Sources & Bioavailability page).
Summary of the Evidence
- Tomato foods: pooled observational studies link higher intake of tomato products, especially cooked tomatoes and sauces, with modestly lower prostate cancer risk; cooked and processed tomato products are concentrated lycopene sources.
- Lycopene supplements: the FDA found no credible evidence linking lycopene intake to lower prostate cancer risk, a large biomarker study found no association, and the Cochrane review found the trials insufficient to support or refute lycopene for prevention. Isolated lycopene is not a proven cancer preventive.
- Food versus isolated lycopene: the clearest comparison is an animal study, in which tomato powder lowered prostate-cancer death and purified lycopene did not.
- BPH: one small randomized trial of lycopene reported less prostate growth and lower PSA; the evidence is preliminary.
- Medical care: lycopene is studied as a dietary factor, not a therapy; decisions about prostate cancer screening, PSA testing, and BPH treatment belong with a clinician.
Key Research Papers
- Giovannucci E, Ascherio A, Rimm EB, et al. (1995). Intake of carotenoids and retinol in relation to risk of prostate cancer. Journal of the National Cancer Institute — PubMed PMID: 7473833
- Giovannucci E (1999). Tomatoes, tomato-based products, lycopene, and cancer: review of the epidemiologic literature. Journal of the National Cancer Institute — PubMed PMID: 10050865
- Clinton SK, Emenhiser C, Schwartz SJ, et al. (1996). cis-trans lycopene isomers, carotenoids, and retinol in the human prostate. Cancer Epidemiology, Biomarkers & Prevention — PubMed PMID: 8896894
- Chen L, Stacewicz-Sapuntzakis M, Duncan C, et al. (2001). Oxidative DNA damage in prostate cancer patients consuming tomato sauce-based entrees as a whole-food intervention. Journal of the National Cancer Institute — PubMed PMID: 11752012
- Boileau TW, Liao Z, Kim S, et al. (2003). Prostate carcinogenesis in N-methyl-N-nitrosourea (NMU)-testosterone-treated rats fed tomato powder, lycopene, or energy-restricted diets. Journal of the National Cancer Institute — PubMed PMID: 14600090
- Etminan M, Takkouche B, Caamaño-Isorna F (2004). The role of tomato products and lycopene in the prevention of prostate cancer: a meta-analysis of observational studies. Cancer Epidemiology, Biomarkers & Prevention — PubMed PMID: 15006906
- Kavanaugh CJ, Trumbo PR, Ellwood KC (2007). The U.S. Food and Drug Administration's evidence-based review for qualified health claims: tomatoes, lycopene, and cancer. Journal of the National Cancer Institute — PubMed PMID: 17623802
- Kristal AR, Till C, Platz EA, et al. (2011). Serum lycopene concentration and prostate cancer risk: results from the Prostate Cancer Prevention Trial. Cancer Epidemiology, Biomarkers & Prevention — PubMed PMID: 21335507
- Ilic D, Forbes KM, Hassed C (2011). Lycopene for the prevention of prostate cancer. Cochrane Database of Systematic Reviews — PubMed PMID: 22071840
- Zu K, Mucci L, Rosner BA, et al. (2014). Dietary lycopene, angiogenesis, and prostate cancer: a prospective study in the prostate-specific antigen era. Journal of the National Cancer Institute — PubMed PMID: 24463248
- Chen P, Zhang W, Wang X, et al. (2015). Lycopene and risk of prostate cancer: a systematic review and meta-analysis. Medicine (Baltimore) — PubMed PMID: 26287411
- Rowles JL 3rd, Ranard KM, Applegate CC, et al. (2018). Processed and raw tomato consumption and risk of prostate cancer: a systematic review and dose-response meta-analysis. Prostate Cancer and Prostatic Diseases — PubMed PMID: 29317772
- Rowles JL 3rd, Ranard KM, Smith JW, An R, Erdman JW Jr (2017). Increased dietary and circulating lycopene are associated with reduced prostate cancer risk: a systematic review and meta-analysis. Prostate Cancer and Prostatic Diseases — PubMed PMID: 28440323
- Schwarz S, Obermüller-Jevic UC, Hellmis E, Koch W, Jacobi G, Biesalski HK (2008). Lycopene inhibits disease progression in patients with benign prostate hyperplasia. Journal of Nutrition — PubMed PMID: 18156403
- Mucci LA, Tamimi R, Lagiou P, Trichopoulou A, Benetou V, Spanos E, Trichopoulos D (2001). Are dietary influences on the risk of prostate cancer mediated through the insulin-like growth factor system? BJU International — PubMed PMID: 11412218
- Siler U, Barella L, Spitzer V, Schnorr J, Lein M, Goralczyk R, Wertz K (2004). Lycopene and vitamin E interfere with autocrine/paracrine loops in the Dunning prostate cancer model. FASEB Journal — PubMed PMID: 15084515
- Natali PG, Piantelli M, Minacori M, et al. (2023). Improving whole tomato transformation for prostate health: benign prostate hypertrophy as an exploratory model. International Journal of Molecular Sciences — PubMed PMID: 36982868
- van Breemen RB, Pajkovic N (2008). Multitargeted therapy of cancer by lycopene. Cancer Letters — PubMed PMID: 18585855