Serine as a Glycine Source — SHMT and One-Carbon Metabolism
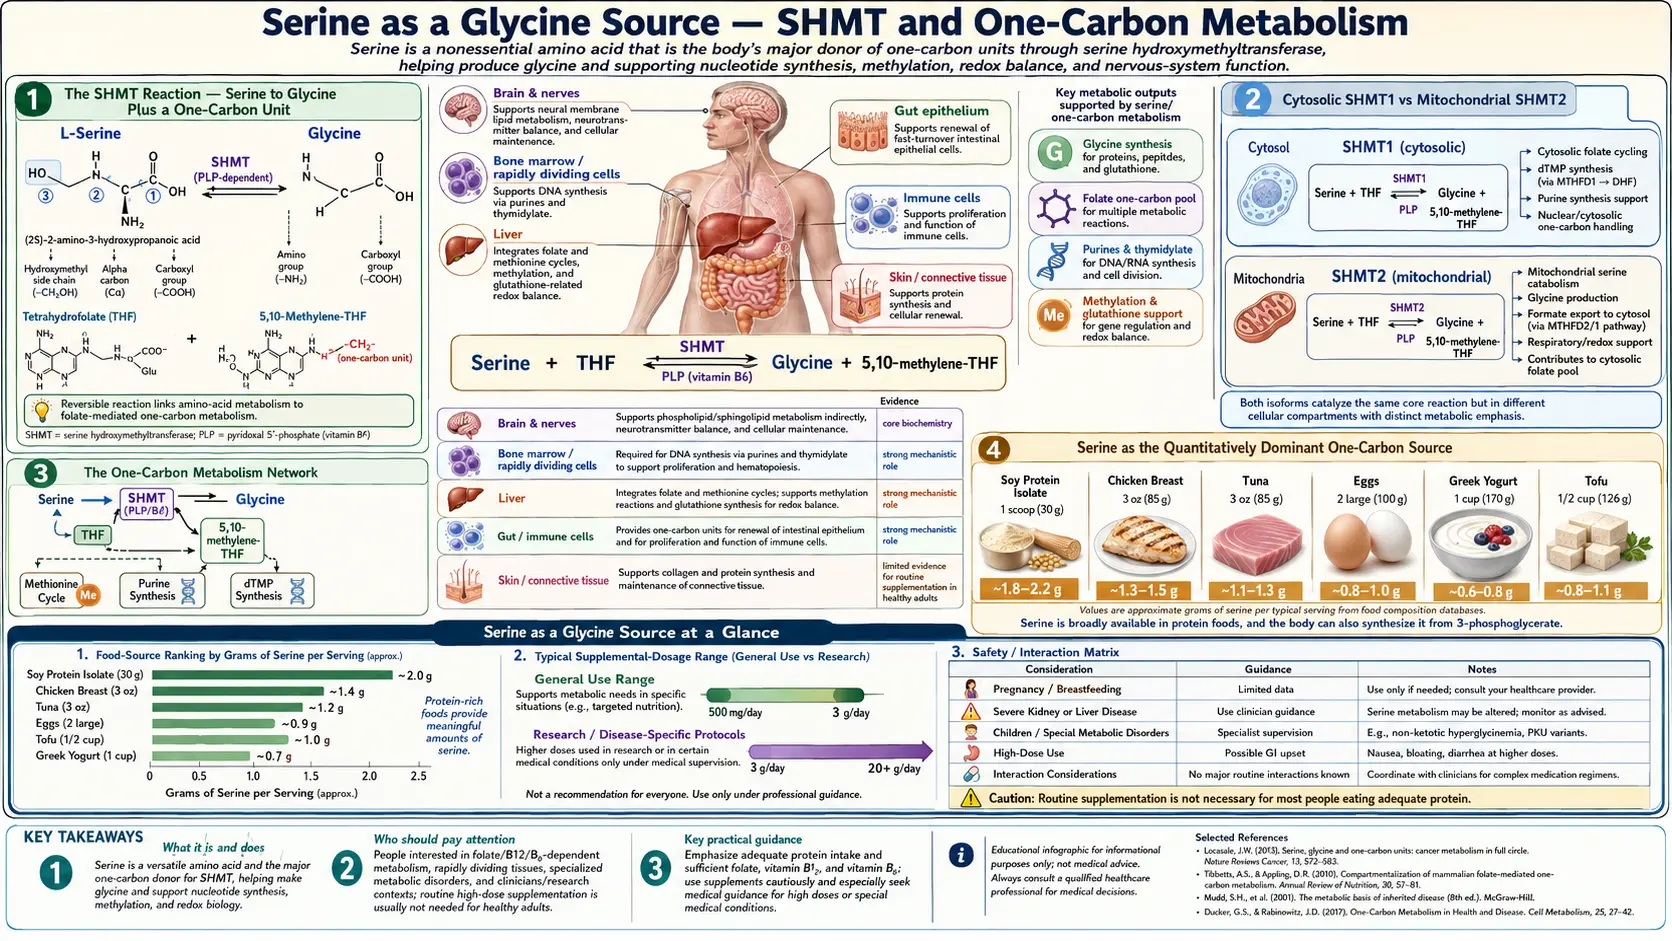
Serine and glycine are interconvertible in a single enzyme reaction catalyzed by serine hydroxymethyltransferase (SHMT). The reaction does two jobs at once: it generates glycine from serine, and it transfers a one-carbon unit from serine to tetrahydrofolate, feeding the entire folate-mediated methylation network. This is the quantitatively dominant source of one-carbon units in human cells, and the rate at which serine flows through SHMT influences DNA methylation, neurotransmitter synthesis, glutathione production, homocysteine clearance, and red-blood-cell production. It is also the body's main glycine supply: glycine has no Recommended Dietary Allowance (RDA), and one analysis estimates that synthesis from serine provides more than 85% of the glycine the body makes — although the same analysis argues that this synthesis plus diet still falls short of total need. This deep-dive walks through the SHMT reaction, the folate cycle interface, the methylation network, and the clinical implications — from cancer metabolism to methylenetetrahydrofolate reductase (MTHFR) variants to the dietary glycine question.
Table of Contents
- The SHMT Reaction — Serine to Glycine Plus a One-Carbon Unit
- Cytosolic SHMT1 vs Mitochondrial SHMT2
- The One-Carbon Metabolism Network
- Serine as the Quantitatively Dominant One-Carbon Source
- Interface with the Methionine / S-Adenosylmethionine Methylation Cycle
- The Glycine Cleavage System — Glycine as Secondary One-Carbon Source
- Why Dietary Glycine Deficiency Rarely Produces Symptoms
- SHMT and Cancer Metabolism — The Drugging Strategy
- Methylenetetrahydrofolate Reductase Variants and the Methylation-Cycle Genetics
- Clinical Implications — How Glycine and Serine Supplements Are Used
- Key Research Papers
- Connections
- Featured Videos
The SHMT Reaction — Serine to Glycine Plus a One-Carbon Unit
Serine hydroxymethyltransferase (SHMT, also called serine transhydroxymethylase, EC 2.1.2.1) catalyzes the reversible reaction:
L-serine + tetrahydrofolate (THF) ⇌ glycine + 5,10-methylenetetrahydrofolate (5,10-CH2-THF) + H2O
The reaction does two things simultaneously, and the elegance of the chemistry is worth a moment of attention:
- Cleavage of serine — the hydroxymethyl group at the β-carbon of serine is broken off, converting serine to glycine
- Transfer of the hydroxymethyl carbon to tetrahydrofolate — the released CH2OH unit is captured by THF, producing 5,10-methylene-THF, the activated one-carbon donor that feeds the rest of folate metabolism
The enzyme requires pyridoxal-5'-phosphate (PLP, the active form of vitamin B6) as cofactor. PLP forms a Schiff base with the α-amino group of serine, and the resulting structure stabilizes the carbanion intermediate that breaks the Cα-Cβ bond. Vitamin B6 deficiency therefore reduces SHMT activity in vivo and impairs the serine-to-glycine and serine-to-folate flux, which has secondary consequences for methylation status and DNA synthesis.
The reaction is reversible in principle (glycine plus 5,10-methylene-THF could in theory regenerate serine), and the direction in any given tissue depends on the relative concentrations of the four reactants and on cellular demand. In most cells under most conditions, the reaction runs in the forward direction (serine to glycine) because cellular demand for one-carbon units and glycine exceeds demand for serine, and because parallel pathways consume the products. Whole-body tracer measurements in rodents, however, found the net flux running the other way, from glycine to serine (McBride 2024, described below).
The thermodynamics make SHMT one of the central control points of one-carbon metabolism. The standard free energy of the reaction is close to zero, so flux direction is determined by mass action. Cancer cells, which have enormous demand for one-carbon units to support DNA synthesis, drive the reaction strongly forward (consuming serine, producing glycine plus 5,10-methylene-THF). This has therapeutic implications discussed in the cancer metabolism section below.
Cytosolic SHMT1 vs Mitochondrial SHMT2
Mammalian cells express two SHMT isoforms encoded by separate genes:
- SHMT1 (cytosolic, encoded by SHMT1 on chromosome 17p11) — predominant in adult liver, kidney, and most differentiated tissues. Provides cytosolic 5,10-methylene-THF for thymidylate synthesis (DNA precursor) and for the cytosolic arm of the methionine cycle.
- SHMT2 (mitochondrial, encoded by SHMT2 on chromosome 12q13) — expressed in nearly all cell types, particularly in proliferating cells and tumors. Provides mitochondrial 5,10-methylene-THF for the mitochondrial portion of the folate cycle, which is the principal source of formate that is exported to the cytosol to support cytosolic one-carbon metabolism.
Both enzymes catalyze the same chemical reaction but in spatially distinct compartments. The compartmentalization matters because mitochondria and cytosol have separate pools of tetrahydrofolate cofactor (the folate carrier protein SLC25A32 transports specific folate species across the mitochondrial inner membrane). The bulk of cellular one-carbon flux runs through the mitochondrial SHMT2 arm: serine enters mitochondria, is cleaved by SHMT2, and the resulting 5,10-methylene-THF is processed through MTHFD2 and MTHFD1L to generate formate, which is exported to the cytosol.
SHMT2 is highly upregulated in cancer. Many tumors require SHMT2 activity to support their proliferation, and SHMT2 expression correlates with tumor aggressiveness across multiple cancer types. Pharmacological inhibition of SHMT2 is an active area of cancer drug development, with SHIN1 and SHIN2 (small-molecule SHMT inhibitors) showing preclinical activity in lymphoma and other cancers.
The One-Carbon Metabolism Network
"One-carbon metabolism" refers to the network of reactions that transfer single-carbon groups (methyl, methylene, methenyl, formyl) between metabolites, mediated by tetrahydrofolate cofactors. This network produces purine and thymidylate nucleotides for DNA and RNA synthesis, regenerates the methionine pool that feeds the universal methyl donor S-adenosylmethionine (SAMe), and supports the synthesis of glycine, serine, and several other small molecules.
The core players:
- Tetrahydrofolate (THF) — the cofactor backbone, carrying one-carbon units at the N5 and N10 positions of the pteridine ring. Dietary folate (folic acid, leafy greens, fortified flour) enters this pool after reduction by dihydrofolate reductase (DHFR).
- 5,10-methylene-THF — produced by SHMT from serine. Donates a methylene to deoxyuridylate (dUMP) to make thymidylate (dTMP, the DNA-specific nucleotide). Also reduced by methylenetetrahydrofolate reductase to make 5-methyl-THF.
- 5-methyl-THF — the methyl donor for the methionine synthase reaction that regenerates methionine from homocysteine.
- 10-formyl-THF — donates formyl groups for purine ring synthesis (positions 2 and 8 of the purine base are derived from formyl-THF).
- Methionine and S-adenosylmethionine — methionine activated by adenosine triphosphate (ATP) becomes S-adenosylmethionine, the universal methyl donor for DNA methylation, histone methylation, neurotransmitter methylation, phospholipid methylation, and dozens of other substrates.
The network is more like a bicycle wheel than a linear pathway. Serine and SHMT sit at the hub, with spokes radiating out to DNA synthesis (thymidylate, purines), to the methionine cycle (5-methyl-THF), to glycine, and to formate export from mitochondria. Disruption at the hub propagates to every spoke.
Serine as the Quantitatively Dominant One-Carbon Source
Multiple parallel reactions could in principle supply one-carbon units to the folate cycle: serine (via SHMT), glycine (via the glycine cleavage system), dimethylglycine (via dimethylglycine dehydrogenase), sarcosine, choline (via betaine homocysteine methyltransferase, BHMT), and formate from various sources. Stable-isotope tracing studies in cultured cells and in animal models have consistently shown that serine is the dominant contributor of one-carbon units, accounting for roughly 50-90% of total one-carbon flux depending on the tissue and metabolic state.
The serine dominance has several explanations:
- Serine biosynthesis pathway — cells can synthesize serine de novo from glycolytic 3-phosphoglycerate via the PHGDH-PSAT1-PSPH pathway. This means serine supply can scale with the cell's metabolic activity and glycolytic flux, particularly in proliferating cells.
- SHMT efficiency — the SHMT reaction has favorable kinetics and high tissue activity, so the serine-to-one-carbon conversion is rapid relative to alternative pathways.
- Dietary serine is abundant — serine is present in virtually all dietary protein, so dietary supply is rarely limiting in healthy individuals.
The clinical implications are subtle but important. In rapidly proliferating cells (immune cells responding to infection, intestinal epithelial cells in the crypts, regenerating hepatocytes after partial hepatectomy, cancer cells), serine supply via the de novo synthesis pathway becomes rate-limiting for one-carbon metabolism and therefore for nucleotide synthesis and methylation. Tumors with high PHGDH expression are particularly serine-dependent — this is the rationale for the dietary serine-and-glycine restriction strategy that has shown preclinical efficacy in certain cancers (Maddocks 2017, Maddocks 2013).
In immune cells, similar logic applies. Activated T cells dramatically upregulate SHMT2 and the de novo serine synthesis pathway, and serine availability is one of the gatekeepers of T-cell expansion. This connects serine to the broader immunometabolism literature and explains why serine status influences immune function.
Interface with the Methionine / S-Adenosylmethionine Methylation Cycle
The folate cycle is coupled to the methionine cycle through the methylenetetrahydrofolate reductase-MS pair. Methylenetetrahydrofolate reductase (MTHFR) reduces 5,10-methylene-THF (the SHMT product) to 5-methyl-THF. Methionine synthase (MS, encoded by MTR) then transfers that methyl group to homocysteine, regenerating methionine. Methionine is activated by methionine adenosyltransferase to form S-adenosylmethionine, the universal methyl donor.
The full chain from serine to S-adenosylmethionine runs:
L-serine → (SHMT, B6) → 5,10-methylene-THF → (methylenetetrahydrofolate reductase) → 5-methyl-THF → (MS, B12) → methionine → (MAT, ATP) → S-adenosylmethionine → methylation reactions
S-adenosylmethionine is consumed in hundreds of methylation reactions, including:
- DNA methylation — cytosine methylation by DNA methyltransferases (DNMT1, DNMT3A, DNMT3B) is the basis of gene silencing and epigenetic regulation. The "methylation status" of CpG islands in gene promoters governs whether genes are expressed or silenced.
- Histone methylation — methylation of specific lysine and arginine residues on histone tails creates the activating and repressive marks (H3K4me3, H3K27me3, H3K9me3, etc.) that regulate gene expression.
- Neurotransmitter methylation — norepinephrine to epinephrine (PNMT), serotonin to N-acetylserotonin to melatonin (HIOMT methylation step), dopamine catabolism by catechol-O-methyltransferase (COMT).
- Phospholipid synthesis — phosphatidylethanolamine N-methyltransferase (PEMT) sequentially methylates phosphatidylethanolamine three times to produce phosphatidylcholine, accounting for roughly 30% of hepatic PC synthesis.
- Creatine synthesis — guanidinoacetate methyltransferase (GAMT) methylates guanidinoacetate to creatine, long estimated to consume more than 70% of all S-adenosylmethionine-derived methyl groups in humans. A 2006 reappraisal (Stead 2006) disputed that figure: dietary creatine can cover as much as 50% of daily creatine needs in people who eat meat, so creatine synthesis uses a smaller share of methyl groups than suggested, and phosphatidylcholine synthesis by PEMT is also a major consumer.
Adequate serine flux through SHMT therefore supports DNA methylation, gene regulation, neurotransmitter biosynthesis, phospholipid synthesis, and creatine production. Disruption at SHMT propagates downstream, and chronic low serine flux can manifest as hypomethylation phenotypes — altered gene expression, neurological dysfunction, fatty liver (when PEMT methylation falls), and elevated homocysteine.
The Glycine Cleavage System — Glycine as Secondary One-Carbon Source
Glycine itself can also donate one-carbon units to the folate cycle through the glycine cleavage system (GCS), a mitochondrial multi-enzyme complex composed of four proteins (P, T, H, L). The GCS reaction:
glycine + nicotinamide adenine dinucleotide (NAD+) + THF → CO2 + NH3 + reduced nicotinamide adenine dinucleotide (NADH) + 5,10-methylene-THF
The GCS therefore also generates the same activated 5,10-methylene-THF that SHMT produces, but starting from glycine rather than serine. The GCS is particularly active in liver and is the principal pathway for glycine catabolism in adult mammals.
The combined SHMT-plus-GCS architecture creates an elegant cycle. SHMT consumes one serine and one THF to produce one glycine and one 5,10-methylene-THF. The GCS can then consume that glycine to produce a second 5,10-methylene-THF (releasing CO2 and NH3). The net stoichiometry is: one serine + two THF + NAD+ → two 5,10-methylene-THF + CO2 + NH3 + reduced nicotinamide adenine dinucleotide. One serine becomes two one-carbon units. This is part of why serine is so quantitatively dominant as a one-carbon source — each serine molecule can yield two activated folate units through the combined SHMT-GCS pathway.
Loss-of-function mutations in the GCS cause non-ketotic hyperglycinemia (NKH), also called glycine encephalopathy. NKH presents in the neonatal period with seizures, profound hypotonia, apnea, and progressive neurological deterioration, driven by glycine accumulation in the central nervous system (CNS) that hyperstimulates N-methyl-D-aspartate (NMDA) receptors (glycine is the obligate co-agonist at N-methyl-D-aspartate receptors — see our D-Serine and N-methyl-D-aspartate deep-dive). The condition demonstrates the importance of glycine catabolism for normal neurological function and the close interconnection of glycine metabolism with N-methyl-D-aspartate-mediated neurotransmission.
NKH comes in a severe form — no developmental progress and seizures that drugs cannot control — and an attenuated form with varied symptoms and outcomes. No treatment that fixes the cause is known. Therapy uses sodium benzoate, which lowers glycine, plus drugs that block the N-methyl-D-aspartate receptor site (dextromethorphan, ketamine), and the results vary from child to child (Nowak 2022). In a study of four families, each with two children affected by attenuated NKH, the second child — diagnosed at birth and treated from the newborn period with benzoate and dextromethorphan at doses that brought blood glycine to normal — reached more developmental milestones and reached them earlier than the first child, who was diagnosed and treated late; in 3 of the 4 pairs the younger child had no seizures while the older child had a seizure disorder (Bjoraker 2016).
Why Dietary Glycine Deficiency Rarely Produces Symptoms
Glycine is classified as a non-essential amino acid in standard nutritional textbooks, but several authors (including Meléndez-Hevia in a much-cited 2009 paper) have argued that adult humans are functionally glycine-deficient — that the body synthesizes about 3 grams of glycine per day (more than 85% of it from serine) and takes in 1.5-3.0 grams per day from the diet, and that together these may fall short of the glycine needed for all uses — protein and collagen synthesis plus glutathione, heme, creatine, purines and bile acids — by about 10 grams per day for a 70 kg adult. On this argument the shortfall remains even after dietary glycine is counted, and the authors describe glycine as semi-essential.
If that argument is correct, why does a low-glycine diet not produce overt deficiency in adults? An older explanation was that the SHMT reaction runs in reverse to supply glycine — but the reverse reaction (glycine + 5,10-methylene-THF → serine + THF) uses glycine up rather than making it. A 2024 Princeton study in rodents (McBride 2024) found that whole-body SHMT flux overall consumes glycine: the liver turns glycine into serine, which is then broken down to pyruvate and burned for energy, and blocking SHMT1/2 with a drug (or removing liver SHMT2) raised blood glycine up to eight-fold. When the animals ate diets lacking serine and glycine, the body did not make more of them; it broke down less. On this evidence, blood serine and glycine are held steady mainly by adjusting how much is used up, with liver SHMT2 a major glycine-consuming enzyme.
Collagen is the richest glycine source in food (bone broth, gelatin, skin-on poultry). Practitioners describe people on collagen-poor diets as having lower glycine status, and describe direct glycine supplementation at 3-15 g/day as well-tolerated; Meléndez-Hevia and colleagues conclude that glycine should be taken as a supplement.
Glycine-rich foods include collagen, bone broth and gelatin; serine-rich foods include eggs, dairy, meat, fish, fermented soy foods and legumes. Practitioners describe glycine at 3-5 g/day before bed for sleep, glutathione production and collagen synthesis, and serine at 2-5 g/day for the broader methylation network and one-carbon metabolism; this page cites no trial for these doses.
For more on glycine specifically, see our Glycine page.
SHMT and Cancer Metabolism — The Drugging Strategy
The serine-and-glycine-restriction strategy for cancer treatment is one of the most active translational research areas in cancer metabolism. The rationale:
- Many cancers (particularly those with PHGDH amplification or with MYC activation) require high de novo serine synthesis to support their proliferation
- SHMT2 is upregulated in these tumors to channel serine through the mitochondrial one-carbon arm
- The resulting flux supports thymidylate synthesis (for DNA replication) and methylation (for epigenetic reprogramming)
- Restricting serine availability (either by dietary serine and glycine restriction or by pharmacological SHMT2 inhibition) starves the tumor of one-carbon units and slows proliferation
The Maddocks 2013 Nature paper showed that cancer cells with working p53 survive serine starvation by briefly pausing the cell cycle and channelling their remaining serine into glutathione, while cells lacking p53 failed to complete this response and suffered oxidative stress and severely impaired growth; a mouse experiment pointed to serine depletion as a possible treatment for p53-deficient tumours. The 2017 follow-up showed that restricting dietary serine and glycine extended survival in genetically engineered mouse models of intestinal cancer (driven by Apc loss) and lymphoma (driven by Myc), while Kras-driven pancreatic and intestinal tumours responded less, because activated Kras raises the tumour's own serine production.
A 2024 colorectal-cancer study (Tong 2024) found that a serine- and glycine-free diet slowed tumour growth in laboratory models and drew in tumour-killing (cytotoxic) T cells, but tumour cells fought back by chemically modifying the immune-checkpoint protein PD-L1 (lactylation) to escape them; blocking the PD-1/PD-L1 pathway restored the T cells. A small single-arm phase I study in patients (ChiCTR2300067929) found the diet feasible and safe.
The pharmacological approach uses small-molecule SHMT2 inhibitors (SHIN1, SHIN2) that block the enzyme directly. Preclinical results in B-cell lymphoma and certain leukemias have been encouraging, and first-in-human trials are underway.
For general readers: serine and glycine restriction has been studied only as a cancer treatment. In people without cancer it would cut into the one-carbon metabolism and methylation functions discussed throughout this page. In cancer, the metabolic dependencies vary widely between tumor types, restriction can also affect normal tissues, and so far the diet has been tested in people only in early trials such as the phase I study above.
Methylenetetrahydrofolate Reductase Variants and the Methylation-Cycle Genetics
The methylenetetrahydrofolate reductase (MTHFR) gene encodes the enzyme that reduces 5,10-methylene-THF (the SHMT product) to 5-methyl-THF, which is the methyl donor for methionine regeneration. Two common single-nucleotide polymorphisms in methylenetetrahydrofolate reductase — C677T and A1298C — produce enzyme variants with reduced activity.
- C677T (Ala222Val) — homozygous TT genotype produces an enzyme with roughly 30% of wild-type activity at 37°C. Population frequency of the T allele is about 30% in European-descent populations (higher in Mediterranean, lower in African). TT homozygotes have modestly elevated plasma homocysteine, particularly if folate intake is suboptimal.
- A1298C (Glu429Ala) — has milder enzymatic consequences than C677T. Compound heterozygotes (C677T/A1298C) show intermediate phenotype.
The clinical relevance of methylenetetrahydrofolate reductase variants is contested. The polymorphisms were widely tested in functional and integrative medicine through the 2000s and 2010s, with assertions that methylenetetrahydrofolate reductase variants cause or contribute to depression, anxiety, autism, cardiovascular disease, miscarriage, and many other conditions. The peer-reviewed evidence supports the variants as a modest risk factor for elevated homocysteine, neural tube defects (in offspring of mothers with low folate intake plus TT genotype), and possibly venous thromboembolism. The evidence for broader psychiatric and developmental claims is weaker than the popular discussion suggests.
For people with documented methylenetetrahydrofolate reductase variants and elevated homocysteine, practitioners commonly use methylated folate (5-methyl-THF / L-methylfolate (calcium salt)) at 400-1000 mcg/day, plus methylcobalamin (vitamin B12) and pyridoxal-5'-phosphate (active B6, the SHMT cofactor), describing the combination as addressing the downstream methylation cycle and supporting SHMT activity. The American College of Medical Genetics in 2013 recommended against routine methylenetetrahydrofolate reductase genotyping in asymptomatic individuals (Hickey 2013).
The connection to serine: SHMT activity provides the substrate (5,10-methylene-THF) that methylenetetrahydrofolate reductase processes. In people with reduced methylenetetrahydrofolate reductase function, adequate SHMT substrate (serine plus B6) is reasoned to support the upstream flux. This is the mechanistic reasoning for the integrative-medicine practice of including B6 and serine in methylation-support protocols for methylenetetrahydrofolate reductase-variant patients.
Clinical Implications — How Glycine and Serine Supplements Are Used
Practitioners describe the following uses of glycine and serine supplements; the doses are practitioner figures, not trial results cited on this page:
- Glycine is used for: sleep support (glycine 3 g at bedtime is reported to shorten the time to fall asleep and improve subjective sleep quality), collagen synthesis support (post-operative recovery, joint support), glutathione production (in conjunction with N-acetylcysteine, NAC), or direct glycine-replete diet support in patients on collagen-poor whole-food diets.
- L-serine is used for: general cognitive support, methylation cycle support (often combined with methylated folate and B12), phosphatidylserine substrate provision (older adults), one-carbon metabolism support in chronic illness, or D-serine substrate provision for N-methyl-D-aspartate-mediated cognitive support.
- Both are used together for: broad support of the methylation network, particularly in older adults or in people with chronic illness and high one-carbon demand. A typical practitioner regimen is serine 2-5 g divided through the day and glycine 3-5 g at bedtime.
The B-vitamin cofactors are part of the same chemistry. Without pyridoxal-5'-phosphate (active B6), SHMT cannot function. Without vitamin B12, methionine synthase cannot regenerate methionine. Without folate, the carrier pool is depleted. Practitioners' methylation-support protocols usually include all of these together, with serine and/or glycine as the carbon-unit substrate.
For elevated homocysteine, practitioners combine methylated folate, B12, B6, and dietary or supplemental serine and glycine, and describe homocysteine normalizing within 8-12 weeks. Homocysteine that stays high despite this regimen can come from poor vitamin B12 absorption, kidney disease, or rare genetic disorders of homocysteine metabolism.
Key Research Papers
- Ducker GS, Rabinowitz JD (2017). One-carbon metabolism in health and disease. Cell Metabolism. — PubMed PMID: 27641100
- Maddocks ODK et al. (2013). Serine starvation induces stress and p53-dependent metabolic remodelling in cancer cells. Nature. — PubMed PMID: 23242140
- Maddocks ODK et al. (2017). Modulating the therapeutic response of tumours to dietary serine and glycine starvation. Nature. — PubMed PMID: 28425994
- Locasale JW (2013). Serine, glycine and one-carbon units: cancer metabolism in full circle. Nature Reviews Cancer. — PubMed PMID: 23822983
- Meléndez-Hevia E et al. (2009). A weak link in metabolism: the metabolic capacity for glycine biosynthesis does not satisfy the need for collagen synthesis. Journal of Biosciences. — PubMed PMID: 20093739
- Tibbetts AS, Appling DR (2010). Compartmentalization of mammalian folate-mediated one-carbon metabolism. Annual Review of Nutrition. — PubMed PMID: 20645850
- Bailey LB et al. (2015). Biomarkers of nutrition for development: folate review. Journal of Nutrition. — PubMed PMID: 26451605
- Nowak M, Chuchra P, Paprocka J (2022). Nonketotic hyperglycinemia: insight into current therapies. Journal of Clinical Medicine. — PubMed PMID: 35683414
- Bjoraker KJ, Swanson MA, Coughlin CR 2nd, et al. (2016). Neurodevelopmental outcome and treatment efficacy of benzoate and dextromethorphan in siblings with attenuated nonketotic hyperglycinemia. Journal of Pediatrics. — PubMed PMID: 26749113
- Frosst P et al. (1995). A candidate genetic risk factor for vascular disease: a common mutation in methylenetetrahydrofolate reductase. Nature Genetics. — PubMed PMID: 7647779
- Hickey SE, Curry CJ, Toriello HV (2013). ACMG Practice Guideline: lack of evidence for MTHFR polymorphism testing. Genetics in Medicine. — PubMed PMID: 23288205
- Stover PJ (2009). One-carbon metabolism-genome interactions in folate-associated pathologies. Journal of Nutrition. — PubMed PMID: 19812215
- Rabinovich S et al. (2015). Diversion of aspartate in ASS1-deficient tumours fosters de novo pyrimidine synthesis. Nature (note: related pyrimidine-synthesis work in cancer). — PubMed PMID: 26560030
- McBride MJ, Hunter CJ, Zhang Z, TeSlaa T, Xu X, Ducker GS, Rabinowitz JD (2024). Glycine homeostasis requires reverse SHMT flux. Cell Metabolism. — PubMed PMID: 38171330
- Tong H et al. (2024). Dual impacts of serine/glycine-free diet in enhancing antitumor immunity and promoting evasion via PD-L1 lactylation. Cell Metabolism. — PubMed PMID: 39577415
- Stead LM, Brosnan JT, Brosnan ME, Vance DE, Jacobs RL (2006). Is it time to reevaluate methyl balance in humans? American Journal of Clinical Nutrition. — PubMed PMID: 16400042