Aspartic Acid and Energy Production
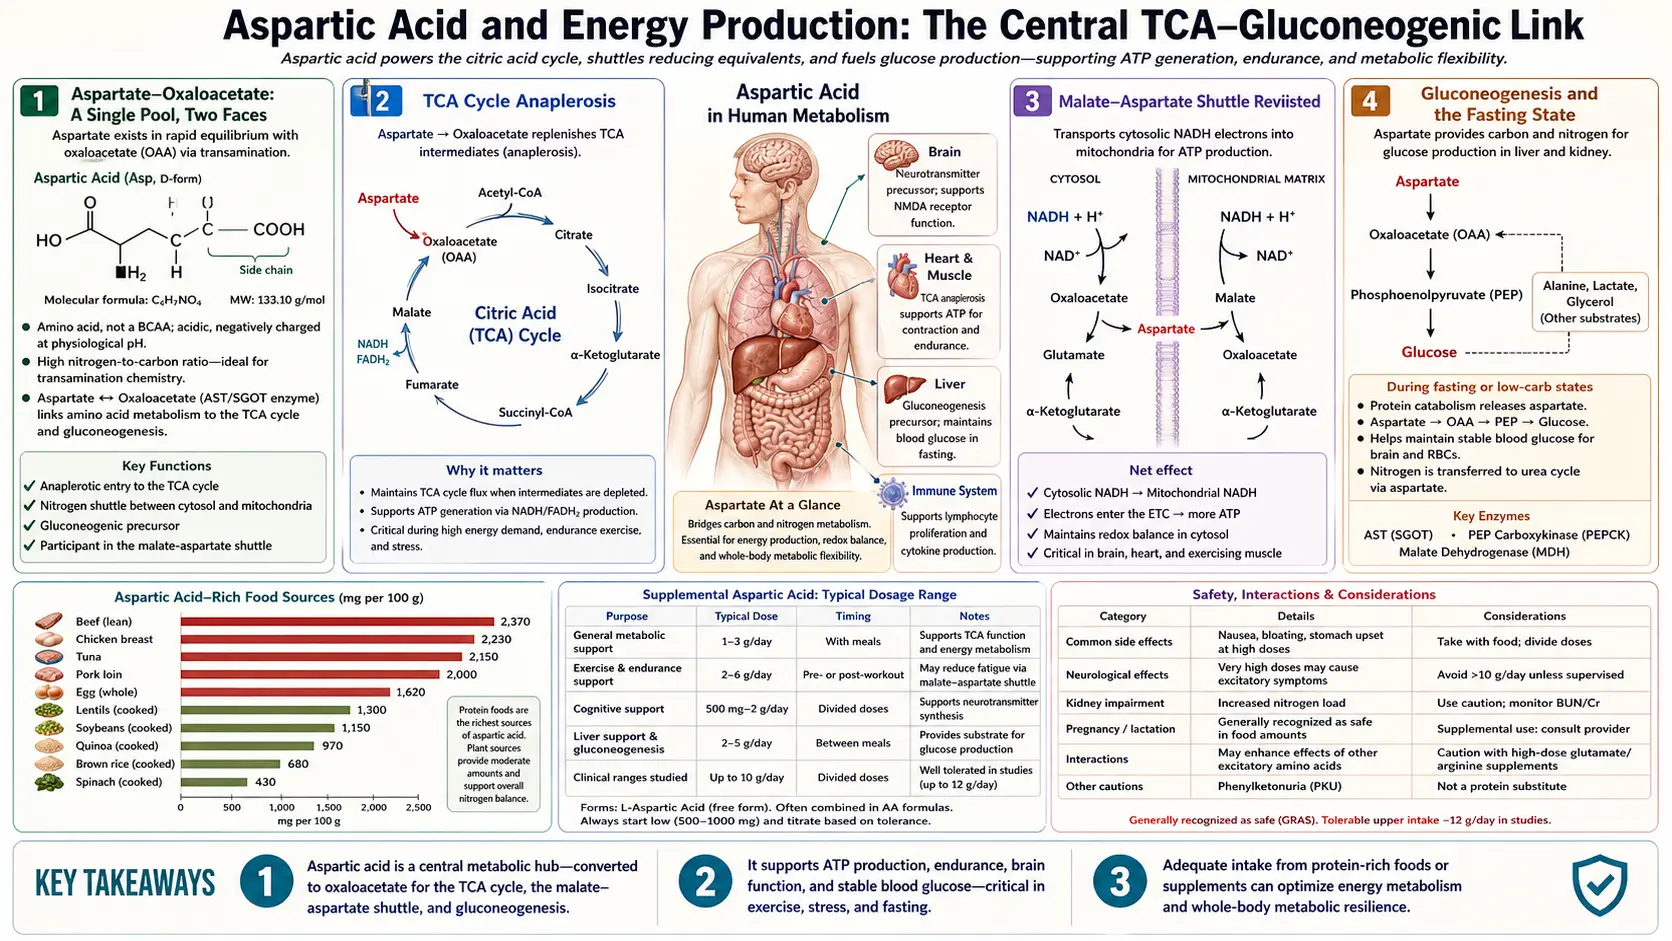
Aspartate sits at a strategic intersection of cellular energy metabolism. Through transamination with oxaloacetate, it is in direct equilibrium with the TCA cycle — aspartate and oxaloacetate are essentially the same metabolic pool seen from two sides. Through the malate-aspartate shuttle, it carries reducing equivalents (reduced nicotinamide adenine dinucleotide, NADH) from cytosol to mitochondria, where they fuel oxidative phosphorylation and adenosine triphosphate (ATP) synthesis. Through gluconeogenesis, it supplies the carbon skeleton for new glucose during fasting. And through the purinosome, it donates nitrogen for adenine and adenosine synthesis — making it indirectly essential for every molecule of adenosine triphosphate the cell produces. This page walks through each role and explains why aspartate has been marketed (with limited evidence) as a fatigue-fighting supplement for over half a century.
Table of Contents
- Aspartate-Oxaloacetate: A Single Pool, Two Faces
- TCA Cycle Anaplerosis
- The Malate-Aspartate Shuttle Revisited
- Gluconeogenesis and the Fasting State
- Purine Synthesis and Adenosine Triphosphate Building Blocks
- Ammonia, Aspartate, and Exercise-Induced Fatigue
- Potassium-Magnesium Aspartate: The 1960s Fatigue Story
- Modern Evidence on Aspartate Supplementation for Performance
- Aspartate in Mitochondrial Disease and Chronic Fatigue
- Clinical Takeaways
- Key Research Papers
- Connections
- Featured Videos
Aspartate-Oxaloacetate: A Single Pool, Two Faces
The enzyme aspartate aminotransferase (AST, also called glutamic-oxaloacetic transaminase, GOT) catalyzes the freely-reversible transamination:
L-aspartate + alpha-ketoglutarate ↔ oxaloacetate + L-glutamate
The reaction is at near-equilibrium under most cellular conditions, meaning aspartate and oxaloacetate are interconverted on a sub-second timescale and their concentrations are tightly coupled. Practically, this means that the cell does not maintain a meaningful distinction between "aspartate pool" and "oxaloacetate pool" — they are a single metabolic pool of the four-carbon dicarboxylic acid, with nitrogen attached or not depending on local supply and demand.
This coupling has profound consequences. Anywhere oxaloacetate is needed (the citrate synthase step of the TCA cycle, gluconeogenesis, the malate-aspartate shuttle), aspartate is an immediately available substrate via aspartate aminotransferase. Anywhere aspartate is needed (the urea cycle argininosuccinate synthetase (ASS1) step, purine biosynthesis, asparagine synthesis), oxaloacetate is an immediately available source via aspartate aminotransferase in reverse. The two pools breathe in unison.
The aspartate aminotransferase enzyme exists in two isoforms: mitochondrial (mAST) and cytosolic (cAST), with similar kinetic properties but distinct subcellular distribution. Both are released into circulation upon hepatocyte damage and are the aspartate aminotransferase measured on the routine liver panel — elevated aspartate aminotransferase signals hepatocellular injury and is one of the most common abnormal liver tests. The clinical interpretation is purely as a damage marker; circulating aspartate aminotransferase has no measurable functional role.
The dependence of the entire aspartate aminotransferase reaction on vitamin B6 (as pyridoxal-5-phosphate) is the molecular reason why B6 deficiency can produce subtle metabolic dysfunction across many systems. Without adequate B6, aspartate aminotransferase capacity drops, the aspartate-oxaloacetate coupling weakens, and downstream pathways (urea cycle, malate-aspartate shuttle, purine synthesis) become rate-limited.
TCA Cycle Anaplerosis
The TCA cycle (also called the Krebs cycle, citric acid cycle, or tricarboxylic acid cycle) is the central catabolic pathway by which acetyl-CoA derived from fats, carbohydrates, and amino acids is oxidized to CO2, generating the reduced cofactors (NADH and reduced flavin adenine dinucleotide, FADH2) that drive adenosine triphosphate synthesis at the electron transport chain.
The cycle is composed of eight enzymatic steps that convert oxaloacetate plus acetyl-CoA to two molecules of CO2, regenerating oxaloacetate for the next turn. In principle the cycle is catalytic — oxaloacetate is regenerated each cycle — but in practice TCA cycle intermediates are constantly withdrawn for biosynthetic purposes (citrate exported for fatty acid synthesis, alpha-ketoglutarate diverted to glutamate, oxaloacetate to aspartate and gluconeogenesis, succinyl-CoA to heme synthesis). These cataplerotic withdrawals must be replaced by anaplerotic reactions that resupply cycle intermediates.
Aspartate is one of the major anaplerotic inputs. Via aspartate aminotransferase, aspartate-derived oxaloacetate refills the TCA cycle:
- During high amino acid catabolism (fasting, high-protein meal, stress), aspartate flow into oxaloacetate maintains TCA cycle flux
- During high gluconeogenic demand, aspartate flow supports the export of oxaloacetate as malate, which drives gluconeogenesis
- During exercise in muscle, aspartate from the purine nucleotide cycle (see below) supplies anaplerotic carbons
The other major anaplerotic input is pyruvate carboxylase, which combines pyruvate plus CO2 plus adenosine triphosphate to make oxaloacetate. This is the dominant anaplerotic pathway in the well-fed state when pyruvate is abundant. The two pathways — aspartate-derived and pyruvate-derived — are complementary, with the relative contribution depending on dietary state and tissue.
The Malate-Aspartate Shuttle Revisited
The malate-aspartate shuttle was described in detail on the Urea Cycle page; here we focus on its energy-production role specifically.
Glycolysis converts glucose to pyruvate in the cytosol, generating 2 molecules of cytosolic reduced nicotinamide adenine dinucleotide per glucose. The reduced nicotinamide adenine dinucleotide must be re-oxidized to nicotinamide adenine dinucleotide (NAD+) for glycolysis to continue, but the inner mitochondrial membrane is impermeable to reduced nicotinamide adenine dinucleotide itself. Two shuttle systems address this:
- Malate-aspartate shuttle — the dominant system in heart, liver, kidney, and brain. Delivers reduced nicotinamide adenine dinucleotide equivalents to mitochondrial Complex I (reduced nicotinamide adenine dinucleotide dehydrogenase), generating ~2.5 adenosine triphosphate per cytosolic reduced nicotinamide adenine dinucleotide
- Glycerol-3-phosphate shuttle — the dominant system in skeletal muscle and brown adipose tissue. Delivers reduced nicotinamide adenine dinucleotide equivalents to mitochondrial Complex II / ubiquinone via FADH2, generating ~1.5 adenosine triphosphate per cytosolic reduced nicotinamide adenine dinucleotide
The choice of shuttle has measurable consequences for cellular adenosine triphosphate yield per glucose. A heart cell using the malate-aspartate shuttle gets approximately 32 adenosine triphosphate per glucose; a fast-twitch muscle cell relying on the glycerol-3-phosphate shuttle gets approximately 30 adenosine triphosphate per glucose. The difference is small but multiplied across the chronic energy budget of an organ makes a difference, and explains in part why the heart (which never stops working) cannot tolerate the bioenergetic deficits that would barely affect skeletal muscle.
The shuttle has clinical relevance in two contexts. In diabetic cardiomyopathy, chronic hyperglycemia and metabolic dysregulation impair malate-aspartate shuttle function in cardiomyocytes, contributing to the energy deficit characteristic of diabetic heart disease. In cancer metabolism, the Warburg phenomenon (preferential glycolysis even in the presence of oxygen) shifts the cell's adenosine triphosphate balance toward glycolytic adenosine triphosphate and away from oxidative adenosine triphosphate, reducing dependence on the malate-aspartate shuttle. Many cancer types have characteristic alterations in shuttle expression.
Gluconeogenesis and the Fasting State
During fasting (overnight, prolonged exercise, ketogenic diet, type 1 diabetes between meals), the liver and kidney synthesize new glucose from non-carbohydrate precursors via gluconeogenesis. The major substrates are lactate (from anaerobic glycolysis in red blood cells and exercising muscle), glycerol (from triglyceride breakdown), and the glucogenic amino acids — of which aspartate is one of the most efficient.
The aspartate-to-glucose pathway:
- Aspartate → oxaloacetate (via aspartate aminotransferase)
- Oxaloacetate → phosphoenolpyruvate (PEP) via phosphoenolpyruvate carboxykinase (PEPCK), consuming guanosine triphosphate (GTP). This is one of the major regulatory steps of gluconeogenesis.
- PEP runs the gluconeogenic pathway in reverse to glycolysis, producing glyceraldehyde-3-phosphate → fructose-1,6-bisphosphate → fructose-6-phosphate → glucose-6-phosphate
- Glucose-6-phosphatase (a liver-and-kidney-specific enzyme) hydrolyzes glucose-6-phosphate to free glucose, which is released into circulation
Each molecule of aspartate consumed yields one half-molecule of glucose (two aspartates produce one glucose). The pathway is most active during overnight fasting and prolonged exercise; chronic high-protein diets that exceed the body's protein needs convert excess amino acid carbon to glucose via this route, contributing to the glucose disposal of dietary protein.
From the energy-production perspective, aspartate's gluconeogenic role means that during fasting, aspartate-derived glucose helps maintain blood glucose homeostasis for brain function (the brain cannot use fatty acids for fuel and depends on glucose plus ketones during fasting). This is a critical role even though aspartate is not itself a direct adenosine triphosphate-producing substrate.
Purine Synthesis and Adenosine Triphosphate Building Blocks
The purine nucleotides — adenine and guanine derivatives — are the molecular building blocks of DNA, RNA, and the high-energy nucleotide cofactors that drive virtually every cellular reaction: ATP, GTP, NADH, NADPH, FAD, coenzyme A, S-adenosylmethionine, and many others. Without purine nucleotides, no biosynthesis, no signaling, no energy currency.
De novo purine synthesis is a 10-step pathway that builds the purine ring atom-by-atom on a ribose-5-phosphate backbone. Each step incorporates specific nitrogen and carbon atoms from different donors: glycine donates the N7-C8-C5 segment, glutamine donates N9 and N3, formate (via N10-formyl-tetrahydrofolate) donates C2 and C8, CO2 donates C6, and aspartate donates N1.
Aspartate is used twice on the way to adenine. In the ring-building pathway, the seventh step uses the enzyme SAICAR synthetase (phosphoribosylaminoimidazole-succinocarboxamide synthetase) to join aspartate to the growing ring; this aspartate supplies N1. When the finished ring, inosine monophosphate (IMP), is then turned into adenosine monophosphate (AMP), the enzyme adenylosuccinate synthetase attaches a second aspartate to IMP, forming adenylosuccinate; aspartate’s amino group becomes the 6-amino group of adenine. The next enzyme, adenylosuccinate lyase, cleaves off fumarate, leaving AMP. The released fumarate is recycled back through the TCA cycle, completing a small metabolic loop called the purine nucleotide cycle that is particularly active in exercising skeletal muscle.
The implication for energy production is direct: aspartate is in the construction lineage of every adenine nucleotide. Each adenosine triphosphate molecule the cell synthesizes traces its N1 atom and its 6-amino group to aspartate. The body's enormous adenosine triphosphate turnover (an adult cycles approximately his/her own body weight in adenosine triphosphate per day) makes purine biosynthesis one of the most demanding ongoing metabolic processes, and aspartate is a quantitatively significant input.
The purine nucleotide cycle in exercising muscle deserves separate mention. During intense exercise, muscle AMP rises (from adenosine triphosphate → adenosine diphosphate (ADP) → AMP), and AMP deaminase converts AMP to IMP plus ammonia. The IMP is reaminated back to AMP using aspartate as the amino-group donor, releasing fumarate (anaplerotic input to the TCA cycle). The net effect is to generate anaplerotic carbons for the TCA cycle from amino acid sources, supporting sustained energy production during exercise. This is one mechanism proposed to underlie the ergogenic claims for aspartate supplementation, though clinical evidence is limited.
Ammonia, Aspartate, and Exercise-Induced Fatigue
Exercise produces ammonia from two sources: the purine nucleotide cycle (described above) and branched-chain amino acid catabolism in working muscle. Ammonia accumulation is one of several mechanisms hypothesized to contribute to muscular and central fatigue during prolonged exercise. The mechanism is multifactorial: ammonia disrupts pH regulation, may interfere with brain neurotransmitter balance (the so-called "central fatigue hypothesis"), and reduces glycolytic flux at high concentrations.
Aspartate's role in ammonia handling provides a mechanistic rationale for its proposed ergogenic effect:
- Aspartate provides nitrogen for the urea cycle, which clears ammonia produced by amino acid catabolism in the liver
- Aspartate provides the amino group the purine nucleotide cycle uses to turn IMP back into AMP after it has been broken down in exercising muscle
- Aspartate-derived anaplerotic fumarate supports continued TCA cycle flux during exercise, maintaining oxidative adenosine triphosphate production
The composite hypothesis: aspartate supplementation would delay the onset of exercise-induced fatigue by enhancing ammonia clearance and supporting mitochondrial energy production. This was the foundation of the substantial mid-twentieth-century supplement literature on potassium-magnesium aspartate as a fatigue-fighter.
Potassium-Magnesium Aspartate: The 1960s Fatigue Story
From the late 1950s through the early 1970s, potassium-magnesium aspartate was actively marketed and clinically studied as a fatigue-relieving supplement. Potassium-magnesium aspartate products (primarily European) typically delivered 1-2 g aspartate per day plus elemental potassium and magnesium. Indications included general fatigue, recovery from surgery or illness, and athletic performance.
Several small clinical trials in the 1960s reported subjective benefit. Rosen et al. (1962) reported reduced perceived exertion at submaximal exercise loads. Several European studies in postoperative recovery reported faster mobilization. The mechanism was attributed to aspartate's role in ammonia clearance and energy production, plus the obvious effect of magnesium and potassium repletion (the patients in these studies were often electrolyte-depleted from their underlying conditions).
Methodologically the early trials were limited — small sample sizes, inconsistent blinding, subjective outcomes — and the supplement-quality and dosing variation was substantial. The category never made it into mainstream sports medicine, and by the 1980s interest had largely waned.
The modern reincarnation has been D-aspartic acid for testosterone (covered on the D-Aspartate page), which is mechanistically distinct from the L-aspartate fatigue claims. The L-aspartate fatigue claim itself has not had a sustained research program, though mineral-aspartate salts (magnesium aspartate, calcium aspartate, zinc aspartate) remain popular forms of mineral supplementation because the aspartate moiety chelates the mineral and enhances bioavailability (compared to oxide or carbonate forms, though typically equivalent to citrate or glycinate forms).
Modern Evidence on Aspartate Supplementation for Performance
The modern sports nutrition consensus is that L-aspartate supplementation provides no measurable ergogenic benefit for trained athletes with adequate nutrition. The mechanistic rationale is real, but the body's endogenous aspartate synthesis (from oxaloacetate, glutamate, and asparagine) is more than sufficient under typical conditions, and exogenous aspartate is metabolized rapidly without a sustained increase in tissue concentration at the relevant sites.
Specific findings:
- Controlled trials of potassium-magnesium aspartate found no improvement in time to exhaustion or in muscle force and endurance time (described below)
- Mineral-aspartate salts (Mg-Asp, K-Asp) for electrolyte repletion are well-tolerated and effective but no superior to other bioavailable mineral forms
- Aspartame intake (the artificial sweetener that metabolizes to aspartate, phenylalanine, and methanol) at typical intake levels does not produce measurable ergogenic or performance-detrimental effects in athletes
- Whole-food protein intake from animal or plant sources provides ample aspartate without need for isolated supplementation
Two controlled studies tested potassium-magnesium aspartate directly. In a double-blind trial, 8 healthy young men took 6 g of potassium-magnesium aspartate or a placebo over 24 hours and then cycled to exhaustion at about 75% of their maximum oxygen uptake: they lasted 82.7 minutes after aspartate and 85.4 minutes after placebo, with no differences in blood glucose, lactate or ammonia (Maughan and Sadler, 1983). A 1985 study found that potassium-magnesium aspartate did not increase force or endurance time during short, intense static muscle work in human volunteers, and in rats it did not change adenosine triphosphate, phosphocreatine or lactate in the thigh (quadriceps) muscle; the 20–50% improvements in muscle performance reported in older literature for long-term activity were not seen for this short, intense activity (de Haan and colleagues, 1985).
The exception to the "no benefit" pattern is in repletion of frank deficiency states — severely malnourished patients in recovery, postoperative patients with poor nutrition, advanced cirrhosis patients with sarcopenia and protein-energy malnutrition. In these populations, comprehensive amino acid repletion (which includes aspartate as part of the total amino acid pool) does improve recovery and functional status. But this is not specifically an aspartate effect — it is a total nutritional rehabilitation effect.
Aspartate in Mitochondrial Disease and Chronic Fatigue
Primary mitochondrial diseases (mitochondrial encephalomyopathy, lactic acidosis and stroke-like episodes (MELAS), myoclonic epilepsy with ragged-red fibres (MERRF), Leigh syndrome, mitochondrial DNA depletion syndromes, and many others) are characterized by impaired oxidative phosphorylation and the resulting bioenergetic deficit. Affected tissues are typically those with the highest energy demand: brain, heart, skeletal muscle, kidney, retina, inner ear.
Aspartate metabolism is dysregulated in many mitochondrial diseases. Plasma aspartate concentrations can be elevated (due to impaired downstream utilization), and the alanine:aspartate ratio is a research biomarker in some mitochondrial myopathies. The aralar (mitochondrial aspartate-glutamate antiporter) deficiency described on the Urea Cycle page is itself a recognized mitochondrial disease with severe neurodevelopmental presentation.
Laboratory work on human cells shows how closely aspartate is tied to the mitochondria. A 2015 cell-culture study found that a main reason cells need a working mitochondrial respiratory chain (the electron transport chain) in order to multiply is to make aspartate. When the chain was blocked, the cytosolic aspartate aminotransferase (GOT1) ran in reverse to make aspartate in the cell fluid, which partly made up for the loss, and adding aspartate allowed cells without a working chain to keep multiplying (Birsoy and colleagues, 2015). This is a result in cells grown in the laboratory, not a treatment result in people.
Therapeutic implications are limited. Direct aspartate supplementation has not been shown to benefit primary mitochondrial disease patients. The general management uses the "mitochondrial cocktail" of coenzyme Q10 (CoQ10), L-carnitine, riboflavin (B2), thiamine (B1), creatine, and alpha-lipoic acid, with variable evidence. Aspartate is not a standard component.
For chronic fatigue syndrome (ME/CFS) and the chronic fatigue overlap with long COVID, fibromyalgia, and postural orthostatic tachycardia syndrome (POTS), the bioenergetic hypothesis (that affected patients have impaired mitochondrial function in skeletal muscle, brain, or both) is one of several working models. Some clinicians prescribe a similar "mitochondrial cocktail" with mixed evidence, occasionally including aspartate-containing supplements. The clinical effect sizes are modest at best, and the heterogeneity of the patient population makes it difficult to identify which subgroups, if any, benefit. Aspartate alone is not an evidence-based intervention.
Clinical Takeaways
- Aspartate is mechanistically essential to cellular energy production through the TCA cycle, the malate-aspartate shuttle, gluconeogenesis, and purine biosynthesis. It is not optional for life.
- Endogenous synthesis is normally adequate. Aspartate is a non-essential amino acid because the body can make it from oxaloacetate and glutamate. Dietary aspartate from protein-containing foods provides additional supply but is not separately required.
- Isolated aspartate supplementation does not enhance energy or athletic performance in well-nourished healthy adults. The mechanistic rationale is real but the marginal contribution from supplementation is below the threshold of detectable benefit.
- Mineral-aspartate salts (magnesium aspartate, potassium aspartate, zinc aspartate) are common forms of mineral supplementation, described as comparable in bioavailability to glycinate or citrate forms and superior to oxide or carbonate forms.
- For chronic fatigue, mitochondrial disease, or chronic illness, aspartate is part of comprehensive nutritional support but is not a primary intervention. The evidence does not support isolated aspartate as a fatigue treatment.
- L-ornithine L-aspartate (LOLA) is the one specific clinical context in which exogenous aspartate is administered to drive a metabolic pathway — the urea cycle in hepatic encephalopathy — with modest evidence of efficacy. A 2018 Cochrane review of 36 randomised trials (outcome data available from 29) found that, with all trials pooled, L-ornithine L-aspartate lowered hepatic encephalopathy (risk ratio 0.70) and death (risk ratio 0.42) compared with placebo or no treatment, but not in the trials at low risk of bias; the reviewers rated the evidence very low quality, and compared with lactulose it showed no effect on death or hepatic encephalopathy. See the Urea Cycle page.
- Vitamin B6 status matters for aspartate metabolism — aspartate aminotransferase requires pyridoxal-5-phosphate, and B6 deficiency can impair aspartate handling across multiple pathways. Severe B6 deficiency is uncommon in developed-country populations; chronic illness, alcoholism, malabsorption and pregnancy are settings in which B6 status can be low.
Key Research Papers
- Krebs HA, Johnson WA (1980). The role of citric acid in intermediate metabolism in animal tissues. FEBS Letters 117 Suppl:K1-10. Reprint of the original 1937 TCA cycle description in Enzymologia. — PubMed PMID: 6998725
- Owen OE, Kalhan SC, Hanson RW (2002). The key role of anaplerosis and cataplerosis for citric acid cycle function. Journal of Biological Chemistry 277(34):30409-12. — PubMed PMID: 12087111
- Birsoy K et al. (2015). An essential role of the mitochondrial electron transport chain in cell proliferation is to enable aspartate synthesis. Cell. — PubMed PMID: 26232224
- Sullivan LB et al. (2015). Supporting aspartate biosynthesis is an essential function of respiration in proliferating cells. Cell. — PubMed PMID: 26232225
- Rosen H, Blumenthal A, Agersborg HP (1962). Effects of the potassium and magnesium salts of aspartic acid on metabolic exhaustion. Journal of Pharmaceutical Sciences 51:592-3. — PubMed PMID: 14493900
- Maughan RJ, Sadler DJ (1983). The effects of oral administration of salts of aspartic acid on the metabolic response to prolonged exhausting exercise in man. International Journal of Sports Medicine 4(2):119-23. — PubMed PMID: 6874173
- de Haan A, van Doorn JE, Westra HG (1985). Effects of potassium + magnesium aspartate on muscle metabolism and force development during short intensive static exercise. International Journal of Sports Medicine 6(1):44-9. — PubMed PMID: 3988415
- Tullson PC, Terjung RL (1991). Adenine nucleotide metabolism in contracting skeletal muscle. Exercise and Sport Sciences Reviews. The purine nucleotide cycle in exercise. — PubMed PMID: 1936094
- Banister EW, Cameron BJ (1990). Exercise-induced hyperammonemia: peripheral and central effects. International Journal of Sports Medicine. — PubMed PMID: 2193891
- Cynober L (2002). Plasma amino acid levels with a note on membrane transport: characteristics, regulation, and metabolic significance. Nutrition. — PubMed PMID: 12297216
- Brand MD (2005). The efficiency and plasticity of mitochondrial energy transduction. Biochemical Society Transactions. — PubMed PMID: 16246006
- Wolf NM, Abad-Zapatero C, Johnson ME, Fung LW (2014). Structures of SAICAR synthetase (PurC) from Streptococcus pneumoniae with ADP, Mg2+, AIR and Asp. Acta Crystallographica Section D, Biological Crystallography 70(Pt 3):841-50. — PubMed PMID: 24598753
- Honzatko RB, Fromm HJ (1999). Structure-function studies of adenylosuccinate synthetase from Escherichia coli. Archives of Biochemistry and Biophysics 370(1):1-8. — PubMed PMID: 10496970
- Goh ET, Stokes CS, Sidhu SS, Vilstrup H, Gluud LL, Morgan MY (2018). L-ornithine L-aspartate for prevention and treatment of hepatic encephalopathy in people with cirrhosis. Cochrane Database of Systematic Reviews 5(5):CD012410. — PubMed PMID: 29762873
PubMed Topic Searches
Connections
- All Amino Acids
- Aspartic Acid Benefits Hub
- Aspartic Acid Overview
- Neurotransmission & N-Methyl-D-Aspartate
- Aspartate in the Urea Cycle
- D-Aspartate & Testosterone
- Glutamic Acid
- Alanine
- Glycine
- Glutamine
- Magnesium (Mg-Aspartate)
- Potassium (K-Aspartate)
- Vitamin B6 (Aspartate Aminotransferase Cofactor)
- Chronic Fatigue
- Mitochondrial Support
- History
- Sources