Carnitine Forms & the Trimethylamine N-Oxide (TMAO) Question
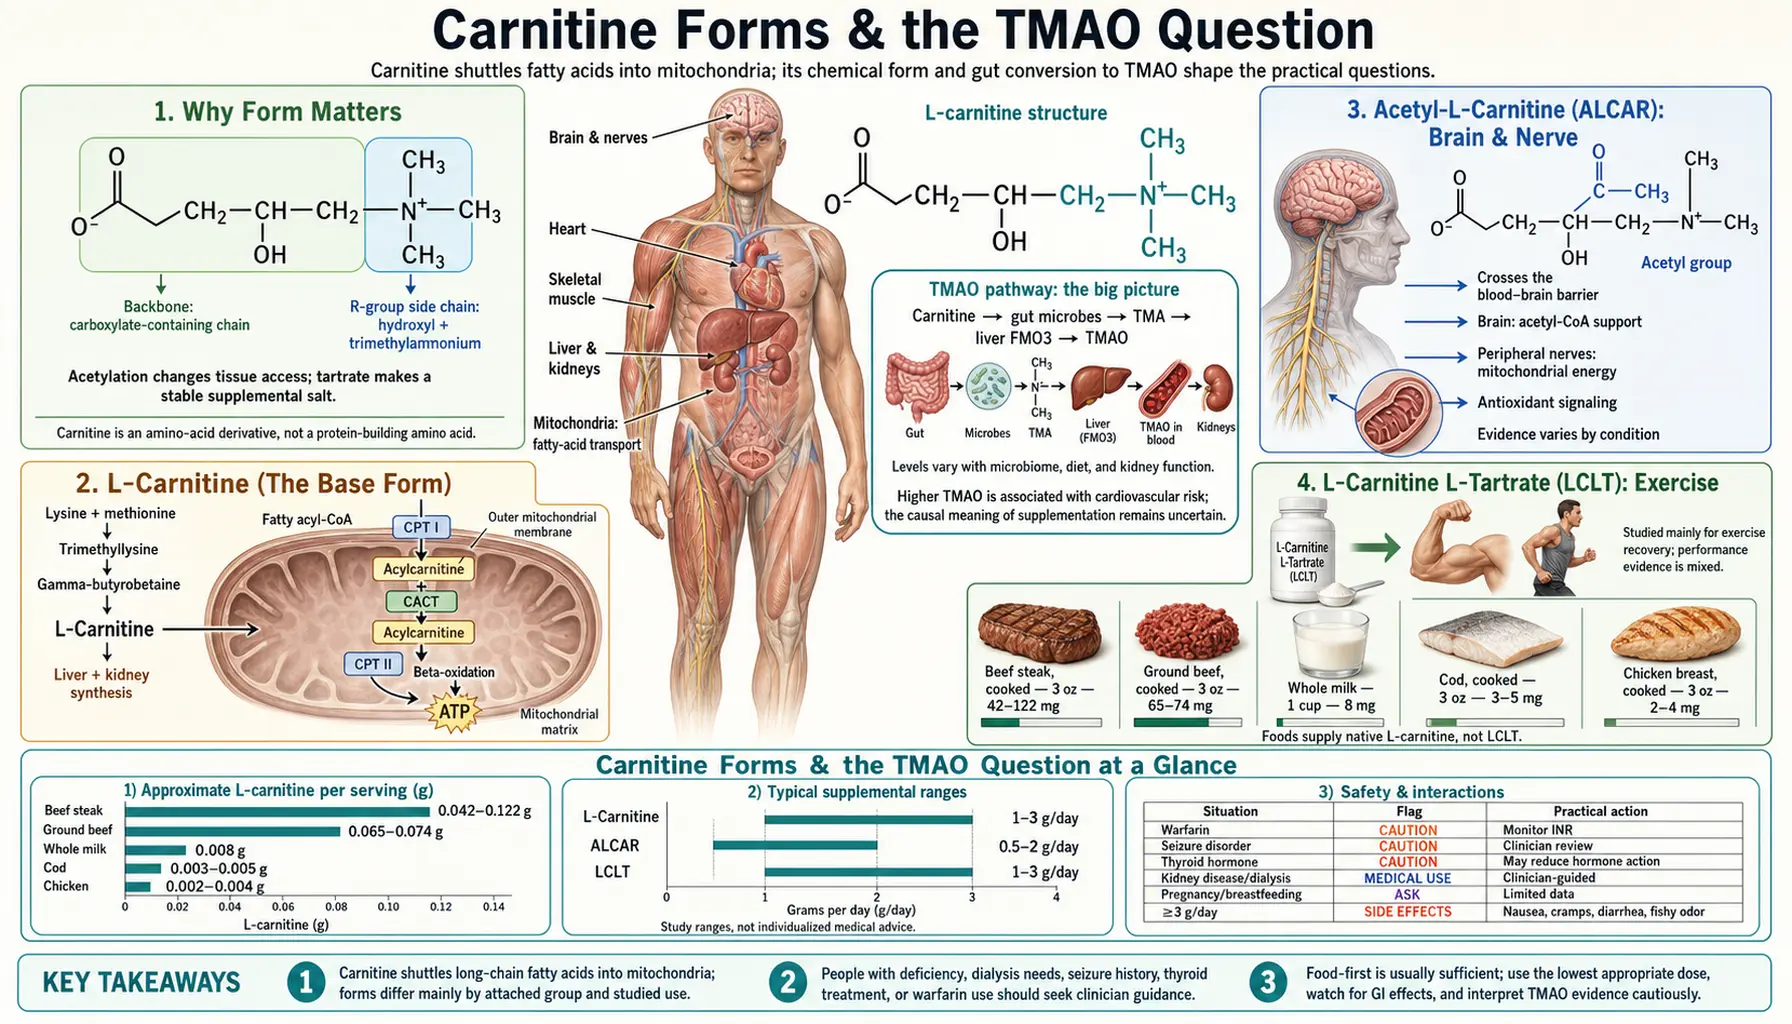
"Carnitine" on a label can mean several different molecules, and the differences matter. Plain L-carnitine is the base form for general and cardiovascular use. Acetyl-L-carnitine (ALCAR) adds an acetyl group that lets it cross the blood-brain barrier, which is why it is the form studied for cognition, mood, and nerve health. L-carnitine L-tartrate (LCLT) is the exercise-recovery form, and propionyl-L-carnitine is the vascular one. Then there is the question that hangs over all of them: gut bacteria can convert carnitine into TMA, which the liver turns into trimethylamine N-oxide (TMAO) — a compound repeatedly linked to atherosclerosis. Yet the cardiovascular trials show benefit. This "carnitine paradox" is genuinely unsettled, and this page lays out honestly what is known and what is not.
Interactive Visualization Fat Burning & Ketosis — what actually happens Follow a fatty acid out of a fat cell to the mitochondrial gate and find it padlocked by insulin. Drop the carbs, open CPT1, and watch the liver start making ketones. Launch →
Table of Contents
- Why Form Matters
- L-Carnitine (The Base Form)
- Acetyl-L-Carnitine (ALCAR): Brain & Nerve
- L-Carnitine L-Tartrate (LCLT): Exercise
- Propionyl-L-Carnitine (PLC): Vascular
- Which Form Was Studied for Which Goal
- The Trimethylamine N-Oxide Pathway: How Gut Bacteria Reshape Carnitine
- The Carnitine Paradox: Benefit Trials vs the Trimethylamine N-Oxide Hypothesis
- What Is Actually Known vs Unsettled
- Practical Takeaways & Safety
- Key Research Papers
- Connections
- Featured Videos
Why Form Matters
All carnitine supplements deliver the same core molecule, but the chemical group attached to it (or paired with it) changes where the carnitine goes, how well it is absorbed, and what it can do once inside the body. Each form has been studied for different uses — the heart-failure trials used plain L-carnitine, while the brain and nerve trials mostly used acetyl-L-carnitine — so a result for one form does not automatically carry over to another. The four forms below cover the uses that have been studied.
L-Carnitine (The Base Form)
Plain L-carnitine (sometimes sold as L-carnitine tartrate for stability, or as a liquid) is the reference form and the one used in most cardiovascular and general-metabolism trials. Only the "L" stereoisomer is biologically active; the "D" form is inactive and can even interfere with L-carnitine, which is why the trials used L-carnitine rather than a "DL" racemic mix.
L-carnitine is the form used in the trials on the Heart & Circulation page (heart failure, post-heart-attack, angina) and for correcting documented deficiency. Oral bioavailability is modest — a 2003 pharmacokinetics review (Evans and Fornasini) put it at 5–18% after oral doses of 1–6 g, against as much as 75% for the smaller amounts in a normal diet — and much of the unabsorbed carnitine is metabolized by gut bacteria, a fact that becomes important in the trimethylamine N-oxide discussion below.
Plain L-carnitine has also been tested on the brain: in a 2007 randomized, placebo-controlled trial (Malaguarnera and colleagues, American Journal of Clinical Nutrition), 66 centenarians with fatigue after slight activity took 2 g of plain L-carnitine (levocarnitine) a day or placebo; the carnitine group had less physical and mental fatigue, gained muscle, lost fat, and scored higher on a memory-and-thinking test (the Mini-Mental State Examination) than the placebo group.
Acetyl-L-Carnitine (ALCAR): Brain & Nerve
Acetyl-L-carnitine (ALCAR) carries an added acetyl group, and that small change has a big consequence: ALCAR crosses the blood-brain barrier far more readily than plain L-carnitine. Once in the brain, it supplies both carnitine and an acetyl group that can feed acetylcholine synthesis and mitochondrial energy metabolism in neurons. This is why ALCAR — not the other forms — is the one studied for the nervous system:
- Diabetic peripheral neuropathy. Sima and colleagues (Diabetes Care, 2005) reported that ALCAR improved pain, nerve-fiber regeneration, and vibratory perception in patients with chronic diabetic neuropathy, with the clearest benefit at higher doses. This is among the stronger ALCAR findings.
- Depressive symptoms. A systematic review and meta-analysis by Veronese and colleagues (Psychosomatic Medicine, 2018) pooled 12 randomized trials (791 people) and found that ALCAR reduced depressive symptoms versus placebo or no treatment; in three trials that compared it with antidepressants, ALCAR worked about as well and caused significantly fewer side effects than the antidepressants. The authors called for larger trials to confirm or refute these findings.
- Mild cognitive impairment and early Alzheimer's. A meta-analysis by Montgomery and colleagues (International Clinical Psychopharmacology, 2003) of double-blind trials found modest benefit of ALCAR over placebo in mild cognitive impairment and mild Alzheimer's disease. The effect is small and the condition is difficult, so ALCAR is not a treatment — but the data are real.
The honest framing for ALCAR mirrors the rest of the carnitine story: genuinely interesting, mechanistically sensible, supported by real trials, but modest in effect and not a substitute for established treatment of neuropathy, depression, or dementia.
L-Carnitine L-Tartrate (LCLT): Exercise
L-carnitine L-tartrate (LCLT) pairs carnitine with tartaric acid, giving rapid dissolution and absorption that make it convenient for dosing around workouts. It is the form used in the University of Connecticut recovery studies described on the Exercise & Recovery page, where roughly 2 g/day reduced markers of exercise-induced muscle damage and soreness. LCLT is the form studied for post-exercise recovery, although the overall exercise benefit is modest and the endurance evidence is weak.
Propionyl-L-Carnitine (PLC): Vascular
Propionyl-L-carnitine (PLC) attaches a propionyl group that can be converted to succinyl-CoA and fed directly into the Krebs cycle, and PLC also appears to support endothelial (blood-vessel-lining) function. These properties made it the form of choice for vascular conditions — angina and, especially, the intermittent claudication of peripheral artery disease. As covered on the Heart & Circulation page, the walking-distance evidence is mixed. A 2013 systematic review (Delaney and colleagues, Atherosclerosis, PubMed 23557982) was modestly positive, while the 2021 Cochrane review of propionyl-L-carnitine for intermittent claudication (Kamoen and colleagues, PubMed 34954832) pooled 12 trials with 1,423 people and found that, compared with placebo, propionyl-L-carnitine increased maximal walking distance by about 51 metres (26%) and pain-free walking distance by about 33 metres (31%). The reviewers judged the improvement mild to moderate, side effects similar to placebo, and the overall certainty of the evidence moderate; they also noted a high proportion of drug-company-backed studies and no trials comparing it with standard treatment.
Which Form Was Studied for Which Goal
- Heart failure, post-heart-attack, angina, or documented deficiency: plain L-carnitine, studied as an add-on to standard treatment.
- Cognition, mood, or diabetic nerve pain: mostly acetyl-L-carnitine (ALCAR), the form that crosses into the brain most readily (the centenarian fatigue trial used plain L-carnitine).
- Exercise recovery and soreness: L-carnitine L-tartrate (LCLT).
- Peripheral artery disease / claudication: propionyl-L-carnitine (PLC).
- General weight loss: no form is a proven fat burner in healthy people — see Fat Metabolism & Weight.
The Trimethylamine N-Oxide Pathway: How Gut Bacteria Reshape Carnitine
Here is the wrinkle that complicates every carnitine benefit claim. In 2013, Koeth and colleagues at the Cleveland Clinic published a landmark paper in Nature Medicine showing a three-step pathway:
- Gut bacteria metabolize dietary carnitine into trimethylamine (TMA). Carnitine that is not absorbed in the small intestine reaches the colon, where certain gut microbes cleave it into the gas-like compound TMA.
- The liver oxidizes TMA into trimethylamine-N-oxide (TMAO) via the enzyme flavin-containing monooxygenase 3 (FMO3).
- Trimethylamine N-oxide is associated with atherosclerosis. In their mouse and human work, higher trimethylamine N-oxide correlated with, and in animal models appeared to promote, atherosclerotic plaque — through effects on cholesterol handling in artery-wall macrophages and on reverse cholesterol transport.
Crucially, the same group showed this is a microbiome-dependent effect: habitual red-meat eaters (omnivores) harbor the bacterial community that produces trimethylamine N-oxide from carnitine, whereas long-term vegetarians and vegans produce very little trimethylamine N-oxide from the same carnitine dose — their gut flora simply lacks the machinery. In the same paper, among 2,595 people having heart check-ups, higher blood carnitine predicted heart disease and later heart attack, stroke or death only in those who also had high trimethylamine N-oxide. A parallel 2013 New England Journal of Medicine paper by Tang and colleagues established the same TMA→trimethylamine N-oxide pathway for choline and phosphatidylcholine, and linked higher trimethylamine N-oxide to increased cardiovascular risk in a large patient cohort. A 2019 follow-up by Koeth and colleagues in the Journal of Clinical Investigation traced the specific microbial steps by which an omnivorous diet builds this atherogenic pathway in humans. After a labelled carnitine dose, omnivores made more than 20 times as much trimethylamine N-oxide as vegans and vegetarians, even though fasting blood carnitine was similar in the two groups (32 vegans and vegetarians, 40 omnivores). Both groups' gut bacteria quickly turned carnitine into an intermediate, gamma-butyrobetaine; the second step, from gamma-butyrobetaine to TMA, was switched on by an omnivorous diet and by months of carnitine supplements, and the researchers traced it to a single low-abundance gut bacterium, Emergencia timonensis.
The Carnitine Paradox: Benefit Trials vs the Trimethylamine N-Oxide Hypothesis
Now hold the two bodies of evidence side by side and the tension is obvious:
- On one hand, the cardiovascular trials and meta-analysis suggest L-carnitine helps the heart — less remodeling after heart attack, fewer arrhythmias, possibly lower mortality.
- On the other hand, the trimethylamine N-oxide research suggests carnitine feeds a gut-microbial pathway that promotes the atherosclerosis underlying most heart disease.
How can both be true? Several possibilities are debated, none proven:
- Different timescales and endpoints. The benefit trials measured short-to-medium-term cardiac function and events in people who already had heart disease; the trimethylamine N-oxide hypothesis concerns slow, lifelong plaque development. A molecule could aid a stressed heart acutely while modestly nudging long-term plaque — or the two effects could operate in different tissues.
- Trimethylamine N-oxide may be a marker as much as a cause. Elevated trimethylamine N-oxide also reflects impaired kidney function and particular dietary and microbiome patterns. Some researchers argue trimethylamine N-oxide is partly a bystander flagging risk rather than a primary driver, which would soften the supplement concern. This remains contested.
- Dose and route differ. A therapeutic carnitine dose in a monitored patient is not the same as decades of high red-meat intake shaping the gut flora. The relevance of the trimethylamine N-oxide pathway to a discrete supplement course is unclear.
- The microbiome is modifiable. Because trimethylamine N-oxide production depends on gut bacteria, it varies enormously between people and can shift with diet — making blanket statements about "carnitine causes trimethylamine N-oxide" too simple.
This genuinely is an open scientific question. The New England Journal of Medicine and Nature Medicine papers are serious science; so is the cardiovascular-benefit literature. They have not been reconciled by a definitive study, and honest sources say so rather than picking a side.
What Is Actually Known vs Unsettled
Reasonably established:
- Gut bacteria convert unabsorbed carnitine (and choline) into TMA, which the liver oxidizes to trimethylamine N-oxide. The pathway is real.
- Trimethylamine N-oxide production is strongly microbiome-dependent; omnivores make much more from a carnitine dose than vegetarians and vegans do.
- Higher circulating trimethylamine N-oxide is statistically associated with cardiovascular events in large cohorts.
Genuinely unsettled:
- Whether trimethylamine N-oxide causes human atherosclerosis or largely marks other risk (kidney function, diet, microbiome), and how much each contributes.
- Whether therapeutic carnitine supplementation meaningfully raises long-term cardiovascular risk in practice — no long-term outcome trial has tested this directly.
- How to weigh the short-to-medium-term cardiac benefit signal against the theoretical long-term trimethylamine N-oxide concern in any individual patient.
Both bodies of findings stand, the paradox is unresolved, and the research supports neither "carnitine is dangerous" nor "trimethylamine N-oxide is nothing."
Practical Takeaways & Safety
- Each form has its own studied use (list above) — L-carnitine for cardiac/deficiency, ALCAR for brain and nerve, LCLT for exercise recovery, PLC for claudication.
- Only the "L" form is active. "DL-carnitine" products contain the D-isomer, which is inactive and can interfere with L-carnitine.
- The trimethylamine N-oxide question in proportion. The benefit trials studied carnitine as a treatment course for specific conditions; for healthy people taking carnitine as a "fat burner," the trials show little benefit (see Fat Metabolism & Weight) while the trimethylamine N-oxide concern remains theoretical.
- Kidney disease is a special case. Impaired kidneys clear trimethylamine N-oxide poorly and change carnitine handling. People on dialysis can develop a secondary carnitine deficiency because carnitine is lost freely through the dialyser, and L-carnitine has been used to treat some patients on long-term haemodialysis (Evans and Fornasini, 2003).
- General tolerability. Oral carnitine is usually well tolerated; higher doses can cause nausea, cramping, diarrhea, and a fishy body odor (from trimethylamine, the very compound at the head of the trimethylamine N-oxide pathway).
This page is educational and does not constitute medical advice. The trimethylamine N-oxide field is evolving, and the questions it raises are sharpest for people with heart or kidney disease.
Key Research Papers
- Koeth RA et al. (2013). Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosis. Nature Medicine. — PubMed PMID: 23563705
- Tang WH, Wang Z, Levison BS, Koeth RA, Britt EB, Fu X, Wu Y, Hazen SL (2013). Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk. New England Journal of Medicine. — PubMed PMID: 23614584
- Koeth RA et al. (2019). L-Carnitine in omnivorous diets induces an atherogenic gut microbial pathway in humans. Journal of Clinical Investigation. — PubMed PMID: 30530985
- Sima AA, Calvani M, Mehra M, Amato A (2005). Acetyl-L-carnitine improves pain, nerve regeneration, and vibratory perception in patients with chronic diabetic neuropathy. Diabetes Care. — PubMed PMID: 15616239
- Veronese N, Stubbs B, Solmi M, Ajnakina O, Carvalho AF, Maggi S (2018). Acetyl-L-carnitine supplementation and the treatment of depressive symptoms: a systematic review and meta-analysis. Psychosomatic Medicine. — PubMed PMID: 29076953
- Montgomery SA, Thal LJ, Amrein R (2003). Meta-analysis of double blind randomized controlled clinical trials of acetyl-L-carnitine versus placebo in the treatment of mild cognitive impairment and mild Alzheimer's disease. International Clinical Psychopharmacology. — PubMed PMID: 12598816
- Kamoen V, Vander Stichele R, Campens L, De Bacquer D, Van Bortel L, De Backer TL (2021). Propionyl-L-carnitine for intermittent claudication. Cochrane Database of Systematic Reviews. — PubMed PMID: 34954832
- Delaney CL, Spark JI, Thomas J, Wong YT, Chan LT, Miller MD (2013). A systematic review to evaluate the effectiveness of carnitine supplementation in improving walking performance among individuals with intermittent claudication. Atherosclerosis. — PubMed PMID: 23557982
- Evans AM, Fornasini G (2003). Pharmacokinetics of L-carnitine. Clinical Pharmacokinetics. — PubMed PMID: 12908852
- Malaguarnera M et al. (2007). L-Carnitine treatment reduces severity of physical and mental fatigue and increases cognitive functions in centenarians. American Journal of Clinical Nutrition. — PubMed PMID: 18065594
PubMed Topic Searches
External Resources
Connections
- All Amino Acids
- Fat Burning & Ketosis — interactive animation
- Carnitine Benefits Hub
- Carnitine (Main Page)
- Heart & Circulation
- Fat Metabolism & Weight
- Exercise & Recovery
- Atherosclerosis
- Coronary Artery Disease
- Peripheral Artery Disease
- Alzheimer's Disease
- Neurology
- Type 2 Diabetes
- Beef (Red Meat & Trimethylamine N-Oxide)
- Organ Meats
- Mediterranean Diet
- Deficiency