Folate / Folic Acid Excess: Unmetabolized Folic Acid
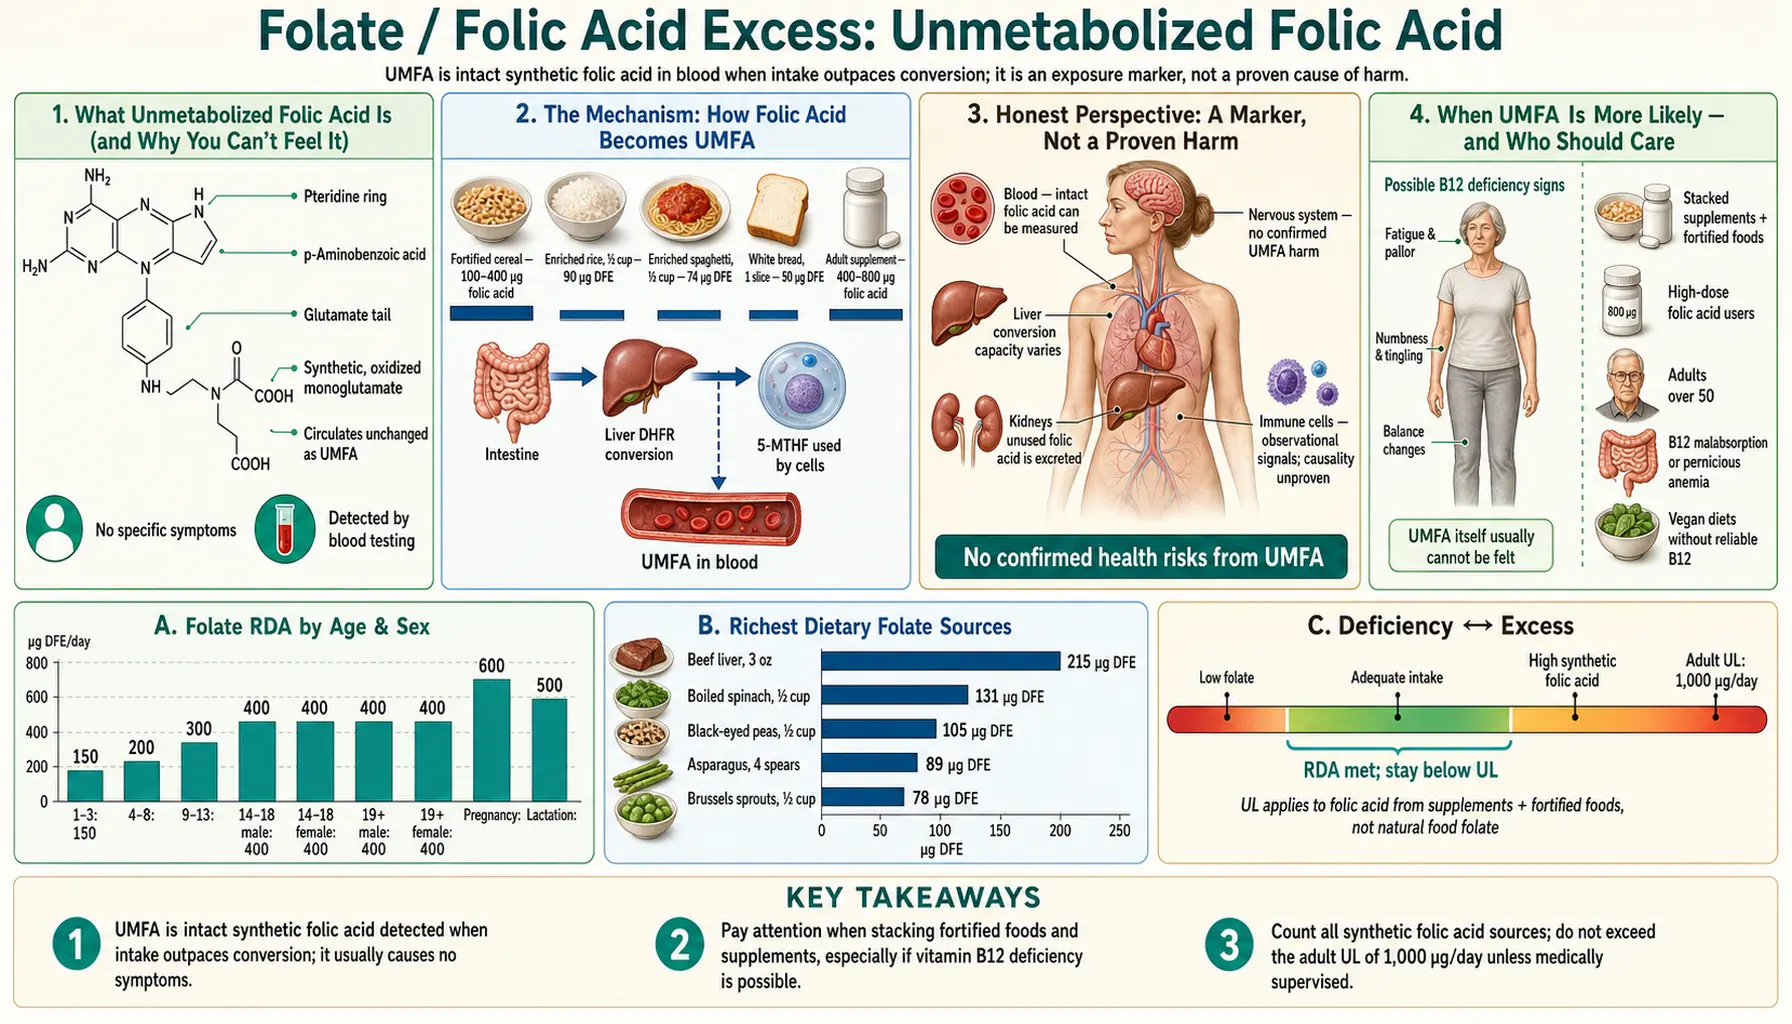
When you take more folic acid — the synthetic form of vitamin B9 in supplements and fortified flour — than your body can promptly convert, some of it slips into the bloodstream still in its raw, unprocessed state. Scientists call this unmetabolized folic acid, or UMFA. It is not a symptom you can feel; it is a marker detected on a research blood test, and in fortified countries it now turns up in almost everyone. The honest bottom line, stated up front: UMFA is a reliable sign of high folic-acid intake, but whether it actually causes harm is genuinely uncertain and debated. Some intriguing associations have been reported — with immune-cell activity and, separately, with cancer in people who already have precancerous changes — but none of these has been established as proven harm in healthy people. This page explains the biochemistry in plain language, lays out what the evidence does and does not show, and helps you put it in perspective.
Table of Contents
- What Unmetabolized Folic Acid Is (and Why You Can't Feel It)
- The Mechanism: How Folic Acid Becomes UMFA
- Honest Perspective: A Marker, Not a Proven Harm
- When UMFA Is More Likely and Who the Research Raises Concerns For
- Where the Extra Folic Acid Comes From
- How UMFA Is Measured
- Where Folic-Acid Intake Can Be Lowered
- Warning Signs and Red Flags
- Key Research Papers
- Connections
- Featured Videos
What Unmetabolized Folic Acid Is (and Why You Can't Feel It)
Most of the “toxicity” pages on this site describe a symptom — something you notice in your body. Unmetabolized folic acid is different, and it is important to be clear about that from the start: UMFA produces no symptoms you can feel. There is no ache, no rash, no fatigue that signals its presence. It is a substance measured in a research laboratory, and the only way to know you have it is a specialized blood test that is almost never ordered in routine care.
To understand UMFA you first need to understand that vitamin B9 comes in two very different chemical outfits:
- Natural folate — the form in leafy greens, beans, liver, and other whole foods. The body absorbs it and, in the gut wall, converts it into the active circulating form, 5-methyltetrahydrofolate (5-MTHF). Crucially, natural food folate does not produce unmetabolized folic acid. It arrives in the blood already in its usable form.
- Folic acid — a synthetic, fully oxidized molecule invented for stability. It is the form in nearly all supplements, in “B-complex” pills, and in the fortified flour, bread, pasta, and cereal mandated in the United States since 1998. It is more shelf-stable and better absorbed than food folate, but the body cannot use it directly. It first has to be chemically reduced and converted — mostly in the liver and intestinal lining — into the same active 5-MTHF.
That conversion step has a speed limit. The enzyme that does the first reduction, dihydrofolate reductase (DHFR), works relatively slowly in humans. When folic acid arrives faster than DHFR can process it — from a large supplement, a fortified meal, or both — the surplus simply spills past the conversion machinery and circulates in the blood unchanged. That circulating, not-yet-converted folic acid is what UMFA is: free synthetic folic acid in your plasma, waiting in line for an enzyme that is already busy.
Because it is invisible to the person carrying it, UMFA is best thought of not as an illness but as a biomarker of intake — a chemical fingerprint that says “this person is taking in more folic acid than their liver can instantly convert.” Whether that fingerprint matters for health is the question the rest of this page works through, carefully and without overstating.
The Mechanism: How Folic Acid Becomes UMFA
The cleanest way to picture this is a small, busy workshop. Folic acid is the raw material delivered to the loading dock; 5-MTHF is the finished, usable part the body actually installs. DHFR is the single machine that must process every piece of raw material before it can move down the line. The machine runs at a fixed, fairly modest pace.
When deliveries are small and steady — the trickle of folic acid you'd get from one fortified slice of bread — the machine keeps up, and essentially everything is converted before it leaves the workshop. But when a large shipment lands all at once — a 400-, 800-, or 1,000-microgram folic-acid tablet, sometimes stacked on top of fortified food — raw material piles up faster than the machine can handle it. The overflow is shipped out of the workshop unprocessed. In the body, “shipped out” means released into the bloodstream as unmetabolized folic acid.
Two features of human biochemistry make this overflow especially easy to trigger:
- Human DHFR is slow and variable. Compared with some other species, the human enzyme reduces folic acid sluggishly, and its activity varies a great deal from person to person — by an order of magnitude or more. Someone with low DHFR activity will spill folic acid into UMFA at a dose that another person clears completely.
- The liver is the bottleneck. Most conversion happens on first pass through the gut wall and liver. Once that capacity is exceeded, the excess does not wait politely — it enters the general circulation, where it can be measured.
This is the precise reason the two forms of B9 behave so differently. Natural food folate is delivered to the workshop already finished (as 5-MTHF) and bypasses the DHFR machine altogether, so eating folate-rich food — even a great deal of it — does not generate UMFA. It is specifically the synthetic, oxidized folic-acid molecule, taken in amounts that outrun the enzyme, that produces it. Understanding this distinction is the single most useful thing on this page: the marker is a property of the synthetic form and the dose, not of vitamin B9 in general. (The fuller story of how folate cycles through one-carbon metabolism is covered on the methylation and homocysteine page.)
Honest Perspective: A Marker, Not a Proven Harm
This is the most important section on the page, and the place where honesty matters most. It is tempting to read “unmetabolized synthetic chemical circulating in your blood” and assume it must be bad. The careful, evidence-based answer is more restrained: UMFA is firmly established as a marker of high folic-acid intake, but its clinical significance — whether it actually harms people — remains uncertain and is actively debated by researchers.
Here is what is genuinely well established:
- UMFA is extremely common. In the fortified United States, a large national survey detected UMFA in nearly all blood samples from children, adolescents, and adults. If UMFA itself were a potent toxin, we would expect to see widespread, obvious harm in the population — and that has not been observed. This near-universality is itself a strong reason not to panic about it.
- Higher folic-acid intake means more UMFA. The relationship between supplement dose, fortification, and circulating UMFA is consistent and dose-dependent. That part is not in doubt.
Now the associations that get cited — each described honestly, with its caveats:
- Natural-killer (NK) cell activity. A frequently quoted 2006 study of postmenopausal women found that those with detectable UMFA had lower measured activity of natural-killer cells — immune cells that help patrol for virus-infected and tumor cells. This is a real and interesting finding, but it is an association in one observational study using a laboratory measure of immune-cell function. It does not show that UMFA caused reduced immunity, and it has not been linked to people actually getting sick more often. It is a signal worth studying, not a demonstrated harm.
- The cancer-promotion hypothesis. The concern here is biologically specific and worth stating precisely: folate is needed for cells to divide, so the worry is that a flood of folic acid might accelerate the growth of cells that have already turned precancerous — for example, an existing colon polyp — even while adequate folate protects healthy tissue from becoming cancerous in the first place. Some trials and analyses raised this possibility, particularly for colorectal adenomas. In long-term follow-up of one trial in people who had recently had colorectal adenomas (1 mg/day of folic acid or placebo), among those who kept taking it any colorectal neoplasia was found in 43% on folic acid versus 36% on placebo (RR 1.21, 95% CI 0.99–1.47, P = 0.06), sessile serrated polyps were significantly more common with folic acid (RR 1.94, 95% CI 1.02–3.68), and there was no effect after treatment stopped (RR 1.01). In Norway, where food is not fortified with folic acid, a combined analysis of two trials in 6,837 patients with ischemic heart disease found more cancer with 0.8 mg/day of folic acid plus vitamin B12 than without it (10.0% versus 8.4%; HR 1.21, 95% CI 1.03–1.41), more cancer deaths (HR 1.38) and more deaths from any cause (HR 1.18), mainly driven by lung cancer — one of the signals that started the concern. Meanwhile, a large pooled analysis of folic-acid supplementation trials found no significant overall increase in cancer incidence over the study periods: across all 13 such trials, with 49,621 participants, folic acid quadrupled blood levels of folic acid but had no significant effect on overall cancer incidence during an average of 5.2 years of treatment (RR 1.06, 95% CI 0.99–1.13, p = 0.10), nor on cancer of the large intestine, prostate, lung, breast or any other specific site. Its authors note that fortification gives doses of folic acid that are, on average, an order of magnitude smaller than the doses used in these trials. The picture is genuinely mixed and unresolved. It is a legitimate scientific hypothesis, not a proven effect of UMFA, and not evidence against getting the folate the body needs.
The same restraint applies to claims you may encounter online that UMFA “blocks folate receptors,” “causes folate deficiency,” or is responsible for vague chronic symptoms. These go well beyond what the evidence supports. The honest summary is this: UMFA tells us a person is taking a lot of folic acid; it does not, on current evidence, tell us that person is being harmed. Confident claims in either direction are not supported by current evidence.
There is one downstream concern that is better supported, and it deserves its own page rather than this one: high folic-acid intake can mask the blood signs of vitamin B12 deficiency, allowing nerve damage to progress undetected. That is a distinct issue from UMFA itself and is covered on the companion page, how folic acid can mask B12 deficiency.
When UMFA Is More Likely and Who the Research Raises Concerns For
Since you cannot feel UMFA, the practical question is not “do I have symptoms?” but “am I in a situation where a high folic-acid load is plausibly worth thinking about?” The honest answer for most people is: probably not worth worrying about at all. But a few situations make a high circulating folic-acid load more likely, and a couple of them are genuinely worth attention — for the B12-masking reason above more than for UMFA itself.
- High-dose supplements stacked on fortified food. The most reliable way to generate substantial UMFA is to take a folic-acid supplement — especially 800–1,000 mcg or more — on top of an American diet already rich in fortified flour. Several B-complex, “energy,” and prenatal products contain folic acid, and they can quietly add up if you take more than one.
- Possible reduced conversion capacity. People whose DHFR works slowly — a normal human variation — spill folic acid into UMFA more readily. There is no routine test for this, and it does not, by itself, indicate any problem; it simply means the marker appears at lower doses in some people than others.
- Older adults with low B12 — the one group the research genuinely flags. The combination that worries clinicians is high folic acid plus low vitamin B12. Cross-sectional national data have linked this specific pairing with worse measures of cognition and anemia in older adults, though the findings are not fully consistent. The point that matters here is not UMFA; it is whether B12 is adequate when folic-acid intake is high. For people over 50, vegetarians and vegans, people on long-term metformin or acid-reducing drugs, and others at risk for B12 deficiency, this is the part that carries weight.
For a healthy young adult getting folic acid mostly from fortified food, the presence of UMFA is best understood as an unremarkable, near-universal background finding — interesting to scientists, not a personal health alarm. The people for whom the topic carries real weight are those at risk of hidden B12 deficiency, and even then the lever to pull is the B12, not a crusade against folic acid.
Where the Extra Folic Acid Comes From
If you want to understand your own folic-acid load, it helps to know the three places synthetic folic acid enters the diet. Notice that none of these is the same as natural food folate, which does not generate UMFA.
- Mandatory food fortification. Since 1998, the United States has required folic acid to be added to enriched flour, bread, pasta, rice, cornmeal, and many breakfast cereals. This program has been a major public-health success — it sharply reduced neural-tube birth defects — but it also means most Americans consume folic acid every day without choosing to. Some breakfast cereals are fortified to 100 percent of the Daily Value (400 mcg) in a single serving.
- Supplements. Standalone folic-acid tablets, multivitamins, B-complex products, and prenatal vitamins are the largest discretionary source. A typical prenatal supplies 400–800 mcg of folic acid; some products and prescriptions go to 1,000 mcg or higher. Taking more than one folic-acid-containing product compounds the dose.
- The Tolerable Upper Intake Level. Health authorities set an upper limit of 1,000 mcg per day of folic acid from supplements and fortified food for adults (lower for children). Importantly, this limit applies only to the synthetic form — it was set specifically because high folic-acid intake can mask B12 deficiency, not because of UMFA — and it does not apply to folate from whole foods, which has no established upper limit.
By contrast, the folate in folate-rich whole foods — spinach, lentils, asparagus, avocado, liver, beans — arrives as natural folate, is converted in the gut wall to active 5-MTHF, and does not produce UMFA no matter how much you eat. This is exactly why “eat your folate” and “watch your folic-acid supplement dose” are two different pieces of advice.
A note on the active supplement form: some products now use L-methylfolate (5-MTHF) instead of folic acid, marketed as bypassing the DHFR step. It is true that 5-MTHF supplements do not generate UMFA the way folic acid does. Whether that translates into any health benefit for the general population is unproven, and it is a more expensive ingredient. It is a reasonable choice, not a medical necessity, and it is not a treatment for any UMFA-related “condition” (there is no recognized one).
How UMFA Is Measured
It is worth being plain: UMFA is almost never tested for in ordinary care, and no guideline calls for it. There is no standard clinical test for it, no widely accepted “normal range,” and no medical society that recommends checking it. UMFA is measured almost exclusively in research laboratories using sensitive techniques such as liquid chromatography–mass spectrometry (LC-MS/MS), which can separate the synthetic folic-acid molecule from the body's natural folate forms and quantify each. That separation is the whole technical challenge, and it is why the measurement lives in research rather than routine care.
What is available, and far more useful, are the ordinary folate and B12 blood tests your clinician already knows how to interpret:
- Serum and red-blood-cell (RBC) folate. These measure total folate status — whether you have enough — not the synthetic-versus-natural split. In a fortified population, true folate deficiency is now uncommon. RBC folate reflects longer-term status than serum folate.
- Vitamin B12 (and, when needed, more specific markers). Because the one substantiated risk of high folic acid involves hidden B12 deficiency, the genuinely worthwhile test is a vitamin B12 level, sometimes alongside homocysteine or methylmalonic acid (MMA) when the B12 result is borderline. These detect the problem that actually matters.
- Complete blood count. A complete blood count can flag the enlarged red cells (macrocytosis) of folate or B12 deficiency — another reason the two vitamins are always considered together.
So when a lab offers to measure “unmetabolized folic acid” and attaches a treatment plan to the result, there is no validated clinical threshold behind it, and the more meaningful, less expensive questions are simply whether your folate is adequate and your B12 is not deficient.
Where Folic-Acid Intake Can Be Lowered
Because UMFA is not a recognized disease, there is nothing to “treat” in the medical sense. But for people who prefer to keep their synthetic folic-acid intake modest — a perfectly reasonable goal — the levers are straightforward, low-key, and cost nothing.
- Supplement labels add up. Folic acid on a label is often listed as “folate” with “mcg DFE” and a folic-acid amount in parentheses, and it can come from a multivitamin, a B-complex, a prenatal, and standalone tablets at once. Many people are surprised to find two or three products each contributing several hundred micrograms.
- The Tolerable Upper Intake Level for adults is 1,000 mcg a day of folic acid from supplements and fortified food (see above); higher doses are given when a clinician prescribes them for a specific medical reason. Most adults who are not pregnant get plenty from fortified food alone and may not need a folic-acid supplement at all.
- Folate from food. Shifting B9 intake toward folate-rich whole foods — leafy greens, legumes, asparagus, avocado, liver — supplies the vitamin in its natural, already-active form that does not produce UMFA, while adding fiber and other nutrients.
- The active form, for people who supplement by choice. A B-vitamin product taken simply for general “insurance” that uses L-methylfolate (5-MTHF) does not generate UMFA. This is an optional preference, not a remedy for a problem.
- B12 status before high folate — the one point that genuinely matters. For people over 50, vegetarians and vegans, and people on metformin or long-term acid-suppressing medication, an adequate B12 status is what protects against the real, established risk of folic acid masking B12 deficiency — far more important than UMFA itself.
One vital exception. For people who are pregnant or planning to become pregnant, the neural-tube benefit of folic acid is proven, and the concerns about UMFA are not. The proven, large benefit of folic acid in preventing serious neural-tube birth defects vastly outweighs the unproven, theoretical concerns about UMFA. The US Preventive Services Task Force (reaffirmed in 2023) recommends that all persons planning to or who could become pregnant take a daily supplement containing 400–800 mcg of folic acid. This is covered fully on the folate and pregnancy page. When the benefit is established and the harm is hypothetical, the benefit wins.
Warning Signs and Red Flags
Unmetabolized folic acid itself does not cause symptoms and is not a medical emergency, so there are no “red flags” for UMFA as such. The warning signs that genuinely warrant attention belong to the conditions that high folic-acid intake can obscure — chiefly an undetected vitamin B12 deficiency — and to using folic acid in place of proper medical evaluation. These are the signs that matter:
- Numbness, tingling, or pins-and-needles in the hands or feet, unsteadiness when walking, or new problems with balance — these can signal the nerve damage of B12 deficiency, which folic acid can mask in the blood while the damage quietly advances.
- Unexplained fatigue, pallor, breathlessness, or a sore, smooth tongue — possible signs of anemia from folate or B12 deficiency; simple blood tests tell the two apart, while more folic acid alone can hide a B12 cause.
- New memory or thinking difficulties in an older adult, especially alongside a vegetarian diet or long-term metformin or acid-reducing medication — situations in which low B12 is a recognized cause.
- Any plan to take high-dose folic acid (above 1,000 mcg/day) long-term, or to treat a diagnosed deficiency — doses above the 1,000 mcg/day upper limit are normally given with a B12 check first, so a B12 deficiency is not hidden.
The underlying principle: folic acid (or any “methylfolate” supplement) used to paper over symptoms can hide a condition that deserves a diagnosis. Folate is genuinely good for you in sensible amounts; the danger lies in letting it conceal something else — and that danger is about B12, not about the unmetabolized folic acid this page describes. A B12 level and a complete blood count answer the questions that matter.
Key Research Papers
- Pfeiffer CM, Sternberg MR, Fazili Z, et al. (2015). Unmetabolized Folic Acid Is Detected in Nearly All Serum Samples from US Children, Adolescents, and Adults. The Journal of Nutrition;145(3):520-531. — DOI: 10.3945/jn.114.201210. — doi:10.3945/jn.114.201210
- Troen AM, Mitchell B, Sorensen B, et al. (2006). Unmetabolized Folic Acid in Plasma Is Associated with Reduced Natural Killer Cell Cytotoxicity among Postmenopausal Women. The Journal of Nutrition;136(1):189-194. — DOI: 10.1093/jn/136.1.189. — doi:10.1093/jn/136.1.189
- Kelly P, McPartlin J, Goggins M, et al. (1997). Unmetabolized folic acid in serum: acute studies in subjects consuming fortified food and supplements. The American Journal of Clinical Nutrition;65(6):1790-1795. — DOI: 10.1093/ajcn/65.6.1790. — doi:10.1093/ajcn/65.6.1790
- Tibbetts AS, Appling DR (2010). Compartmentalization of Mammalian Folate-Mediated One-Carbon Metabolism. Annual Review of Nutrition;30:57-81. — DOI: 10.1146/annurev.nutr.012809.104810. — PubMed PMID: 20645850
- Crider KS, Yang TP, Berry RJ, Bailey LB (2012). Folate and DNA Methylation: A Review of Molecular Mechanisms and the Evidence for Folate's Role. Advances in Nutrition;3(1):21-38. — DOI: 10.3945/an.111.000992. — doi:10.3945/an.111.000992
- Morris MS, Jacques PF, Rosenberg IH, Selhub J (2007). Folate and vitamin B-12 status in relation to anemia, macrocytosis, and cognitive impairment in older Americans in the age of folic acid fortification. The American Journal of Clinical Nutrition;85(1):193-200. — DOI: 10.1093/ajcn/85.1.193. — doi:10.1093/ajcn/85.1.193
- Bailey RL, Jun S, Murphy L, et al. (2020). High folic acid or folate combined with low vitamin B-12 status: potential but inconsistent association with cognitive function in a nationally representative cross-sectional sample of US older adults (NHANES). The American Journal of Clinical Nutrition;112(6):1547-1557. — DOI: 10.1093/ajcn/nqaa239. — doi:10.1093/ajcn/nqaa239
- Ebbing M, Bønaa KH, Nygård O, et al. (2009). Cancer Incidence and Mortality After Treatment With Folic Acid and Vitamin B12. JAMA;302(19):2119-2126. — DOI: 10.1001/jama.2009.1622. — doi:10.1001/jama.2009.1622
- Vollset SE, Clarke R, Lewington S, et al.; B-Vitamin Treatment Trialists' Collaboration (2013). Effects of folic acid supplementation on overall and site-specific cancer incidence during the randomised trials: meta-analyses of data on 50,000 individuals. The Lancet;381(9871):1029-1036. — DOI: 10.1016/S0140-6736(12)62001-7. — PubMed PMID: 23352552
- Passarelli MN, Barry EL, Rees JR, et al. (2019). Folic acid supplementation and risk of colorectal neoplasia during long-term follow-up of a randomized clinical trial. The American Journal of Clinical Nutrition;110(4):903-911. — DOI: 10.1093/ajcn/nqz160. — PubMed PMID: 31401653
- Quinlivan EP, Gregory JF (2003). Effect of food fortification on folic acid intake in the United States. The American Journal of Clinical Nutrition;77(1):221-225. — DOI: 10.1093/ajcn/77.1.221. — doi:10.1093/ajcn/77.1.221
- Institute of Medicine (US) Standing Committee on the Scientific Evaluation of Dietary Reference Intakes and its Panel on Folate, Other B Vitamins, and Choline (1998). Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline. Washington (DC): National Academies Press. — DOI: 10.17226/6015. — PubMed PMID: 23193625
- US Preventive Services Task Force; Barry MJ, Nicholson WK, Silverstein M, et al. (2023). Folic acid supplementation to prevent neural tube defects: US Preventive Services Task Force reaffirmation recommendation statement. JAMA;330(5):454-459. — DOI: 10.1001/jama.2023.12876. — PubMed PMID: 37526713
PubMed Topic Searches
Connections
- All Vitamins
- Folic Acid Excess Hub
- How Folic Acid Masks B12 Deficiency
- Folate Deficiency Hub
- Vitamin B9 (Folate) Overview
- Folate Benefits
- Folate, Methylation & Homocysteine
- Folate and Pregnancy / Neural-Tube Defects
- Folate Food Sources
- Vitamin B12
- B12 Deficiency Diagnosis
- Vitamin B12 Test
- Homocysteine Test
- Complete Blood Count
- Anemia