Folate / Folic Acid Excess: Masking B12 Deficiency
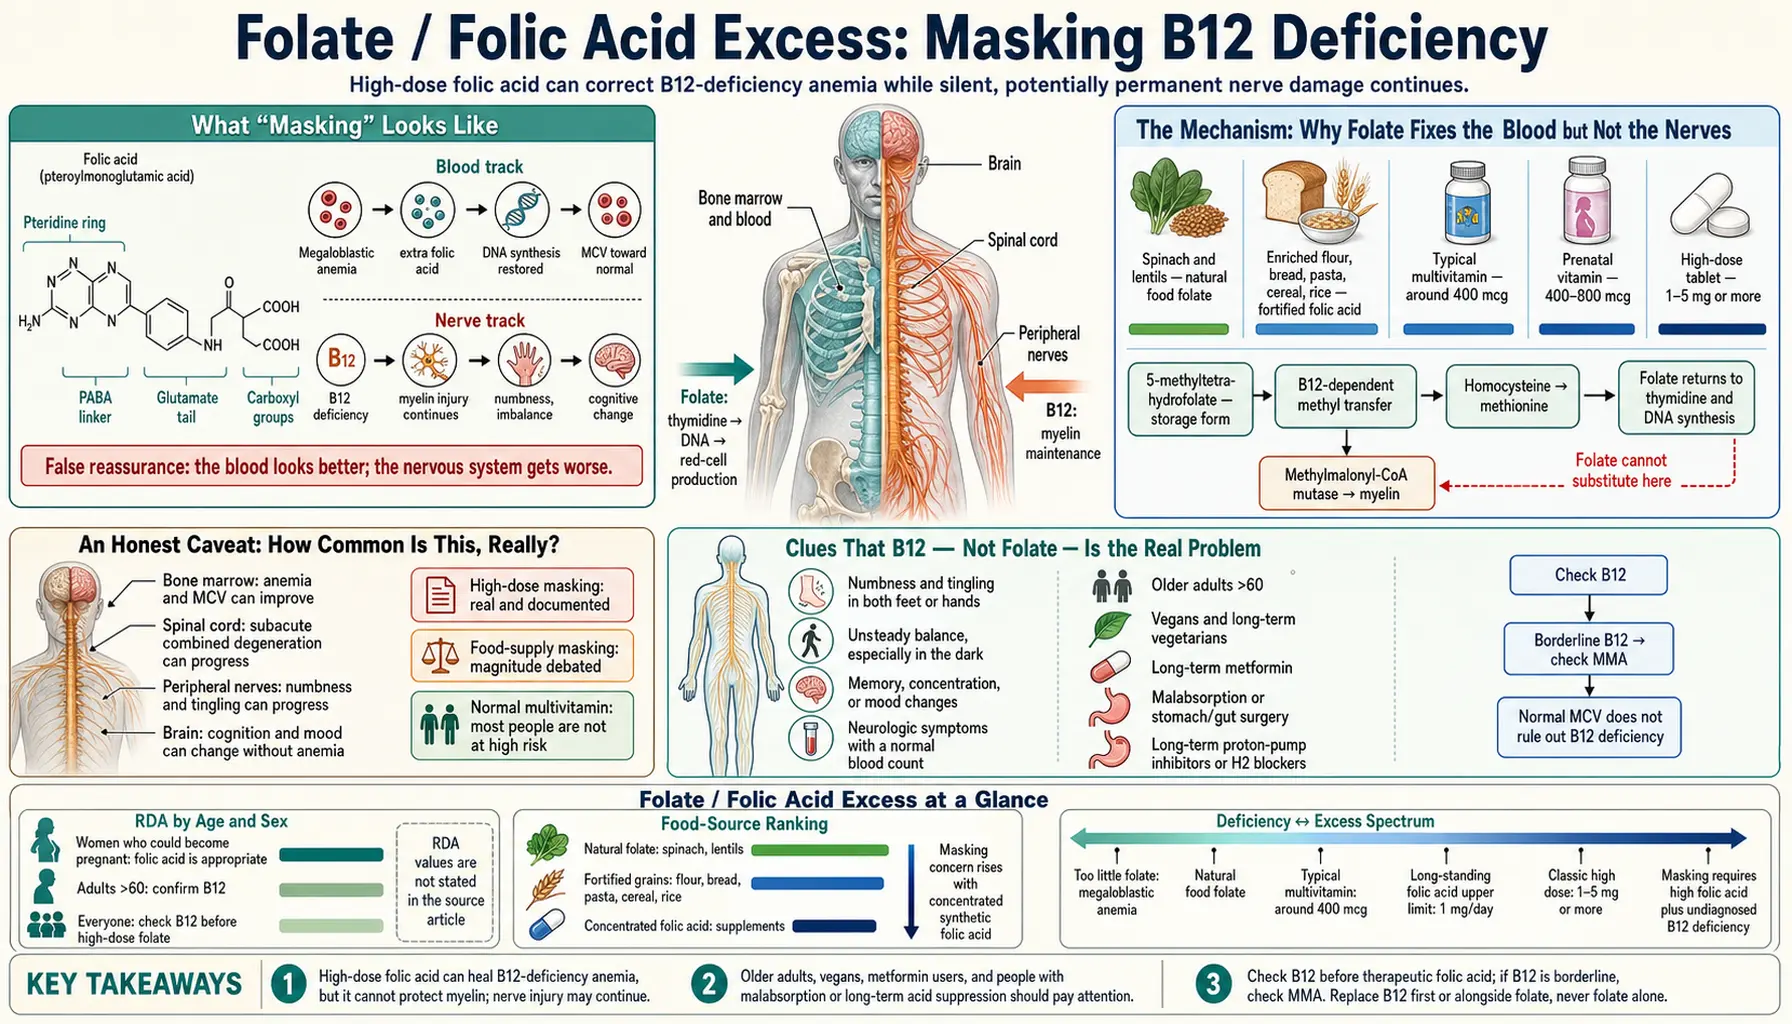
The single most important hazard of taking high-dose folic acid is not what it does on its own — folate is remarkably safe — but what it can hide. In a person who is also low in vitamin B12, a generous dose of folic acid can heal the anemia that would otherwise have raised the alarm, while the separate nerve damage of B12 deficiency keeps advancing in silence. The blood looks better; the nervous system gets worse. The long-standing clinical rule is simple: B12 is checked before high-dose folate is started. This page explains exactly how this masking happens, why it matters most for older adults, vegans, and people on metformin, and how a low B12 is found even when the blood count looks normal.
Table of Contents
- What “Masking” Looks Like
- The Mechanism: Why Folate Fixes the Blood but Not the Nerves
- An Honest Caveat: How Common Masking Is
- Clues That B12 — Not Folate — Is the Real Problem
- Where the Excess Folate Comes From
- Who Is Most at Risk
- How B12 Is Checked Before High-Dose Folate
- Sequencing and Treatment
- When to Seek Care / Red Flags
- Key Research Papers
- Connections
- Featured Videos
What “Masking” Looks Like
Masking is not a symptom you feel — it is a symptom you stop feeling, while the real danger continues underneath. To picture it, it helps to know how a vitamin B12 deficiency normally announces itself, because it does so along two separate tracks.
- The blood track. B12 deficiency typically causes megaloblastic anemia — the bone marrow makes red blood cells that are too few, too large, and immature. This produces the familiar signs of anemia: tiredness, breathlessness on exertion, pallor, and a fast heartbeat. Crucially, this shows up on a routine Complete Blood Count as a high MCV (mean cell volume) — a red flag a doctor can hardly miss.
- The nerve track. Independently, B12 deficiency damages the nervous system. The classic injury is subacute combined degeneration of the spinal cord — the protective myelin sheath frays along specific spinal pathways — producing numbness and tingling in the feet and hands, unsteady balance, and, if it goes far enough, weakness and cognitive change. This damage can become permanent.
Here is the trap. Folic acid can correct the blood track — the anemia improves, the MCV falls back toward normal, the fatigue lifts — while doing nothing for the nerve track. So a person feels better, their blood test looks reassuring, and the obvious clue that would have triggered a B12 test (the macrocytic anemia) quietly disappears. Meanwhile the silent erosion of the spinal cord and peripheral nerves grinds on. By the time numbness, imbalance, or memory trouble force the issue, months may have passed and some of the nerve injury may no longer be reversible.
In short, masking is a story of false reassurance: the warning light gets switched off while the fire still burns. That is why this is the central, clinically important hazard of high folic acid intake — not toxicity in the usual sense, but a hidden delay in diagnosing a different deficiency.
The Mechanism: Why Folate Fixes the Blood but Not the Nerves
To understand why one vitamin can paper over a shortage of another, you have to see where they overlap and where they part ways. Folate (vitamin B9) and vitamin B12 are partners in a single chemical task — but only one of them does a second job the other cannot touch.
The shared job: making DNA. Every time a cell divides, it must copy its DNA, and that requires a steady supply of the DNA building block thymidine. Folate, in its active form, donates the carbon atoms needed to build it. But there is a catch: the body keeps much of its folate locked in a storage form (5-methyltetrahydrofolate), and the only enzyme that unlocks it for DNA work is one that requires vitamin B12. This reaction — in which B12 transfers a methyl group, converting the amino acid homocysteine into methionine — simultaneously frees folate to re-enter the DNA-building cycle.
When B12 is missing, that unlocking step stalls, and active folate gets trapped in its storage form — the so-called “methylfolate trap.” Functionally, the cell now behaves as if it were folate-deficient even when folate is plentiful. The fastest-dividing cells — the red-cell factory in the bone marrow — feel it first, and the result is the same megaloblastic anemia you would see from a true folate shortage. This is the key insight: the anemia of B12 deficiency is, at the cellular level, a folate problem. So when you flood the system with extra folic acid, you bypass the trap — there is now enough free folate to keep DNA synthesis (and red-cell production) going despite the B12 shortfall. The anemia heals.
The job folate cannot do: maintaining myelin. Vitamin B12 has a second, entirely separate role that folate cannot substitute for. It is a required cofactor for an enzyme (methylmalonyl-CoA mutase) involved in handling certain fats and in maintaining the myelin that insulates nerves. When B12 runs low, this pathway fails too — and no amount of folate can rescue it, because folate is simply not part of that reaction. The nerve damage therefore proceeds unchecked, even as the blood picture is rescued by folic acid.
An analogy. Imagine B12 is the only key to a warehouse holding two kinds of supplies: bricks (for building cells) and insulation (for wiring). Without the key, both are locked away. Pouring in extra folic acid is like trucking in a separate, emergency supply of bricks through a side door — the building keeps going up, so from the street everything looks fine. But there is no side door for the insulation. The wiring keeps degrading behind the walls, and because the building looks healthy from outside, no one calls the electrician until the lights start flickering.
That is the whole mechanism in one image: both vitamins converge on DNA synthesis, so folate can fix the blood; only B12 maintains the nerves, so folate cannot fix them. One symptom is silenced; the dangerous one is not.
Possibly worse, not only hidden. A 2024 review by Miller, Smith, Troen, Mason, Jacques and Selhub reports that high-dose folic acid given to patients with pernicious anemia or epilepsy caused significant falls in serum B12, and that people with low B12 and high folate have lower cognitive test scores and higher blood homocysteine and methylmalonic acid than people with low B12 and normal folate. The authors summarize a hypothesis that high-dose folic acid depletes holotranscobalamin (the “active” B12 carried to cells in the blood), which would make a B12 deficiency worse rather than just hide it. They state that this evidence is “primarily correlative or from uncontrolled clinical observations” and that the hypothesis “has not yet been tested.”
An Honest Caveat: How Common Masking Is
It is important to be candid here, because masking is easy to exaggerate. Two things are simultaneously true: this is a real and well-documented phenomenon, and it is not something that happens to most people who take a folate-containing supplement.
- The classic, indisputable form is high-dose folic acid. The clearest masking comes from large therapeutic doses (historically 1–5 mg or more daily, the kind once used to treat anemia; the 2024 review by Miller and colleagues puts the 1940s–1950s pernicious-anemia doses at more than 5 mg a day) given to a person whose anemia was actually from B12. This is genuine, was the basis for the long-standing 1 mg-per-day upper limit on folic acid, and is the reason clinicians are taught to never treat a macrocytic anemia with folate before knowing the B12 level.
- Whether ordinary fortification masks B12 deficiency at the population level is genuinely debated. Since many countries began adding folic acid to flour to prevent neural tube defects in pregnancy, researchers have asked whether this lower-level, universal exposure delays B12 diagnoses. In 1,459 older adults in the 1999–2002 US national nutrition survey (Morris 2007), people with low B12 and high blood folate (above 59 nmol/L) had more anemia (odds ratio 3.1) and more cognitive impairment (odds ratio 2.6) than people with low B12 and lower folate — while in people with normal B12, high folate went with less cognitive impairment (odds ratio 0.4); other reviews conclude the population-level masking risk is small and outweighed by fortification's clear benefit in preventing birth defects. The honest summary is that the food-supply dose is far less likely to mask than a deliberate high-dose supplement, and the debate is about magnitude, not whether to fortify.
- Most people taking a normal multivitamin are not at high risk of masking. A typical multivitamin contains around 400 mcg of folic acid. Masking becomes a real concern mainly when (a) the dose is high and (b) the person genuinely has an undiagnosed B12 deficiency. The point is not that folate is dangerous; it is that high-dose folate taken without knowing the B12 status can hide a B12 deficiency.
So this page is about checking B12 first, not about fearing folate. Folate prevents birth defects, supports healthy methylation and homocysteine handling, and is one of the safer vitamins. The masking problem is specifically about order of operations: the B12 status is known before the folate is poured in.
Clues That B12 — Not Folate — Is the Real Problem
Because masking hides the obvious blood clue, the warning signs that remain are the neurological ones — and they deserve special attention in anyone taking folate. The pattern that clinicians treat as a reason for a B12 check is:
- Numbness, tingling, or “pins and needles,” usually starting in both feet and sometimes the hands — a symmetric “stocking-glove” distribution. This is the most common early neurologic sign and overlaps with peripheral neuropathy.
- Unsteady balance, especially in the dark or with eyes closed — a feeling of not knowing quite where your feet are. This reflects damage to the spinal cord's position-sense pathways and is a hallmark of subacute combined degeneration.
- Memory, concentration, or mood changes — B12 deficiency can cause cognitive slowing and depression. Critically, the landmark research showed these can appear without any anemia or enlarged red cells at all, which is exactly the scenario masking creates.
- A normal-looking blood count that doesn't fit the symptoms. The most telling clue of all: neurological symptoms in someone whose blood count is reassuringly normal — particularly if they take folic acid — is the classic sign that folate may be hiding a B12 problem rather than ruling it out.
Overlap with other causes. None of these symptoms is unique to B12 deficiency. Numbness and balance trouble are also caused by diabetes, alcohol, thyroid disease, medications, and ordinary aging; fatigue and low mood have countless causes. The point is not that these symptoms prove a B12 deficiency — it is that, in a person on folate, a normal blood count does not explain them away. The whole danger of masking is that the normal blood count is misleading. (For the closely related issue of high circulating unmetabolized folic acid, see the sibling page.)
Where the Excess Folate Comes From
Unlike most vitamin-excess problems, masking is rarely about food — you cannot eat enough spinach or lentils to mask a B12 deficiency, because natural food folate is not delivered in the concentrated, fully-available form that high-dose folic acid is. The relevant excess almost always comes from folic acid, the synthetic form used in supplements and food fortification:
- High-dose folic acid supplements. The classic culprit. Single-ingredient folic acid tablets of 1 mg, 5 mg, or higher are sold over the counter and prescribed for various reasons (anemia work-ups, certain medications, kidney disease). A person who self-treats fatigue or a “low blood count” with high-dose folic acid, without a B12 test, is the textbook masking scenario.
- Fortified foods. In the United States and many other countries, folic acid is added to enriched flour, bread, pasta, cereal, and rice. A diet heavy in fortified grains plus a multivitamin can add up to a meaningful daily folic acid intake — lower-risk than a high-dose pill, but not zero.
- Multivitamins and prenatal vitamins. Most contain folic acid (commonly 400–800 mcg). This is exactly the right thing for women who could become pregnant, and the masking risk in that group is low — but it underlines why B12 status matters for anyone also at risk for B12 deficiency.
- “B-complex” and energy products. Combination supplements may contain substantial folic acid. Helpfully, many B-complex products also contain B12 — which mitigates the risk — but the doses are not always matched, and a folate-heavy formula can still mask.
The common thread is concentrated synthetic folic acid taken without knowing the B12 status. The long-standing clinical answer is not avoiding folate but pairing it with a one-time look at B12.
Who Is Most at Risk
Masking only matters in someone who actually has, or could develop, a vitamin B12 deficiency. The groups below combine a meaningful chance of low B12 with a realistic chance of taking folate — and for them, the B12 status matters most.
- Older adults. This is the highest-priority group. With age, stomach acid and intrinsic factor decline, and B12 absorption falls; B12 deficiency is genuinely common in people over 60. Older adults also take multivitamins and fortified foods, and their early neurologic symptoms are easy to write off as “just aging.” Folic acid masking the anemia in an older person is the scenario most likely to cause real harm.
- Vegans and long-term vegetarians. Vitamin B12 comes almost exclusively from animal foods, so people who avoid meat, eggs, and dairy without supplementing B12 are at clear risk of deficiency — while often eating plenty of folate-rich plants and taking plant-based multivitamins. This is a classic high-folate, low-B12 pairing.
- People taking metformin. The widely used type 2 diabetes drug metformin reduces B12 absorption, and long-term use measurably lowers B12 levels. In a randomized placebo-controlled trial in 390 insulin-treated people with type 2 diabetes (de Jager 2010), 850 mg of metformin three times a day for 4.3 years lowered B12 by 19% compared with placebo, and B12 deficiency at the end of the trial was 7.2 percentage points more common — one extra case for every 13.8 people treated. Many people with diabetes also take multivitamins, so the masking setup is common. The trial's authors concluded that “regular measurement of vitamin B-12 concentrations during long term metformin treatment should be strongly considered.”
- People with malabsorption or stomach/gut surgery. Pernicious anemia (an autoimmune loss of intrinsic factor), atrophic gastritis, celiac or Crohn's disease, and surgeries that remove or bypass parts of the stomach or small intestine all impair B12 absorption.
- Acid-suppressing medications. Long-term proton-pump inhibitors and H2 blockers reduce the stomach acid needed to release B12 from food, modestly raising deficiency risk over years.
For people in these groups who take — or are about to start — folic acid, a B12 blood test is the step that reveals a hidden deficiency. (For broader context on the anemia itself, see Anemia.)
How B12 Is Checked Before High-Dose Folate
The good news is that detecting the hidden problem is straightforward and inexpensive. The long-standing clinical principle that prevents masking is simple: the B12 status is established before, or at the same time as, starting meaningful folate — and a macrocytic anemia is never treated with folate alone.
- Serum vitamin B12. The first-line test is a direct vitamin B12 blood level. A clearly low value confirms deficiency. Its main limitation is a wide “gray zone” in the low-normal range, where the level looks acceptable but tissue B12 may still be inadequate — which is where the next tests earn their place.
- Methylmalonic acid (MMA). This is the most useful tie-breaker, because it rises when B12 is functionally deficient but is not affected by folate. A high methylmalonic acid points specifically to B12 deficiency — even when the serum B12 is borderline and even when folate is plentiful. It is the test that sees through masking.
- Homocysteine. A homocysteine level rises in both folate and B12 deficiency, so on its own it cannot separate the two — but paired with a normal-or-high folate and a high methylmalonic acid, it helps build the case for B12 as the culprit.
- Complete Blood Count, read carefully. A Complete Blood Count still belongs in the work-up — but with a caveat that is the heart of this page: in someone taking folic acid, a normal MCV and hemoglobin do not rule out B12 deficiency, because the folate may have corrected exactly those values. Reassuring red cells in a folate-taker are not reassurance about B12.
In practice, for someone starting high-dose folic acid, or with unexplained neurologic symptoms while taking folate, the short list that closes the masking loophole is a B12 level — and a methylmalonic acid if the B12 is borderline.
Sequencing and Treatment
Managing this is less about treating a toxicity and more about getting the order right so a B12 deficiency is found and treated promptly. Folate itself is not the problem; the order is.
- B12 first — the core principle. The long-standing clinical rule is that B12 adequacy is confirmed before therapeutic-dose folic acid is started. If both are low, the rule is to replace B12 first (or at least alongside folate), never folate alone, so the nerves are protected while the blood is corrected.
- A B12 deficiency is treated directly. Treatment is replacement — either vitamin B12 injections (used when absorption is the problem, as in pernicious anemia, and for severe or neurologic cases) or high-dose oral B12, which works for many people because a small fraction is absorbed by passive diffusion that does not need intrinsic factor. The choice depends on the cause and severity.
- Time matters for the nerves. The reason masking is dangerous is that neurologic damage can become permanent. The earlier B12 is replaced, the better the recovery; many people improve substantially, but long-standing subacute combined degeneration may leave lasting deficits. This is why a delayed diagnosis is the real cost of masking.
- Folate usually continues. Once B12 is being replaced, continuing appropriate folate is fine and often beneficial — the problem was never the folate itself, only taking it without knowing the B12 status.
- The underlying cause. Reviewing metformin use (with monitoring rather than necessarily stopping), looking for malabsorption, and routine B12 for vegans are the usual ways the deficiency is kept from recurring.
For people on long-term metformin, on a long-term vegan diet, or simply over 60 and taking supplements, periodic B12 monitoring catches a shortfall on a lab report long before it reaches the nerves.
When to Seek Care / Red Flags
Because masking removes the usual warning sign, the signs that call for prompt medical assessment are mostly neurological — and they matter more, not less, in someone who takes folic acid and feels otherwise well:
- New or worsening numbness, tingling, or burning in both feet or hands — especially a symmetric pattern that is creeping upward over weeks to months.
- Unsteadiness or frequent stumbling, particularly difficulty walking in the dark or a sense of not feeling the ground — these point to spinal-cord involvement and warrant prompt evaluation.
- New memory loss, confusion, or marked low mood, particularly in an older adult — cognitive change from B12 deficiency can occur without anemia and is more recoverable when caught early.
- Neurologic symptoms while taking folic acid with a “normal” blood count — a reassuring complete blood count (CBC) does not rule out B12 deficiency, because the normal count may be the masking at work.
- Being in a high-risk group (older, vegan, on metformin, malabsorption) and having any unexplained neurologic symptoms — this combination is the classic reason for a B12 (and, if borderline, methylmalonic acid) check without delay.
None of these is an emergency in the minute-to-minute sense, but they are time-sensitive: the value of catching a masked B12 deficiency lies entirely in catching it before the nerve damage sets. When neurologic symptoms appear in anyone taking folate, a work-up that includes B12 — not just the blood count — is what finds the masked deficiency.
Key Research Papers
- Lindenbaum J, Healton EB, Savage DG, et al. (1988). Neuropsychiatric Disorders Caused by Cobalamin Deficiency in the Absence of Anemia or Macrocytosis. New England Journal of Medicine;318(26):1720-1728. — DOI: 10.1056/NEJM198806303182604. — doi:10.1056/NEJM198806303182604
- Healton EB, Savage DG, Brust JCM, et al. (1991). Neurologic Aspects of Cobalamin Deficiency. Medicine (Baltimore);70(4):229-245. — DOI: 10.1097/00005792-199107000-00001. — doi:10.1097/00005792-199107000-00001
- Reynolds E (2006). Vitamin B12, folic acid, and the nervous system. The Lancet Neurology;5(11):949-960. — DOI: 10.1016/S1474-4422(06)70598-1. — doi:10.1016/S1474-4422(06)70598-1
- Morris MS, Jacques PF, Rosenberg IH, Selhub J (2007). Folate and vitamin B-12 status in relation to anemia, macrocytosis, and cognitive impairment in older Americans in the age of folic acid fortification. The American Journal of Clinical Nutrition;85(1):193-200. — DOI: 10.1093/ajcn/85.1.193. — doi:10.1093/ajcn/85.1.193
- Selhub J, Morris MS, Jacques PF, Rosenberg IH (2009). Folate–vitamin B-12 interaction in relation to cognitive impairment, anemia, and biochemical indicators of vitamin B-12 deficiency. The American Journal of Clinical Nutrition;89(2):702S-706S. — DOI: 10.3945/ajcn.2008.26947c. — doi:10.3945/ajcn.2008.26947c
- Allen LH (2009). How common is vitamin B-12 deficiency? The American Journal of Clinical Nutrition;89(2):693S-696S. — DOI: 10.3945/ajcn.2008.26947a. — doi:10.3945/ajcn.2008.26947a
- de Jager J, Kooy A, Lehert P, et al. (2010). Long term treatment with metformin in patients with type 2 diabetes and risk of vitamin B-12 deficiency: randomised placebo controlled trial. BMJ;340:c2181. — DOI: 10.1136/bmj.c2181. — doi:10.1136/bmj.c2181
- Stabler SP (2013). Vitamin B12 Deficiency. New England Journal of Medicine;368(2):149-160. — DOI: 10.1056/NEJMcp1113996. — doi:10.1056/NEJMcp1113996
- Paul C, Brady DM (2017). Comparative Bioavailability and Utilization of Particular Forms of B12 Supplements With Potential to Mitigate B12-Related Genetic Polymorphisms. Integrative Medicine (Encinitas);16(1):42-49. — PubMed PMID: 28223907
- Paul L, Selhub J (2017). Interaction between excess folate and low vitamin B12 status. Molecular Aspects of Medicine;53:43-47. — DOI: 10.1016/j.mam.2016.11.004. — doi:10.1016/j.mam.2016.11.004
- Mills JL, Molloy AM, Reynolds EH (2018). Do the benefits of folic acid fortification outweigh the risk of masking vitamin B12 deficiency? (Head-to-head debate.) BMJ;360:k724. — DOI: 10.1136/bmj.k724. — PubMed PMID: 29496696
- Miller JW, Smith A, Troen AM, Mason JB, Jacques PF, Selhub J (2024). Excess Folic Acid and Vitamin B12 Deficiency: Clinical Implications? Food and Nutrition Bulletin;45(1_suppl):S67-S72. — DOI: 10.1177/03795721241229503. — PubMed PMID: 38987872
PubMed Topic Searches
Connections
- All Vitamins
- Folate / Folic Acid Excess Hub
- Unmetabolized Folic Acid
- Vitamin B9 (Folate) Overview
- Folate, Methylation & Homocysteine
- Folate & Neural Tube Defects
- Vitamin B12 Overview
- Vitamin B12 Blood Test
- Homocysteine Test
- Complete Blood Count
- Anemia
- Peripheral Neuropathy
- Diabetes (Metformin)
- Beef Liver (B12 & Folate Source)
- Spinach (Folate Source)
- Lentils (Folate Source)