Biotin (Vitamin B7) Deficiency: Skin Rashes
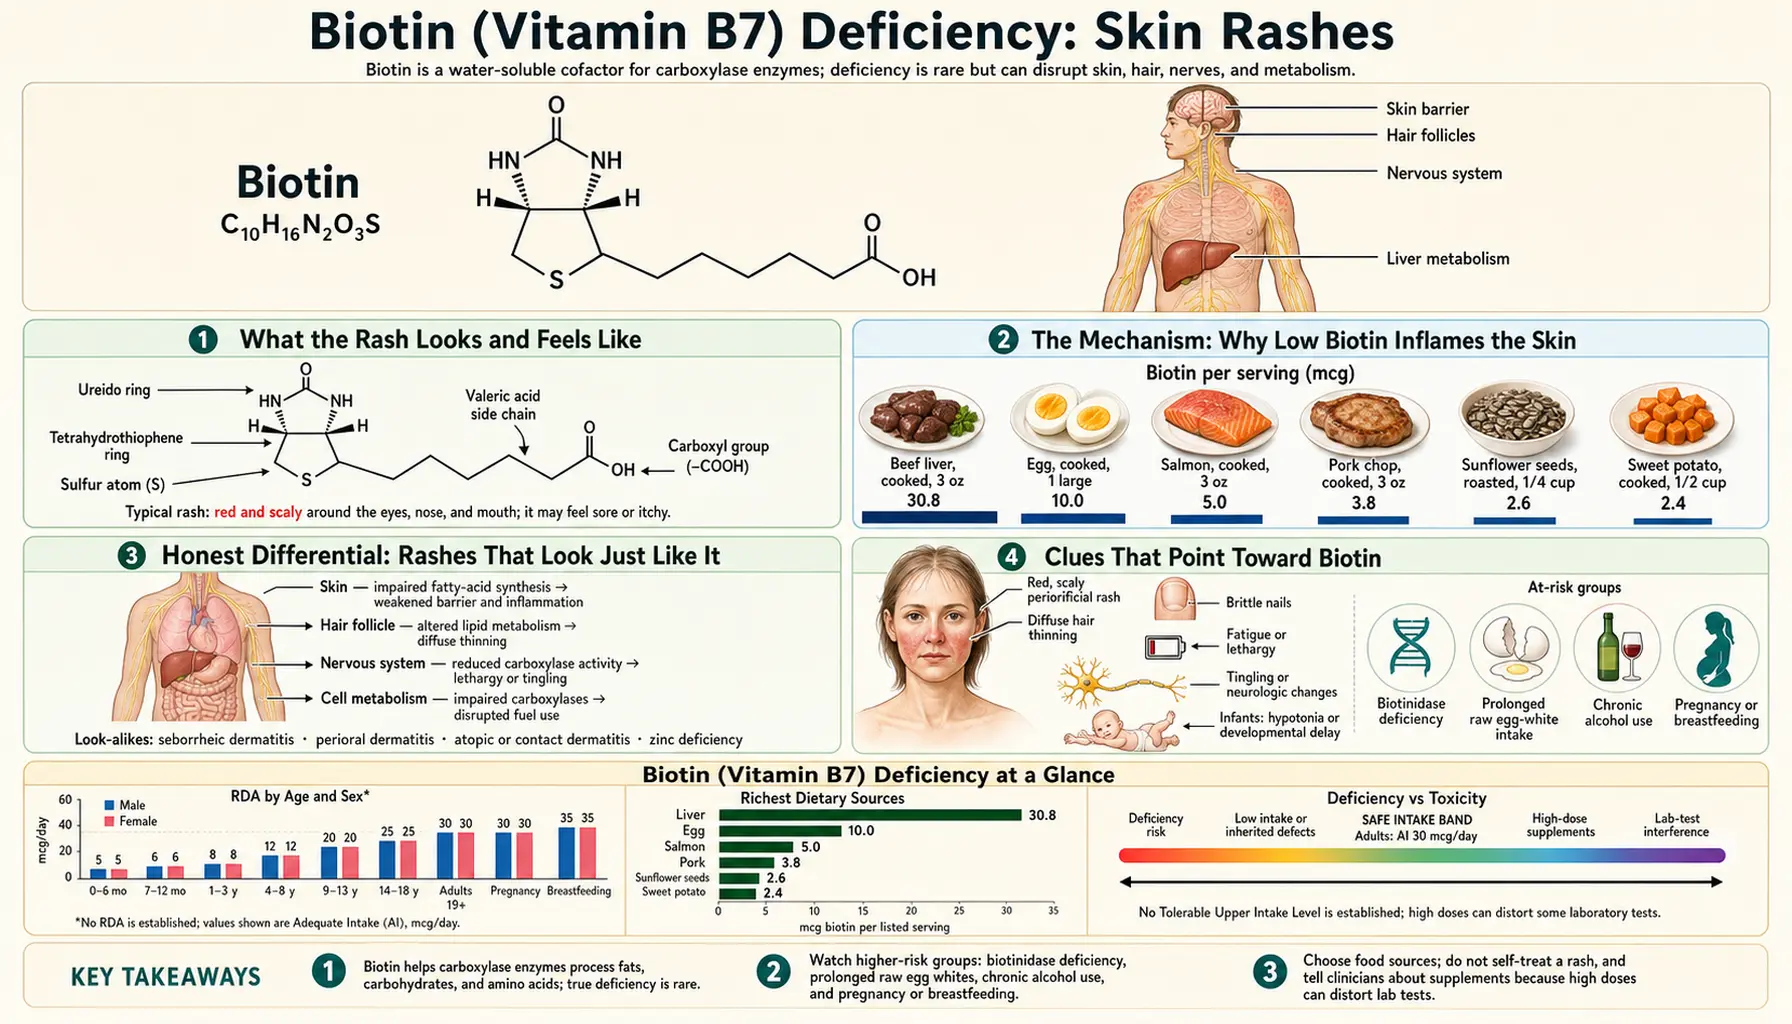
The skin rash of biotin deficiency has a distinctive look: a red, scaly, flaking dermatitis that tends to gather around the openings of the face — the edges of the eyes, the creases beside the nose, and the corners of the mouth. Doctors call this a periorificial pattern (“around the orifices”). In babies it can look more like stubborn cradle-cap-style seborrheic dermatitis. The honest headline, from the start: this exact rash is not unique to biotin deficiency. The closest mimic — zinc deficiency (acrodermatitis enteropathica) — looks almost identical, and ordinary eczema and seborrheic dermatitis are vastly more common. True biotin deficiency is uncommon. This page explains what the rash looks like, why low biotin produces it, how to tell it apart from its far more frequent look-alikes, and what actually fixes it.
Table of Contents
- What the Rash Looks and Feels Like
- The Mechanism: Why Low Biotin Inflames the Skin
- Honest Differential: Rashes That Look Just Like It
- Clues That Point Toward Biotin
- What Actually Causes Biotin Deficiency
- Getting Diagnosed
- Correcting It: Food, Supplements, and the Real Fix
- When to Seek Care / Red Flags
- Key Research Papers
- Connections
- Featured Videos
What the Rash Looks and Feels Like
The dermatitis of biotin deficiency is usually described by a small cluster of features that tend to appear together. None of them, taken alone, proves biotin is the cause — but the pattern is what dermatologists recognize:
- Red, scaly, flaking skin (a “dermatitis”) — patches that are pink to dull red, dry, and shedding fine or greasy scale. The surface can look chapped, crusted, or cracked, and may weep slightly when it is rubbed or scratched.
- A periorificial distribution — the rash characteristically rings the openings of the face: the rims and corners of the eyes, the folds running from the nose to the mouth (the nasolabial creases), and the angles of the lips. In more advanced cases it spreads to the scalp, and the diaper/genital area in infants.
- Cracking at the corners of the mouth — sore, fissured splits at the lip angles, sometimes called angular cheilitis. (This overlaps heavily with deficiencies of other B vitamins, especially riboflavin (B2).)
- Itch and irritation — the patches are often itchy or stinging rather than painful. Constant scratching can thicken the skin and invite a secondary infection, particularly with a yeast (Candida) on top.
- An infantile, “cradle cap” look — in babies the rash frequently resembles seborrheic dermatitis: greasy yellow-brown scale on the scalp, brows, and skin folds. In the rare inherited disorders of biotin handling, this seborrheic-type rash appears alongside hair loss and is one of the first visible clues.
Two companions almost always travel with the deficiency rash, and they matter for recognition: thinning or shedding hair (see Hair Loss) and, over time, weak, splitting nails (see Brittle Nails). Skin, hair, and nails are all built by fast-dividing cells, so they tend to falter together. A rash on its own, with perfectly normal hair and nails and no other symptoms, points away from a true biotin deficiency rather than toward it.
The Mechanism: Why Low Biotin Inflames the Skin
Biotin (vitamin B7) is not directly a “skin vitamin.” Its real job is to act as a helper molecule — a cofactor — for a small family of enzymes called carboxylases. There are five of them in humans, and they sit at key junctions of metabolism: building fatty acids, breaking down certain amino acids and odd-chain fats, and feeding the body's energy and glucose-making pathways. To work, each carboxylase must have a biotin molecule clipped onto it (a step performed by an enzyme called holocarboxylase synthetase). When biotin runs low, these enzymes are left partly “uncapped” and lose activity.
The skin connection runs largely through fatty-acid metabolism. One of the biotin-dependent enzymes, acetyl-CoA carboxylase, performs the first committed step in making fatty acids. The skin barrier — the brick-and-mortar layer that holds moisture in and irritants out — is built from lipids, and it relies on a steady supply of certain fats, including essential omega-6 fatty acids. Biotin researcher Donald Mock tested this in rats. Five rats fed an egg-white diet (which blocks biotin) developed the typical skin lesions of biotin deficiency, while five rats on the same diet that also received a fat emulsion rich in linoleic acid (an omega-6 fatty acid) did not — even though both groups were equally short of biotin. From this rat experiment he concluded that a disturbance of omega-6 polyunsaturated fatty-acid metabolism — not a lack of biotin in the skin itself — drives the cutaneous rash. The direct test was done in animals; in people, abnormal fatty-acid profiles have been detected in biotin deficiency, but the causal link has not been tested in the same way. In other words, the rash is a downstream consequence: starve the skin's fat-building machinery, and the barrier weakens, dries, scales, and inflames.
An analogy. Picture the skin barrier as a brick wall whose mortar is made fresh each day by a small crew of workers. Biotin is the tool that lets those workers mix the mortar. Remove the tool and the wall isn't demolished overnight — but no fresh mortar gets made, so the existing mortar dries, cracks, and crumbles at the most stressed seams first. On the face, the most stressed seams are the folds and edges around the eyes, nose, and mouth, which is exactly where the rash shows up. Hand the workers their tool back (restore biotin) and they resume mixing mortar; the wall is repointed and the rash heals.
This also explains why the rash is rarely a stand-alone problem. The same uncapped carboxylases that disturb skin lipids also disrupt energy and amino-acid metabolism elsewhere, which is why a genuine deficiency usually arrives as a package — rash plus hair loss plus, in more severe or inherited cases, neurological symptoms (see Neurological Symptoms). The most dramatic version is seen in the inborn errors of biotin handling, multiple carboxylase deficiency and biotinidase deficiency, where multiple carboxylases fail at once and the skin, hair, and nervous system are all hit.
Honest Differential: Rashes That Look Just Like It
This is the most important section on the page, because the single biggest mistake people make is to see a scaly facial rash, read that biotin deficiency causes scaly facial rashes, and conclude they must be biotin-deficient. In reality, a red, scaly, periorificial rash is a final common appearance that many far more frequent conditions produce. Biotin deficiency is near the bottom of that list by sheer frequency. Honest possibilities include:
- Zinc deficiency (acrodermatitis enteropathica) — the closest mimic by far. Low zinc produces a strikingly similar red, scaly, crusted rash in the very same periorificial and diaper-area distribution, often with hair loss and diarrhea. The two deficiencies are so alike clinically that they are routinely considered together; see Zinc Deficiency: Skin Rashes. Because zinc deficiency is more common than biotin deficiency, it is often the more likely answer when this rash appears.
- Seborrheic dermatitis — extremely common, harmless, and unrelated to any vitamin lack. It produces greasy, yellowish scale on the scalp, eyebrows, sides of the nose, and behind the ears, and in infants it is the familiar “cradle cap.” Because the infantile biotin rash looks like seborrheic dermatitis, ordinary cradle cap is mistaken for a deficiency far more often than the reverse.
- Eczema (atopic dermatitis) — a very common itchy, red, scaly inflammatory skin condition, frequently lifelong and allergy-related. It is not caused by biotin deficiency. See Eczema.
- Other B-vitamin and nutrient gaps — deficiency of riboflavin (B2) classically causes cracked lip corners and a scaly dermatitis around the nose and mouth, and niacin (B3) deficiency (pellagra) causes a sun-exposed scaly rash. Essential-fatty-acid deficiency causes a similar dry, scaly dermatitis. These overlap so much that a rash alone cannot single out biotin.
- Perioral / periorificial dermatitis (the dermatologic entity) — a common rash of small red bumps and scale around the mouth, nose, or eyes, often triggered by topical steroid creams or certain cosmetics. Despite the matching name, it has nothing to do with biotin.
- Contact dermatitis and psoriasis — irritant or allergic reactions, and the silvery-scaled plaques of psoriasis, can both be mistaken for a nutritional rash.
The honest bottom line: a scaly facial rash is common; biotin deficiency is uncommon. Biotin does not treat eczema, seborrheic dermatitis, or zinc deficiency, so a biotin supplement taken for the rash alone usually does nothing for it — and (as covered below) it can interfere with lab tests and delay the correct diagnosis.
Clues That Point Toward Biotin
If a scaly rash has so many causes, when does biotin deficiency become a reasonable suspect? A few features raise it from “very unlikely” to “worth testing for”:
- The full triad, not just skin. A genuine deficiency tends to bring the rash together with hair thinning or loss and, over weeks, brittle nails. A periorificial rash accompanied by diffuse hair shedding is more suggestive than a rash by itself. (Still not specific — zinc deficiency does the same thing.)
- A plausible cause is present. Biotin deficiency does not strike out of a clear sky. There is almost always a reason: long-term intravenous (parenteral) nutrition without added biotin, prolonged use of certain anti-seizure drugs, heavy alcohol use, or — the famous one — eating large amounts of raw egg white over time (see Causes below). If none of these fits, biotin deficiency becomes much less likely.
- An infant with cradle-cap-like rash plus hair loss, floppy tone, or seizures. In babies, the combination of a seborrheic-type rash with neurological signs is the red flag for the inherited disorders multiple carboxylase deficiency and biotinidase deficiency — rare but genuinely biotin-responsive, and detected by newborn screening in many countries.
- The rash improves only after biotin is replaced. When deficiency is real, the skin typically responds within days to weeks of restoring biotin — a response that does not happen if the true cause was eczema or seborrheic dermatitis.
The practical message: the rash points toward biotin chiefly when it is part of a bigger picture and a recognized cause is on the table. Otherwise, zinc deficiency and the common skin conditions above are far more likely explanations than biotin deficiency.
What Actually Causes Biotin Deficiency
Biotin is widespread in food and is also made by bacteria in the gut, so dietary deficiency in an otherwise healthy person eating a normal diet is rare. When a true deficiency does occur, it almost always traces to one of a short list of specific situations:
- Eating large amounts of raw egg white over time. Raw egg white contains a protein called avidin that binds biotin extremely tightly in the gut and blocks its absorption. Historic cases of “egg-white injury” appeared in people who ate many raw eggs daily for long stretches. Cooking denatures avidin, so cooked eggs are not a problem — they are, in fact, a good biotin source. See Eggs.
- Long-term intravenous (parenteral) nutrition without biotin. Before biotin was routinely added to intravenous-feeding formulas, adults and infants on prolonged parenteral nutrition developed the classic deficiency — scaly periorificial rash, hair loss, and neurological symptoms — that resolved when biotin was added. This is one of the best-documented real-world causes.
- Certain anti-seizure (anticonvulsant) medications. Long-term use of drugs such as phenytoin, carbamazepine, primidone, and phenobarbital can lower biotin status by interfering with its absorption and increasing its breakdown.
- Heavy alcohol use. Chronic alcohol intake impairs biotin absorption and is associated with lower biotin levels, layered on top of the broader poor nutrition that often accompanies it.
- Pregnancy. Research by Mock and colleagues found that about 50% of pregnant women have an abnormally raised urine level of 3-hydroxyisovaleric acid, a sensitive marker of low biotin. In a placebo-controlled trial of 26 such women, 300 micrograms (mcg) of biotin a day for 14 days lowered it, which the researchers read as evidence of a marginal (mild, subclinical) biotin deficiency in normal pregnancy, even on an ordinary diet. This marginal state usually does not produce an obvious rash, but it is a real and surprisingly common shift in biotin status.
- Inherited disorders of biotin handling. Biotinidase deficiency and holocarboxylase synthetase deficiency are genetic conditions in which the body cannot recycle or attach biotin properly. They cause a functional deficiency despite normal dietary intake and are the settings where biotin truly is lifesaving.
Note what is not on this list: a normal, varied diet. Biotin is found in eggs (cooked), liver and other organ meats (see Beef Liver), salmon, nuts and seeds, legumes, and many vegetables. For the great majority of people with a scaly rash, dietary biotin lack is not the explanation.
Getting Diagnosed
Because the rash is non-specific, the diagnosis of biotin deficiency leans on the story (is one of the causes above present?) plus, when needed, biochemical testing — and on a clinician examining the skin rather than a self-diagnosis from a photo on the internet.
Serum (blood) biotin is, somewhat surprisingly, not a reliable test — the level can look normal even when the body's biotin economy is genuinely short. The markers researchers trust are functional: the urine level of 3-hydroxyisovaleric acid (3-HIA), which rises when a biotin-dependent enzyme (3-methylcrotonyl-CoA carboxylase) falters, and the activity of propionyl-CoA carboxylase in lymphocytes, which falls in marginal deficiency. These specialized tests are used mainly in research and in suspected inherited disease, not for everyday rashes.
For the inherited disorders in infants, the key test is biotinidase enzyme activity, measured on the newborn-screening blood spot in many countries and confirmed with a dedicated blood assay if the screen is abnormal.
There is one more critically important point about testing — one that cuts the opposite way from what most people expect. Taking high-dose biotin supplements can throw off completely unrelated blood tests. Many common lab assays (for thyroid hormones, vitamin D, troponin used to diagnose heart attacks, and others) use a biotin-based detection chemistry, and a high level of biotin in the blood can produce falsely high or falsely low results. This has caused real diagnostic errors. So the irony is sharp: someone who self-treats a rash with high-dose biotin not only is unlikely to help the rash, but may also corrupt the very lab tests a doctor needs to find the real cause. This is covered in detail on the Biotin Lab-Test Interference page. In a 2017 study, six healthy adults took 10 mg of biotin a day (a dose common in over-the-counter supplements) for one week. The tests checked included thyroid hormones, parathyroid hormone, vitamin D, prolactin, ferritin and others: 9 of the 23 biotin-based tests were distorted — 5 of 8 competitive tests read falsely high and 4 of 15 sandwich tests read falsely low — while none of the 14 tests without biotin chemistry were affected (Li 2017).
Correcting It: Food, Supplements, and the Real Fix
When biotin deficiency is genuinely the cause, treatment is straightforward and the rash usually responds well. But because the rash is so often not biotin deficiency, the first principle is to confirm the cause — or at least to address the recognized trigger — rather than to reach reflexively for a supplement.
- Removing the cause. This is the real fix and is often all that is needed. Cooking denatures avidin, so cooked eggs no longer block biotin the way a long raw-egg-white habit does; long-term anti-seizure medication, heavy alcohol use, and intravenous-nutrition formulas without added biotin are the other recognised triggers. When the upstream problem is corrected, the downstream rash clears.
- Food first, in ordinary cases. For the common, mild concern about biotin intake, food more than covers needs. Good sources include cooked eggs, organ meats such as beef liver, salmon, nuts, seeds, legumes, and many vegetables. There is no official Recommended Dietary Allowance for biotin; the adult Adequate Intake (AI) is 30 micrograms (mcg) per day (set by the U.S. National Academies / U.S. National Institutes of Health (NIH) Office of Dietary Supplements), and a varied diet supplies this comfortably.
- Supplemental biotin, when there is a true deficiency. Replacing biotin when a real deficiency is confirmed reliably heals the skin, hair, and nails over weeks. Doses used clinically for deficiency are far higher than the 30 mcg Adequate Intake; in the inherited disorders below, daily doses of 5–20 mg are common.
- Lifesaving doses in the inherited disorders. In biotinidase deficiency and related conditions, daily pharmacologic biotin (commonly 5–20 mg) is genuinely curative for the skin and protective for the nervous system, and is taken lifelong under specialist care.
- Supplements for ordinary rashes. High-dose biotin marketed for “hair, skin, and nails” has little evidence behind it in people who are not deficient — reviews in the dermatology literature have called for rethinking this routine use. If your rash is eczema, seborrheic dermatitis, or zinc deficiency, biotin will not fix it, and (per the testing section above) it can muddy your lab results. See Biotin for Hair, Skin & Nails — the marketing claim vs the evidence.
If the cause is actually a different deficiency, the rash responds to correcting that one: a zinc-responsive rash clears with zinc, not biotin. Matching the treatment to the real cause is the whole point of getting the diagnosis right first.
When to Seek Care / Red Flags
A scaly rash is rarely an emergency, but clinics and hospitals treat the following features as urgent or as needing proper testing:
- An infant or young child with a spreading, crusted, periorificial or diaper-area rash — especially if combined with hair loss, poor feeding, unusual floppiness or stiffness, developmental slipping, or seizures. This combination can signal a treatable inherited disorder of biotin metabolism and needs urgent evaluation.
- A rash plus diffuse hair loss in someone on long-term intravenous (IV) nutrition, anti-seizure drugs, or with heavy alcohol use — a recognized setup for true deficiency that deserves proper testing, not guesswork.
- A rash that is rapidly spreading, weeping, blistering, intensely painful, or accompanied by fever — these point to infection or a more serious skin condition, not a simple nutritional rash.
- Signs of secondary infection — increasing redness, warmth, pus, golden crusting, or red streaks spreading from the patch.
- High-dose biotin taken for a facial rash. Biotin can distort thyroid, vitamin D, and heart-attack (troponin) blood tests and lead to wrong diagnoses; in the 2017 study above, 10 mg a day for one week distorted 9 of 23 biotin-based tests (see Lab-Test Interference).
- Any rash that does not clear, or that keeps coming back, deserves a proper look from a clinician to pin down the cause — eczema, seborrheic dermatitis, zinc deficiency, and biotin deficiency are all managed quite differently.
The reassuring counterpoint: the great majority of scaly facial rashes are common, benign skin conditions, not a vitamin deficiency at all. The reason to get it checked is precisely so the right cause — whatever it turns out to be — gets the right treatment.
Key Research Papers
- Zempleni J, Mock DM (1999). Biotin biochemistry and human requirements. The Journal of Nutritional Biochemistry;10(3):128-138. — DOI: 10.1016/s0955-2863(98)00095-3. — doi:10.1016/s0955-2863(98)00095-3
- Mock DM (1990). Evidence for a pathogenic role of ω6 polyunsaturated fatty acid in the cutaneous manifestations of biotin deficiency. Journal of Pediatric Gastroenterology and Nutrition;10(2):222-229. — DOI: 10.1097/00005176-199002000-00013. — doi:10.1097/00005176-199002000-00013
- Innis SM, Allardyce DB (1983). Possible biotin deficiency in adults receiving long-term total parenteral nutrition. The American Journal of Clinical Nutrition;37(2):185-187. — DOI: 10.1093/ajcn/37.2.185. — doi:10.1093/ajcn/37.2.185
- Mock NI, Malik MI, Stumbo PJ, Bishop WP, Mock DM (1997). Increased urinary excretion of 3-hydroxyisovaleric acid and decreased urinary excretion of biotin are sensitive early indicators of decreased biotin status in experimental biotin deficiency. The American Journal of Clinical Nutrition;65(4):951-958. — DOI: 10.1093/ajcn/65.4.951. — doi:10.1093/ajcn/65.4.951
- Stratton SL, Bogusiewicz A, Mock MM, Mock NI, Wells AM, Mock DM (2006). Lymphocyte propionyl-CoA carboxylase and its activation by biotin are sensitive indicators of marginal biotin deficiency in humans. The American Journal of Clinical Nutrition;84(2):384-388. — DOI: 10.1093/ajcn/84.2.384. — doi:10.1093/ajcn/84.2.384
- Mock DM, Quirk JG, Mock NI (2002). Marginal biotin deficiency during normal pregnancy. The American Journal of Clinical Nutrition;75(2):295-299. — DOI: 10.1093/ajcn/75.2.295. — doi:10.1093/ajcn/75.2.295
- Mock DM (2005). Marginal biotin deficiency is teratogenic in mice and perhaps humans: a review of biotin deficiency during human pregnancy and effects of biotin deficiency on gene expression and enzyme activities in mouse dam and fetus. The Journal of Nutritional Biochemistry;16(7):435-437. — DOI: 10.1016/j.jnutbio.2005.03.022. — doi:10.1016/j.jnutbio.2005.03.022
- Wolf B (2015). The story of biotinidase deficiency and its introduction into newborn screening: the role of serendipity. International Journal of Neonatal Screening;1(1):3-12. — DOI: 10.3390/ijns1010003. — doi:10.3390/ijns1010003
- Lipner SR (2018). Rethinking biotin therapy for hair, nail, and skin disorders. Journal of the American Academy of Dermatology;78(6):1236-1238. — DOI: 10.1016/j.jaad.2018.02.018. — doi:10.1016/j.jaad.2018.02.018
- Thompson KG, Kim N (2021). Dietary supplements in dermatology: a review of the evidence for zinc, biotin, vitamin D, nicotinamide, and Polypodium. Journal of the American Academy of Dermatology;84(4):1042-1050. — DOI: 10.1016/j.jaad.2020.04.123. — doi:10.1016/j.jaad.2020.04.123
- Li D, Radulescu A, Shrestha RT, Root M, Karger AB, Killeen AA, Hodges JS, Fan SL, Ferguson A, Garg U, Sokoll LJ, Burmeister LA (2017). Association of biotin ingestion with performance of hormone and nonhormone assays in healthy adults. JAMA;318(12):1150-1160. — DOI: 10.1001/jama.2017.13705. — PubMed PMID: 28973622
- U.S. National Institutes of Health, Office of Dietary Supplements. Biotin — Health Professional Fact Sheet (intakes, deficiency, sources). — NIH ODS Biotin Fact Sheet
PubMed Topic Searches
- PubMed: Biotin deficiency and periorificial dermatitis
- PubMed: Biotin deficiency and infantile seborrheic dermatitis
- PubMed: Acrodermatitis: zinc vs biotin deficiency
- PubMed: Biotin supplements and laboratory-test interference
- PubMed: Biotinidase deficiency, skin rash, and newborn screening
- PubMed: Biotin deficiency dermatitis clinical features
Connections
- All Vitamins
- Biotin Deficiency Hub
- Biotin Deficiency: Hair Loss
- Biotin Deficiency: Brittle Nails
- Biotin Deficiency: Neurological Symptoms
- Vitamin B7 (Biotin) Overview
- Biotin for Hair, Skin & Nails
- Multiple Carboxylase Deficiency
- Biotin Lab-Test Interference
- Zinc Deficiency: Skin Rashes and Acne
- Zinc Deficiency Hub
- Zinc Overview
- Eczema
- Vitamin B2 (Riboflavin)
- Vitamin B3 (Niacin)
- Eggs
- Beef Liver
- Salmon