 — July 26, 2026
· Cyclospora in the Lettuce Supply — What the 2026 Outbreak Actually Shows
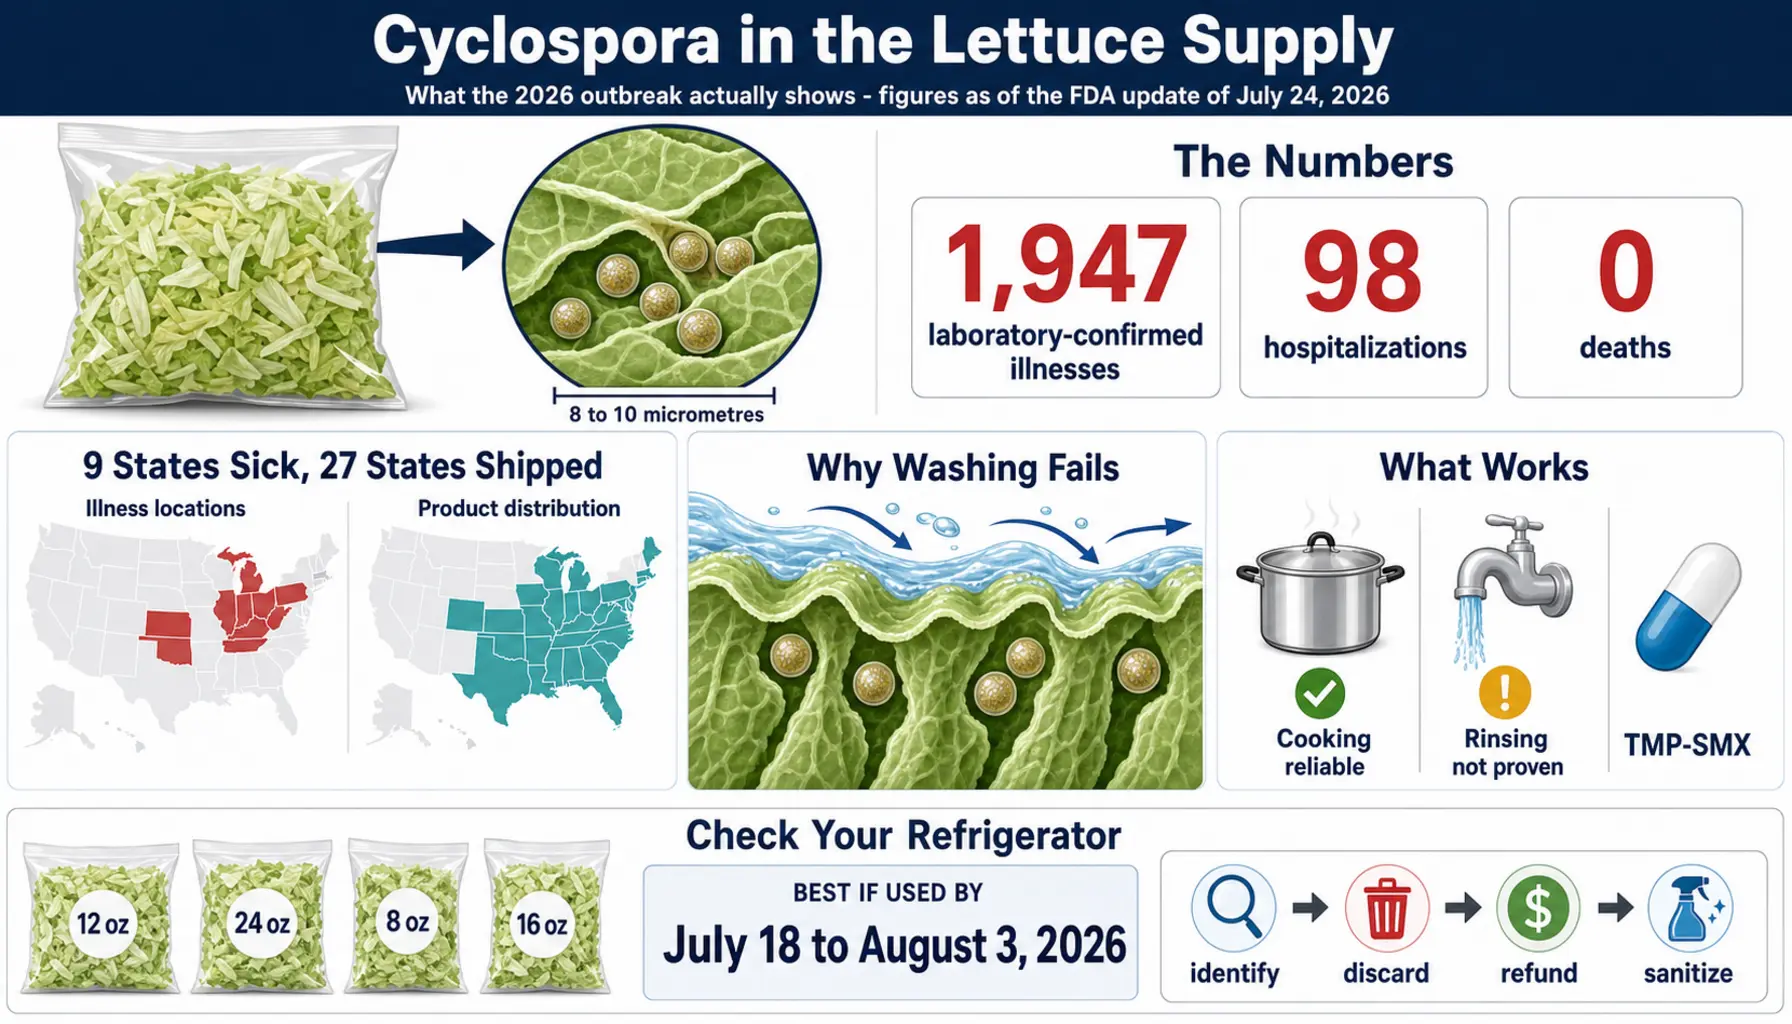
There is an active foodborne parasite outbreak in the United States, and its official numbers are easy to garble in retelling, because two different state counts are circulating and they measure two different things. This article walks through what the FDA and CDC say, as of their most recent updates at the time of writing, and separates that from what has been garbled in retelling.
The organism is Cyclospora cayetanensis, a single-celled parasite roughly eight to ten micrometres across — smaller than the width of a human hair. Investigators linked it to shredded iceberg lettuce. Washing has not been shown to reliably remove it. It is not thought to spread directly from person to person. It causes an illness that can last for weeks and that characteristically seems to end and then comes back. And there is a specific, inexpensive, decades-old antibiotic combination that cleared it in a placebo-controlled trial — which makes the diagnosis unusually consequential.
A nine-part deep-dive series accompanies this article, because several of these threads need more room than a news piece allows. Those links are collected below.
Interactive Visualization Cyclospora: From Contaminated Field to Relapsing Illness — watch why washing cannot save the salad Follow the parasite from irrigation water to your gut: rinse the leaves and watch it survive, chill the field so it never ripens, then treat it with the drug that works — and the one that has no target on it. Launch →Table of Contents
- The Outbreak at a Glance
- The Recall: Products, Dates and Distribution
- Nine States or Twenty-Seven? The Number That Keeps Getting Garbled
- Why the Case Count Keeps Climbing After a Recall
- What Cyclospora Actually Is
- Why Washing the Lettuce Is Not Enough
- Why It Is Not Contagious — The Two-Week Delay
- The Symptom Signature: Duration, Not Severity
- Why a Normal Stool Test Does Not Rule It Out
- Treatment: What Actually Works
- The Ivermectin Question
- The “False Positive” That Was Not an All-Clear
- Key Points From the CDC and FDA Guidance
- Deep-Dive Series
- External Authoritative Resources
- Key Research Papers
- Connections
- Featured Videos
1. The Outbreak at a Glance
These are the figures from the FDA’s outbreak page as of its July 24, 2026 update. Numbers in an active outbreak move, so this is a dated snapshot rather than a permanent figure; the later and final counts are in the “Since then” note below the table.
| Measure | Figure (FDA, July 24, 2026) |
|---|---|
| Laboratory-confirmed illnesses | 1,947 (people with confirmed infection who reported eating at locations of a fast-food restaurant chain) |
| Hospitalizations | At least 98 |
| Deaths | 0 |
| States with illnesses | 9 — Illinois, Indiana, Kansas, Kentucky, Michigan, Ohio, Oklahoma, Pennsylvania, West Virginia |
| Illness onset range | June 22, 2026 – July 20, 2026 |
| Implicated food | Shredded iceberg lettuce from a single supplier, sourced from growers in central Mexico |
| Recall date | July 17, 2026 |
| Investigation status | Ongoing (as of July 24) |
The FDA is explicit that the illnesses in this outbreak are “a subset of the Cyclospora infections identified nationwide.” In other words, there is a baseline of cyclosporiasis in the United States every summer that has nothing to do with this lettuce; the outbreak count is the portion investigators have tied to this particular supply chain.
Since then (FDA and CDC updates, August 5 – October 2, 2026): on August 5 the outbreak definition was widened to include people who reported exposure either to the restaurant chain or to the recalled lettuce, and the count that day rose to 6,358 illnesses in 15 states. CDC declared the outbreak over on September 11, 2026, with a final count of 12,883 laboratory-confirmed illnesses from 21 states, 570 hospitalizations and 2 deaths. Both deaths were in Michigan, in people with significant underlying health conditions whose illness began before the July 17 recall. CDC’s final update gives illness onsets from June 14 through August 17, 2026. Confirmed foodservice distribution of the recalled lettuce grew to 31 states, with possible further distribution to eight more jurisdictions. In its closing update of October 2, FDA reported that onsite sampling in Mexico found Cyclospora in two environmental samples — a tank holding outgoing wastewater from the processing facility and a drainage ditch at one of the growers — while stating that there is not enough evidence to conclusively determine how the contamination occurred.
2. The Recall: Products, Dates and Distribution
On July 17, 2026, the supplier identified by FDA’s traceback, a processor based in Guanajuato, Mexico, announced it was voluntarily removing all iceberg lettuce sourced from central Mexico from the U.S. market, and initiated a recall the same day.
The recall covered one retail line, a store-brand product sold at a national retail chain, in these sizes and dates:
- Iceberg salad — 12 oz or 24 oz bags
- Shredded lettuce — 8 oz or 16 oz bags
- Best-if-Used-By dates: July 18, 2026 through August 3, 2026
According to FDA’s list of affected stores (last updated August 13, 2026), the retail product was sold in fifteen states: Alabama, Arkansas, Florida, Georgia, Indiana, Kansas, Kentucky, Louisiana, Missouri, Mississippi, Oklahoma, Tennessee, Texas, Virginia and West Virginia.
Separately, foodservice product — the lettuce that goes to restaurants rather than grocery shelves — was distributed June 29 through July 16, 2026. On the restaurant side, the illnesses were first linked to shredded iceberg lettuce served at locations of a fast-food restaurant chain; FDA reports that the chain committed to stop using lettuce from the supplier and was no longer using it as of July 17, 2026.
The recall notice told consumers who had bought the recalled lettuce to discard it immediately and not eat it, and stated that full refunds were available at the place of purchase; washing is not part of that instruction. FDA’s outbreak guidance adds cleaning and sanitizing any surfaces or containers the product touched, citing the risk of cross-contamination — the concern is not only the lettuce itself but whatever it has been sitting against. On July 24, FDA wrote that it encouraged the public “to continue to avoid all products listed” in the recall.
3. Nine States or Twenty-Seven? The Number That Keeps Getting Garbled
This is the single most-mangled fact in the coverage, and it is worth slowing down for, because both numbers are real and they are not in conflict.
- Nine states have reported illnesses in this outbreak: IL, IN, KS, KY, MI, OH, OK, PA, WV.
- Twenty-seven states received the recalled foodservice product, according to the recall notice (FDA’s list of retail states adds West Virginia, making twenty-eight states in all): AL, AR, CT, FL, GA, IA, IL, IN, KS, KY, LA, MA, MD, MI, MO, MS, NC, NH, NJ, OH, OK, PA, SC, TN, TX, VA, WI.
Merging the two lists produces the incorrect claim that people were sick across twenty-seven states. As of July 24 they were not: twenty-seven states is the footprint of the product; nine is the footprint of the illness. The distribution window is also easy to misread — the recall notice and FDA give it as June 29 through July 16. Both footprints grew later; the final figures are in the “Since then” note in section 1.
There is a second, subtler discrepancy, because it explains why a state health department may publish a larger number than the federal one. The FDA and CDC report only laboratory-confirmed cases. FDA notes that state data “may include both probable and confirmed cases” — probable cases being people whose symptoms and exposure history fit the outbreak but who never had a confirmatory test — and that state counts may also include initial reports not yet sent to CDC. Neither figure is wrong. They answer different questions, and a summary is only clear when it says which one it is quoting.
4. Why the Case Count Keeps Climbing After a Recall
It is natural to read “cases still rising” as “the recall did not work.” That is usually the wrong inference, for a mundane reason the FDA states plainly: it can take as long as six weeks for CDC and state officials to determine whether a sick person belongs to a given outbreak.
The chain is long. Someone becomes ill; they may wait days before seeking care; the clinician has to order the right test; the lab has to run it; the result goes to the state health department; the state has to interview the patient about what they ate; and for outbreak linkage the isolate may need molecular typing to confirm it matches the cluster. Cases reported in late July may have begun in mid-June.
The FDA also noted that part of the recent jump came from adding four new states to the outbreak definition — a change in the accounting boundary, not necessarily a surge in new infections. The illness onset dates, rather than the report dates, are what show whether an outbreak is still growing.
5. What Cyclospora Actually Is
Cyclospora cayetanensis is a coccidian protozoan — a single-celled parasite in the phylum Apicomplexa, the same broad group that contains Cryptosporidium, Toxoplasma and the malaria parasite Plasmodium. It is not a bacterium, not a virus, and not a worm. That last distinction turns out to matter enormously when we get to treatment.
It travels as an oocyst: a roughly 8–10 micrometre package wrapped in an environmentally hardened wall. Think of it less as a fragile cell and more as an armoured seed, built to survive outside a host.
One fact shapes everything else about this parasite: humans are its only known host. There is no established animal reservoir. Contamination of produce is therefore attributed to human faecal material reaching food, with water and soil contaminated by faecal matter the vehicles reviews describe — although in many outbreaks, this one included, the exact route is never conclusively determined. That is an uncomfortable thing to read about a bagged salad, and it places the problem upstream, in agricultural water and the supply chain, rather than in the household kitchen.
6. Why Washing the Lettuce Is Not Enough
This is the part that surprises many readers, because washing produce is close to a moral instinct. Two things work against washing here.
The wall. The oocyst is built to survive outside a host: in one laboratory study, sporulation was not affected after oocysts were held for a week at refrigerator (4 °C) or room (23 °C) temperature. CDC states that Cyclospora “is unlikely to be killed by routine chemical disinfection or sanitizing methods,” and FDA’s consumer guidance states that Cyclospora parasites are resistant to standard chlorine-based sanitizers. The research points the same way. A 1994 letter in The Lancet reported a Cyclospora outbreak associated with chlorinated drinking water. In a 2008 study, gaseous chlorine dioxide applied to basil and lettuce for 20 minutes reduced Cryptosporidium, Encephalitozoon and E. coli loads but did not affect Cyclospora sporulation. A 2025 study of agricultural water found that chlorine at 50 ppm and lower produced reductions in infectivity of less than one log, which were not statistically significant, for Cryptosporidium and for Eimeria tenella, a close relative used as a stand-in for Cyclospora. A review of inactivation methods found ozone more effective than chlorine or chlorine dioxide against protozoan parasites in water.
The surface. A lettuce leaf is not a smooth surface; at the scale of a ten-micrometre particle it is a landscape of ridges, veins and folds. Cyclospora oocysts also appear to cling more tightly than other parasites: in a 2021 study of berries rinsed under a cold tap for one minute, the wash removed on average at least 80% of Giardia and Cryptosporidium but less Cyclospora, which the authors wrote “seems to be stickier.” FDA’s guidance adds that commercial washing processes for pre-washed or pre-cut produce “may not be sufficient to remove the parasite.”
It is worth being precise about the strength of this claim: the evidence shows that consumer washing is not proven to reliably remove or inactivate this parasite — not that it is useless in every circumstance. FDA describes rinsing as “an appropriate first step but may not reliably eliminate the parasite.” Heat is the step the agencies describe as reliable: FDA’s guidance calls cooking to at least 158 °F (70 °C) “the safest option” for produce that can be cooked, stating that Cyclospora “cannot survive at these elevated temperatures,” and in the 2006 laboratory study no oocysts sporulated after exposure to 70 °C or 100 °C.
None of this means produce washing has no value: FDA and CDC guidance still lists rinsing under running water as a first step, and in the berry study a simple tap rinse removed most of the Giardia and Cryptosporidium. What the evidence does not support is treating a rinse as equivalent to discarding a recalled product.
7. Why It Is Not Contagious — The Two-Week Delay
Here is the quirk that makes Cyclospora behave unlike a stomach bug, and it is genuinely reassuring for households.
Oocysts shed by a sick person are not yet infectious. They leave the body immature. They then need time in the environment — “days to weeks,” in FDA’s words, and thought to be at least one to two weeks in favourable conditions, according to CDC — to sporulate, maturing into a form capable of infecting anyone. Only then are they infectious.
The consequences are worth spelling out:
- It is not thought to spread directly from person to person the way norovirus does; CDC describes direct person-to-person transmission as unlikely. Caring for a sick family member does not carry the same direct risk.
- Contamination happened long before anyone got sick. By the time a cluster of illnesses becomes visible, the implicated food has usually been eaten or thrown out. This is why traceback in these outbreaks is so painfully slow.
- It points investigators upstream — toward irrigation water and field sanitation — rather than at a sick employee at the end of the chain.
An analogy: it is a letter that has to sit in a warm mailbox for a week or two before it can be opened. That delay is the whole reason this parasite is both harder to trace and less frightening to live with than a norovirus outbreak.
8. The Symptom Signature: Duration, Not Severity
The FDA’s symptom list: watery diarrhoea with frequent bowel movements, loss of appetite, weight loss, stomach cramps and pain, bloating, increased gas, nausea and fatigue. Vomiting, body aches, headache and fever may occur. Notably, some infected people have no symptoms at all.
But the symptom list is not what distinguishes this from ordinary food poisoning. The distinguishing feature is the shape of the illness over time.
Most food poisoning is a fast arc: you feel dreadful for a day or three, then you turn the corner. Untreated cyclosporiasis does not do that. In FDA’s description it can run from a few days to a month or longer, and it characteristically remits and relapses — in the FDA’s own wording, symptoms “may seem to go away and then return one or more times.” Incubation averages about a week (CDC gives a range from 2 days to 2 weeks or more), so the meal responsible may have been eaten up to two weeks before symptoms began.
The danger here is cumulative rather than acute. It is not one catastrophic day; it is attrition — fluid loss, electrolyte loss and weight loss stacking up over weeks. FDA notes that people with weakened immune systems, the elderly and children may experience more severe illness or complications from severe dehydration.
That relapsing pattern has one more consequence worth flagging early, because it recurs later in this article: anything taken during a natural remission will appear to have worked. This is the single biggest reason personal anecdotes about treating this illness are unreliable.
9. Why a Normal Stool Test Does Not Rule It Out
People with this infection can be told their stool tests came back clear. Here is why that happens.
A routine stool workup does not look for it. Standard bacterial stool culture does not detect Cyclospora, and CDC states that testing for it “is not routinely conducted in most U.S. laboratories” — it is not typically part of a routine ova-and-parasite examination. Microscopy needs particular methods: modified acid-fast staining, on which the oocysts are “variably acid fast,” or ultraviolet fluorescence microscopy, under which they autofluoresce blue or green. In practice, CDC’s guidance is for clinicians to request Cyclospora testing specifically when it is indicated.
Shedding is intermittent. The parasite is not released steadily, so a single negative stool sample does not exclude infection. CDC notes that patients “might need to submit several specimens collected on different days,” which is why one negative result does not settle the question in someone who is still ill.
Molecular testing is the newer approach. Multiplex gastrointestinal PCR panels look for the parasite’s DNA rather than trying to see it under a microscope, and some include Cyclospora — the 22-target panel evaluated in a 2015 multicentre study does — but CDC notes that “not all gastrointestinal polymerase chain reaction (PCR) panels include a target for Cyclospora.”
The details the guidance ties to the diagnosis are the organism, the timeframe and the exposure. A CDC surveillance report advises clinicians to consider Cyclospora in persistent or remitting-relapsing diarrhoea, especially with symptom onset in spring or summer, and FDA’s outbreak notice singled out people who ate shredded iceberg lettuce in the two weeks before they got sick.
10. Treatment: What Actually Works
The good news in this story is that cyclosporiasis has a specific, inexpensive, well-established treatment.
Trimethoprim–sulfamethoxazole (TMP-SMX) — also called co-trimoxazole — is, in CDC’s words, “the treatment of choice for cyclosporiasis”; CDC’s adult regimen is one double-strength tablet (160 mg TMP plus 800 mg SMX) twice a day for 7–10 days. The evidence is unusually clean for a parasitic illness. A randomised, double-blind, placebo-controlled trial among expatriates attending two clinics in Kathmandu, published in The Lancet in 1995, found that after seven days of treatment Cyclospora was still detectable in 1 of 16 treated patients (6%) who submitted stool specimens, compared with 15 of 17 on placebo (88%); eradication of the organism correlated with clinical improvement.
The real clinical difficulty is sulfa allergy, because the alternatives are weaker. Ciprofloxacin is the studied fallback: a randomised controlled trial in HIV-infected patients in Haiti found it “not as effective” as TMP-SMX but “acceptable for patients who cannot tolerate” it, while CDC adds that substantial anecdotal experience among people with healthy immune systems suggests ciprofloxacin is ineffective. Nitazoxanide has also been used. CDC states that the effectiveness of either alternative is uncertain because of limited evidence and a lack of robust clinical trials, and that observation with symptomatic treatment is another approach for people who cannot take TMP-SMX. Decisions in that situation belong with a clinician, sometimes with an infectious-disease specialist.
Alongside the antibiotic, rehydration matters more here than in a 24-hour illness, simply because of how long the fluid and electrolyte losses go on. People with weakened immune systems may need longer courses of therapy, according to CDC; in the Haiti trial, HIV-infected patients who responded went on to 10 weeks of secondary prophylaxis, and all of those on TMP-SMX remained disease-free.
All of this is prescription medicine; it is described here as what the trials and CDC’s clinical guidance report, not as self-treatment.
11. The Ivermectin Question
This question comes up often, and it deserves a straight, respectful answer rather than a dismissal. Ivermectin is a genuinely remarkable antiparasitic drug — its discovery earned a share of the 2015 Nobel Prize in Physiology or Medicine, and it has transformed the treatment of several devastating diseases. People asking about it are not being unreasonable.
But it is not a treatment for Cyclospora, and there is no evidence that it works.
First, the literature. PubMed searches run on July 26, 2026, and re-run with identical results on October 12, 2026, show the following. A search for ivermectin AND Cyclospora returns two records, and neither is a treatment study — one is a case report about Strongyloides stercoralis, the other a French overview of diagnosing intestinal parasitosis; both simply happen to mention the two terms. A search for ivermectin AND cyclosporiasis returns a single record: a 1996 New England Journal of Medicine review of antiparasitic drugs as a class, which does not report ivermectin treating this parasite. A search for avermectin AND coccidia returns nothing at all. There are no clinical trials. There are no case series. There are no animal studies. The absence is not an oversight in the literature — the absence is the finding.
Second, the mechanism, which explains the absence. Ivermectin works by binding glutamate-gated chloride channels — ion channels found on the nerve and muscle cells of nematodes and arthropods. The drug opens them slowly and essentially irreversibly, producing a long-lasting change in the cell’s membrane potential that blocks further nerve and muscle function and paralyses the worm or mite. These channels are found only in protostome invertebrates, so humans do not have them; reviews attribute ivermectin’s low toxicity in mammals to that difference in receptor targets and to the P-glycoprotein pump, which limits the drug’s entry into the human nervous system.
It is also why there is no known target for it here. Cyclospora is a single-celled protozoan, not an invertebrate animal: it has no nervous system, no muscle, and no glutamate-gated chloride channel. There is no lock for this particular key. The infections ivermectin is used for — Strongyloides, onchocerciasis (river blindness), lymphatic filariasis, and the mites behind scabies and Demodex — are caused by worms or mites, which carry the channel.
Third, the nuance, because overstating a negative is its own kind of error. There is experimental interest in ivermectin against Plasmodium, which is also an apicomplexan, and the results are mixed. In primary human liver cells, ivermectin inhibited P. falciparum liver stages at micromolar concentrations (2024). In rhesus macaques, high oral doses given for seven days produced no inhibition or delay of P. cynomolgi infection (2020). Against asexual blood stages in culture, researchers concluded it has no clinically relevant activity (2023), and a small placebo-controlled pilot trial in Gabonese adults found that parasite levels fell at a similar rate with ivermectin and with placebo (2023). So a blanket claim that ivermectin can never affect any apicomplexan would be too strong. But none of this involves Cyclospora: there are no human cyclosporiasis data at all, and the conclusion for this infection is unchanged.
Fourth, why this matters — and here the relapsing pattern returns. Cyclosporiasis naturally remits and relapses on its own. Anyone who takes an ineffective remedy during a spontaneous remission will sincerely conclude that it worked, and will tell other people so, in complete good faith. This is precisely the trap that placebo-controlled trials exist to escape, and it is why the 1995 Lancet study — where the placebo group is right there in the numbers, still carrying the parasite at 88% — carries so much more weight than any accumulation of testimony.
The cost of an ineffective remedy is not abstract: untreated, the illness can run from a few days to a month or longer, with the dehydration and weight loss that brings, while in the 1995 trial a seven-day course of an inexpensive, decades-old antibiotic cleared the parasite in 15 of 16 treated patients. CDC names TMP-SMX as the treatment of choice; for people who cannot take sulfa drugs, the alternatives described above are less well supported.
The full mechanistic argument and the citations are set out at greater length in Cyclospora Treatment: What Works, and Why Ivermectin Does Not.
12. The “False Positive” That Was Not an All-Clear
On July 18 FDA reported a positive result on a sample of the supplier’s lettuce collected at the border. On July 19, 2026, the FDA announced that its laboratory experts had re-reviewed the result and concluded that the finding “does not represent true amplification” and was a false positive. As of July 19, FDA reported no confirmed positive product samples.
Headlines about a retracted test naturally read as though the case had collapsed. It has not, and the FDA was unusually direct about this: the false positive “DOES NOT change the basis for FDA’s ongoing outbreak investigation or the overwhelming epidemiological data supporting the current voluntary recall.”
Two things are worth understanding here. First, with this organism a negative product test is weak evidence. Recovering microscopic oocysts from leafy produce is difficult: unlike most bacteria, parasites cannot be multiplied in the laboratory before testing, and in a 2014 study oocysts seeded onto basil at 100 per 25 g were detected in only 18.5–92.6% of wash samples, depending on the wash solution. FDA itself cited “the complexity in detection of Cyclospora” when it withdrew the July 18 result. Absence of a positive sample is not evidence of a safe food.
Second, the case rests on epidemiology and traceback, which is standard in outbreak investigation. FDA’s traceback converged on a single supplier of the lettuce used at the restaurant locations where sick people ate. Michigan health officials analysed food exposures for 190 cases who reported eating at the restaurant chain, and 90% of those interviewed reported eating iceberg lettuce. When most of the people who got sick ate the same ingredient, traced to the same supplier, investigators act on that pattern rather than waiting for a positive product sample; FDA described the epidemiological data supporting the recall as “overwhelming.” Later onsite sampling found the parasite in the growing and processing environment (see the “Since then” note in section 1).
13. Key Points From the CDC and FDA Guidance
- The recalled product. The recall covered store-brand iceberg salad (12/24 oz) and shredded lettuce (8/16 oz) with Best-if-Used-By dates from July 18 through August 3, 2026, plus foodservice lettuce. The recall notice told consumers to discard the product rather than eat it, with refunds at the place of purchase. In its later updates FDA reported that the best-by dates had passed and that it was confident all recalled lettuce linked to the outbreak was off the market.
- Surfaces and containers. FDA’s outbreak guidance is to carefully clean and sanitize any surfaces or containers the recalled lettuce touched, because of the risk of cross-contamination.
- Washing. FDA describes rinsing under clean running water as an appropriate first step that may not reliably eliminate the parasite, states that Cyclospora is resistant to standard chlorine-based sanitizers, and advises against using soap or bleach on produce. The research summarised in section 6 is consistent with that.
- Cooking. FDA describes cooking produce to at least 158 °F (70 °C) as the safest option for produce that can be cooked, and CDC’s outbreak notice gives the same temperature. FDA also lists discarding the outer two to three layers of leafy greens among the steps it describes for the Cyclospora season.
- The symptom signature. The distinguishing feature is duration, not severity: watery diarrhoea that lasts, and that may seem to resolve and then return. FDA’s guidance on contacting a healthcare provider highlights diarrhoea or other severe symptoms lasting more than three days, and its outbreak notice singled out people who ate shredded iceberg lettuce in the two weeks before getting sick.
- Testing. Cyclospora is not part of most routine U.S. stool examinations; CDC’s guidance is for clinicians to request it specifically. There is an effective treatment, TMP-SMX, but only once the diagnosis is made.
- Dehydration and higher-risk groups. FDA notes that untreated illness can lead to dehydration and severe complications requiring higher levels of care, that people with weakened immune systems, the elderly and children may have more severe illness and may need longer treatment, and that prompt care is important, especially for people who are immunocompromised. Signs commonly associated with dehydration include dizziness on standing, passing very little urine and being unable to keep fluids down.
14. Deep-Dive Series
Nine companion articles go considerably deeper than this news piece:
The 2026 Iceberg Lettuce Outbreak
The full dossier: timeline, recall specifics, the nine-versus-twenty-seven state confusion, and why the count keeps rising.
Read the deep dive →Why Washing Does Not Work
The oocyst wall, the chlorine evidence, and the microscopic geometry of a lettuce leaf.
Read the deep dive →Life Cycle and Sporulation
Why a parasite that needs two weeks in a warm environment is not contagious — and is nearly impossible to trace.
Read the deep dive →Symptoms and the Relapsing Course
The full symptom picture, the remitting-relapsing pattern, and the warning signs clinical guidance describes.
Read the deep dive →Diagnosis and Testing
Why the standard stool test misses it, which tests detect it, and how PCR panels changed the picture.
Read the deep dive →Treatment & the Ivermectin Question
TMP-SMX and the trial behind it, the sulfa-allergy problem, and the full evidence on ivermectin.
Read the deep dive →Gut Recovery and Malabsorption
What weeks of small-intestine infection cost nutritionally, and how people recover afterward.
Read the deep dive →Produce Safety at Home
What the agencies’ produce-handling guidance says during an active outbreak, and what the research shows about washing.
Read the deep dive →Cyclospora vs Other Gut Infections
How it differs from Giardia, Cryptosporidium, norovirus and ordinary food poisoning.
Read the deep dive →External Authoritative Resources
The outbreak figures in this article come from the following official pages, which are the authoritative and continuously updated record; where numbers differ between them, the difference is stated above. The research findings come from the papers listed under Key Research Papers.
- FDA — Investigation of Multistate Outbreak of Cyclospora Illnesses: Iceberg Lettuce (July 2026) (titled “9-State Outbreak” at the time of the July 24 update). Primary source for case counts, hospitalizations, state lists, distribution dates, the July 24, 2026 update and the later updates through October 2, 2026.
- FDA — the supplier’s recall notice: iceberg lettuce from central Mexico (July 17, 2026). The recall notice, including the complete foodservice product list and the 27-state foodservice distribution list.
- CDC — Cyclospora Outbreak Advisory, July 2026.
- CDC — Investigation Update: Cyclospora Outbreak, July 2026. Source for the traceback findings and the Michigan interview data (190 cases, 90% iceberg lettuce).
- FDA — Cyclospora pathogen page. Source for the symptom list and the consumer guidance on rinsing, chlorine resistance and cooking quoted above.
- CDC — Cyclosporiasis home. General background, with linked clinical pages on diagnosis, testing and treatment — the source of the CDC statements on testing, TMP-SMX and the alternatives quoted above.
- The restaurant chain’s public statement.
Key Research Papers
The scientific claims in this article rest on the following peer-reviewed sources. Each PMID was verified against PubMed on July 26, 2026, and re-checked on October 12, 2026.
- Hoge CW, Shlim DR, Ghimire M, et al. Placebo-controlled trial of co-trimoxazole for Cyclospora infections among travellers and foreign residents in Nepal. Lancet 1995;345(8951):691-693. — PubMed PMID: 7885125
- Verdier RI, Fitzgerald DW, Johnson WD, Pape JW. Trimethoprim-sulfamethoxazole compared with ciprofloxacin for treatment and prophylaxis of Isospora belli and Cyclospora cayetanensis infection in HIV-infected patients. Annals of Internal Medicine 2000;132(11):885-888. — PubMed PMID: 10836915
- Giangaspero A, Gasser RB. Human cyclosporiasis. The Lancet Infectious Diseases 2019;19(7):e226-e236. — PubMed PMID: 30885589
- Ortega YR, Sanchez R. Update on Cyclospora cayetanensis, a food-borne and waterborne parasite. Clinical Microbiology Reviews 2010;23(1):218-234. — PubMed PMID: 20065331
- Dubey JP, Khan A, Rosenthal BM. Life cycle and transmission of Cyclospora cayetanensis: knowns and unknowns. Microorganisms 2022;10(1):118. — PubMed PMID: 35056567
- Almeria S, Cinar HN, Dubey JP. Cyclospora cayetanensis and cyclosporiasis: an update. Microorganisms 2019;7(9):317. — PubMed PMID: 31487898
- Sathyanarayanan L, Ortega YR. Effects of temperature and different food matrices on Cyclospora cayetanensis oocyst sporulation. Journal of Parasitology 2006;92(2):218-222. — PubMed PMID: 16729675
- Ortega YR, Mann A, Torres MP, Cama V. Efficacy of gaseous chlorine dioxide as a sanitizer against Cryptosporidium parvum, Cyclospora cayetanensis, and Encephalitozoon intestinalis on produce. Journal of Food Protection 2008;71(12):2410-2414. — PubMed PMID: 19244892
- Hadjilouka A, Tsaltas D. Cyclospora cayetanensis — major outbreaks from ready to eat fresh fruits and vegetables. Foods 2020;9(11):1703. — PubMed PMID: 33233660
- Casillas SM, Hall RL, Herwaldt BL. Cyclosporiasis surveillance — United States, 2011-2015. MMWR Surveillance Summaries 2019;68(3):1-16. — PubMed PMID: 31002104
- Buss SN, Leber A, Chapin K, et al. Multicenter evaluation of the BioFire FilmArray gastrointestinal panel for etiologic diagnosis of infectious gastroenteritis. Journal of Clinical Microbiology 2015;53(3):915-925. — PubMed PMID: 25588652
- McHardy IH, Wu M, Shimizu-Cohen R, et al. Detection of intestinal protozoa in the clinical laboratory. Journal of Clinical Microbiology 2014;52(3):712-720. — PubMed PMID: 24197877
- Wolstenholme AJ, Rogers AT. Glutamate-gated chloride channels and the mode of action of the avermectin/milbemycin anthelmintics. Parasitology 2005;131 Suppl:S85-S95. — PubMed PMID: 16569295
- McCavera S, Rogers AT, Yates DM, Woods DJ, Wolstenholme AJ. An ivermectin-sensitive glutamate-gated chloride channel from the parasitic nematode Haemonchus contortus. Molecular Pharmacology 2009;75(6):1347-1355. — PubMed PMID: 19336526
- Liu LX, Weller PF. Antiparasitic drugs. New England Journal of Medicine 1996;334(18):1178-1184. — PubMed PMID: 8602186
- Johnson-Arbor K. Ivermectin: a mini-review. Clinical Toxicology 2022;60(5):571-575. — PubMed PMID: 35225114
- Ahart L, Jacobson D, Rice M, et al. Retrospective evaluation of an integrated molecular-epidemiological approach to cyclosporiasis outbreak investigations — United States, 2021. Epidemiology and Infection 2023;151:e131. — PubMed PMID: 37466070
- Sifuentes-Osornio J, Porras-Cortes G, Bendall RP, et al. Cyclospora cayetanensis infection in patients with and without AIDS: biliary disease as another clinical manifestation. Clinical Infectious Diseases 1995;21(5):1092-1097. — PubMed PMID: 8589126
- Wolstenholme AJ. Glutamate-gated chloride channels. Journal of Biological Chemistry 2012;287(48):40232-40238. — PubMed PMID: 23038250
- Annamalai Subramani P, Tipthara P, Kolli SK, et al. Efficacy of ivermectin and its metabolites against Plasmodium falciparum liver stages in primary human hepatocytes. Antimicrobial Agents and Chemotherapy 2024;68(8):e0127223. — PubMed PMID: 38904389
- Vanachayangkul P, Im-Erbsin R, Tungtaeng A, et al. Safety, pharmacokinetics, and activity of high-dose ivermectin and chloroquine against the liver stage of Plasmodium cynomolgi infection in rhesus macaques. Antimicrobial Agents and Chemotherapy 2020;64(9):e00741-20. — PubMed PMID: 32660993
- Yipsirimetee A, Tipthara P, Hanboonkunupakarn B, et al. Activity of ivermectin and its metabolites against asexual blood stage Plasmodium falciparum and its interactions with antimalarial drugs. Antimicrobial Agents and Chemotherapy 2023;67(7):e0173022. — PubMed PMID: 37338381
- Ekoka Mbassi D, Mombo-Ngoma G, Held J, et al. Efficacy and safety of ivermectin for the treatment of Plasmodium falciparum infections in asymptomatic male and female Gabonese adults — a pilot randomized, double-blind, placebo-controlled single-centre phase Ib/IIa clinical trial. EBioMedicine 2023;97:104814. — PubMed PMID: 37839134
- Temesgen TT, Robertson LJ, Stigum VM, Tysnes KR. Removal of parasite transmission stages from berries using washing procedures suitable for consumers. Foods 2021;10(2):481. — PubMed PMID: 33672362
- McCaughan KJ, Scott Z, Rock C, Kniel KE. Evaluation of aqueous chlorine and peracetic acid sanitizers to inactivate protozoa and bacteria of concern in agricultural water. Applied and Environmental Microbiology 2025;91(1):e0165324. — PubMed PMID: 39641604
- Erickson MC, Ortega YR. Inactivation of protozoan parasites in food, water, and environmental systems. Journal of Food Protection 2006;69(11):2786-2808. — PubMed PMID: 17133829
- Rabold JG, Hoge CW, Shlim DR, et al. Cyclospora outbreak associated with chlorinated drinking water [letter]. Lancet 1994;344(8933):1360-1361. — PubMed PMID: 7968039
- Chandra V, Torres M, Ortega YR. Efficacy of wash solutions in recovering Cyclospora cayetanensis, Cryptosporidium parvum, and Toxoplasma gondii from basil. Journal of Food Protection 2014;77(8):1348-1354. — PubMed PMID: 25198596
PubMed Topic Searches
Connections
- Cyclospora: From Contaminated Field to Relapsing Illness — interactive animation
- Cyclospora — main article
- The 2026 Iceberg Lettuce Outbreak
- Treatment & the Ivermectin Question
- Why Washing Does Not Work
- Diagnosis and Testing
- Parasites — category index
- Cryptosporidium
- Giardia
- Blastocystis
- Chronic Diarrhea
- SIBO
- Probiotics
- Leafy Greens