Methylmalonic Acid: The Test That Catches B12 Deficiency Earlier
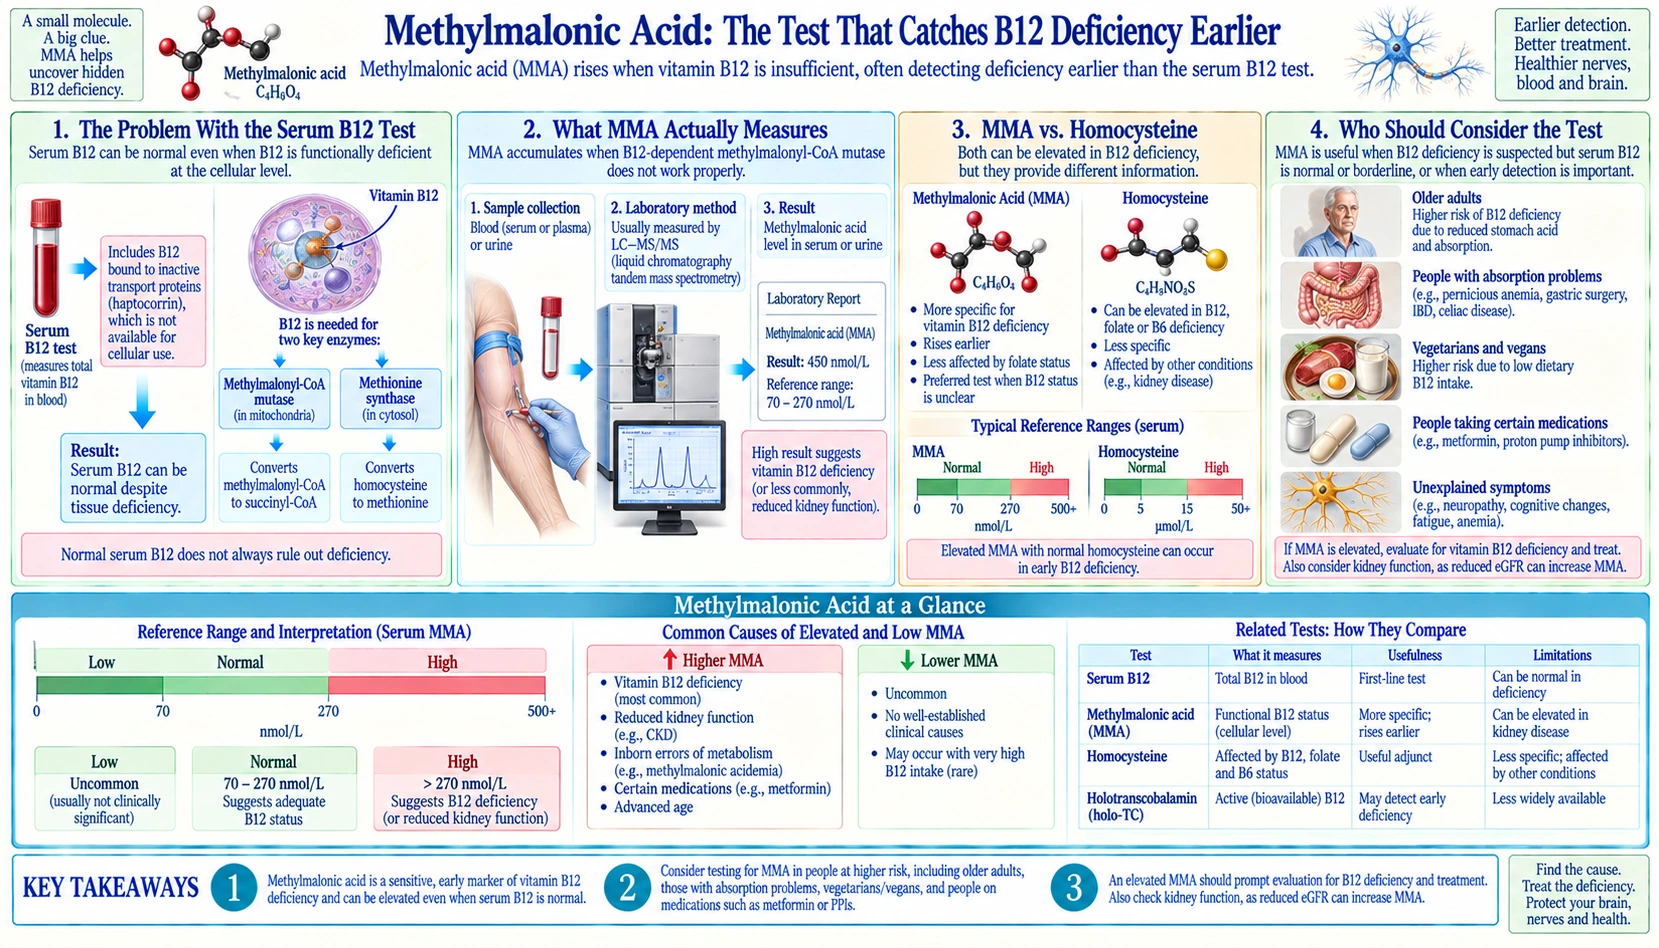
The methylmalonic acid (MMA) test is a blood (or urine) test that answers a question the standard vitamin B12 test cannot: are your cells actually getting enough B12 to do their job? A serum B12 level tells you how much of the vitamin is floating in your bloodstream. MMA tells you whether the B12-dependent machinery inside your cells is running or stalling — and it starts rising before the standard test drops below the "normal" line. That makes it the closest thing medicine has to an early-warning system for B12 deficiency.
This matters because B12 deficiency is common, sneaky, and — if it reaches the nervous system — only partially reversible. Millions of people sit in the "gray zone" of the standard test: tired, tingling, foggy, told their B12 is "fine." For many of them, an MMA test is the second look that settles the question for well under $100. This article explains what MMA measures, who should consider it, how to read the result (including the one big false-positive trap: kidney function), and what honest treatment and retesting look like.
Table of Contents
- The Problem With the Serum B12 Test
- What MMA Actually Measures
- MMA vs. Homocysteine
- Telling B12 Deficiency from Folate Deficiency
- Who the Test Is Most Useful For
- Reading Your Results
- The Kidney Caveat, and Other Causes of a High Result
- The Neurological Stakes
- Getting Tested: Ordering, Cost, Preparation
- Treating and Retesting
- Related Tests Ordered Alongside MMA
- Key Research Papers
- Connections
- Featured Videos
The Problem With the Serum B12 Test
The standard serum B12 test measures the total amount of vitamin B12 in your blood. The problem is that most of that total is not available to your cells. Roughly 70–80% of circulating B12 rides on a carrier protein called haptocorrin, which cells cannot take up; only the remaining fraction, bound to transcobalamin (so-called "active B12" or holotranscobalamin), can actually be delivered into tissues. Two people with the same total B12 number can have very different amounts of usable vitamin, and shifts in the carrier proteins — from pregnancy, oral contraceptives, liver disease, or ordinary genetic variation — can move the total up or down without changing what cells receive.
Then there is the gray zone. Most labs flag serum B12 as "low" only below roughly 200 pg/mL (≈148 pmol/L). But a large body of research shows that people with values between roughly 200 and 400 pg/mL — officially "normal" — are frequently deficient at the tissue level, with elevated metabolic markers and real symptoms. In the landmark case series by Lindenbaum and colleagues in the New England Journal of Medicine, a substantial share of patients with outright neurologic disease from B12 deficiency had serum values that were low-normal rather than frankly low — and about 28% had no anemia and no enlarged red cells at all, the two findings doctors are traditionally taught to wait for.
The practical rule that follows: a "normal" B12 result in a person with suggestive symptoms deserves a second look. Numbness or tingling, balance problems, burning feet, unexplained fatigue, brain fog, a sore or smooth tongue, or unexplained mood and memory changes — with a serum B12 anywhere under about 400 pg/mL — is exactly the situation the MMA test was made for. Functional markers like MMA catch the deficiency the screening test misses.
What MMA Actually Measures
Here is the biochemistry in one paragraph. When you metabolize certain fats (odd-chain fatty acids and cholesterol fragments) and certain amino acids (valine, isoleucine, methionine, threonine), the breakdown products funnel into a molecule called methylmalonyl-CoA. To finish the job, an enzyme called methylmalonyl-CoA mutase must convert methylmalonyl-CoA into succinyl-CoA, which feeds your cells' energy cycle. That enzyme has an absolute requirement for vitamin B12 (in its adenosylcobalamin form) as a cofactor. No B12, no conversion — methylmalonyl-CoA piles up at the blocked step, the cell hydrolyzes the excess into methylmalonic acid, and the MMA spills out into the blood and urine, where a lab can measure it.
That is why MMA is called a functional marker: it does not measure how much B12 you have, it measures whether a specific B12-dependent reaction is failing inside your cells. In the classic diagnostic studies by Allen, Stabler, Savage, and Lindenbaum, MMA was elevated in more than 98% of patients with clinically confirmed B12 deficiency — including many whose serum B12 sat in the normal range. Because the metabolite backs up as soon as tissue supplies run short, MMA typically rises weeks to months before the serum level falls below the lab cutoff, which is the entire case for using it as an early-detection test. (Very high MMA in an infant is a different matter entirely — a rare inherited enzyme defect called methylmalonic acidemia, caught by newborn screening — and is not what this article is about.)
MMA vs. Homocysteine
B12 works as a cofactor in exactly two human enzymes, and each one gives us a lab marker. The first is methylmalonyl-CoA mutase, described above — its failure raises MMA. The second is methionine synthase, which recycles homocysteine back into methionine and needs both B12 (as methylcobalamin) and folate to run. Its failure raises homocysteine. So in true B12 deficiency, both markers typically rise together.
The reason to know both is that they fail differently, and the pattern localizes the problem:
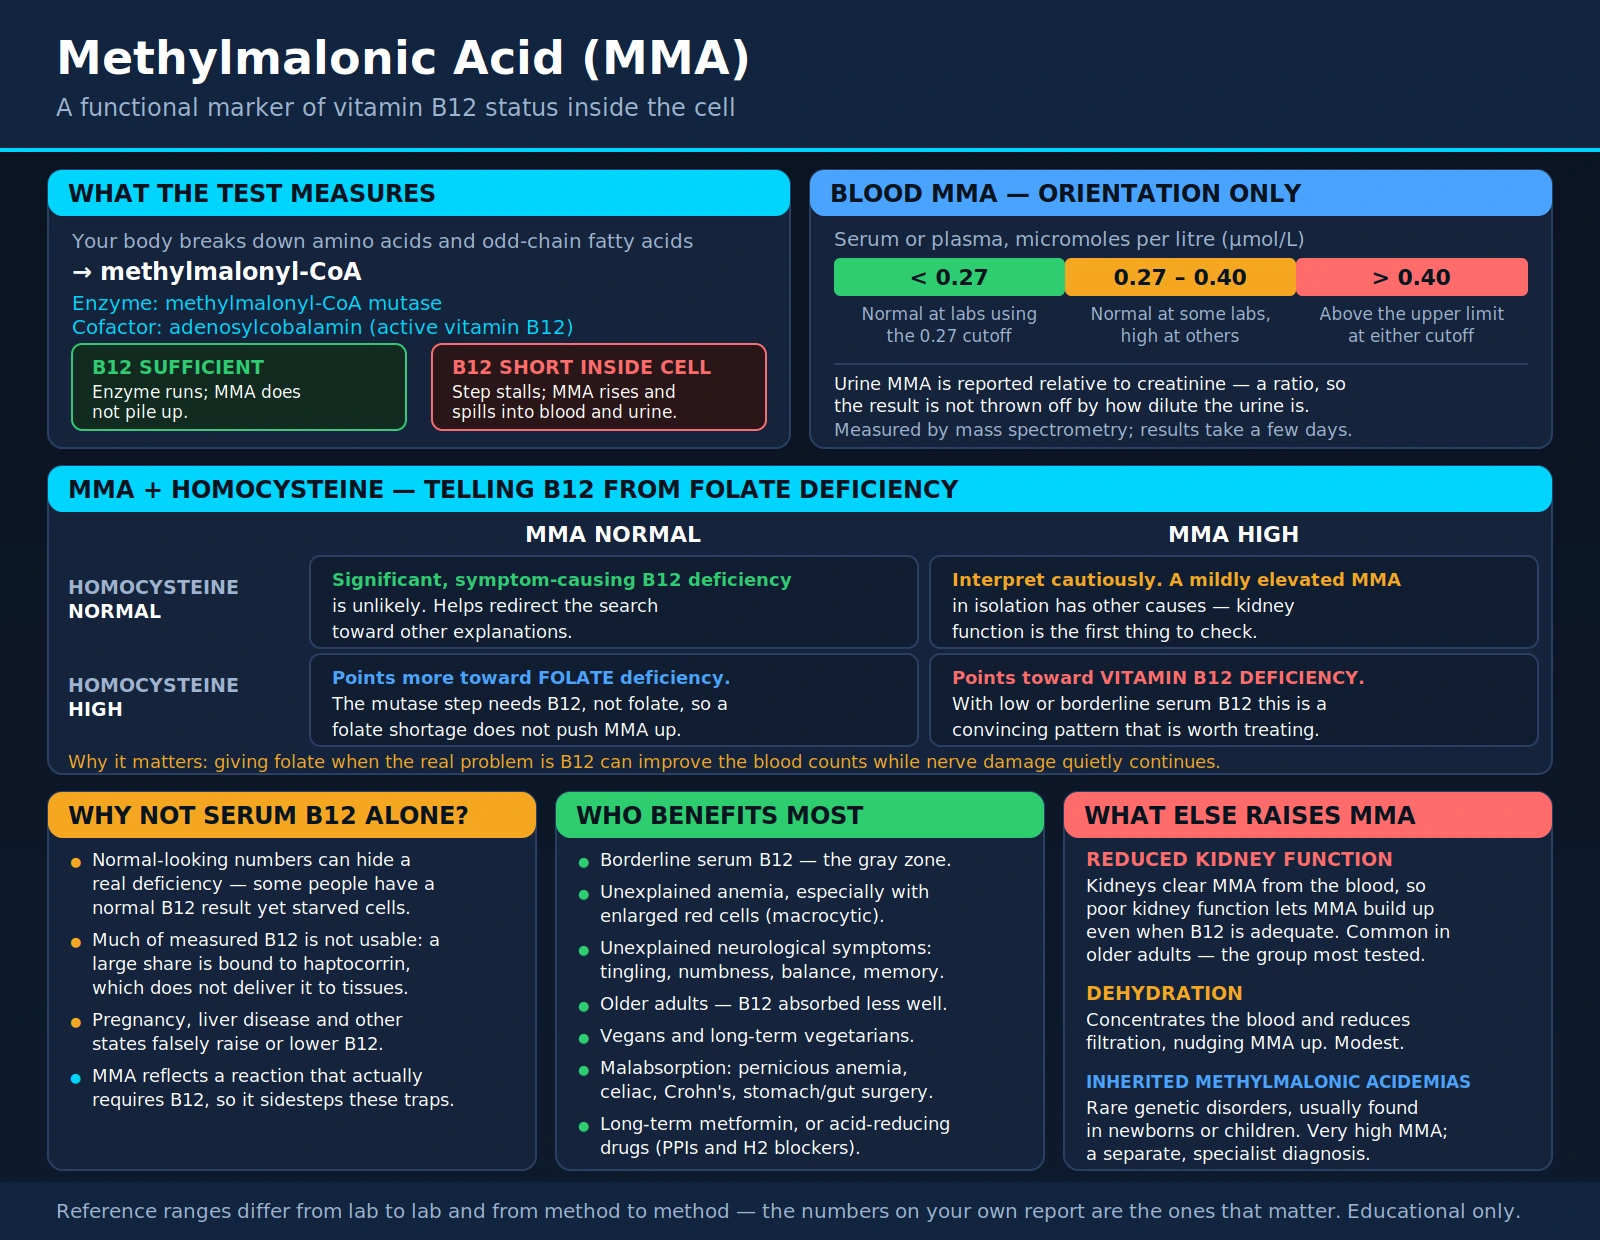
- MMA high + homocysteine high — points to B12 deficiency (folate cannot rescue the mutase reaction).
- MMA normal + homocysteine high — points to folate deficiency (or vitamin B6 shortfall, hypothyroidism, kidney impairment, or certain genetic variants) rather than B12.
- Both normal — makes clinically significant deficiency of either vitamin unlikely; in the large case series, fewer than 1 in 200 confirmed B12-deficiency episodes had two normal metabolites.
Of the two, MMA is the more specific B12 marker: homocysteine rises with folate deficiency, B6 deficiency, kidney disease, hypothyroidism, smoking, and age, while an elevated MMA has a much shorter list of alternative explanations (kidney function being the big one — see below). Many clinicians order the pair when the picture is murky; if only one test is being added to a workup, MMA is usually the one. The site's homocysteine article covers that marker's own story, including its cardiovascular associations.
Telling B12 Deficiency from Folate Deficiency
This is one of the most genuinely useful things MMA can do, and it is worth understanding clearly. Vitamin B12 and folate (vitamin B9) are chemical partners: they work together in the body, and a shortage of either one can cause a very similar type of anemia (large, immature red blood cells) and overlapping symptoms. That makes them easy to confuse.
Here is the distinction that MMA helps draw:
- MMA is elevated in B12 deficiency, but normal in folate deficiency. The mutase reaction needs B12, not folate — so folate shortage does not cause MMA to rise.
- Homocysteine rises in both. Both B12 and folate are needed to keep homocysteine low, so a high homocysteine cannot, by itself, tell the two apart.
Putting those together gives a helpful pattern: high MMA + high homocysteine points toward B12 deficiency, whereas normal MMA + high homocysteine points more toward folate deficiency. Getting this right matters, because treating the wrong one can cause harm — giving folate to someone whose real problem is B12 can improve the blood counts while the nerve damage from untreated B12 deficiency quietly continues.
Who the Test Is Most Useful For
An MMA test earns its cost wherever B12 deficiency is more likely than average, or where the standard test has already returned an ambiguous answer. The groups below account for most real-world cases:
- Vegans and long-term vegetarians. B12 occurs naturally only in animal foods; plants supply none. Without fortified foods or supplements, body stores (which can last years) slowly drain, and MMA is often the first number to move.
- People taking metformin. This is the best-documented drug-induced B12 depletion. In a 4.3-year randomized placebo-controlled trial, metformin lowered B12 levels by about 19% versus placebo, and in the Diabetes Prevention Program Outcomes Study, years of metformin use meaningfully increased the odds of B12 deficiency — the American Diabetes Association now advises periodic B12 assessment for long-term users, especially those with anemia or neuropathy. Metformin-related nerve symptoms are easy to misfile as "diabetic neuropathy," which is precisely why testing matters.
- People on long-term acid suppression (PPIs or H2 blockers). Stomach acid is required to split B12 off food proteins. In a large case-control study in JAMA, two or more years of proton-pump-inhibitor use was associated with roughly 65% higher odds of B12 deficiency (H2 blockers, about 25%).
- Older adults. Atrophic gastritis and low stomach acid (achlorhydria) become common with age, impairing the release of food-bound B12 even when intake is fine. This is why deficiency rates climb steadily after age 60 — and why crystalline B12 in supplements, which needs no acid, still absorbs.
- Anyone after bariatric or stomach surgery. Gastric bypass and similar operations remove or bypass both the acid and the intrinsic-factor machinery that B12 absorption depends on; lifelong supplementation and periodic monitoring are standard.
- Pernicious anemia workups. When autoimmune destruction of the stomach's parietal cells is suspected, MMA plus homocysteine confirm that a borderline B12 is genuinely functional deficiency, alongside intrinsic-factor antibody testing.
- Unexplained neuropathy. Numbness, tingling, or burning in the feet and hands without an obvious cause is a standard indication — B12 deficiency is one of the few fully treatable causes of peripheral neuropathy, and one no workup should miss.
- Unexplained fatigue with a normal CBC. Waiting for anemia to appear is a mistake; the Lindenbaum series showed the nervous system can take the hit first. A normal blood count rules out anemia, not B12 deficiency.
- Nitrous oxide exposure. Recreational use ("whippits") — and occasionally repeated anesthesia — chemically inactivates B12 and can produce severe, rapid-onset neurologic deficiency, often with a normal serum B12. MMA is the test that exposes it.
Reading Your Results
Serum MMA. Reference intervals vary by laboratory and method, but most labs flag serum MMA above roughly 0.27 to 0.40 µmol/L (270–400 nmol/L) — treat the exact cutoff on your report as the one that counts. As a rough guide used in the research literature: values just above the cutoff are borderline and worth repeating or corroborating; values above about 0.75 µmol/L are strongly suggestive of true B12 deficiency in a person with normal kidney function. Mild elevations become more common with age, so a single borderline number in an older adult is a prompt for confirmation, not a verdict.
Urine MMA. Some laboratories (including several direct-to-consumer services) measure MMA in urine, normalized to creatinine. Urine MMA tracks serum MMA well, requires no blood draw, and is less distorted by mild kidney impairment, which makes it a reasonable screening alternative — though serum remains the better-studied standard, and any surprising urine result deserves serum confirmation.
What lowers MMA. B12 itself. If you started B12 supplements before testing, even a genuinely deficient person's MMA can already be normalizing — the test reads clean because treatment is working. For a clean diagnostic answer, test before supplementing, or interpret a normal result on supplements as "treatment adequate" rather than "never deficient."
What a high MMA does not tell you. It flags that the B12 pathway is failing, not why. A confirmed elevation still needs a cause: dietary, autoimmune (pernicious anemia), drug-induced, surgical, or malabsorptive. And one condition can raise MMA without any deficiency at all — which brings us to the kidney.
The Kidney Caveat, and Other Causes of a High Result
MMA is cleared from the blood by the kidneys. When kidney function declines, MMA accumulates because it is being excreted more slowly, not because cells lack B12. Chronic kidney disease is by far the single largest source of false-positive MMA results, and it matters in practice because reduced kidney function and B12 deficiency concentrate in the same population: older adults, people with diabetes on metformin, people with hypertension.
- Always read MMA next to a kidney number (creatinine/eGFR, usually already on your chemistry panel). A modestly elevated MMA with an eGFR of 45 is ambiguous; the same value with normal kidneys is meaningful.
- Homocysteine does not break the tie — it also rises with kidney impairment. In significant CKD, both markers lose specificity together.
- Ways through the ambiguity: an "active B12" (holotranscobalamin) level, which the kidneys do not inflate; urine MMA; or the most pragmatic move of all — a therapeutic trial of B12 with retesting, since MMA that falls substantially on treatment was deficiency, and MMA that stays put was the kidneys.
- Smaller confounders exist too: small-intestinal bacterial overgrowth (SIBO) can nudge MMA upward because gut bacteria produce propionate, the precursor feeding the pathway; volume depletion and thyroid disease have minor effects. None of these approach kidney function in importance.
Dehydration
Being significantly dehydrated can concentrate the blood and reduce kidney filtration, nudging MMA upward. This is usually a modest effect, but it is one more reason a single borderline value is confirmed rather than acted on blindly.
Rare inherited methylmalonic acidemias
There is a separate, much rarer world in which MMA is central: the inherited disorders called methylmalonic acidemias. These are genetic conditions, typically identified in newborns or young children, in which the mutase enzyme (or the machinery that supplies its B12 cofactor) is faulty from birth. They cause very high MMA and are a distinct, specialized diagnosis handled by metabolic experts — not the everyday adult B12-deficiency question this page focuses on. It is worth knowing they exist so the term "methylmalonic acidemia" is not confused with the ordinary MMA test used to check B12 status in adults.
The Neurological Stakes
The reason to catch functional B12 deficiency early — the reason this test exists — is what late deficiency does to the nervous system. B12 is required to maintain myelin, the insulation around nerve fibers. Prolonged deficiency produces subacute combined degeneration: demyelination of the spinal cord's dorsal columns (which carry vibration and position sense) and corticospinal tracts (which carry movement commands). It announces itself as tingling and numbness in the feet and hands, a strange loss of balance in the dark, clumsiness, stiff or weak legs — and, in parallel, as memory problems, depression, irritability, or in severe cases frank dementia and psychosis.
Two facts give the condition its urgency. First, it does not wait for anemia: in the Lindenbaum series, about 28% of patients with neuropsychiatric disease from B12 deficiency had neither anemia nor macrocytosis, so a normal CBC offers no reassurance. Second, recovery is only partial once damage is established. Treatment reliably halts progression, and symptoms of weeks-to-months duration often improve substantially — but deficits that have persisted a year or more frequently leave permanent residue. The same injury caught at the "tingling toes and a high MMA" stage is fully preventable. That asymmetry — cheap test, irreversible endpoint — is the entire argument for testing early in anyone at risk.
There is also the folate-masking problem. Folic acid can substitute for B12 in red-blood-cell production but not in myelin maintenance. A person deficient in B12 who takes folic acid (or simply eats a fortified-grain diet, as most Americans do) can have their anemia corrected or prevented while the neurologic damage advances silently — the classic "masked" deficiency. In a fortification era, the old strategy of letting anemia reveal B12 deficiency is broken, which strengthens the case for functional markers like MMA in symptomatic people.
Getting Tested: Ordering, Cost, Preparation
Any clinician can order serum MMA; it is a routine send-out at worst. If your doctor declines or you prefer to self-pay, direct-to-consumer laboratory services in most U.S. states sell serum MMA for roughly $30–$90, and urine MMA kits exist in a similar range. Hospital-lab list prices can run several hundred dollars before insurance adjustment — ask for the cash price. Insurance generally covers the test when tied to a plausible indication (neuropathy, unexplained anemia, a borderline B12 result, long-term metformin use). All prices here are rough U.S. figures that vary by region and lab.
Preparation is minimal: fasting is not usually required, though some laboratories prefer a fasting sample — follow your lab's instructions. The one preparation rule that genuinely changes the answer: if you want a diagnosis, test before starting B12 supplements, because supplementation begins normalizing MMA within days. Pairing the test with a metabolic panel (for kidney function) and, when budget allows, homocysteine or holotranscobalamin gives the most interpretable picture in one draw.
Blood or Urine
MMA can be measured in blood or urine, and both are straightforward for you as the patient.
- Blood test: a technician draws a small sample from a vein in your arm, just like a routine blood test. No special preparation is usually required, though your clinician may ask about timing relative to other tests or medications.
- Urine test: you provide a urine sample, and the lab reports MMA relative to creatinine so the result is not thrown off by how concentrated the urine is.
Behind the scenes, laboratories typically measure MMA using highly precise chemistry methods (such as mass spectrometry) that can detect these small molecules accurately. From your side, though, it is simply a blood draw or a urine cup. Results usually take a few days, because the specialized analysis is often run in batches or sent to a reference laboratory.
Treating and Retesting
If MMA confirms deficiency, the treatment question is oral versus injection — and the evidence here is more reassuring than most patients expect. About 1% of a swallowed B12 dose absorbs by passive diffusion, needing no stomach acid and no intrinsic factor. That means high-dose oral B12 — 1,000 to 2,000 mcg daily — delivers enough even in pernicious anemia and after gastric surgery. In the randomized trial by Kuzminski and colleagues, 2,000 mcg oral daily corrected blood counts and normalized MMA at least as well as a standard injection schedule; a Cochrane review reached the same conclusion, while honestly noting the trials are few and small. So: the evidence favors oral therapy working for most people, with a limited evidence base rather than a mountain of it.
Injections still have a place: significant neurologic deficits (where rapid, guaranteed repletion is worth it — typically several loading injections over the first weeks, then maintenance), severe symptomatic anemia, malabsorption so complete that adherence to daily pills is doubtful, or simply a patient who prefers a monthly shot to a daily tablet. Either route, the cause determines the duration: dietary deficiency can eventually be maintained by diet or modest supplements, while pernicious anemia and post-surgical deficiency need lifelong therapy.
Retesting is how you close the loop. MMA begins falling within about a week of adequate treatment and typically normalizes within a few weeks; homocysteine falls on a similar schedule. A sensible plan is to recheck MMA (with a blood count, if anemia was present) around 2–3 months after starting therapy. Interpreting the recheck is refreshingly binary: MMA that has fallen to normal confirms both the diagnosis and the adequacy of your dose; MMA that has not budged on verified supplementation means the elevation was never about B12 — look again at kidney function, consider SIBO, or (rarely, in the young) an inherited enzyme variant. Expect nerve symptoms to lag the labs: numbness and balance improve over 3–12 months, and the longer symptoms stood before treatment, the slower and less complete the recovery — one more argument for having tested early.
Related Tests Ordered Alongside MMA
MMA is most informative as part of a small cluster of tests that, together, build a clear picture of B12 and folate status:
- Serum vitamin B12 — the first-line screen; MMA is often used to interpret a borderline B12 result.
- Homocysteine — rises in both B12 and folate deficiency; pairing it with MMA helps separate the two.
- Folate (vitamin B9) — checked alongside B12 because their deficiencies look alike and must be told apart.
- Holotranscobalamin ("active B12") — measures the fraction of B12 actually available to cells, another way to sharpen a borderline result.
- Complete blood count (CBC) with MCV — looks for anemia and, in particular, enlarged red blood cells (a high MCV, called macrocytosis) that often accompany B12 or folate deficiency.
- Kidney function tests — important context, since reduced kidney function can raise MMA on its own.
Your clinician chooses among these based on your symptoms and risk factors; you rarely need all of them at once.
Key Research Papers
- Savage DG, Lindenbaum J, Stabler SP, Allen RH. Sensitivity of serum methylmalonic acid and total homocysteine determinations for diagnosing cobalamin and folate deficiencies. The American Journal of Medicine. 1994;96(3):239–246. — doi:10.1016/0002-9343(94)90149-X
- Allen RH, Stabler SP, Savage DG, Lindenbaum J. Diagnosis of cobalamin deficiency I: usefulness of serum methylmalonic acid and total homocysteine concentrations. American Journal of Hematology. 1990;34(2):90–98. — doi:10.1002/ajh.2830340204
- Lindenbaum J, Healton EB, Savage DG, et al. Neuropsychiatric disorders caused by cobalamin deficiency in the absence of anemia or macrocytosis. New England Journal of Medicine. 1988;318(26):1720–1728. — doi:10.1056/NEJM198806303182604
- Stabler SP. Vitamin B12 deficiency. New England Journal of Medicine. 2013;368(2):149–160. — doi:10.1056/NEJMcp1113996
- Carmel R. How I treat cobalamin (vitamin B12) deficiency. Blood. 2008;112(6):2214–2221. — doi:10.1182/blood-2008-03-040253
- Devalia V, Hamilton MS, Molloy AM; British Committee for Standards in Haematology. Guidelines for the diagnosis and treatment of cobalamin and folate disorders. British Journal of Haematology. 2014;166(4):496–513. — doi:10.1111/bjh.12959
- Wolffenbuttel BHR, Wouters HJCM, Heiner-Fokkema MR, van der Klauw MM. The many faces of cobalamin (vitamin B12) deficiency. Mayo Clinic Proceedings: Innovations, Quality & Outcomes. 2019;3(2):200–214. — doi:10.1016/j.mayocpiqo.2019.03.002
- Kuzminski AM, Del Giacco EJ, Allen RH, Stabler SP, Lindenbaum J. Effective treatment of cobalamin deficiency with oral cobalamin. Blood. 1998;92(4):1191–1198. — doi:10.1182/blood.V92.4.1191
- Vidal-Alaball J, Butler CC, Cannings-John R, et al. Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database of Systematic Reviews. 2005;(3):CD004655. — doi:10.1002/14651858.CD004655.pub2
- de Jager J, Kooy A, Lehert P, et al. Long term treatment with metformin in patients with type 2 diabetes and risk of vitamin B-12 deficiency: randomised placebo controlled trial. BMJ. 2010;340:c2181. — doi:10.1136/bmj.c2181
- Aroda VR, Edelstein SL, Goldberg RB, et al. Long-term metformin use and vitamin B12 deficiency in the Diabetes Prevention Program Outcomes Study. The Journal of Clinical Endocrinology & Metabolism. 2016;101(4):1754–1761. — doi:10.1210/jc.2015-3754
- Lam JR, Schneider JL, Zhao W, Corley DA. Proton pump inhibitor and histamine 2 receptor antagonist use and vitamin B12 deficiency. JAMA. 2013;310(22):2435. — doi:10.1001/jama.2013.280490
- Carmel R. Biomarkers of cobalamin (vitamin B-12) status in the epidemiologic setting: a critical overview of context, applications, and performance characteristics of cobalamin, methylmalonic acid, and holotranscobalamin II. The American Journal of Clinical Nutrition. 2011;94(1):348S-358S. — Compares the strengths and limits of the main B12 markers, including MMA. — doi:10.3945/ajcn.111.013441
- Green R. Vitamin B12 deficiency from the perspective of a practicing hematologist. Blood. 2017;129(19):2603-2611. — A practical review of how to diagnose and manage B12 deficiency, including the role of MMA in ambiguous cases. — doi:10.1182/blood-2016-10-569186
- Green R, Allen LH, Bjørke-Monsen AL, et al. Vitamin B12 deficiency. Nature Reviews Disease Primers. 2017;3:17040. — A comprehensive overview of B12 deficiency biology, diagnosis, and treatment. — doi:10.1038/nrdp.2017.40
- Allen RH, Stabler SP, Savage DG, Lindenbaum J. Metabolic abnormalities in cobalamin (vitamin B12) and folate deficiency. The FASEB Journal. 1993;7(14):1344-1353. — Explains the biochemistry linking B12 to methylmalonic acid and homocysteine accumulation. — doi:10.1096/fasebj.7.14.7901104
- Klee GG. Cobalamin and folate evaluation: measurement of methylmalonic acid and homocysteine vs vitamin B12 and folate. Clinical Chemistry. 2000;46(8):1277-1283. — Reviews the laboratory case for using metabolite markers to evaluate B12 and folate status. — doi:10.1093/clinchem/46.8.1277
- Hannibal L, Lysne V, Bjørke-Monsen AL, et al. Biomarkers and algorithms for the diagnosis of vitamin B12 deficiency. Frontiers in Molecular Biosciences. 2016;3:27. — Proposes practical algorithms combining B12, MMA, homocysteine, and holotranscobalamin. — doi:10.3389/fmolb.2016.00027
- Nexo E, Hoffmann-Lücke E. Holotranscobalamin, a marker of vitamin B-12 status: analytical aspects and clinical utility. The American Journal of Clinical Nutrition. 2011;94(1):359S-365S. — Describes "active B12," a complementary marker often interpreted alongside MMA. — doi:10.3945/ajcn.111.013458
- Oberley MJ, Yang DT. Laboratory testing for cobalamin deficiency in megaloblastic anemia. American Journal of Hematology. 2013;88(6):522-526. — Reviews how MMA and related tests are used to work up macrocytic anemia. — doi:10.1002/ajh.23421
- Vashi P, Edwin P, Popiel B, et al. Methylmalonic acid and homocysteine as indicators of vitamin B-12 deficiency in cancer. PLOS ONE. 2016;11(1):e0147843. — Illustrates MMA and homocysteine detecting B12 deficiency missed by serum B12 alone. — doi:10.1371/journal.pone.0147843
PubMed Topic Searches
Connections
- Lab Tests
- Vitamin B12
- Vitamin B12 Deficiency
- Diagnosing B12 Deficiency
- Active B12 (Holotranscobalamin) Test
- B12 and the Nervous System
- Homocysteine Test
- Anemia
- Pernicious Anemia
- Peripheral Neuropathy
- SIBO
- Interactive: Vitamin B12 Absorption
- Vitamin B12 Test
- Folate Test
- Complete Blood Count (CBC)
- Kidney Function Tests
- MTHFR Gene Testing
- Folate (Vitamin B9)
- Peripheral Neuropathy