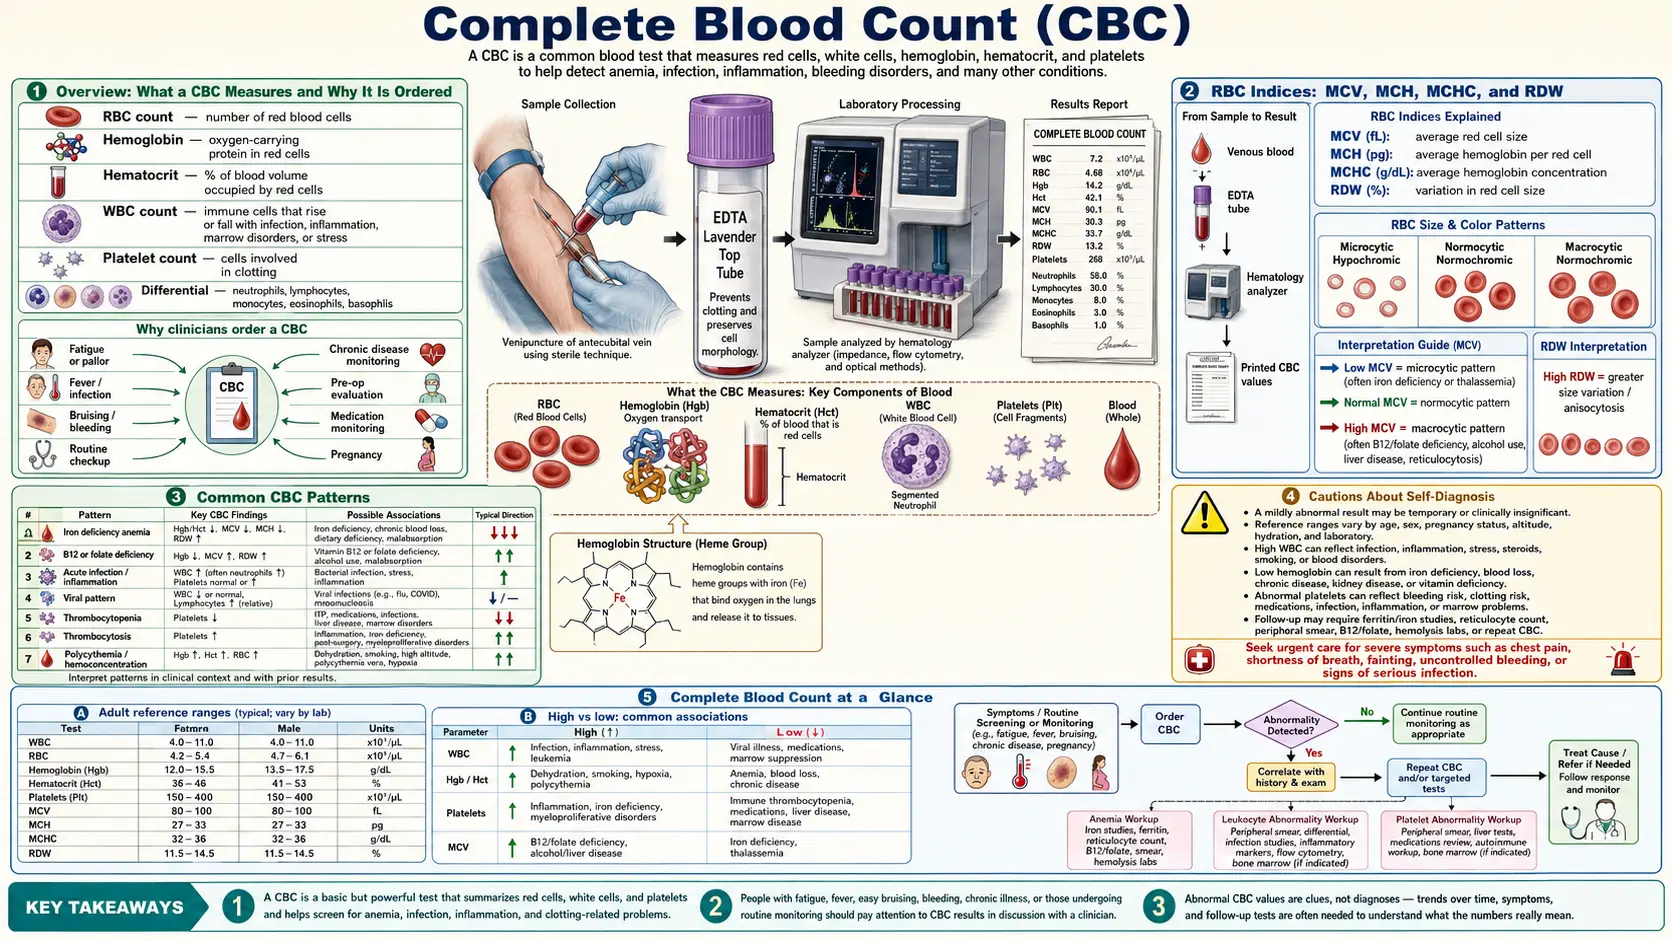
Complete Blood Count (CBC)
Table of Contents
- Overview: What a CBC Measures and Why It Is Ordered
- White Blood Cells (WBC) — Total Count
- WBC Differential: Neutrophils, Lymphocytes, Monocytes, Eosinophils, and Basophils
- Red Blood Cells (RBC) — Count, Hemoglobin, and Hematocrit
- RBC Indices: MCV, MCH, MCHC, and RDW
- Platelets: Count and Mean Platelet Volume (MPV)
- What High and Low Values Mean for Each Marker
- Common CBC Patterns
- Nutrition and CBC Markers: What the Research Reports
- Retesting: What Guidelines Describe
- Related Tests
- Cautions About Self-Diagnosis
- Key Research Papers
- Connections
- Featured Videos
Overview: What a CBC Measures and Why It Is Ordered
The Complete Blood Count (CBC) is a commonly performed blood test (MedlinePlus). It measures the three main cell populations circulating in the blood — white blood cells (leukocytes), red blood cells (erythrocytes), and platelets (thrombocytes) — together with hemoglobin, hematocrit, and the red-cell indices. A CBC with differential also reports each of the five main types of white blood cell (MedlinePlus).
About the ranges on this page. Unless another source is named, every range below is an example range from MedlinePlus (U.S. National Library of Medicine) — its CBC page and its pages for each component. MedlinePlus notes that normal value ranges vary slightly among laboratories, that some labs use different measurements or test different samples, and that blood counts may vary with altitude; a result is read against the range printed on the report from the laboratory that ran it. The MedlinePlus pages do not all give the same numbers, which illustrates how much ranges differ between sources. A laboratory reference interval describes the typical distribution of results in a healthy reference population, and a result outside it does not necessarily indicate disease; a clinical decision limit, by contrast, is tied to the risk of a specific outcome (Ozarda 2018, for the IFCC Committee on Reference Intervals and Decision Limits).
Some functional-medicine and naturopathic practitioners describe narrower “optimal” ranges for CBC markers. These ranges differ from one practitioner to another, and none of the sources cited on this page defines them, so they are not listed here.
MedlinePlus lists these reasons a CBC is ordered:
- As part of a routine checkup
- Symptoms such as fatigue, weakness, weight loss, fever or other signs of infection, bruising, or bleeding
- Treatments (medicines or radiation) that may change blood count results
- Monitoring a long-term condition that may change blood counts, such as chronic kidney disease
- Before and after major surgery, and during pregnancy (listed on the MedlinePlus hemoglobin and hematocrit pages)
- Investigating suspected infection, anemia, or leukemia (listed on the MedlinePlus blood differential page)
White Blood Cells (WBC) — Total Count
White blood cells are mediators of inflammation and the immune response (MedlinePlus). The total WBC count is used to help diagnose infection, allergic reaction, inflammation, and blood cancers such as leukemia or lymphoma (MedlinePlus WBC count page).
MedlinePlus example range: 4,500 to 11,000 cells per microliter (4.5 to 11.0 × 10⁹/L)
A count below 4,500 cells per microliter is called leukopenia. MedlinePlus lists bone marrow deficiency or failure, cancer-treating and other medicines, autoimmune disorders such as lupus, disease of the liver or spleen, radiation treatment, certain viral illnesses such as mononucleosis, cancers that damage the bone marrow, very severe bacterial infections, and an ethnic/genetic trait that is not uncommon in African Americans (see the Duffy-null section below).
A count above the range is called leukocytosis. MedlinePlus lists certain medicines (such as corticosteroids), cigarette smoking, spleen removal, infections (most often bacterial), inflammatory disease such as rheumatoid arthritis or allergy, leukemia or Hodgkin disease, tissue damage such as burns, pregnancy, and severe emotional or physical stress.
The differential, below, shows which cell types account for the total. MedlinePlus notes that an abnormal increase in one type of white blood cell can lower the percentage of the other types.
WBC Differential: Neutrophils, Lymphocytes, Monocytes, Eosinophils, and Basophils
The differential reports the five main types of white blood cell, each as a percentage of all white cells (MedlinePlus blood differential page). Multiplying a percentage by the total white cell count gives an absolute count — the method MedlinePlus describes for the absolute eosinophil count.
Neutrophils
Neutrophils make up the largest share of circulating white cells in the MedlinePlus ranges and are early responders to bacterial infection and acute inflammation. They are short-lived cells that arrive quickly at sites of tissue damage or microbial invasion.
- MedlinePlus example range: 40% to 60% of white cells; band (young) neutrophils 0% to 3%
MedlinePlus lists acute infection, inflammation, acute stress, eclampsia, gout, leukemia, myeloproliferative diseases, rheumatoid arthritis, rheumatic fever, thyroiditis, trauma, and cigarette smoking among causes of an increased neutrophil percentage, and aplastic anemia, chemotherapy, influenza and other viral infections, radiation, and sepsis among causes of a decreased percentage.
Neutropenia bands. Neutropenia is defined as an absolute neutrophil count (ANC) below 1,500 per µL in adults and children older than 1 year, and below 1,000 per µL in infants. It is classified as mild (1,000–1,500 per µL), moderate (500–999 per µL), or severe (below 500 per µL). The same review lists vitamin B12, folate, and copper deficiency among the nutritional causes of acquired neutropenia, and describes febrile neutropenia — fever with an ANC below 500 per µL — as an oncologic emergency (Kim 2025).
Duffy-null associated neutrophil count (formerly “benign ethnic neutropenia”). Many people of African ancestry have lower neutrophil counts without an increased risk of infection, a pattern associated with the Duffy-null phenotype (no Duffy antigen on red blood cells). In 120 healthy self-identified Black adults at one primary care center, 66.7% were Duffy-null; their median ANC was 2,820 per µL, compared with 5,005 per µL in Duffy non-null participants, and 23.8% of the Duffy-null participants had an ANC below 2,000 per µL, compared with none of the non-null group. The authors proposed replacing the term “benign ethnic neutropenia” with “Duffy-null associated neutrophil count” and developing Duffy-null-specific reference ranges (Merz 2023). A 2019 review, using the older name, described it as one of the most common causes of chronic neutropenia in people of African, Middle Eastern, and West Indian descent, with no increased risk of infection (Atallah-Yunes 2019). A 2026 study of 8,018 healthy Duffy-null adults on four continents established Duffy-null reference intervals (for the United States, ANC 1,210 to 5,390 per µL) and found that standard institutional reference intervals classified 21.7% to 50.9% of them as neutropenic, depending on the country; ANC did not differ significantly between Black and non-Black Duffy-null participants (Hibbs 2026).
Lymphocytes
Lymphocytes include T cells and B cells (MedlinePlus), as well as natural killer (NK) cells. They carry out adaptive immunity, including antibody production and immune memory.
- MedlinePlus example range: 20% to 40% of white cells
MedlinePlus lists chronic bacterial infection, infectious hepatitis, infectious mononucleosis, tuberculosis, lymphocytic leukemia, multiple myeloma, and viral infections such as mumps or measles among causes of an increased lymphocyte percentage, and chemotherapy, HIV/AIDS, leukemia, radiation, sepsis, steroid use, and aging among causes of a decreased percentage.
Monocytes
Monocytes migrate into tissues and become macrophages, which engulf microbes, dead cells, and debris. They also present antigens to T cells.
- MedlinePlus example range: 2% to 8% of white cells
MedlinePlus lists chronic inflammatory disease, leukemia, parasitic infection, tuberculosis, and viral infections (for example infectious mononucleosis, mumps, or measles) among causes of an increased monocyte percentage.
Eosinophils
Eosinophils are specialized cells involved in combating parasitic infections and modulating allergic and inflammatory responses. They release cytotoxic granules and pro-inflammatory mediators.
- MedlinePlus example range: 1% to 4% of white cells; absolute eosinophil count less than 500 cells per microliter
MedlinePlus lists adrenal gland deficiency (Addison disease), allergic disease including hay fever, asthma, autoimmune diseases, eczema, fungal infections, hypereosinophilic syndrome, leukemia and other blood disorders, lymphoma, and parasite infections such as worms among causes of a high eosinophil count, and notes that certain medicines can raise it. It also notes that the count cannot tell whether a rise is caused by allergy or by a parasite infection.
Basophils
Basophils are the rarest of the white blood cells and play a role in allergic reactions by releasing histamine and heparin. They are involved in immediate hypersensitivity responses.
- MedlinePlus example range: 0.5% to 1% of white cells
MedlinePlus lists spleen removal, allergic reaction, chronic myelogenous leukemia, collagen vascular disease, myeloproliferative diseases, and chickenpox among causes of an increased basophil percentage, and acute infection, cancer, and severe injury among causes of a decreased percentage.
Red Blood Cells (RBC) — Count, Hemoglobin, and Hematocrit
Red blood cells transport hemoglobin, which carries oxygen; the amount of oxygen body tissues receive depends on the amount and function of red cells and hemoglobin (MedlinePlus). This part of the CBC is used to detect anemia and conditions with too many red cells, such as polycythemia vera.
RBC Count
The RBC count measures the number of red blood cells in a given volume of blood.
- MedlinePlus CBC page: male 4.6 to 6.2 million cells/mcL; female 4.2 to 5.4 million cells/mcL
- MedlinePlus RBC count page: male 4.2 to 5.7 million cells/mcL; female 3.8 to 5.1 million cells/mcL
Hemoglobin (Hgb)
Hemoglobin is the iron-containing protein within red blood cells that carries oxygen. The World Health Organization defines anaemia by haemoglobin concentration.
- MedlinePlus CBC page: male 13 to 18 g/dL; female 12 to 16 g/dL
- MedlinePlus hemoglobin page: male 13.8 to 17.2 g/dL (138 to 172 g/L); female 12.1 to 15.1 g/dL (121 to 151 g/L)
WHO 2024 anaemia cutoffs. The 2024 WHO guideline defines anaemia by these haemoglobin cutoffs, set at the 5th percentile of haemoglobin in apparently healthy populations (WHO 2024):
- Children 6–23 months: below 105 g/L
- Children 24–59 months: below 110 g/L
- Children 5–11 years: below 115 g/L
- Children 12–14 years (boys and non-pregnant girls): below 120 g/L
- Non-pregnant women 15–65 years: below 120 g/L
- Men 15–65 years: below 130 g/L
- Pregnancy: below 110 g/L in the first and third trimesters, below 105 g/L in the second trimester
For adults, the guideline grades anaemia as mild at 110–129 g/L in men and 110–119 g/L in non-pregnant women, moderate at 80–109 g/L, and severe below 80 g/L. Compared with earlier WHO guidance, the 2024 guideline changed the cutoff for children 6–23 months and adopted the existing cutoff for the second trimester of pregnancy; it notes that data in adult men may suggest a higher cutoff (135 g/L) but retained 130 g/L because of uncertainty in the evidence. It recommends adjusting haemoglobin for elevation of residence and for smoking, and not adjusting it for infection or inflammation or for genetic ancestry, ethnicity, or race (WHO 2024).
MedlinePlus lists bleeding; a bone marrow unable to produce new red cells (from leukemia, other cancers, drug toxicity, radiation therapy, infection, or marrow disorders); chronic illness; chronic kidney disease; destruction of red cells (hemolysis); malnutrition; pregnancy; too little iron, folate, vitamin B12, and vitamin B6 in the diet; and too much water in the body among causes of a low hemoglobin. A high hemoglobin is most often caused by low blood oxygen (hypoxia) over a long period; MedlinePlus lists polycythemia vera, cigarette smoking, dehydration, failure of the right side of the heart (cor pulmonale), kidney tumor, congenital heart disease, and scarring of the lungs (pulmonary fibrosis), notes that hemoglobin rises for several weeks at higher altitude, and on its CBC page adds testosterone use.
Hematocrit (Hct)
Hematocrit is the share of whole blood made up of red blood cells (MedlinePlus). It usually moves in parallel with hemoglobin and RBC count.
- MedlinePlus CBC page: male 40% to 55%; female 36% to 48%
- MedlinePlus hematocrit page: male 37% to 48%; female 34% to 43%
Hemoglobin and hematocrit are concentrations, so hydration affects them: MedlinePlus lists dehydration (for example from severe diarrhea) among causes of a high hematocrit and too much water in the body among causes of a low one. MedlinePlus also lists copper deficiency alongside iron, folate, vitamin B12, and vitamin B6 deficiency among causes of a low hematocrit.
RBC Indices: MCV, MCH, MCHC, and RDW
The RBC indices measure the size and hemoglobin content of red blood cells, and the results are used to diagnose different types of anemia (MedlinePlus RBC indices page).
Mean Corpuscular Volume (MCV)
MCV measures the average size of red blood cells in femtoliters (fL).
- MedlinePlus CBC page: 80 to 100 fL
- MedlinePlus RBC indices page: 79 to 95 fL
MedlinePlus describes an MCV below normal (microcytic anemia) as possibly due to low iron levels, lead poisoning, or thalassemia; a normal MCV with anemia (normocytic anemia) as possibly due to sudden blood loss, long-term diseases, kidney failure, aplastic anemia, or man-made heart valves; and an MCV above normal (macrocytic anemia) as possibly due to low folate or vitamin B12 levels, chemotherapy, or liver disease.
Macrocytosis is generally defined as an MCV greater than 100 fL. A 2009 review lists alcoholism, vitamin B12 and folate deficiencies, and medications as the most common causes, and hypothyroidism, liver disease, and primary bone marrow disorders (including myelodysplasia and myeloproliferative disorders) as some of the more common other causes. A peripheral smear and a reticulocyte count help separate megaloblastic causes from drug or alcohol toxicity and from hemolysis or hemorrhage (Kaferle 2009).
Mean Corpuscular Hemoglobin (MCH)
MCH measures the average amount of hemoglobin per red blood cell in picograms (pg). It generally correlates with MCV.
- MedlinePlus CBC page: 27 to 32 pg/cell
- MedlinePlus RBC indices page: 26 to 33 pg/cell (female); 27 to 33 pg/cell (male)
MedlinePlus describes an MCH below normal (hypochromic anemia) as often due to low iron levels, and an MCH above normal as possibly due to low folate or vitamin B12 levels, chemotherapy, or liver disease.
Mean Corpuscular Hemoglobin Concentration (MCHC)
MCHC measures the average concentration of hemoglobin within red blood cells. It reflects how densely packed hemoglobin is within each cell.
- MedlinePlus example range: 32 to 36 g/dL (320 to 360 g/L)
MCHC is one of the red-cell parameters traditionally used in the diagnosis of hereditary spherocytosis, an inherited hemolytic disorder caused by red-cell membrane protein deficiency (Polizzi 2025).
Red Cell Distribution Width (RDW)
RDW measures how much the volume and size of red blood cells vary (anisocytosis). It is usually reported as a percentage and compared with a reference range that varies with the laboratory; MedlinePlus gives no single example range (MedlinePlus RDW page).
Bessman and colleagues combined MCV with RDW to classify anemias and reported that this improved the distinction of iron deficiency anemia from heterozygous thalassemia or the anemia of chronic disease, and improved the detection of early iron and folate deficiency; red-cell volume histograms also identified fragmented red cells and dimorphic (two-population) red cells (Bessman 1983).
MedlinePlus lists chronic liver disease, heart disease, diabetes, kidney disease, and cancer, especially colorectal cancer, among conditions that a high RDW may signal; it notes that a normal RDW does not rule out anemia and that a low RDW is not a sign of anemia. A 2015 review described an increased RDW as a strong and independent risk factor for death in the general population, while noting that it has not been established whether RDW is a cause or only a marker of underlying disturbances (Salvagno 2015).
Platelets: Count and Mean Platelet Volume (MPV)
Platelets are small cell fragments produced by megakaryocytes in the bone marrow. They are essential for blood clotting and wound healing. The platelet section of the CBC provides information about both clotting ability and underlying inflammatory or marrow conditions.
Platelet Count
- MedlinePlus example range: 150,000 to 400,000 platelets per microliter (150 to 400 × 109/L)
A count below 150,000 per microliter is thrombocytopenia (MedlinePlus; Gauer 2022). MedlinePlus notes that the risk of bleeding is higher below 50,000 per microliter. A 2022 review reports that people with counts above 50,000 per µL are generally without symptoms, that counts between 20,000 and 50,000 per µL may bring mild skin signs (petechiae, purpura, or bruising), and that counts below 10,000 per µL carry a high risk of serious bleeding. In stable outpatients, the review describes first excluding pseudothrombocytopenia (a falsely low count from platelet clumping in the sample) by repeating the count in a tube containing heparin or sodium citrate; common non-emergency causes are drug-induced thrombocytopenia, immune thrombocytopenia, and liver disease (Gauer 2022). MedlinePlus groups the causes as too few platelets made in the marrow, platelets destroyed in the bloodstream, and platelets destroyed in the spleen or liver, and lists cancer treatments, medicines, and autoimmune disorders as three of the more common causes; its CBC page adds pregnancy and an enlarged spleen.
A count of 400,000 per microliter or above is thrombocytosis. MedlinePlus lists iron deficiency, certain infections, major surgery or trauma, cancer, certain medicines, myeloproliferative neoplasms (including polycythemia vera), and spleen removal, and notes that some people with very high counts may be at risk of blood clots or of bleeding.
Mean Platelet Volume (MPV)
- Study range: in 326 healthy adults in a Turkish population study, measured on one analyzer, 95% had an MPV between 7.2 and 11.7 fL (mean 8.9 fL) (Demirin 2011); each laboratory sets its own range
MPV measures the average size of platelets. Newly made platelets are larger than older platelets (MedlinePlus MPV page). MedlinePlus describes a high MPV as possibly meaning that older platelets are being destroyed faster and the marrow is making many new ones, listing thrombocytopenia, myeloproliferative diseases, preeclampsia, heart disease, diabetes, and hemolytic anemia; and a low MPV as possibly meaning the marrow is not making enough new platelets, listing certain cancers, side effects of certain medicines, aplastic anemia, autoimmune diseases, bacterial or viral infections, genetic conditions, and alcohol use disorder.
In a 2010 meta-analysis, MPV was higher in people with acute myocardial infarction than in those without (mean difference 0.92 fL; 16 cross-sectional studies, 2,809 patients), and an elevated MPV was associated with death after myocardial infarction and with restenosis after coronary angioplasty; the authors wrote that whether the relationship is causal, and whether MPV has a role in guiding treatment, remains unknown (Chu 2010).
What High and Low Values Mean for Each Marker
Interpreting CBC results requires looking at each marker individually and in relation to the others. The summary below collects the causes listed in the sections above; it is a list of possibilities, not a diagnosis.
White Blood Cells
- High WBC: Infection (most often bacterial), inflammatory disease, allergy, leukemia or Hodgkin disease, cigarette smoking, corticosteroids and certain other medicines, tissue damage such as burns, pregnancy, severe physical or emotional stress, spleen removal (MedlinePlus)
- Low WBC: Bone marrow failure, chemotherapy and certain other medicines, radiation, autoimmune disorders, liver or spleen disease, viral illnesses, very severe bacterial infections, the Duffy-null trait (MedlinePlus; Merz 2023)
Red Blood Cells, Hemoglobin, and Hematocrit
- High values: Dehydration, long-term low blood oxygen (heart or lung disease, living at high altitude), polycythemia vera, cigarette smoking, kidney tumors, testosterone use (MedlinePlus)
- Low values: Blood loss, hemolysis, bone marrow failure, chronic illness, chronic kidney disease, deficiency of iron, copper, folate, vitamin B12, or vitamin B6, pregnancy, over-hydration (MedlinePlus)
MCV
- High MCV: Vitamin B12 or folate deficiency, alcohol, medications, chemotherapy, hypothyroidism, liver disease, primary bone marrow disorders (MedlinePlus; Kaferle 2009)
- Low MCV: Iron deficiency, thalassemia, lead poisoning (MedlinePlus)
RDW
- High RDW: Early iron or folate deficiency, two red-cell populations, and conditions MedlinePlus lists such as chronic liver disease, heart disease, diabetes, kidney disease, and cancer (Bessman 1983; MedlinePlus)
- Low RDW: Not a sign of anemia (MedlinePlus)
Platelets
- High Platelets: Iron deficiency, certain infections, major surgery or trauma, cancer, myeloproliferative neoplasms, spleen removal (MedlinePlus)
- Low Platelets: Medicines, immune thrombocytopenia, liver disease, cancer treatments, bone marrow failure, enlarged spleen, pregnancy, and the laboratory artifact pseudothrombocytopenia (MedlinePlus; Gauer 2022)
Common CBC Patterns
Certain combinations of results point toward particular causes. MedlinePlus describes the CBC as only one tool, read together with medical history, symptoms, and other tests.
Iron Deficiency Pattern
The pattern usually described for iron deficiency includes:
- Low or low-normal hemoglobin and hematocrit
- Low MCV (microcytic cells) (MedlinePlus)
- Low MCH (hypochromic cells) (MedlinePlus)
- Raised RDW, which improved the detection of early iron deficiency in the MCV/RDW classification (Bessman 1983)
- Possibly a raised platelet count, since MedlinePlus lists iron deficiency among causes of thrombocytosis
- Low or low-normal RBC count
Iron deficiency is confirmed with iron studies. The British Society of Gastroenterology’s 2021 guideline describes serum ferritin as the single most useful marker: a ferritin below 15 µg/L indicates absent iron stores and one below 30 µg/L generally indicates low stores, so most laboratories’ lower limit lies between 15 and 30 µg/L. Because ferritin rises with inflammation, an apparently normal ferritin can occur with iron deficiency when inflammation is present, and transferrin saturation can help. For microcytosis with normal iron studies, the guideline describes hemoglobin electrophoresis to look for thalassemia. It also reports that about a third of men and postmenopausal women presenting with iron deficiency anemia have an underlying abnormality, most commonly in the gastrointestinal tract, which is why investigation of the cause accompanies treatment (Snook 2021).
B12 and Folate Deficiency Pattern
This pattern reflects impaired DNA synthesis in developing red blood cells, causing them to become abnormally large:
- Low or low-normal hemoglobin and hematocrit
- High MCV (macrocytosis, generally defined as above 100 fL) (Kaferle 2009)
- High MCH (MedlinePlus)
- Raised RDW in early folate deficiency (Bessman 1983)
- Possibly a low neutrophil count, since B12 and folate deficiency are among the nutritional causes of neutropenia (Kim 2025)
- Megaloblastic changes on the peripheral smear (Kaferle 2009)
MedlinePlus lists the CBC, reticulocyte count, lactate dehydrogenase, bilirubin, serum B12, methylmalonic acid (MMA), homocysteine, and anti-intrinsic factor and anti-parietal cell antibodies among the tests used for B12 deficiency anemia. The British Society for Haematology guideline states that there is no “gold standard” test for cobalamin (B12) deficiency: serum cobalamin is the first-line test, plasma MMA is a second-line test that helps clarify uncertain results, and homocysteine is less specific than MMA. It concludes that definitive cut-off points for clinical and subclinical deficiency are not possible because of differences in methods, that local reference ranges are to be established, and that when results conflict with strong clinical features of deficiency, treatment is not delayed, because of the risk of neurological impairment (Devalia 2014).
Chronic Infection and Inflammation Pattern
Long-lasting infection or inflammation can shift several CBC values:
- A total WBC count that is normal or raised
- Raised monocytes, which MedlinePlus lists with chronic inflammatory disease, tuberculosis, and some viral infections
- Raised lymphocytes, which MedlinePlus lists with viral infections, tuberculosis, and chronic bacterial infection
- Normocytic anemia (low hemoglobin with normal MCV), which MedlinePlus lists with long-term diseases
- A raised platelet count, which MedlinePlus lists after certain infections
Dehydration Pattern
MedlinePlus lists dehydration among causes of a high RBC count, hemoglobin, and hematocrit, and too much water in the body among causes of low values. Because these are concentrations, a sample drawn during dehydration reads higher than one drawn at normal hydration, which can make a low hemoglobin look closer to normal.
Nutrition and CBC Markers: What the Research Reports
Nutritional deficiencies are one group of causes behind abnormal CBC results: MedlinePlus lists too little iron, copper, folate, vitamin B12, and vitamin B6 among causes of low red-cell values. The findings below describe what studies and guidelines report. Decisions about supplements belong with a clinician, partly because the cause of a deficiency — for example blood loss from the gastrointestinal tract — also needs to be found (Snook 2021).
Iron-Rich Foods and Iron Absorption
Iron bioavailability has been estimated at about 14–18% from mixed diets and 5–12% from vegetarian diets in people with no iron stores. Phytate, polyphenols, and calcium (which reduce absorption) and ascorbic acid and meat (which increase it) change iron absorption in single-meal isotope studies, but their effect is more modest in multi-meal studies of a varied diet, and a person’s iron status generally has a greater effect on absorption than diet composition (Hurrell 2010).
- Heme iron sources: Red meat, liver and organ meats, dark poultry meat, fish, oysters and clams
- Non-heme iron sources: Lentils, chickpeas, dark leafy greens (spinach, kale, Swiss chard), pumpkin seeds, blackstrap molasses, quinoa
- Tea and meals: The British Society of Gastroenterology guideline notes that taking oral iron with meals can reduce its bioavailability by up to 75%, and that the inhibitory effect of tea on iron absorption dissipates within 60 minutes (Snook 2021).
- Iron cookware: In a systematic review of 11 randomized trials in low- and middle-income countries, 4 of 8 studies of iron pots and 1 of 3 studies of iron ingots found significant increases in hemoglobin or iron indices; the authors called for further research on efficacy and safety (Alves 2019).
Oral Iron Preparations
The British Society of Gastroenterology guideline reports that gastrointestinal side effects (nausea, diarrhea, constipation) are much commoner with oral than with intravenous iron, and finds no convincing evidence that any of the readily available traditional iron salts is superior to the others (Snook 2021). In a meta-analysis of 17 randomized trials, ferrous bisglycinate (an iron–amino acid chelate) given for 4–20 weeks produced higher hemoglobin concentrations (standardized mean difference 0.54 g/dL) and fewer gastrointestinal adverse events (incidence rate ratio 0.36) than other iron supplements in pregnant women, with no significant difference in children; the authors called for more trials in other populations (Fischer 2023). A meta-analysis of 4 trials in 600 pregnant women with iron deficiency anemia concluded that oral bovine lactoferrin was as effective as ferrous sulfate in improving hematological values, with fewer gastrointestinal side effects (Abu Hashim 2017).
Vitamin C and Iron Absorption
Ascorbic acid increases iron absorption from a single meal (Hurrell 2010). In a randomized equivalence trial in 440 adults with iron deficiency anemia, adding 200 mg of vitamin C to each 100 mg oral iron tablet, taken every 8 hours for 3 months, gave a hemoglobin rise at 2 weeks equivalent to iron alone, with no difference in ferritin gain at 8 weeks or in adverse events (Li 2020). Citing that trial, the British Society of Gastroenterology guideline recommends against routinely adding vitamin C to oral iron therapy (Snook 2021). Whole-food sources of vitamin C include citrus fruits, kiwi, strawberries, bell peppers, broccoli, and guava.
Vitamin B12
- Food sources: Meat, poultry, shellfish, eggs, and dairy products, as well as fortified foods such as breakfast cereals (MedlinePlus). A 2014 review identified dried purple laver (nori) as the most suitable naturally occurring plant source of B12 then available (Watanabe 2014).
- Who is at risk: A review of studies that measured MMA or holotranscobalamin found B12 depletion or deficiency among vegetarians in every population studied, with higher rates in vegans and in people vegetarian since birth (Pawlak 2013). A Cochrane review notes that B12 deficiency is common and its incidence increases with age (Wang 2018).
- Absorption: B12 absorption depends on intrinsic factor, a protein released by cells in the stomach. MedlinePlus lists pernicious anemia, surgery that removes parts of the stomach or small intestine (including some weight-loss surgeries), Crohn disease, celiac disease, fish tapeworm infection, alcohol use, long-term antacid and heartburn medicines, long-term metformin, and nitrous oxide abuse among causes of poor absorption.
- Oral versus injected B12: A Cochrane review of 3 trials (153 participants) found low-quality evidence that oral B12 (1,000 µg/day in two trials, 2,000 µg/day in one) and intramuscular B12 normalize serum B12 levels similarly, with lower treatment costs for the oral route (Wang 2018).
Folate
- Food sources: Dark leafy greens, asparagus, Brussels sprouts, avocado, lentils, beets, liver
- Testing: The British Society for Haematology guideline names serum folate as the first-line test of folate status (Devalia 2014).
- Folic acid and B12 deficiency: In the 1940s and 1950s, high-dose folic acid (more than 5 mg/day) was used to reverse the megaloblastic anemia of B12 deficiency caused by pernicious anemia; this masked the underlying B12 deficiency and possibly worsened its neurological progression. A 2024 review describes the evidence that excess folic acid worsens B12 deficiency as mainly correlative or from uncontrolled observations, but sufficient to warrant increased vigilance for B12 deficiency in at-risk people who take excessive or high-dose folic acid (Miller 2024).
Additional Supportive Nutrients
- Copper: MedlinePlus lists copper deficiency among causes of a low RBC count and hematocrit, and a 2025 review lists it among nutritional causes of neutropenia (Kim 2025). Food sources include liver, oysters, dark chocolate, and mushrooms.
- Vitamin B6: MedlinePlus lists too little vitamin B6 among causes of a low hemoglobin. Food sources include poultry, fish, potatoes, bananas, and sunflower seeds.
Retesting: What Guidelines Describe
The timing of a repeat CBC depends on the condition being followed. The intervals below are those described in the sources named.
- Iron deficiency anemia treated with oral iron: The British Society of Gastroenterology guideline reports that hemoglobin usually rises within 2 weeks of starting oral iron, and that in anemic patients a rise of 10 g/L or more within 2 weeks is highly suggestive of absolute iron deficiency. It recommends monitoring the hemoglobin response in the first 4 weeks and continuing treatment for around 3 months after hemoglobin normalizes to replenish marrow iron stores; once hemoglobin is normal, it describes a check blood count every 3 months for 12 months and then every 6 months for 2–3 years as reasonable (Snook 2021).
- B12 or folate deficiency: Follow-up blood counts and B12 or folate tests are part of monitoring treatment; the sources cited on this page do not give a fixed interval.
- Routine checkups: MedlinePlus notes that a CBC is often part of a routine checkup.
- Acute illness: Repeat testing depends on the condition being monitored and can be within days.
MedlinePlus notes that diet, activity level, medicines, a menstrual period, not drinking enough water, and other factors can affect results, so results drawn under similar conditions are easier to compare over time.
Related Tests
A CBC provides an overview, and its findings often lead to further testing. Tests commonly read alongside a CBC include:
- Iron Panel: Serum iron, ferritin, TIBC (total iron-binding capacity), and transferrin saturation. Serum ferritin is described as the single most useful marker of iron deficiency anemia, with transferrin saturation helpful when a falsely normal ferritin is suspected (Snook 2021).
- Vitamin B12 and Folate: Serum B12, serum folate, methylmalonic acid (MMA), and homocysteine, used in evaluating macrocytic anemia (MedlinePlus; Devalia 2014).
- Reticulocyte Count: Measures the production rate of new red blood cells; in macrocytosis it helps separate drug or alcohol toxicity from hemolysis or hemorrhage (Kaferle 2009).
- Comprehensive Metabolic Panel (CMP): Provides information about liver and kidney function; MedlinePlus lists erythropoietin deficiency from kidney disease among causes of a low RBC count.
- C-Reactive Protein (CRP) and ESR: Markers of systemic inflammation that help put WBC and platelet elevations in context.
- Thyroid Panel: TSH, free T3, free T4, and thyroid antibodies. Hypothyroidism is among the more common non-nutritional causes of macrocytosis (Kaferle 2009).
- Peripheral Blood Smear: A microscopic review of blood cells that can show abnormal cell shapes, inclusions, and megaloblastic changes not captured by automated counts (Kaferle 2009).
- Hemoglobin Electrophoresis: Described for microcytosis with normal iron studies, to look for thalassemia (Snook 2021).
- Hemoglobin A1c: Reflects average blood glucose over about three months, the lifespan of red cells; MedlinePlus notes that anemia or another blood disorder can make the A1C test inaccurate for diagnosing diabetes.
- Copper Level: Copper deficiency is listed among causes of a low RBC count and hematocrit (MedlinePlus) and of neutropenia (Kim 2025).
Cautions About Self-Diagnosis
Understanding CBC results supports informed conversations with health care providers, but the test has limits. MedlinePlus describes the CBC as only one tool, read together with medical history, symptoms, and other tests, and notes that an abnormal result does not always mean a medical condition that needs treatment.
- Context matters: A single CBC result is a snapshot in time. MedlinePlus notes that diet, activity level, medicines, a menstrual period, and not drinking enough water can affect results. Trends over several tests give more information than any single result.
- Patterns over individual markers: Isolated values rarely tell the complete story. A slightly elevated WBC means something very different during an acute cold than after months of unexplained fatigue, which is why the CBC is read as a whole and alongside symptoms and other tests.
- Serious conditions: Many CBC abnormalities reflect common causes such as nutritional deficiencies, but some point to serious conditions, including leukemia, lymphoma, myelodysplasia, aplastic anemia, and other blood disorders (MedlinePlus; Kaferle 2009). Persistent or unexplained abnormalities are the usual reason for further evaluation.
- Supplements carry risks: Iron supplementation is a recognized hazard for people with hemochromatosis or other iron overload, and high-dose folic acid can mask vitamin B12 deficiency (Miller 2024). Decisions about supplements belong with a clinician who can assess the full clinical picture.
- Reference intervals are not diagnoses: A result outside a reference interval does not necessarily indicate disease (Ozarda 2018). The narrower “optimal” ranges used by some practitioners are not defined by the sources cited on this page.
- Individual variation: Some people have consistently low or high values that are normal for them; the lower neutrophil counts of Duffy-null individuals are one example (Merz 2023). Trained endurance athletes have a lower hematocrit, sometimes called “sports anemia,” caused by an increased plasma volume, although their total red-cell and hemoglobin mass is higher than that of sedentary people (Mairbäurl 2013). Results from times of good health give a baseline for comparison during illness.
The CBC is a widely available, routinely performed test. Its results are read alongside history, symptoms, and other tests, and decisions about further testing or treatment belong with a clinician.
Key Research Papers
- World Health Organization (2024). Guideline on haemoglobin cutoffs to define anaemia in individuals and populations. Geneva: World Health Organization (WHO Guidelines Approved by the Guidelines Review Committee) — PubMed PMID: 38530913
- Kim MJ, Forlini C, Kremsreiter K (2025). Neutropenia: Evaluation and Management in the Primary Care Setting. American Family Physician 112(6):618-628 — PubMed PMID: 41533406
- Merz LE, Story CM, Osei MA, et al. (2023). Absolute neutrophil count by Duffy status among healthy Black and African American adults. Blood Advances 7(3):317-320 — PubMed PMID: 35994632
- Hibbs SP, Chipare I, Halawani AJ, et al. (2026). Multinational assessment of absolute neutrophil counts and white blood cell counts among healthy Duffy-null adults. Blood 147(3):290-298 — PubMed PMID: 41191521
- Atallah-Yunes SA, Ready A, Newburger PE (2019). Benign ethnic neutropenia. Blood Reviews 37:100586 — PubMed PMID: 31255364
- Bessman JD, Gilmer PR Jr, Gardner FH (1983). Improved classification of anemias by MCV and RDW. American Journal of Clinical Pathology 80(3):322-326 — PubMed PMID: 6881096
- Salvagno GL, Sanchis-Gomar F, Picanza A, Lippi G (2015). Red blood cell distribution width: A simple parameter with multiple clinical applications. Critical Reviews in Clinical Laboratory Sciences 52(2):86-105 — PubMed PMID: 25535770
- Kaferle J, Strzoda CE (2009). Evaluation of macrocytosis. American Family Physician 79(3):203-208 — PubMed PMID: 19202968
- Polizzi A, Dicembre LP, Failla C, et al. (2025). Overview on Hereditary Spherocytosis Diagnosis. International Journal of Laboratory Hematology 47(1):18-25 — PubMed PMID: 39467036
- Gauer RL, Whitaker DJ (2022). Thrombocytopenia: Evaluation and Management. American Family Physician 106(3):288-298 — PubMed PMID: 36126009
- Demirin H, Ozhan H, Ucgun T, et al. (2011). Normal range of mean platelet volume in healthy subjects: Insight from a large epidemiologic study. Thrombosis Research 128(4):358-360 — PubMed PMID: 21620440
- Chu SG, Becker RC, Berger PB, et al. (2010). Mean platelet volume as a predictor of cardiovascular risk: a systematic review and meta-analysis. Journal of Thrombosis and Haemostasis 8(1):148-156 — PubMed PMID: 19691485
- Snook J, Bhala N, Beales ILP, et al. (2021). British Society of Gastroenterology guidelines for the management of iron deficiency anaemia in adults. Gut 70(11):2030-2051 — PubMed PMID: 34497146
- Hurrell R, Egli I (2010). Iron bioavailability and dietary reference values. American Journal of Clinical Nutrition 91(5):1461S-1467S — PubMed PMID: 20200263
- Alves C, Saleh A, Alaofè H (2019). Iron-containing cookware for the reduction of iron deficiency anemia among children and females of reproductive age in low- and middle-income countries: A systematic review. PLoS One 14(9):e0221094 — PubMed PMID: 31479458
- Fischer JAJ, Cherian AM, Bone JN, Karakochuk CD (2023). The effects of oral ferrous bisglycinate supplementation on hemoglobin and ferritin concentrations in adults and children: a systematic review and meta-analysis of randomized controlled trials. Nutrition Reviews 81(8):904-920 — PubMed PMID: 36728680
- Abu Hashim H, Foda O, Ghayaty E (2017). Lactoferrin or ferrous salts for iron deficiency anemia in pregnancy: A meta-analysis of randomized trials. European Journal of Obstetrics & Gynecology and Reproductive Biology 219:45-52 — PubMed PMID: 29059584
- Li N, Zhao G, Wu W, et al. (2020). The Efficacy and Safety of Vitamin C for Iron Supplementation in Adult Patients With Iron Deficiency Anemia: A Randomized Clinical Trial. JAMA Network Open 3(11):e2023644 — PubMed PMID: 33136134
- Devalia V, Hamilton MS, Molloy AM; British Committee for Standards in Haematology (2014). Guidelines for the diagnosis and treatment of cobalamin and folate disorders. British Journal of Haematology 166(4):496-513 — PubMed PMID: 24942828
- Pawlak R, Parrott SJ, Raj S, Cullum-Dugan D, Lucus D (2013). How prevalent is vitamin B12 deficiency among vegetarians? Nutrition Reviews 71(2):110-117 — PubMed PMID: 23356638
- Wang H, Li L, Qin LL, Song Y, Vidal-Alaball J, Liu TH (2018). Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database of Systematic Reviews 3:CD004655 — PubMed PMID: 29543316
- Watanabe F, Yabuta Y, Bito T, Teng F (2014). Vitamin B12-containing plant food sources for vegetarians. Nutrients 6(5):1861-1873 — PubMed PMID: 24803097
- Miller JW, Smith A, Troen AM, Mason JB, Jacques PF, Selhub J (2024). Excess Folic Acid and Vitamin B12 Deficiency: Clinical Implications? Food and Nutrition Bulletin 45(1 Suppl):S67-S72 — PubMed PMID: 38987872
- Ozarda Y, Sikaris K, Streichert T, Macri J; IFCC Committee on Reference Intervals and Decision Limits (2018). Distinguishing reference intervals and clinical decision limits – A review by the IFCC Committee on Reference Intervals and Decision Limits. Critical Reviews in Clinical Laboratory Sciences 55(6):420-431 — PubMed PMID: 30047297
- Mairbäurl H (2013). Red blood cells in sports: effects of exercise and training on oxygen supply by red blood cells. Frontiers in Physiology 4:332 — PubMed PMID: 24273518
PubMed Topic Searches
- Complete blood count interpretation — PubMed literature search
- Neutrophil lymphocyte ratio prognosis — PubMed literature search
- MCV macrocytosis causes — PubMed literature search
- Red cell distribution width — PubMed literature search
- Thrombocytopenia evaluation — PubMed literature search
- Eosinophilia differential — PubMed literature search
- Leukocytosis clinical — PubMed literature search
- Microcytic anemia iron deficiency — PubMed literature search
- Lymphocytosis viral infection — PubMed literature search
- Mean platelet volume cardiovascular — PubMed literature search
External Authoritative Resources
- MedlinePlus — Laboratory Tests Reference
- MedlinePlus — Complete Blood Count (CBC) medical test
- MedlinePlus — Medical Tests (U.S. National Library of Medicine)
- MedlinePlus Medical Encyclopedia — CBC blood test
- MedlinePlus Medical Encyclopedia — WBC count
- MedlinePlus Medical Encyclopedia — Blood differential test
- MedlinePlus Medical Encyclopedia — Eosinophil count – absolute
- MedlinePlus Medical Encyclopedia — RBC count
- MedlinePlus Medical Encyclopedia — Hemoglobin
- MedlinePlus Medical Encyclopedia — Hematocrit
- MedlinePlus Medical Encyclopedia — RBC indices
- MedlinePlus Medical Encyclopedia — Platelet count
- MedlinePlus — RDW (Red Cell Distribution Width)
- MedlinePlus — MPV Blood Test
- MedlinePlus Medical Encyclopedia — Vitamin B12 deficiency anemia
- MedlinePlus — Hemoglobin A1C (HbA1c) Test
Connections
- All Lab Tests
- Anemia
- Relationship Between Hemoglobin and Ceruloplasmin — why ceruloplasmin (the copper ferroxidase) is required to load iron into hemoglobin, and why "iron-deficiency anemia" is often functional copper deficiency.
- Iron Panel
- Vitamin B12
- Inflammatory Markers
- Iron
- Homocysteine
- Thrombocytopenia
- Polycythemia Vera
- Thalassemia
- Liver Disease
- Kidney Function
- Hemoglobin A1C
- Vitamin B12 (Vitamin)
- Vitamin C
- Hemochromatosis
- Fatigue
- Full Body MRI
- Sepsis
- Rosalyn Yalow — the assay behind most modern blood tests, and how to read a reference range
- Metabolic Panel
Featured Videos