Dong Quai and Menopause: An Evidence Review
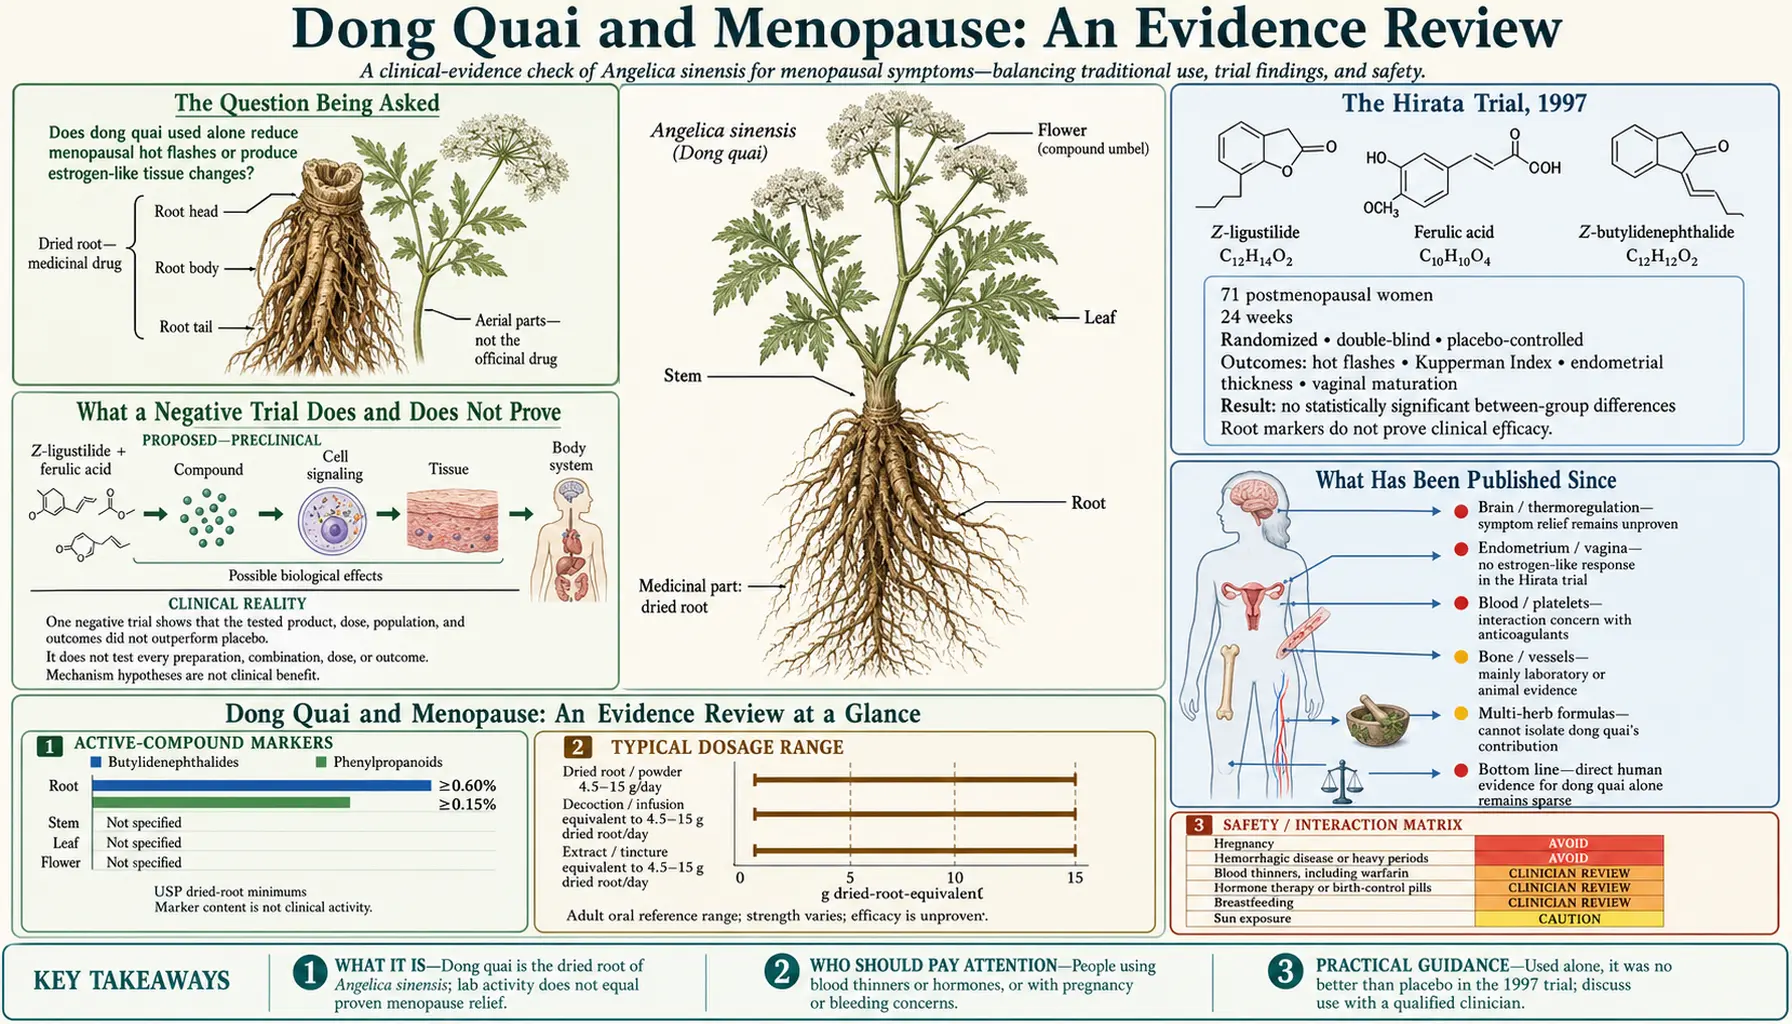
This page is a review, not a benefit claim. Dong Quai is one of the most widely sold botanicals for hot flushes, and it is also one of the very few that has been put through a properly designed randomised, placebo-controlled trial. The trial was negative, nothing published since has overturned it, and this article explains what was tested, what the fair counter-arguments are, and why they do not rescue the claim.
Table of Contents
- The Question Being Asked
- The Hirata Trial, 1997
- What a Negative Trial Does and Does Not Prove
- What Has Been Published Since
- The Fair Counter-Argument — and Its Limits
- How Oestrogenic Dong Quai Is: What the Tests Show
- Endometrial Safety and Hormone-Sensitive Conditions
- The Bleeding Argument Against Casual Use
- What Actually Works for Hot Flushes
- The Bottom Line
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
The Question Being Asked
This page is precise about the claim on trial, because vagueness is how weak evidence survives.
The claim made by the supplement market is: a woman with vasomotor symptoms — hot flushes and night sweats — who takes Dong Quai capsules will have fewer or milder flushes than she would otherwise. That is a testable claim about a single herb taken alone, in a capsule, for a defined symptom, and it is the claim that matters because it is the one people spend money on.
It is a different question from “does a Chinese herbal formula prescribed by a practitioner for a diagnosed pattern help menopausal complaints”, and different again from “is Dang Gui a useful herb”. Those questions have their own answers, discussed below. But when a bottle labelled “Dong Quai — Female Ginseng” sits on a shelf in the menopause aisle, the first claim is the one being sold, and it is the one this page evaluates.
One piece of context is worth carrying through: as the Benefits hub explains, “female ginseng” is a Western marketing label. Traditional Chinese medicine does not classify Dang Gui as a menopause remedy, and it does not use it as a solo herb. The Western use case was, from the beginning, something of an invention.
The Hirata Trial, 1997
In 1997, Hirata and colleagues published a randomised, double-blind, placebo-controlled trial in Fertility and Sterility with the blunt title “Does dong quai have estrogenic effects in postmenopausal women?”
The design was straightforward and, for a botanical trial of that era, unusually good:
- 71 postmenopausal women, randomised.
- Dong Quai root preparation versus matching placebo, double-blind.
- 24 weeks of treatment — long enough for a real effect on vasomotor symptoms to appear, and long enough to look at tissue endpoints.
- Three outcomes chosen to detect both symptom relief and any oestrogen-like tissue effect:
- Hot flush counts — the symptom that matters to patients.
- Vaginal maturation index — a cytological measure of oestrogenic effect on vaginal epithelium.
- Endometrial thickness on ultrasound — another tissue-level oestrogen readout.
The result: no difference from placebo on any of the three. Hot flushes did not fall more in the treatment group. The vaginal maturation index did not change. Endometrial thickness did not change. The authors concluded that dong quai used alone did not produce oestrogen-like effects and was no more useful than placebo for menopausal symptoms.
Two features of the design deserve emphasis, because they are what make this trial hard to argue with:
- It was placebo-controlled and double-blind. Hot flushes are notoriously placebo-responsive — placebo arms in vasomotor trials routinely report reductions of 20–40% or more. An uncontrolled study of any hot-flush remedy will look impressive. Only a placebo arm separates the drug from the expectation.
- It measured tissue as well as symptoms. A herb could theoretically relieve flushes without being oestrogenic. Hirata's design tested both, and found neither.
What a Negative Trial Does and Does Not Prove
Honesty runs in both directions, so here is what the trial does not establish.
- It does not prove Dong Quai is inert. It tested one preparation, at one dose, in one population, for one set of outcomes.
- With 71 participants, a very small effect could have been missed. That is true of any trial of that size. But an effect on hot flushes too small to detect in 71 women over 24 weeks would be a small effect at best.
- It tested the single herb, not a formula. This is the strongest legitimate objection and it is addressed below.
What the trial does establish is more than enough for a purchasing decision: a Dong Quai preparation taken alone for 24 weeks did not beat a sugar pill for hot flushes. Given that this is precisely how the product is sold in the West, that is the relevant finding.
What Has Been Published Since
Nearly three decades on, the picture has not changed. Systematic reviews of botanicals for menopausal symptoms have repeatedly examined Dong Quai and have not found evidence that the single herb reduces hot flushes; reviews of complementary approaches for menopause consistently place it among the botanicals without supportive trial evidence, in contrast with a handful of others where the data are merely mixed.
The most relevant subsequent randomised trial actually tested a formula rather than the solo herb. Haines and colleagues, publishing in Climacteric in 2008, ran a randomised, double-blind, placebo-controlled study of Dang Gui Buxue Tang — the classical two-herb astragalus-and-Dong-Quai decoction — in 100 Hong Kong Chinese women with menopausal symptoms (50 per group, 6 months, a 1:5 mix of Dang Gui and Huang Qi). Overall the formula was not shown to be more effective than placebo for hot flushes and night sweats. The one exception was mild hot flushes: these fell significantly in the formula group (from 18.9 to 8.6 a month) but not significantly in the placebo group, so the authors found the formula “statistically superior to placebo only in the treatment of mild hot flushes”. Moderate flushes and night sweats fell significantly only in the placebo group.
That result matters because it closes off the easiest escape route. It is not the case that nobody ever tested a traditional Dang Gui formula properly. Someone did, in the population where the tradition originates, and apart from mild flushes it also failed to beat placebo.
A 2026 systematic review (Jing, Keane and Reynolds, Nutrients) gathered 30 randomised trials of herbal supplements other than soy for menopausal symptoms. Most herbs reported some improvement, but “the two RCTs using black cohosh and dong quai found no measurable effects”. The authors judged the trials too varied in herb, dose, length and measurement to reach an overall conclusion.
The Fair Counter-Argument — and Its Limits
There is a real argument on the other side, and it deserves to be stated properly rather than strawmanned.
The argument: Chinese medicine never uses Dang Gui as a solo herb for menopausal symptoms. Traditional practice diagnoses a pattern — kidney yin deficiency with empty heat, liver qi constraint, and so on — and prescribes a multi-herb formula tailored to it, adjusted over time. Testing a single herb in an undifferentiated population is, from within that framework, testing something the tradition never claimed. Herbs in a formula also interact chemically: as the research on Dang Gui Bu Xue Tang shows, co-decoction changes what is extracted, and combinations are not the sum of their parts.
Some combination products have performed better than the solo herb. A small trial by Kupfersztain and colleagues, published in 2003, tested a preparation combining Angelica sinensis with German chamomile (Matricaria chamomilla) in 55 postmenopausal women with hot flushes who did not want hormone therapy. Over 12 weeks, hot flushes fell in number and intensity by 90–96% on the tablets versus 15–25% on placebo. These are unusually large figures for a hot-flush trial, which is one reason replication matters. This is a genuine data point, and it is reported here in full.
Now the limits of that argument, which are substantial:
- The Kupfersztain study was small, and combination trials of this size in a condition with a large placebo response are exactly the kind of study that fails to replicate.
- A positive result for Angelica sinensis plus chamomile is not evidence for Angelica sinensis. Chamomile is the other half of the product, and attributing the effect to the herb you are selling is the oldest error in botanical research. The same logic applies to Si Wu Tang derivatives, where peony and chuan xiong are equally credible candidates.
- When a traditional Dang Gui formula was tested properly — Haines 2008, 100 women for 6 months — it did not beat placebo either, except for mild hot flushes.
- Most decisively: the counter-argument is an argument for formulas, not for the product people actually buy. Even if it is entirely correct, it provides no support whatsoever for a bottle of single-herb Dong Quai capsules. If anything, it argues against them.
So the fair position is this: individualised Chinese herbal treatment for menopausal symptoms is a legitimate open question that has not been settled, and in practice it is given by licensed practitioners as multi-herb formulas. A 2026 systematic review written to inform the International Menopause Society's recommendations (Maunder and colleagues, 158 studies) found moderate-certainty evidence that Chinese herbal medicine improves menopausal symptom scores, sleep and blood pressure, while noting that most of the evidence on complementary therapies was of low or very low certainty. That finding is about formulas; it does not make the solo-herb evidence positive. That remains negative.
How Oestrogenic Dong Quai Is: What the Tests Show
Two claims circulate simultaneously, which should itself be a warning sign: that Dong Quai works because it is a phytoestrogen, and that it is dangerous because it is a phytoestrogen. Both rest on the same unresolved premise.
What the evidence actually shows:
- Hirata's trial found no oestrogenic tissue effects — no change in vaginal maturation index, no change in endometrial thickness — after 24 weeks. This is the most relevant human evidence available, and it points away from clinically meaningful oestrogenicity.
- Laboratory tests point in two directions. Amato and colleagues, in Menopause in 2002, tested four herbs commonly sold for menopausal symptoms (dong quai, ginseng, black cohosh and licorice root) in human cell tests and in a mouse bioassay. Dong quai did not switch on either human oestrogen receptor (alpha or beta) in the cell test, and given by mouth to mice for 4 days it did not change uterine weight. But it made MCF-7 cells (a human breast-cancer cell line) grow 16-fold more than untreated cells, by a route the authors found to be independent of oestrogen activity. They wrote that, given the lack of proven benefit and this potential for adverse effects, use of these herbs in humans “warrants caution pending further study”. These are laboratory and animal results, not human ones.
- Dong Quai is not a classical phytoestrogen source. It is not rich in isoflavones or lignans the way soy, red clover and flaxseed are. Its characteristic constituents are phthalides, coumarins, ferulic acid and polysaccharides — chemistry with no obvious reason to bind oestrogen receptors.
Honest verdict: the oestrogenic question is unresolved, and the weight of the human evidence leans towards “not meaningfully oestrogenic”. Anyone who tells you confidently that Dong Quai is a phytoestrogen — whether to sell it or to warn you off it — is going beyond the data.
Endometrial Safety and Hormone-Sensitive Conditions
Standard advice lists breast, uterine and ovarian cancer, endometriosis and fibroids as conditions in which Dong Quai is avoided. It helps to know what that advice rests on.
It rests on precaution, not demonstration. Given that the oestrogenic question is unresolved, and given that these are conditions where an unnecessary hormonal exposure could plausibly matter, the precaution weighs a possible harm against a benefit that trials have not shown.
In people, no study has shown Dong Quai stimulating hormone-sensitive tissue: Hirata's 24-week trial found no change in endometrial thickness. In the laboratory, however, Amato's 2002 study found that dong quai made MCF-7 breast-cancer cells grow 16-fold, by a route independent of oestrogen activity. So the human evidence found no tissue effect, while the laboratory evidence gives the precaution a reason beyond theory — through a mechanism that is not the oestrogen effect usually assumed.
A separate and firmer point: bleeding after menopause is a warning sign that doctors investigate every time, whatever supplements are being taken, because it can be the first sign of cancer of the womb lining (endometrial cancer). A herb is not an accepted explanation for it.
The Bleeding Argument Against Casual Use
Even setting efficacy aside, Dong Quai carries a specific risk that is under-communicated in the menopause context. As set out in the circulation article, Z-ligustilide has demonstrated antiplatelet activity, and a published case report (Page and Lawrence, 1999) describes a more than two-fold rise in the international normalized ratio (INR, a measure of how slowly blood clots) in a 46-year-old woman on stable warfarin after 4 weeks of Dong Quai; her clotting values returned to acceptable levels a month after she stopped the herb.
This matters more, not less, at this stage of life. Women in their fifties and sixties are increasingly likely to be taking daily aspirin, an anticoagulant for atrial fibrillation, or an antiplatelet drug after a cardiac event — and increasingly likely to be scheduled for procedures where bleeding matters. Dong Quai adds a documented interaction with the most-monitored drug in the pharmacopoeia to that picture, without a demonstrated benefit for hot flushes.
What Actually Works for Hot Flushes
It would be a failure of this page to say “this does not work” and stop there. Vasomotor symptoms are genuinely miserable, they can last for years, and they are treatable. Options with trial evidence include:
- Menopausal hormone therapy remains the most effective treatment for hot flushes by a wide margin. The risk picture is far more favourable than the 2002 headlines suggested, particularly for women starting within ten years of their final period and under 60, and transdermal oestrogen carries a different venous-thrombosis profile from oral. The decision is individual, but many women were frightened away from an effective treatment by a misread of the evidence.
- Non-hormonal prescription options — certain selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (such as venlafaxine, paroxetine and escitalopram), gabapentin, oxybutynin, and clonidine — have randomised evidence for vasomotor symptoms and are useful when hormones are contraindicated or unwanted.
- Neurokinin-3 receptor antagonists such as fezolinetant are a newer non-hormonal class developed specifically for vasomotor symptoms, working on the hypothalamic thermoregulatory pathway rather than on hormones. A second drug of this family, elinzanetant (which blocks both the neurokinin-1 and neurokinin-3 receptors), was tested in two 26-week trials, OASIS 1 and 2, in about 800 women with moderate to severe hot flushes: compared with placebo it cut hot flushes by about 3 more per day at weeks 4 and 12, and it improved sleep problems and menopause-related quality of life at week 12.
- Cognitive behavioural therapy for menopausal symptoms has randomised evidence. It does not reduce flush frequency much, but it reliably reduces how bothersome they are — which is often the thing that actually affects daily life.
- Practical measures: layered clothing, a cool bedroom, reducing alcohol and identifying personal triggers, weight management, and stopping smoking.
- Other botanicals — black cohosh has the largest evidence base of any herb here. The 2026 review for the International Menopause Society rated the evidence for black cohosh on hot flushes and menopause scores as moderate certainty; the 2026 Nutrients review, by contrast, counted it with dong quai among trials that found no measurable effect, so the picture is still mixed. On the evidence it stands ahead of Dong Quai, which is a low bar.
The Bottom Line
Stated plainly:
For Dong Quai capsules taken for hot flushes, the best available evidence found no benefit. A 24-week randomised, double-blind, placebo-controlled trial in 71 postmenopausal women found no effect on hot flush frequency, no effect on vaginal maturation, and no effect on endometrial thickness. A later randomised placebo-controlled trial of the classical Dang Gui Buxue Tang formula also failed to beat placebo overall, doing better only for mild flushes. Nothing published since has overturned either result.
Dong Quai remains a genuinely important herb in Chinese medicine with real pharmacology and a long, serious history — explored in the History article. Menopause is simply not what it is good at, and it never was: that use case was created by Western marketing, not by the tradition. The options listed above have the trial evidence for hot flushes that Dong Quai lacks.
Cautions and Contraindications
- Warfarin — the single most important item. A published case report describes a more than two-fold rise in the international normalized ratio (INR, a measure of how slowly blood clots) after Dong Quai was taken for 4 weeks with stable warfarin; coumarin constituents plus antiplatelet phthalides make the mechanism doubly plausible. The same clotting concern applies in principle to apixaban, rivaroxaban, edoxaban, dabigatran, clopidogrel and daily aspirin.
- Surgery and dental procedures. Because of its antiplatelet activity, pre-surgery advice commonly lists stopping Dong Quai two weeks before surgery and dental procedures and telling the team it was taken.
- Pregnancy. Dong Quai has a traditional reputation as a uterine stimulant and no human safety data in pregnancy. This is relevant in perimenopause, where pregnancy is still possible.
- Breastfeeding. There are no safety data for breastfeeding.
- Hormone-sensitive conditions. Avoidance is conventionally advised in breast, uterine and ovarian cancer, endometriosis and fibroids. This is precautionary: evidence that Dong Quai is meaningfully oestrogenic is weak and inconsistent, although one laboratory study found it made breast-cancer cells grow by a route independent of oestrogen (Amato 2002). The question is not settled.
- Tamoxifen and aromatase inhibitors. Botanicals marketed as hormonal are a particular concern for people taking these oestrogen-blocking cancer drugs, which is why oncology teams ask about every supplement.
- Photosensitivity — state the uncertainty. Widely asserted, imperfectly demonstrated for this species. A. sinensis contains far lower furanocoumarin levels than A. archangelica, and the warning is largely extrapolated from related species. A theoretical caution at high doses, not an established effect.
- Any postmenopausal bleeding is a warning sign that doctors investigate every time; a supplement is not an accepted explanation for it.
- Heavy or erratic perimenopausal bleeding. Dong Quai's antiplatelet activity could add to this bleeding.
Key Research Papers
- Hirata JD, Swiersz LM, Zell B, Small R, Ettinger B. Does dong quai have estrogenic effects in postmenopausal women? A double-blind, placebo-controlled trial. Fertility and Sterility. 1997;68(6):981–986. — PubMed PMID: 9418683
- Haines CJ, Lam PM, Chung TK, Cheng KF, Leung PC. A randomized, double-blind, placebo-controlled study of the effect of a Chinese herbal medicine preparation (Dang Gui Buxue Tang) on menopausal symptoms in Hong Kong Chinese women. Climacteric. 2008;11(3):244–251. — PubMed PMID: 18568789
- Kupfersztain C, Rotem C, Fagot R, Kaplan B. The immediate effect of natural plant extract, Angelica sinensis and Matricaria chamomilla (Climex) for the treatment of hot flushes during menopause. Clinical and Experimental Obstetrics & Gynecology. 2003;30(4):203–206. — PubMed PMID: 14664413
- Amato P, Christophe S, Mellon PL. Estrogenic activity of herbs commonly used as remedies for menopausal symptoms. Menopause. 2002;9(2):145–150. — PubMed PMID: 11875334
- Wei WL, Zeng R, Gu CM, Qu Y, Huang LF. Angelica sinensis in China — A review of botanical profile, ethnopharmacology, phytochemistry and chemical analysis. Journal of Ethnopharmacology. 2016;190:116–141. — PubMed PMID: 27211015
- Zhang Y, Zhu Z, Li X, et al. Angelica sinensis: Botany, Traditional Uses, Phytochemistry, Pharmacology, Safety, and Applications. The American Journal of Chinese Medicine. 2026;54(4):1213–1251. — PubMed PMID: 42366516
- Page RL 2nd, Lawrence JD. Potentiation of warfarin by dong quai. Pharmacotherapy. 1999;19(7):870–876. — PubMed PMID: 10417036
- Ge B, Zhang Z, Zuo Z. Updates on the clinical evidenced herb-warfarin interactions. Evidence-Based Complementary and Alternative Medicine. 2014;2014:957362. — PubMed PMID: 24790635
- Gong AG, Li N, Lau KM, et al. Calycosin orchestrates the functions of Danggui Buxue Tang, a Chinese herbal decoction composing of Astragali Radix and Angelicae Sinensis Radix. Journal of Ethnopharmacology. 2015;168:150–157. — PubMed PMID: 25796405
- Maunder A, Mardon AK, Rao V, et al. Complementary therapies for management of menopausal symptoms: a systematic review to inform the update of the International Menopause Society recommendations on women's midlife health. Climacteric. 2026;29(2):165–209. — PubMed PMID: 41498229
- Jing G, Keane CM, Reynolds CM. The effectiveness of non-soy oral herbal supplements for menopausal symptoms: a systematic review. Nutrients. 2026;18(13):2037. — PubMed PMID: 42451042
- Pinkerton JV, Simon JA, Joffe H, Maki PM, Nappi RE, Panay N, et al. Elinzanetant for the treatment of vasomotor symptoms associated with menopause: OASIS 1 and 2 randomized clinical trials. JAMA. 2024;332(16):1343–1354. — PubMed PMID: 39172446
PubMed Topic Searches
- PubMed: Dong quai and menopause
- PubMed: Angelica sinensis and hot flushes
- PubMed: Danggui Buxue Tang menopausal symptoms
- PubMed: Phytoestrogens and vasomotor symptoms
- PubMed: Placebo response in hot-flush trials
- PubMed: Fezolinetant for vasomotor symptoms
- PubMed: CBT for menopausal hot flushes
- PubMed: Black cohosh for menopause
- PubMed: Hormone therapy and the timing hypothesis
Connections
- All Herbs
- Dong Quai (Angelica sinensis)
- Dong Quai Benefits Hub
- Dong Quai: History and Traditional Use
- Menstrual Health and Cramps
- Blood Building and Anemia
- Circulation and Cardiovascular
- Black Cohosh
- Chasteberry
- White Peony
- Astragalus
- Angelica (Angelica archangelica)
- Ferulic Acid