Dong Quai for Circulation and Cardiovascular Health
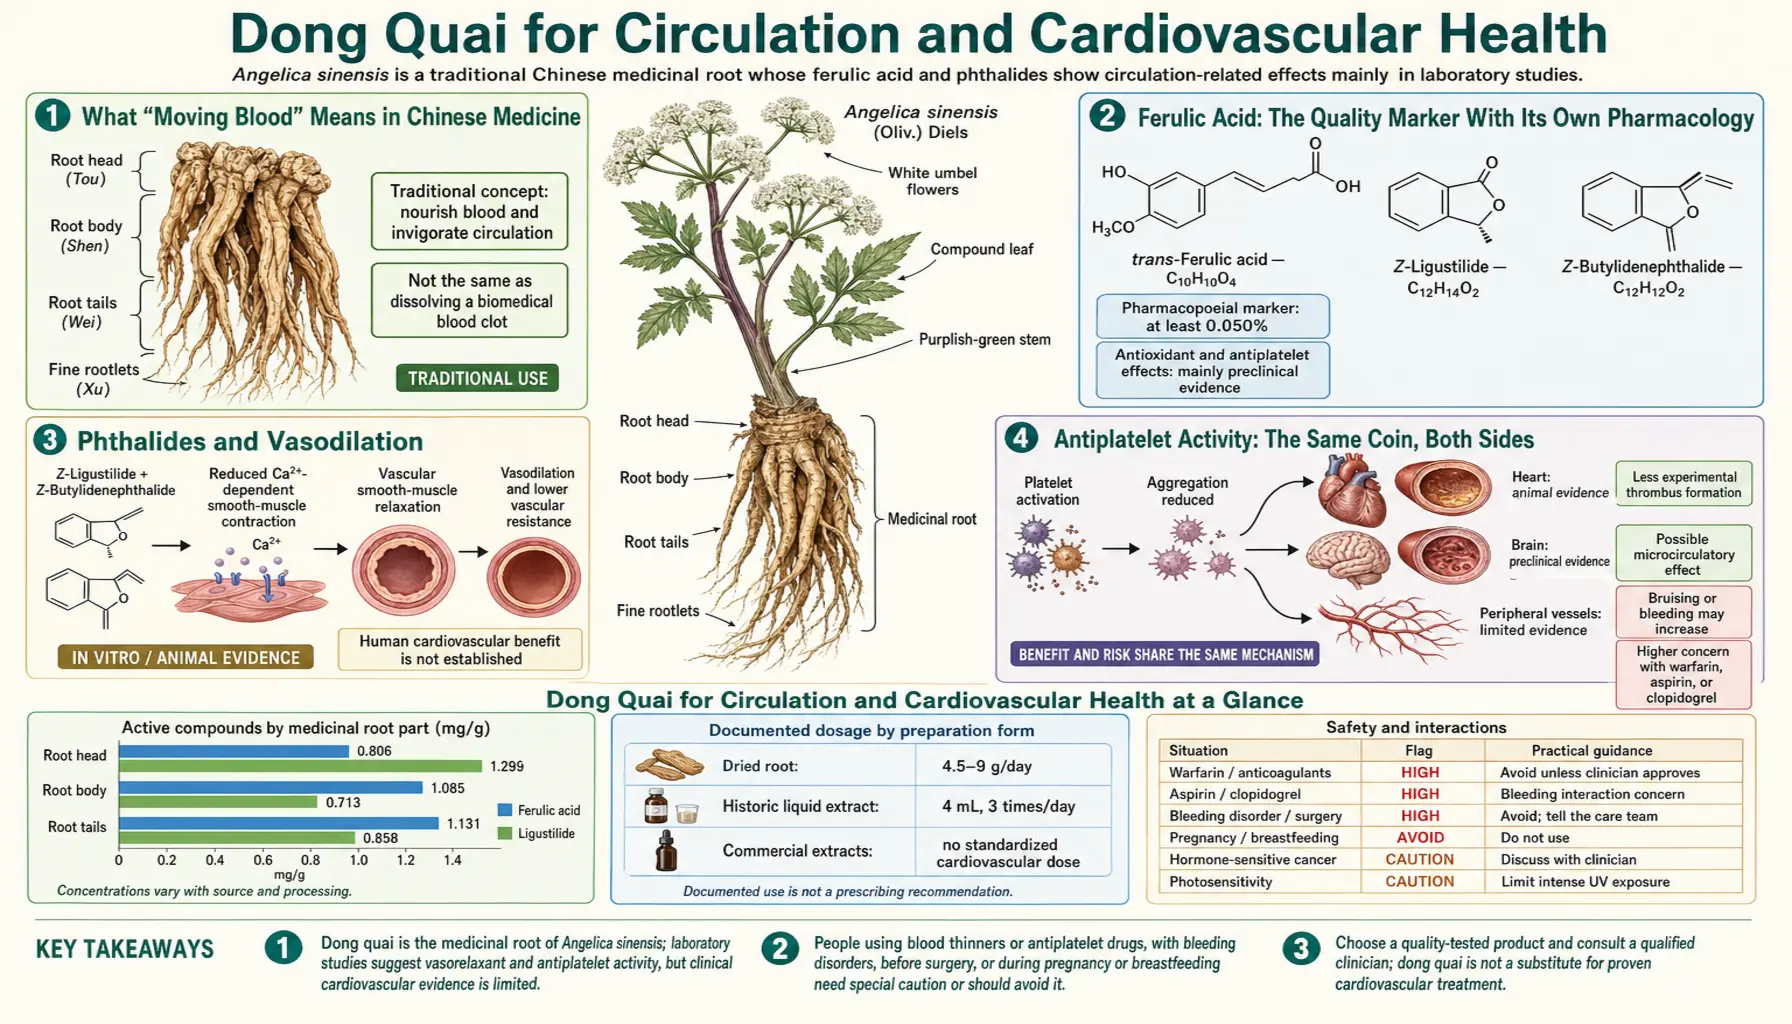
This is the area where Dong Quai's laboratory pharmacology is most convincing — the root contains compounds that genuinely relax blood vessels and genuinely inhibit platelets. It is also the area where that same pharmacology creates the herb's most serious safety problem. A herb that thins the blood is a herb that can make you bleed, and the case reports involving warfarin are not hypothetical.
Table of Contents
- What “Moving Blood” Means in Chinese Medicine
- Ferulic Acid: The Quality Marker With Its Own Pharmacology
- Phthalides and Vasodilation
- Antiplatelet Activity: The Same Coin, Both Sides
- Dang Gui Bu Xue Tang and Vascular Research
- What Human Cardiovascular Evidence Exists
- Warfarin, Surgery and Bleeding Disorders: The Documented Risks
- Forms, Doses and Quality
- What Actually Moves Cardiovascular Risk
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
What “Moving Blood” Means in Chinese Medicine
Chinese medicine describes a pattern called xue yu — blood stasis. Its signs are fixed, stabbing pain that is worse at night and worse with pressure, dark or purplish discolouration of the tongue and lips, visible spider veins, dark clotted menstrual flow, and masses or lumps. Herbs that treat it are said to “invigorate blood and dispel stasis” (huo xue hua yu).
It is worth appreciating that this is one of the places where a traditional category maps unusually well onto modern physiology. A description of fixed pain, dusky colour, clotting and mass formation is a reasonable pre-modern description of impaired perfusion and thrombosis. So when the tradition says Dang Gui “moves blood” and modern chemistry finds vasodilator and antiplatelet compounds in the root, that is a genuine convergence rather than a retrofit.
Dong Quai occupies an unusual position: it both tonifies and moves blood. The fine root tails (dang gui wei) were traditionally considered the stronger movers, the body (dang gui shen) the stronger tonic. Almost all commercial material is whole root, quan dang gui.
Ferulic Acid: The Quality Marker With Its Own Pharmacology
Ferulic acid is a hydroxycinnamic acid found throughout the plant kingdom — in rice bran, wheat bran, coffee, artichoke and, relevantly here, in Dong Quai root. The Chinese Pharmacopoeia uses it as the high-performance liquid chromatography (HPLC) quality marker for Radix Angelicae Sinensis, with a minimum content around 0.05%.
Two things need saying about that, and the second is the one usually left out.
First, ferulic acid is not pharmacologically inert. It is a capable free-radical scavenger, has been reported to inhibit platelet aggregation and thromboxane formation, and is studied for endothelial effects. In Chinese pharmacology it is often described as a contributor to the “blood-moving” actions.
Second — and this is the honest caveat — a marker compound is chosen for measurability, not for importance. Ferulic acid is stable, cheap to assay and easy to standardise against, which makes it an excellent quality control tool. It does not follow that it is the constituent doing the work, and the concentration of ferulic acid a person achieves in plasma after a decoction is far below what most cell experiments use. A product that passes on ferulic acid may still have lost nearly all of its volatile oil, which is where the phthalides live.
Phthalides and Vasodilation
The volatile oil is the more interesting fraction for circulation. Its dominant component is Z-ligustilide, accompanied by butylidenephthalide, senkyunolide A and a family of related and dimerised phthalides.
In isolated-tissue and animal work, these compounds relax vascular smooth muscle. The reported mechanisms include interference with calcium entry into smooth-muscle cells and effects on vascular tone regulation; ligustilide has also been studied for effects on cerebral blood flow and in models of ischaemic brain injury. Butylidenephthalide has a long history in Chinese pharmacology as an antianginal candidate, and phthalides as a class have attracted drug-development interest well beyond cardiology — including for neurodegenerative disease.
Two structural facts about ligustilide shape everything downstream:
- It is volatile and unstable. It oxidises, polymerises and dimerises on exposure to air, light and warmth. Stored root loses it. This is the honest explanation for why Dong Quai from a busy Chinese pharmacy and Dong Quai from a supermarket shelf behave differently.
- Its systemic exposure after oral dosing is modest and short-lived. Pharmacokinetic studies show rapid absorption and rapid elimination. The plasma concentrations achieved are not obviously in the range used in tissue-bath work.
So the fair statement is: the vasodilator pharmacology is real in the laboratory and mechanistically coherent with traditional use, and it has not been shown to produce a measurable clinical benefit in people. That gap is not a technicality — it is where the great majority of promising botanical mechanisms stop.
Antiplatelet Activity: The Same Coin, Both Sides
Platelets are the first responders of clotting. When adenosine diphosphate (ADP), collagen or thrombin activates them, they change shape, become sticky, and aggregate into a plug. Aspirin works by permanently disabling one enzyme (cyclooxygenase-1, COX-1) in that pathway; clopidogrel works by blocking the ADP receptor.
Z-ligustilide has been shown to reduce ADP-induced platelet aggregation in rats and to reduce thrombus formation in an arteriovenous shunt model; in the same rat study, at 10 or 40 mg/kg it had no significant effect on coagulation time (activated partial thromboplastin time and prothrombin time). Ferulic acid has been reported to inhibit platelet aggregation as well. Traditional practice, in its own vocabulary, has been saying the same thing for centuries: this herb moves blood and is not given to someone who is bleeding.
Here is the thing that supplement marketing consistently fails to say out loud. “Improves circulation” and “increases bleeding risk” are the same finding described twice. There is no version of this pharmacology in which the herb thins the blood usefully but not inconveniently. The circulation claim and the bleeding claim rest on identical evidence, and the bleeding side actually has human case reports behind it while the benefit side does not.
Dang Gui Bu Xue Tang and Vascular Research
Dang Gui Bu Xue Tang is the two-herb formula that pairs Dong Quai with astragalus, and it has become a favourite research model for the study of herbal combinations. It contains a famous surprise: the ratio is five parts astragalus to one part Dong Quai by weight, even though the formula is named after Dong Quai, the minor ingredient.
Modern work on the formula has looked at what that ratio actually does chemically. Co-decoction changes the extraction of constituents relative to decocting the herbs separately; the astragalus isoflavonoid calycosin has been identified as a major contributor to the decoction's measured biological activities, including in assays relevant to blood-vessel formation and endothelial function; and, strikingly, work on the formula has reported that components of the Angelica volatile oil can suppress some of the decoction's biological properties — which argues directly against the intuition that more Dang Gui would make it stronger.
Interpret it carefully. This literature is chemistry and cell biology of considerable sophistication. It tells you that traditional ratios are not arbitrary and that herb combinations are chemically more than the sum of their parts. It does not tell you that the formula improves circulation in human beings, and it hints that the vascular activity people attribute to Dong Quai may substantially belong to the astragalus sitting next to it.
What Human Cardiovascular Evidence Exists
Very little, stated without euphemism.
- There are no randomised outcome trials. Nothing showing that Dong Quai reduces heart attacks, strokes, cardiovascular death, or amputation in peripheral arterial disease.
- There are no substantial randomised trials of surrogate endpoints — blood pressure, flow-mediated dilation, walking distance in claudication, lipid profiles — that would carry weight in a cardiology setting.
- Intravenous Angelica preparations have been used in Chinese hospital practice for stroke and vascular indications, and there is a Chinese-language literature on them. Those studies generally do not meet the methodological standards applied elsewhere, they use a parenteral product with a different exposure profile, and they say nothing about a capsule bought online.
- The best-designed randomised placebo-controlled trial of Dong Quai in any indication — Hirata and colleagues, 1997 — was negative. That is a different question, but it is a useful reminder of what happens to this herb under proper methodology.
The bottom line: taking Dong Quai for the heart or the circulation rests on plausible mechanism, not on demonstrated benefit — and it carries a documented bleeding risk. The research raises the greatest concern for people already taking an antithrombotic (blood-thinning) drug.
Warfarin, Surgery and Bleeding Disorders: The Documented Risks
This section carries the most important safety information on the page.
Warfarin
There are published case reports describing a substantial rise in international normalized ratio (INR) after Dong Quai was added to previously stable warfarin therapy. The best known is a 1999 report in Pharmacotherapy: a 46-year-old woman with atrial fibrillation, stable on warfarin, had a more than 2-fold rise in prothrombin time and INR after taking dong quai alongside it for 4 weeks. No other cause for the rise was found, and her values returned to acceptable levels 1 month after she stopped the herb. Reviews of clinically evidenced herb-warfarin interactions list Dong Quai among the herbs with reported potentiation: a 2014 review describes a second case report in which INR rose to 10 when warfarin and Chinese angelica (dong quai) were taken together for a month, notes that most experimental evidence shows Chinese angelica inhibiting the enzymes CYP2C9 and CYP3A4 (CYP2C9 is the main route by which the body breaks down warfarin), and rates the interaction as “probable”.
The mechanism is plausible from two independent directions:
- Coumarin-type constituents. Warfarin is itself a coumarin derivative; the Apiaceae are rich in coumarins. Additive or pharmacokinetic effects are entirely credible.
- Antiplatelet phthalides and ferulic acid. Adding platelet inhibition on top of anticoagulation raises bleeding risk even when the international normalized ratio does not move.
Warfarin plus Dong Quai is the combination with human case reports behind it. The 2014 review states that, for safety, Chinese angelica use should be avoided unless the effects on anticoagulation can be monitored. The same theoretical concern extends to apixaban, rivaroxaban, edoxaban and dabigatran (where there is no international normalized ratio to signal a change), to clopidogrel, ticagrelor and prasugrel, and to daily low-dose aspirin.
One population study looked at the antiplatelet drugs. Using a population-based health database in Taiwan, it followed 79,463 outpatients prescribed antiplatelet drugs (such as aspirin and clopidogrel) continuously and looked at the 1,209 who were hospitalised with new bleeding in 2012 and 2013; each patient served as their own control, comparing times with and without prespecified Chinese medicines (such as Asian ginseng and dong quai). Taking the antiplatelet drugs together with any of these medicines did not significantly raise the risk of bleeding over the control periods (odds ratio 1.00, 95% confidence interval 0.51 to 1.95, and odds ratio 1.13, 95% confidence interval 0.65 to 1.97). That study looked at antiplatelet drugs, not warfarin.
A 2007 case report describes a 53-year-old woman with spontaneous subarachnoid haemorrhage (bleeding around the brain) due to the use of an herbal supplement containing red clover, dong quai and Siberian ginseng — herbs used for perimenopausal symptoms such as hot flashes, and all known to contain coumarins. Because the product combined several herbs, the 2014 warfarin review notes that it is not possible to identify which, if any, of them contributed to the haemorrhage.
Surgery and procedures
The interval commonly given for stopping Dong Quai before planned surgery, dental extraction, colonoscopy with likely biopsy, or an epidural or spinal injection is at least two weeks, and the anaesthetist and surgeon need to know it was being taken. Herbal supplements are the most commonly omitted category on pre-operative medication lists, and anaesthesia teams would far rather hear about it.
Other bleeding contexts
- Bleeding disorders — haemophilia, von Willebrand disease, thrombocytopenia, liver disease with coagulopathy. The antiplatelet activity raises a concern here.
- Peptic ulcer disease or recent gastrointestinal (GI) bleeding. The same concern applies.
- Heavy menstrual bleeding. The same concern applies — see Menstrual Health and Cramps.
- Combination with other antiplatelet botanicals — high-dose fish oil, garlic extract, ginkgo, ginger, turmeric/curcumin, feverfew and nattokinase all carry the same theoretical concern. Stacking them multiplies the uncertainty.
Forms, Doses and Quality
- Decoction is the traditional route: 6–12 g of dried root per day, almost always within a multi-herb formula. Water extraction captures both the polysaccharides and a portion of the volatile oil.
- Granule extracts of Dang Gui Bu Xue Tang or Si Wu Tang are the practical modern equivalent and what a licensed practitioner is likely to dispense. Their doses come from the product label, not from converting raw-herb grams.
- Capsules typically supply 500–600 mg of powdered root, an order of magnitude below the traditional dose. Powder degrades faster than whole root because of surface area.
- Tinctures extract the volatile oil well but leave behind the water-soluble polysaccharide fraction.
- Quality signals: the binomial Angelica sinensis on the label (not archangelica, not bare “angelica”); ferulic acid standardisation; a recent manufacture date; and a strong sweet, celery-like smell. Odourless root has lost its phthalides.
What Actually Moves Cardiovascular Risk
Because it would be dishonest to write a page about circulation and leave the reader with a herb of unproven benefit as their plan, here is where the evidence is overwhelming rather than suggestive:
- Not smoking — the single largest modifiable factor, and the one where quitting produces measurable risk reduction within a year.
- Blood pressure control.
- Low-density lipoprotein (LDL) cholesterol, addressed according to your absolute risk.
- Regular movement — and in peripheral arterial disease specifically, supervised walking-to-claudication programmes improve walking distance substantially. This is one of the few interventions that literally improves circulation in the sense people mean.
- Sleep, weight and glucose control.
- A Mediterranean-style dietary pattern, which has randomised evidence behind it.
Dong Quai is not a substitute for any of them, and no study shows it can replace a prescribed antithrombotic drug.
Cautions and Contraindications
- Warfarin — the standout item. Published case reports of markedly raised international normalized ratio (more than doubled in one report, 10 in another); one report of bleeding around the brain involved a multi-herb supplement containing dong quai. The same concern extends to all anticoagulants and antiplatelet agents, including daily aspirin.
- Surgery, dental work and interventional procedures — a stop of two weeks beforehand is the interval commonly given, and the team needs to know about it.
- Bleeding disorders, active ulcer, recent haemorrhagic stroke. The research raises a concern for these.
- Heavy menstrual bleeding. The same concern applies.
- Pregnancy. Traditional uterine-stimulant reputation and no human safety data.
- Breastfeeding. Insufficient safety data.
- Photosensitivity — report the uncertainty. Furanocoumarins cause phototoxicity, but A. sinensis contains far lower levels than A. archangelica, and the warning is largely extrapolated from related species rather than demonstrated for this one. A reasonable caution at high doses; not an established effect.
- Hormone-sensitive conditions. Conventionally advised against; the evidence that Dong Quai is meaningfully oestrogenic is weak and inconsistent. Certainty is not warranted either way.
- Chest pain, claudication, palpitations and leg swelling are symptoms that need a diagnosis, and no study shows Dong Quai treats them. New or worsening chest pain, sudden unilateral leg swelling, or sudden breathlessness are signs hospitals treat as emergencies.
Key Research Papers
- Zhang L, Du JR, Wang J, et al. Z-ligustilide extracted from Radix Angelica sinensis decreased platelet aggregation induced by ADP ex vivo and arterio-venous shunt thrombosis in vivo in rats. Yakugaku Zasshi. 2009;129(7):855–859. — PubMed PMID: 19571521
- Page RL 2nd, Lawrence JD. Potentiation of warfarin by dong quai. Pharmacotherapy. 1999;19(7):870–876. — PubMed PMID: 10417036
- Ge B, Zhang Z, Zuo Z. Updates on the clinical evidenced herb-warfarin interactions. Evidence-Based Complementary and Alternative Medicine. 2014;2014:957362. — PubMed PMID: 24790635
- Gong AG, Li N, Lau KM, et al. Calycosin orchestrates the functions of Danggui Buxue Tang, a Chinese herbal decoction composing of Astragali Radix and Angelicae Sinensis Radix. Journal of Ethnopharmacology. 2015;168:150–157. — PubMed PMID: 25796405
- Zhan JY, Zheng KY, Zhang WL, et al. Identification of Angelica oil as a suppressor for the biological properties of Danggui Buxue Tang. Journal of Ethnopharmacology. 2014;154(3):825–831. — PubMed PMID: 24837305
- Zhu FQ, Ma JY, Zhang YY, Yu Y. Research progress on mechanisms and pharmacokinetics of ligustilide in treatment of locomotor system diseases [in Chinese]. China Journal of Chinese Materia Medica. 2024;49(24):6625–6634. — PubMed PMID: 39805752
- Wei WL, Zeng R, Gu CM, Qu Y, Huang LF. Angelica sinensis in China — A review of botanical profile, ethnopharmacology, phytochemistry and chemical analysis. Journal of Ethnopharmacology. 2016;190:116–141. — PubMed PMID: 27211015
- Zhang Y, Zhu Z, Li X, et al. Angelica sinensis: Botany, Traditional Uses, Phytochemistry, Pharmacology, Safety, and Applications. The American Journal of Chinese Medicine. 2026;54(4):1213–1251. — PubMed PMID: 42366516
- Vinayagam J, Kalaivani D, Senthilkumar GP. Nature-origin phthalides for Parkinson's disease drug development. Neurochemistry International. 2026;197:106181. — PubMed PMID: 42134657
- Tsai HH, Lin HW, Tsai CL, Yam FK, Lin SS. Uncertain associations of major bleeding and concurrent use of antiplatelet agents and Chinese medications: a nested case-crossover study. Evidence-Based Complementary and Alternative Medicine. 2017;2017:9417186. — PubMed PMID: 28831288
- Friedman JA, Taylor SA, McDermott W, Alikhani P. Multifocal and recurrent subarachnoid hemorrhage due to an herbal supplement containing natural coumarins. Neurocritical Care. 2007;7(1):76–80. — PubMed PMID: 17634840
PubMed Topic Searches
- PubMed: Angelica sinensis platelet aggregation
- PubMed: Ligustilide vasodilation
- PubMed: Butylidenephthalide vascular effects
- PubMed: Ferulic acid and endothelial function
- PubMed: Angelica sinensis and warfarin
- PubMed: Herbal supplements and perioperative bleeding
- PubMed: Danggui Buxue Tang and angiogenesis
- PubMed: Supervised exercise for claudication
Connections
- All Herbs
- Dong Quai (Angelica sinensis)
- Dong Quai Benefits Hub
- Dong Quai: History and Traditional Use
- Menstrual Health and Cramps
- Blood Building and Anemia
- Menopause: Evidence Review
- Ferulic Acid
- Astragalus
- Angelica (Angelica archangelica)
- White Peony
- Black Cohosh
- Chasteberry