White Peony Root and Liver Protection
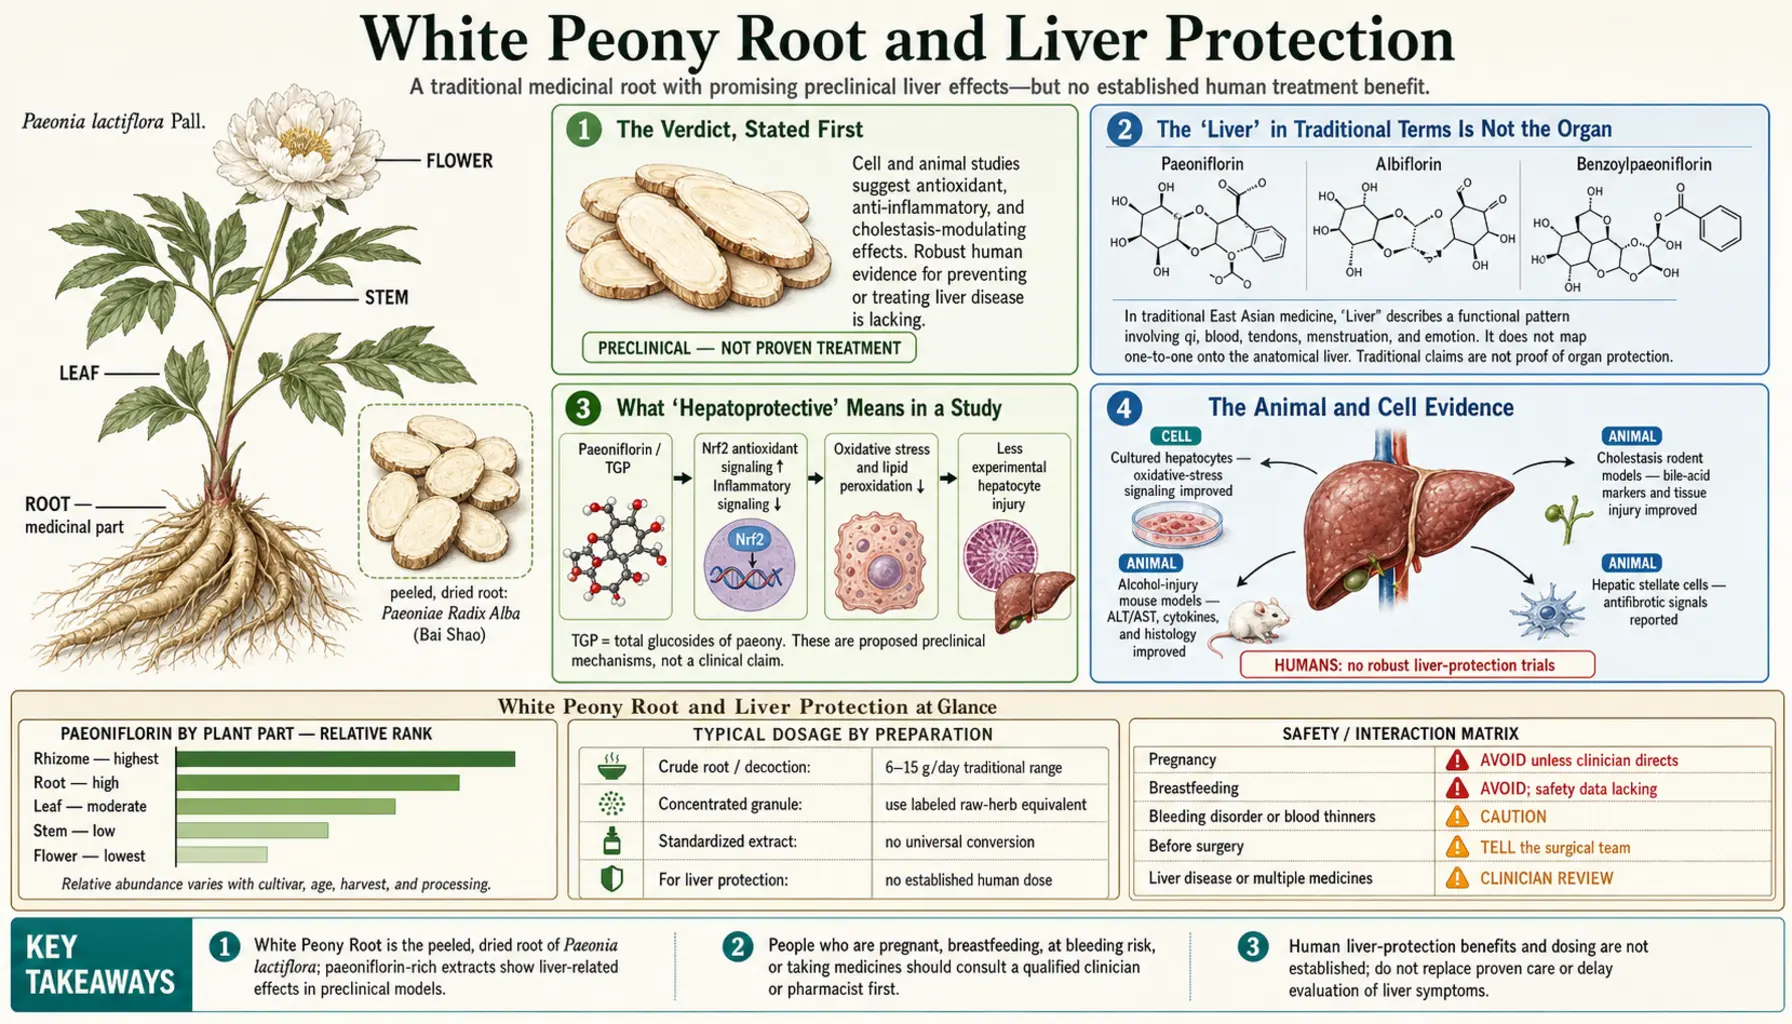
“Liver support” is one of the most heavily marketed claims in the supplement world, and white peony root — Radix Paeoniae Alba, Bai Shao, the boiled and peeled root of Paeonia lactiflora — gets pulled into it regularly. There is a real scientific literature behind the claim. It is also, honestly, much weaker than the evidence for peony extract in rheumatoid arthritis, and this page starts by saying so rather than burying it.
What follows is the actual state of play: what the animal and cell studies show, what the one clinically interesting human observation is, why oral bioavailability complicates the whole story, and what genuinely protects a liver.
Table of Contents
- The Verdict, Stated First
- The “Liver” in Traditional Terms Is Not the Organ
- What “Hepatoprotective” Means in a Study
- The Animal and Cell Evidence
- The Paeoniflorin Mechanism
- The Human Data: TGP and Drug-Related Liver Enzymes
- The Bioavailability Problem
- The Mirror-Image Risk: Herbs That Damage Livers
- What Actually Protects a Liver
- Forms, Doses and Label Reading
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
The Verdict, Stated First
White peony root and its purified constituent paeoniflorin show consistent protective effects against experimental liver injury in rodents and in cultured liver cells. That body of work is substantial, reproducible across several different injury models, and mechanistically coherent.
It is also almost entirely preclinical. There is no large, well-controlled human trial showing that taking peony root or peony extract improves the course of any liver disease. The one human observation with genuine clinical interest is indirect: within the rheumatoid arthritis literature, adding Total Glucosides of Paeony to methotrexate has repeatedly been associated with fewer liver-enzyme abnormalities. That is a real and repeated finding, but it comes from trials designed to study arthritis, not liver disease, and mostly from a single country.
So: a promising laboratory story, an interesting side observation in arthritis patients, and nothing that would justify treating liver disease with a peony capsule. Abnormal liver enzymes have a cause, and finding that cause is what opens the way to treating it.
The “Liver” in Traditional Terms Is Not the Organ
A large part of the confusion here is a translation problem that nobody warned you about.
Classical descriptions of white peony root say it “softens the liver” and is used in formulas for “liver qi stagnation” Xiao Yao San and Si Ni San being the standard examples. Read in English, that sounds like a hepatology claim. It is not. In classical Chinese medicine the 肝 (gan) system is a functional category covering the smooth flow of emotion, tension in muscles and tendons, menstrual regulation, and eye symptoms. Its clinical picture — irritability, tightness, sighing, premenstrual tension — does not correspond to hepatitis, fatty liver or cirrhosis.
So when a marketing page cites “traditionally used to support the liver,” it is quoting a claim about a functional system, not about the organ that filters your blood. This is not a criticism of the tradition; it is a warning about the translation. Nothing in the classical literature amounts to evidence for treating hepatitis or fatty liver disease with peony.
What “Hepatoprotective” Means in a Study
Almost every hepatoprotection study follows the same design, and knowing it lets you read any of them:
- Take a rodent, or a dish of liver cells.
- Give it a known liver poison — carbon tetrachloride, high-dose paracetamol, D-galactosamine with bacterial endotoxin, concanavalin A (an immune-mediated hepatitis model), alcohol, or a fat-loaded diet.
- Give some animals the test compound, usually before or alongside the poison.
- Measure liver-enzyme leakage into blood (alanine aminotransferase (ALT) and aspartate aminotransferase (AST)), plus markers of oxidative stress and inflammation, plus how the liver looks under a microscope.
Three limitations are structural, and they apply to every herb marketed as liver-protective, not just this one:
- Pre-treatment is not treatment. Most of these studies give the compound before the injury. That models prevention of a single acute insult, not repair of years of accumulated damage.
- The doses are high and often injected. Rodent doses per kilogram frequently translate to human doses nobody takes, and intraperitoneal injection bypasses the gut entirely — which matters enormously for a poorly absorbed compound.
- The models are acute and artificial. Carbon tetrachloride poisoning is not fatty liver disease, and a mouse given endotoxin is not a person with hepatitis B.
The Animal and Cell Evidence
With those caveats in place, here is what the literature reports for peony and paeoniflorin. The consistency across different injury models is the genuinely notable part.
| Model | What it represents | Reported effect |
|---|---|---|
| Carbon tetrachloride | Free-radical chemical injury; the classic fibrosis model | Lower alanine aminotransferase/aspartate aminotransferase, less necrosis, less fibrosis on repeated dosing |
| Paracetamol (acetaminophen) overdose | Glutathione-depleting drug injury | Reduced injury markers and oxidative stress |
| D-galactosamine + endotoxin | Inflammation-driven hepatitis | Reduced inflammatory cytokines and liver damage |
| Concanavalin A | T-cell-mediated, immune hepatitis — the closest model to autoimmune hepatitis | Reduced immune-mediated injury; fits paeoniflorin’s immunomodulatory profile |
| Alcohol feeding | Alcohol-related liver injury | Reduced fat accumulation and injury markers |
| High-fat diet | Fatty liver disease (metabolic dysfunction-associated steatotic liver disease (MASLD)/non-alcoholic fatty liver disease (NAFLD)) | Less hepatic fat, improved insulin-related measures |
| Bile duct ligation / fibrosis models | Scarring from chronic obstruction | Reduced fibrosis markers and stellate-cell activation |
The immune-hepatitis result is the most interesting one, because it is the model that best matches what paeoniflorin appears to do elsewhere. This is not a compound that looks like a general antioxidant; it looks like an immune modulator that happens to help most in injuries with a strong immune component.
The Paeoniflorin Mechanism
Four threads run through the mechanistic literature. All rest on cell and rodent work.
1. Damping inflammatory signalling. Paeoniflorin reduces activation of NF-κB, the master switch that turns on inflammatory genes, and lowers production of tumor necrosis factor-α, interleukin-1 beta (IL-1β) and interleukin-6 (IL-6). In the liver, much of the damage in hepatitis is done not by the original insult but by the immune response to it — the fire brigade breaking down the door. Turning down that response reduces collateral damage.
2. Supporting antioxidant defences. Reported effects include preservation of glutathione, the liver’s primary detoxification thiol, and increased activity of superoxide dismutase and catalase. Several studies implicate the Nrf2 pathway, the cell’s own antioxidant-gene programme — meaning the effect is less “peony mops up free radicals” and more “peony tells the cell to make its own mops.”
3. Reducing programmed cell death. Paeoniflorin has been reported to reduce hepatocyte apoptosis in injury models, with effects on the usual apoptotic machinery.
4. Anti-fibrotic effects. Liver scarring is driven by hepatic stellate cells, which transform from quiet fat-storing cells into collagen factories under TGF-β signalling. Paeoniflorin has been reported to interfere with stellate-cell activation and TGF-β/Smad signalling in animal fibrosis models. If this held in humans it would be genuinely important, because there is no approved anti-fibrotic drug for most liver disease. It has not been shown to hold in humans.
The Human Data: TGP and Drug-Related Liver Enzymes
The one human observation worth taking seriously comes from a completely different field. In the rheumatoid arthritis literature — where Total Glucosides of Paeony (TGP), a standardized extract of roughly 40 percent or more paeoniflorin, is an approved Chinese prescription drug at 600 mg two to three times daily — multiple trials and pooled analyses have reported that patients taking TGP alongside methotrexate, usually combined with leflunomide, had fewer liver-enzyme elevations than those on the same drugs without TGP.
Methotrexate raising alanine aminotransferase and aspartate aminotransferase is a routine clinical nuisance that causes dose reductions and treatment interruptions, so a genuine protective effect would matter. The signal has been reported repeatedly, and it fits the animal data.
The numbers behind it:
- A 2015 randomized trial in 268 people with active rheumatoid arthritis added TGP (1.8 g a day) to methotrexate (10 mg a week) plus leflunomide (20 mg a day) for 12 weeks and compared it with the two drugs alone. Abnormal liver function appeared in 11.38% of the TGP group versus 23.26% of the comparison group (P=0.013), and liver enzymes (ALT/AST) above three times the upper limit of normal in 1.63% versus 7.75% (P=0.022). Other side effects were similar in both groups except diarrhoea.
- A 2021 safety meta-analysis pooled 39 studies (randomized trials and cohort studies) with 3,680 people with rheumatoid arthritis. Liver side effects were less common when TGP was added (risk ratio 0.31), and so was a low white-cell count, leukopenia (risk ratio 0.41). But in the liver results, the difference was statistically significant only in the groups that included leflunomide — TGP plus leflunomide, and TGP plus methotrexate and leflunomide — not in TGP plus methotrexate alone.
Then note what it is not:
- These were arthritis trials. Liver enzymes were a safety measure, not the primary endpoint, and safety endpoints in unblinded trials are collected less rigorously than primary ones.
- Nobody has shown a clinical liver outcome — fewer cases of significant liver injury, less fibrosis on biopsy, better long-term liver health. A smaller number on a blood test is not the same as a healthier liver.
- The trials are overwhelmingly Chinese-language, single-country, and of moderate methodological quality, with the same publication-bias concerns that affect the whole TGP literature.
- It says nothing about people who are not taking a drug that strains the liver.
A second drug, not methotrexate, shows the same signal. In a 2017 double-blind, placebo-controlled trial of 108 people with moderate-to-severe plaque psoriasis, all taking the psoriasis drug acitretin for 12 weeks, the liver enzyme ALT rose in 6.25% of those also given TGP versus 20.4% of those given placebo. It is still a blood-test result from a trial designed for skin disease, not a liver outcome.
Beyond this, there are Chinese reports of TGP or peony-containing formulas used in chronic hepatitis and other liver conditions, but the trials are small, heterogeneous, and generally use multi-herb products in which peony is one ingredient among many. That is not a foundation for a recommendation.
The Bioavailability Problem
Here is the technical wrinkle that most “peony protects the liver” articles skip.
Paeoniflorin is a glucoside — a molecule with a sugar attached — and it is large and water-loving. Animal pharmacokinetic studies consistently report low oral bioavailability. In a 1995 rat study, only 3.2–3.8% of an oral dose of paeoniflorin (0.5–5 mg/kg) reached the bloodstream compared with the same dose injected into a vein, and after an oral dose of 5 mg/kg only 1.0% appeared unchanged in the urine within 48 hours. Most of an oral dose does not reach the bloodstream intact.
Instead, much of it is worked on by gut bacteria, which cleave the sugar and generate different metabolites that are absorbed in its place. So the compound circulating in your blood after a cup of peony decoction is not entirely the compound that was dropped onto the liver cells in a dish. Two consequences follow:
- The gap between a cell-culture result and a human result is wider than usual for this compound — wide enough that a strong laboratory effect can vanish entirely in a person.
- Individual variation may be large, because gut microbial composition differs between people and is altered by antibiotics and diet. Two people taking the same capsule may not be getting the same exposure.
This does not mean oral peony does nothing — the arthritis trials suggest something reaches its target, whether as paeoniflorin or as a metabolite. It does mean that any argument of the form “paeoniflorin protects liver cells in vitro, therefore peony capsules protect your liver” skips over the step where most of the compound never arrives.
The Mirror-Image Risk: Herbs That Damage Livers
An honest liver page has to say the uncomfortable part. Herbal and dietary supplements are now a leading cause of drug-induced liver injury in several countries, and the proportion of severe cases attributed to supplements has been rising in registry data. A 2017 review from a U.S. National Institutes of Health research symposium reported that supplement-induced liver injury now accounts for 20% of cases of liver toxicity in the United States in research data. The liver is the organ that processes everything you swallow, which makes it the organ most exposed to whatever is actually in the bottle.
White peony root itself is not a recognised common cause of liver injury, and it has a reassuring traditional and clinical safety record. But the risk in practice is rarely the named herb:
- Multi-ingredient products. A “liver support” blend may contain a dozen botanicals, and any of them could be the problem. Attribution becomes impossible.
- Adulteration and substitution. Peony species are confused in trade — Bai Shao, Chi Shao and tree peony bark are different drugs — and botanical supply chains have documented problems with misidentification and undeclared pharmaceutical adulterants.
- Contamination. Heavy metals and pesticide residues have been found in some imported herbal products.
- Interactions. A herb taken to “protect the liver” can interfere with a drug’s metabolism and cause harm that way.
The same 2017 review found that most supplement-related liver injury in the United States comes from multi-ingredient products, and that the ingredient responsible is usually unknown or can only be suspected. Each added product is one more possible cause to sort through when liver enzymes are already raised. The U.S. National Institutes of Health (NIH) LiverTox database is the reference clinicians use for this.
What Actually Protects a Liver
Unglamorous and effective, in rough order of impact:
- Alcohol reduction. Nothing on any supplement shelf competes with this for anyone whose intake is above low-risk levels.
- Weight and metabolic health. Fatty liver disease (metabolic dysfunction-associated steatotic liver disease/non-alcoholic fatty liver disease) is the most common liver disease in most countries, and modest sustained weight loss — on the order of 7–10 percent of body weight — can reduce liver fat and inflammation. This is one of the few interventions with genuine biopsy-confirmed evidence: in a 2015 study of 293 people with biopsy-proven non-alcoholic steatohepatitis (NASH) on a 52-week lifestyle programme, everyone who lost 10% or more of their body weight had a lower disease-activity score on the repeat biopsy, 90% had resolution of NASH and 45% had regression of fibrosis.
- Hepatitis B and C. Hepatitis B vaccination prevents it; hepatitis C is now curable in most people with a short course of direct-acting antivirals. Both are massively underdiagnosed, and a blood test is how either is found — information no herb can provide.
- Paracetamol dosing. Staying within the maximum daily dose, and being aware that it is hidden inside combination cold and painkiller products, prevents a leading cause of acute liver failure.
- Medication review. Several common drugs affect liver enzymes; a pharmacist review is free and useful.
- Coffee. A genuinely interesting one: large observational studies consistently associate regular coffee consumption with lower rates of liver fibrosis, cirrhosis and liver cancer. A 2016 meta-analysis of nine studies (432,133 participants) found that each extra two cups of coffee a day was associated with a relative risk of cirrhosis of 0.56. Observational data cannot prove causation, but the consistency is striking and the intervention is harmless for most people.
- Investigating abnormal enzymes rather than supplementing over them. Raised alanine aminotransferase has a cause, and identifying that cause is what opens the way to treating it.
Forms, Doses and Label Reading
Each kind of peony product corresponds to a different piece of evidence — or to none.
| Product | Paeoniflorin content | Evidence in a liver context |
|---|---|---|
| Total Glucosides of Paeony (TGP) | ≈40%+; prescription drug in China | The only product with human data — and only as fewer methotrexate-related enzyme rises in arthritis patients |
| “White peony root” capsules | ≈1.6% (pharmacopeial minimum), often unstated | None. Roughly a twenty-fifth the concentration of TGP |
| Traditional decoction, 6–15 g/day in a formula | Crude root | Traditional use only, and the traditional “liver” is not the organ |
| Multi-herb “liver support” blends | Usually undisclosed | None for peony specifically; adds attribution and interaction risk |
The label details that let a product be matched to a study are: the species Paeonia lactiflora Pall.; the part and processing (root, peeled — Bai Shao / Radix Paeoniae Alba); a stated paeoniflorin percentage and milligram amount per dose; the phrase “total glucosides of paeony” if that is what is claimed; disclosed licorice content; and third-party testing with a certificate of analysis. A product that names no marker compound cannot be compared with any study, and “10:1 extract” is a manufacturing ratio, not a dose.
Cautions and Contraindications
- Existing liver disease: this is the population with the least margin for an unexpected reaction, and the one where supplement-related injury is hardest to distinguish from disease progression.
- Abnormal liver enzymes: an unexplained raised alanine aminotransferase has a cause. Supplementing over it delays diagnosis of treatable conditions such as hepatitis C, haemochromatosis, autoimmune hepatitis and Wilson disease.
- Methotrexate and other disease-modifying antirheumatic drugs (DMARDs): the enzyme-sparing trials, such as the 2015 trial with methotrexate and leflunomide, added TGP to the prescribed drugs rather than replacing them, and tracked liver function throughout the 12 weeks.
- Licorice-containing peony formulas: a particular concern in cirrhosis. Licorice causes sodium and water retention and potassium loss through pseudoaldosteronism, which worsens the fluid build-up in the abdomen (ascites) that cirrhosis already causes. See the cramps article for the full mechanism.
- Pregnancy and breastfeeding: the safety of concentrated extracts has not been established.
- Anticoagulants and antiplatelets: peony preparations have reported platelet effects, and people with liver disease are already prone to bleeding.
- Surgery: herbs with reported platelet effects, peony among them, are commonly stopped at least two weeks before an operation.
- Gastrointestinal effects: loose stools are the commonest adverse effect of concentrated peony preparations. The frequently quoted “one in ten” rate could not be traced to a verifiable source; pooled rheumatoid-arthritis safety data found no excess of gastrointestinal effects when TGP was added to conventional drugs, while add-on trials in other conditions did report more diarrhoea than control.
- Warning signs: yellowing of the eyes or skin, dark urine, pale stools, persistent right-upper-abdominal pain, unusual bruising, or confusion are signs of liver injury that hospitals treat as urgent.
Key Research Papers
Every numbered identifier below was checked live against NCBI E-utilities — author, title, journal and year all had to match before a PMID was printed. Where an identifier could not be confirmed that way, the entry keeps a PubMed topic search instead of a possibly incorrect number.
- Hepatoprotective effects of paeoniflorin in experimental liver injury — the core preclinical literature. PubMed search.
- Paeoniflorin in concanavalin A-induced immune-mediated hepatitis. PubMed search.
- Paeoniflorin, hepatic stellate cells and TGF-β/Smad signalling in liver fibrosis. PubMed search.
- Paeoniflorin, Nrf2 signalling and oxidative stress in the liver. PubMed search.
- Paeoniflorin in non-alcoholic fatty liver disease and high-fat-diet models. PubMed search.
- Xiang N, Li XM, Zhang MJ, et al. Total glucosides of paeony can reduce the hepatotoxicity caused by methotrexate and leflunomide combination treatment of active rheumatoid arthritis. International Immunopharmacology. 2015;28(1):802–807. — PubMed PMID: 26292180
- Zhou YX, Gong XH, Zhang H, Peng C. A review on the pharmacokinetics of paeoniflorin and its anti-inflammatory and immunomodulatory effects. Biomedicine & Pharmacotherapy. 2020;130:110505. — PubMed PMID: 32682112
- Intestinal bacterial metabolism of paeoniflorin and its metabolites. PubMed search.
- Navarro VJ, Khan I, Björnsson E, Seeff LB, Serrano J, Hoofnagle JH. Liver injury from herbal and dietary supplements. Hepatology. 2017;65(1):363–373. — PubMed PMID: 27677775
- Zhang W, Dai SM. Mechanisms involved in the therapeutic effects of Paeonia lactiflora Pallas in rheumatoid arthritis. International Immunopharmacology. 2012;14(1):27–31. — PubMed PMID: 22705050
- Kennedy OJ, Roderick P, Buchanan R, Fallowfield JA, Hayes PC, Parkes J. Systematic review with meta-analysis: coffee consumption and the risk of cirrhosis. Alimentary Pharmacology & Therapeutics. 2016;43(5):562–574. — PubMed PMID: 26806124
- Liu B, Meng X, Ma Y, et al. Clinical safety of total glucosides of paeony adjuvant therapy for rheumatoid arthritis treatment: a systematic review and meta-analysis. BMC Complementary Medicine and Therapies. 2021;21(1):102. — PubMed PMID: 33771151
- Yu C, Fan X, Li Z, Liu X, Wang G. Efficacy and safety of total glucosides of paeony combined with acitretin in the treatment of moderate-to-severe plaque psoriasis: a double-blind, randomised, placebo-controlled trial. European Journal of Dermatology. 2017;27(2):150–154. — PubMed PMID: 28400341
- Takeda S, Isono T, Wakui Y, et al. Absorption and excretion of paeoniflorin in rats. Journal of Pharmacy and Pharmacology. 1995;47(12A):1036–1040. — PubMed PMID: 8932691
- Vilar-Gomez E, Martinez-Perez Y, Calzadilla-Bertot L, et al. Weight loss through lifestyle modification significantly reduces features of nonalcoholic steatohepatitis. Gastroenterology. 2015;149(2):367–378.e5. — PubMed PMID: 25865049
PubMed Topic Searches
- PubMed: Paeonia lactiflora and liver
- PubMed: Paeoniflorin and NF-κB
- PubMed: TGP and hepatoprotection
- PubMed: Anti-fibrotic natural compounds
- PubMed: Supplement-induced liver injury
- PubMed: Weight loss and liver histology in MASLD
- PubMed: Hepatitis C direct-acting antivirals
- PubMed: Paracetamol hepatotoxicity
- PubMed: Coffee and liver fibrosis, cirrhosis and liver cancer
Connections
- All Herbs
- White Peony Root (Bai Shao)
- White Peony Root Benefits — hub
- White Peony Root: History and Traditional Use
- Rheumatoid Arthritis and Autoimmunity — where the human data lives
- Licorice — why it is a poor choice in cirrhosis
- Dong Quai
- Codonopsis