White Peony Root for Rheumatoid Arthritis and Autoimmunity
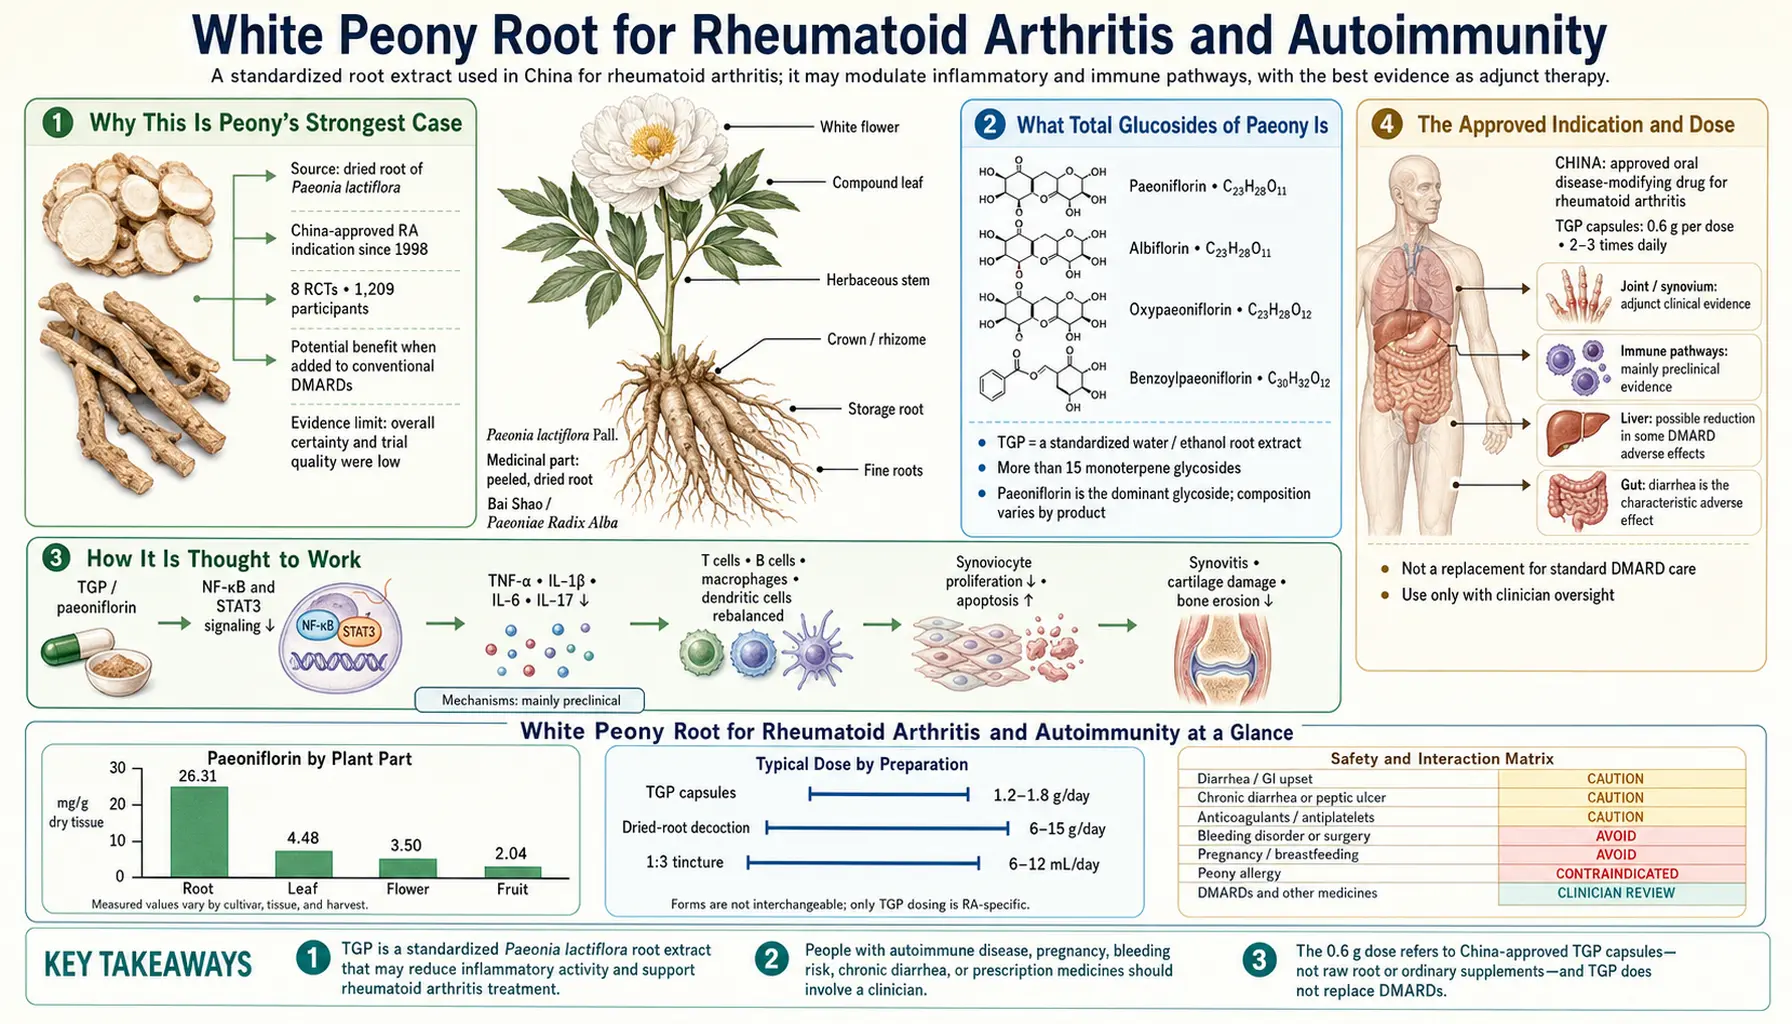
Of everything written about white peony root — Radix Paeoniae Alba, the boiled and peeled root of Paeonia lactiflora — this is the part with real clinical substance behind it. Not because the crude herb was tested, but because a standardized extract of it, Total Glucosides of Paeony (TGP), became a licensed prescription drug in China in 1998 and has since been through dozens of randomized trials in rheumatoid arthritis.
That makes peony unusual among herbs. It also creates a trap, because the drug and the supplement share a name in casual conversation but are not the same product at all. This article walks through what TGP is, what the trials actually found, where the evidence is weak, and what you can and cannot conclude if you are holding a bottle of peony capsules.
Table of Contents
- Why This Is Peony’s Strongest Case
- What Total Glucosides of Paeony Is
- How It Is Thought to Work
- The Approved Indication and Dose
- What the Trials and Meta-Analyses Report
- TGP as a Methotrexate-Sparing Add-On
- The Honest Limitations
- Beyond Rheumatoid Arthritis: Sjögren’s, Lupus, Lichen Planus, Psoriasis
- Side Effects: The Diarrhoea Problem
- What a Peony Label Does and Does Not Tell You
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Why This Is Peony’s Strongest Case
Most herbal claims rest on one of three foundations: centuries of traditional use, a pile of cell-culture experiments, or a couple of small trials with soft endpoints. White peony root in rheumatoid arthritis rests on something sturdier — a purified extract with a defined marker compound, a fixed dose, a regulatory approval, and a trial literature large enough that people have been able to pool it into systematic reviews.
That does not make it a proven equal of modern disease-modifying antirheumatic drugs. It means the question “does this do anything?” has been asked in a testable form, repeatedly, and the answers have generally leaned positive. In herbal medicine that is a genuinely high bar, and peony clears it. The rest of this article is about how high the bar actually was.
What Total Glucosides of Paeony Is
TGP is not a tea, a tincture, or a milled root powder. It is a chemically defined extract fraction, produced by extracting Paeonia lactiflora root and then enriching the monoterpene glucoside fraction until paeoniflorin makes up roughly 40 percent or more of the material. Other glucosides — albiflorin, oxypaeoniflorin, benzoylpaeoniflorin — make up much of the remainder.
Sources disagree on the exact share. A 2020 review by Zhang and Wei states that paeoniflorin accounts for more than 40 percent of TGP, while a 2011 review by He and Dai calls paeoniflorin the most abundant component of TGP, at more than 90 percent. The figures below use the lower, 40 percent figure.
Compare that with the crude drug. The Chinese Pharmacopoeia requires white peony root to contain at least about 1.6 percent paeoniflorin. TGP is therefore something like a twenty-five-fold concentration of the active fraction, delivered in a capsule with a stated milligram content.
| Crude white peony root | Total Glucosides of Paeony (TGP) | |
|---|---|---|
| Regulatory status in China | Herbal drug in the pharmacopoeia | Approved prescription medicine since 1998 |
| How it is sold | — | Total glucosides of paeony capsules, branded and generic |
| Paeoniflorin content | ≈1.6% minimum | ≈40%+ |
| Typical unit | Sliced dried root, 6–15 g/day in decoction | 300 mg capsule |
| Typical daily dose studied | Not standardized | 1,200–1,800 mg/day |
| Used alone? | Almost never — a formula herb | Yes, as a single agent or add-on |
The important consequence: every clinical result described below belongs to TGP. If you read a supplement label that says “white peony root extract, 500 mg” with no paeoniflorin percentage, you have no basis for assuming any of it applies.
How It Is Thought to Work
Rheumatoid arthritis is an autoimmune disease in which immune cells that should be patrolling for infection instead take up residence in the synovium — the thin membrane lining a joint. The membrane thickens into an invasive tissue called pannus, which chews into cartilage and bone. Driving that process is a self-sustaining loop of pro-inflammatory signalling molecules, chiefly tumour necrosis factor alpha (tumor necrosis factor-α), interleukin-1 (IL-1) and interleukin-6 (IL-6).
Modern biologic drugs interrupt that loop by blocking one messenger with surgical precision — an anti-TNF antibody is a key cut to exactly one wire. Paeoniflorin behaves differently. In laboratory and animal work it looks like a broad, gentle damper rather than a switch:
- It reduces production of tumor necrosis factor-α, interleukin-1β and interleukin-6 by activated immune cells, rather than neutralising the molecules after release.
- It dampens NF-κB signalling, the master transcription switch that turns on most inflammatory genes.
- It is bidirectional (“immunoregulatory”) — in animal models it suppresses over-active immune responses but does not appear to flatten normal immunity the way a strong immunosuppressant does. This is the most-cited reason TGP is described in China as an immunomodulator rather than an immunosuppressant.
- Its pain-relieving effect appears to run partly through the adenosine A1 receptor. This is worth stating precisely, because it is often mis-stated: in the review literature the A1 receptor is linked to peony’s analgesia in animal pain models, not to the immune effects listed above.
- It reduces synovial fibroblast proliferation and migration in cell models — relevant to the pannus that does the joint damage.
A caveat applies here. Nearly all of the above is cell-culture and rodent work, chiefly collagen-induced and adjuvant arthritis models in rats and mice. It explains why a benefit is plausible. It does not by itself demonstrate benefit in humans, and a mechanism has never once cured anybody.
The Approved Indication and Dose
TGP was approved in China in 1998 for rheumatoid arthritis, positioned as a slow-acting anti-rheumatic agent. The regimen used in most of the trial literature and in routine Chinese practice is:
- 600 mg (two 300 mg capsules) two to three times daily, with meals — 1,200 mg/day rising to 1,800 mg/day.
- Often started at a lower dose and increased over one to two weeks, specifically to limit the loose stools that are its main side effect.
- Given for at least 12 weeks, and usually 24 weeks or more, before its effect is judged. Like methotrexate and unlike an anti-inflammatory painkiller, it is not expected to work in days.
- Most commonly used alongside a conventional disease-modifying drug, not instead of one.
Outside China, TGP is not an approved medicine. In the United States, the United Kingdom, the European Union, Canada and Australia it has no drug licence, and any product you can buy is being sold as a food supplement under supplement rules — which do not require it to contain what a trial used.
What the Trials and Meta-Analyses Report
There is a large body of randomized controlled trials of TGP in rheumatoid arthritis, overwhelmingly conducted and published in China. Several systematic reviews and meta-analyses have pooled them. The consistent direction of the findings is as follows.
Symptom and function measures
Pooled analyses generally report improvement in the standard rheumatoid arthritis (RA) outcome set: fewer swollen joints and tender joints, shorter morning stiffness, better grip strength, and improved composite scores. Where trials report ACR20 (the conventional threshold of a 20 percent improvement across a defined set of measures), TGP arms tend to reach it more often than control arms. The effect sizes described are typically modest to moderate — the language of reviews is “improved,” not “remission.”
Behind that summary, a 2017 systematic review by Luo and colleagues found only 8 trials, enrolling 1,209 people with active rheumatoid arthritis, that met its criteria. On top of conventional disease-modifying antirheumatic drugs (DMARDs), TGP was linked to higher ACR20, ACR50 and ACR70 response rates and fewer adverse effects than no add-on, but the review rated both the methods of the trials and the quality of the evidence as limited.
Laboratory markers
This is where TGP looks most interesting, because these numbers are harder to talk yourself into. Reviews commonly report reductions in erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP), the two routine blood measures of systemic inflammation, and in rheumatoid factor (RF). A patient can convince themselves their joints feel better; an erythrocyte sedimentation rate does not have opinions. Consistent movement in these markers across many trials is a meaningful signal, even when the trials themselves are imperfect.
A 2019 meta-analysis by Huang and colleagues of 8 randomized trials gives the size of that movement when TGP is added to methotrexate plus leflunomide: compared with the two drugs alone, the erythrocyte sedimentation rate was lower by 2.80 mm/h on average, C-reactive protein by 4.17 mg/L and rheumatoid factor by 12.09 IU/mL, and adverse events — liver toxicity in particular — were less frequent in the TGP groups (risk ratio 0.55).
Safety comparisons
A recurring finding is that adding TGP to conventional therapy is associated with fewer of the adverse events that force dose reductions. The largest safety pooling — 39 studies, randomized trials and cohort studies together, with 3,680 participants — found significantly fewer hepatic adverse effects (risk ratio 0.31) and less leukopenia (risk ratio 0.41) in the TGP arms, while gastrointestinal adverse effects were no more common than in the comparison arms (risk ratio 1.05, not significant). That is the observation that produced the methotrexate-sparing hypothesis discussed next.
The largest pooling across five kinds of arthritis
A 2023 meta-analysis by Yang and colleagues gathered 63 randomized trials with 5,293 participants across five kinds of inflammatory arthritis: rheumatoid arthritis, ankylosing spondylitis, osteoarthritis, juvenile idiopathic arthritis and psoriatic arthritis. For rheumatoid arthritis it reported that TGP may improve the Disease Activity Score in 28 joints (DAS28) and lower the erythrocyte sedimentation rate, C-reactive protein, rheumatoid factor, tumor necrosis factor-α and interleukin-6. Across the trials, adding TGP did not increase adverse events. The authors describe the trials as low in quality and small in number, and call for large multi-centre trials to confirm the results.
One honest framing: the pooled picture is of a drug that is mild but real. Nobody in this literature is claiming TGP outperforms methotrexate, and no serious source suggests replacing a biologic with it.
TGP as a Methotrexate-Sparing Add-On
Methotrexate is the anchor drug of rheumatoid arthritis treatment worldwide. It works, and it is cheap. Its problem is tolerability: nausea, mouth ulcers, fatigue on dosing day, raised liver enzymes, and drops in white blood cell count. Some people cannot stay on an effective dose because of those effects.
The most clinically interesting claim in the TGP literature is that adding TGP to methotrexate lets patients stay on treatment more comfortably — with fewer liver-enzyme abnormalities and less marrow suppression — while at least maintaining disease control. Some trials have also examined TGP combined with leflunomide, and TGP alongside glucocorticoids with a view to reducing steroid dose.
This is a promising and repeatedly reported observation, not a settled fact. The mechanism proposed — that paeoniflorin’s hepatoprotective effects offset methotrexate’s liver burden — is plausible and has animal support, but the human trials testing it were not designed primarily as safety studies and were rarely blinded. If your rheumatologist has never heard of it, that is not ignorance; it is that the evidence has not crossed the language and quality threshold that changes international guidelines.
The Honest Limitations
Everything above needs to be read against a set of real problems with the evidence base. These are not nitpicks — they are the reasons TGP is standard in one country and unknown in the rest.
- Almost all trials come from a single country. The rheumatoid arthritis literature on TGP is overwhelmingly Chinese, published in Chinese-language journals. That matters not because Chinese research is inferior, but because independent replication in a different health system, with different patients and different investigators, is how medicine checks itself. That replication has essentially not happened.
- Publication bias is a live concern. Analyses of Chinese-language trials of traditional medicines have repeatedly found that an implausibly high proportion report positive results. When almost nothing negative is published, pooled estimates drift upward.
- Methodological quality is moderate at best. Reviews of this literature routinely note inadequate description of randomization and allocation concealment, absent or unclear blinding, missing intention-to-treat analysis, and short follow-up.
- Many trials are unblinded. In an open trial, subjective endpoints such as pain and morning stiffness inflate. This is exactly why the erythrocyte sedimentation rate and C-reactive protein results carry more weight than the symptom scores.
- Radiographic progression is barely studied. The endpoint that matters most in rheumatoid arthritis is whether joints are being destroyed over years. The TGP literature is dominated by 12- to 24-week symptom and lab outcomes, with little X-ray or long-term joint-damage data.
- Product variability. Even among TGP preparations, manufacturers differ. Outside a regulated drug supply, the variability is far worse.
The fair summary: TGP is a genuinely evidence-supported adjunct within Chinese rheumatology practice, and a plausible but unproven one everywhere else.
Beyond Rheumatoid Arthritis: Sjögren’s, Lupus, Lichen Planus, Psoriasis
Because TGP is a general immune modulator rather than a joint-specific drug, Chinese investigators extended it into other autoimmune conditions. All of these literatures are smaller and weaker than the rheumatoid arthritis one.
Primary Sjögren’s syndrome
In Sjögren’s, immune attack on the tear and saliva glands produces relentless dry eyes and dry mouth, plus fatigue and joint pain. This is a condition with few good drug options, so even modest help is welcome. Randomized trials and pooled reviews of TGP in Sjögren’s report improvement in dryness scores, salivary flow and inflammatory markers, sometimes with reduced steroid requirements. Trial sizes are small and blinding is often absent, so this remains suggestive rather than established.
Systemic lupus erythematosus
TGP has been studied mainly as an add-on to steroids and conventional immunosuppressants in mild-to-moderate lupus, with reported reductions in disease-activity scores and, in some trials, steroid dose. Lupus is a dangerous disease with an unpredictable course; nothing in this literature supports substituting peony for standard treatment, and doing so would be reckless.
Oral lichen planus
This chronic immune-mediated condition produces painful white striae and erosions inside the mouth, and topical steroids are the usual answer. TGP has been trialled as an oral systemic option added to steroids, with reported improvement in lesion severity and pain. In one study of 81 patients followed for 6 months, TGP capsules (1,200 mg) plus topical or systemic corticosteroids were compared with corticosteroids alone. Trials are small.
Psoriasis
TGP has been studied in plaque psoriasis, generally combined with conventional topical or systemic therapy, with reported reductions in PASI (Psoriasis Area and Severity Index). Again: small, mostly unblinded, mostly single-country.
Not every psoriasis trial is unblinded, though. A multicentre, double-blind, placebo-controlled trial by Yu and colleagues (2017) randomized 108 people with moderate-to-severe plaque psoriasis to TGP plus acitretin or placebo plus acitretin for 12 weeks. A 50 percent fall in PASI was reached by 90 percent of the TGP group and 70.5 percent of the placebo group, and a rise in the liver enzyme alanine aminotransferase was seen in 6.25 percent versus 20.4 percent. The pooled reviews point the same way, with a limit: a 2019 meta-analysis of 30 trials (2,802 participants) found TGP used alone was no better than other single treatments (risk ratio 0.93, not significant), while adding TGP to other treatments improved the response (risk ratio 1.31). A 2025 meta-analysis of 36 trials (3,140 participants) found that TGP added to conventional psoriasis treatments raised the PASI 60 response (risk ratio 1.32), and rated the methodological quality of the trials as limited.
A pattern worth naming: across all four conditions the reported results look similar in shape — moderate improvement, better lab markers, good tolerability apart from loose stools, and possible drug-sparing. That consistency is either a real class effect of a broad immunomodulator, or a signature of a literature with systematic optimism. Both explanations remain open.
Side Effects: The Diarrhoea Problem
TGP’s safety record within the trial literature is good, and that is one of its selling points relative to conventional DMARDs. The dominant adverse effect is gastrointestinal.
- Loose stools or diarrhoea are the dominant complaint. Reviews of this literature consistently name mild-to-moderate diarrhoea as TGP’s most common adverse effect, and it usually appears in the first two weeks. A reliable rate is harder to pin down than the internet suggests. One traceable figure comes from a 2011 review by He and Dai, describing the first double-blind TGP trial (1993: 450 people with rheumatoid arthritis, TGP 1.8 g/day versus methotrexate 10 mg/week for 12 weeks): adverse events occurred in 13.3 percent of the people taking TGP, most of them gastrointestinal disturbances, mostly mild diarrhoea, and most settled on their own within 1–2 weeks. What the pooled data show is mixed: in rheumatoid arthritis, adding TGP to conventional drugs did not increase gastrointestinal adverse effects at all, whereas trials in other conditions did find an excess — in chronic urticaria (hives), diarrhoea was about six times as common with TGP added to antihistamines (risk ratio 6.19), which the review’s evidence table puts at 11 more cases per 1,000 people, and in recurrent mouth ulcers, abdominal symptoms were about three times as common with TGP (risk ratio 3.27).
- It is typically mild and self-limiting, and often settles with dose reduction, slower dose escalation, or taking capsules with food.
- Less commonly reported: abdominal pain, poor appetite, nausea, and mild dizziness or rash.
- Serious adverse events are rarely reported in these trials. That is reassuring but not conclusive, because short trials in selected patients are poor detectors of rare harm.
Ongoing diarrhoea causes potassium and magnesium loss, which is its own problem, especially in someone also taking diuretics.
What a Peony Label Does and Does Not Tell You
This is where the article gets blunt. A supplement bottle labelled “White Peony Root” is not TGP, and no amount of marketing language changes that.
The arithmetic is simple. TGP at 1,800 mg/day and 40 percent paeoniflorin delivers about 720 mg of paeoniflorin daily. A crude-root capsule at the pharmacopeial 1.6 percent would need roughly 45 grams of root per day to match it. At 500 mg per capsule that is ninety capsules a day. Nobody is taking that, and nobody has tested whether it would be safe.
What a label can and cannot show:
- A stated paeoniflorin percentage AND a milligram amount per capsule are what connect a product to the trial doses. “Standardized extract” without a number means nothing.
- The phrase “total glucosides of paeony” or “total paeony glycosides” marks the trial-type extract. A product without it is most likely crude root.
- Species and part: the trial extract comes from Paeonia lactiflora root. Peony flower products are a different thing sold to a different market.
- Hidden licorice. Many peony formulas include it, and long-term licorice raises blood pressure and lowers potassium (see the cramps article).
- Prescribed DMARDs and biologics: uncontrolled rheumatoid arthritis destroys joints permanently, and that damage does not come back. Most TGP trials added it to these drugs rather than replacing them.
- Blood-test monitoring: the methotrexate-sparing question is precisely the kind of thing rheumatologists follow with blood tests rather than guesswork.
Cautions and Contraindications
- Pregnancy and breastfeeding: there is no adequate human safety data for TGP or for concentrated peony extracts in pregnancy, and peony appears in traditional formulas with contested uterine effects. Traditional culinary-level exposure in a formula is a different matter from a concentrated daily extract, but the honest position is that this has not been studied.
- Immunosuppressive therapy: TGP is used alongside these drugs in China. Any immune-modulating agent added to methotrexate, leflunomide, azathioprine, mycophenolate, a JAK inhibitor or a biologic adds to a regimen that clinicians track with blood-count monitoring.
- Existing liver or kidney disease: clearance and safety margins are not well characterised in impaired organ function.
- Anticoagulants and antiplatelets: peony preparations, especially red peony, have reported effects on platelet aggregation, which raises a bleeding-risk question for people taking warfarin, direct oral anticoagulants, clopidogrel or high-dose aspirin.
- Surgery: herbs with possible platelet effects are commonly stopped at least two weeks before an operation, as a general precaution.
- Licorice-containing peony formulas: licorice raises blood pressure and lowers potassium, a known risk for people with hypertension, heart failure, kidney disease or low potassium, and for people who take diuretics, digoxin or corticosteroids.
- Children: not established. Paediatric use has been reported in some Chinese settings but is outside anything supportable elsewhere.
- Persistent diarrhoea: reviews report that TGP’s diarrhoea is usually mild and often settles on its own or after the dose is lowered; ongoing diarrhoea causes potassium and magnesium loss.
Key Research Papers
Every numbered identifier below was checked live against NCBI E-utilities — author, title, journal and year all had to match before a PMID was printed. Where an identifier could not be confirmed that way, the entry keeps a PubMed topic search rather than risk a number that points at the wrong paper.
- Zhang W, Dai SM. Mechanisms involved in the therapeutic effects of Paeonia lactiflora Pallas in rheumatoid arthritis. International Immunopharmacology. 2012;14(1):27–31. — PubMed PMID: 22705050
- Luo J, Jin DE, Yang GY, et al. Total glucosides of paeony for rheumatoid arthritis: a systematic review of randomized controlled trials. Complementary Therapies in Medicine. 2017;34:46–56. — PubMed PMID: 28917375
- Huang Y, Wang H, Chen Z, et al. Efficacy and safety of total glucosides of paeony combined with methotrexate and leflunomide for active rheumatoid arthritis: a meta-analysis. Drug Design, Development and Therapy. 2019;13:1969–1984. — PubMed PMID: 31354242
- He DY, Dai SM. Anti-inflammatory and immunomodulatory effects of Paeonia lactiflora Pall., a traditional Chinese herbal medicine. Frontiers in Pharmacology. 2011;2:10. — PubMed PMID: 21687505
- Paeoniflorin effects on collagen-induced and adjuvant-induced arthritis in rodents. PubMed search.
- Feng Z, Zhang BQ, Zhu YM, et al. The effectiveness and safety of total glucosides of paeony in primary Sjögren’s syndrome: a systematic review and meta-analysis. Frontiers in Pharmacology. 2019;10:550. — PubMed PMID: 31178729
- Wang M, Wang Z, Liu Y, et al. The effectiveness and safety of total glucosides of paeony in systemic lupus erythematosus: a systematic review and meta-analysis. Medicine (Baltimore). 2022;101(50):e32029. — PubMed PMID: 36550839
- Zhou L, Cao T, Wang Y, et al. Clinical observation on the treatment of oral lichen planus with total glucosides of paeony capsule combined with corticosteroids. International Immunopharmacology. 2016;36:106–110. — PubMed PMID: 27129091
- Zheng Q, Jiang W, Sun X, et al. Total glucosides of paeony for the treatment of psoriasis: a systematic review and meta-analysis of randomized controlled trials. Phytomedicine. 2019;62:152940. — PubMed PMID: 31100680
- Liu B, Meng X, Ma Y, et al. Clinical safety of total glucosides of paeony adjuvant therapy for rheumatoid arthritis treatment: a systematic review and meta-analysis. BMC Complementary Medicine and Therapies. 2021;21(1):102 — PubMed PMID: 33771151. For the diarrhoea signal in non-rheumatological add-on trials, see Li M, Li Y, Xiang L, Li L. Efficacy and safety of total glucosides of paeony as an add-on treatment in adolescents and adults with chronic urticaria: a systematic review and meta-analysis. Frontiers in Pharmacology. 2022;13:961371 — PubMed PMID: 36263138, and Liu Z, Liu X, Han Y, et al. Efficacy and safety of total glucosides of paeony in the treatment of recurrent aphthous ulcers: a systematic review and meta-analysis. Frontiers in Pharmacology. 2024;15:1378782 — PubMed PMID: 38716235.
- Vickers A, Goyal N, Harland R, Rees R. Do certain countries produce only positive results? A systematic review of controlled trials. Controlled Clinical Trials. 1998;19(2):159–166. — PubMed PMID: 9551280
- Yang K, Zeng L, Long Z, et al. Efficacy and safety of total glucosides of paeony in the treatment of 5 types of inflammatory arthritis: a systematic review and meta-analysis. Pharmacological Research. 2023;195:106842. — PubMed PMID: 37402434
- Yu C, Fan X, Li Z, Liu X, Wang G. Efficacy and safety of total glucosides of paeony combined with acitretin in the treatment of moderate-to-severe plaque psoriasis: a double-blind, randomised, placebo-controlled trial. European Journal of Dermatology. 2017;27(2):150–154. — PubMed PMID: 28400341
- Li Z, Lu J, Guan K, et al. Add-on effects of total glucosides of paeony on conventional therapies for psoriasis: a systematic review and meta-analysis of randomized controlled trials. Frontiers in Pharmacology. 2025;16:1527288. — PubMed PMID: 40046738
- Zhang L, Wei W. Anti-inflammatory and immunoregulatory effects of paeoniflorin and total glucosides of paeony. Pharmacology & Therapeutics. 2020;207:107452. — PubMed PMID: 31836457
PubMed Topic Searches
- PubMed: TGP and rheumatoid arthritis
- PubMed: Paeoniflorin and NF-κB
- PubMed: Paeoniflorin and synovial fibroblasts
- PubMed: Paeonia lactiflora immunomodulation
- PubMed: TGP with leflunomide
- PubMed: TGP and steroid sparing
- PubMed: Paeoniflorin pharmacokinetics
- PubMed: Herbal medicine in RA — systematic reviews
Connections
- All Herbs
- Herbs and Supplements for Rheumatoid Arthritis
- White Peony Root (Bai Shao)
- White Peony Root: History and Traditional Use
- White Peony Root Benefits — hub
- Rheumatology — rheumatoid arthritis and related conditions
- Licorice — the common formula partner and its risks
- Dong Quai
- Codonopsis