Preterm Labor
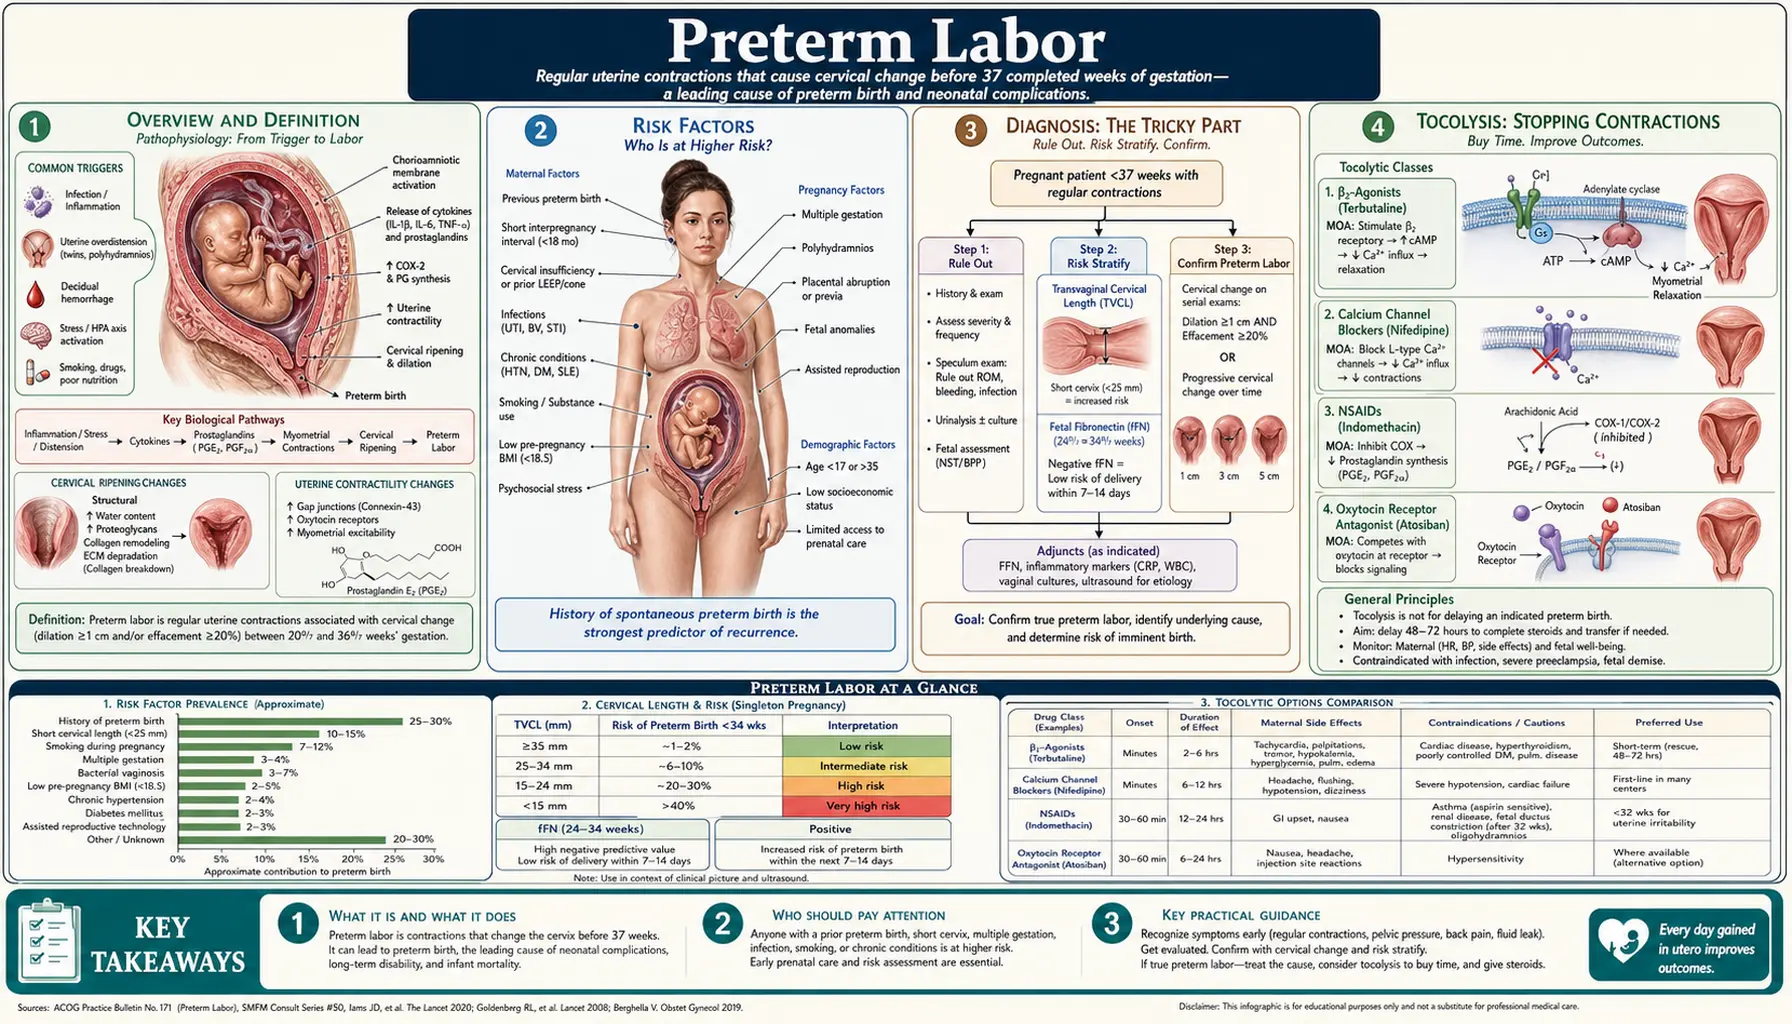
Table of Contents
- Overview and Definition
- Risk Factors
- Diagnosis: The Tricky Part
- Tocolysis: Stopping Contractions
- Antenatal Corticosteroids
- Magnesium for Fetal Brain Protection
- Progesterone for Prevention
- Cervical Cerclage
- What Parents Can Expect: NICU
- Signs That Need Immediate Evaluation
- Key Research Papers
- Connections
- Featured Videos
Overview and Definition
Preterm labor is defined as regular uterine contractions — at least 4 in 20 minutes or at least 8 in one hour — accompanied by cervical change (dilation, effacement, or both) before 37 completed weeks of pregnancy. It is the most common cause of neonatal illness and death in the United States, and the US has one of the highest preterm birth rates among wealthy nations.
In provisional US national data, the preterm birth rate was 10.41% in 2024, unchanged from 2023 — roughly 380,000 babies every year. After congenital anomalies, preterm birth is the leading cause of infant death. Survivors face real long-term risks: cerebral palsy, chronic lung disease, developmental delay, vision loss, and hearing loss. The earlier a baby is born, the higher those risks.
The Preterm Spectrum
- Late preterm (34–36 6/7 weeks): About 70% of all preterm births. These babies often appear healthy and "big enough" but carry subtle vulnerabilities — feeding difficulties, temperature instability, low blood sugar, jaundice, and breathing issues that may not show up until the first day or two at home. They need close follow-up after discharge.
- Early preterm (<34 weeks): More serious risks across the board. NICU admission is the norm rather than the exception.
- Extremely preterm (<28 weeks): Requires intensive NICU care. Viability begins around 22–23 weeks with aggressive intervention, but survival with disability is common at those gestational ages.
An Important Distinction: PPROM
Preterm labor (contractions causing cervical change) is different from PPROM — Preterm Premature Rupture of Membranes, before 37 weeks, meaning the bag of water breaks before labor starts. These are related but separate entities with different management pathways. Hospitals treat water breaking before 37 weeks as urgent, even when there are no contractions.
Cause Is Often Unknown
In many cases, no single clear cause is found. This can be frustrating and even guilt-inducing for mothers — but preterm labor frequently happens without any identifiable reason. It is not your fault.
Racial Disparities
Black women in the US experience preterm birth at roughly twice the rate of white and Hispanic women. Research increasingly points to structural racism, chronic stress (the "allostatic load" hypothesis), and systemic barriers to care — not biological differences — as the driving factors behind this disparity.
Risk Factors
Some risk factors are strong predictors; others add moderate risk. Knowing your risk can help you and your provider watch more closely — but having risk factors does not mean you will deliver preterm, and many preterm births happen in women with no known risk factors at all.
Strongest Predictors
- Prior preterm birth: The single strongest risk factor. If you delivered preterm before, your risk of preterm birth in a future pregnancy is 2.5 to 5 times higher than average. The shorter the previous pregnancy, the higher the recurrence risk.
- Short cervical length: Measured by transvaginal ultrasound between 16 and 24 weeks. A cervix shorter than 25 mm is a significant risk factor. A cervix shorter than 10 mm carries approximately a 70% chance of delivery before 35 weeks. This measurement is one of the most useful tools providers have, especially after a prior preterm birth or with other risk factors.
- Positive fetal fibronectin (fFN): A protein in cervicovaginal secretions that is normally not detectable between 22 and 34 weeks. The standard qualitative test uses a threshold of 50 ng/mL. In a 2013 study of 300 women with preterm labor symptoms, the chance of birth before 34 weeks rose with the level: 19% at 10 ng/mL, 32% at 50, 61% at 200 and 75% at 500. A level above 200 ng/mL therefore raises more concern. More usefully, a negative result is highly reassuring — if fFN is negative, there is less than a 1% chance of delivering within the next 14 days. This makes fFN a very useful test to rule out preterm labor and avoid unnecessary hospitalization or treatment.
Moderate Risk Factors
- Multiple gestation: Twins deliver at about 36 weeks on average; triplets around 33 weeks. Carrying more than one baby significantly raises preterm risk.
- Uterine anomalies: Bicornuate uterus, septate uterus, or other structural differences in the uterus can increase risk.
- Prior cervical procedures: LEEP or cone biopsy for abnormal Pap results can shorten the cervix or weaken it, sometimes leading to cervical incompetence (the cervix opens silently, without contractions).
- Infections: Bacterial vaginosis (BV), urinary tract infections, sexually transmitted infections, and chorioamnionitis (infection of the membranes) are all associated with preterm labor. Treatment of these infections is important throughout pregnancy.
- Short time between pregnancies: An interpregnancy interval of less than 6 months raises preterm risk.
- Substance use: Smoking, alcohol, and illicit substances all increase the risk.
- Domestic violence: Physical and emotional abuse are independently associated with preterm birth.
Social Determinants of Health
Poverty, food insecurity, neighborhood violence, inadequate prenatal care access, and chronic stress are all independently associated with higher preterm birth rates. These are not minor contributors — they are among the most powerful drivers of preterm birth disparities in the US. Prenatal providers and hospital social workers are the usual route to resources for these challenges.
Diagnosis: The Tricky Part
Diagnosing preterm labor is genuinely difficult — and getting it wrong in either direction has consequences. Here is the central problem: about 80% of women admitted for suspected preterm labor do not actually deliver preterm. This means most contractions before 37 weeks are not true preterm labor — but you cannot know which ones are without an evaluation.
Symptoms of Preterm Labor
- Regular contractions — every 5 to 10 minutes or closer — that last 30 to 60 seconds
- Pelvic pressure or a feeling of heaviness "down there"
- Low back pain that is dull, constant, or rhythmic
- Abdominal cramping that feels like strong period cramps but doesn't go away
- A change in your vaginal discharge (more, thicker, tinged with pink or blood)
- A feeling that the baby is pushing down harder than usual
How Providers Confirm Preterm Labor
- Contractions on the monitor: Regular pattern documented on the fetal monitor (tocometer)
- Cervical change on exam: Dilation or effacement found on digital vaginal exam, or change from a previous exam
- Transvaginal ultrasound: Short cervical length (<25 mm) supports the diagnosis
- Fetal fibronectin (fFN): A negative result is very reassuring; a positive result raises concern but is not definitive on its own
False Labor (Braxton Hicks Contractions)
Braxton Hicks contractions are irregular practice contractions that most pregnant women feel, especially after 28 weeks. They tend to be irregular, do not intensify over time, often stop with a change in position, rest, or drinking water, and — most importantly — do not cause the cervix to dilate or efface. They can feel exactly like real contractions to you. This is why it can be so hard to tell the difference at home.
When Contractions Are a Reason to Go In
Contractions that are 10 minutes apart or less, lasting 30 to 60 seconds, for more than one hour are the pattern labor units want checked — even when a woman is not sure, even when they feel mild, even after being sent home before. Providers would always rather check and reassure than miss true preterm labor. Preterm labor caught early may be stopped or slowed — time matters enormously.
Rule of thumb: The common answer from labor units to the question of whether to call or go in is yes.
Tocolysis: Stopping Contractions
Tocolysis means using medications to slow or stop uterine contractions. It is important to understand the goal clearly: tocolysis is not meant to prevent preterm birth permanently. The realistic goal is to delay delivery for 48 hours — long enough to give antenatal steroids (which need 24–48 hours to fully work) and, if needed, to transfer you to a hospital with a higher-level NICU. Even a 48-hour delay can make a meaningful difference in your baby's outcomes.
Nifedipine (Calcium Channel Blocker) — First-Line
Nifedipine is taken by mouth and is widely used as the first-line tocolytic in the US. A typical regimen is a loading dose of 10–30 mg followed by 10–20 mg every 4 to 6 hours. Common maternal side effects include flushing, headache, and heart palpitations — usually temporary and manageable. A common caution is that nifedipine and magnesium sulfate together can cause dangerous drops in blood pressure. A 2005 chart review looked at this in women with preeclampsia, not preterm labor: among 162 women given both and 215 given magnesium without nifedipine, the combination did not increase serious magnesium-related effects, and low blood pressure in the mother was less common (41.4%) than in women on magnesium and no blood-pressure drug (53.0%).
Indomethacin (COX Inhibitor)
Indomethacin is a non-steroidal anti-inflammatory given as a rectal suppository (loading dose 50–100 mg) then orally (25–50 mg every 6 hours). It is effective but has an important limitation: it is only used at or before 32 weeks of gestation, because after that point it can cause premature closure of the ductus arteriosus — a blood vessel in the baby's heart that needs to stay open before birth. It is also limited to short courses (48–72 hours maximum) and is avoided in women with kidney disease.
Magnesium Sulfate
Magnesium is given intravenously. When used before 32 weeks, its primary role is protecting the baby's brain — not stopping contractions (see the Magnesium section below). It does have some tocolytic effect, but this is modest and secondary. It is not used as a standalone tocolytic.
Terbutaline (Betamimetic)
Terbutaline given as a subcutaneous injection (0.25 mg) can briefly slow contractions. Its cardiac side effects — rapid heart rate, palpitations, chest tightness — limit its use to short-term, closely monitored settings. The injection label carries a boxed warning that terbutaline "has not been approved and should not be used for prolonged tocolysis (beyond 48-72 hours)". The tablet label says oral terbutaline "has not been approved and should not be used for acute or maintenance tocolysis". Both report that "Serious adverse reactions, including death, have been reported" after use in pregnant women, including increased heart rate, cardiac arrhythmias, pulmonary edema and myocardial ischemia in the mother. Oral terbutaline for ongoing prevention of preterm birth is not proven to work for this purpose.
What Does NOT Work
- Bedrest: No evidence that routine bedrest prevents preterm birth or improves outcomes. It can actually cause harm (blood clots, muscle loss, psychological impact) in prolonged use.
- Intravenous (IV) hydration: No evidence that routine hydration for preterm contractions prevents preterm birth. It may be given for comfort or to rule out dehydration as a trigger, but it is not a treatment for preterm labor itself.
- Oral tocolytics for maintenance: Continuing tocolytic pills at home after the acute episode has passed does not prevent recurrence, and the terbutaline labels warn against maintenance tocolysis in the outpatient or home setting.
Antenatal Corticosteroids: The Single Most Important Treatment
If you are between 24 and 34 weeks pregnant and facing the possibility of preterm birth, the most important thing your medical team can do — beyond anything else — is give you antenatal corticosteroids. These are steroid shots that help your baby's lungs, brain, and intestines mature faster than they normally would.
What Is Given
- Betamethasone: 12 mg injected into muscle, two doses given 24 hours apart. This is the most widely used regimen.
- Dexamethasone: 6 mg injected into muscle, four doses given 12 hours apart. Equivalent effectiveness to betamethasone.
The shots take 24 to 48 hours to reach full effect in the baby. Even if delivery happens sooner, partial benefit still occurs.
What They Prevent
- Respiratory distress syndrome: relative risk 0.71 in the 2020 Cochrane review of 27 trials (0.66 in the 2017 version)
- Neonatal death: relative risk 0.78 in the 2020 review (0.69 in the 2017 version)
- Intraventricular hemorrhage (brain bleeding): relative risk 0.58 in the 2020 review, rated "probably" reduced (0.55 in the 2017 version)
- Necrotizing enterocolitis (serious intestinal condition): relative risk 0.50 in the 2017 version; the 2020 summary gives no figure
Rescue Course
If you received steroids more than 14 days ago and are now facing preterm birth again before 34 weeks, your provider may give one additional "rescue course" of steroids. The evidence supports this in certain situations.
Late Preterm Steroids (34–36 6/7 Weeks)
A landmark 2016 trial called the ALPS trial (led by Dr. Gyamfi-Bannerman, published in the New England Journal of Medicine) showed that betamethasone reduces respiratory complications even in late preterm infants — babies at 34 to 36 weeks who look relatively healthy. The main result, a measure of breathing support or death in the first 72 hours, occurred in 11.6% of babies on betamethasone and 14.4% on placebo. The same trial found a harm: low blood sugar in the newborn was more common after betamethasone (24.0% vs 15.0%). The betamethasone injection label also says newborn low blood sugar "has been reported after antenatal administration".
A U.S. Food and Drug Administration (FDA) expansion of the approved indication to late preterm pregnancy in 2019 could not be confirmed: the current betamethasone injection label on DailyMed lists allergic, skin, hormone and other uses, and it has no antenatal or fetal-lung-maturation indication.
Steroids in Low-Resource Hospitals
The WHO ACTION trial tested dexamethasone in 2,852 women at 26 to 33 weeks in 29 hospitals in Bangladesh, India, Kenya, Nigeria and Pakistan. Neonatal death fell from 23.5% on placebo to 19.6% (relative risk 0.84), and possible bacterial infection in the mother did not increase (6.3% on placebo, 4.8% on dexamethasone).
Things to Know as a Patient
- The shots may sting briefly — this is normal
- Blood sugar may rise temporarily, especially if you have gestational diabetes — your team will monitor you
- Your white blood cell count will go up — this is an expected steroid effect and does not mean you have an infection
Magnesium Sulfate for Fetal Brain Protection
When preterm birth before 32 weeks appears imminent, magnesium sulfate is given intravenously — not primarily to stop contractions, but to protect your baby's developing brain.
Why Magnesium Protects the Brain
The developing brain of an extremely premature baby is vulnerable to a type of injury called excitotoxicity — essentially, overstimulation of brain cells by glutamate that causes them to die. Magnesium blocks a key receptor (the N-methyl-D-aspartate (NMDA) glutamate receptor) that mediates this damage, particularly in the white matter of the brain (the "wiring" that connects different brain regions). White matter injury is one of the main causes of cerebral palsy in premature babies.
The Evidence
- The BEAM trial (2008, Rouse et al., New England Journal of Medicine): A randomized controlled trial of 2,241 women at imminent risk of delivery at 24 to 31 weeks. Its main measure, death or moderate or severe cerebral palsy, was not different (11.3% on magnesium vs 11.7% on placebo). In a planned secondary analysis across the whole trial, moderate or severe cerebral palsy was less frequent (1.9% vs 3.5%; relative risk 0.55, the 45% reduction often quoted). Deaths did not differ significantly (9.5% vs 8.5%).
- The ACTOMgSO4 trial (Crowther et al., 2003, JAMA): Among 1,062 women before 30 weeks, cerebral palsy in survivors (6.8% vs 8.2%) and death or cerebral palsy (19.8% vs 24.0%) were less frequent with magnesium, but neither difference was statistically significant. Substantial gross motor dysfunction was significantly lower (3.4% vs 6.6%; relative risk 0.51).
- The 2009 Cochrane review pooled five trials (6,145 babies) and found less cerebral palsy (relative risk 0.68). The 2026 update has six trials (5,917 women): up to 2 years of age, cerebral palsy had a relative risk of 0.71, about 60 women treated per case avoided, and death or cerebral palsy 0.87, with little to no difference in death alone (0.96). At early school age the two trials with follow-up showed little to no difference in cerebral palsy (0.99, low certainty). Side effects in the mother severe enough to stop treatment were more common (relative risk 3.21).
Magnesium Given Later in Pregnancy
Magnesium given later has not shown the same benefit. In the 2023 MAGENTA trial, magnesium at 30 to 34 weeks did not improve child survival free of cerebral palsy at 2 years, though the trial had limited power to detect small differences. Babies had less respiratory distress syndrome (34% vs 41%), and mothers had more adverse events (77% vs 20%) and more major bleeding after birth (3.4% vs 1.7%).
How It Is Given
A loading dose of 4 to 6 grams is given intravenously over 15 to 30 minutes (this can cause a sensation of warmth or flushing — tell your nurse if you feel this). Then a maintenance infusion of 1 to 2 grams per hour continues for at least 12 hours, or until delivery.
Monitoring for Safety
Your nurses will check these closely while you are on magnesium:
- Patellar reflex (knee jerk): This is checked every hour. When magnesium levels get too high, the reflex disappears — this is an early warning sign before more serious toxicity
- Breathing rate: Watched to stay above 12 breaths per minute
- Urine output: Magnesium is cleared by the kidneys
The antidote for magnesium toxicity is calcium gluconate, which is kept at the bedside whenever magnesium is running. Magnesium crosses the placenta, so your newborn may have some effects (low muscle tone, brief breathing issues) that the NICU team will be watching for and can manage.
Progesterone for Prevention
Progesterone is a hormone that plays a key role in maintaining pregnancy — it keeps the uterus relaxed, maintains cervical length, and suppresses inflammation and contractions. Two types of progesterone supplementation have been studied for preventing preterm birth.
Vaginal Progesterone — For Short Cervix
Vaginal progesterone (200 mg per night inserted vaginally from about 20 weeks through 36 weeks) has solid evidence supporting its use in women with a short cervix (less than 25 mm) found on ultrasound, even without a prior preterm birth. Multiple randomized trials support this, including the Fonseca NEJM 2007 trial and the Hassan 2011 trial in Ultrasound in Obstetrics & Gynecology. FIGO (the international obstetrics society) recommends it for this indication. The Society for Maternal-Fetal Medicine stated in 2023 that the withdrawal of the injected form described below was no reason to change indications for vaginal progesterone in patients with a short cervix.
17-Alpha-Hydroxyprogesterone Caproate (17-OHPC) — A Complicated Story
This drug is a weekly injection given from 16–20 weeks through 36 weeks. It was approved by the U.S. Food and Drug Administration in 2011 based on a 2003 trial by Meis et al. in the New England Journal of Medicine showing reduced preterm birth in women with prior preterm birth. However, a much larger subsequent trial (the PROLONG trial) failed to replicate this benefit in a broader population: birth before 35 weeks occurred in 11.0% on the drug and 11.5% on placebo. On April 5, 2023, the U.S. Food and Drug Administration withdrew approval of the drug, brand-name and generic versions alike, because of the lack of evidence that it reduces the risk of recurrent preterm birth.
This does not mean 17-alpha-hydroxyprogesterone caproate definitely does not work for any individual — the science is genuinely uncertain and the patient population in the two trials differed. The Society for Maternal-Fetal Medicine agreed with the withdrawal and discourages continued prescribing, including through compounding pharmacies. For vaginal progesterone after a prior preterm birth without a short cervix, its 2023 statement calls for a shared decision.
A 2021 pooled analysis of the original patient data from 31 trials (11,644 women) found birth before 34 weeks reduced in high-risk single pregnancies with vaginal progesterone (relative risk 0.78) and with the injected form (relative risk 0.83, range 0.68 to 1.01). Neither reduced preterm birth before 34 weeks in twins (vaginal progesterone relative risk 1.01).
Why Vaginal and Injected Progesterone Have Different Results
This is still not fully understood. The two forms of progesterone are absorbed differently, may reach the uterus and cervix through different pathways, and may act through different mechanisms. Researchers are actively studying this question.
Cervical Cerclage
Cervical cerclage is a surgical procedure in which a stitch (suture) is placed around the cervix to hold it closed and prevent it from opening prematurely. It is typically placed under spinal or general anesthesia as an outpatient procedure.
Types of Cerclage
- McDonald cerclage: A circumferential suture placed around the cervix near the opening (external os). The most common type; can be placed in the office or operating room. Removed at 36–37 weeks or at the onset of labor.
- Shirodkar cerclage: Placed higher, closer to the internal opening of the cervix. Requires more dissection. Used when the McDonald approach is not technically feasible.
- Transabdominal cerclage: Placed through the abdomen, not vaginally, at or near the uterine isthmus (the very top of the cervix). Used when transvaginal cerclage has failed, or when the cervix is too short or damaged for a vaginal approach. Often placed laparoscopically before conception or early in pregnancy. Delivery must be by cesarean section.
When Cerclage Is Recommended
- History-indicated (prophylactic): If you have had one or more second-trimester pregnancy losses or preterm births where the cervix opened painlessly without contractions, your provider may recommend cerclage placed at 12–14 weeks of gestation — before any cervical shortening is visible on ultrasound. This is the strongest indication.
- Ultrasound-indicated: If you have a prior preterm birth AND a short cervix (less than 25 mm) found on ultrasound between 16 and 24 weeks, cerclage combined with vaginal progesterone may be recommended. Evidence supports benefit in this specific group.
- Physical exam-indicated (emergency cerclage): If your cervix is found to be dilated with membranes visible or prolapsed into the vagina — sometimes called a "bulging bag" cerclage. This is controversial and high-risk, but in carefully selected cases it can prolong pregnancy by 4 to 5 weeks.
When Cerclage Does NOT Help
Cerclage does not benefit women who have a short cervix without a prior preterm birth. Multiple meta-analyses have shown no benefit — and it may even cause harm — in this group. Vaginal progesterone alone is preferred for short cervix without prior preterm birth.
Risks of Cerclage
- Infection (chorioamnionitis)
- Premature rupture of membranes triggered by the procedure itself
- Preterm labor from the procedure
- Uterine rupture at delivery if the cerclage is not removed before labor — which makes a cerclage in place important information for any provider, especially in emergencies
What Parents Can Expect: NICU Survival and Care
If your baby is born preterm, they will likely be cared for in a Neonatal Intensive Care Unit (NICU). This can be one of the most frightening experiences a parent can face. Here is honest information to help you understand what to expect.
Survival Rates by Gestational Age
A US registry of 10,877 babies born at 22 to 28 weeks at 19 academic centers from 2013 to 2018 found that 78.3% survived to discharge. Survival was 10.9% of live births at 22 weeks (30.0% when actively treated), 55.8% of actively treated babies at 23 weeks, and 94.0% at 28 weeks. The rough figures often quoted by week are:
- 22 weeks: 10–30% survival with the most aggressive intervention. Most survivors have significant disabilities. This is the edge of viability — decisions about intensive care at this age are deeply personal and are made by families with the medical team.
- 23 weeks: About 50% survival with intensive care.
- 24 weeks: 60–70% survival. This is widely recognized as the threshold of viability where intensive care is generally offered.
- 26 weeks: About 80% survival.
- 28 weeks: About 90% survival.
- 32 weeks: About 95% survival — with NICU support.
- 34–36 weeks (late preterm): Most survive, but US data for 2002 show infant deaths 3 times higher than in full-term babies (7.9 vs 2.4 per 1,000 live births). Short-term NICU issues are common.
Common Issues in Premature Babies
- Respiratory distress syndrome (RDS): The lungs haven't made enough surfactant (the substance that keeps air sacs open). Treated with synthetic surfactant given directly into the lungs, and breathing support (CPAP or ventilator).
- Intraventricular hemorrhage (IVH): Bleeding into or around the ventricles of the brain. More common in babies born before 28 weeks. Graded 1 through 4; mild bleeds (grades 1–2) often resolve without long-term consequences; severe bleeds (grades 3–4) are associated with higher risk of developmental problems.
- Necrotizing enterocolitis (NEC): A serious condition where portions of the intestine become inflamed and may die. More common in extremely premature babies. Treatment ranges from antibiotics to surgery.
- Retinopathy of prematurity (ROP): Abnormal blood vessel growth in the eye that can lead to vision problems or blindness if untreated. All premature babies born before 32 weeks are screened by an ophthalmologist.
- Feeding difficulties: Premature babies have not yet developed the coordinated suck-swallow-breathe reflex needed for bottle or breast feeding. Feeding through a small tube in the nose or mouth is routine until the baby is ready.
- Temperature instability: Premature babies have very little body fat for insulation. They are cared for in incubators (isolettes) that maintain their temperature.
- Jaundice: Very common in premature babies. Treated with phototherapy (a special light).
Your Role in the NICU
You are not a bystander in the NICU — you are an essential part of your baby's care team:
- Kangaroo care (skin-to-skin): Holding your baby against your bare chest has proven benefits. Research shows it reduces infection rates, improves feeding, helps regulate the baby's temperature and heart rate, and shortens length of NICU stay. It often starts earlier than parents expect. In a WHO trial of babies weighing 1.0 to 1.799 kg in hospitals in Ghana, India, Malawi, Nigeria and Tanzania, starting skin-to-skin care right after birth, before the baby was stable, lowered deaths in the first 28 days (12.0% vs 15.7%; relative risk 0.75). The trial was stopped early because of this benefit.
- Talking and reading to your baby: Your voice is recognized and comforting. NICU babies who hear their parents' voices regularly show better development outcomes.
- Questions: You have every right to understand what every medication, intervention, and monitor is doing. Nurses and doctors can explain each one.
- Your own care: NICU stays are a marathon, not a sprint. Food, sleep and support matter here too. Your wellbeing matters — for you, and for your baby.
Signs That Need Immediate Evaluation
Before 37 weeks of pregnancy, these are the signs hospitals treat as needing immediate attention, without waiting to see if things get better on their own.
Signs Labor and Delivery Units Treat as Urgent
- Contractions every 5 to 10 minutes, lasting 30 to 60 seconds, for more than one hour — even if they feel mild, even if they feel irregular, even if you are not sure they are real contractions
- 4 or more contractions per hour, even if they are painless — preterm contractions can be completely painless
- Low back pressure or pelvic fullness that does not go away with changing position or resting
- A feeling that something is "different" or "not right" — labor units take this report seriously
- Fluid gushing or leaking from the vagina: this may be the water breaking (PPROM). Standard emergency instructions are to insert nothing into the vagina, to lie down, and to call 911 when fluid is soaking through clothing.
- Any vaginal bleeding
Reassuring Signs (Less Urgent)
- Occasional tightening that changes when you change position
- Contractions that stop when you walk, rest, or drink water
- Irregular pattern with no regularity building up over time
- No cervical change on a recent exam (if you were just checked)
The Bottom Line
The common answer from labor units to the question of whether to call or go in is: go in. Preterm labor caught early has a better chance of being slowed or stopped. A false alarm is not a burden — it is the right call. Every provider would rather check you than miss something serious.
Key Research Papers
- Blencowe H et al. — National, regional, and worldwide estimates of preterm birth rates in the year 2010 with time trends since 1990 for selected countries: a systematic analysis and implications (Lancet, 2012)
Landmark global epidemiological study estimating preterm birth rates across 184 countries; established the scale of the preterm birth burden worldwide and identified the US as having one of the highest rates among high-income nations.
— PubMed PMID: 22682464 - Gyamfi-Bannerman C et al. — Antenatal Betamethasone for Women at Risk for Late Preterm Delivery (ALPS Trial, NEJM 2016)
Randomized controlled trial demonstrating that antenatal betamethasone reduces respiratory complications in late preterm infants (34–36 6/7 weeks) even when they appear clinically stable; newborn low blood sugar was more common with betamethasone (24.0% vs 15.0%). An FDA expansion of the indication could not be confirmed on the current label.
— PubMed PMID: 26842679 - Rouse DJ et al. — A randomized, controlled trial of magnesium sulfate for the prevention of cerebral palsy (BEAM Trial, NEJM 2008)
Multicenter RCT of 2,241 women at imminent risk of delivery at 24 to 31 weeks; no significant difference in the main measure, death or moderate or severe cerebral palsy (11.3% vs 11.7%), while moderate or severe cerebral palsy was less frequent in a prespecified secondary analysis (1.9% vs 3.5%; relative risk 0.55), the source of the 45% figure; established magnesium for neuroprotection as standard of care in the US.
— PubMed PMID: 18753646 - Meis PJ et al. — Prevention of Recurrent Preterm Delivery by 17 Alpha-Hydroxyprogesterone Caproate (NEJM 2003)
RCT in women with prior preterm birth showing significant reduction in recurrent preterm birth with weekly injections of the drug; formed the basis for FDA approval in 2011, though later contradicted by the PROLONG trial leading to withdrawal of approval in 2023.
— PubMed PMID: 12802023 - Fonseca EB et al. — Progesterone and the Risk of Preterm Birth Among Women with a Short Cervix (NEJM 2007)
RCT demonstrating that vaginal progesterone (200 mg/night) significantly reduced preterm birth before 34 weeks in women with a cervical length below 15 mm; established vaginal progesterone for short cervix as evidence-based prevention.
— PubMed PMID: 17671254 - Hassan SS et al. — Vaginal progesterone reduces the rate of preterm birth in women with a sonographic short cervix: a multicenter, randomized, double-blind, placebo-controlled trial (Ultrasound Obstet Gynecol 2011;38(1):18-31)
Large RCT (n=458) confirming that vaginal progesterone gel (90 mg/day) in women with cervical length 10–20 mm reduced preterm birth before 33 weeks and composite neonatal morbidity; reinforced international guidelines favoring vaginal progesterone for short cervix.
— PubMed PMID: 21472815 - To MS et al. — Cervical cerclage for prevention of preterm delivery in women with short cervix: randomised controlled trial (Lancet 2004)
Multicenter RCT in 253 women whose cervix measured 15 mm or less on routine scan at 22–24 weeks: a Shirodkar stitch did not substantially reduce birth before 33 weeks (22% vs 26%, relative risk 0.84).
— PubMed PMID: 15183621 - Romero R, Gómez R, Chaiworapongsa T, Conoscenti G, Kim JC, Kim YM — The Role of Infection in Preterm Labour and Delivery (Paediatric and Perinatal Epidemiology 2001;15 Suppl 2:41-56)
Comprehensive review of the evidence linking intrauterine infection and subclinical infection to preterm labor; describes the inflammatory cascade triggered by infection that activates uterine contractions and cervical ripening.
— PubMed PMID: 11520399 - Goldenberg RL et al. — Epidemiology and Causes of Preterm Birth (Lancet 2008)
Landmark review of preterm birth epidemiology, causes, risk factors, and racial disparities in the US and globally; identified the multifactorial and often idiopathic nature of preterm birth and called for public health approaches to reduction.
— PubMed PMID: 18177778 - Crowther CA et al. — Effect of magnesium sulfate given for neuroprotection before preterm birth: a randomized controlled trial (ACTOMgSO4, JAMA 2003)
Australian and New Zealand RCT in which cerebral palsy in survivors and death or cerebral palsy were less frequent with magnesium but not significantly so, while substantial gross motor dysfunction was significantly reduced (3.4% vs 6.6%); one of the key trials supporting magnesium neuroprotection alongside BEAM.
— PubMed PMID: 14645308 - Delnord M, Zeitlin J — Epidemiology of Late Preterm and Early Term Births: An International Perspective (Seminars in Fetal and Neonatal Medicine 2019)
International review reporting late preterm birth rates of 3% to 6% of singleton live births across countries; birth before 39 weeks is linked with poorer child health across a wide range of settings.
— PubMed PMID: 30309813 - Hamilton BE, Martin JA, Osterman MJK — Births: Provisional Data for 2024 (Vital Statistics Rapid Release, National Center for Health Statistics, Report No. 38, 2025)
— PubMed PMID: 41747069 - Tomashek KM et al. — Differences in mortality between late-preterm and term singleton infants in the United States, 1995-2002 (J Pediatr 2007;151(5):450-6)
— PubMed PMID: 17961684 - Abbott DS et al. — Evaluation of a quantitative fetal fibronectin test for spontaneous preterm birth in symptomatic women (Am J Obstet Gynecol 2013;208(2):122.e1-6)
— PubMed PMID: 23164760 - Magee LA et al. — Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with preeclampsia (Am J Obstet Gynecol 2005;193(1):153-63)
— PubMed PMID: 16021073 - McGoldrick E et al. — Antenatal corticosteroids for accelerating fetal lung maturation for women at risk of preterm birth (Cochrane Database Syst Rev 2020;12(12):CD004454)
— PubMed PMID: 33368142 - Roberts D et al. — Antenatal corticosteroids for accelerating fetal lung maturation for women at risk of preterm birth (Cochrane Database Syst Rev 2017;3(3):CD004454)
— PubMed PMID: 28321847 - WHO ACTION Trials Collaborators — Antenatal Dexamethasone for Early Preterm Birth in Low-Resource Countries (N Engl J Med 2020;383(26):2514-2525)
— PubMed PMID: 33095526 - Doyle LW et al. — Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus (Cochrane Database Syst Rev 2009;(1):CD004661)
— PubMed PMID: 19160238 - Shepherd ES et al. — Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus (Cochrane Database Syst Rev 2026;9(9):CD004661)
— PubMed PMID: 42689525 - Crowther CA et al. — Prenatal Intravenous Magnesium at 30-34 Weeks' Gestation and Neurodevelopmental Outcomes in Offspring: The MAGENTA Randomized Clinical Trial (JAMA 2023;330(7):603-614)
— PubMed PMID: 37581672 - Blackwell SC et al. — 17-OHPC to Prevent Recurrent Preterm Birth in Singleton Gestations (PROLONG Study): A Multicenter, International, Randomized Double-Blind Trial (Am J Perinatol 2020;37(2):127-136)
— PubMed PMID: 31652479 - Society for Maternal-Fetal Medicine, SMFM Publications Committee — Society for Maternal-Fetal Medicine Statement: Response to the Food and Drug Administration's withdrawal of 17-alpha hydroxyprogesterone caproate (Am J Obstet Gynecol 2023;229(1):B2-B6)
— PubMed PMID: 37061078 - EPPPIC Group — Evaluating Progestogens for Preventing Preterm birth International Collaborative (EPPPIC): meta-analysis of individual participant data from randomised controlled trials (Lancet 2021;397(10280):1183-1194)
— PubMed PMID: 33773630 - Bell EF et al. — Mortality, In-Hospital Morbidity, Care Practices, and 2-Year Outcomes for Extremely Preterm Infants in the US, 2013-2018 (JAMA 2022;327(3):248-263)
— PubMed PMID: 35040888 - WHO Immediate KMC Study Group — Immediate "Kangaroo Mother Care" and Survival of Infants with Low Birth Weight (N Engl J Med 2021;384(21):2028-2038)
— PubMed PMID: 34038632
Connections
- Reproductive Medicine
- Preeclampsia
- Gestational Diabetes
- Postpartum Hemorrhage
- Recurrent Pregnancy Loss
- Hyperemesis Gravidarum
- Ectopic Pregnancy
- Folate (Vitamin B9)
- Magnesium