⚠ Evidence warning: Clinical trials or other evidence do not support the claims that warm compresses, lid massage, lid cleansers and diet changes clear or prevent chalazia and styes. This page keeps it as a report of what people, websites or other media say.
Chalazion and Stye (Hordeolum)
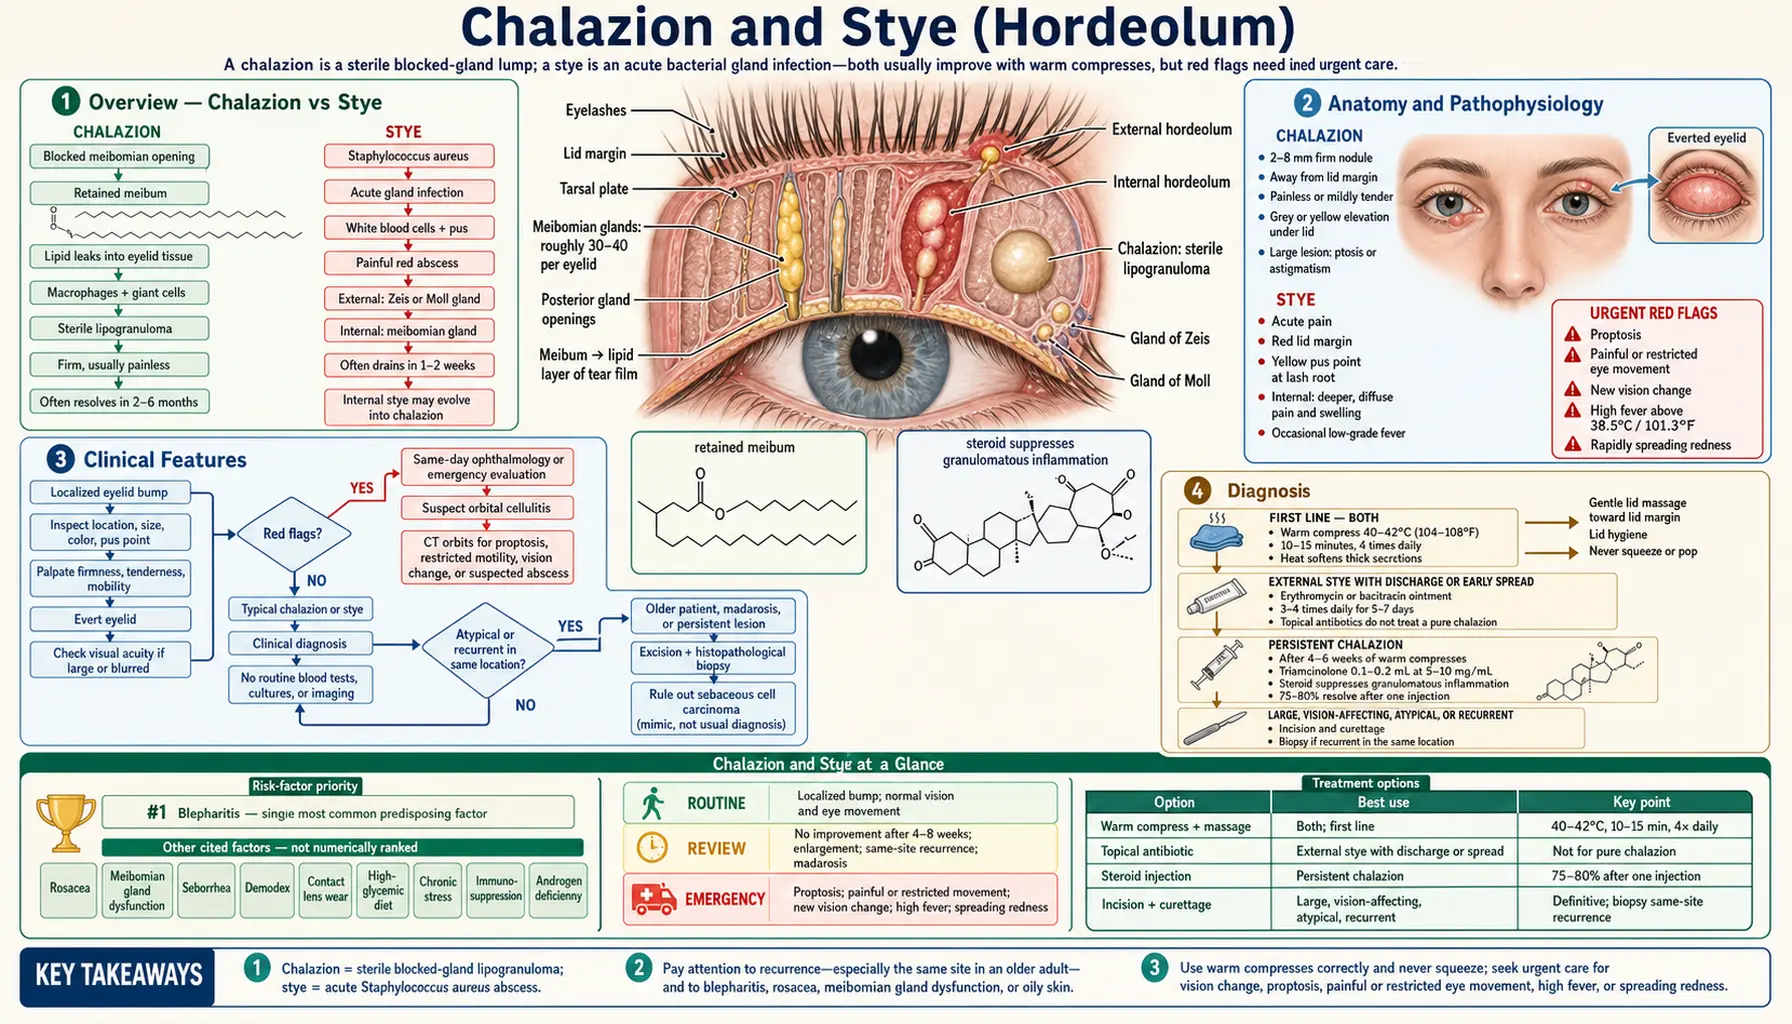
A chalazion is a small, firm lump that develops on the eyelid when one of the oil-producing glands inside becomes blocked and inflamed. A stye — medically called a hordeolum — is an acute bacterial infection of a different set of eyelid glands, causing a painful, red swelling, often with a visible pus point near the base of an eyelash. Both conditions are extremely common, affecting people of all ages, and the vast majority resolve on their own or with simple home care such as warm compresses applied several times daily.
Together, chalazia and styes account for millions of doctor visits every year. Most people experience at least one in their lifetime, and some — particularly those with oily skin, rosacea, or blepharitis — may develop them repeatedly. Understanding the difference between the two, and knowing when home treatment is enough versus when you need professional care, can spare you unnecessary worry and help you heal faster.
Most styes and chalazia are not dangerous, but certain warning signs are treated as reasons for same-day or emergency evaluation: fever, any change in vision, the eyeball appearing to be pushed forward, the inability to move the eye normally, or redness spreading rapidly beyond the eyelid onto the cheek or bridge of the nose. These signs suggest the infection may have spread deeper into the eye socket — a serious condition called orbital cellulitis that requires immediate medical attention.
- Overview — Chalazion vs Stye
- Anatomy and Pathophysiology
- Clinical Features
- Diagnosis
- Conservative Treatment — Warm Compresses and Lid Hygiene
- Medical Treatment
- Surgical Treatment — Incision and Curettage
- Prevention and Management of Recurrence
- Key Research Papers
- Connections
Overview — Chalazion vs Stye
Chalazion and stye are two distinct eyelid conditions that are often confused with each other because they can look similar — both cause a bump or swelling on the eyelid. However, their causes, timelines, and treatments differ in important ways.
A chalazion (plural: chalazia; from the Greek word for "hailstone") is a sterile lipogranuloma of the meibomian gland, or less commonly of the glands of Zeis or Moll. It is not an infection. Instead, when a meibomian gland becomes obstructed, the oily secretion it normally releases into the tear film backs up inside the gland. Over days to weeks, this retained lipid material leaks into the surrounding eyelid tissue, triggering the immune system to form a granulomatous reaction — a walled-off collection of immune cells trying to contain and digest the lipid. The result is a painless or minimally tender, firm, rubbery nodule that sits within the eyelid tissue and moves when the overlying skin is gently pressed. Most chalazia slowly resolve on their own over two to six months, though larger ones may need treatment.
A large chalazion can cause complications beyond mere appearance: if it sits on the upper eyelid and is heavy enough, it can push the eyelid down and cause ptosis (drooping). If it presses on the cornea — the clear front surface of the eye — it can indent the cornea just enough to alter its curvature and produce astigmatism, which blurs vision. These complications generally resolve when the chalazion is treated. One important caution: a chalazion that keeps coming back in exactly the same location, especially in an older adult, is routinely biopsied to rule out sebaceous gland carcinoma, a rare but serious eyelid malignancy that can masquerade as a persistent chalazion.
A hordeolum — the medical name for a stye — is an acute bacterial infection of an eyelid gland, almost always caused by Staphylococcus aureus. There are two types: an external hordeolum is an abscess of the glands of Zeis or Moll, which sit at the base of the eyelashes along the lid margin. It presents as a tiny, acutely painful pustule right at the lash line — often with a yellow point of pus visible at the center. It usually ruptures and drains on its own within one to two weeks. An internal hordeolum is an abscess of a meibomian gland — larger, deeper, and more painful than the external type, pointing toward the inner surface of the eyelid. After the acute bacterial phase resolves, an internal hordeolum may leave behind a residual blocked gland that then evolves into a chalazion — which is why the two conditions are so often discussed together.
Anatomy and Pathophysiology
To understand why chalazia and styes form, it helps to know the glandular architecture of the eyelid.
The eyelids contain three types of glands relevant to these conditions. The meibomian glands are the largest and most important: there are roughly 30 to 40 of them in each eyelid, running vertically through the tarsal plate (the firm connective-tissue scaffold that gives the eyelid its structure). They are modified sebaceous glands, meaning they produce an oily secretion called meibum. Their openings line the posterior lid margin, just behind the lash line. Meibum spreads across the surface of each blink to form the outermost, lipid layer of the tear film, which prevents the watery layer beneath it from evaporating too quickly. When meibomian gland openings become narrowed or plugged — a condition called meibomian gland dysfunction (MGD) — the glands cannot express their secretions normally. Over time, the backed-up meibum thickens, the gland enlarges, and the stage is set for a chalazion.
The glands of Zeis are small modified sebaceous glands that open into each eyelash follicle. When they become infected, the result is an external hordeolum. The glands of Moll are modified apocrine sweat glands also located at the lid margin, interdigitated between the lashes; infection here also produces an external hordeolum.
In chalazion pathophysiology, the sequence is: blocked meibomian gland opening → retained meibum → lipid leaks into the surrounding eyelid tissue (through rupture of the gland wall or gradual seepage) → macrophages and other immune cells recognize the lipid as foreign → a lipogranuloma forms. Under the microscope, a chalazion consists of lipid-laden macrophages (foam cells), lymphocytes, epithelioid histiocytes, and multinucleated giant cells surrounding a central lipid pool — the hallmark of a granulomatous reaction. There are no bacteria in a pure chalazion; it is entirely a sterile inflammatory process.
In hordeolum pathophysiology, bacteria — overwhelmingly Staphylococcus aureus, including in some cases methicillin-resistant strains (methicillin-resistant Staphylococcus aureus, MRSA) — colonize the gland, replicate rapidly, and trigger a classic suppurative (pus-forming) abscess. White blood cells rush to the site, pus accumulates, and the lesion either points and drains spontaneously or, if internal, may wall off and evolve into the sterile granuloma of a chalazion once the bacteria are cleared.
The key risk factors for both conditions overlap considerably. Blepharitis — chronic inflammation of the eyelid margins — is the single most common predisposing factor: it alters the quality of meibum, promotes bacterial overgrowth along the lid margin, and physically plugs gland openings with debris and crusting. Rosacea accelerates meibomian gland dysfunction through its inflammatory effects on skin and glands. Seborrhea (oily skin) clogs gland openings with excess sebum. Demodex folliculorum — a microscopic mite that lives in eyelash follicles and is nearly universal in older adults — disrupts the gland architecture and promotes blepharitis. Contact lens wear, high glycemic-index diets, chronic stress, and immunosuppression (from medication or systemic disease) all increase recurrence risk. Androgen deficiency, which reduces meibum production and alters its composition, may also contribute, particularly in postmenopausal women and men on androgen-deprivation therapy.
Clinical Features
Recognizing the presentation of each condition guides treatment decisions and helps identify the rare cases that need urgent evaluation.
Chalazion presentation: The typical chalazion appears as a painless or mildly tender firm nodule within the body of the upper or lower eyelid. It is usually 2 to 8 millimeters in diameter. Crucially, it does not sit at the lid margin — it points away from it, toward the inner eyelid surface (the tarsal conjunctiva). When you gently pinch the overlying skin, the nodule moves with the deeper tissue, indicating it is attached to the tarsal plate rather than to the skin itself. The overlying skin is usually normal in color, though it may be slightly pink early on. Everting the eyelid (flipping it inside-out to expose its inner surface) reveals a grey or yellow elevation at the site of the blocked meibomian gland.
Early in its formation (the first one to two weeks), a chalazion may be acutely tender, warm, and associated with some eyelid redness as the granuloma is establishing. This acute phase can be easily confused with an internal hordeolum. After the acute phase, the lesion becomes a firm, non-tender nodule that persists without further change for weeks to months. Larger chalazia can cause significant cosmetic concern or, as described above, ptosis and induced astigmatism with blurred vision. These size-related effects generally resolve after treatment.
Hordeolum presentation: A stye almost always begins with acute pain. The external hordeolum presents as a tiny tender swelling at the base of one eyelash, often with a small yellow pus point visible at its center within a day or two. The surrounding lid margin is red. It is like a pimple at the lash root — and indeed behaves similarly, with most pointing and draining within seven to fourteen days. An internal hordeolum is larger, deeper, and more diffusely painful — the entire inner lid may feel tender to touch, and the eyelid may swell significantly. There may be mild periorbital (around-the-eye) swelling. A low-grade fever is occasionally present with larger internal hordeola. Most internal hordeola either drain through the conjunctival surface on their own or evolve into a chalazion as described above.
Red flags that hospitals treat as urgent — the following signs are not features of a simple stye or chalazion; they are signs that hospitals and eye specialists assess the same day or in the emergency room:
- Proptosis — the eyeball appearing to protrude or push forward out of the socket
- Restricted or painful eye movement — difficulty or pain when trying to look in any direction
- Vision change — any blurring, double vision, or loss of vision that is new
- High fever (above 38.5°C / 101.3°F) combined with a red, swollen eyelid
- Rapidly spreading redness — erythema extending onto the cheek, forehead, or bridge of the nose beyond the eyelids
- Severe pain on eye movement
Any of these features suggests that what appeared to be a simple eyelid infection has spread behind the orbital septum into the eye socket itself — the dangerous condition of orbital cellulitis — which is a medical emergency requiring intravenous (IV) antibiotics and potentially surgery.
Diagnosis
In the vast majority of cases, a chalazion or stye is a clinical diagnosis — meaning a doctor can identify it by looking at and examining the eyelid. No blood tests, cultures, or imaging are needed for a typical presentation.
The examination includes inspection of the external eyelid (noting location, size, color, presence of a pus point), palpation (assessing firmness, tenderness, and whether the lesion is mobile), and eversion of the eyelid to inspect the inner surface. Visual acuity is usually checked if the lesion is large or the patient reports any blurring.
The most important diagnostic task is not distinguishing chalazion from stye — it is ruling out conditions that look similar but carry very different implications. The differential diagnosis includes:
- Sebaceous gland carcinoma (SGC) — the most important and dangerous mimic of a chalazion. SGC is a malignancy of the sebaceous glands of the eyelid and accounts for approximately 1–5% of all eyelid malignancies. It classically masquerades as a recurrent chalazion or persistent blepharitis. Doctors suspect SGC when: the "chalazion" is in an atypical location; the patient is elderly; there is associated loss of eyelashes (madarosis); the lesion recurs in exactly the same spot after surgical excision; or there is a yellowish, firm nodule with loss of the normal follicle details. Standard practice is to excise any atypical or recurrent chalazion in an older patient and send the tissue for histopathological examination.
- Preseptal (periorbital) cellulitis — diffuse warmth, redness, and tenderness of the entire eyelid, usually following a stye, minor trauma, or skin break; the eye itself moves normally and there is no proptosis. Requires oral or intravenous antibiotics, unlike a simple stye. Critical to distinguish from orbital cellulitis (behind the septum), which requires emergency management.
- Pyogenic granuloma — a rapidly growing, soft, vascular red nodule that bleeds easily. Often appears after minor trauma or following a stye or chalazion. Treated by excision or laser.
- Basal cell carcinoma and squamous cell carcinoma — slow-growing, pearly or scaly nodules; more likely at the lower lid margin in sun-exposed patients; do not fluctuate in size like infected lesions.
- Molluscum contagiosum — small, dome-shaped, umbilicated (centrally dimpled) nodules; viral; common in children; may appear on the lid margin and cause a follicular conjunctivitis.
- Dermoid cyst — smooth, non-inflamed, slowly enlarging cystic swelling, typically at the lateral upper orbital rim in children; present from birth but may not be noticed until adolescence.
- Dacryocystitis — infection of the lacrimal sac at the medial corner of the eye; produces a tender swelling at the medial canthal angle (inner corner), not within the eyelid body. Associated with tearing and discharge from the punctum.
When to image: computed tomography (CT) scanning of the orbits is indicated when orbital cellulitis is suspected (proptosis, restricted motility, vision change), when an abscess is suspected, or when a child fails to improve after 24 to 48 hours of appropriate intravenous antibiotics. Computed tomography is not indicated for a routine chalazion or stye.
Conservative Treatment — Warm Compresses and Lid Hygiene
Warm compresses are the standard first-line home treatment for both chalazia and styes. A 2017 Cochrane review found no controlled trials of non-surgical treatments for acute internal styes and no evidence for or against them, so warm compresses, lid cleaning and massage rest on long clinical practice rather than on trials. They are thought to work through two mechanisms: heat softens the thickened, stagnant secretions inside the blocked gland, making them more fluid and easier to express; and gentle warmth increases local blood flow, which supports the immune response.
How to apply warm compresses correctly:
- The usual practice is four sessions a day of at least 10 to 15 minutes each — not just briefly touching a warm cloth to the eye. Practitioners describe short, perfunctory applications as ineffective.
- The skin-surface temperature usually aimed for is 40 to 42°C (104 to 108°F) — warm, but not hot enough to burn the delicate eyelid skin. The simplest method is a clean cloth soaked in warm tap water, re-warmed as the water cools.
- Commercial microwaveable warm compress masks designed for eyelid use are heated briefly in a microwave and are made to hold their temperature for the full 10 to 15 minutes, which is the advantage they are sold on over a simple wet cloth.
- Each warm compress session is usually followed straight away by lid massage: a clean finger gently massages the eyelid with circular or sweeping motions directed toward the lid margin. This is meant to express the softened contents of the gland, and practitioners report that it can speed resolution. The pressure used is gentle, never painful.
Lid hygiene addresses the bacterial overgrowth and crusting along the lid margin that contribute to gland blockage. Cleansing options include:
- Hypochlorous acid lid spray (sold under several brand names) — a dilute solution of hypochlorous acid that kills bacteria and demodex without irritating the eye. It is sprayed onto a cotton pad or directly onto closed lids and wiped gently.
- Diluted baby shampoo — a classic option: a small amount of mild, no-tears baby shampoo is diluted in warm water, applied to a cotton ball or pad, gently scrubbed along the lid margins in a back-and-forth motion, and rinsed off. It is inexpensive and widely used, though slightly more irritating than hypochlorous acid.
- Pre-moistened lid wipes (several brands) — convenient for travel or patients who find the scrub technique difficult.
Expected timeline: An external stye typically ruptures and resolves within 7 to 14 days of diligent warm compresses. An internal hordeolum may take 2 to 4 weeks. A chalazion commonly takes 4 to 8 weeks for full resolution with conservative treatment — and some require 3 to 6 months. Practitioners continue warm compresses and lid hygiene for the entire duration, not just until the nodule shrinks slightly, and describe stopping too early as a cause of incomplete drainage and recurrence.
Squeezing or trying to pop a stye or chalazion carries a specific risk: squeezing introduces bacteria from the skin surface into the semi-closed space of an inflamed gland, which can convert a simple localized infection into preseptal cellulitis or, rarely, orbital cellulitis. The usual approach lets the process proceed at its own pace with warmth and gentle massage.
Medical Treatment
When conservative measures are insufficient, or when the underlying cause needs to be addressed to prevent recurrence, several medical treatments are available.
Topical antibiotics are indicated for an external hordeolum that has associated discharge or that appears to be causing early preseptal spread. Erythromycin ophthalmic ointment or bacitracin ointment applied to the lid margin three to four times daily for five to seven days reduces bacterial load and limits spread. Topical antibiotics do not reach meibomian glands in effective concentrations — they cannot penetrate to where a chalazion or internal hordeolum lives — so they are not useful for pure chalazion or uncomplicated internal hordeolum.
Oral doxycycline is one of the most useful medical treatments for patients with recurrent chalazia, particularly those who also have rosacea, blepharitis, or MGD. Doxycycline at low anti-inflammatory doses (50 mg once daily, or the sub-antimicrobial dose of 20 mg twice daily) taken for four to eight weeks reduces both the inflammatory response in the eyelid and, separately, alters meibum composition to make it less viscous and less likely to obstruct gland openings. It also has modest activity against staphylococci. Multiple studies have shown reduced recurrence rates with doxycycline in this population. Oral azithromycin is an alternative used in some centers. In a 2015 randomised trial of 110 people with MGD that had not improved with conservative care, a 5-day course of azithromycin (500 mg on day 1, then 250 mg a day) improved symptoms as much as one month of doxycycline 200 mg a day, and gave a better overall clinical response and better redness and eye-surface staining scores; mild stomach side effects were similar, except more with doxycycline at one visit.
Demodex-targeted treatment is used when examination reveals heavy demodex mite infestation (cylindrical dandruff at lash bases, collarettes). Options include:
- Ivermectin 1% cream applied to the lid margin nightly for several weeks, killing mites without eye irritation
- Oral ivermectin (200 mcg/kg single dose, repeated in two weeks) for severe or treatment-resistant cases
- Tea tree oil (TTO) 10% lid scrubs for maintenance after initial eradication — kills mites but irritates the cornea if it reaches it
- Lotilaner 0.25% eye drops — the first drug approved by the US Food and Drug Administration (FDA) for Demodex blepharitis. In two pivotal trials pooled together (833 people, drops twice a day for 6 weeks), mites were cleared in 60.2% of treated people vs 16.1% on a dummy drop, and the crusting at the lash base (collarettes) cleared to grade 0 in 49.8% vs 9.9%; adverse events were low, with no serious drug-related eye adverse events reported
- In-office thermal pulsation treatments for severe MGD with demodex component
Intralesional triamcinolone acetonide injection is a highly effective office-based treatment for persistent chalazia that have not responded to 4 to 6 weeks of warm compresses. The procedure involves injecting a small volume (0.1 to 0.2 mL) of triamcinolone acetonide (5 to 10 mg/mL concentration) directly into the body of the chalazion using a fine needle. The steroid suppresses the granulomatous inflammation, causing the lesion to shrink and resorb. In a 2011 randomised trial of 94 people with first-time chalazia, the injection cleared 81% (42 of 52) compared with 79% (33 of 42) for surgical incision and curettage; the average time to resolution after injection was 5 days, 92% needed only one injection, and no skin lightening, eye-pressure rise or vision loss was seen in either group. It is particularly preferred when the chalazion is in a cosmetically sensitive location where even a small scar from surgery would be objectionable (such as near the lacrimal punctum, or at the center of the lower eyelid). One important caution: in patients with darker skin tones, steroid injection carries a risk of producing a visible patch of skin hypopigmentation at the injection site that may persist for months — in such patients, surgical excision is usually chosen. Other risks include skin atrophy and, if the needle is misplaced anteriorly, inadvertent punctal occlusion.
Surgical Treatment — Incision and Curettage
Surgical incision and curettage (I&C) is the definitive treatment for chalazia that fail conservative management and steroid injection, and is the preferred initial treatment for large, vision-affecting, or cosmetically unacceptable lesions. It is a brief office procedure performed under local anesthesia with a very high success rate.
Indications for surgery:
- Chalazion larger than 3 to 4 mm that has not resolved after 4 to 8 weeks of diligent warm compresses
- Chalazion causing ptosis or induced astigmatism with blurred vision
- Cosmetically unacceptable lesion that the patient wants removed
- Recurrent chalazion in the same location (a biopsy is taken at the time of surgery as standard)
- Any atypical lesion where sebaceous gland carcinoma has not been ruled out
Internal (transconjunctival) approach — the most commonly used technique for chalazia. After local anesthetic injection into the eyelid, a chalazion clamp is applied to stabilize the lid and reduce bleeding. The eyelid is then everted to expose its inner (conjunctival) surface. A vertical incision is made through the conjunctiva directly into the body of the chalazion — vertical so that it runs parallel to the meibomian glands rather than across them. The granulomatous contents are curetted (scooped out) and sent for biopsy if there are any atypical features. The incision is typically not sutured — it heals spontaneously. An antibiotic ointment is applied post-procedure. The key advantage of the internal approach is that the incision is on the inner surface of the lid, leaving no visible scar on the skin.
External (transcutaneous) approach — used when the chalazion points anteriorly toward the skin surface, when it is firmly adherent to the skin, or when the surgeon prefers this approach for lower-lid lesions at certain locations. A small horizontal incision is made through the skin directly over the chalazion. The contents are evacuated and the incision closed with fine absorbable sutures. A small scar may be visible on the skin for several weeks but generally heals to an imperceptible line.
What to expect after I&C: The eyelid is typically bruised and swollen for 3 to 7 days post-procedure. An eye patch is sometimes worn for a few hours. Antibiotic ointment to the lid margin twice daily for 5 to 7 days reduces the small risk of secondary infection. Warm compresses can be resumed 48 hours post-operatively to help with residual swelling. Full healing typically takes 1 to 2 weeks.
Recurrence after I&C occurs in 10 to 20% of cases and almost always indicates that the underlying cause — most commonly MGD or blepharitis — has not been adequately addressed. In a 2024 review of the records of 649 patients who had chalazion surgery at one US hospital, fewer than one in three had a recurrence; recurrence was more likely in younger patients, in girls and women, and when more chalazia were drained. When a chalazion recurs in the same anatomical location after surgical excision, biopsy of the excised tissue is standard practice, as this is precisely the pattern associated with sebaceous gland carcinoma. This is why a chalazion that keeps coming back in the same spot is routinely biopsied.
Prevention and Management of Recurrence
For many patients, chalazia and styes are not one-time events — they recur, sometimes repeatedly, until the underlying predisposing factors are identified and controlled. Prevention efforts focus on the root cause, not just the bump.
Underlying blepharitis — since blepharitis is the single most common predisposing factor, its management is central to preventing recurrence. This is a chronic condition usually managed with permanent daily maintenance, not a short course of treatment. A typical regimen:
- Daily warm compress + lid massage (10 minutes every morning, indefinitely)
- Daily lid hygiene with hypochlorous acid spray or diluted baby shampoo
- Oral doxycycline 50 mg daily for 3 to 6 months in moderate-to-severe cases, then reassess
Rosacea — patients with rosacea have a dramatically elevated risk of chalazion formation because of its systemic effects on meibomian gland function. Management often involves a dermatologist: oral doxycycline, topical metronidazole or azelaic acid, avoidance of rosacea triggers (alcohol, spicy food, ultraviolet (UV) exposure), and sun protection all reduce the frequency of eyelid flares.
Demodex is treated when a heavy mite burden is contributing. When a child has molluscum contagiosum (another source of lid margin inflammation), household contacts are often treated too. The ivermectin or tea tree oil regimen described under Medical Treatment is the one used here.
Dietary measures with emerging evidence:
- Omega-3 fatty acid supplementation — fish oil, which supplies eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA), is widely used for meibomian gland dysfunction and dry eye, but the trial evidence is mixed. In the largest trial, the 2018 Dry Eye Assessment and Management (DREAM) study of 535 people with moderate-to-severe dry eye, 3,000 mg of EPA+DHA a day for 12 months did not improve symptoms more than an olive-oil placebo (symptom scores fell 13.9 and 12.5 points), and eye-surface staining, tear break-up time and the Schirmer tear test did not differ either. No trial of fish oil on chalazion recurrence was found.
- Refined carbohydrates and high-glycemic foods — some evidence suggests that high-glycemic dietary patterns may worsen sebaceous gland dysfunction, paralleling the diet-acne relationship; mechanistic data are not yet definitive, and practitioners describe cutting refined carbohydrates as a low-risk change.
- Adequate hydration — dehydration concentrates meibum and worsens tear film quality.
Contact lens hygiene — contact lens wear increases eyelid margin inflammation and bacterial colonization. For people who develop recurrent styes or chalazia while wearing contact lenses, the measures eye-care practitioners describe are daily disposable lenses (which eliminate the microbial biofilm that accumulates on reusable lenses), not sleeping in lenses, replacing the contact lens case monthly, and pausing lens wear during acute flares.
Signs that usually lead to a follow-up visit:
- No improvement after 4 to 8 weeks of consistent warm compresses
- Any enlargement of the lesion, especially rapid growth
- Vision change or blurring that persists beyond a few days
- Fever or redness spreading beyond the eyelid
- Third or subsequent recurrence in the same eyelid location — the point at which a biopsy is usually taken
- Eyelash loss (madarosis) near the lesion — a red flag for malignancy
Key Research Papers
The following peer-reviewed publications form the evidence base for the diagnosis and management of chalazion and hordeolum. Each citation closes with its PubMed record.
- Ben Simon GJ, Rosen N, Rosner M, Spierer A. "Intralesional triamcinolone acetonide injection versus incision and curettage for primary chalazia: a prospective, randomized study." Am J Ophthalmol. 2011;151(4):714–718.e1 — Demonstrated equivalent efficacy of steroid injection versus surgical I&C, supporting injection as a first-line alternative to surgery for primary chalazia. — PubMed PMID: 21257145
- Lederman C, Miller M. "Hordeola and chalazia." Pediatr Rev. 1999;20(8):283–284 — Practical review of eyelid infections in the pediatric population including diagnostic criteria and treatment thresholds. — PubMed PMID: 10429150
- Kashkouli MB, Fazel AJ, Kiavash V, Nojomi M, Ghiasian L. "Oral azithromycin versus doxycycline in meibomian gland dysfunction: a randomised double-masked open-label clinical trial." Br J Ophthalmol. 2015;99(2):199–204 — Randomized trial in 110 patients: both drugs improved symptoms equally; 5-day azithromycin gave better signs and a better overall clinical response than one month of doxycycline. — PubMed PMID: 25138765
- Lindsley K, Nichols JJ, Dickersin K. "Non-surgical interventions for acute internal hordeolum." Cochrane Database Syst Rev. 2017;1(1):CD007742 — No trials were identified; the review found no evidence for or against non-surgical treatments for internal styes. — PubMed PMID: 28068454
- Dry Eye Assessment and Management Study Research Group, Asbell PA, Maguire MG, Pistilli M, Ying GS, Szczotka-Flynn LB, Hardten DR, Lin MC, Shtein RM. "n-3 Fatty Acid Supplementation for the Treatment of Dry Eye Disease." N Engl J Med. 2018;378(18):1681–1690 — 535 patients; 3,000 mg EPA+DHA daily did not improve symptoms or signs more than olive-oil placebo over 12 months. — PubMed PMID: 29652551
- Yeu E, Paauw JD, Vollmer P, Berdy GJ, Whitson WE, Meyer J, Simmons B, Peterson JD, Periman LM, Boehmer BE, Bloomenstein MR, Whitley WO, Koetting C, Dhamdhere K, Neervannan S, Ciolino JB. "Safety and Efficacy of Lotilaner Ophthalmic Solution (0.25%) in Treating Demodex Blepharitis: Pooled Analysis of Two Pivotal Trials." Ophthalmol Ther. 2025;14(3):555–571 — 833 participants; mite eradication 60.2% vs 16.1% at day 43. — PubMed PMID: 39873946
- Sorensen R, Calderara G, Welsh J, Hick E, Hsiou D, Chen A, Hunt PJ, Mehta JJ, Allen RC, Williams K. "Age and number of lesions predict chalazion recurrence." Orbit. 2024;43(6):714–719 — Chart review of 649 surgical patients: younger age, female sex and more chalazia drained predicted recurrence. — PubMed PMID: 38861504