Merkel Cell Carcinoma
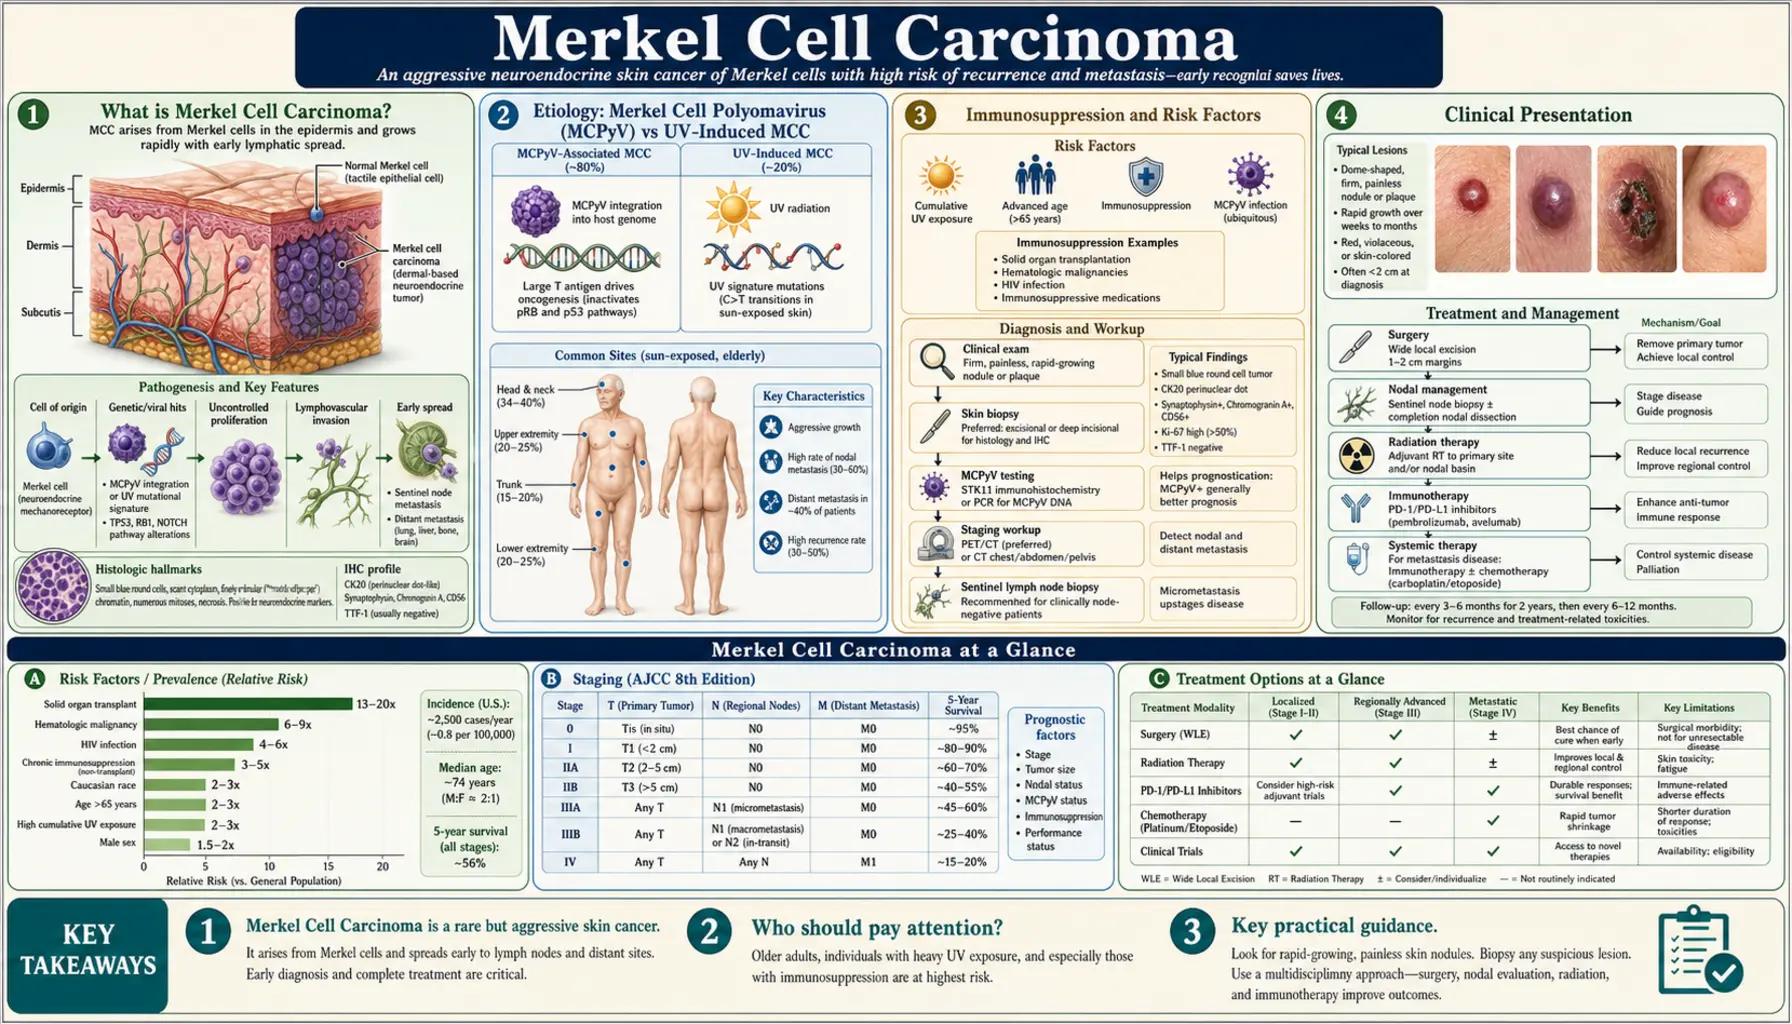
- Merkel Cell Carcinoma Explained
- Etiology: Merkel Cell Polyomavirus (MCPyV) vs Ultraviolet-Induced
- Immunosuppression and Risk Factors
- Clinical Presentation
- Diagnosis: Pathology, Immunohistochemistry, and Staging
- Treatment: Surgery, Radiation, and Sentinel Lymph Node Biopsy
- Immunotherapy: Avelumab, Pembrolizumab, and the Revolution in MCC
- Prognosis, Surveillance, and MCPyV Serology as Biomarker
- Special Populations: Immunocompromised Patients
- Key Research Papers
- Connections
Merkel Cell Carcinoma Explained
Merkel cell carcinoma (MCC) is a rare but highly aggressive neuroendocrine malignancy of the skin. It arises from Merkel cells — specialized mechanoreceptor cells located in the basal layer of the epidermis that play a role in light-touch sensation. These cells are thought to derive from either neural crest precursors or epidermal progenitors, and their malignant transformation produces a tumor with a distinctly high metastatic potential and substantial mortality.
A study of United States cancer-registry data (the Surveillance, Epidemiology, and End Results SEER-18 database, 6,600 cases) counted 2,488 new cases in 2013 and found that reported cases rose 95% from 2000 to 2013, compared with 57% for melanoma and 15% for all solid cancers. Because the population is aging, the authors projected 2,835 new cases a year in 2020 and 3,284 in 2025. Rising rates of immunosuppression (from organ transplantation and certain cancers) and greater clinical recognition are also described as contributors. Globally, MCC remains rare but is similarly trending upward.
MCC carries a worse prognosis than melanoma at equivalent stages. In an analysis of 9,387 cases that formed the basis of the American Joint Committee on Cancer (AJCC) 8th edition staging system, five-year overall survival was 51% for disease confined to the skin (local), 35% with spread to regional lymph nodes and 14% with distant spread. Historically, treatment outcomes were poor, but the advent of immunotherapy beginning in 2016–2018 transformed the management landscape for advanced MCC, producing durable responses in a meaningful fraction of patients.
The disease was first formally described in 1972 by pathologist Cyril Toker, who called it "trabecular carcinoma of the skin." Its neuroendocrine nature was subsequently clarified, and the discovery in 2008 of the Merkel cell polyomavirus (MCPyV) as a causal agent in approximately 80% of cases in Western populations marked a fundamental advance in understanding its biology.
Etiology: Merkel Cell Polyomavirus (MCPyV) vs Ultraviolet-Induced MCC
MCC arises through two biologically distinct pathways, distinguishable by the presence or absence of Merkel cell polyomavirus (MCPyV) integration in the tumor genome.
MCPyV-Positive MCC (approximately 80% of cases in the USA and Europe)
MCPyV was discovered in 2008 by Feng et al. and identified as a clonally integrated polyomavirus in the majority of MCC tumors. The mechanism involves monoclonal integration of truncated viral DNA into the host genome — a finding that serves as a molecular fingerprint of viral causation, since all tumor cells from a given patient carry the same integration site. The viral large T-antigen (LT-Ag) and small T-antigen (sT-Ag) function as oncoproteins, disrupting the Rb tumor suppressor pathway and activating translation and cell-cycle progression.
MCPyV is extraordinarily common in the general population — seroprevalence studies suggest that the majority of adults have been exposed by early adulthood, yet MCC develops only rarely. Additional cofactors — particularly immunosuppression and aging — are required for tumor development. In MCPyV-positive tumors, the mutational burden is relatively low, and viral T-antigen epitopes may serve as neoantigens that engage the immune system, which partly explains why these tumors respond well to immune checkpoint inhibitor therapy.
MCPyV-Negative MCC (approximately 20% of cases)
In MCPyV-negative MCC, the tumor arises through an ultraviolet-radiation-driven mutational mechanism more closely related to cutaneous squamous cell carcinoma. These tumors carry a high mutational burden, harbor ultraviolet-signature C→T transitions, and commonly show TP53 mutations and RB1 deletions. MCPyV-negative MCC is more common in patients of Asian or Pacific Islander ancestry and tends to occur in older, more heavily ultraviolet-exposed individuals. The biology overlaps more with carcinogen-driven epithelial cancers than with virus-driven neuroendocrine tumors.
The two subtypes are not always clinically distinguishable at presentation, but the distinction has biological significance: MCPyV serology can be used as a surveillance biomarker only in MCPyV-positive patients, and emerging data suggest differential responses to immune checkpoint inhibitors between the two groups.
Immunosuppression and Risk Factors
The single most important risk factor for MCC beyond age and ultraviolet (UV) exposure is immunosuppression. The immune system normally surveils and suppresses early MCC development, and any condition that compromises this surveillance dramatically amplifies risk:
- Chronic lymphocytic leukemia (CLL): In a study of 195 patients with MCC, CLL was more than 30-fold overrepresented among the patients. CLL impairs B-cell and T-cell immunity and is thought to permit MCPyV-driven tumor escape. The combination of CLL and MCC represents a particularly aggressive clinical scenario with poor outcomes.
- Solid organ transplantation: Recipients face a 10- to 30-fold increased risk. Maintenance immunosuppression (calcineurin inhibitors, mycophenolate) suppresses the T-cell immunity needed to control MCPyV-positive tumors. MCC in transplant recipients often presents at more advanced stages.
- Human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS): Approximately 13-fold elevated risk, particularly in patients with uncontrolled viremia and low CD4 counts. Antiretroviral therapy optimization can reduce risk.
- Primary immunodeficiency syndromes: Rare inherited conditions that impair T-cell function (e.g., DOCK8 deficiency) have been reported in association with MCC.
Beyond immunosuppression, established risk factors include:
- Ultraviolet radiation: Chronic sun exposure, particularly cumulative lifetime ultraviolet dose, is the dominant environmental driver. Geographic distribution of MCC follows ultraviolet exposure patterns. Tanning bed use has been associated with increased risk. Ozone depletion is believed to contribute to the rising incidence.
- Fair skin phenotype: Fair skin, blue or green eyes, and inability to tan are consistent risk features. MCC is rare in individuals of African descent, likely reflecting the protective effect of melanin.
- Age: The median age at diagnosis is approximately 76 years. MCC under age 50 is rare (less than 5% of cases) and may be associated with a higher prevalence of immunosuppression in younger patients who develop the disease.
- Male sex: Men account for approximately 60% of MCC cases for unclear reasons.
Clinical Presentation
MCC typically presents as a rapidly enlarging, flesh-colored to red-violet firm dermal nodule. The appearance is deceptively benign at initial presentation, often mistaken for a lipoma, inflamed epidermal inclusion cyst, or enlarged lymph node. In a study of 195 patients, Heath and colleagues summarized the most characteristic features at diagnosis with the acronym AEIOU; 89% of the primary tumors had 3 or more of them:
- A — Asymptomatic: painless, not tender (88% of tumors)
- E — Expanding rapidly: fast growth in the 3 months before diagnosis (63%)
- I — Immune suppression (profound immune suppression in 7.8% of the patients)
- O — Older than 50 years (90% of the patients)
- U — Ultraviolet-exposed site on a person with fair skin (81% of tumors arose on sun-exposed skin; 98% of the patients were white)
In the same study, 56% of tumors were red or pink, and 56% were thought to be harmless (benign) when they were biopsied — a cyst or acne-like lesion was the single most common guess (32%). The median delay from first appearance to biopsy was 3 months (range 1–54 months), and the median tumor diameter was 1.8 cm.
The anatomic distribution reflects ultraviolet exposure: approximately 50% of tumors arise on the head and neck (particularly the periorbital region and cheek), 40% on the extremities, and 10% on the trunk. A small fraction arise at sun-protected sites, and rare cases lack a primary cutaneous lesion (presenting with lymph node or visceral MCC alone, known as "unknown primary MCC").
Lymphatic spread is early and clinically silent. Even at presentation without palpable lymphadenopathy — so-called clinically node-negative disease — sentinel lymph node biopsy (SLNB) reveals occult lymph node metastases in approximately 30% of patients. Because of this high rate of hidden (occult) nodal disease, SLNB is standard practice for nearly all patients who are fit for surgery.
Staging follows the AJCC 8th edition system:
- Stage I: Primary tumor ≤2 cm, no nodal involvement — local disease (stages I and II together): 5-year overall survival 51%
- Stage II: Primary tumor >2 cm or with local invasion, no nodal involvement — included in the 51% local-disease figure
- Stage III: Regional lymph node involvement (either clinical or microscopic) — 5-year overall survival 35% (40% when the nodal spread was found only under the microscope, 27% when it could be detected on examination or scans)
- Stage IV: Distant metastases (most common: liver, lung, bone, brain) — 5-year overall survival 14%
The survival figures are from the 9,387-case national analysis behind the 8th edition system (cases diagnosed 1998–2012); overall survival counts deaths from any cause.
Diagnosis: Pathology, Immunohistochemistry, and Staging
The diagnosis of MCC requires skin biopsy with histopathologic evaluation and immunohistochemistry (IHC). Clinical suspicion alone is insufficient — MCC mimics many other conditions, and the histology is specific.
Histopathology
On hematoxylin and eosin staining, MCC appears as sheets or trabeculae of small round blue cells within the dermis, often extending into the subcutaneous fat. The cells have scant cytoplasm, finely dispersed ("salt-and-pepper") chromatin, inconspicuous nucleoli, and frequent mitotic figures. Geographic necrosis and lymphovascular invasion are common. The morphologic differential includes metastatic small-cell lung carcinoma, cutaneous lymphoma, Ewing sarcoma, and other small round blue cell tumors — IHC is required for distinction.
Immunohistochemistry
The IHC panel for MCC is distinctive:
- CK20 (cytokeratin 20): Positive in approximately 90–95% of MCC, characteristically in a perinuclear dot-staining pattern — a paranuclear cytoplasmic globule that is nearly pathognomonic of MCC among small round blue cell tumors.
- CAM5.2: Low-molecular-weight cytokeratin, positive in MCC.
- Synaptophysin and chromogranin A: Neuroendocrine markers, positive in most MCC — confirm the neuroendocrine lineage.
- CD56 (neural cell adhesion molecule, NCAM): Also frequently positive.
- CK7 (cytokeratin 7): Negative in MCC — the most important distinguishing feature from metastatic small-cell lung carcinoma (SCLC), which is CK7-positive and CK20-negative. The CK7−/CK20+ pattern is the IHC fingerprint of MCC.
- TTF-1 (thyroid transcription factor-1): Negative in MCC; positive in SCLC — provides additional distinction from metastatic pulmonary disease.
MCPyV status can be assessed by IHC using the CM2B4 antibody (directed against the large T-antigen) or by quantitative polymerase chain reaction (PCR) of tumor DNA.
Workup and Staging
Complete staging workup includes:
- SLNB: Standard practice for surgically fit patients with clinically node-negative disease. Where available, positron emission tomography (PET)/computed tomography (CT) is commonly done before SLNB, since positron emission tomography may identify nodal or distant disease that renders SLNB moot.
- Computed tomography chest/abdomen/pelvis: For systemic staging.
- Positron emission tomography/computed tomography: Superior sensitivity for nodal and distant disease; upstages 10–15% of patients beyond conventional computed tomography alone; preferred if available.
- Brain magnetic resonance imaging (MRI): For patients with neurological symptoms or stage IV disease.
- MCPyV serology (anti-T-antigen antibody titer): Obtained at baseline for all patients; useful as a surveillance biomarker in MCPyV-positive disease.
Treatment: Surgery, Radiation, and Sentinel Lymph Node Biopsy
For localized and regionally confined MCC, treatment combines surgical excision, sentinel lymph node evaluation, and adjuvant radiation therapy. MCC is highly radiosensitive — a property that distinguishes it from many other skin cancers and makes radiation central to both adjuvant and definitive treatment strategies.
Surgery
Wide local excision with 1–2 cm margins is the standard surgical approach. Unlike melanoma, Mohs micrographic surgery does not confer a clear advantage in local control and is not routinely used. The surgical goal is microscopically clear margins. Local recurrence after surgery alone has been reported at approximately 40% in some series, which is why adjuvant radiation is widely used in patients fit for it; in a single-center study of 171 patients, 3-year local control was 91.2% with radiation therapy versus 76.9% without. The risk depends on the tumor: in a University of Michigan series of 105 primary tumors smaller than 2 cm treated with surgery alone, without radiation to the primary site, only 1 true local recurrence occurred, and the authors questioned the need for radiation to the primary site for small, low-risk tumors.
Sentinel Lymph Node Biopsy
SLNB is performed at the time of or shortly after primary excision. The 30% rate of occult nodal disease in clinically node-negative (N0) patients makes SLNB the most important staging procedure in MCC. A positive SLNB upstages the patient to Stage III and mandates treatment of the regional nodal basin — either complete lymph node dissection (CLND) or regional radiation therapy (increasingly preferred over CLND due to equivalent regional control and lower morbidity).
Adjuvant Radiation Therapy
Adjuvant radiation to the primary site and regional nodal basin dramatically reduces locoregional recurrence — from approximately 40% to under 10% in most series. Intensity-modulated radiation therapy (IMRT) is preferred for its ability to deliver precise doses while minimizing exposure to surrounding structures. Typical doses are 50–56 Gy to the primary site and 45–50 Gy to regional nodes.
For patients who are medically inoperable, definitive radiation therapy alone achieves excellent local control and represents a legitimate curative-intent strategy for localized MCC.
Adjuvant Systemic Therapy
Platinum-based chemotherapy (carboplatin or cisplatin + etoposide) was historically used in the adjuvant setting but has never demonstrated improved survival in randomized trials and is no longer recommended routinely. Adjuvant immune checkpoint inhibition is under active investigation; this remains an evolving area and is not yet universally incorporated into guidelines.
The first randomized trial of adjuvant immunotherapy, ADMEC-O, enrolled 179 people with completely removed MCC at 20 academic centers in Germany and the Netherlands and assigned them to one year of nivolumab (118 people) or observation (61 people). Disease-free survival was 85% at 12 months and 84% at 24 months with nivolumab, versus 77% and 73% with observation, but the difference was not statistically certain (hazard ratio 0.58, 95% confidence interval 0.30–1.12), and adjuvant radiotherapy was more common in the observation group. Serious (grade 3–4) side effects occurred in 42% of the people given nivolumab and in 11% of those under observation; no treatment-related deaths were reported, and overall survival data were not yet mature at this interim analysis.
Immunotherapy: Avelumab, Pembrolizumab, and the Revolution in MCC
The development of immune checkpoint inhibitors targeting the PD-1/PD-L1 axis transformed MCC from a disease with dismal outcomes in the metastatic setting to one in which durable complete remissions are achievable in a meaningful fraction of patients. MCC was, in many ways, an ideal tumor for immunotherapy: it carries viral neoantigens (in MCPyV-positive cases), often expresses PD-L1, and is associated with states of immune deficiency that checkpoint inhibition can potentially reverse.
Pembrolizumab
Pembrolizumab — a humanized anti-PD-1 monoclonal antibody — received U.S. Food and Drug Administration (FDA) approval in December 2018 for the treatment of adult and pediatric patients with recurrent locally advanced or metastatic MCC based on the KEYNOTE-017 trial. In this single-arm phase 2 trial of 50 patients with advanced MCC who had not received prior systemic therapy, pembrolizumab achieved an objective response rate (ORR) of 56%, including 24% complete responses (59% in virus-positive and 53% in virus-negative tumors). Responses were durable — at a median follow-up of 14.9 months, the median duration of response had not been reached (responses lasted from 5.9 to more than 34.5 months). The 24-month progression-free survival rate was 48.3% and the 24-month overall survival rate 68.7%. Serious (grade 3 or higher) treatment-related side effects occurred in 28% of patients, including one treatment-related death. Pembrolizumab is widely used as a first-line treatment for advanced MCC.
Avelumab
Avelumab — an anti-PD-L1 antibody — received U.S. Food and Drug Administration approval in March 2017, becoming the first immunotherapy approved for MCC. Approval was based on the JAVELIN Merkel 200 trial, a phase 2 study of 88 patients with chemotherapy-refractory metastatic MCC. In the first report (median follow-up 10.4 months), 28 of 88 patients (31.8%) responded, including 8 complete responses. After at least 1 year of follow-up, the confirmed objective response rate was 33.0%, with 11.4% complete responses; 1-year progression-free survival was 30%, 1-year overall survival was 52%, and an estimated 74% of responses lasted at least 1 year. The trial excluded people with HIV, immunosuppression, blood cancers (haematological malignancies) or a previous organ transplant, so its results come only from people with a working immune system, not from the immunocompromised patients covered in the Special Populations section below.
In part B of the same trial, avelumab was given as the first treatment for distant metastatic MCC. In a preplanned interim analysis of 29 patients with at least 3 months of follow-up, the confirmed objective response rate was 62.1%, with 14 of 18 responses still ongoing; no treatment-related deaths or grade 4 side effects occurred. In the full group of 116 patients followed for a median of 54.3 months, median overall survival was 20.3 months and 38% were alive at 4 years (PubMed PMID: 38744102; see Avelumab).
Nivolumab
In the MCC group of the CheckMate 358 trial — 68 patients with recurrent or metastatic MCC who had not received immunotherapy before and had 0–2 earlier systemic treatments — nivolumab (anti-PD-1) alone produced an objective response rate of 60% in 25 patients, with a median response duration of 60.6 months. Though not U.S. Food and Drug Administration-approved for MCC, it provides an additional anti-PD-1 option and is used off-label at some centers.
In the same 2025 report, adding ipilimumab to nivolumab (43 patients) did not improve responses (58% versus 60%) and caused more serious (grade 3/4) treatment-related side effects (47% versus 28%); the authors noted that this contradicted earlier, smaller reports that had suggested a benefit from the combination.
Retifanlimab
Retifanlimab, another anti-PD-1 antibody, received U.S. Food and Drug Administration approval in March 2023; its label covers adults with metastatic or recurrent locally advanced MCC. In its phase 2 trial (POD1UM-201) of 101 patients who had not received earlier systemic treatment, 54.5% responded, including 17.8% complete responses; the median progression-free survival was 16.0 months, and 63% of patients were alive at 3 years. Serious (grade 3) immune-related side effects occurred in 10.9% of patients.
Comparison with Prior Chemotherapy
Prior to immunotherapy, first-line systemic treatment for advanced MCC consisted of platinum-based doublet chemotherapy (carboplatin or cisplatin + etoposide). Response rates of 50–60% were achieved, but responses were almost uniformly transient, with a median duration of approximately 3 months and no demonstrated improvement in overall survival. Chemotherapy is now reserved for immunotherapy-refractory patients or situations where rapid debulking is needed while awaiting immunotherapy response.
Biology of Response
MCPyV-positive tumors may respond better to checkpoint inhibition because viral T-antigen peptides serve as tumor-specific neoantigens, generating a pre-existing immune response that checkpoint blockade can amplify. MCPyV-negative tumors, with their higher mutational burden, also respond but outcomes may be somewhat more heterogeneous. PD-L1 expression on tumor cells is common in MCC and correlates with response in some analyses, but is not routinely used to select patients for therapy.
Prognosis, Surveillance, and MCPyV Serology as Biomarker
MCC has a high recurrence rate — approximately 40–50% of patients experience disease recurrence, most commonly within the first two years after diagnosis. Locoregional recurrence (local skin, in-transit lesions, regional nodes) is the most common pattern in early-stage disease; distant recurrence affects the liver, lung, bone, and brain in advanced cases.
MCPyV Antibody Titer as a Surveillance Biomarker
One of the most valuable and novel features of MCC — unique among skin cancers — is the use of MCPyV oncoprotein antibody titers as a real-time biomarker of tumor burden in MCPyV-positive patients. Antibodies against the MCPyV small T-antigen and large T-antigen (measurable with a clinical oncoprotein-antibody blood test) are detectable at baseline in the majority of MCPyV-positive MCC patients. In a prospective study of 219 newly diagnosed patients, these antibodies were present in 52% of the patients but in only 1% of healthy people. Key clinical principles:
- A high titer at diagnosis indicates active MCPyV-positive tumor and establishes a baseline for monitoring.
- A falling titer after treatment correlates with effective tumor clearance; in seropositive patients whose disease did not come back, titers fell quickly and became negative by a median of 8.4 months.
- A rising titer during surveillance is an early signal of recurrence that can precede radiographic or clinical detection by weeks to months, enabling earlier intervention. In the 219-patient study, among 71 seropositive patients tested repeatedly (282 time points), a rising titer had a positive predictive value of 66% for clinically evident recurrence, and a falling titer had a negative predictive value of 97%.
- Patients who are MCPyV-seronegative at diagnosis either have MCPyV-negative tumors or are immunologically unable to mount an antibody response; serology cannot be used for surveillance in these patients. Antibody status at diagnosis is itself a risk signal: having the antibodies predicted a lower risk of recurrence (hazard ratio 0.58) after adjustment for age, sex, stage and immunosuppression, so seronegative patients form the higher-risk group, in whom the study authors note that scans may play a more prominent role.
Surveillance Schedule
Standard post-treatment surveillance includes:
- History and physical examination every 3–6 months for the first 3 years, then annually thereafter
- Cross-sectional imaging (computed tomography chest/abdomen/pelvis or positron emission tomography (PET)/computed tomography) every 6–12 months for 3 years
- MCPyV antibody titers at each visit in seropositive patients
- Skin examination at each visit, with particular attention to the primary site, in-transit lymphatics, and regional nodes
Distant recurrence beyond 5 years is uncommon but documented; lifelong awareness of recurrence risk is warranted for survivors.
Special Populations: Immunocompromised Patients
Immunocompromised patients represent the highest-risk subgroup in MCC and pose distinct management challenges. They account for a disproportionate fraction of MCC cases and face uniformly worse outcomes compared to immunocompetent patients:
- More advanced stage at presentation
- Higher rates of locoregional and distant recurrence
- Shorter disease-specific and overall survival
- Reduced immune response to checkpoint inhibitor therapy in some subgroups
Solid Organ Transplant Recipients
Checkpoint inhibitor use in transplant recipients carries significant risk of allograft rejection, mediated by T-cell activation against both tumor and allograft. Case reports and series document rates of rejection of 40–50% in solid organ transplant recipients receiving anti-PD-1/PD-L1 therapy. Management requires careful multidisciplinary discussion between oncology and transplant medicine. Reduction of immunosuppression — if clinically feasible without threatening the allograft — may improve immune surveillance. In some patients, the risk-benefit calculation favors immunotherapy despite transplant risk; in others, radiation and surgery without systemic immunotherapy may be the preferred approach.
Patients with CLL
CLL + MCC is a particularly aggressive combination. CLL-directed therapies, particularly Bruton tyrosine kinase inhibitors (ibrutinib, acalabrutinib), may inadvertently modulate immune function in ways that affect MCC biology. Ibrutinib has complex immunologic effects — it suppresses some pathologic B-cell activity while potentially impairing T-cell function. Whether CLL-directed therapy improves or worsens MCC outcomes in individual patients requires careful case-by-case assessment. Checkpoint inhibitors may be used in CLL + MCC but clinical trial data specific to this population are limited.
Human Immunodeficiency Virus-Positive Patients
In human immunodeficiency virus-positive patients, optimization of antiretroviral therapy to achieve viral suppression and immune reconstitution is a critical adjunct to MCC-directed therapy. Immune reconstitution can restore the T-cell surveillance that normally suppresses MCPyV-driven tumor growth, and some patients have experienced tumor regression with antiretroviral therapy alone. Checkpoint inhibitors appear to be safe in human immunodeficiency virus-positive patients with well-controlled viral loads, though prospective data in MCC specifically are limited.
Key Research Papers
- Feng H et al. "Clonal integration of a polyomavirus in human Merkel cell carcinoma." Science. 2008;319(5866):1096–100. — PubMed PMID: 18202256
- Nghiem PT et al. "PD-1 Blockade with Pembrolizumab in Advanced Merkel-Cell Carcinoma." N Engl J Med. 2016;374(26):2542–52. — PubMed PMID: 27093365
- Kaufman HL et al. "Avelumab in patients with chemotherapy-refractory metastatic Merkel cell carcinoma." Lancet Oncol. 2016;17(10):1374–85. — PubMed PMID: 27592805
- Becker JC et al. "Merkel cell carcinoma." Nat Rev Dis Primers. 2017;3:17077. — PubMed PMID: 29072302
- Nghiem P et al. "Durable Tumor Regression and Overall Survival in Patients With Advanced Merkel Cell Carcinoma Receiving Pembrolizumab as First-Line Therapy." J Clin Oncol. 2019;37(9):693–702. — PubMed PMID: 30726175
- Bhatia S et al. "Nivolumab With or Without Ipilimumab in Patients With Recurrent or Metastatic Merkel Cell Carcinoma: A Nonrandomized, Open-Label, International, Multicenter Phase I/II Study." J Clin Oncol. 2025;43(9):1137–1147. — PubMed PMID: 39889250
- Lemos B et al. "Pathologic nodal evaluation improves prognostic accuracy in Merkel cell carcinoma." J Am Acad Dermatol. 2010;63(5):751–61. — PubMed PMID: 20646783
- Strom T et al. "Radiation Therapy is Associated with Improved Outcomes in Merkel Cell Carcinoma." Ann Surg Oncol. 2016;23(11):3572–3578. — PubMed PMID: 27251134
- Paulson KG et al. "Antibodies to merkel cell polyomavirus T antigen oncoproteins reflect tumor burden in merkel cell carcinoma patients." Cancer Res. 2010;70(21):8388–97. — PubMed PMID: 20959478
- Albores-Saavedra J et al. "Merkel cell carcinoma demographics, morphology, and survival based on 3870 cases: a population based study." J Cutan Pathol. 2010;37(1):20–7. — PubMed PMID: 19638070
- Pectasides D et al. "Merkel cell cancer of the skin." Ann Oncol. 2006;17(10):1489–95. — PubMed PMID: 16565213
- Heath M et al. "Clinical characteristics of Merkel cell carcinoma at diagnosis in 195 patients: the AEIOU features." J Am Acad Dermatol. 2008;58(3):375–81. — PubMed PMID: 18280333
- Harms KL et al. "Analysis of Prognostic Factors from 9387 Merkel Cell Carcinoma Cases Forms the Basis for the New 8th Edition AJCC Staging System." Ann Surg Oncol. 2016;23(11):3564–3571. — PubMed PMID: 27198511
- Paulson KG et al. "Merkel cell carcinoma: Current US incidence and projected increases based on changing demographics." J Am Acad Dermatol. 2018;78(3):457–463.e2. — PubMed PMID: 29102486
- Frohm ML et al. "Recurrence and Survival in Patients With Merkel Cell Carcinoma Undergoing Surgery Without Adjuvant Radiation Therapy to the Primary Site." JAMA Dermatol. 2016;152(9):1001–7. — PubMed PMID: 27248515
- Kaufman HL et al. "Updated efficacy of avelumab in patients with previously treated metastatic Merkel cell carcinoma after ≥1 year of follow-up: JAVELIN Merkel 200, a phase 2 clinical trial." J Immunother Cancer. 2018;6(1):7. — PubMed PMID: 29347993
- D'Angelo SP et al. "Efficacy and Safety of First-line Avelumab Treatment in Patients With Stage IV Metastatic Merkel Cell Carcinoma: A Preplanned Interim Analysis of a Clinical Trial." JAMA Oncol. 2018;4(9):e180077. — PubMed PMID: 29566106
- Becker JC et al. "Adjuvant immunotherapy with nivolumab versus observation in completely resected Merkel cell carcinoma (ADMEC-O): disease-free survival results from a randomised, open-label, phase 2 trial." Lancet. 2023;402(10404):798–808. — PubMed PMID: 37451295
- Paulson KG et al. "Viral oncoprotein antibodies as a marker for recurrence of Merkel cell carcinoma: A prospective validation study." Cancer. 2017;123(8):1464–1474. — PubMed PMID: 27925665
- Grignani G et al. "Phase II study of retifanlimab in patients with recurrent locally advanced or metastatic Merkel cell carcinoma (POD1UM-201)." J Immunother Cancer. 2025;13(8):e012478. — PubMed PMID: 40796223