Folliculitis
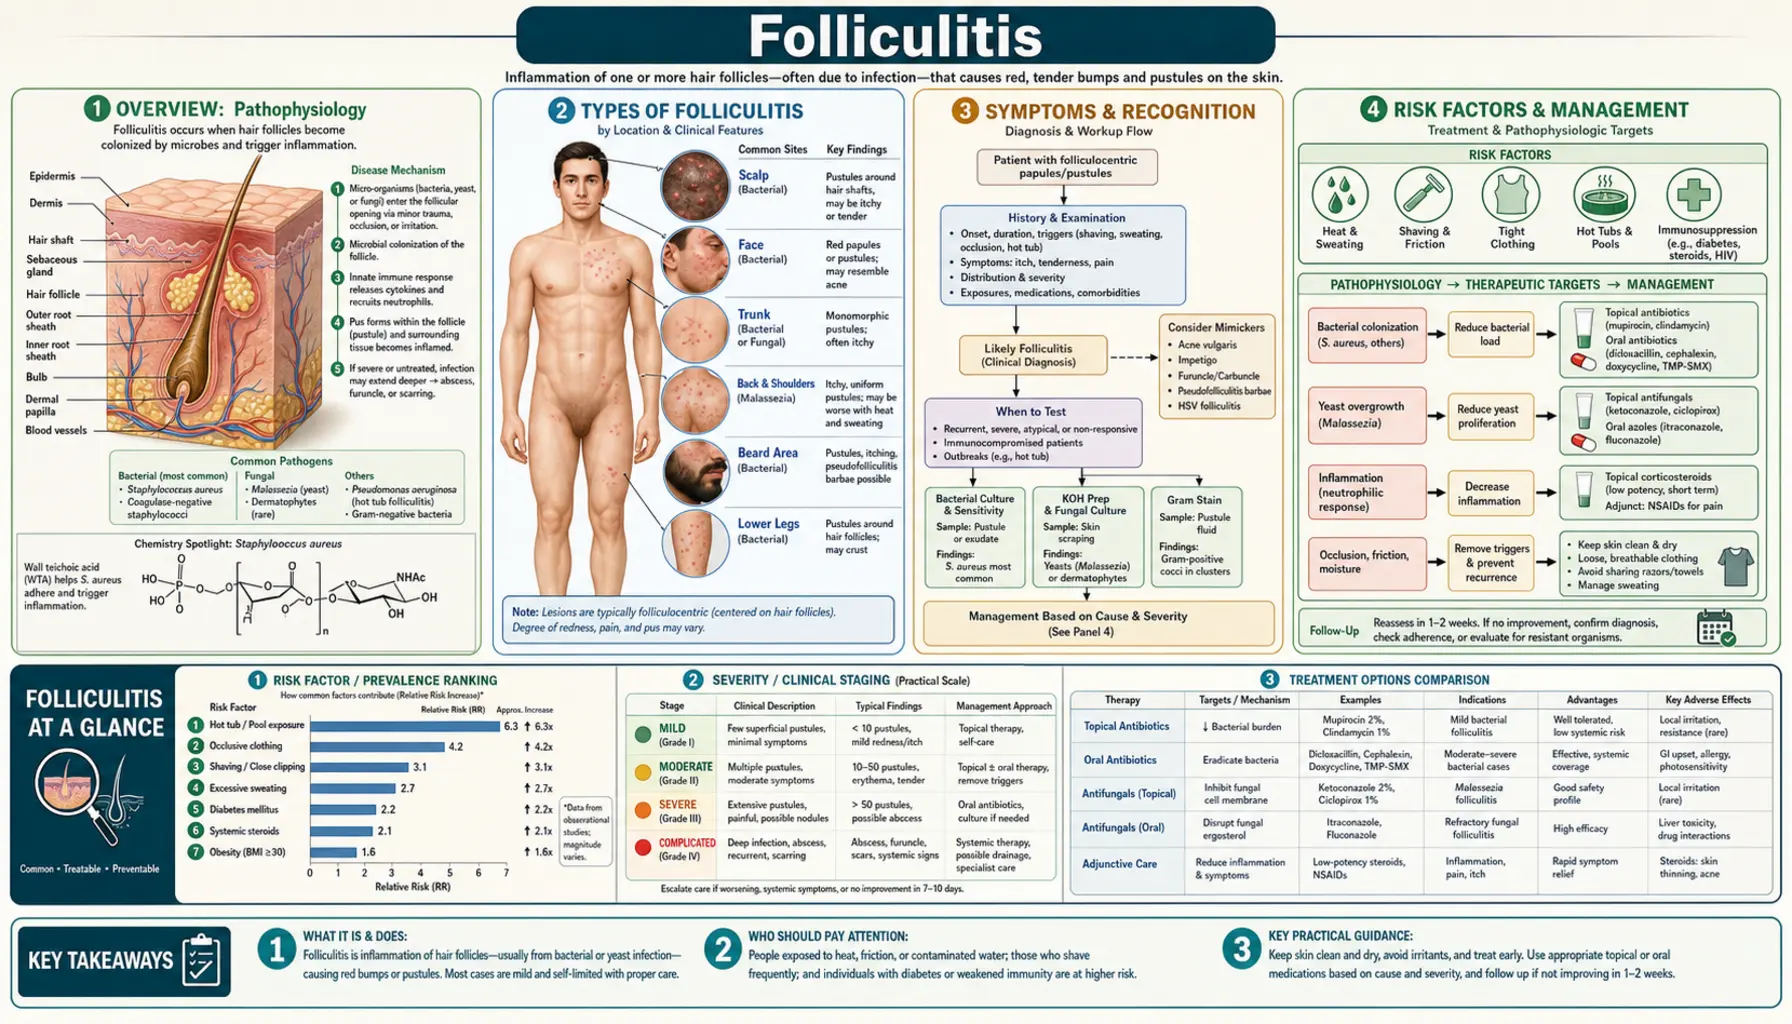
Table of Contents
Overview
Folliculitis is inflammation of one or more hair follicles — the tiny pockets in the skin from which each hair grows. It is one of the most common skin conditions worldwide, estimated to affect more than one billion people at some point in their lives. Folliculitis can occur anywhere hair grows on the body: the scalp, face, neck, chest, back, buttocks, and legs are all frequent sites.
Most cases are caused by bacteria, with Staphylococcus aureus being the most common culprit. However, folliculitis can also be triggered by fungi (most often Malassezia yeast), viruses, parasites, or non-infectious causes such as ingrown hairs and hot-tub exposure. The condition ranges from a mild, self-resolving nuisance — small red bumps that clear up on their own — to deeper, painful infections such as boils and carbuncles that require medical treatment.
Because folliculitis looks similar to several other skin conditions, it is frequently misdiagnosed. Malassezia folliculitis (a fungal form) is routinely mistaken for acne, and treating it with antibiotics actually makes it worse. Which type of folliculitis is present decides which treatment works.
Types of Folliculitis
Bacterial Folliculitis
The vast majority of folliculitis cases are bacterial, and Staphylococcus aureus is the organism responsible for most of them.
Superficial folliculitis (Bockhart's impetigo) is the most common form. A small pustule forms right at the follicle opening with the hair shaft visible at its center. The surrounding skin is slightly red but the infection stays shallow and usually clears within 1–2 weeks with basic care.
Deep folliculitis involves the entire hair follicle. When a single follicle becomes deeply infected it forms a furuncle (boil) — a painful, swollen nodule 1–5 cm across with a tender fluctuant center and a central yellowish plug. When several adjacent follicles fuse into one large interconnected infection the result is a carbuncle, which has multiple drainage points, causes significant pain, and often produces fever and general malaise, signs that doctors treat as needing prompt care.
Gram-negative folliculitis is a less obvious form that paradoxically develops after prolonged antibiotic therapy for acne. Long-term antibiotics wipe out the normal skin flora that kept gram-negative bacteria (such as E. coli, Klebsiella, Enterobacter, and Proteus) in check. The result is a pustular flare concentrated around the nose and chin that looks like worsening acne but does not respond to standard acne antibiotics.
Sycosis barbae is a chronic, deep staphylococcal folliculitis confined to the beard area in men. It presents as recurring, tender papules and pustules in the mustache and beard area and can be difficult to eradicate without addressing methicillin-resistant Staphylococcus aureus (MRSA) carrier status.
Pseudomonas (Hot Tub) Folliculitis
Pseudomonas aeruginosa thrives in warm, improperly chlorinated water — hot tubs, whirlpool baths, water parks, and swimming pools. Exposure to contaminated water allows the bacteria to enter follicles. Symptoms appear 1–2 days after exposure: itchy red bumps and pustules concentrated on the trunk and buttocks (the areas covered by a bathing suit). A concurrent ear infection (swimmer's ear) may develop at the same time.
In healthy people, hot tub folliculitis is self-limiting and resolves without treatment in 1–2 weeks. The key clue is the cluster exposure — if multiple people who shared the same hot tub all break out simultaneously, Pseudomonas is almost certainly the cause.
Fungal (Malassezia) Folliculitis
A full article covers this form: Malassezia Folliculitis: The Yeast Behind Fungal Acne.
Malassezia furfur (also called Pityrosporum) is a yeast that normally lives on human skin. Under the right conditions — heat, sweating, occlusive clothing, oily skin, or antibiotic use — it overgrows inside follicles and triggers inflammation.
Malassezia folliculitis presents as uniformly sized itchy pustules on the upper back, chest, and shoulders. This monomorphic appearance — all bumps look exactly alike — is an important distinguishing feature from ordinary acne, which has mixed lesions (blackheads, whiteheads, and inflamed spots of varying sizes). Antibiotics worsen Malassezia folliculitis by killing the bacteria that compete with the yeast, so the diagnosis matters before treatment starts. A good response to antifungal treatment is one of the findings that supports the diagnosis.
Malassezia folliculitis is often called "fungal acne." A 2026 review (Draelos and colleagues) reports that it is more common in people diagnosed with acne than in the general population, that its risk factors include hot, humid weather, blocked hair follicles and a weakened immune system, and that because it looks like acne it is often misdiagnosed and can persist for years. A 2025 review (Chalupczak and Lipner) cites a study of 110 patients with confirmed Malassezia folliculitis in which 75% had already been treated for acne without success.
Pseudofolliculitis Barbae (Razor Bumps)
Pseudofolliculitis barbae is not an infection at all — it is a mechanical, inflammatory reaction. After shaving, naturally curly or coily hair shafts re-enter the skin near the follicle opening rather than growing outward. The immune system treats the embedded hair as a foreign body and mounts an inflammatory response, producing painful red bumps and, over time, post-inflammatory hyperpigmentation and scarring.
This condition affects an estimated 45–85% of Black men and up to 30% of Black women who shave, though it can affect anyone with curly hair. The chin, neck, and bikini line are the most commonly affected sites.
Viral Folliculitis
Herpes simplex virus can infect hair follicles, producing clusters of vesicles (blisters) around the mouth or genital area that are sometimes mistaken for bacterial folliculitis. Demodex mites (microscopic skin mites), which play a central role in rosacea, can also cause a folliculitis-like eruption, particularly in immunocompromised individuals.
Symptoms and Recognition
The hallmark of folliculitis in any form is that the bumps are centered on hair follicles. A hair shaft emerging from the center of a bump is the single most reliable sign of folliculitis rather than another skin condition.
Superficial folliculitis produces small red papules (bumps) or white-headed pustules at the follicle opening. They are mildly tender or itchy, surrounded by a thin ring of redness, and usually no larger than a few millimeters. Most people notice them on the legs after shaving, on the scalp, or on the back.
Deep folliculitis is more dramatic. A furuncle starts as a firm, tender nodule that grows over 4–7 days into a fluctuant (fluid-filled) swelling. A yellow or white central point eventually forms as pus accumulates. Carbuncles are larger, deeper, and accompanied by systemic signs: fever, chills, and fatigue.
Where on the body the bumps appear is an important clue to the cause:
- Scalp: staphylococcal folliculitis in adults; tinea capitis (ringworm) in children; dissecting cellulitis of the scalp in severe cases
- Face and beard area: sycosis barbae, pseudofolliculitis barbae, viral folliculitis
- Upper back and chest: Malassezia folliculitis (most likely), staphylococcal folliculitis
- Trunk and buttocks: hot tub folliculitis (especially after a cluster exposure)
- Thighs and buttocks: staphylococcal folliculitis from friction and occlusion
- Lower legs: post-shaving folliculitis; gram-negative folliculitis after waxing
Eosinophilic folliculitis is a distinct form seen in people with human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS) or other immunocompromising conditions, and in newborns. It produces intensely itchy, recurrent eruptions with a high eosinophil count in the blood. A skin biopsy showing eosinophilic infiltrates around the follicle confirms the diagnosis.
Risk Factors
Factors That Raise Bacterial Risk
- Breaks in the skin barrier — cuts, abrasions, insect bites, or eczema allow bacteria to enter follicles
- Friction and occlusion — tight clothing, thigh rubbing, and equipment straps trap heat and moisture
- Shaving, waxing, and plucking — all disrupt the follicle opening temporarily
- Acne — inflamed follicles are already compromised
- Immunosuppression — diabetes, human immunodeficiency virus, corticosteroid use, and chemotherapy all impair the skin's ability to fight bacterial invasion
- Methicillin-resistant Staphylococcus aureus carrier status — nasal methicillin-resistant Staphylococcus aureus carriage is a major source of recurrent skin infections
- Contact sports — wrestling in particular carries a high risk of skin-to-skin bacterial transmission ("wrestler's impetigo")
Factors That Raise Fungal Risk
- Antibiotic use — oral antibiotics reduce bacterial competition and allow yeast to proliferate
- Hot, humid climates and heavy sweating
- Occlusive synthetic fabrics — trap heat and moisture against the skin
- Oily skin — Malassezia feeds on fatty acids in sebum
Factors That Raise Hot Tub Risk
- Using hot tubs, whirlpools, or pools with inadequate chlorination or pH control
- Extended time in the water — longer exposure means more bacterial entry
Factors That Raise Pseudofolliculitis Risk
- Naturally curly or coily hair — the strongest single risk factor
- Shaving very closely or against the grain
- Multi-blade razors — each additional blade cuts the hair below the skin surface, making re-entry more likely
- Tight collars and waistbands — the friction drives hair ends back into the skin
Occupational Risks
- Oil and grease workers — mineral oil blocks follicles mechanically (oil folliculitis)
- Healthcare workers — higher methicillin-resistant Staphylococcus aureus exposure
Diagnosis
Most folliculitis is diagnosed clinically — a combination of the appearance of the lesions, where they are located, and the patient's history is usually enough to reach the right diagnosis. No testing is needed for a straightforward, first-time, mild case.
Additional testing becomes important when:
- Folliculitis is recurrent or treatment is not working
- Methicillin-resistant Staphylococcus aureus is suspected (recent hospitalization, household contacts with skin infections, known methicillin-resistant Staphylococcus aureus history)
- The diagnosis is uncertain
- Systemic symptoms (fever, swollen lymph nodes) are present
Tests Used
- Bacterial culture: A swab of the contents of a pustule shows which bacteria are present and which antibiotics work against them. It is the standard test for suspected methicillin-resistant Staphylococcus aureus and for treatment failures.
- Potassium hydroxide (KOH) preparation: A quick microscopy test where skin scrapings or the pustule contents are dissolved in potassium hydroxide. In Malassezia folliculitis, clusters of round budding yeast and short threads (hyphae) may be visible under the microscope (the "spaghetti and meatballs" name belongs to the look of a related yeast rash, tinea versicolor). Because Malassezia lives on almost everyone's skin, a positive result is counted as diagnostic when the rash itself already points to it. In one study of 49 patients cited in a 2025 review, the test picked up 81.6% of cases.
- Fungal culture: More sensitive than KOH but takes days to weeks to grow. Used when KOH is negative but fungal infection is still suspected.
- Wood's lamp examination: An ultraviolet (UV) light that makes Malassezia lesions fluoresce pale yellow-green. Useful in a clinic setting for quick screening; in the same 49-patient study it picked up 66.7% of cases, and the glow is not specific to Malassezia.
- Skin biopsy: Punch biopsy with histopathology is the most definitive test. Used when the diagnosis remains uncertain after simpler tests, or when eosinophilic folliculitis, demodex infestation, or a non-infectious cause is suspected.
- Blood tests: A complete blood count (CBC) is helpful for deep infections with systemic symptoms. Human immunodeficiency virus testing is commonly offered to people with eosinophilic folliculitis or recurrent severe infections without an obvious cause.
Conditions That Can Look Like Folliculitis
- Acne vulgaris: Acne has comedones (blackheads and whiteheads), which folliculitis does not. Acne is also more concentrated on the face and back.
- Keratosis pilaris: Rough, "chicken skin" bumps on the upper arms and thighs. No pustules, no infection — just keratin plugging the follicle opening.
- Eczema: Intense itch, scale, and weeping without a follicular pattern.
- Miliaria (heat rash): Tiny vesicles caused by blocked sweat ducts, not follicles. Appears in heat, no central hair.
- Contact dermatitis: Rash confined to the area of contact with an irritant or allergen; no follicular clustering.
Treatment: Bacterial Folliculitis
Mild, Localized Cases
Most superficial bacterial folliculitis clears up with basic measures:
- Warm compresses applied 3–4 times daily for 15–20 minutes soothe discomfort and promote natural drainage of pustules.
- Topical mupirocin 2% ointment applied three times daily for 7–10 days is effective for localized staphylococcal folliculitis and for methicillin-resistant Staphylococcus aureus on the skin surface.
- Topical clindamycin 1% lotion or gel twice daily is an alternative first-line topical antibiotic.
- Benzoyl peroxide wash (5–10%) used daily reduces S. aureus colonization of the skin surface and helps prevent recurrence. It does not cause antibiotic resistance.
- Gentle exfoliation with a soft washcloth removes dead skin cells that can block follicle openings.
- Non-occlusive, fragrance-free skincare products do not further block follicles.
Moderate Cases (Spreading, Deeper, or Recurrent)
When folliculitis is widespread, involves deeper tissue, or keeps coming back, oral antibiotics are used:
- Cephalexin 500 mg four times daily for 7–10 days is the standard first-line oral antibiotic for staphylococcal folliculitis when methicillin-resistant Staphylococcus aureus is not suspected.
- Dicloxacillin 500 mg four times daily is an alternative with excellent staphylococcal coverage.
Methicillin-Resistant Staphylococcus Aureus-Suspected Folliculitis
Methicillin-resistant Staphylococcus aureus (MRSA) does not respond to cephalexin or dicloxacillin. A recent hospital stay, household contacts with skin infections, or an infection that is not responding to standard antibiotics raise the likelihood of methicillin-resistant Staphylococcus aureus. Antibiotics used against it include:
- Trimethoprim-sulfamethoxazole 1–2 double-strength tablets twice daily for 7–10 days — highly effective against community-acquired methicillin-resistant Staphylococcus aureus
- Doxycycline 100 mg twice daily for 7–10 days
- Clindamycin 300 mg three times daily (local resistance rates vary — a culture-based sensitivity test helps guide this choice)
Managing a Furuncle (Boil)
Warm compresses speed up the process of a boil coming to a head (pointing). Once the boil is soft and fluctuant, incision and drainage (I&D) by a clinician is the definitive treatment — it relieves pain immediately and promotes healing far faster than antibiotics alone.
Whether antibiotics add anything after I&D in an otherwise healthy person was long debated; two large placebo-controlled trials have since tested it. In a 2016 trial at five United States emergency departments (Talan and colleagues), people over 12 with a drained, uncomplicated abscess took trimethoprim-sulfamethoxazole or a placebo for 7 days: the abscess was cured in 80.5% of 630 people on the antibiotic versus 73.6% of 617 on placebo. In the group that followed the protocol, the antibiotic also meant fewer repeat drainage procedures (3.4% vs 8.6%), fewer new skin infections at other sites (3.1% vs 10.3%) and fewer infections in household members (1.7% vs 4.1%), with slightly more mild stomach side effects. In a 2017 trial of 786 adults and children with abscesses 5 cm across or smaller (Daum and colleagues), cure after drainage was 83.1% with clindamycin and 81.7% with trimethoprim-sulfamethoxazole versus 68.9% with placebo; the benefit was limited to infections caused by Staphylococcus aureus, side effects were more frequent with clindamycin (21.9%) than with trimethoprim-sulfamethoxazole (11.1%) or placebo (12.5%), and the authors wrote that the benefit must be weighed against these side effects.
Antibiotics are also commonly added when the person is immunocompromised, has diabetes, has a fever, shows signs of surrounding skin infection (cellulitis), or the boil is in a high-risk location (face, genitalia).
Methicillin-Resistant Staphylococcus Aureus Decolonization for Recurrent Staph Infections
People who keep getting staph folliculitis or boils may be carrying methicillin-resistant Staphylococcus aureus in the nose or on the skin without knowing it. Decolonization aims to break the cycle:
- Nasal mupirocin 2% ointment applied inside both nostrils twice daily for 5 days eliminates nasal methicillin-resistant Staphylococcus aureus carriage, the most common reservoir for recurrent skin infections.
- Chlorhexidine 4% body wash used daily for 5–14 days reduces skin surface methicillin-resistant Staphylococcus aureus colonization.
- Household contacts are usually treated at the same time — re-colonization from a family member is a frequent reason decolonization fails.
- Bedding, towels, and clothing that contact affected skin are washed and dried as part of decolonization, because methicillin-resistant Staphylococcus aureus can survive on fabric for days.
Bleach baths. Dilute bleach baths are another home measure. A 2014 randomized trial (Kaplan and colleagues) gave children with probable community-acquired Staphylococcus aureus skin or invasive infections routine daily hygiene measures, with or without bleach baths twice a week for 3 months. Within 12 months, a recurrence needing medical care occurred in 17% (84 of 495) of the bleach-bath group and 21% (103 of 492) of the hygiene-only group, a difference too small to rule out chance.
Treatment: Non-Bacterial Forms
Malassezia (Fungal) Folliculitis
The key insight here is that antifungal treatment — not antibiotics — is required. Antibiotics actively worsen this condition.
- Topical ketoconazole 2% shampoo applied to the chest and back daily for 4 weeks, left on for 5 minutes before rinsing, is the standard first-line treatment. A rapid response (itching improves within 1–2 weeks) supports the diagnosis.
- Selenium sulfide 2.5% shampoo used similarly is a cost-effective alternative.
- Topical ciclopirox gel or cream applied twice daily works against Malassezia and is available by prescription.
- Oral itraconazole 200 mg daily for 5–7 days is reserved for more severe or treatment-resistant cases.
- Maintenance therapy with weekly ketoconazole wash prevents recurrence in susceptible individuals, especially in hot weather or after antibiotic courses.
A 2025 review (Chalupczak and Lipner) describes topical and oral antifungals as highly effective but notes that relapses are common once treatment stops. A 2026 review (Draelos and colleagues) adds that antifungal medicine is the mainstay of treatment, and that because Malassezia folliculitis and acne share causes (more skin oil, the enzyme lipase, and inflammation), acne treatments that act on both, including benzoyl peroxide and retinoids, may also help; the authors say this needs further study.
Pseudomonas (Hot Tub) Folliculitis
In healthy people this almost always clears up on its own within 1–2 weeks without any treatment. The usual management is reassurance and staying out of hot tubs until it clears.
Antibiotics (ciprofloxacin 500 mg twice daily for 7–10 days) are used only when symptoms persist beyond two weeks or the person is immunocompromised.
Prevention depends on the water. Pseudomonas aeruginosa is readily killed by disinfectants such as chlorine and bromine, and the United States Centers for Disease Control and Prevention (CDC) publishes minimum free-chlorine and pH levels for hot tubs. A 2024 CDC outbreak report notes that pool and hot tub users can check the disinfectant level and pH themselves with test strips sold at hardware and big-box stores. Owners also "shock" the water with a higher-dose chlorine treatment.
Pseudofolliculitis Barbae (Razor Bumps)
This condition is mechanical, not infectious, so antibiotics and antifungals have no role. The goal is to stop the hair from re-entering the skin:
- A pause in shaving for 2–4 weeks lets existing ingrown hairs grow out and inflammation subside. Even a few days of stubble makes a difference.
- Single-blade razors — multi-blade razors pull the hair beyond the skin surface before cutting, depositing the cut end below skin level where it can re-enter. A single blade cuts at skin level only.
- Shaving with the grain, not against it. Shaving against the grain creates a sharper, angled cut end that penetrates skin more easily.
- Chemical depilatories (products containing calcium thioglycolate or benzoyl benzoate) dissolve hair at skin level rather than cutting it, eliminating the sharp-edged stub that causes re-entry. These products can irritate sensitive skin.
- Topical tretinoin 0.025–0.05% cream applied nightly speeds up skin cell turnover and helps prevent the skin from growing over re-entering hairs.
- Eflornithine cream slows hair regrowth, reducing shaving frequency and the risk of re-entry.
- Glycolic acid exfoliants (5–8%) gently loosen the skin surface, freeing trapped hairs before they cause inflammation.
- Laser hair removal is described in a 2023 review (Dalia and colleagues) as a potential long-term option, with more studies needed on how long-lasting and permanent its results are; the same review names topical treatments as the current mainstay. The neodymium-doped yttrium aluminium garnet (Nd:YAG) 1064nm laser is used on all skin types including dark skin tones (where pulsed dye lasers and some intense pulsed light (IPL) devices are not). Multiple sessions (typically 6–8) are used, and the one-time cost is set against ongoing razor and treatment costs.
Eosinophilic Folliculitis
This rare form is treated with:
- Permethrin 5% cream when Demodex mites are suspected as a contributing factor
- Antihistamines for symptomatic itch relief
- Narrowband ultraviolet B (UVB) phototherapy reduces the eosinophilic inflammation
- Isotretinoin in severe, refractory cases
- Antiretroviral therapy for human immunodeficiency virus-positive patients — treating the underlying immune dysfunction is the most important step
Prevention
Everyday practices described for lowering the chance of folliculitis:
Daily Skin Hygiene
- Daily washing with a gentle, non-comedogenic cleanser; harsh soaps strip the skin's natural protective oils.
- Showering promptly after exercise, swimming, or any activity that causes heavy sweating. S. aureus counts on the skin surface rise significantly within 30 minutes of starting exercise.
- Non-occlusive, fragrance-free moisturizers; heavy creams and oils can block follicles.
Clothing and Physical Activity
- Breathable, moisture-wicking fabrics (100% cotton is often described as ideal for underwear and base layers).
- Tight synthetic fabrics trap heat and moisture against the skin in warm weather.
- Wiping down shared exercise equipment before and after use; gym equipment harbors S. aureus and methicillin-resistant Staphylococcus aureus.
- Washing workout clothes after every use; re-wearing sweaty clothing puts bacteria back on the skin.
Shaving Best Practices
- Softening hair with warm water for at least 2–3 minutes before shaving.
- A sharp blade; dull blades drag and tear rather than cut cleanly.
- Shaving with the grain of hair growth.
- For people with curly or coily hair: single-blade razors, electric shavers (which do not cut as close), or other hair removal methods.
- Regular blade changes; a single-use disposable is commonly described as good for no more than 3–5 shaves.
Hot Tub and Pool Safety
- Home hot tubs: regular testing of free chlorine and pH against the CDC minimum levels for hot tubs, and periodic shock chlorination.
- At shared facilities (gyms, water parks, spas), a test strip dipped before entering shows the disinfectant level and pH; a 2024 CDC report notes such strips are sold at hardware and big-box stores. Some people go by smell instead, taking a faint chlorine smell as a sign the water is treated and no smell at all from heavily used water as a warning sign.
- Showering right after leaving a shared water facility.
Preventing Methicillin-Resistant Staphylococcus Aureus Spread
- Not sharing razors, towels, washcloths, or clothing, even with family members.
- Covering open wounds, cuts, and abrasions with clean bandages.
- Early treatment of skin infections, rather than waiting to see whether a boil resolves on its own.
- When someone in a household has recurrent staph infections, the decolonization described above (nasal mupirocin 2% twice daily for 5 days and chlorhexidine 4% body washes) is usually given to all household members at the same time.
Diet and Immune Support
- Zinc is essential for skin barrier function, wound healing, and immune defense against bacterial invasion. Adequate dietary zinc (from meat, shellfish, legumes, seeds) or supplementation supports resistance to folliculitis.
- Vitamin C supports collagen synthesis and immune function, both critical for skin integrity.
- Adequate protein provides the amino acids needed for skin repair and antibody production.
- High-glycemic diets (refined sugar, white bread, soft drinks) raise levels of insulin-like growth factor 1 (IGF-1), which increases sebum production and promotes follicular inflammation. Reducing sugar and refined carbohydrates is described as benefiting both acne and folliculitis.
- Well-controlled blood sugar in people with diabetes significantly reduces the risk of skin infections — poorly controlled diabetes impairs neutrophil function and slows wound healing.
Natural and Integrative Approaches
Mild folliculitis often self-resolves. Moderate or severe cases are treated with prescription medicines. The approaches below are used alongside those treatments, not in place of prescription antibiotics or antifungals when those are indicated.
Tea Tree Oil
Melaleuca alternifolia oil has well-documented antibacterial activity against S. aureus, including some methicillin-resistant Staphylococcus aureus strains. The trial usually cited was in acne, not folliculitis: a 1990 single-blind randomized trial (Bassett and colleagues) in 124 patients with mild to moderate acne compared 5% tea tree oil gel with 5% benzoyl peroxide lotion. Both reduced inflamed and non-inflamed lesions; tea tree oil worked more slowly but caused fewer side effects. For skin use, tea tree oil is diluted (5% in a carrier oil or gel) and applied 2–3 times daily. Undiluted tea tree oil can cause chemical burns at full strength, and it irritates the eyes.
Manuka Honey
Manuka honey from New Zealand contains high concentrations of methylglyoxal (MGO), which gives it potent antibacterial activity including against methicillin-resistant Staphylococcus aureus. Applied topically to folliculitis lesions or as an occlusive wound dressing on boils, manuka honey creates a moist healing environment while actively inhibiting bacterial growth. Medical-grade manuka honey is labelled with a rating of its antibacterial strength; higher numbers mean more antibacterial activity.
Colloidal Oatmeal
Finely ground oatmeal has U.S. Food and Drug Administration-approved status as a skin protectant. Its avenanthramides inhibit inflammation driven by nuclear factor kappa B (NF-kB), reducing redness and itch. The usual home use is 1 cup in a lukewarm bath for a 15–20 minute soak, or a colloidal oatmeal cream applied directly to itchy folliculitis lesions. It is described as particularly helpful for widespread, itchy cases like hot tub folliculitis.
Apple Cider Vinegar (Diluted)
Undiluted acetic acid from apple cider vinegar has in vitro antibacterial activity and lowers skin surface pH (which inhibits bacterial colonization). The home method described is 1 part apple cider vinegar to 1 part water, applied with a cotton ball to affected areas. On broken, open, or severely inflamed skin the acidity stings and can delay healing. The evidence is limited to laboratory (in vitro) studies.
Neem Oil
Azadirachta indica (neem) has demonstrated antibacterial and antifungal properties in laboratory studies, including activity against S. aureus and Malassezia species. Traditional Ayurvedic medicine has used neem preparations for skin infections for centuries. It is applied diluted (a few drops in a carrier oil) to affected areas. Clinical trial evidence in humans remains limited, but the safety profile is good for topical use.
Aloe Vera
Fresh aloe vera gel contains compounds including acemannan and aloin that inhibit prostaglandin production and reduce inflammation. Applied topically, it soothes redness, reduces itch, and maintains skin hydration — all useful adjuncts to active folliculitis treatment. Pure gel (without added alcohol or artificial fragrance) is typically applied 2–3 times daily.
Turmeric (Internal and Topical)
Curcumin, the active compound in turmeric, inhibits S. aureus biofilm formation in vitro — biofilm is the protective matrix that makes folliculitis harder to treat and more prone to recurrence. Curcumin also inhibits nuclear factor kappa B, reducing production of inflammatory cytokines. Some people take oral curcumin (500–1000 mg daily, often with black pepper extract for absorption) alongside topical treatment. A paste of turmeric powder mixed with a small amount of coconut oil applied to individual pustules is a traditional remedy with plausible biological rationale.
Probiotics
Emerging evidence suggests that the skin microbiome — the community of beneficial bacteria living on skin — protects against S. aureus colonization. Oral probiotics, particularly Lactobacillus strains, may help restore this balance. Probiotics also support gut barrier integrity, which is relevant to the systemic inflammatory component of recurrent skin infections. Evidence is early but the safety profile of standard probiotic supplements is excellent.
Zinc
Zinc deficiency impairs neutrophil function, keratinocyte differentiation, and the skin's ability to mount an antibacterial defense. Topical zinc pyrithione (the active ingredient in many dandruff shampoos) also has direct activity against Malassezia species, making it a dual-purpose adjunct for Malassezia folliculitis when used as a body wash. Oral zinc supplementation (25–30 mg as zinc picolinate or bisglycinate daily) supports skin healing from within.
Key Research Papers
- Laureano AC, Schwartz RA, Cohen PJ. Facial bacterial infections: folliculitis. Clinics in Dermatology. 2014;32(6):711-714. — PubMed PMID: 25441463
- Luelmo-Aguilar J, Santandreu MS. Folliculitis: recognition and management. American Journal of Clinical Dermatology. 2004;5(5):301-310. — PubMed PMID: 15554731
- Stulberg DL, Penrod MA, Blatny RA. Common bacterial skin infections. American Family Physician. 2002;66(1):119-124. — PubMed PMID: 12126026
- Talan DA, Mower WR, Krishnadasan A, Abrahamian FM, Lovecchio F, Karras DJ, Steele MT, Rothman RE, Hoagland R, Moran GJ. Trimethoprim-Sulfamethoxazole versus Placebo for Uncomplicated Skin Abscess. New England Journal of Medicine. 2016;374(9):823-832. — PubMed PMID: 26962903
- Daum RS, Miller LG, Immergluck L, Fritz S, Creech CB, Young D, Kumar N, Downing M, Pettibone S, Hoagland R, Eells SJ, Boyle MG, Parker TC, Chambers HF; DMID 07-0051 Team. A Placebo-Controlled Trial of Antibiotics for Smaller Skin Abscesses. New England Journal of Medicine. 2017;376(26):2545-2555. — PubMed PMID: 28657870
- Kaplan SL, Forbes A, Hammerman WA, Lamberth L, Hulten KG, Minard CG, Mason EO. Randomized trial of "bleach baths" plus routine hygienic measures vs. routine hygienic measures alone for prevention of recurrent infections. Clinical Infectious Diseases. 2014;58(5):679-682. — PubMed PMID: 24265356
- Chalupczak NV, Lipner SR. Malassezia Folliculitis: An Underdiagnosed Mimicker of Acneiform Eruptions. Journal of Fungi (Basel). 2025;11(9):662. — PubMed PMID: 41003208
- Draelos ZD, Barbieri JS, Tanghetti EA, Farris P, Lain ET, Prevete S, Choi SY, Wroblewski K, Baldwin H, Kircik LH. Malassezia Folliculitis Presentation, Diagnosis, and Treatment: A Review of "Fungal Acne". Journal of Drugs in Dermatology. 2026;25(5):427-434. — PubMed PMID: 42081639
- Lamere L, Smith E, Grieser H, Arduino M, Hlavsa MC, Combes S. Pseudomonas Infection Outbreak Associated with a Hotel Swimming Pool - Maine, March 2023. MMWR Morbidity and Mortality Weekly Report. 2024;73(2):32-36. — PubMed PMID: 38236783
- Dalia Y, Khatib J, Odens H, Patel T. Review of treatments for pseudofolliculitis barbae. Clinical and Experimental Dermatology. 2023;48(6):591-598. — PubMed PMID: 36840647
- Bassett IB, Pannowitz DL, Barnetson RS. A comparative study of tea-tree oil versus benzoylperoxide in the treatment of acne. Medical Journal of Australia. 1990;153(8):455-458. — PubMed PMID: 2145499
PubMed Topic Searches
Curated PubMed searches on folliculitis. Each link opens a live query so you always see the most current studies.
- PubMed: Folliculitis staphylococcal treatment
- PubMed: Malassezia folliculitis
- PubMed: Hot tub Pseudomonas folliculitis
- PubMed: Pseudofolliculitis barbae razor bumps
- PubMed: methicillin-resistant Staphylococcus aureus decolonization
- PubMed: Furuncle and carbuncle treatment
- PubMed: Eosinophilic folliculitis human immunodeficiency virus
- PubMed: Tea tree oil Staphylococcus
- PubMed: Laser hair removal pseudofolliculitis
- PubMed: Gram-negative folliculitis
- PubMed: Zinc skin immunity
- PubMed: Manuka honey methicillin-resistant Staphylococcus aureus