Insulin Types and Dosing Strategies
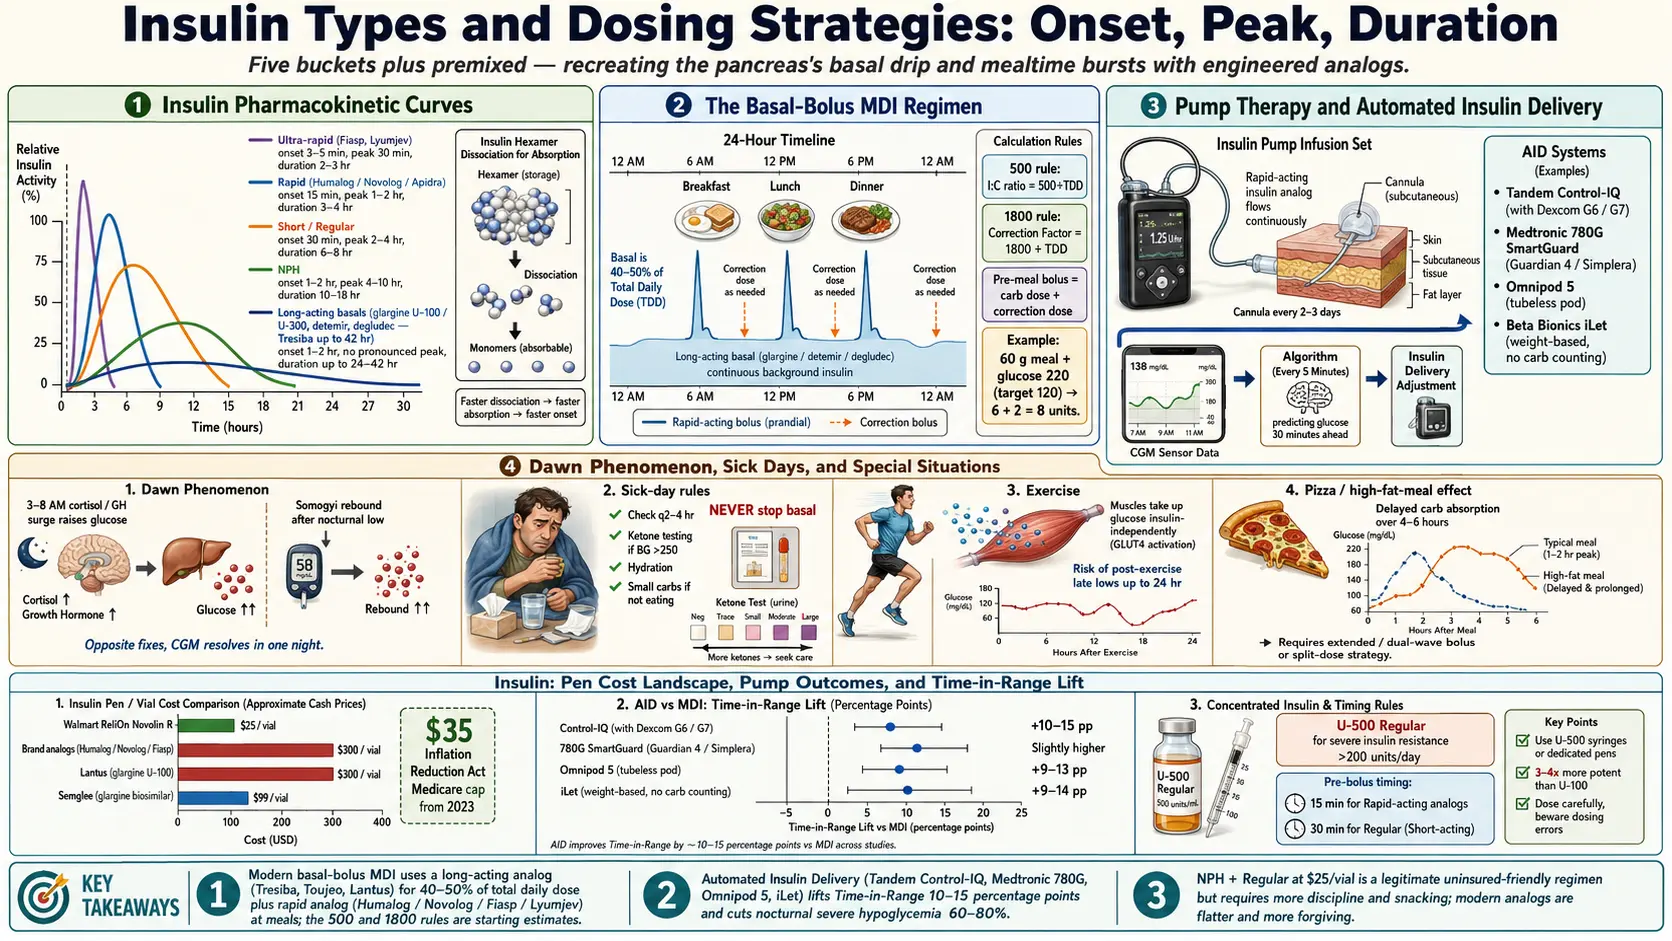
Table of Contents
- Why There Are So Many Insulins
- Rapid-Acting Bolus Insulins
- Ultra-Rapid and Inhaled
- Short-Acting (Regular) Insulin
- Intermediate — NPH
- Long-Acting Basal Insulins
- Premixed Insulins
- Pump-Compatible Insulins
- The Basal-Bolus MDI Regimen
- Pump Therapy and AID Systems
- Carb Counting Basics
- I:C Ratio, Correction Factor, and the 500/1800 Rules
- Basal Dosing and Basal Testing
- Dawn Phenomenon vs Somogyi
- Sick-Day Rules
- Exercise Adjustments
- Hypoglycemia Prevention in Brittle T1D
- Insurance and Cost Realities
- Key Research Papers
- Connections
- Featured Videos
Why There Are So Many Insulins
A healthy pancreas releases insulin in two patterns. There is a slow background drip that runs twenty-four hours a day to keep the liver from dumping too much glucose into the blood, and there are fast bursts at every meal that shove dietary carbohydrate into muscle and fat cells. Insulin by injection is an attempt to recreate both of those patterns with products that come out of a vial. No single insulin can do both jobs well — fast and short for meals, slow and flat for background — so pharmaceutical companies have engineered a menu of molecules, each tuned to a different onset and duration. This article describes every major category, how the types differ, and the dosing methods that diabetes educators and published trials describe.
For people new to insulin, the sheer number of names is intimidating. But the logic is simple: everything falls into one of five buckets — ultra-rapid, rapid, short, intermediate, long — plus premixed combinations. Once the onset, peak, and duration of each bucket are clear, the product names matter much less.
Rapid-Acting Bolus Insulins
Rapid-acting analogs are the workhorses of mealtime dosing. They appeared in the 1990s and replaced Regular insulin for most people because they match the speed of a carbohydrate meal far better. Three molecules share nearly identical pharmacology:
- Insulin lispro (including a follow-on biosimilar version and an ultra-rapid formulation).
- Insulin aspart (including a faster-acting formulation).
- Insulin glulisine.
All three have an onset of roughly 15 minutes, a peak between 1 and 2 hours, and a total duration of 3 to 4 hours. In practice that means an injection 10 to 15 minutes before eating (not at the first bite) and the dose is mostly gone by the next meal. The tail is short enough that stacking — giving a second dose before the first is finished — is less dangerous than with Regular insulin, but it is still the most common cause of unexpected lows.
For most people there is no clinically important difference between insulin lispro, insulin aspart, and insulin glulisine. Choice is usually driven by insurance formulary, pump compatibility, or personal response; people who get site irritation or unpredictable absorption with one product often switch to another.
Ultra-Rapid and Inhaled
Two newer analogs squeeze the onset even shorter. Faster-acting insulin aspart adds niacinamide to aspart, which speeds absorption. Ultra-rapid insulin lispro adds treprostinil and citrate, which dilate the capillary bed around the injection and pull the drug into circulation faster. Both have onsets around 3 to 5 minutes, with a peak roughly 30 minutes earlier than the older analogs.
The practical advantage is postprandial control — the 1- and 2-hour glucose after a meal. For people whose continuous glucose monitor (CGM) traces show a big spike between eating and the two-hour mark even with pre-bolusing, a switch to one of these faster formulations often flattens that curve. They also shine for people who cannot reliably pre-bolus (toddlers, people with gastroparesis, people who have to eat unpredictably at work).
Inhaled insulin is human insulin as a dry powder. A single-use cartridge goes into a small inhaler and the dose is breathed in at the start of a meal. The U.S. label (DailyMed, revised May 2026) gives these timings from a study in 30 people with type 1 diabetes: a first measurable effect at about 12 minutes; a peak effect at about 35, 45, and 55 minutes after doses of 4, 12, and 48 units; and a return to baseline at about 90, 180, and 270 minutes — so the effect lasts longer as the dose rises. Insulin in the blood peaks 10 to 20 minutes after inhalation. It is used by people who dislike needles or want very tight postprandial numbers. Cartridges hold 4, 8, or 12 units, and larger doses are made by combining cartridges. The current label covers adults and children 6 years of age and older.
The label carries a boxed warning: sudden tightening of the airways (acute bronchospasm) has been seen in people with asthma and chronic obstructive pulmonary disease (COPD) who used inhaled insulin, and it is contraindicated in chronic lung disease such as asthma or COPD. A breathing test (spirometry, measuring FEV1) is required before starting, then after the first 6 months and every year after that. The label states that inhaled insulin is not recommended for people who smoke or who have recently stopped smoking, and not recommended for treating diabetic ketoacidosis.
In a 24-week trial in type 1 diabetes (Bode 2015; 174 people on inhaled insulin and 171 on injected insulin aspart, both with basal insulin), HbA1c fell by 0.21 percentage points with inhaled insulin and 0.40 with insulin aspart — within the trial's non-inferiority margin — though more people on insulin aspart reached an HbA1c under 7% (30.7% against 18.3%). The inhaled-insulin group had fewer low-glucose events (9.8 against 14.0 per patient-month) and a small weight loss (0.4 kg) instead of a gain (0.9 kg). Cough, generally mild, affected 31.6% of inhaled-insulin users against 2.3%, and led 5.7% to stop.
Short-Acting (Regular) Insulin
Regular insulin — also called R or human regular insulin — is plain recombinant human insulin. It has an onset of 30 minutes, peak at 2 to 4 hours, and duration of 6 to 8 hours. For decades it was the only mealtime option. Today it is mostly used for three reasons: cost, high-protein meals, and severe insulin resistance.
For cost: a large U.S. retail chain sells store-brand human regular insulin for about $25 a vial without a prescription in most states. Compared with $300 for a brand-name analog, that is life-saving for people without insurance, even though it is harder to use.
For high-protein meals: Regular's longer tail actually helps cover the delayed glucose rise from pizza, cheeseburgers, or a big steak dinner — the so-called "pizza effect," where dietary protein and fat slow carbohydrate absorption for hours. Some pump users run a "combo" or "dual-wave" bolus of rapid insulin, but a small dose of Regular in addition to rapid can do the same thing with a pen.
For severe insulin resistance: U-500 Regular insulin is five times more concentrated than standard U-100. It is reserved for people requiring more than about 200 units per day of total insulin, where U-100 volumes become impractical (imagine injecting 2 mL five times a day). U-500 dosing is a specialist-only territory because the timing and stacking behavior change — it behaves more like an intermediate than a true short-acting insulin.
Intermediate — NPH
NPH (Neutral Protamine Hagedorn) is Regular insulin mixed with a fish-sperm-derived protein that slows its release. Onset is 1 to 2 hours, peak 4 to 10 hours, duration 10 to 18 hours. It is cloudy — the vial or pen is rolled between the palms to resuspend the crystals before a dose is drawn.
NPH is the cheapest basal option — about $25 a vial as a retail store brand — and still the global workhorse outside wealthy countries. The downside is the peak. A 10-hour peak means that NPH taken at bedtime carries a real risk of 3 a.m. hypoglycemia, and NPH taken at breakfast can bring a late-afternoon low. Variability vial-to-vial and day-to-day is worse than with the true long-acting analogs.
For most insured patients, NPH has been replaced by glargine or degludec. For uninsured patients who cannot afford analogs, NPH plus Regular is a completely legitimate regimen — it is the regimen that kept people alive from the 1950s until the 1990s. It simply requires more discipline, more snacks, and more glucose monitoring.
Long-Acting Basal Insulins
Modern basal insulins are engineered to release at a slow, flat rate for roughly a full day or longer. Four products matter:
- Insulin glargine U-100 (the original product plus follow-on biosimilars, one of them designated interchangeable). Onset 1–2 hours, minimal peak, duration about 24 hours. Once-daily dosing in most people, split twice-daily in a minority who run out before 24 hours.
- Insulin glargine U-300. Same molecule, three times more concentrated. The smaller injection depot releases even more slowly, giving a flatter profile and duration up to 36 hours. Less hypoglycemia than U-100 in head-to-head trials.
- Insulin detemir. Binds reversibly to albumin in the blood, which smooths absorption. Often used twice daily because its duration is closer to 18–22 hours. Popular in pregnancy because of its safety data.
- Insulin degludec. Forms multi-hexamer chains at the injection site that slowly release monomers for up to 42 hours. Its label allows a flexible injection time but requires at least 8 hours between consecutive doses. The flattest, most forgiving basal on the market. Lower nocturnal hypoglycemia than glargine U-100 in the SWITCH trials: in SWITCH 1 (501 adults with type 1 diabetes and at least one risk factor for lows, a double-blind crossover trial with 32 weeks on each insulin), night-time symptomatic lows ran at 277.1 against 428.6 episodes per 100 patient-years (rate ratio 0.64), all symptomatic lows at a rate ratio of 0.89, and 10.3% against 17.1% of people had a severe low during the maintenance period.
Whether the choice of basal insulin matters depends on the person. For someone whose numbers are stable on insulin glargine U-100, the product makes little difference. For someone waking up low at 3 a.m. despite careful dosing, a switch to glargine U-300 or degludec often fixes it. For someone who works rotating shifts or travels across time zones, degludec's flatness is a real quality-of-life gain.
Once-weekly basal insulins. Two once-a-week basal insulins, insulin icodec and insulin efsitora alfa, have been tested in large trials (the ONWARDS and QWINT programmes). The European Medicines Agency authorised icodec on 17 May 2024 for adults with type 1 or type 2 diabetes. In the United States, the Food and Drug Administration approved icodec on 26 March 2026 for adults with type 2 diabetes and extended that approval on 23 October 2026 to children 10 years and older with type 2 diabetes; it approved efsitora alfa on 23 September 2026 for adults with type 2 diabetes, and the efsitora label states that it is not recommended in type 1 diabetes. The approvals and the trial numbers are set out on Once-Weekly Basal Insulins. A 2024 review's meta-analysis of the phase 3 icodec trials (4,347 adults with type 1 or type 2 diabetes) found icodec lowered HbA1c slightly more than once-daily basal insulin (by 0.14 percentage points), with a weight gain of 0.62 kg and a similar overall frequency of low-glucose events; it worked best when used as basal insulin alone rather than with mealtime insulin. A 2025 review reports that in type 2 diabetes both weekly insulins matched once-daily basal insulin, and in some trials did better, with similar rates of clinically significant and severe lows, while in type 1 diabetes (the ONWARDS 6 and QWINT-5 trials) HbA1c fell about as much as with daily insulin degludec but lows were more frequent. A pooled safety analysis of ONWARDS 1–6 (2,170 people on icodec and 2,170 on daily basal insulin) found similar rates of all, serious, and severe adverse events; injection-site reactions, mostly mild, ran at 5.86 against 3.66 per 100 patient-years. Long-term heart outcomes and long-term safety are still open questions, the 2025 review notes. The first efsitora trial in people with type 2 diabetes new to insulin (QWINT-1) was published in 2025 and reviewed in a 2026 Drug and Therapeutics Bulletin commentary.
Premixed Insulins
Premixed insulins combine a basal and a bolus in one pen. Common ratios:
- 70/30 — 70% NPH + 30% Regular, or 70% aspart protamine + 30% aspart.
- 75/25 — 75% lispro protamine + 25% lispro.
- 50/50 — half-and-half for people with larger meal boluses.
Premixed regimens are usually twice daily, before breakfast and before dinner. They are simpler than basal-bolus — two injections instead of five — and they suit people with steady schedules and steady meal sizes: older adults, people with cognitive impairment, people whose caregivers do the dosing. The trade-off is flexibility. The basal part cannot be adjusted separately during illness, nor the bolus part when a meal is skipped. For type 1 diabetes, premixed is generally not adequate. For stable type 2, it can be an excellent pragmatic choice.
Pump-Compatible Insulins
Insulin pumps deliver continuous subcutaneous infusion through a small cannula changed every 2 to 3 days. Only rapid-acting analogs are used in pumps: insulin lispro and insulin aspart, including their faster formulations. Insulin glulisine is U.S. Food and Drug Administration-approved for pump use but tends to crystallize in tubing over 48 hours and is less popular. Regular insulin is not used in modern pumps because its long tail destroys the math of automated dosing.
Some pump users prefer the faster formulations for the quicker meal response; others find the ultra-rapid formulations more likely to cause infusion-set irritation and stay with standard insulin lispro or insulin aspart. This is an individual trial.
The Basal-Bolus MDI Regimen
MDI means multiple daily injections. It is the gold-standard regimen for type 1 diabetes when not using a pump, and an excellent regimen for insulin-requiring type 2. The structure is:
- Long-acting basal once daily (insulin glargine U-100 or U-300, or insulin degludec) or twice daily (insulin detemir). Usually 40–50% of total daily dose.
- Rapid-acting bolus before each meal. Dose = (carbs ÷ I:C ratio) + (correction for high glucose).
- Correction doses between meals for out-of-range highs, using the same rapid-acting insulin.
Four to five injections a day sounds like a lot, but the pen needle is 4 mm long and thinner than a human hair. Most patients describe the injections as painless within two weeks. Basal-bolus dosing allows tight glucose control, at the cost of a learning curve.
Pump Therapy and AID Systems
An insulin pump replaces the basal insulin (with a programmable micro-drip of rapid insulin delivered every few minutes) and replaces mealtime pens (the wearer pushes buttons instead). Since a 2016 safety study of a hybrid closed-loop system (Bergenstal 2016, below), pumps have evolved into automated insulin delivery (AID) systems — also called hybrid closed-loop systems — that read the wearer's CGM in real time and adjust the basal rate minute-by-minute.
The commercial systems in the U.S. fall into a few designs:
- Tubed pumps paired with a CGM — one design adjusts basal every 5 minutes and delivers automatic correction boluses once an hour if glucose is trending high; another auto-corrects every 5 minutes, including micro-boluses.
- Tubeless patch pumps — a disposable 3-day pod paired with a CGM that adjusts basal toward a personalized target glucose.
- Weight-based "bionic pancreas" system — the dosing algorithm is weight-based only, with no carb counting required. The user announces meals as "usual, less, or more" and the pump estimates the dose.
In the six-month iDCL trial (Brown 2019; 168 people with type 1 diabetes aged 14 to 71), time in range (70–180 mg/dL) rose from 61% to 71% with a closed-loop system and stayed at 59% in the comparison group, which used a pump with a CGM (a sensor-augmented pump) rather than injections — an 11-percentage-point difference. Time below 70 mg/dL was 0.88 percentage points lower and HbA1c 0.33 points lower with the closed-loop system; no serious lows occurred in either group, and one episode of diabetic ketoacidosis occurred in the closed-loop group. AID systems are not magic — users still bolus for meals (except on the weight-based system), still change sites, still replace CGM sensors — but they dramatically reduce the mental load of T1D.
Carb Counting Basics
Carb counting means measuring the grams of carbohydrate in each meal so the bolus can be calculated. In practice three tools are used in combination:
- Nutrition labels. The figure used is "Total Carbohydrate" (not "net carbs" and not "sugars"). Fiber is subtracted only in the net-carb approach some educators teach, and the figure is multiplied by the number of servings actually eaten.
- Apps. Food-tracking apps with large crowd-sourced databases vary in accuracy; some specialise in restaurant and packaged foods, some in low-carb and keto eating, and some estimate portions from photos.
- Restaurant disclosure. U.S. chains with more than 20 locations are federally required to publish calorie and often carbohydrate counts, on printed menus or online.
Protein and fat matter too. A pure-carb meal (toast with jam) hits the bloodstream within 30 minutes. A high-fat, high-protein meal (pizza, lasagna, cheeseburger and fries) releases glucose over 4 to 6 hours — the pizza effect. Pump users handle this with extended or combo boluses. MDI users either split the bolus (half before the meal, half at the 90-minute mark) or add a small dose of Regular insulin. Most people with T1D eventually learn which foods do this to them. Dinner leftovers for lunch usually behave differently than the same food fresh — another quirk to log.
I:C Ratio, Correction Factor, and the 500/1800 Rules
Two numbers drive every bolus calculation:
Insulin-to-carb ratio (I:C) is how many grams of carbohydrate one unit of rapid insulin covers. An I:C of 1:10 means 1 unit per 10 grams of carb. A 60-gram meal = 6 units.
The classic starting estimate is the 500 rule: 500 divided by the total daily dose (TDD) of insulin. For someone taking 50 units a day in total, the I:C works out to about 500 ÷ 50 = 10, so 1 unit per 10 g carb. For Regular insulin instead of rapid, the 450 rule is used.
Correction factor (CF), also called insulin sensitivity factor (ISF), is how far one unit of rapid insulin lowers glucose. A CF of 50 means one unit lowers blood sugar by 50 mg/dL. A reading of 220 with a target of 120 means a 100-point drop needed = 2 units of correction.
Starting estimate: the 1800 rule (some endocrinologists use 1700). 1800 divided by the TDD. For a 50-unit-per-day person: 1800 ÷ 50 = 36 mg/dL per unit.
A pre-meal dose is the sum: carb dose + correction dose. For a 60 g carb meal with a pre-meal glucose of 220 and a target of 120, that comes to 6 + 2 = 8 units.
These are starting points. Real I:C and CF vary by time of day — most people are more insulin-resistant in the morning — by menstrual cycle, by exercise, by illness, and by stress. Pumps can be programmed with three or four different ratios across the day. MDI users can simply note that, say, breakfast needs 1:8 while dinner needs 1:12.
Basal Dosing and Basal Testing
Basal insulin is meant to cover glucose between meals without causing lows. The usual split is 40 to 50% of total daily dose as basal, with the rest as mealtime bolus. For a 50-unit-per-day person that means roughly 20 to 25 units of long-acting.
To confirm the basal dose is right, endocrinologists use basal testing. In the usual method a meal (say, lunch) is skipped with no bolus, and glucose is checked every 2 to 3 hours for the next 6 hours. If glucose stays flat within about 30 mg/dL of the starting value, the basal in that window is considered correct; a drift up means basal is too low, a drift down that it is too high. The test is repeated across breakfast, lunch, and dinner windows on different days to map the whole 24-hour profile. CGM users can do this passively by scanning the CGM line during accidental skipped meals.
The usual teaching is to change basal by no more than 10% every 3 days. Basal insulins take 3 to 5 days to reach a new steady state, so faster adjustments chase ghosts.
Dawn Phenomenon vs Somogyi
Many people with diabetes wake up with higher glucose than they went to bed with. The two classic explanations:
- Dawn phenomenon. Between 3 and 8 a.m., cortisol and growth hormone rise to prepare the body for waking. These hormones push the liver to release glucose and reduce insulin sensitivity. Most people — diabetic or not — have this surge; in diabetes it simply is not absorbed. A CGM trace shows a smooth upward curve from about 3 a.m. onward. Usual responses: a slightly higher basal dose, moving the basal injection from evening to morning, or a pump with a higher overnight basal rate.
- Somogyi effect (rebound hyperglycemia). A nocturnal low around 2–3 a.m. triggers counter-regulatory hormones that overshoot, leaving glucose high by 7 a.m. CGM shows a dip before the rise. The usual response is a lower basal dose — the opposite of the dawn-phenomenon response, which is why guessing is dangerous.
Somogyi is much rarer than it used to be thought — modern CGM data suggest dawn phenomenon accounts for the vast majority of morning highs. But the distinction matters because the two conditions need opposite adjustments. CGM answers the question in one night.
Sick-Day Rules
Infections, fevers, vomiting, and surgery all push glucose up and, in type 1 diabetes, can push ketones up fast. Sick-day plans taught by diabetes educators commonly cover these points:
- Basal insulin continues. Even without food, the liver is still releasing glucose and the body still needs basal coverage. Stopping basal insulin during a stomach bug in type 1 diabetes is the classic path to diabetic ketoacidosis (DKA).
- More frequent checks. Glucose every 2 to 4 hours, around the clock. CGM covers this automatically.
- Ketone checks. Urine ketone strips (about $10 for 50) or a blood beta-hydroxybutyrate (ketone) meter. Blood ketone readings are real-time; urine readings lag by hours. Sick-day plans treat any ketones above trace during illness as a signal to act.
- Higher basal during fever. Infection and fever raise insulin resistance. A 10–20% increase in basal for the duration of illness is a common starting adjustment, guided by glucose trends.
- Correction doses every 2–3 hours for high glucose plus ketones, with clear fluids and electrolyte replacement (oral rehydration solution, broth, diluted juice if glucose is low).
- Emergency signs. Being unable to keep fluids down, moderate or large ketones, fruity-smelling breath, deep and fast breathing, or confusion are signs of DKA, which hospitals treat as a medical emergency.
Exercise Adjustments
Exercise is one of the most powerful glucose-lowering tools available, and also one of the most common causes of hypoglycemia. Three patterns matter:
- Planned exercise within 2 hours of a meal bolus. Common guidance lowers the pre-meal rapid dose by 25 to 75% depending on intensity and duration — for example about 25% less bolus for a 45-minute walk after dinner and 50–75% less for a 2-hour hike.
- Long-duration aerobic exercise (cycling, running, hiking more than an hour) raises insulin sensitivity for up to 24 hours afterward. A 10–20% lower basal dose the evening before and the night after is a common adjustment. Pump users often program a temporary basal rate at 70–80% for the workout window plus the recovery night.
- Resistance training and high-intensity intervals release adrenaline, which can push glucose up during the workout and crash it afterward. A small correction dose during the workout, followed by reduced basal for recovery, is a common pattern.
Many people carry fast carbs (glucose tablets or candy, or a juice box) to every workout, and CGM users often set a low-alert threshold around 90 mg/dL during exercise to get a warning before symptoms.
Hypoglycemia Prevention in Brittle T1D
Some people, especially long-duration T1D patients, develop hypoglycemia unawareness — they no longer feel the shakiness, sweating, or hunger that warn of a low. Numbers can drop into the 40s before they notice. The standard toolkit:
- Rule of 15. The standard teaching for a low (under 70 mg/dL) is 15 grams of fast carbs (4 glucose tablets, 4 oz juice, 1 tablespoon honey), a re-check after 15 minutes, and a repeat if still low. Over-treating is a common trap — stacking 60 g of juice into a 55 mg/dL low can push glucose to 250 an hour later.
- Glucagon. For severe lows when the person cannot swallow. Modern options: nasal glucagon (a nasal powder, no mixing required), a glucagon autoinjector or prefilled syringe, and a prefilled pen of the glucagon analog dasiglucagon. These have replaced the old red emergency kit. Diabetes educators commonly describe keeping one at home, one in the car, and one at work, with family members trained to use it.
- Pump auto-suspend. The current automated insulin delivery systems predict low glucose and reduce or suspend basal automatically.
- CGM alerts. A common setup is an urgent-low threshold at 55 mg/dL and a predictive low alert at 80–90 mg/dL with a 20–30 minute look-ahead window. Readings can be shared with a partner or parent overnight.
- Hypoglycemia unawareness can reverse. Two to three weeks of strict avoidance of any glucose under 70 often restores awareness. This is hard and usually involves CGM plus a looser basal dose.
Insurance and Cost Realities
U.S. insulin pricing has been a national political issue for a decade. The picture in 2026:
- Retail prices for brand-name analogs historically exceeded $300 per vial or $500 per box of pens. Biosimilars cut that roughly in half, to about $160 per vial.
- 2023 price reductions. Insulin prices were lowered in 2023 under political pressure, a change a 2023 JAMA Viewpoint examined as a possible path to lowering other drug costs (Brennan 2023). One maker dropped the list prices of its insulin lispro and human insulin by 70%. Another cut insulin aspart and insulin detemir by 75%. A third capped its insulin glargine and its follow-on insulin lispro at $35/month out-of-pocket for commercially insured patients. These cuts are finally visible at the pharmacy counter in 2025–2026.
- Medicare Part D $35 cap. Since January 2023, all insulins covered under Part D are capped at $35 per month copay. This applies to every Medicare beneficiary automatically — no enrollment needed. A 2026 study of 2,860,394 Medicare insulin users (Myerson 2026) found that almost no insulin fills exceeded the cap in 2023, against 13% that would have in 2021–2022; the average cost per 30-day supply fell from $22.95 to $18.16, and insulin use rose among people who had paid the most before the cap.
- Manufacturer copay programs. Commercially insured patients can use manufacturer savings cards to cap most insulins at $35 per month. These do not work with Medicare, Medicaid, or TriCare.
- Retail store-brand insulin. Human regular insulin, NPH, and premixed 70/30 are sold under a large retail chain's store brand for about $25 per vial with no prescription in most states. The same store brand's insulin aspart is about $73 per vial. These are the fallback for uninsured patients. They keep people alive, but the older formulations require more discipline.
- Inhaled insulin runs around $200–$300 per month with insurance coverage and typically more without.
- Biosimilar landscape. Insulin glargine has several biosimilars. One is designated interchangeable — pharmacists can substitute it without a new prescription. Another is a non-interchangeable biosimilar that requires the prescription to specifically name it, and a third glargine biosimilar is also on the market. For aspart, premixed insulin aspart has several biosimilar candidates in late-stage development.
For people facing an unaffordable insulin bill, the insulin makers run manufacturer patient-assistance programmes; most provide free insulin to uninsured patients below about 400% of the federal poverty line. Rationing insulin carries a real risk of death.
Key Research Papers
Foundational peer-reviewed work on insulin analog pharmacology, basal-bolus and pump regimens, and the move toward automated insulin delivery. Each citation links to the paper via DOI or PubMed.
- Hirsch IB. Insulin Analogues. New England Journal of Medicine. 2005;352(2):174–183. — doi:10.1056/NEJMra040832
- Russell-Jones D, Bode BW, De Block C, et al. Fast-Acting Insulin Aspart Improves Glycemic Control in Basal-Bolus Treatment for Type 1 Diabetes (onset 1). Diabetes Care. 2017;40(7):943–950. — doi:10.2337/dc16-1771
- Bergenstal RM, Garg S, Weinzimer SA, et al. Safety of a Hybrid Closed-Loop Insulin Delivery System in Patients with Type 1 Diabetes. JAMA. 2016;316(13):1407–1408. — doi:10.1001/jama.2016.11708
- Brown SA, Kovatchev BP, Raghinaru D, et al. Six-Month Randomized, Multicenter Trial of Closed-Loop Control in Type 1 Diabetes (iDCL). New England Journal of Medicine. 2019;381(18):1707–1717. — doi:10.1056/NEJMoa1907863
- Pickup JC, Sutton AJ. Severe Hypoglycaemia and Glycaemic Control in Type 1 Diabetes: Meta-Analysis of Multiple Daily Insulin Injections Compared with Continuous Subcutaneous Insulin Infusion. Diabetic Medicine. 2008;25(7):765–774. — doi:10.1111/j.1464-5491.2008.02486.x
- Holman RR, Farmer AJ, Davies MJ, et al. Three-Year Efficacy of Complex Insulin Regimens in Type 2 Diabetes (4-T). New England Journal of Medicine. 2009;361(18):1736–1747. — doi:10.1056/NEJMoa0905479
- The Diabetes Control and Complications Trial Research Group. The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus (DCCT). New England Journal of Medicine. 1993;329(14):977–986. — doi:10.1056/NEJM199309303291401
- UK Prospective Diabetes Study (UKPDS) Group. Intensive Blood-Glucose Control with Sulphonylureas or Insulin Compared with Conventional Treatment and Risk of Complications in Patients with Type 2 Diabetes (UKPDS 33). Lancet. 1998;352(9131):837–853. — doi:10.1016/S0140-6736(98)07019-6
- American Diabetes Association Professional Practice Committee for Diabetes. 9. Pharmacologic Approaches to Glycemic Treatment: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S183–S215. — PubMed PMID: 41358900
- Bode BW, McGill JB, Lorber DL, et al. Inhaled Technosphere Insulin Compared With Injected Prandial Insulin in Type 1 Diabetes: A Randomized 24-Week Trial. Diabetes Care. 2015;38(12):2266–2273. — PubMed PMID: 26180109
- Lane W, Bailey TS, Gerety G, et al. Effect of Insulin Degludec vs Insulin Glargine U100 on Hypoglycemia in Patients With Type 1 Diabetes: The SWITCH 1 Randomized Clinical Trial. JAMA. 2017;318(1):33–44. — PubMed PMID: 28672316
- Lisco G, De Tullio A, De Geronimo V, et al. Once-Weekly Insulin Icodec in Diabetes Mellitus: A Systematic Review and Meta-Analysis of Randomized Clinical Trials (ONWARDS Clinical Program). Biomedicines. 2024;12(8):1852. — PubMed PMID: 39200316
- Denimal D. Emerging perspectives on once-weekly insulins in type 1 and type 2 diabetes: a mini-review. Frontiers in Endocrinology. 2025;16:1656884. — PubMed PMID: 40937414
- Bajaj HS, Andersen SB, Hristova B, et al. Once-Weekly Insulin Icodec: Safety Profile in Type 2 and Type 1 Diabetes Based on a Pooled Analysis of ONWARDS 1-6. Endocrine Practice. 2026;32(10):1475–1482. — PubMed PMID: 42119975
- Khong TK, Vanniasegaram D. Once-weekly insulin (insulin efsitora) for patients with type 2 diabetes. Drug and Therapeutics Bulletin. 2026;64(7):100–102. — PubMed PMID: 42270287
- Brennan T. Does Insulin Price Reduction Suggest a Path Forward for Lowering Drug Costs? JAMA. 2023;329(16):1345–1346. — PubMed PMID: 36988976
- Myerson R, Kim NH, Romley J, et al. Insulin Costs and Use by Medicare Beneficiaries After the Inflation Reduction Act Out-of-Pocket Cap. JAMA. 2026;336(1):25–34. — PubMed PMID: 42250272
PubMed Topic Searches
Each link opens a live PubMed query so results stay current as new papers are indexed.
- PubMed: Insulin analog pharmacokinetics
- PubMed: Basal-bolus therapy in type 1 diabetes
- PubMed: Insulin degludec and nocturnal hypoglycemia
- PubMed: Automated insulin delivery and hybrid closed-loop systems
- PubMed: Insulin-to-carbohydrate ratio methodology
- PubMed: Dawn phenomenon in diabetes
- PubMed: Hypoglycemia unawareness in type 1 diabetes
- PubMed: Inhaled insulin clinical outcomes
- PubMed: Insulin biosimilars and interchangeability
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Diabetes Overview
- Type 1 vs Type 2 vs LADA and MODY
- Cardio-Renal Protection: Sodium-Glucose Cotransporter-2 and Glucagon-Like Peptide-1
- Hypoglycemia Awareness and Prevention
- Remission and Reversal Strategies
- CGM and Time-in-Range
- Hemoglobin A1c, Fructosamine, and Glycation Markers
- Complications: Retinopathy, Nephropathy, Neuropathy
- Diabetic Foot Care and Ulcer Prevention
- Insulin Resistance
- Obesity
- Metabolic Syndrome
- Hashimoto's Thyroiditis
- Gestational Diabetes
- Continuous Glucose Monitor
- Peripheral Neuropathy
- Glucagon-Like Peptide-1 Receptor Agonists
- Fasting