Sulforaphane for Brain and Cognitive Health
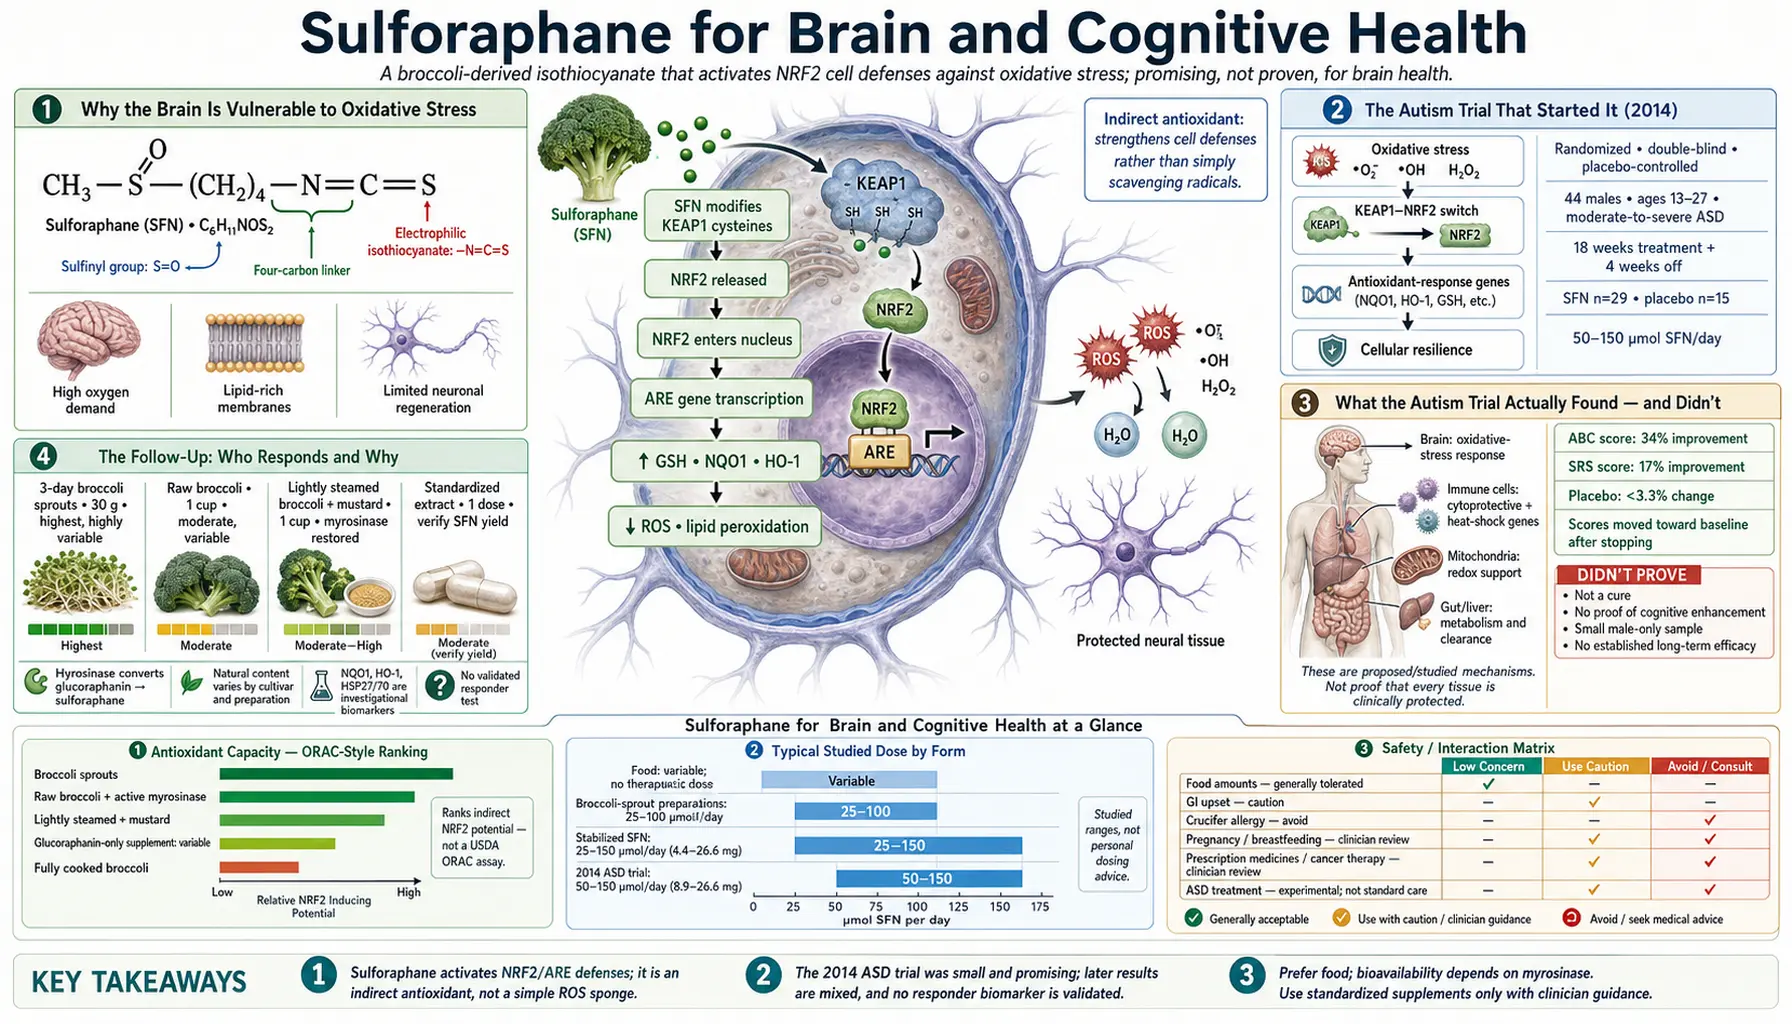
Sulforaphane's brain research is genuinely interesting — and genuinely preliminary. A 2014 randomized trial reported behavioral improvements in young men with autism, a small open-label follow-up study found urinary chemical signatures that tracked symptom changes, a 7-day human imaging pilot reported a rise in glutathione levels inside the living brain, and a small open-label study explored schizophrenia. Later randomized trials in children with autism and in schizophrenia found no significant benefit on their main measures, with some smaller signals described below. The underlying logic is coherent: the brain is unusually vulnerable to oxidative stress and inflammation, and sulforaphane raises the brain's antioxidant defenses. But every one of these studies is small, early, and in need of replication. This page lays out exactly what was found and, just as importantly, what was not — because the autism field in particular has been plagued by overhyped and even dangerous "treatments."
Interactive Visualization Free Radicals & Your Antioxidant Network Follow one superoxide radical down the whole relay — superoxide dismutase (SOD), catalase, glutathione, vitamin E, vitamin C, reduced nicotinamide adenine dinucleotide phosphate (NADPH) — then release free iron and watch a membrane tear itself apart. Launch →
Table of Contents
- Why the Brain Is Vulnerable to Oxidative Stress
- The Autism Trial That Started It (2014)
- What the Autism Trial Actually Found — and Didn't
- Later Autism Trials in Children (2021–2025)
- The Follow-Up: Urinary Markers That Tracked Symptom Changes
- How Far Sulforaphane Reaches Into the Brain: Glutathione Imaging
- Schizophrenia: An Open-Label Signal, Then Randomized Trials
- Neurodegeneration Research (Preclinical)
- How to Read This Evidence Honestly
- Practical Notes for Families Considering It
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Why the Brain Is Vulnerable to Oxidative Stress
The brain is a natural target for an Nrf2-activating antioxidant for several structural reasons. It consumes about 20% of the body's oxygen despite being only 2% of its weight, so it generates a large volume of reactive oxygen species. It is rich in polyunsaturated fatty acids, which are especially prone to oxidative damage. And its own antioxidant defenses — particularly glutathione — are comparatively modest relative to that oxidative load. Add neuroinflammation, driven by activated microglia releasing inflammatory cytokines, and you have the two exact processes sulforaphane is best at countering: oxidative stress (via Nrf2 induction) and inflammation (via NF-κB suppression), both described on the Antioxidant & Cellular Protection page.
Oxidative stress and neuroinflammation are documented features of a wide range of neurological and neurodevelopmental conditions, including autism spectrum disorder, schizophrenia, and the major neurodegenerative diseases. That shared biology is why a single compound has been investigated across such different-looking conditions — the common denominator is redox and inflammatory imbalance in brain tissue.
The Autism Trial That Started It (2014)
The study that put sulforaphane on the neuroscience map was published in PNAS in 2014 by Kanwaljit Singh, Andrew Zimmerman, and colleagues. It was a randomized, double-blind, placebo-controlled trial — the gold-standard design — in 44 young men (aged 13–27) with moderate-to-severe autism spectrum disorder: 29 received sulforaphane and 15 received placebo. Participants received a daily dose of sulforaphane (derived from broccoli-sprout extract, roughly 50–150 µmol depending on body weight) or placebo for 18 weeks.
The rationale was specific. A subset of children with autism had been observed to show temporary behavioral improvement during febrile illness (the "fever effect"), and the researchers hypothesized this reflected a heat-shock and stress-response mechanism that sulforaphane, as an Nrf2 and heat-shock-protein inducer, might mimic pharmacologically. It was a mechanistically motivated experiment, not a shot in the dark.
What the Autism Trial Actually Found — and Didn't
Behavior was rated by clinicians and caregivers using standard instruments (the Aberrant Behavior Checklist, the Social Responsiveness Scale, and clinical global impression scales). The results:
- After 18 weeks, scores improved by 34% on the Aberrant Behavior Checklist (P < 0.001, comparing treatments) and by 17% on the Social Responsiveness Scale (P = 0.017) with sulforaphane, while the placebo group showed minimal change (<3.3%).
- The sulforaphane group showed statistically significant improvements versus placebo in measures of aberrant behavior, social interaction, and verbal communication over the 18 weeks.
- A meaningful fraction of the treated group were rated as "much" or "very much" improved by clinicians, versus few on placebo.
- The effect was not universal — many participants did not respond, and the study was small (44 people).
- The improvements reversed after sulforaphane was stopped, with scores drifting back toward baseline — consistent with a symptomatic, not curative, effect.
- Sulforaphane was well tolerated, with no serious adverse events attributable to it.
What the trial did not show is equally important. It did not show that sulforaphane cures or reverses autism. It did not change the underlying neurodevelopmental condition. It did not test children (participants were adolescents and young adults); the later trials in children are described in the next section. And with only 44 participants at a single research program, it needs independent replication in larger, more diverse groups before any firm clinical conclusion can be drawn. It is a promising proof-of-concept, nothing more and nothing less.
Later Autism Trials in Children (2021–2025)
The 2014 result has since been tested in children, with weaker results.
- 2021 trial in 57 children. Zimmerman and colleagues ran a 15-week randomized, double-blind, placebo-controlled trial in 57 children aged 3–12 with autism spectrum disorder (28 assigned sulforaphane, 29 placebo), followed by 15 weeks of open-label treatment. On the main measure, the Ohio Autism Clinical Impressions Scale (OACIS), the difference between sulforaphane and placebo was not significant at 7 and 15 weeks. Caregiver ratings on the Aberrant Behavior Checklist improved significantly more with sulforaphane at 15 weeks, but ratings on the Social Responsiveness Scale-2 did not. The authors wrote that the clinical effects were less notable in children than in their earlier trial in young men. Side effects, none serious, included rare insomnia, irritability and intolerance of the taste and smell.
- 2023 trial in 40 children. Magner and colleagues randomized 40 children aged 3–7 to sulforaphane or placebo in a double-blind study lasting 36 weeks; 28 completed it. Scores on the Aberrant Behaviour Checklist and the Social Responsiveness Scale-2 improved in both groups, but none of the changes reached statistical significance, and the authors "found no significant clinical improvement in the behavioural outcome measures."
- 2025 pooled analysis of six trials. A systematic review and meta-analysis by Wang and colleagues pooled six randomized controlled trials. Sulforaphane significantly improved total symptoms (standardized mean difference -0.27, 95% confidence interval -0.42 to -0.12), aberrant behavior, hyperactivity, social interaction, social communication, and restricted and repetitive behaviors. Effects on irritability, anxiety, sensory sensitivity and several social-skill measures were not statistically significant. Adverse events were similar between the sulforaphane and control groups. The authors wrote that the results should be interpreted cautiously because of possible influences from assessment tools, outcome assessors and treatment duration.
The Follow-Up: Urinary Markers That Tracked Symptom Changes
Stephen Bent and colleagues followed up in a 2018 study in Molecular Autism. It was a 12-week open-label study (no placebo group) of sulforaphane in children and young adults at a school for autism and related neurodevelopmental disorders, and 15 children completed it. Its stated goal was identifying a potential mechanism of action. Both symptom scores improved, but only the change on the Social Responsiveness Scale was significant (an improvement of 9.7 points); the Aberrant Behavior Checklist improved by 7.1 points, which was not significant. The researchers identified 77 urinary metabolites that correlated with changes in symptoms, and these clustered into pathways of oxidative stress, amino acid and gut-microbiome metabolism, neurotransmitters, hormones, and sphingomyelin metabolism.
The authors concluded that urinary metabolomics is a useful tool to identify pathways that may be involved in how such treatments work. The practical hope is a future ability to identify, from a simple urine test, the subgroup of individuals whose biology makes them likely to benefit — moving from "sulforaphane helps some people with autism, we don't know who" toward "sulforaphane helps people with this specific metabolic signature." That biomarker-guided precision approach is still in the research phase and is not clinically available, but it is the sensible scientific direction and it reinforces a recurring theme: sulforaphane response is highly individual.
How Far Sulforaphane Reaches Into the Brain: Glutathione Imaging
An obvious skeptical question is whether an orally eaten broccoli compound even reaches the brain in a way that changes brain chemistry. Thomas Sedlak and colleagues addressed this directly in a 2018 human pilot study using magnetic resonance spectroscopy (MRS), an imaging method that measures the concentration of specific chemicals inside living brain tissue non-invasively.
Healthy volunteers took sulforaphane by mouth daily for 7 days, and their blood glutathione rose. In parallel, the researchers explored brain glutathione in three regions (the anterior cingulate cortex, the hippocampus, and the thalamus) with 7-tesla MRS, and reported "a consistent increase in brain GSH levels in response to treatment." A significant correlation between the blood and brain changes was seen in the thalamus. This is an early bridge: it suggests the mechanism proposed for the behavioral trials is physically plausible. It does not, by itself, prove clinical benefit, and as a small pilot in healthy volunteers it awaits confirmation.
Schizophrenia: An Open-Label Signal, Then Randomized Trials
Because oxidative stress and glutathione deficits are implicated in schizophrenia, the same logic has been extended there. Shiina and colleagues ran a small open-label study in 2015 giving sulforaphane-rich broccoli-sprout extract (30 mg of sulforaphane-glucosinolate a day for 8 weeks) to 10 outpatients with schizophrenia. Of the 7 who completed it, scores improved significantly on one cognitive test (the Accuracy component of the One Card Learning Task), with no other significant changes. This was an open-label study — no placebo group, everyone knew they were getting the active compound — which is the weakest trial design and highly prone to expectation effects. It is best read as a hypothesis-generating pilot that justifies a proper randomized trial, not as evidence that sulforaphane treats schizophrenia. See our Psychiatry section for context on the condition.
Randomized trials followed. A 2025 systematic review and meta-analysis by Kassar and colleagues pooled four randomized controlled trials with 369 patients with schizophrenia. Sulforaphane did not significantly improve the overall score or the positive-symptom score on the Positive and Negative Syndrome Scale (PANSS). Negative symptoms improved modestly at 12 weeks (mean difference -1.06), but this was not maintained at the latest follow-up; general psychopathology scores improved significantly (mean difference -1.5). No cognitive benefits were observed. Low-density lipoprotein (LDL) cholesterol, triglycerides and total cholesterol fell significantly, and fewer people stopped treatment in the sulforaphane groups (relative risk 0.68). The authors wrote that, because of limited data and differences between the trials, the findings should be interpreted with caution.
Neurodegeneration Research (Preclinical)
Sulforaphane has been widely studied in cell and animal models of neurodegenerative disease, reviewed by Tarozzi and colleagues. In these preclinical models, Nrf2 activation protects neurons against the oxidative and inflammatory damage central to Alzheimer's disease and Parkinson's disease — reducing markers of protein aggregation, mitochondrial dysfunction, and microglial inflammation, and preserving cognitive or motor performance in treated animals.
These are genuinely encouraging mechanistic results, but the caveat is large and familiar: the vast majority of this evidence is preclinical. Countless compounds protect neurons in a mouse and then fail in human trials. Sulforaphane has not been shown in adequate human trials to prevent, slow, or treat any neurodegenerative disease. It represents a plausible research direction supported by strong mechanism and animal data, awaiting the human outcome trials that would be needed to make any clinical claim. See our Neurology section.
How to Read This Evidence Honestly
A fair summary of the whole brain literature on sulforaphane:
- Mechanism: coherent — the brain has exactly the oxidative/inflammatory vulnerabilities sulforaphane addresses, and a small 7-day pilot in healthy volunteers found blood glutathione rose and reported a consistent increase in brain glutathione.
- Autism: a handful of small randomized trials with mixed results — the 2014 trial in young men found a positive but non-curative, reversible, and non-universal effect; the 2021 and 2023 trials in children found no significant benefit on their main measures; a 2025 pooling of six trials found a small improvement in total symptoms. Not an established treatment.
- Schizophrenia: a 2025 pooling of four randomized trials (369 patients) found no improvement in overall symptoms or cognition, with a modest short-term change in negative symptoms that did not last.
- Neurodegeneration: preclinical only — hypothesis-generating, not clinically actionable.
The research supports neither dismissal nor hype. Sulforaphane is one of the more scientifically credible dietary compounds being investigated for brain health, and that investigation deserves to continue — but "under active study" is not "proven."
Practical Notes for Families Considering It
Families of people with autism or other neurological conditions understandably read the headlines and wonder whether to try broccoli-sprout extract. A few honest, practical points:
- Side effects reported in the trials. In the 2021 trial in 57 children, sulforaphane was very well tolerated; side effects, none serious, included rare insomnia, irritability and intolerance of the taste and smell, and clinical laboratory tests confirmed product safety.
- Studied as a possible adjunct, not a replacement. Sulforaphane has not been shown to substitute for evidence-based autism support (behavioral, educational, speech, and occupational therapies) or for prescribed psychiatric care.
- Dosing in trials came from concentrated, standardized extracts. The autism trial used carefully quantified sulforaphane (tied to body weight), not a handful of grocery-store sprouts. Ordinary dietary sprouts are healthy food but deliver variable, generally lower doses.
- Response is individual and reversible. Even in the positive trial, many did not respond, and benefits faded when treatment stopped.
- Food sources are low-risk. Regular cruciferous vegetables and sprouts are a sound, low-risk part of a healthy diet for the whole family, independent of any specific neurological hope (raw sprouts carry the hygiene concern listed under Cautions).
Cautions
- Not an approved treatment. Sulforaphane is not an approved therapy for autism, schizophrenia, Alzheimer's, Parkinson's, or any neurological condition. Research is preliminary.
- Children. The safety data in children come from small trials; in the 2021 trial in 57 children, side effects were rare and none were serious.
- Well tolerated but not risk-free. Trials report good tolerability (mild gastrointestinal effects), but long-term high-dose safety data in neurological populations are limited.
- Overstated claims. The autism field attracts unproven and sometimes harmful "cures." Sulforaphane's modest research does not support miracle claims or the replacement of established supports.
- Raw-sprout hygiene. The hygiene concern with raw sprouts matters most for immunocompromised people, for whom lightly cooked broccoli is the lower-risk source — see the Sources & Bioavailability page.
Key Research Papers
- Singh K, et al. (2014). Sulforaphane treatment of autism spectrum disorder (ASD). PNAS — PubMed PMID: 25313065
- Bent S, et al. (2018). Identification of urinary metabolites that correlate with clinical improvements in children with autism treated with sulforaphane from broccoli. Molecular Autism — PubMed PMID: 29854372
- Zimmerman AW, et al. (2021). Randomized controlled trial of sulforaphane and metabolite discovery in children with Autism Spectrum Disorder. Molecular Autism — PubMed PMID: 34034808
- Magner M, et al. (2023). Sulforaphane Treatment in Children with Autism: A Prospective Randomized Double-Blind Study. Nutrients — PubMed PMID: 36771424
- Wang R, Ren Z, Li Y (2025). The effect of sulforaphane on autism spectrum disorder: systematic review and meta-analysis. EXCLI Journal — PubMed PMID: 40458076
- Sedlak TW, et al. (2018). Sulforaphane Augments Glutathione and Influences Brain Metabolites in Human Subjects: A Clinical Pilot Study. Molecular Neuropsychiatry — PubMed PMID: 29888232
- Shiina A, et al. (2015). An Open Study of Sulforaphane-rich Broccoli Sprout Extract in Patients with Schizophrenia. Clinical Psychopharmacology and Neuroscience — PubMed PMID: 25912539
- Kassar O, et al. (2025). Efficacy and safety of sulforaphane in schizophrenia: a systematic review and meta-analysis of randomized controlled trials. BMC Psychiatry — PubMed PMID: 41184790
- Tarozzi A, et al. (2013). Sulforaphane as a potential protective phytochemical against neurodegenerative diseases. Oxidative Medicine and Cellular Longevity — PubMed PMID: 23983898
- Dinkova-Kostova AT, Fahey JW, Kostov RV, Kensler TW (2017). KEAP1 and Done? Targeting the NRF2 Pathway with Sulforaphane. Trends in Food Science & Technology — PubMed PMID: 29242678
- Houghton CA, Fassett RG, Coombes JS (2016). Sulforaphane and Other Nutrigenomic Nrf2 Activators: Can the Clinician's Expectation Be Matched by the Reality? Oxidative Medicine and Cellular Longevity — PubMed PMID: 26881038
- Vanduchova A, Anzenbacher P, Anzenbacherova E (2019). Isothiocyanate from Broccoli, Sulforaphane, and Its Properties. Journal of Medicinal Food — PubMed PMID: 30372361
- Dinkova-Kostova AT, et al. (2002). Direct evidence that sulfhydryl groups of Keap1 are the sensors regulating induction of phase 2 enzymes. PNAS — PubMed PMID: 12193649
- Zhang Y, Talalay P, Cho CG, Posner GH (1992). A major inducer of anticarcinogenic protective enzymes from broccoli: isolation and elucidation of structure. PNAS — PubMed PMID: 1549603
PubMed Topic Searches
External Authoritative Resources
Connections
- Free Radicals & Your Antioxidant Network — interactive animation
- Sulforaphane (Main Page)
- Sulforaphane Benefits Hub
- Antioxidant & Cellular Protection
- Detoxification & Nrf2
- Glutathione
- Melatonin
- Ergothioneine
- Autism
- Autism Spectrum Disorder (Pediatrics)
- Alzheimer's Disease
- Parkinson's Disease
- Psychiatry
- Neurology
- All Antioxidants