French Maritime Pine Bark for Circulation and Vein Health
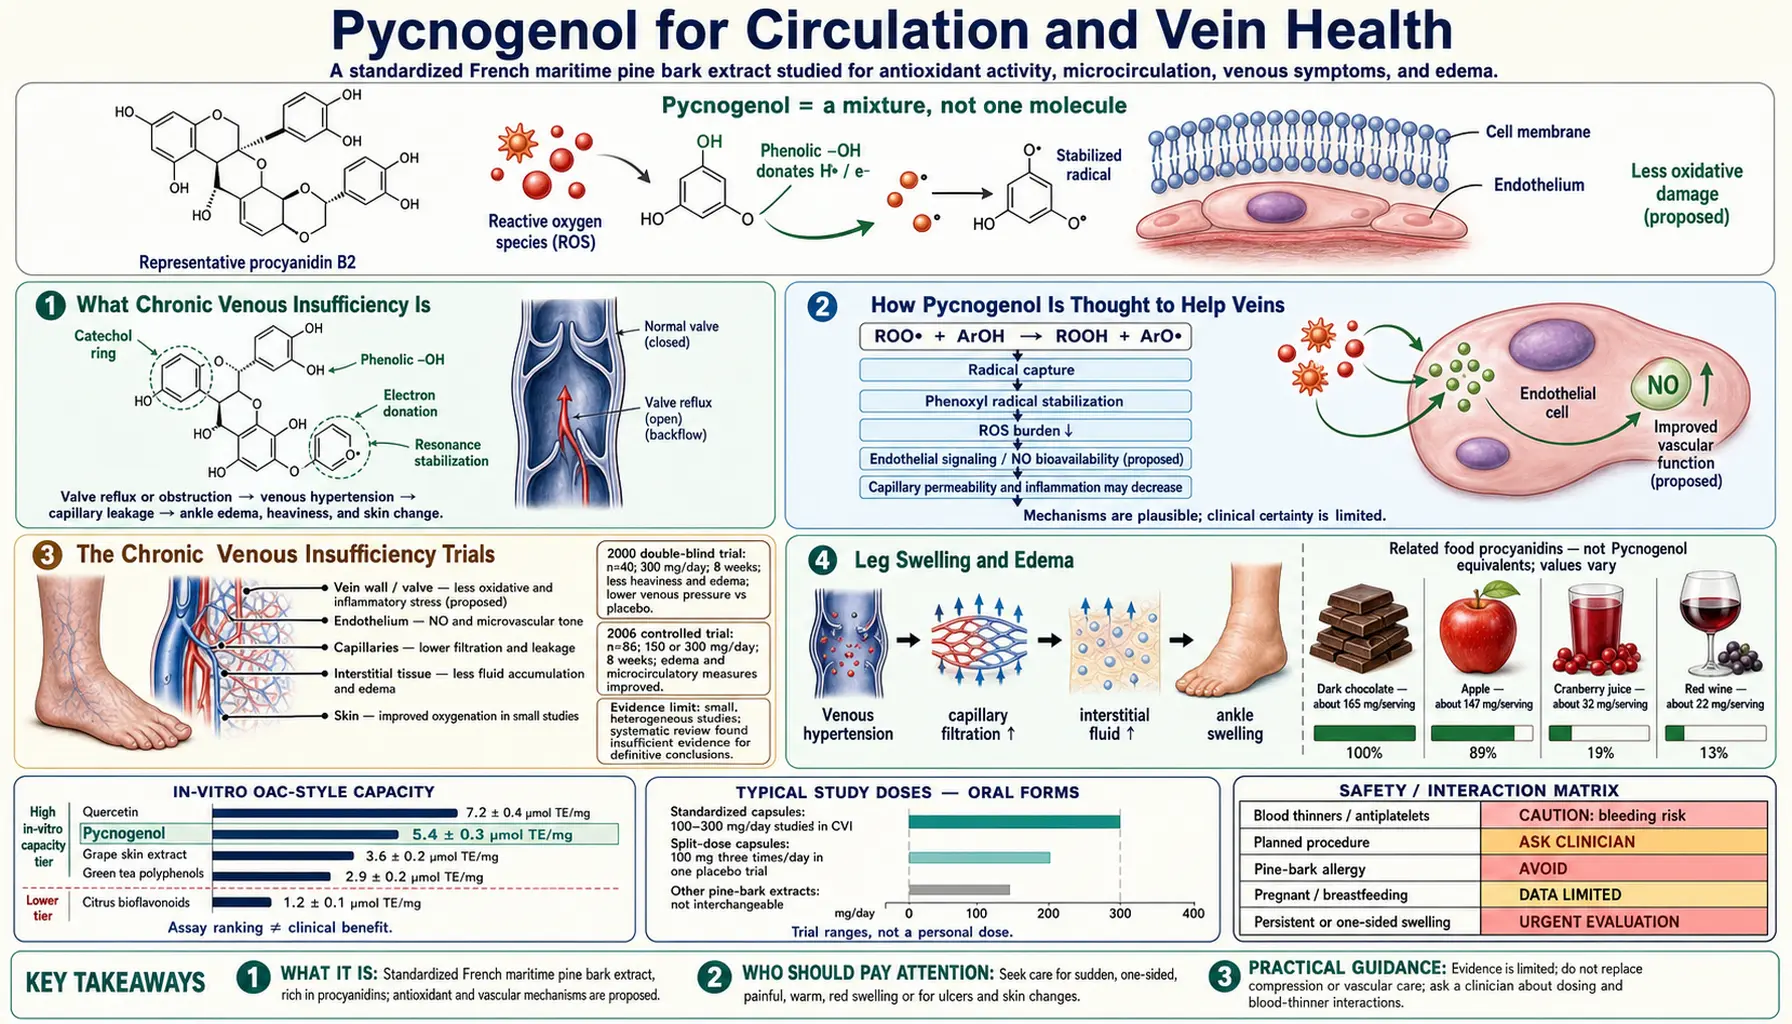
If French maritime pine bark extract has one use where the evidence is strongest and the mechanism makes the most sense, it is heavy, aching, swollen legs — the everyday face of chronic venous insufficiency. Procyanidins are thought to seal leaky capillaries, strengthen the vein wall, and improve blood flow through the smallest vessels, and a series of controlled trials report less swelling, less heaviness, and less pain. This page walks through what venous insufficiency is, how the extract is believed to work, the trial evidence (including head-to-head comparisons with compression stockings and with a prescription venotonic drug), the long-haul-flight studies, and the honest limits of that evidence — because even here, the 2020 Cochrane review rated the certainty of the research evidence as very low.
Table of Contents
- What Chronic Venous Insufficiency Is
- How Pine Bark Extract Is Thought to Help Veins
- The Chronic Venous Insufficiency Trials
- Leg Swelling and Edema
- Compared With Compression and Other Venotonics
- Long-Haul Flights: Edema and Clots
- Venous Leg Ulcers and Microcirculation
- Beyond the Legs: Retinal Microcirculation
- Practical Use: Dose, Timing, Expectations
- Cautions and the Evidence Caveat
- Key Research Papers
- External Resources
- Connections
- Featured Videos
What Chronic Venous Insufficiency Is
Veins carry blood back to the heart against gravity. In the legs, that job depends on two things: the squeeze of the calf muscles (the “muscle pump”) and a series of one-way valves inside the veins that stop blood from falling back down. When those valves weaken or the vein walls stretch, blood pools in the lower legs — a condition called chronic venous insufficiency (CVI). It is extremely common, especially with age, pregnancy, prolonged standing, and being overweight.
The pooling raises pressure inside the tiny capillaries, and that pressure forces fluid out into the surrounding tissue. The result is the familiar cluster of symptoms: swelling (edema) around the ankles that is worse by evening, a feeling of heaviness or tiredness in the legs, aching, cramping, itching, restless legs, and visible varicose veins. In more advanced disease the skin can darken, harden, and eventually break down into a slow-healing venous ulcer.
Standard care is compression (stockings), leg elevation, exercise, weight management, and in selected cases procedures to close faulty veins. “Venotonic” or “phlebotonic” agents — oral compounds meant to firm the vein and reduce leakage — are widely used in Europe as an add-on. Pine bark extract sits in this venotonic category, and CVI is the setting where it has been studied the most.
How Pine Bark Extract Is Thought to Help Veins
The proposed mechanisms map neatly onto the problem of a leaky, poorly toned venous system:
- Reducing capillary permeability. The central idea is that oligomeric procyanidins reduce the leakiness of capillaries — the exact step that turns venous back-pressure into visible ankle swelling. Less leakage means less fluid escaping into the tissue.
- Protecting collagen and elastin. Procyanidins bind to these connective-tissue proteins, which form the scaffolding of the vein wall and the capillary basement membrane. By resisting their breakdown by enzymes and free radicals, the extract may help the vessel keep its structure and tone.
- Improving microcirculation and nitric oxide. By supporting endothelial nitric oxide, the extract may improve flow through the smallest vessels, helping clear the congestion that makes legs feel heavy. Improved microcirculation is a recurring measured outcome in the trials.
- Calming inflammation. Venous disease has an inflammatory component; the anti-inflammatory (NF-κB-dampening) action may contribute to reduced aching and swelling.
These are the same four mechanisms described on the Benefits hub. What makes the venous story relatively convincing is that the mechanism (sealing leaky capillaries) and the measured outcome (less edema) line up directly.
The Chronic Venous Insufficiency Trials
Several controlled studies have tested the standardized extract in CVI. Petrassi and colleagues (2000) reported that supplementation reduced symptoms and signs of venous insufficiency compared with placebo. Their study had a double-blind phase, in which 20 patients were randomly given placebo or the extract (100 mg doses for 2 months), and an open phase in which another 20 patients took the extract on the same schedule; in total 30 took the extract and 10 placebo. The extract significantly improved leg heaviness and swelling under the skin, and venous pressure was also significantly reduced. Cesarone and colleagues (2010) ran a prospective controlled study in CVI with microangiopathy (small-vessel disease) and reported improvement in both symptoms and objective microcirculatory measures, including reduced ankle swelling and improved capillary filtration. They randomly assigned 98 people with symptomatic CVI and swelling to 150 mg of the extract a day, to elastic stockings, or to both; after 8 weeks all three groups improved, the combination gave significantly better results, and the extract alone did better than stockings alone on every measure.
Across this body of work, the consistent findings are reduced edema, less leg heaviness and pain, and improvements in laboratory measures of microcirculation. The important qualifier is that many of these studies come from a single research group in Italy and are not always double-blinded or independently replicated. That does not make the results wrong, but it means they read as promising rather than definitive — a point the Standardization & Safety page returns to.
Leg Swelling and Edema
Ankle and lower-leg swelling is the symptom pine bark extract most reliably moves in the studies. Edema is measured objectively — by ankle circumference, by water displacement, or by a technique called capillary filtration rate that gauges how fast fluid leaks into tissue. Trials in CVI patients report reductions in these measures alongside patients' own reports of lighter, less swollen legs.
The edema effect is also what underlies the long-haul-flight studies discussed below, where the “condition” is not a disease at all but the ordinary swelling healthy people get from sitting still for many hours in a low-pressure cabin. Because the mechanism is about capillary leakage rather than a specific disease, the anti-edema effect appears in several settings.
Compared With Compression and Other Venotonics
Some of the more useful trials put the extract head-to-head with established treatments rather than only against placebo:
- Versus a prescription venotonic (micronized purified flavonoid fraction, widely used in Europe). Cesarone and colleagues (2006) compared the two in CVI and reported that pine bark extract produced at least comparable — in their data, somewhat greater — symptom and edema improvement.
- Versus compression stockings. Comparative studies (including Belcaro's 2015 comparison with a red vine leaf extract and stockings, and a 2024 study alongside elastic compression) suggest the extract can improve edema and microcirculation, sometimes in the same range as compression. Compression stockings remain the first-line, inexpensive standard; these results point to a possible role for the extract as an add-on, or for people who cannot tolerate compression.
The wider class of vein drugs has been reviewed as a whole. A 2020 Cochrane review of oral phlebotonics (venotonic drugs) included 69 randomized trials, of which 56 (7690 participants, average age 50) gave usable data; two of them tested French maritime pine bark extract. Compared with placebo, moderate-certainty evidence showed that phlebotonics probably reduce swelling in the lower legs slightly (risk ratio, RR, 0.70; 13 studies; 1245 participants) and probably reduce ankle circumference (by an average of 4.27 mm). They probably make little or no difference to quality of life, may have little or no effect on ulcer healing (RR 0.94; low-certainty evidence), and probably increase side effects slightly (RR 1.14), stomach and gut upsets being the most often reported. The reviewers noted that the trials gave only short-term safety data and that findings for individual groups of these drugs are limited by small study numbers.
Read plainly, these comparisons show pine bark extract behaving like a legitimate venotonic. Whether it is truly equal or superior to compression cannot be settled from small, mostly single-group studies — but the signal is consistent.
Long-Haul Flights: Edema and Clots
A distinctive line of research looked at long-haul air travel, where immobility, dehydration, and cabin pressure combine to swell the legs and, in higher-risk travelers, raise the odds of a clot (deep vein thrombosis, DVT). Cesarone and colleagues (2005) reported that the extract reduced flight-related leg edema compared with placebo: of 211 people without symptoms who were included, 169 completed the study, and after the flight the edema score rose by 17.9% with the extract versus 58.3% in the control group. Belcaro and colleagues (2004) reported fewer episodes of venous thrombosis and superficial thrombophlebitis in higher-risk long-haul passengers taking the extract. In that study 198 passengers at moderate to high risk completed follow-up, and flights lasted on average 8 hours and 15 minutes; the control group had five clotting events (one deep vein thrombosis and four superficial thromboses), while the extract group had none, only localized phlebitis without a clot.
These findings are intriguing and consistent with the anti-edema and mild antiplatelet effects, but they are preliminary: they come from the same investigator group, and clot prevention is a serious claim that has not had large, independent, randomized confirmation. For high-risk travelers, the established measures — moving regularly, hydration, compression stockings, and medical anticoagulation when indicated — remain the standard of care, and these studies do not establish the extract as an alternative to them.
Venous Leg Ulcers and Microcirculation
At the severe end of venous disease, chronically congested skin can break down into a venous leg ulcer that heals very slowly. Toledo and colleagues (2017) randomly assigned 30 adults with venous ulcers to oral pine bark extract (50 mg three times daily) or to diosmin/hesperidin, an oral vein drug used as add-on treatment for chronic venous insufficiency, and followed them for 90 days; ulcers healed similarly in both groups, and both treatments significantly reduced the circumference of the affected leg. The authors concluded that the extract has an add-on effect on ulcer healing similar to diosmin/hesperidin. Belcaro's group has similarly reported microcirculatory improvements in diabetic and venous microangiopathy.
Venous ulcers are treated with wound care and compression; in this study the extract was tested only as an adjunct to standard care, not as a stand-alone treatment. The direction of the evidence — better microcirculation and healing comparable to an established venotonic — fits the rest of the venous story.
Beyond the Legs: Retinal Microcirculation
The same “seal the leaky small vessels” mechanism has been studied in the eye. Steigerwalt and colleagues (2009) reported that the extract improved retinal microcirculation, reduced retinal edema, and improved visual acuity in people with early diabetic retinopathy — a disease of leaky retinal capillaries that is, in a sense, the eye's version of what happens in the legs. Earlier reviews (Schönlau and Rohdewald, 2001) summarized similar signals for vascular retinopathies.
This is early evidence in a serious eye condition, and diabetic retinopathy is managed by an ophthalmologist. It is included here because it illustrates the unifying theme: wherever tiny blood vessels leak, the procyanidin mechanism has been tested, with generally positive but preliminary results.
Practical Use: Dose, Timing, Expectations
Most venous trials used a single standardized, patented French maritime pine bark extract; results may not transfer to other pine bark products. Doses were typically roughly 100–360 mg per day, most often 150–300 mg divided into two or three doses with meals, taken by mouth as tablets or capsules. Benefits built over weeks rather than days — most studies ran for four to twelve weeks, and reduced heaviness and swelling tended to appear gradually over that window.
In these studies pine bark extract acted as a symptom-and-comfort intervention for venous disease: it may make legs feel lighter and look less swollen, and it may complement compression. It does not repair failed valves or make varicose veins disappear, and it is not a substitute for compression, exercise, weight management, or, when indicated, a vein procedure. New or one-sided leg swelling, calf pain, or a leg ulcer can signal a clot or other problem that needs medical evaluation.
Cautions and the Evidence Caveat
- Evidence quality. The 2020 Cochrane review (Robertson et al.) of pine bark extract rated every outcome it assessed as very low-certainty evidence (for chronic venous insufficiency it found two studies with 60 participants) and concluded that “no definitive conclusions regarding the efficacy or safety of pine bark extract supplements are possible”; the 2012 Cochrane review (Schoonees et al.) reached a similar cautious verdict. Much of the venous research comes from a single research group. Positive results are encouraging, not settled.
- Bleeding and blood thinners. Because pine bark extract may modestly reduce platelet stickiness, the research raises a concern for people taking anticoagulants (warfarin, apixaban) or antiplatelet drugs (aspirin, clopidogrel), and around surgery. Decisions about combinations belong with a clinician.
- Blood pressure. The extract can nudge blood pressure down; in people taking antihypertensives, the effects may add together.
- Red-flag symptoms. Sudden one-sided leg swelling, warmth, and pain can indicate a deep vein thrombosis — a medical emergency that needs urgent medical care, which a supplement does not replace.
- Pregnancy. Some venous studies were done in late pregnancy: in a 2006 study, women in the third trimester with lower back, hip or pelvic pain, pain from varicose veins or calf cramps took 30 mg a day and reported a significant reduction in pain scores compared with a control group, with no unwanted effects observed. Safety data are still limited; decisions in pregnancy belong with a clinician. See the Standardization & Safety page.
Key Research Papers
- Petrassi C, Mastromarino A, Spartera C (2000). Pycnogenol in chronic venous insufficiency. Phytomedicine — PubMed PMID: 11081989
- Cesarone MR et al. (2006). Comparison of Pycnogenol and Daflon in treating chronic venous insufficiency: a prospective, controlled study. Clinical and Applied Thrombosis/Hemostasis — PubMed PMID: 16708123
- Cesarone MR et al. (2010). Improvement of signs and symptoms of chronic venous insufficiency and microangiopathy with Pycnogenol: a prospective, controlled study. Phytomedicine — PubMed PMID: 20579863
- Belcaro G (2015). A clinical comparison of Pycnogenol, Antistax, and stocking in chronic venous insufficiency. International Journal of Angiology — PubMed PMID: 26648668
- Belcaro G et al. (2024). Improvements in edema and microcirculation in chronic venous insufficiency with Pycnogenol or elastic compression. Minerva Surgery — PubMed PMID: 38953757
- Cesarone MR et al. (2005). Prevention of edema in long flights with Pycnogenol. Clinical and Applied Thrombosis/Hemostasis — PubMed PMID: 16015414
- Belcaro G et al. (2004). Prevention of venous thrombosis and thrombophlebitis in long-haul flights with Pycnogenol. Clinical and Applied Thrombosis/Hemostasis — PubMed PMID: 15497024
- Toledo RR et al. (2017). Effect of Pycnogenol on the healing of venous ulcers. Annals of Vascular Surgery — PubMed PMID: 27521821
- Belcaro G et al. (2017). Postpartum varicose veins: supplementation with Pycnogenol or elastic compression — a 12-month follow-up. International Journal of Angiology — PubMed PMID: 28255210
- Steigerwalt R et al. (2009). Pycnogenol improves microcirculation, retinal edema, and visual acuity in early diabetic retinopathy. Journal of Ocular Pharmacology and Therapeutics — PubMed PMID: 19916788
- Gulati OP (2014). Pycnogenol in chronic venous insufficiency and related venous disorders. Phytotherapy Research — PubMed PMID: 23775628
- Robertson NU, Schoonees A, Brand A, Visser J (2020). Pine bark (Pinus spp.) extract for treating chronic disorders. Cochrane Database of Systematic Reviews — PubMed PMID: 32990945
- Martinez-Zapata MJ, Vernooij RW, Simancas-Racines D, Uriona Tuma SM, Stein AT, Moreno Carriles RMM, Vargas E, Bonfill Cosp X (2020). Phlebotonics for venous insufficiency. Cochrane Database of Systematic Reviews — PubMed PMID: 33141449
- Kohama T, Inoue M (2006). Pycnogenol alleviates pain associated with pregnancy. Phytotherapy Research — PubMed PMID: 16521117
- Schoonees A et al. (2012). Pycnogenol (extract of French maritime pine bark) for the treatment of chronic disorders. Cochrane Database of Systematic Reviews — PubMed PMID: 22513958
PubMed Topic Searches
External Resources
- Cochrane Review (2020) — Pine bark extract for chronic disorders (independent, cautious assessment)
- Drugs.com — pine bark extract monograph (uses, dosing, interactions)
- PubMed — pine bark extract and venous disease