⚠ Evidence warning: Clinical trials or other evidence do not support the claim that people with darker skin or a working MC1R receptor respond better to phenylalanine plus ultraviolet A, and that added nutrients (copper, vitamin D3, vitamins C and E, alpha-lipoic acid, L-tyrosine) support response rates and reduce relapse. This page keeps it as a report of what people, websites or other media say.
Phenylalanine for Skin Pigmentation and Vitiligo
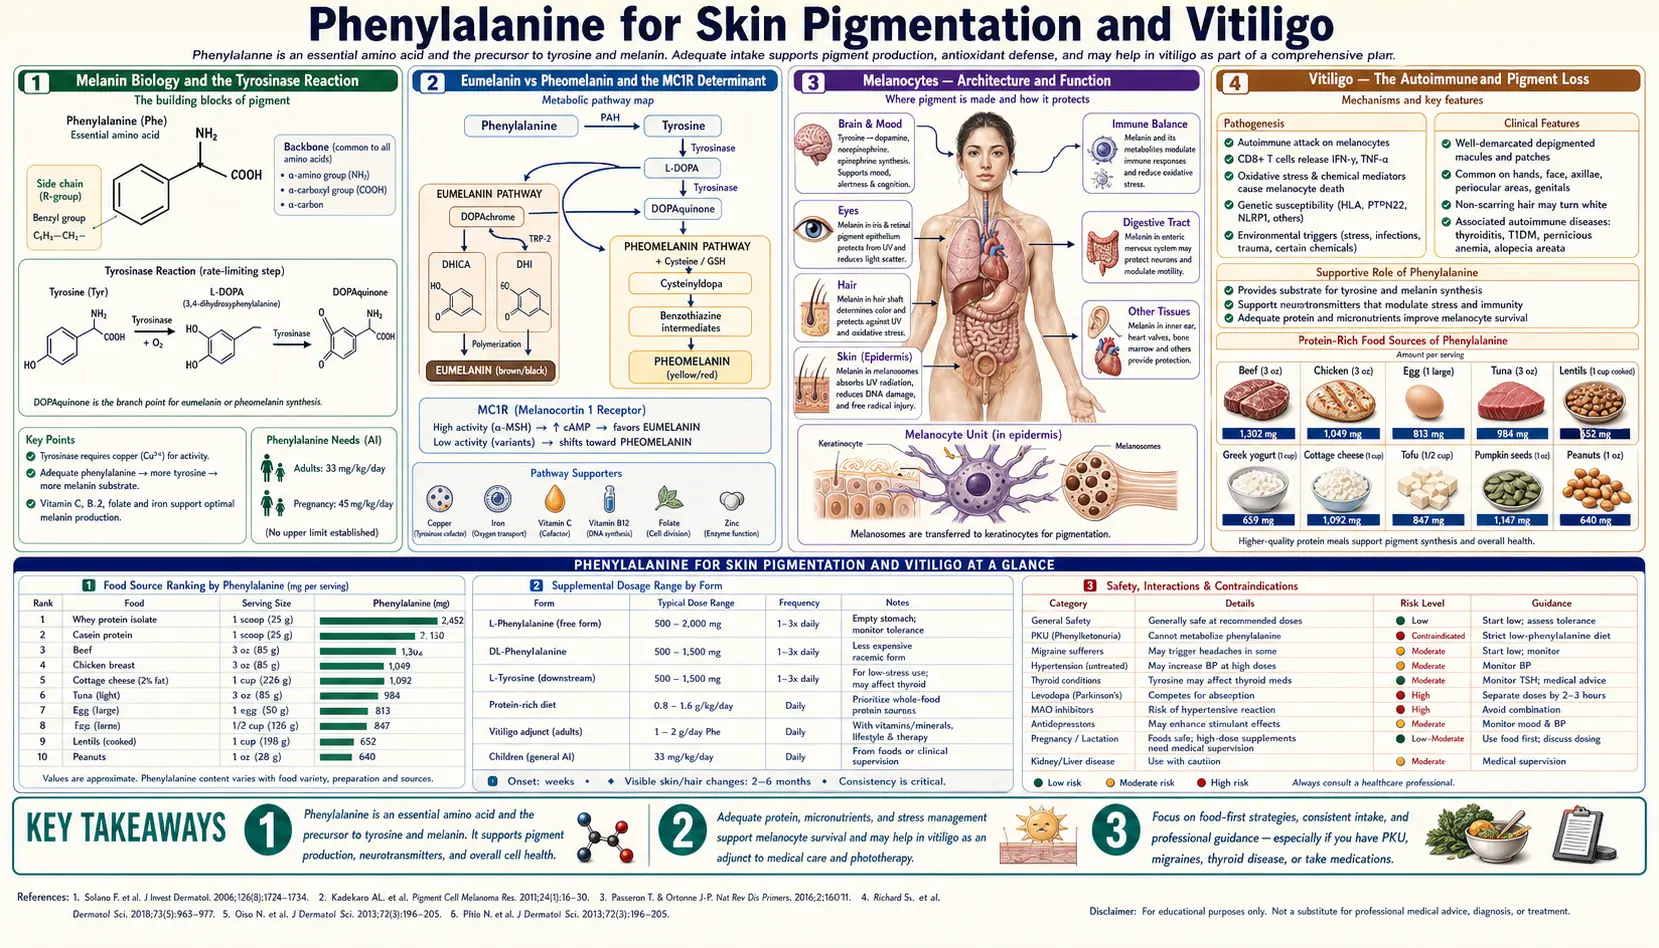
The same biochemical pathway that converts phenylalanine to tyrosine to L-DOPA also delivers the substrate for melanin — the pigment that gives skin, hair, and eyes their color and that protects the genome of every superficial skin cell from ultraviolet damage. In specialized melanocyte cells of the epidermis, tyrosine is oxidized by the copper-dependent enzyme tyrosinase to form DOPA and then dopaquinone, which polymerizes through a complex series of reactions into eumelanin (brown-black) or pheomelanin (red-yellow). When this pathway fails locally — as it does in the autoimmune disease vitiligo, where melanocytes are destroyed by the patient's own immune system — supplying additional substrate can support the survival and re-pigmentation activity of remaining melanocytes. The Cormane 1985 study and the Antoniou 1989 study reported that oral phenylalanine combined with ultraviolet A (UVA) exposure can produce repigmentation in vitiligo patients (in the Cormane study mainly in skin areas lying over subcutaneous fat). The mechanism, the evidence, and the protocols the studies used are the subject of this deep-dive.
Table of Contents
- Melanin Biology and the Tyrosinase Reaction
- Eumelanin vs Pheomelanin and the MC1R Determinant
- Melanocytes — Architecture and Function
- Vitiligo — The Autoimmune Pigment Loss
- The Cormane 1985 Trial
- The Antoniou 1989 Trial with Ultraviolet A
- Oral vs Topical Phenylalanine Protocols
- Response Patterns and Patient Selection
- Comparison to Khellin (KUVA) Therapy
- Comparison to Tacrolimus and Calcineurin Inhibitors
- Combination Protocols and Adjunct Nutrients
- PKU and the Lighter Pigmentation Connection
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Melanin Biology and the Tyrosinase Reaction
Melanin is the principal pigment of human skin, hair, and the iris of the eye. It absorbs ultraviolet radiation across a broad spectrum, dissipates the absorbed energy as heat, scavenges reactive oxygen species, and provides physical protection to the genome of underlying keratinocyte stem cells. Without adequate melanin, skin is vulnerable to ultraviolet-induced DNA damage, sunburn, accelerated photoaging, and dramatically increased risk of skin cancer including melanoma.
The biosynthesis of melanin begins with tyrosine. The first and rate-limiting step is performed by tyrosinase (EC 1.14.18.1), a copper-containing enzyme that catalyzes two sequential reactions:
- Tyrosine + O2 → L-DOPA (3,4-dihydroxyphenylalanine). The hydroxylation of tyrosine, requiring molecular oxygen and the two copper atoms at the tyrosinase active site.
- L-DOPA + O2 → dopaquinone. The further oxidation of L-DOPA to a reactive quinone.
Dopaquinone is then routed through one of two divergent pathways depending on the local cellular environment:
- In the absence of sulfur-containing cofactors (cysteine, glutathione), dopaquinone undergoes intramolecular cyclization to form dopachrome, which is further processed via DHICA and DHI intermediates and ultimately polymerized into eumelanin, the brown-black pigment
- In the presence of cysteine or glutathione, dopaquinone reacts to form cysteinyldopa, which is further processed into pheomelanin, the red-yellow pigment
The same precursor pathway that supplies dopamine and the catecholamines also supplies melanin. The branch point is tissue-specific: in catecholamine-producing neurons, the L-DOPA produced by tyrosine hydroxylase is decarboxylated to dopamine by aromatic L-amino acid decarboxylase. In melanocytes, the L-DOPA produced by tyrosinase is oxidized to dopaquinone and polymerized to melanin. The phenylalanine and tyrosine that feed both pathways are the same dietary pool.
Eumelanin vs Pheomelanin and the MC1R Determinant
Human skin and hair color is determined principally by the ratio of eumelanin to pheomelanin. Eumelanin dominates in dark skin and dark hair; pheomelanin dominates in fair skin and red hair. The mixture is determined by the activity of the melanocortin 1 receptor (MC1R) on the melanocyte surface, which is activated by alpha-melanocyte-stimulating hormone (alpha-MSH).
The relationships are:
- High MC1R activity (functional receptor + adequate alpha-MSH stimulation) — promotes eumelanin synthesis. Dark skin, dark hair, robust tanning response, low pheomelanin, low skin cancer risk per ultraviolet (UV) dose
- Low MC1R activity (loss-of-function MC1R variants common in northern European populations) — promotes pheomelanin synthesis. Fair skin, red or blond hair, poor tanning response, high pheomelanin, increased skin cancer risk per ultraviolet dose
The clinical relevance for phenylalanine supplementation: increasing substrate availability does not change the eumelanin/pheomelanin ratio. A patient with low MC1R activity who responds to phenylalanine supplementation produces more pheomelanin, not more eumelanin. The protective effect against ultraviolet damage is therefore better in patients with functional MC1R who can route the additional substrate to eumelanin. This explains some of the inter-patient variability in vitiligo treatment response — patients with darker constitutive skin tone tend to respond better to phenylalanine + ultraviolet A repigmentation protocols than patients with very fair skin and red hair phenotype.
Melanocytes — Architecture and Function
Melanocytes are the specialized dendritic cells of the basal epidermis that produce melanin. They constitute approximately 5 to 10 percent of basal epidermal cells. Each melanocyte projects long dendritic processes that contact approximately 36 surrounding keratinocytes, forming the "epidermal melanin unit." Melanin synthesized within the melanocyte's melanosome organelles is packaged and transferred to the surrounding keratinocytes through a phagocytic process, ultimately positioning the melanin granules over the nuclei of the keratinocytes to shield the keratinocyte DNA from ultraviolet damage.
Melanocytes are unusual cells in several ways relevant to vitiligo:
- They are derived from the neural crest in embryologic development, migrating to the skin during the first trimester. This shared neural-crest origin explains some of the immunologic cross-reactivity between melanocytes and other neural-crest derivatives
- They produce reactive oxygen species as a byproduct of melanin synthesis. The same pathway that produces protective pigment also generates intracellular oxidative stress, making melanocytes particularly dependent on antioxidant defense systems
- They express tyrosinase and several other proteins (tyrosinase-related protein 1 and 2, MITF, gp100) that are recognized as autoantigens in vitiligo and in melanoma immunotherapy
- They are relatively rare and have limited regenerative capacity in adult skin, which is why pigment loss is often persistent and slow to reverse
The reservoir of melanocyte precursors that can repopulate depigmented areas comes from two sources: the outer root sheath of hair follicles (the principal source for most skin) and migratory melanoblasts from immediately adjacent normally-pigmented skin. The hair follicle reservoir explains the perifollicular pattern of repigmentation that is the typical clinical sign of successful vitiligo treatment — pigment spots appear first around hair follicles and gradually coalesce.
Vitiligo — The Autoimmune Pigment Loss
Vitiligo is an acquired depigmentation disorder affecting approximately 1 percent of the global population. It is characterized by patches of complete pigment loss in previously normally-pigmented skin, typically appearing in young adulthood, often initially on sun-exposed areas (face, hands) or in areas of friction (elbows, knees, axillae) or genital regions. The course is variable: some patients have stable patches that never extend; others have steadily progressive depigmentation that can eventually involve most of the body surface.
The current consensus on pathophysiology is that vitiligo is an autoimmune disease in which CD8+ cytotoxic T cells specifically destroy melanocytes. The autoantigens include tyrosinase, TRP1, TRP2, gp100, and other melanocyte-specific proteins. The trigger for autoimmunity is multifactorial — genetic susceptibility (multiple loci including NLRP1, PTPN22, TYR), oxidative stress within melanocytes producing autoantigens through protein damage, environmental triggers (Koebner phenomenon — new patches appearing at sites of skin trauma), and possible cross-reactivity with infectious antigens.
The relevant subtypes for treatment planning are:
- Segmental vitiligo — depigmentation in a single dermatomal distribution, typically unilateral, often early-onset, frequently stable after initial spread. Tends to respond less well to medical treatment but is more amenable to surgical melanocyte transplantation
- Generalized vitiligo (non-segmental) — bilateral and symmetric patches, often progressive, associated with autoimmune comorbidities (thyroid disease, type 1 diabetes, alopecia areata, Addison disease). The principal target for medical treatment including phenylalanine protocols
- Acrofacial vitiligo — involvement of distal extremities and periorificial face. Often refractory to all treatments. Phenylalanine + ultraviolet A helps face but is less effective for hands and feet
- Universal vitiligo — near-complete depigmentation. Treatment shifts to depigmentation of the remaining pigmented areas for cosmetic uniformity
Standard medical treatments include topical corticosteroids (high-potency for non-facial, mid-potency for facial), topical calcineurin inhibitors (tacrolimus, pimecrolimus — particularly useful for facial and intertriginous areas where steroids are problematic), phototherapy (narrowband ultraviolet B (UVB) is current standard, sometimes combined with topical agents), excimer laser for localized patches, JAK inhibitors (recently approved ruxolitinib cream), and in advanced or stable disease, surgical melanocyte transplantation. Oral and topical phenylalanine combined with ultraviolet A exposure occupies a complementary niche for patients seeking nutritional adjunct therapy and for facial repigmentation maintenance.
The Cormane 1985 Trial
The classical clinical demonstration of phenylalanine for vitiligo was published by R.H. Cormane and colleagues in 1985 in Archives of Dermatological Research. Patients took oral L-phenylalanine at 50 mg/kg body weight, which raised the phenylalanine level in their blood. Because the blood level peaks between 30 and 45 minutes after the dose, the ultraviolet A exposure was given at that time.
The Cormane results, as the published summary reports them:
- After 4 months (32 treatments), reasonable repigmentation occurred, mainly in skin areas lying over subcutaneous fat (fatty tissue)
- Patients could tolerate more sun than usual, especially on the white patches, and had no sunburn from the phenylalanine + ultraviolet A treatment
- Normal skin also tanned very well
The published summary gives no patient count and describes no control group, so the natural fluctuation of vitiligo and placebo and observer biases may have contributed to the results. The mechanism proposed was that oral phenylalanine raises plasma and intra-melanocyte tyrosine, providing substrate for melanin synthesis, while the ultraviolet A exposure stimulates melanocyte proliferation and increases tyrosinase activity. The combined effect was hypothesized to overcome the substrate limitation that constrains remaining melanocytes in vitiligous skin.
The Cormane 1985 paper is significant as the first published demonstration of phenylalanine for vitiligo and remains the most-cited reference for the approach. Subsequent controlled trials have produced more modest response rates but generally confirm that the protocol produces meaningful repigmentation in a subset of patients.
The Antoniou 1989 Trial with Ultraviolet A
C. Antoniou and colleagues published a follow-up study in 1989 in the International Journal of Dermatology. Twenty-one patients with vitiligo were divided into two groups. Eleven took oral L-phenylalanine at 100 mg/kg body weight with ultraviolet A exposure. Ten took the same oral dose with ultraviolet A exposure and, in addition, applied a cream containing 10% L-phenylalanine to the white patches.
Antoniou results:
- The best results occurred in the second group, which added the phenylalanine cream to the oral dose
- No side effects were found in either group
Later studies reported results in the same direction:
- Schulpis and colleagues (1989) treated 13 children with oral L-phenylalanine followed by ultraviolet A. Three had repigmentation of all their white patches, 6 improved by 50% to 90%, and 4 did not respond. None of the children had side effects.
- Siddiqui and colleagues (1994) ran an open trial (149 patients, 18 months) and a small double-blind trial (32 patients, 6 months). They saw various grades of repigmentation, not exceeding 77% in the open trial and 60% in the blind trial. A higher phenylalanine dose raised blood phenylalanine levels but did not improve the results, and the authors concluded that the best dose appears to be lower than 50 mg/kg a day.
- Camacho and Mazuecos (1999) reported 6 years of experience with oral and topical phenylalanine.
Face and trunk are described as responding best and hands and feet least. Multiple meta-analyses of vitiligo treatments have included phenylalanine + ultraviolet A as one of the established options, generally placing it as a second-line or adjunctive treatment after topical corticosteroids, topical calcineurin inhibitors, and narrowband ultraviolet B phototherapy.
Oral vs Topical Phenylalanine Protocols
Two delivery routes have been studied:
- Oral L-phenylalanine — 50 to 100 mg/kg per day (typical adult dose 3 to 7 grams) taken 30 to 60 minutes before ultraviolet A exposure. The systemic delivery raises plasma phenylalanine, which then equilibrates with the melanocyte intracellular pool
- Topical L-phenylalanine — 10 percent cream or gel applied to depigmented areas 30 minutes before ultraviolet A exposure. Delivers substrate directly to the affected melanocytes without raising systemic phenylalanine. Useful for patients with localized vitiligo or who want to avoid systemic supplementation
The Cormane study used oral dosing; the Antoniou study gave the oral dose to both groups and added a 10% phenylalanine cream in one of them. Topical-only protocols have been studied with less rigor but have shown comparable response rates with smaller magnitude effects per treated area, presumably because topical penetration is limited. In the small Antoniou study, oral plus topical treatment gave better results than oral treatment alone.
What the published protocols used:
- Oral L-phenylalanine 50 mg/kg body weight in the Cormane study and 100 mg/kg in the Antoniou study. Siddiqui and colleagues (1994) found that a higher dose raised blood phenylalanine but did not improve results, and put the best dose below 50 mg/kg a day
- Ultraviolet A exposure timed to the peak blood level: 30 to 45 minutes after the oral dose in the Cormane study (Siddiqui measured the peak at 30 to 60 minutes)
- Practitioners describe ultraviolet A exposure starting at 3 to 5 minutes and building gradually to 15 to 30 minutes per session, twice weekly
- Courses of 4 months (Cormane, 32 treatments), 6 months (Siddiqui double-blind trial) and 18 months (Siddiqui open trial)
- A cream containing 10 percent phenylalanine on the white patches, added to the oral dose in the better-performing Antoniou group
- Practitioners describe sunscreen on normally pigmented skin, because tanning there increases the contrast with the white patches
- Some protocols add vitamin and antioxidant cofactors throughout treatment (see below)
Response Patterns and Patient Selection
The clinical pattern of vitiligo response to phenylalanine + ultraviolet A is characteristic and predictable:
- Initial signs appear at 2 to 4 months of treatment as perifollicular hyperpigmentation — small spots of pigment around hair follicles in the depigmented patch
- Coalescence proceeds over the subsequent 4 to 12 months as the perifollicular spots enlarge and merge
- Maximum response is typically reached at 12 to 18 months of consistent treatment
- Plateau or completion — further repigmentation is unlikely beyond 18 to 24 months
- Maintenance — some patients require ongoing intermittent treatment to maintain the achieved pigment; others have stable repigmentation that persists indefinitely
Patient features associated with better response:
- Face and trunk involvement (best response)
- Recent disease onset (better response than long-standing patches)
- Active disease with new patches (paradoxically responds better than stable old disease)
- Darker constitutive skin tone (more substrate routing to eumelanin)
- Pediatric onset with adult treatment (better than adult-onset)
- Generalized non-segmental vitiligo (better than segmental for medical therapy)
Patient features associated with poorer response:
- Hand and foot involvement — almost universally refractory
- Periorificial vitiligo (around mouth, eyes, nostrils, genitals) — relatively refractory
- Very fair skin and red hair phenotype with MC1R loss-of-function
- Long-standing patches greater than 5 years duration
- Segmental vitiligo (generally responds better to surgical melanocyte transplantation)
- Concurrent autoimmune comorbidities with active disease activity
How long the pigment lasts. A German follow-up study (Greiner and colleagues, 1994) looked back at 41 people treated with phenylalanine plus ultraviolet A about 5 years earlier. Twenty-five could be examined: 11 of them (44%) had lasting repigmentation, but 16 (64%) had lost pigment again during or after treatment. Signs that went with better repigmentation were vitiligo covering less than 25% of the body, onset before age 21, a generalized and symmetrical pattern, and a long course of ultraviolet therapy. None of the patients had long-term side effects, and 52% were satisfied with the treatment and would repeat it.
Comparison to Khellin (KUVA) Therapy
Khellin is a furanochromone extracted from the seeds of the Mediterranean plant Ammi visnaga (toothpick weed). It has been used in combination with ultraviolet A exposure (the KUVA protocol) as an alternative to traditional psoralen + UVA (PUVA) therapy for vitiligo. The mechanism is similar to psoralens — photo-activation produces reactive intermediates that stimulate melanocyte proliferation and tyrosinase activity — but khellin lacks the carcinogenic potential of the linear psoralens that limit long-term PUVA use.
Comparison with phenylalanine + ultraviolet A:
- Khellin + ultraviolet A — response rates of approximately 60 to 70 percent in published trials. Acts through photoactivation of khellin in the skin. Side effects include nausea and headache from oral khellin, with rare hepatotoxicity reported. Topical khellin is better tolerated
- Phenylalanine + ultraviolet A — response rates of approximately 50 to 80 percent across published trials. Acts through substrate supply. Side effects minimal, no hepatotoxicity. Slower onset of effect (6 to 18 months) compared with KUVA (3 to 12 months)
For patients seeking the most evidence-based current options, narrowband ultraviolet B phototherapy (twice weekly for 6 to 12 months) has displaced both KUVA and phenylalanine + ultraviolet A as the preferred first-line phototherapy because of comparable efficacy and superior safety. Phenylalanine + ultraviolet A retains a niche for patients who prefer a nutritional adjunct, who have limited access to narrowband ultraviolet B, or who want to combine oral phenylalanine with other phototherapy.
Comparison to Tacrolimus and Calcineurin Inhibitors
Topical tacrolimus 0.1 percent ointment (and pimecrolimus 1 percent cream) are calcineurin inhibitors originally developed for atopic dermatitis that have become first-line treatments for vitiligo, particularly facial and intertriginous involvement. The mechanism is local immunosuppression that reduces the CD8+ T-cell attack on remaining melanocytes, allowing them to survive and resume pigment production.
Comparison with phenylalanine:
- Tacrolimus — mechanism is immunosuppression. Response rates of 60 to 90 percent on face. Onset of effect at 2 to 4 months. Side effects minimal (transient burning), no skin atrophy unlike steroids. First-line for face. Limited evidence for body areas
- Phenylalanine + ultraviolet A — mechanism is substrate supply + photoactivation. Response rates of 50 to 80 percent. Onset of effect at 6 to 12 months. Side effects minimal. Useful for both face and trunk. Requires ultraviolet A exposure
The two are complementary rather than competing. Some practitioners describe a combined approach for facial vitiligo: topical tacrolimus 0.1 percent twice daily (the immunosuppressive component) with oral phenylalanine 50 mg/kg daily and twice-weekly ultraviolet A exposure (the substrate and proliferative components), with topical corticosteroids added briefly during actively spreading disease before longer-term maintenance with tacrolimus + phenylalanine.
Ruxolitinib cream, a newer option. Ruxolitinib blocks the Janus kinase 1 and 2 enzymes (a JAK inhibitor). In two phase 3 trials published in 2022 (674 patients aged 12 and over with non-segmental vitiligo covering 10% or less of the body), 1.5% ruxolitinib cream or an inactive cream was applied twice daily for 24 weeks. At least 75% improvement in the facial vitiligo score was reached by 29.8% and 30.9% of the ruxolitinib groups, versus 7.4% and 11.4% of the inactive-cream groups. The most common side effects were acne and itching where the cream was applied, and the authors noted that larger and longer trials are needed to judge its effect and safety.
For an updated comprehensive treatment review including JAK inhibitors and other recent additions, see our Vitiligo page.
Combination Protocols and Adjunct Nutrients
A comprehensive nutritional adjunct protocol alongside phenylalanine + ultraviolet A for vitiligo includes attention to several other deficiencies and antioxidant systems:
- Copper — tyrosinase requires copper at the active site. The typical Western diet provides adequate copper, so routine copper supplementation is not part of these protocols; low copper status matters mainly for people on heavy zinc supplementation (which depletes copper) or with documented low ceruloplasmin
- Vitamin B12 and folate — some evidence (Juhlin and Olsson 1997) for vitamin B12 1 mg/day + folic acid 5 mg/day plus sun exposure producing repigmentation in approximately 50 percent of patients. Particularly relevant for patients with documented B12 or folate insufficiency
- Vitamin D3 — immunomodulatory and supports keratinocyte function. Target serum 25-OH-D of 50 to 70 ng/mL. Vitamin D analog topical preparations (calcipotriol) have modest evidence in vitiligo
- Vitamin C and vitamin E — oxidative stress reduction within melanocytes. Vitamin C 500 to 1,000 mg per day, vitamin E 400 international units (IU) per day (mixed tocopherols preferred)
- Alpha-lipoic acid — antioxidant that crosses cell membranes, supports glutathione recycling, may protect remaining melanocytes from oxidative damage. 300 to 600 mg per day
- Polypodium leucotomos — fern extract, taken as an oral Polypodium leucotomos extract, with documented evidence for adjunctive use in vitiligo, particularly with narrowband ultraviolet B. 240 to 480 mg per day
- Ginkgo biloba — some evidence for halting progression of active vitiligo. 120 mg per day standardized extract
- L-tyrosine — can be added at 1 to 2 grams per day to support the same melanin pathway as phenylalanine. Particularly useful for patients with high MC1R activity (darker constitutive skin) who can route the substrate to eumelanin
The nutritional adjunct approach is unlikely to produce dramatic repigmentation by itself but appears to support response rates and reduce relapse when combined with standard phototherapy and topical treatments.
What a 2021 systematic review found. A systematic review of diet, supplement and herbal add-on treatments for vitiligo (Shakhbazova and colleagues, 2021) examined 26 studies. It named three as the most promising: oral phenylalanine added to ultraviolet A therapy, oral Ginkgo biloba on its own, and oral Polypodium leucotomos with light therapy. The reviewers called the growing evidence promising but said more studies are needed.
PKU and the Lighter Pigmentation Connection
The connection between phenylalanine metabolism and skin pigmentation is dramatically visible in untreated phenylketonuria. PKU patients lack functional phenylalanine hydroxylase and cannot efficiently convert phenylalanine to tyrosine. The downstream consequence is reduced tyrosine availability for both catecholamine and melanin synthesis. Untreated PKU patients characteristically have:
- Lighter skin than would be expected for their ethnic background
- Lighter (often blond) hair
- Blue or light eyes regardless of family ethnicity
- Reduced tanning response to sun exposure
The mechanism is straightforward: even though dietary phenylalanine intake may be adequate, the absent phenylalanine hydroxylase prevents conversion to tyrosine, and the resulting tyrosine deficit limits melanin synthesis. The simultaneous accumulation of phenylalanine itself may further inhibit melanin synthesis through direct competitive inhibition of tyrosinase, since phenylalanine and tyrosine have similar structures.
The PKU pigmentation phenotype is reversible (at least in part) by dietary tyrosine supplementation in PKU patients, which can produce darkening of hair and skin. This provides indirect confirmation that the pigmentation defect is substrate-limited rather than melanocyte-intrinsic.
Phenylalanine handling in vitiligo itself. A 1998 study (Schallreuter and colleagues) measured phenylalanine in the skin of 23 people with vitiligo and found higher levels in the white patches than in normal skin of the same person in every case. After a single oral dose of L-phenylalanine (100 mg/kg body weight) in 32 patients, all showed slower conversion of phenylalanine to tyrosine, and in 41% the conversion was significantly slower. None had raised blood phenylalanine without the test dose.
The PKU connection has two practical implications for the phenylalanine and vitiligo discussion:
- It validates the substrate hypothesis — melanin synthesis is indeed limited by phenylalanine/tyrosine availability under sufficient deficiency
- It confirms the absolute contraindication of phenylalanine supplementation in PKU. Even for vitiligo treatment, tyrosine, not phenylalanine, is the substrate that bypasses the missing enzyme in PKU
Cautions and Contraindications
- Phenylketonuria — absolute contraindication. For people with PKU and vitiligo, tyrosine supplementation bypasses the deficient phenylalanine hydroxylase, which phenylalanine cannot do
- Pregnancy and lactation. Phenylalanine + ultraviolet A protocols are not used during pregnancy, and ultraviolet A exposure in pregnancy is generally limited to narrow medical indications
- Childhood vitiligo. The high oral doses used in adult phenylalanine + ultraviolet A protocols are not established for children; the Schulpis 1989 report treated 13 children and found no side effects. Topical phenylalanine + narrowband ultraviolet B is described as a safer pediatric approach
- Photosensitizing medications. Patients on tetracyclines, fluoroquinolones, sulfonamides, or other photosensitizing drugs require caution with ultraviolet A exposure regardless of the phenylalanine component
- History of skin cancer or actinic damage. Repeated ultraviolet A exposure carries its own carcinogenic risk over decades. For people with extensive prior sun damage, melanoma history, or non-melanoma skin cancer history, the cosmetic benefit comes with that added photocarcinogenic risk
- MAO inhibitors. The L-phenylalanine component is contraindicated with monoamine oxidase inhibitors (MAOIs) because of catecholamine accumulation and hypertensive crisis risk
- Uncontrolled hypertension. Listed as a caution; blood pressure is the measure tracked during treatment
- Active autoimmune disease flare. Phenylalanine has no immunomodulatory effect, and treating active vitiligo without addressing the underlying autoimmune activity will produce poor results. Hashimoto's thyroiditis, Addison disease and other coexisting autoimmune disorders are part of that underlying activity
- Ultraviolet sensitivity disorders. Patients with porphyria, lupus erythematosus, xeroderma pigmentosum, or other photosensitive conditions cannot safely undergo ultraviolet A exposure
The phenylalanine + ultraviolet A approach to vitiligo is generally safe when used by patients without these contraindications and when the ultraviolet A exposure is controlled and progressive. Patient adherence over the required 12 to 18 month treatment course is the main practical limitation.
Key Research Papers
- Cormane RH, Siddiqui AH, Westerhof W, Schutgens RB (1985). Phenylalanine and UVA light for the treatment of vitiligo. Archives of Dermatological Research, 277(2):126-30. — PubMed PMID: 3885873
- Antoniou C et al. (1989). Vitiligo therapy with oral and topical phenylalanine with UVA exposure. International Journal of Dermatology, 28(8):545-7. — PubMed PMID: 2583897
- Schulpis CH et al. (1989). Phenylalanine plus ultraviolet light: Preliminary report of a promising treatment for childhood vitiligo. Pediatric Dermatology, 6(4):332-5. — PubMed PMID: 2616391
- Siddiqui AH et al. (1994). L-Phenylalanine and UVA irradiation in the treatment of vitiligo. Dermatology, 188(3):215-8. — PubMed PMID: 8186511
- Camacho F, Mazuecos J (1999). Treatment of vitiligo with oral and topical phenylalanine: 6 years of experience. Archives of Dermatology. — PubMed PMID: 10052421
- Greiner D, Ochsendorf FR, Milbradt R (1994). Vitiligo therapy with phenylalanine/UV A. Catamnestic studies after five years [article in German]. Hautarzt, 45(7):460-3. — PubMed PMID: 7928339
- Juhlin L, Olsson MJ (1997). Improvement of vitiligo after oral treatment with vitamin B12 and folic acid and the importance of sun exposure. Acta Dermato-Venereologica. — PubMed PMID: 9394983
- Schallreuter KU et al. (1998). In vivo evidence for compromised phenylalanine metabolism in vitiligo. Biochemical and Biophysical Research Communications, 243(2):395-9. — PubMed PMID: 9480820
- Ortonne JP, MacDonald DM, Micoud A, Thivolet J (1979). PUVA-induced repigmentation of vitiligo: a histochemical (split-DOPA) and ultrastructural study. British Journal of Dermatology, 101(1):1-12. — PubMed PMID: 113025
- Le Poole IC et al. (1993). Presence or absence of melanocytes in vitiligo lesions: An immunohistochemical investigation. Journal of Investigative Dermatology. — PubMed PMID: 7684427
- Ezzedine K et al. (2015). Vitiligo. The Lancet, 386(9988):74-84. — PubMed PMID: 25596811
- Picardo M et al. (2015). Vitiligo. Nature Reviews Disease Primers. — PubMed PMID: 27189851
- Slominski A, Tobin DJ, Shibahara S, Wortsman J (2004). Melanin pigmentation in mammalian skin and its hormonal regulation. Physiological Reviews, 84(4):1155-228. — PubMed PMID: 15383650
- Rosmarin D et al. (2022). Two Phase 3, Randomized, Controlled Trials of Ruxolitinib Cream for Vitiligo. New England Journal of Medicine, 387(16):1445-1455. — PubMed PMID: 36260792
- Shakhbazova A, Wu H, Chambers CJ, Sivamani RK (2021). A Systematic Review of Nutrition, Supplement, and Herbal-Based Adjunctive Therapies for Vitiligo. Journal of Alternative and Complementary Medicine, 27(4):294-311. — PubMed PMID: 33337930
PubMed Topic Searches
Connections
- All Amino Acids
- Phenylalanine Overview
- Phenylalanine Benefits Hub
- Phenylalanine for Mood
- Phenylalanine for Pain
- Phenylalanine for Cognition
- Vitiligo
- Tyrosine
- Copper (Tyrosinase Cofactor)
- Vitamin D3
- Vitamin B12 (Juhlin Protocol)
- Alpha-Lipoic Acid
- Vitamin C
- Vitamin E
- Aspartame (PKU Warning)
- History
- Sources