⚠ Evidence warning: Clinical trials or other evidence do not support the claims that arginine-supplemented formulas heal pressure ulcers 30-50% faster, that arginine and glutamine supplements reduce infections and deaths in burns, and that bone broth and gelatin foods do what arginine or proline supplements do for wound healing. This page keeps it as a report of what people, websites or other media say.
Proline for Wound Healing
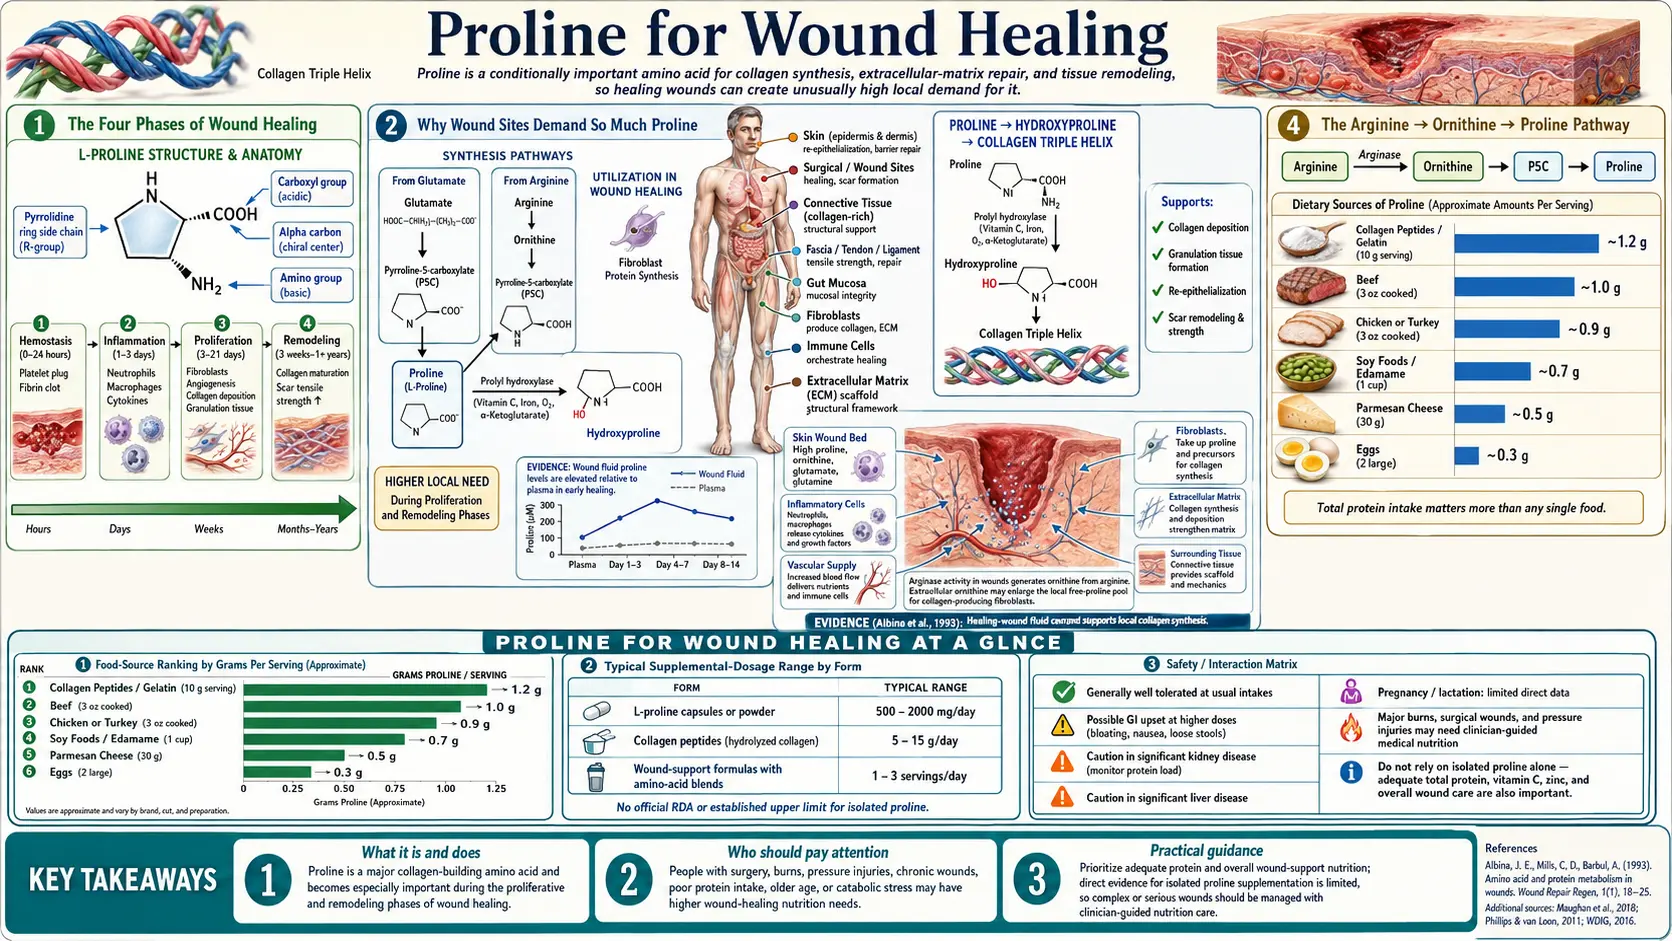
Wound healing is the closest thing the human body has to a stress test for collagen biosynthesis. When tissue is injured, the local demand for proline can rise to many times the surrounding plasma concentration. Albina's rat-wound studies of 1988 to 1993 found wound fluid rich in proline and its precursors — which this page reads as reflecting active local uptake, local synthesis from arginine, and the metabolic priority that activated fibroblasts give to depositing new collagen. The arginine → ornithine → proline pathway, mediated by macrophage arginase and ornithine aminotransferase, is the metabolic key that distinguishes regenerative wound repair (productive collagen deposition) from chronic non-healing wounds (failure of fibroblast collagen output). This deep-dive walks through the cellular mechanism, the clinical trials, and the practical implications for surgical patients, burn victims, diabetic ulcers, and pressure sores.
Table of Contents
- The Four Phases of Wound Healing
- Why Wound Sites Demand So Much Proline
- The Albina Wound Studies of 1988, 1990 and 1993
- The Arginine → Ornithine → Proline Pathway
- Macrophage Arginase and the M1/M2 Switch
- Productive Collagen Deposition vs Fibrotic Scarring
- Surgical Wound Healing Clinical Trials
- Chronic Wounds: Diabetic Ulcers and Pressure Sores
- Burn Wound Management
- Supplement Amounts Described in Wound Care
- Key Research Papers
- Connections
- Featured Videos
The Four Phases of Wound Healing
Wound healing is conventionally divided into four overlapping phases, each with distinct cellular actors and biochemical demands.
1. Hemostasis (seconds to hours). Vascular constriction and platelet aggregation form the initial clot. Fibrin scaffolding provides the temporary matrix into which inflammatory cells will migrate. Proline demand is minimal at this stage.
2. Inflammation (hours to several days). Neutrophils arrive first, debriding necrotic tissue and killing bacteria. Macrophages follow at 48-96 hours, phagocytosing debris and orchestrating the transition to repair. Activated macrophages begin to express arginase, beginning the metabolic shift that will produce proline locally.
3. Proliferation (days to weeks). Fibroblasts migrate into the wound bed and begin producing type III collagen, the initial repair collagen, followed by type I collagen as the wound matures. New blood vessels form (angiogenesis), keratinocytes migrate across the wound surface to re-epithelialize, and granulation tissue fills the wound space. Proline demand peaks during this phase — this is when active collagen deposition occurs at the highest rate.
4. Remodeling (weeks to years). The initial type-III-rich collagen scaffold is gradually replaced by type I collagen, fibrils are cross-linked by lysyl oxidase, and the scar matures and contracts. Proline demand decreases but does not fall to zero — the remodeling process continues for months to years, with ongoing collagen turnover.
The proliferation phase is the rate-limiting step in most wound-healing scenarios. The body's ability to mobilize proline (and the other amino acids, oxygen, vitamin C, iron, and zinc needed for collagen biosynthesis) to the wound site during this phase determines how quickly the wound closes and how strong the resulting scar tissue will be.
Why Wound Sites Demand So Much Proline
A typical surgical wound 5 cm long by 5 cm deep that fills in with granulation tissue might deposit several grams of new collagen during the proliferation phase. Since proline plus hydroxyproline accounts for roughly 23% of collagen mass, that means hundreds of milligrams of proline must be delivered to the wound site over the span of a week or two, in addition to the normal collagen turnover happening elsewhere in the body.
Most of this proline does not come from the systemic plasma pool. The plasma proline concentration in adults is typically 100-300 micromolar — small in absolute terms. Even maximal upregulation of intestinal proline absorption and hepatic release cannot supply the demand at an active wound site through systemic delivery alone. Instead, the wound generates much of its own proline locally, through the arginine pathway, using arginase enzyme activity supplied by activated macrophages.
The local proline concentration in wound fluid has been described as substantially higher than the simultaneous plasma concentration — the wound is concentrating proline relative to the surrounding tissue. This is not passive leakage; it reflects active local synthesis. Albina's 1993 work found that wound fibroblasts in culture turn ornithine into free proline, and a 2013 mouse study found that blocking arginase impaired healing. Local proline production is described as essential for normal healing, and disruption of the pathway (macrophage dysfunction, arginase inhibition, ornithine aminotransferase deficiency, or systemic arginine depletion) as impairing it.
The Albina Wound Studies of 1988, 1990 and 1993
The picture of arginine feeding proline in wounds comes from three rat and cell studies led by Albina, each answering a different part of the question. Their full texts were not available for checking; what follows is what their abstracts report. The wound models were Schilling chambers and polyvinyl alcohol sponges, small implants that fill with fluid and inflammatory cells, and injured skeletal muscle.
- 1988, American Journal of Physiology. All three rat wound models showed low arginine, high ornithine and high arginase activity. Macrophages contained arginase, but released it only after the cells broke open; viable macrophages released none in the lab. The authors suggest the arginase outside cells in wounds may come from dead macrophages.
- 1990, Journal of Immunology. Rat sponge fluid sampled from 6 hours to 15 days showed two periods with arginine well below plasma. In the first 3 days, the fluid held the most citrulline and nitrite, pointing to the pathway that makes reactive nitrogen compounds. After day 3, ornithine built up and arginase activity was high.
- 1993, Journal of Surgical Research. Wound fluid was “rich in proline and its metabolic precursors: ornithine, glutamate, and glutamine.” Wound fibroblasts in culture built little ornithine straight into protein as proline; instead they released ornithine-derived free proline. The authors conclude ornithine “may contribute” to protein-bound proline in wounds by raising the pool of free proline outside the cells.
Other statements long made about these measurements are not in those abstracts, and stay here as reported claims:
- Wound fluid proline concentrations were substantially elevated above plasma levels — up to 50% higher in the active proliferative phase
- The depleted arginine reflects active consumption of arginine by macrophage arginase
- The ratio of wound proline to wound arginine progressively increased over time as the wound matured, consistent with active conversion of arginine to proline via ornithine
- Pharmacological inhibition of arginase reduced wound proline accumulation. A 2013 mouse study reports that inhibiting local arginase perturbed healing and was associated with increased inflammation and defects in matrix deposition
Glutamine, the other major wound amino acid, serves as fuel for rapidly proliferating fibroblasts and inflammatory cells, and as another nitrogen source for amino acid synthesis.
These papers are the basis of a framework in which wound healing is, at the metabolic level, the conversion of arginine to proline for the purpose of synthesizing collagen at the repair site, though the 1993 and 1988 results quoted above are more cautious than that. The corollary is that any condition that depletes systemic arginine (severe sepsis, major trauma, prolonged catabolic states) or that impairs the macrophage arginine-to-proline conversion (immune dysfunction, certain medications) will impair healing through this pathway.
Subsequent work has refined the picture — later accounts describe the M1-to-M2 macrophage polarization switch as the key regulatory event, that hypoxia in the wound bed up-regulates arginase expression, and that the wound's local proline production peaks around days 5-7 post-injury during the proliferative phase. In the 2013 mouse study, however, inhibiting or depleting arginase did not change the number of alternatively activated (M2) macrophages. The basic framework drawn from Albina's papers remains in use.
The Arginine → Ornithine → Proline Pathway
The metabolic pathway from arginine to proline runs through ornithine as an intermediate, with three enzymes catalyzing the sequential conversion:
- Arginase (ARG1 or ARG2) hydrolyzes arginine to ornithine plus urea. ARG1 is the cytosolic liver isoform that is part of the urea cycle. ARG2 is the mitochondrial isoform expressed in extra-hepatic tissues including activated macrophages. Both isoforms produce ornithine from arginine. For wound healing, a 2013 mouse study titled “Local arginase 1 activity is required for cutaneous wound healing” found that deleting ARG1 in Tie2-expressing cells perturbed healing.
- Ornithine aminotransferase (OAT) transaminates ornithine, transferring the amino group to alpha-ketoglutarate (producing glutamate as a byproduct) and yielding glutamic-gamma-semialdehyde. The semialdehyde spontaneously cyclizes to pyrroline-5-carboxylate (P5C).
- Pyrroline-5-carboxylate reductase (PYCR1, PYCR2, or PYCR3) reduces P5C to proline using reduced nicotinamide adenine dinucleotide phosphate (NADPH) or reduced nicotinamide adenine dinucleotide (NADH) as the electron donor. PYCR1 and PYCR2 are mitochondrial enzymes; PYCR3 is cytosolic. All three contribute to proline synthesis depending on cell type.
The net stoichiometry is: 1 arginine + 1 alpha-ketoglutarate + 1 reduced nicotinamide adenine dinucleotide phosphate → 1 proline + 1 urea + 1 glutamate + 1 NADP+. Note that the pathway also produces glutamate as a byproduct, which can re-enter proline synthesis through the alternative P5C pathway from glutamate. The overall flux gives the cell substantial proline output from each arginine consumed.
The competing fate of arginine in macrophages is conversion to nitric oxide (NO) by inducible nitric oxide synthase (iNOS, NOS2). The arginine pool is partitioned between arginase (producing ornithine and ultimately proline, a "healing" output) and inducible nitric oxide synthase (producing NO, an "antimicrobial / pro-inflammatory" output). The balance between these two enzymes is controlled by the M1/M2 polarization of the macrophage, which is discussed in the next section.
Macrophage Arginase and the M1/M2 Switch
Macrophages are not a single cell type but a continuum of activation states. Two extreme polarizations are conventionally distinguished:
- M1 (classically activated, pro-inflammatory) — induced by interferon-gamma, lipopolysaccharide, and other T helper 1 (Th1) signals. M1 macrophages express inducible nitric oxide synthase, produce NO, and kill intracellular pathogens. They use arginine to make NO. Predominant during the inflammation phase of wound healing.
- M2 (alternatively activated, repair-promoting) — induced by interleukin-4 (IL-4), interleukin-13 (IL-13), interleukin-10 (IL-10), and other T helper 2 (Th2) signals. M2 macrophages express arginase (ARG1 and ARG2), produce ornithine and ultimately proline, and support tissue repair. They use arginine to make proline. Predominant during the proliferation phase of wound healing.
The temporal sequence of M1 to M2 polarization is critical for wound healing. M1 dominance in the early inflammatory phase is necessary to clear debris and prevent infection. The transition to M2 dominance around days 3-5 is what enables the shift to active collagen deposition. Failure to make this transition — either persistent M1 polarization (excessive inflammation) or premature M2 polarization (inadequate debridement and infection control) — produces non-healing wounds.
Diabetic foot ulcers are the prototypical example of impaired M1-to-M2 transition. The diabetic wound is stuck in a prolonged M1-dominant state, with persistent inflammation, ongoing tissue destruction by neutrophil-derived proteases, and impaired collagen deposition because the M2 arginase pathway is not adequately engaged. Therapeutic strategies that promote the M1-to-M2 switch — including some dressings, growth factors, and possibly nutritional interventions — can help shift these chronic wounds toward healing.
The implication for proline supplementation is nuanced. Simply providing more dietary proline does not necessarily help if the limitation is local M2 macrophage activity rather than systemic proline supply. However, supplemental arginine plus adequate vitamin C, iron, zinc, and protein status creates the conditions under which the arginase pathway can operate optimally if and when the wound transitions to the M2 phase.
Productive Collagen Deposition vs Fibrotic Scarring
Not all collagen deposition is good collagen deposition. There is a critical distinction between productive collagen deposition (which restores tissue function) and excessive fibrosis (which produces dysfunctional scar tissue, contractures, keloids, and pathologic fibrosis in organs like liver, lung, and kidney).
The biochemistry of both processes involves the same prolyl-hydroxylase machinery, the same procollagen processing, and the same lysyl-oxidase cross-linking. What differs is the magnitude, timing, and tissue context of the collagen deposition. Productive collagen deposition is appropriately scaled to the tissue defect, ends when the defect is filled, and is followed by remodeling that aligns collagen fibrils along functional stress lines. Fibrotic scarring is excessive (depositing more collagen than the defect requires), persistent (failing to switch off when the defect is filled), and disorganized (collagen fibrils oriented randomly rather than along stress lines).
Keloids and hypertrophic scars are the most visible examples of dysfunctional collagen deposition. Both involve excessive type III and type I collagen deposition with disorganized fibril architecture. The fibroblasts in these lesions have abnormal transforming growth factor beta (TGF-beta) signaling, prolonged growth factor receptor activation, and reduced sensitivity to the apoptotic signals that normally end the proliferation phase. Keloids in particular are more common in patients with darker skin pigmentation and tend to extend beyond the boundaries of the original wound.
Pathologic organ fibrosis — idiopathic pulmonary fibrosis, cirrhosis, chronic kidney disease, cardiac fibrosis — involves the same dysfunctional collagen deposition but distributed throughout an entire organ rather than at a single wound site. Anti-fibrotic drugs like pirfenidone and nintedanib work in part by reducing fibroblast collagen output. None of these drugs target proline directly, but the entire fibrotic phenotype depends on adequate proline supply, which is why proline metabolism is increasingly viewed as a therapeutic target in fibrosis research.
The clinical implication is that proline supplementation in a patient prone to keloid formation or active fibrosis may not be benign. For most healthy patients with normal wound healing, supplementation poses little risk. For people with a known keloid tendency or active fibrotic disease, the concern is the one above: the same collagen machinery drives the scarring. None of the studies read for this page tested proline or collagen supplements in these people, so whether supplements add to scarring is not known from them.
Surgical Wound Healing Clinical Trials
The strongest clinical evidence for amino acid supplementation in wound healing comes from surgical patient populations. Several randomized controlled trials have examined the effects of arginine, glutamine, and protein supplementation on post-surgical wound outcomes:
- Major gastrointestinal surgery — multiple randomized controlled trials (RCTs) have shown that perioperative immunonutrition formulas containing arginine, omega-3 fatty acids, and nucleotides reduce infectious complications and shorten hospital length of stay in patients undergoing major gastrointestinal (GI) or head-and-neck cancer surgery. The mechanism is thought to involve improved arginase activity for collagen deposition plus broader immune modulation. A 2026 meta-analysis of randomized trials, with data from 7,462 people with gastrointestinal cancer, found that formulas based on arginine, nucleotides and omega-3 fatty acids lowered the odds of leaks where bowel is rejoined (anastomotic leak, odds ratio 0.62), wound infections (0.67) and sepsis (0.45), and shortened hospital stay by a mean of 2.47 days, with no significant effect on overall survival. Omega-3 fatty acids alone did not lower complications.
- Pressure ulcer treatment — arginine-supplemented formulas have been reported to speed the healing of stage III and IV pressure ulcers, with effect sizes on the order of 30-50% faster healing. The studies give narrower or more mixed results. The OEST trial (Cereda 2015; 200 malnourished people with stage II-IV ulcers, an oral formula enriched with arginine, zinc and antioxidants, or a matching formula, for 8 weeks) found ulcer area fell 60.9% against 45.2% (adjusted difference 18.7%), with no difference in complete healing. A small observational study (Brewer 2010; 18 people with spinal cord injury against 17 historical controls) reported mean healing times of 10.5 against 21 weeks. A trial called HEAL has also been credited with this result; it was not found in PubMed or Europe PMC. A 2022 meta-analysis (8 studies, 196 patients) reported improvement with arginine (standardized mean difference -0.6), larger above 15 g/day (-2.8), while a 2025 systematic review (15 studies, 1,085 people) concludes that the “evidence remains inconclusive.”
- Burn patients — arginine and glutamine supplementation have been described as standard of care in major burn units, with reports of reduced infection rates and possibly a mortality benefit in severe burns (for glutamine, see the 2022 trial under Burn Wound Management below). The metabolic stress of major burn injury depletes systemic arginine, and supplementation restores wound-site availability.
- Diabetic foot ulcer trials — smaller studies of arginine, vitamin C, and protein supplementation have shown improvements in healing rates, though the heterogeneity of diabetic ulcer trials makes meta-analysis challenging.
The role of proline-specific supplementation, separate from arginine, has been less extensively studied. Most clinical trials have used arginine because the conversion to proline happens locally at the wound site through the arginase pathway, and arginine is more efficiently absorbed and transported. Free proline supplementation is not generally part of standard surgical nutrition protocols, though collagen peptide supplementation (which delivers proline, glycine, and hydroxyproline as small absorbable peptides) has gained some interest in surgical recovery research.
One small randomized trial did test a supplement containing proline directly, along with arginine, vitamins A, C and E, zinc and selenium: 30 people with hard-to-heal wounds took 200 ml twice a day for four weeks, or a control. Wound area fell significantly with the supplement (p=0.004). Proline's own share of that result cannot be separated.
The ASPEN and ESPEN clinical practice guidelines for nutrition in wound healing recommend ensuring adequate total protein intake (1.25-1.5 g/kg/day for healing wounds, up to 2.0 g/kg/day for severe burns or pressure ulcers), with arginine supplementation considered in stage III-IV pressure ulcers and major burns. Specific proline supplementation is not in the guidelines, but adequate dietary protein with collagen-containing food sources (bone broth, gelatin, organ meats) likely accomplishes similar objectives.
Chronic Wounds: Diabetic Ulcers and Pressure Sores
Chronic non-healing wounds — defined as wounds that fail to progress through normal healing within 4-6 weeks — were put at 2.21 per 1,000 people (mixed causes) and 1.51 per 1,000 (chronic leg ulcers) in a 2019 pooled analysis of general-population studies. The three major categories are diabetic foot ulcers, pressure sores, and venous leg ulcers. All three share common pathophysiologic features: persistent inflammation, impaired M1-to-M2 transition, reduced fibroblast collagen output, and matrix degradation that exceeds matrix deposition.
Diabetic foot ulcers are the leading cause of lower extremity amputation in the United States. The pathophysiology involves: (1) peripheral neuropathy that allows continued mechanical injury without pain feedback; (2) peripheral arterial disease that limits oxygen and nutrient delivery; (3) hyperglycemia-driven dysfunction of neutrophil, macrophage, and fibroblast activity; (4) advanced glycation end-product (AGE) accumulation in tissue collagen that increases stiffness and impairs cell migration; and (5) chronic infection that perpetuates inflammation. Nutritional support that addresses the collagen-deposition limitations — adequate protein, arginine, vitamin C, zinc, and possibly collagen peptides — is one component of a multimodal treatment approach that also includes offloading, glycemic control, debridement, and infection management.
Pressure ulcers (decubitus ulcers) develop in immobilized patients (nursing home residents, intensive care unit (ICU) patients, spinal cord injury patients) when sustained pressure on a body prominence (sacrum, heels, ischial tuberosities, hips) exceeds capillary perfusion pressure for prolonged periods. Tissue ischemia leads to necrosis, ulcer formation, and chronic wound. Many pressure ulcer patients are simultaneously protein-undernourished, with serum albumin below 3.5 g/dL. Aggressive nutritional repletion — oral supplements, enteral feeding if needed, with adequate protein, arginine, vitamin C, and zinc — is one of the most evidence-supported components of pressure ulcer management.
A 2024 Cochrane review (33 trials, 7,920 people) calls the benefits of nutrition for pressure ulcers “uncertain.” Energy, protein and micronutrient supplements may slightly raise the number of healed ulcers (366 against 253 per 1,000; low-certainty evidence). Arginine with micronutrients may not raise the number healed, though ulcer area was 15.8% lower. Collagen supplements probably shrink ulcers (1.81 cm² smaller; one trial, 74 people, moderate-certainty evidence).
Venous leg ulcers develop in the setting of chronic venous insufficiency, with elevated venous pressures damaging cutaneous tissue around the medial malleolus. Compression therapy is the primary treatment. Nutritional support has a smaller role in venous ulcers than in diabetic or pressure ulcers because most venous ulcer patients are not severely undernourished, but adequate protein and micronutrient status is still described as part of care.
Burn Wound Management
Severe burns produce the most extreme catabolic state in clinical medicine, with resting energy expenditure increased by 100-200% over baseline, daily nitrogen losses of 20-30 grams, and dramatic depletion of systemic amino acid pools including arginine, glutamine, and proline. Major burns simultaneously impose massive wound healing demand — thousands of square centimeters of full-thickness burn require collagen deposition during repair — on a system that is metabolically compromised.
Modern burn nutrition protocols address this through:
- Aggressive caloric provision (1.5-2.0 times basal metabolic rate)
- High protein intake (2.0-2.5 g/kg/day in some protocols, sometimes higher in very severe burns; the 2013 ESPEN-endorsed recommendations give 1.5-2 g/kg in adults and 3 g/kg in children)
- Arginine supplementation (12-15 g/day in some protocols)
- Glutamine supplementation (0.3-0.5 g/kg/day)
- Vitamin C supplementation (often gram-level doses)
- Zinc, selenium, copper supplementation
- Adequate vitamin A and D
- Early enteral feeding (within 24-48 hours)
The role of arginine in burn care has been somewhat controversial because of concerns about arginine-derived nitric oxide contributing to vasodilation and inflammation in critically ill patients. However, in burn patients specifically, the evidence supports benefit from arginine supplementation for wound healing and infection prevention, and arginine has been described as part of burn nutrition protocols in guidelines (ASPEN, ESPEN, European Burn Association). The abstract of the 2013 ESPEN-endorsed burn recommendations, which lists eight main recommendations, does not name arginine; the full guideline texts were not read for this page.
Glutamine now has a large trial behind it. RE-ENERGIZE (2022) randomized people with severe burns (1,200 analysed; mean burn 33% of the body) to 0.5 g/kg/day of enteral glutamine or placebo. Median time to discharge alive was 40 days against 38 (P=0.17), and deaths at 6 months were 17.2% against 16.2%. The authors conclude that supplemental glutamine “did not reduce the time to discharge alive from the hospital.”
From a proline-specific perspective, the massive arginase activity at burn wound sites consumes large amounts of arginine to produce ornithine and ultimately proline locally. Adequate systemic arginine availability is therefore the rate-limiting input. Direct proline supplementation has not been established as separately beneficial beyond what dietary protein and arginine supplementation provide, though collagen peptides could plausibly contribute to the local proline pool through absorbed Pro-Hyp dipeptides.
Supplement Amounts Described in Wound Care
For significant wound healing demands — major surgery, burns, chronic ulcers — wound-care nutrition writing describes these amounts:
- Adequate total protein — 1.25-2.0 g/kg/day depending on wound severity. This is the foundation; everything else is built on top of adequate protein status.
- Arginine — 4-15 g/day in divided doses for major wounds. Often delivered as part of immunonutrition formulas. The cleanest evidence is in pressure ulcers, gastrointestinal surgery, and burns.
- Glutamine — 10-30 g/day for major wounds and burns. Supports enterocyte and immune cell metabolism; also a nitrogen source for amino acid synthesis. The 2022 burn trial above found no shorter time to discharge at 0.5 g/kg/day.
- Collagen peptides (hydrolyzed collagen) — 10-15 g/day delivers a proline-, glycine-, and hydroxyproline-rich amino acid mix in the exact ratios needed for collagen synthesis. The Pro-Hyp dipeptide is absorbed intact and reaches measurable plasma concentrations.
- Bone broth — 1-2 cups daily as a traditional food source of collagen amino acids. Less standardized than collagen peptides but provides additional minerals and may be more palatable for some patients.
- Vitamin C — 500-2,000 mg/day. Essential for prolyl hydroxylase function. Higher doses in severe burns and major surgery.
- Zinc — 15-40 mg/day. Required for over 300 enzymes including those involved in collagen and DNA synthesis. Higher doses (40 mg/day) are described for active wound healing. Long-term high-dose zinc is linked to copper deficiency; the same writing describes a limit of 6-8 weeks without copper monitoring.
- Vitamin A — 5,000-10,000 international units (IU)/day supports epithelialization and reverses corticosteroid-induced impaired wound healing. The research raises a concern about higher doses in pregnancy.
- Iron — status is measured by serum ferritin and transferrin saturation, and iron is replaced when deficient. Iron is required for prolyl hydroxylase activity. Routine iron supplementation is described only for people who are deficient.
The timing of supplementation matters. Pre-operative immunonutrition for 5-7 days before major elective surgery has the strongest evidence base. For unplanned wounds (trauma, burns, sudden non-healing ulcers), the same writing describes starting as soon as possible after the injury or diagnosis. Continuation for at least 2-3 weeks post-injury covers the proliferative phase of healing.
Key Research Papers
- Albina JE, Abate JA, Mastrofrancesco B (1993). Role of ornithine as a proline precursor in healing wounds. Journal of Surgical Research. — PubMed PMID: 8105150
- Albina JE, Mills CD, Barbul A, Thirkill CE, Henry WL, Mastrofrancesco B, Caldwell MD (1988). Arginine metabolism in wounds. American Journal of Physiology. — PubMed PMID: 3354662
- Albina JE, Mills CD, Henry WL, Caldwell MD (1990). Temporal expression of different pathways of L-arginine metabolism in healing wounds. Journal of Immunology. — PubMed PMID: 2332635
- Witte MB, Barbul A (2003). Arginine physiology and its implication for wound healing. Wound Repair and Regeneration. — PubMed PMID: 14617280
- Stechmiller JK et al. (2005). Arginine supplementation and wound healing. Nutrition in Clinical Practice. — PubMed PMID: 16207646
- Brewer S et al. (2010). Effect of an arginine-containing nutritional supplement on pressure ulcer healing in community spinal patients. Journal of Wound Care. — PubMed PMID: 20616774
- Cereda E, Klersy C, Serioli M, Crespi A, D'Andrea F; OligoElement Sore Trial Study Group (2015). A nutritional formula enriched with arginine, zinc, and antioxidants for the healing of pressure ulcers: a randomized trial. Annals of Internal Medicine. — PubMed PMID: 25643304
- Barbul A et al. (1990). Arginine enhances wound healing and lymphocyte immune responses in humans. Surgery. — PubMed PMID: 2382229
- Curran JN, Winter DC, Bouchier-Hayes D (2006). Biological fate and clinical implications of arginine metabolism in tissue healing. Wound Repair and Regeneration. — PubMed PMID: 16939563
- Mills CD (2012). M1 and M2 macrophages: oracles of health and disease. Critical Reviews in Immunology. — PubMed PMID: 23428224
- Phang JM, Liu W (2012). Proline metabolism and cancer. Frontiers in Bioscience. — PubMed PMID: 22201839
- ESPEN guidelines on enteral nutrition in surgery and the surgical patient — PubMed
- Posthauer ME, Banks M, Dorner B, Schols JM (2015). The role of nutrition for pressure ulcer management: national pressure ulcer advisory panel, European pressure ulcer advisory panel, and pan pacific pressure injury alliance white paper. Advances in Skin and Wound Care. — PubMed PMID: 25775201
- Munoz N, Posthauer ME, Cereda E, Schols JMGA, Haesler E (2020). The Role of Nutrition for Pressure Injury Prevention and Healing: The 2019 International Clinical Practice Guideline Recommendations. Advances in Skin and Wound Care. — PubMed PMID: 32058438
- Campbell L, Saville CR, Murray PJ, Cruickshank SM, Hardman MJ (2013). Local arginase 1 activity is required for cutaneous wound healing. Journal of Investigative Dermatology. — PubMed PMID: 23552798
- Meeks KR, Tanner JJ (2023). Expression and kinetic characterization of PYCR3. Archives of Biochemistry and Biophysics. — PubMed PMID: 36414121
- Budai BC, Panait R, Laczkó B, et al. (2026). Immunonutrition Decreases Postoperative Complications in Gastrointestinal Cancer-A Systematic Review and Meta-analysis of Randomized Controlled Trials. Advances in Nutrition. — PubMed PMID: 42331289
- Cheshmeh S, Hojati N, Mohammadi A, Rahmani N, Moradi S, Pasdar Y, Elahi N (2022). The use of oral and enteral tube-fed arginine supplementation in pressure injury care: A systematic review and meta-analysis. Nursing Open. — PubMed PMID: 34170617
- Torsy T, Tency I, Beeckman D, Isoherranen K, Litchford M, De Vylder F (2025). The Role of Glutamine and Arginine in Wound Healing of Pressure Ulcers: A Systematic Review. Wound Repair and Regeneration. — PubMed PMID: 40748005
- Mehl AA, Damião AO, Viana SD, Andretta CP (2021). Hard-to-heal wounds: a randomised trial of an oral proline-containing supplement to aid repair. Journal of Wound Care. — PubMed PMID: 33439085
- Langer G, Wan CS, Fink A, Schwingshackl L, Schoberer D (2024). Nutritional interventions for preventing and treating pressure ulcers. Cochrane Database of Systematic Reviews. — PubMed PMID: 38345088
- Heyland DK, Wibbenmeyer L, Pollack J, et al.; RE-ENERGIZE Trial Team (2022). A Randomized Trial of Enteral Glutamine for Treatment of Burn Injuries. New England Journal of Medicine. — PubMed PMID: 36082909
- Rousseau AF, Losser MR, Ichai C, Berger MM (2013). ESPEN endorsed recommendations: nutritional therapy in major burns. Clinical Nutrition. — PubMed PMID: 23582468
- Martinengo L, Olsson M, Bajpai R, Soljak M, Upton Z, Schmidtchen A, Car J, Järbrink K (2019). Prevalence of chronic wounds in the general population: systematic review and meta-analysis of observational studies. Annals of Epidemiology. — PubMed PMID: 30497932
PubMed Topic Searches
Connections
- All Amino Acids
- Proline Overview
- Proline Benefits Hub
- Proline for Collagen Synthesis
- Proline for Cardiovascular Health
- Proline for Skin Health
- Arginine (Proline Precursor)
- Glutamine (Wound Fuel)
- Glycine (Collagen Glycine Residue)
- Lysine (Collagen Cross-Link)
- Vitamin C (Prolyl Hydroxylase)
- Vitamin A (Epithelialization)
- Zinc (Wound Healing Mineral)
- Iron (Prolyl Hydroxylase Cofactor)
- Bone Broth (Dietary Collagen)
- Collagen Peptides
- Type 2 Diabetes (Diabetic Ulcers)
- Ornithine — the arginase product sitting between arginine and proline in the wound-healing pathway.
- History
- Sources