High-Dose Biotin in Progressive Multiple Sclerosis — The Rise and Fall of MD1003
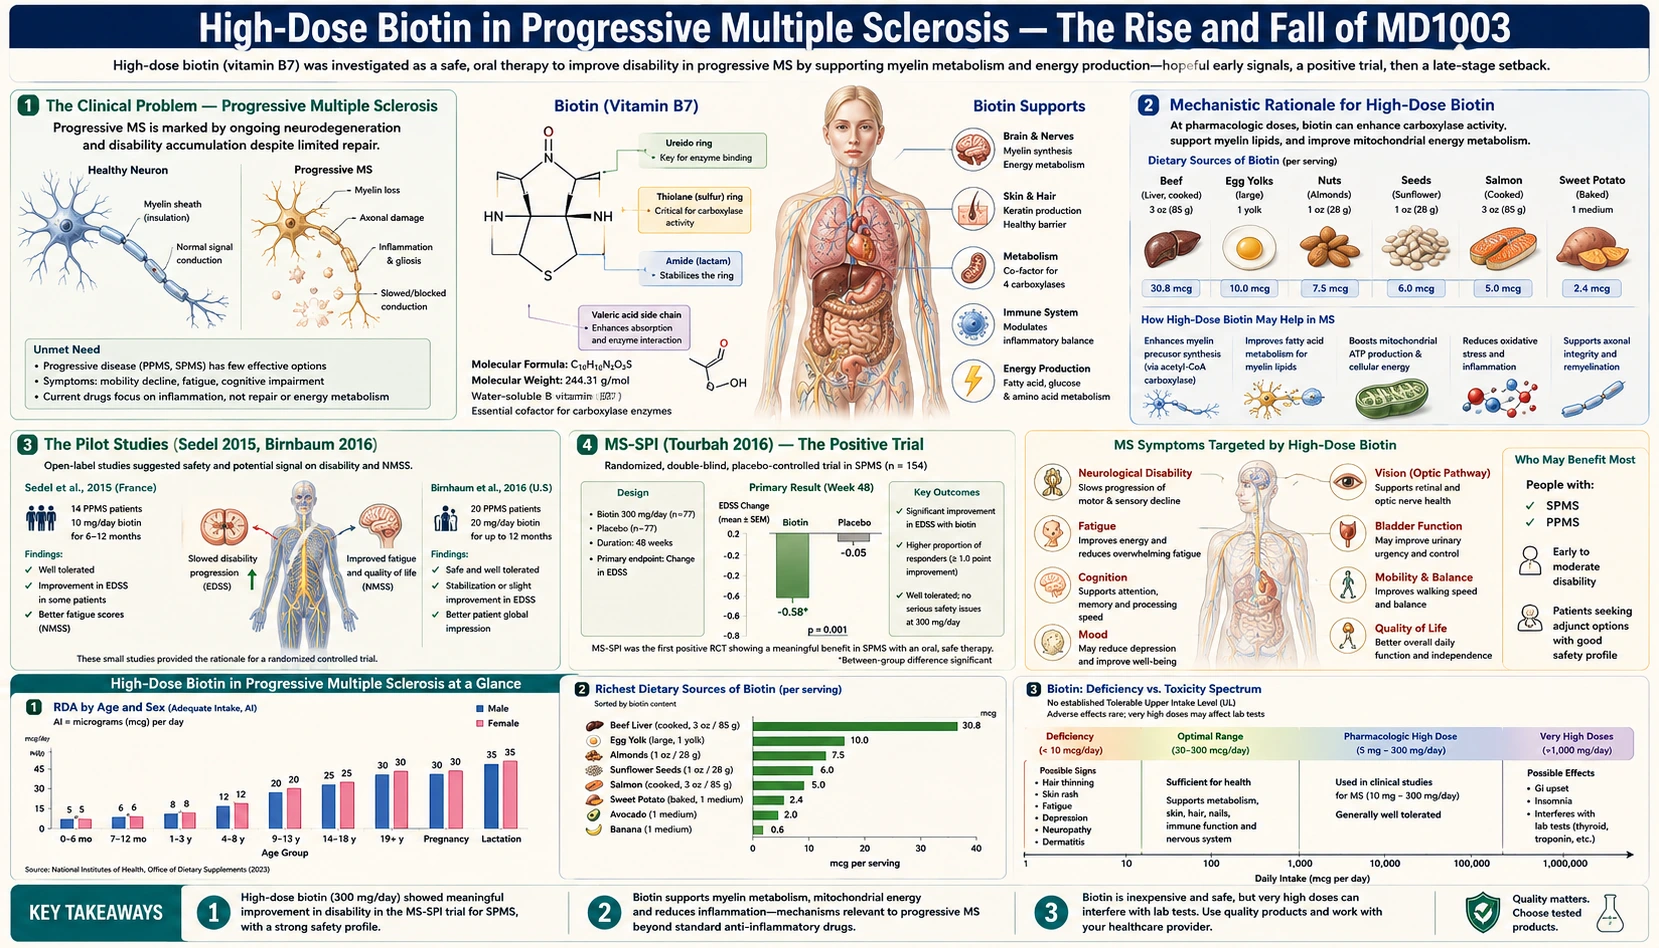
Between 2015 and 2020, the multiple sclerosis community lived through one of the most instructive cycles in modern clinical trials. A mechanistically credible hypothesis — that very high-dose biotin (300 mg per day, 10,000 times the adult Adequate Intake) could promote remyelination by boosting fatty acid synthesis and oligodendrocyte energy metabolism — was tested in MS-SPI (Tourbah 2016) and produced a striking positive signal: 12.6% of treated progressive multiple sclerosis (MS) patients achieved sustained disability improvement vs 0% on placebo. The result energized a generation of patients and a Phase 3 confirmatory program. Five years later, MS-SPI2 — a larger, longer, more rigorous trial — was firmly NEGATIVE. The disconnect produced one of the cleaner examples in modern neurology of why mechanistic plausibility and an initial positive signal do not equal clinical efficacy. This page walks through both trials, the mechanistic rationale, the lab-test interference problem the protocol introduced, and where the field stands today.
Table of Contents
- The Clinical Problem — Progressive Multiple Sclerosis
- Mechanistic Rationale for High-Dose Biotin
- The Pilot Studies (Sedel 2015, Birnbaum 2017)
- MS-SPI (Tourbah 2016) — The Positive Trial
- After MS-SPI — Off-Label Uptake and Compassionate Use
- MS-SPI2 (Cree 2020) — The Negative Confirmatory Trial
- Explaining the Disconnect
- The Thyroid-Stimulating Hormone Lab-Interference Problem the Trials Created
- Where the Field Stands Now
- Lessons for Clinical Research
- Patient FAQ
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Clinical Problem — Progressive Multiple Sclerosis
Multiple sclerosis has two clinical phenotypes that drive disability accumulation. Relapsing-remitting MS (RRMS) — the more common form, affecting ~85% of patients at diagnosis — is characterized by discrete inflammatory attacks separated by periods of stability or partial recovery. The treatment revolution in RRMS has been enormous: high-efficacy disease-modifying therapies (natalizumab, ocrelizumab, ofatumumab, alemtuzumab, cladribine, the S1P modulators) can suppress relapses by >80% and dramatically slow disability accumulation in most patients.
The other phenotype is progressive multiple sclerosis — either primary progressive (10-15% of patients from onset) or secondary progressive (the evolution of RRMS over years to decades into a progressive phase). Progressive multiple sclerosis is dominated not by acute inflammation but by chronic neurodegeneration: progressive axonal loss, demyelination without effective remyelination, and brain volume loss. Disability accumulates steadily without relapses.
The treatment landscape for progressive multiple sclerosis is sparse. Ocrelizumab modestly slows progression in primary progressive multiple sclerosis (PPMS). Siponimod modestly slows progression in secondary progressive multiple sclerosis (SPMS) with active relapses. Cladribine and rituximab have some effect. But these interventions slow the rate of decline without halting or reversing it. There is no approved therapy that genuinely improves disability in established progressive multiple sclerosis.
This unmet need is the reason any credible candidate for progressive multiple sclerosis receives enormous attention from patients and clinicians. Biotin's emergence as a candidate — combined with its safety, low cost, and oral administration — produced an unusually intense clinical-trial cycle.
Mechanistic Rationale for High-Dose Biotin
Frederic Sedel and colleagues at the Pitie-Salpetriere in Paris articulated the mechanistic hypothesis that motivated the multiple sclerosis trials. Two complementary pathways:
1. Promoting myelin synthesis
Myelin is composed of approximately 70% lipids by dry weight — a higher proportion than essentially any other tissue. The lipid composition is dominated by cholesterol, galactocerebrosides, sphingomyelin, and phosphatidylethanolamine. The synthesis of these lipids requires a steady supply of fatty acids, which in turn requires acetyl-CoA carboxylase (ACC) — one of the biotin-dependent carboxylase enzymes.
The hypothesis: in oligodendrocytes attempting to remyelinate damaged axons, ACC activity becomes a potential rate-limiting step for lipid biosynthesis. Saturating these cells with super-physiological biotin (10,000× the Adequate Intake, AI) might activate ACC to a greater extent than normal physiology allows, accelerating fatty-acid synthesis and supporting remyelination.
2. Boosting energy metabolism in stressed neurons
Neurons in chronically demyelinated white matter face a substantial energy deficit. Without the saltatory conduction that myelin enables, action-potential propagation costs much more adenosine triphosphate (ATP) per unit length of axon. Mitochondrial dysfunction further compromises adenosine triphosphate supply. The result is chronic energy failure that eventually drives axonal degeneration.
Biotin activates pyruvate carboxylase (PC) — the enzyme that replenishes the citric acid cycle and supports glucose oxidation. The hypothesis: high-dose biotin boosts mitochondrial energy production in stressed neurons, improving their resilience to the energy deficit of chronic demyelination.
Why "high dose"
Normal physiologic biotin doses (30 mcg/day Adequate Intake — biotin has no Recommended Dietary Allowance — even 1 mg/day supplementation) are essentially saturating for the body's normal metabolic needs. The mechanistic hypothesis required supra-physiologic concentrations capable of forcing additional flux through ACC and PC beyond their normal regulated rates. The 300 mg/day dose was chosen empirically as the highest tolerable dose with reasonable pharmacokinetics — 10,000 times the Adequate Intake, divided as 100 mg three times daily.
The mechanism was speculative — there was no direct demonstration that ACC or PC was actually rate-limiting in oligodendrocytes or axons, nor evidence that 300 mg/day produced concentrations capable of increasing flux. The rationale was plausible but unproven. The clinical trials would test whether the speculation translated into clinical benefit.
The Pilot Studies (Sedel 2015, Birnbaum 2017)
Sedel et al. published an open-label pilot in 23 patients with progressive multiple sclerosis in 2015. Patients received 100-300 mg/day biotin for 2 to 36 months (mean 9.2 months). The reported outcomes:
- In four patients with prominent visual impairment related to optic nerve injury, visual acuity improved significantly; visual evoked potentials in two patients showed progressive reappearance of P100 waves
- Sixteen of 18 patients (89%) with prominent spinal cord involvement were considered improved, confirmed by blinded review of videotaped clinical examination in 9 cases
- In all cases, improvement was delayed from 2 to 8 months after the start of treatment
The pilot was uncontrolled and open-label, with all the limitations that implies: regression to the mean, attention effects, observer bias, selection of patients likely to respond. But the consistency of the findings and the magnitude in some patients was enough to justify a controlled trial.
Birnbaum and Stulc (2017) published US clinical experience with off-label high-dose biotin in a similar uncontrolled context, and their findings were negative: of 43 patients with progressive multiple sclerosis given 300 mg/day pharmaceutical-grade biotin in a specialty clinic, “None of the patients' EDSS scores improved,” one-third (38-43%) worsened, and several worsened patients improved after stopping biotin. The authors concluded that high-dose biotin was safe and well tolerated “but of no demonstrable long-term benefit.” By 2014-2015, a meaningful number of multiple sclerosis specialists were already prescribing high-dose biotin off-label based on the pilot data, awaiting Phase 3 confirmation.
The pilot's main visual claim was later tested directly. In the MS-ON trial, 93 people with chronic visual loss from multiple sclerosis were randomised 2:1 to 300 mg/day high-dose pharmaceutical biotin (65 patients) or placebo (28 patients) for 6 months. The study “did not meet its primary endpoint” (visual acuity change, p = 0.66); in the subgroup with slowly progressive optic neuropathy there was a non-significant trend favouring biotin (p = 0.45), and no benefit over placebo in patients with acute optic neuritis.
MS-SPI (Tourbah 2016) — The Positive Trial
MS-SPI was the first randomized, placebo-controlled trial of high-dose pharmaceutical biotin in progressive multiple sclerosis. The trial was published in Multiple Sclerosis Journal in 2016. Key parameters:
- Population: 154 patients with progressive multiple sclerosis (primary progressive or secondary progressive), Expanded Disability Status Scale (EDSS) 4.5-7.0, with evidence of disease worsening within the previous two years
- Intervention: Biotin 300 mg/day (100 mg three times daily) vs placebo, 2:1 randomization, for 12 months, followed by 12-month open-label extension
- Primary outcome: Proportion of patients with confirmed disability reversal — defined as improvement in EDSS or timed 25-foot walk that was seen at month 9 and confirmed at month 12
- Secondary outcomes: EDSS change, timed 25-foot walk (T25FW) time, mean change in Multiple Sclerosis Functional Composite (MSFC), proportion with disability progression
Headline result
- 13 (12.6%) of the biotin-treated patients achieved the primary outcome of confirmed disability reversal (month 9, confirmed at month 12)
- 0% of placebo patients achieved the primary outcome
- p = 0.005
The contrast was striking. The trial also showed signals on T25FW improvement and reduced odds of progression. Treatment was well-tolerated; the main adverse event was lab-test interference (specifically suppressed thyroid-stimulating hormone, TSH).
The multiple sclerosis community took notice. A treatment that improved disability — not just slowed progression — in 12.6% of an otherwise-untreatable population was potentially transformative. Off-label biotin uptake accelerated. Expanded access programs opened. France granted a temporary authorisation for use (ATU) for high-dose pharmaceutical biotin. A marketing application for biotin in progressive multiple sclerosis was submitted to the European Medicines Agency.
After MS-SPI — Off-Label Uptake and Compassionate Use
In the 2016-2019 window between the MS-SPI publication and the larger confirmatory trial, high-dose biotin became widely used in progressive multiple sclerosis:
- Many multiple sclerosis specialists prescribed 300 mg/day biotin off-label, either by writing for compounded preparations or instructing patients to assemble the dose from over-the-counter biotin tablets (often 30-60 tablets of 5 mg or 10 mg per day)
- The temporary-authorisation (ATU) program in France enrolled thousands of patients
- The expanded experience — published as observational cohorts by Couloume, Birnbaum, and others — produced mixed signals. Some cohorts showed modest benefit; some showed no benefit; some raised concerns about increased relapses or accelerated disability in subsets
- The lab-test interference problem became apparent at scale: thyroid-stimulating hormone and free T4 panels in biotin-treated multiple sclerosis patients required either washout (impractical for those on continuous high-dose therapy) or interpretation accounting for the artifact
The largest routine-care cohort was a prospective study of 178 patients who started high-dose biotin at Nantes or Rennes hospitals in France. At 12 months, only 3.8% had an improved EDSS score; of the 74 patients (41.6%) who had an MRI scan, 20 (27.0%) had new T2 lesions. The authors concluded that high-dose biotin “did not seem to be associated with a clear improvement in disability.”
The mixed observational data prompted more cautious interpretation among some experts, but a formal Phase 3 confirmatory trial was needed to know whether MS-SPI's headline finding would replicate in a larger, more rigorous study.
MS-SPI2 (Cree 2020) — The Negative Confirmatory Trial
MS-SPI2 (named SPI2 in the paper; published by Cree et al. in The Lancet Neurology in 2020) was designed to be the definitive Phase 3 confirmatory trial. Key parameters — deliberately larger and longer than MS-SPI:
- Population: 642 patients with progressive MS (PPMS or non-active SPMS), EDSS 3.5-6.5, with documented progression. Importantly, the inclusion criteria were broader than MS-SPI to better reflect the real-world target population.
- Intervention: high-dose pharmaceutical biotin (oral biotin 100 mg three times daily) vs placebo, 1:1 randomization; the mean time in the placebo-controlled phase was 20.1 months (range 15-27), compared to 12 months in MS-SPI. Concomitant disease-modifying therapies were allowed.
- Primary outcome: proportion with confirmed improvement in EDSS or timed 25-foot walk at month 12, confirmed at month 15, versus baseline (MS-SPI measured month 9, confirmed at month 12)
- Secondary outcomes: Multiple disability and patient-reported outcome measures
Headline result
- 39 (12%) of 326 biotin-treated patients achieved confirmed improvement
- 29 (9%) of 316 placebo patients achieved confirmed improvement
- Odds ratio 1.35 (95% CI 0.81-2.26) — NOT statistically significant
The difference between the active and placebo arms was clinically and statistically meaningless. Secondary outcomes showed no signal favoring biotin. Most strikingly, the placebo response rate in MS-SPI2 (9%) was much higher than in MS-SPI (0%), and the active arm response rate was nearly identical (12% vs 12.6%). The MS-SPI2 findings were unambiguous: high-dose biotin does not produce clinically meaningful improvement in progressive multiple sclerosis beyond placebo.
The Phase 3 program of high-dose pharmaceutical biotin for multiple sclerosis ended. The marketing application in Europe had already been withdrawn on 13 November 2017, before SPI2 reported; at the time of the withdrawal, the European Medicines Agency's Committee for Medicinal Products for Human Use (CHMP) was of the opinion that the benefits did not outweigh the risks. The compassionate-use programs wound down. The SPI2 investigators concluded that high-dose biotin did not significantly improve disability or walking speed and, with “the potential … for deleterious health consequences from interference of laboratory tests,” it “cannot be recommended for treatment of progressive multiple sclerosis.”
A 2021 systematic review and meta-analysis pooled the three randomised trials (889 people, 830 of them with progressive multiple sclerosis); all three used high-dose biotin as an add-on treatment. At 12 to 15 months there was “insufficient evidence” that the biotin and placebo groups differed in composite improvement of disability (relative risk 2.87; 95% CI 0.29-28.40; low certainty). Pooled improvement in 25-foot walk time favoured biotin (relative risk 2.06; 95% CI 1.04-4.09; moderate certainty). Of 662 pooled patients on high-dose biotin, 31 (4.7%) had laboratory test interference, compared with none in the placebo groups.
Explaining the Disconnect
Why did MS-SPI show a robust positive signal that disappeared on replication? Multiple hypotheses, none fully resolved:
- Differences in the placebo arm. The 0% placebo response in MS-SPI was strikingly low — it is unusual for any chronic disease trial of disability improvement to have literally zero placebo responders over 12 months. The 9% placebo response in MS-SPI2 is more typical. Some have suggested the MS-SPI placebo arm was unusually stable (perhaps reflecting a more selected population, more aggressive natural history, or chance). The MS-SPI2 placebo arm reflects the more realistic spontaneous-improvement rate in this population.
- Differences in the population. MS-SPI required documented progression over 2 years; MS-SPI2 was somewhat broader. The MS-SPI population may have been more enriched for patients destined to plateau or stabilize, producing a higher apparent treatment effect.
- Regression to the mean. Both trials enrolled patients with recent documented progression, but in MS-SPI the requirement was tighter. Patients with recent rapid progression have a higher than baseline probability of spontaneous stabilization (regression to the mean), and this effect is amplified by selection.
- Statistical artifact. A modestly sized Phase 2 trial (154 patients) is more susceptible to false-positive findings than a larger Phase 3 trial (642 patients). The MS-SPI result may have been a chance excursion that did not reflect the true population effect.
- Differences in MS-SPI vs MS-SPI2 outcome adjudication. Some commentators noted subtle differences in how disability reversal was confirmed across the two trials. The differences likely do not explain the magnitude of the disconnect.
- Pharmaceutical biotin formulation differences. Both trials used the same pharmaceutical biotin product; this hypothesis has limited support.
- True clinical heterogeneity. Perhaps biotin works in a minority of progressive multiple sclerosis patients with a specific underlying pathophysiology that is enriched in some populations and not others. This is not testable from the available data and remains speculative.
The most parsimonious interpretation: the MS-SPI signal was a combination of an unusually low placebo response, a modestly enriched treatment-responsive population, and statistical variation that was not reproducible in the larger, longer confirmatory study. The mechanistic rationale, while plausible, did not translate into reliable clinical benefit.
The Thyroid-Stimulating Hormone Lab-Interference Problem the Trials Created
One of the unintended consequences of the MS-SPI trials was the creation of a population of patients on 300 mg/day biotin — a dose 10,000× the Adequate Intake and ~30× the typical hair-and-nails supplement dose. This population brought the streptavidin-biotin immunoassay interference problem to clinical attention at unprecedented scale.
Specific problems:
- Thyroid-stimulating hormone suppression mimicking Graves'. On affected tests, a patient on high-dose biotin can show a suppressed thyroid-stimulating hormone and elevated free T4 reading. The pattern is biochemically identical to true hyperthyroidism. A 2021 meta-analysis of the three randomised trials found laboratory test interference in 31 of 662 pooled patients (4.7%) on high-dose biotin, compared with none on placebo. The interference depends on the assay: one laboratory report found that biotin interfered with free thyroid hormone and thyroglobulin measurements but not with thyroid-stimulating hormone on the immunoassay system it tested. Some patients received inappropriate antithyroid drugs before the cause was recognized.
- The death linked to falsely low troponin. Before its 2017 safety communication, the U.S. Food and Drug Administration (FDA) had received a report that one patient taking high levels of biotin died following low troponin test results when a troponin test subject to biotin interference was used. The FDA's updated safety communication of November 5, 2019 repeated this, noted that physicians may recommend up to 300 mg per day of biotin for conditions such as multiple sclerosis, and said the agency remained concerned about laboratory tests that had not addressed the risk of biotin interference.
- Routine laboratory monitoring during the trial. Trial-specific protocols had to either (a) hold biotin for 72+ hours before lab draws (challenging logistically and a possible confound for the trial), (b) use biotin-free assay platforms (not universally available), or (c) interpret results with the known interference accounting. None of these was ideal.
The MS-SPI experience accelerated the clinical-chemistry field's investment in biotin-resistant assay platforms (described on the Lab-Test Interference page). In that sense, the trial had a positive downstream impact even though the primary efficacy question came back negative.
Where the Field Stands Now
Following MS-SPI2's negative result:
- The major multiple sclerosis clinical guidelines (American Academy of Neurology, AAN; European Committee for Treatment and Research in Multiple Sclerosis, ECTRIMS) do not recommend high-dose biotin for progressive multiple sclerosis, and the SPI2 investigators concluded that it “cannot be recommended for treatment of progressive multiple sclerosis”
- Development of high-dose pharmaceutical biotin for multiple sclerosis has been discontinued
- The marketing application in Europe was withdrawn on 13 November 2017; it was never approved
- Off-label use has substantially decreased but some patients continue, often based on subjective benefit perception or the original positive Phase 2 data
- Most multiple sclerosis specialists who continue to prescribe high-dose biotin do so as a small number of selected patient cases, typically with explicit informed discussion of MS-SPI2's negative result, and with attention to lab-test interference management
- The mechanistic hypothesis itself — that supporting oligodendrocyte energy metabolism could promote remyelination — remains active in the field, but the search for compounds has moved beyond biotin to other candidates (clemastine, opicinumab, GSK239512, and others)
Current standard care for progressive multiple sclerosis consists of the approved disease-modifying therapies (ocrelizumab for PPMS, siponimod for active SPMS) where they apply, symptom management (spasticity, fatigue, bladder, gait) and rehabilitation. All three randomised trials tested high-dose biotin as an add-on to such care, not as a replacement for it.
Lessons for Clinical Research
The high-dose biotin trajectory illustrates several enduring lessons:
- Mechanistic plausibility is not clinical efficacy. A compelling biochemical story (fatty acid synthesis, oligodendrocyte energy) does not guarantee clinical benefit. The link from mechanism to outcome involves dozens of unknown variables.
- Phase 2 positive signals require Phase 3 replication. Small early trials are prone to false-positive findings — chance excursions, regression to the mean, unblinding artifacts, selection effects. Confirmatory trials are designed to filter these out, and a positive Phase 2 signal that fails to replicate in Phase 3 is a familiar outcome, not a surprise.
- Placebo response in chronic disease is variable. The dramatic difference in placebo response between MS-SPI (0%) and MS-SPI2 (9%) illustrates how a "control" arm can vary by population, timing, expectation, and chance.
- Off-label uptake based on Phase 2 data has costs. Years of patient effort, expense, and time were invested in a treatment that did not work — a cost of adopting an unconfirmed intervention even when the rationale seems strong.
- Negative trials are important to publish. MS-SPI2 was published promptly and clearly, despite the disappointing result. This transparency allowed the field to recalibrate quickly. Negative trial publication bias remains a problem in clinical research generally; this one was handled well.
- An intervention can fail at the primary outcome while still teaching us something. The lab-test interference problems brought to attention by high-dose biotin accelerated improvements in clinical chemistry that benefit all biotin users, including the consumer hair-supplement population.
Patient FAQ
What is known for people still taking 300 mg/day biotin for progressive multiple sclerosis
The current consensus is that high-dose biotin does not meaningfully alter progressive multiple sclerosis outcomes based on the MS-SPI2 confirmatory trial. Some patients perceive subjective benefit, which may be real (placebo, attention, hope-based improvement in fatigue and mood) or may reflect natural disease variation. In one US clinic series of 43 patients, several who worsened on biotin improved after stopping it. Continuing carries minimal medical risk from biotin itself but produces ongoing laboratory-test interference (Graves' mimic, troponin masking) and adds expense.
Why the trials disagreed
The most likely explanation is that MS-SPI was a small Phase 2 trial with an unusually low placebo response rate (0%) due to chance plus a possibly enriched study population. MS-SPI2 was larger, longer, and had a more representative placebo response (9%). The active-arm response was similar in both (~12%). The MS-SPI2 finding (12% active vs 9% placebo = no meaningful difference) is the more reliable estimate of the true effect.
When a neurologist still prescribes high-dose biotin
This has become less common after MS-SPI2. Where it continues, it is typically in a specific patient with severe progressive disease, limited other options, and willingness to manage the lab-test interference, with an explicit informed-consent discussion of the negative confirmatory trial and the lab-test issues.
How lower biotin doses compare
The proposed mechanism specifically required supra-physiological doses (300 mg/day). Lower doses (1-10 mg/day) are unlikely to engage the mechanism even if it existed. So scaling down does not produce a safer-but-still-active intermediate — it produces a typical biotin supplement dose with no mechanism for multiple sclerosis benefit.
How biotin can make a thyroid panel look like Graves' disease
Biotin interference is a known cause in people taking high-dose pharmaceutical biotin or any 5 mg+ daily biotin, depending on the assay the laboratory uses. Suppressed thyroid-stimulating hormone and elevated free T4 in a biotin user with no other clinical features of hyperthyroidism is biotin interference until proven otherwise. The diagnostic test is to stop biotin for 5-7 days, retest the panel, and observe normalization. See the Lab-Test Interference page.
Treatments used for progressive multiple sclerosis
For primary progressive multiple sclerosis: ocrelizumab is U.S. Food and Drug Administration-approved and modestly slows progression. For active secondary progressive multiple sclerosis: siponimod is U.S. Food and Drug Administration-approved. Other interventions used include rituximab, cladribine, and natalizumab in selected cases. Beyond disease-modifying therapies, evidence-based interventions include rehabilitation, exercise programs, and management of spasticity, fatigue, bladder symptoms, and depression.
Other "remyelination" candidates under investigation
Clemastine (an old antihistamine that promotes oligodendrocyte differentiation in vitro and showed modest signal in the ReBUILD trial), opicinumab (anti-LINGO-1), and several other candidates are in various stages of investigation. None has yet achieved Phase 3 success. The remyelination question remains a major unmet need in multiple sclerosis therapeutics.
Cautions
- Lab-test interference dominates the safety profile at 300 mg/day. Patients on this dose will have falsely-suppressed thyroid-stimulating hormone, falsely-elevated free T4 (Graves' mimic), falsely-low troponin (potential to mask myocardial infarction, MI), falsely-low or -high other immunoassay analytes. Biotin use therefore changes how any of these results is read. See the dedicated page.
- The death linked to falsely low troponin. The U.S. Food and Drug Administration's 2019 communication cited a report of one patient taking high levels of biotin who died following low troponin test results on a troponin test subject to biotin interference. This is not theoretical risk — it has happened. Troponin is the blood test used to diagnose a heart attack, so chest pain in a person taking high-dose biotin is the situation where a falsely low result can hide one.
- Biotin was tested as an add-on, not a replacement. The approved disease-modifying therapies for progressive multiple sclerosis are ocrelizumab and siponimod; all three randomised trials tested high-dose biotin alongside standard care, not in place of it.
- Off-label compounding cost. Without a high-dose pharmaceutical biotin product commercially available, achieving 300 mg/day from over-the-counter biotin requires 30-60 tablets per day or compounded preparations. Annual cost can run $1,500-$3,000+ for a treatment that did not show clinical benefit in the confirmatory trial.
- Subjective benefit perception is real but uncertain. Some patients report subjective improvement in fatigue, gait, or vision on high-dose biotin. The MS-SPI2 result suggests these are largely placebo effects, but the experience to the individual is real. Stopping the supplement may not produce reciprocal worsening even if it was contributing to perceived improvement.
- Withdrawal in patients with biotinidase deficiency. A multiple sclerosis patient with undiagnosed biotinidase deficiency taking 300 mg/day biotin would have her biotinidase deficiency treated as a side effect. If she stops, the carboxylase deficiency would manifest. This is rare but worth keeping on the differential in any high-dose biotin user with unexpected metabolic findings on discontinuation.
Key Research Papers
- Tourbah A, Lebrun-Frenay C, Edan G et al. (2016). MD1003 (high-dose biotin) for the treatment of progressive multiple sclerosis: A randomised, double-blind, placebo-controlled study. Multiple Sclerosis Journal. 22(13):1719-1731 — PubMed PMID: 27589059
- Cree BAC, Cutter G, Wolinsky JS et al. (2020). Safety and efficacy of MD1003 (high-dose biotin) in patients with progressive multiple sclerosis (SPI2): a randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Neurology. 19(12):988-997 — PubMed PMID: 33222767
- Sedel F, Papeix C, Bellanger A et al. (2015). High doses of biotin in chronic progressive multiple sclerosis: a pilot study. Multiple Sclerosis and Related Disorders. — PubMed PMID: 25787192
- Sedel F, Bernard D, Mock DM, Tourbah A (2016). Targeting demyelination and virtual hypoxia with high-dose biotin as a treatment for progressive multiple sclerosis. Neuropharmacology. — PubMed PMID: 26327679
- Birnbaum G, Stulc J (2017). High dose biotin as treatment for progressive multiple sclerosis. Multiple Sclerosis and Related Disorders. — PubMed PMID: 29141796
- Couloume L, Barbin L, Leray E et al. (2020). High-dose biotin in progressive multiple sclerosis: A prospective study of 178 patients in routine clinical practice. Multiple Sclerosis Journal. 26(14):1898-1906 — PubMed PMID: 31845825
- Espiritu AI, Remalante-Rayco PPM (2021). High-dose biotin for multiple sclerosis: A systematic review and meta-analyses of randomized controlled trials. Multiple Sclerosis and Related Disorders. 55:103159 — PubMed PMID: 34332461
- Lim SK, Pilon A, Guéchot J (2017). Biotin interferes with free thyroid hormone and thyroglobulin, but not TSH measurements using Beckman-Access immunoassays. Annales d'Endocrinologie. 78(3):186-187 — PubMed PMID: 28209262
- Tourbah A, Gout O, Vighetto A et al. (2018). MD1003 (high-dose pharmaceutical-grade biotin) for the treatment of chronic visual loss related to optic neuritis in multiple sclerosis: A randomized, double-blind, placebo-controlled study. CNS Drugs. 32(7):661-672 — PubMed PMID: 29808469
- Peyro Saint Paul L, Debruyne D, Bernard D, Mock DM, Defer G (2016). Pharmacokinetics and pharmacodynamics of MD1003 (high-dose biotin) in the treatment of progressive multiple sclerosis. Expert Opinion on Drug Metabolism & Toxicology. — PubMed PMID: 26699811
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B7 Overview
- Benefits Hub
- Hair, Skin & Nails
- Lab-Test Interference
- Multiple Carboxylase Deficiency
- Multiple Sclerosis
- Vitamin D (Multiple Sclerosis connection)
- Vitamin B12 (myelin)
- Vitamin B1 (Thiamine)
- Thyroid-Stimulating Hormone
- Free T4
- Troponin
- Graves' Disease
- Heart Attack
- Optic Neuritis
- Deficiency
- Toxicity
- History