Vitamin B5 for Acne and Skin Health
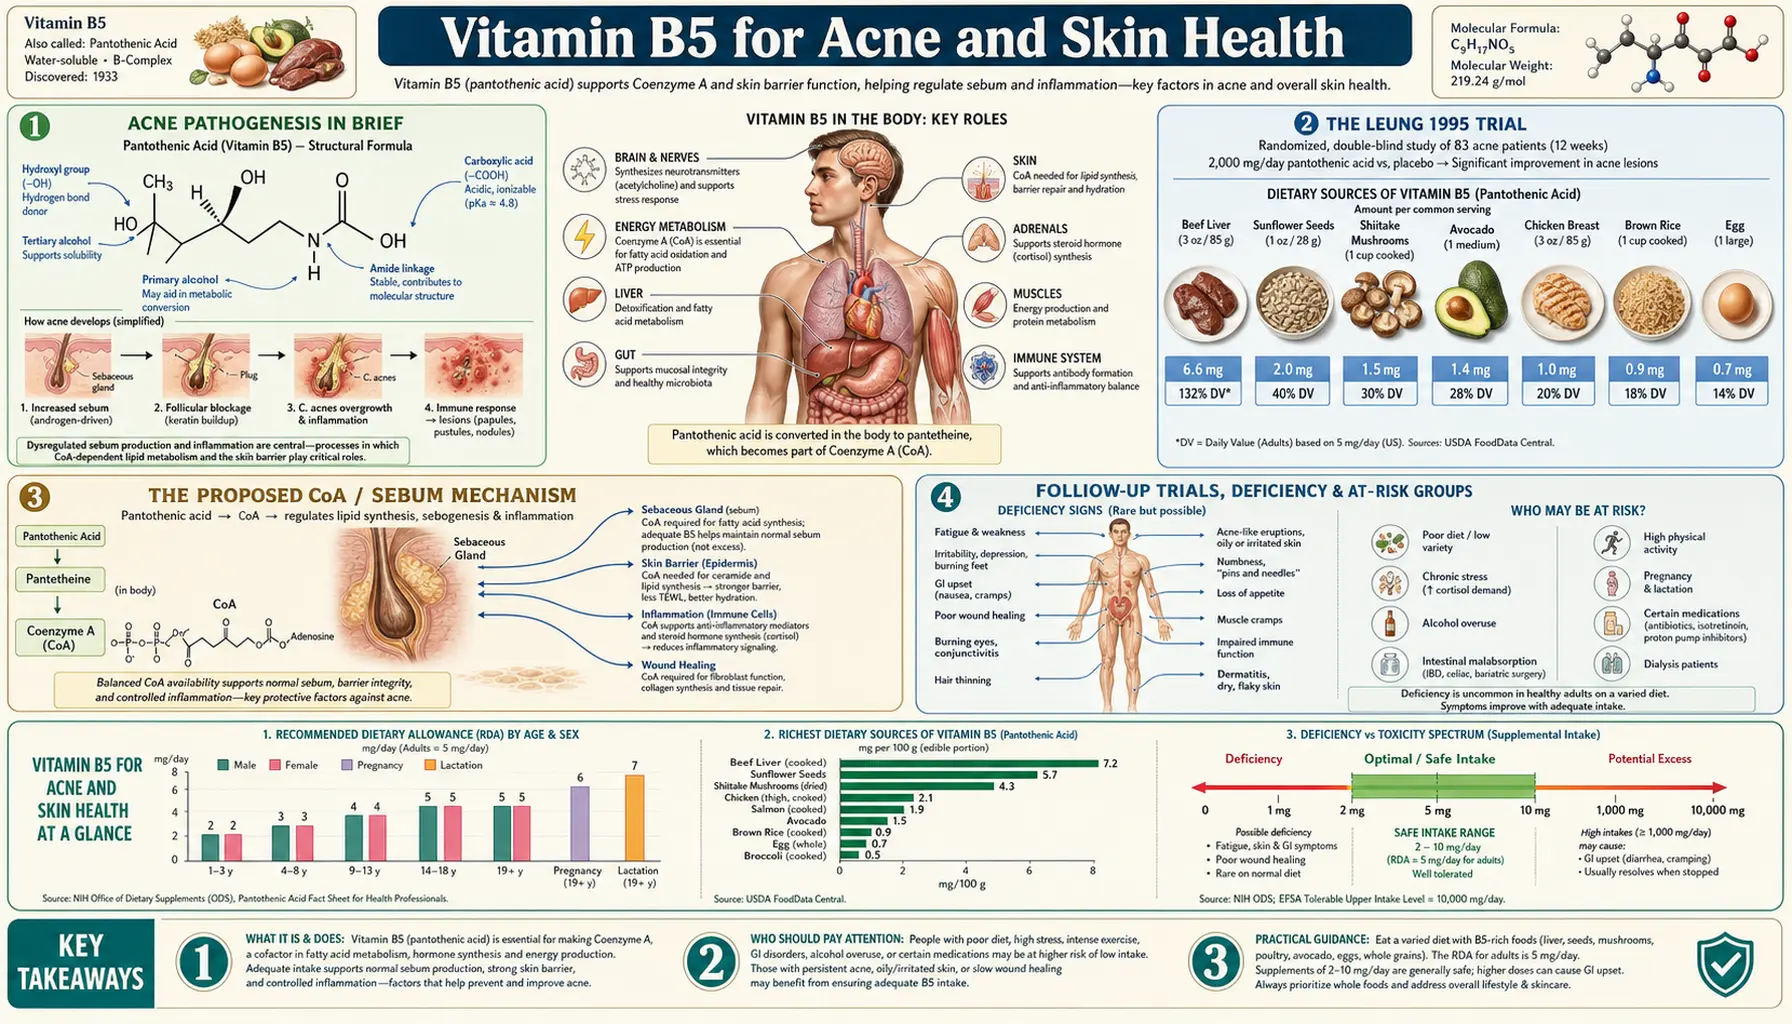
In 1995, Hong Kong physician Lit-Hung Leung (a surgeon at Hong Kong Central Hospital) proposed in Medical Hypotheses that acne comes from a shortage of pantothenic acid, and in a 1997 Journal of Orthomolecular Medicine article he described treating 100 acne patients with 10 g/day of oral pantothenic acid plus a 20% pantothenic acid cream — less oily skin within 2-3 days, lesions starting to regress after 2 weeks, and moderate acne “normally in complete control in about 8 weeks”, in his words. The proposed mechanism was that CoA pool expansion drove the sebaceous gland to oxidize fatty acids rather than secrete them as sebum, reducing the substrate for Cutibacterium acnes (formerly Propionibacterium acnes) overgrowth and the resulting inflammation. The protocol entered integrative-dermatology practice and remains in use today — though, as practitioners describe it, typically at lower doses (1-2 g/day) and often combined with L-carnitine and pantethine. Mainstream dermatology has remained skeptical given the methodological limitations of the original trial. This page covers the Leung study and its successors, the mechanistic hypothesis, modern combination protocols, royal-jelly-derived pantothenate, the safety record at gram-level dosing, and honest framing of what the evidence shows.
Table of Contents
- Acne Pathogenesis in Brief
- The Leung Case Series (1995 and 1997)
- The Proposed CoA / Sebum Mechanism
- Follow-up Trials
- Yang 2014 — The Modern Randomized Controlled Trial
- B5 + L-Carnitine + Pantethine Combinations
- Royal Jelly-Derived Pantothenate
- Protocols Described in Practice and in the Studies
- Topical Dexpanthenol
- The Mainstream Dermatology View
- Common Questions, Answered as Facts
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Acne Pathogenesis in Brief
Acne vulgaris involves the interaction of four overlapping pathogenic factors in the pilosebaceous unit (the hair follicle + adjacent sebaceous gland):
- Increased sebum production. Driven primarily by androgens (testosterone, dihydrotestosterone) acting on the sebaceous gland. Insulin and insulin-like growth factor 1 (IGF-1) also stimulate sebogenesis — which is part of why high-glycemic-load diets and dairy intake worsen acne in many patients.
- Abnormal follicular keratinization. Keratinocytes lining the follicular duct fail to shed normally and instead form a plug (microcomedone), trapping sebum and debris inside the follicle.
- Cutibacterium acnes proliferation. The skin commensal bacterium (formerly named Propionibacterium acnes) overgrows in the lipid-rich anaerobic environment of the blocked follicle. The bacteria produce inflammatory mediators and activate Toll-like receptor 2 on host immune cells.
- Inflammation. The host inflammatory response — recruitment of neutrophils, release of cytokines — produces the visible erythema and pustule formation. Significant inflammation also occurs before visible lesion formation, in the microcomedone stage.
Conventional treatments target each factor: topical retinoids (normalize keratinization), benzoyl peroxide and topical/oral antibiotics (reduce C. acnes), oral contraceptives and spironolactone in women (reduce androgen drive), and isotretinoin (reduces sebum production and combines all the mechanisms). The pantothenate hypothesis enters at point 1 — reducing sebum production through a CoA-dependent metabolic mechanism.
The Leung Case Series (1995 and 1997)
Lit-Hung Leung first set out the theory, and said a complete cure follows a “very liberal replacement therapy” with the vitamin, in a 1995 Medical Hypotheses paper. He described his patient series in more detail in a 1997 Journal of Orthomolecular Medicine article (volume 12, pages 99-114), where he writes that the results “were first reported in Medical Hypotheses”.
Study design, as Leung describes it in the 1997 article:
- 100 patients of Chinese descent with acne vulgaris (45 males, 55 females, ages 10-30, about 80% of them aged 13-23)
- Open-label, no control group, no blinding
- Oral pantothenic acid 10 g/day in 4 divided doses
- A cream of 20% pantothenic acid by weight applied to the affected area 4-6 times a day
- Treatment continued until the acne was controlled
Results as Leung reported them (he gives no percentage of patients cleared):
- A noticeable decrease in facial sebum usually 2-3 days after starting
- After 2 weeks, existing lesions start to regress and new lesions appear more slowly; skin pores look smaller within 1-2 weeks
- In moderate cases, the condition “normally in complete control in about 8 weeks”
- In severe cases, complete control may take months, sometimes six months or longer, and the dose was sometimes raised to 15-20 g/day
- Leung wrote that he had observed no toxicity in anyone taking 10-20 or more grams a day for prolonged periods, in some cases more than a year
- On maintenance, he wrote that most patients technically do not need a maintenance dose because acne tends to subside after puberty, but that he favoured one for all patients, lowered or adjusted to symptoms
The series' limitations are significant: open-label, uncontrolled, single-investigator, single-site, with no outcome percentages reported, and the detailed account published in a journal not indexed in most mainstream databases. Methodologically, this is far below the standard required for U.S. Food and Drug Administration (FDA) drug approval. But the size of the reported effect was so striking, and the safety profile so benign, that the protocol entered integrative-dermatology practice. The 1990s and 2000s saw widespread anecdotal use of "Dr. Leung's protocol" in alternative medicine circles, particularly online acne-discussion communities.
The Proposed CoA / Sebum Mechanism
Leung's mechanistic hypothesis, articulated in the 1995 Medical Hypotheses paper:
The sebaceous gland is one of the most metabolically active tissues in the human body, producing tens of grams of sebum per day. Sebum consists primarily of triglycerides, wax esters, squalene, and free fatty acids — all of which require CoA-dependent fatty acid synthesis to manufacture. The proposed bottleneck: the high lipid synthesis flux in the sebaceous gland consumes CoA faster than the gland can regenerate it from limited dietary pantothenate, particularly during the hormonal surge of puberty when androgen drive maximally stimulates the gland.
Under pantothenate insufficiency at the sebaceous-gland level, the gland is theoretically forced into a compensatory metabolic state: incomplete fatty acid metabolism, accumulation of free fatty acids in sebum (irritating to the follicle), increased sebum viscosity, and possibly altered sebum composition that favors C. acnes growth. Supplementing pantothenate at gram-level doses, in this model, expands the cellular CoA pool sufficiently to allow the sebaceous gland to redirect fatty acids from secretion into oxidation — reducing the volume of sebum produced and altering its composition toward less inflammatory species.
How much of this is correct is unclear. The hypothesis is mechanistically plausible — CoA pool size does influence the balance between fatty acid synthesis and oxidation in metabolically active tissues. But the assumption that sebaceous-gland CoA is rate-limiting in pantothenate-replete humans is unproven, and the broader assumption that pantothenate at the Adequate Intake level is insufficient for the sebaceous gland under normal hormonal drive is also unproven. The mechanism may be entirely wrong even if the clinical effect Leung described is real (which is itself uncertain).
An alternative mechanism that has been proposed: high-dose pantothenate exerts a direct antibacterial effect on C. acnes, or modulates the host inflammatory response, or acts through pantethine-driven changes in fatty acid metabolism that don't require the assumption of baseline pantothenate deficiency. None of these alternatives have strong evidence either, but they are mentioned in the literature.
Follow-up Trials
Between Leung's 1995 publication and the late 2000s, the pantothenate-for-acne literature consisted mostly of case reports, small clinical observations, and online patient self-reports — not formal randomized trials. Why no large randomized controlled trial (RCT) replicated Leung's protocol is itself a question worth asking: the absence of a patentable compound removes commercial incentive for pharmaceutical-industry funding; dermatology research priorities have been dominated by isotretinoin, hormonal therapies, and topical agents; and the methodological limitations of the original work made it easy for mainstream dermatology to dismiss without re-investigating.
The most-cited follow-up work:
- Capodice JL (2012) — a feasibility study of a pantothenic-acid-based dietary supplement in mild to moderate facial acne. As the later Yang 2014 trial describes it, 8 weeks of daily supplementation was feasible and safe, and total facial lesions fell over the 8-week study as a secondary endpoint.
- Various integrative-medicine case series — mostly publications in integrative or naturopathic journals reporting clinical experience with 1-3 g/day pantothenate protocols in private practice. Useful as observation, weak as evidence.
Independent replication of Leung's reported results has not been published in the peer-reviewed dermatology literature. The most likely explanation: the effect is real but smaller than Leung reported (open-label trials systematically inflate effect sizes), and the dose required for the smaller real effect is too inconvenient (4 divided doses of large capsules daily) to compete with isotretinoin or oral antibiotics as a mainstream therapy.
Yang 2014 — The Modern Randomized Controlled Trial
The first reasonably-powered randomized trial of pantothenic acid for acne in the mainstream literature was Yang et al., 2014, published in Dermatology & Therapy:
- Adults with mild to moderate acne vulgaris recruited at 2 dermatology sites: 48 randomized, 41 evaluable (20 on the supplement, 21 on placebo; 5 men and 36 women)
- Randomized, double-blind, to a pantothenic-acid-based dietary supplement (two tablets twice a day with food; each day's four tablets contained 2.2 g pantothenic acid) or a matched placebo, for 12 weeks
- Primary outcome: total facial lesion count
Results:
- Lesion count in the supplement group versus the placebo group was reduced by 68.21% at 12 weeks (the authors also describe it as a “greater than 67% reduction”)
- The difference was statistically significant (P = 0.0197)
- Inflammatory and non-inflammatory lesions both fell significantly more than on placebo, and quality-of-life (Dermatology Life Quality Index) scores were significantly lower
- Two adverse events (fatigue on placebo, shingles on the supplement) were judged unrelated; blood counts and liver tests did not change
The Yang trial is the closest thing to mainstream-acceptable evidence that pantothenic-acid-based protocols can reduce acne lesions. The limitations: small sample, 7 of 48 randomized people not evaluable, and the tested tablet was a manufacturer-supplied commercial formulation — a common source of bias in supplement research, so independent replication matters. But the dose (2.2 g/day) is more achievable than Leung's 10 g/day, and the effect size is large enough to be clinically meaningful.
The reasonable summary: there is now some randomized-trial evidence supporting the integrative-medicine practice of using gram-level pantothenate for acne — though in practice it is typically used as part of a combination rather than alone.
B5 + L-Carnitine + Pantethine Combinations
The most common modern protocols described by integrative practitioners combine pantothenic acid with other CoA-pathway-adjacent nutrients to enhance the fatty acid oxidation effect:
- L-Carnitine (500-2,000 mg/day). Required to transport long-chain fatty acyl-CoAs into mitochondria for β-oxidation. Pairing carnitine with pantothenate provides both the CoA pool and the transporter for the proposed "burn fat rather than secrete it" sebaceous-gland shift.
- Pantethine (300-600 mg/day). The disulfide dimer of pantetheine, downstream of PANK in CoA biosynthesis, theoretically more efficient at expanding the CoA pool than pantothenate itself. Sometimes substituted for part of the pantothenate dose in protocols.
- Zinc (30-50 mg/day, with copper if long-term). Required cofactor for retinol-binding protein, has been independently studied for acne with modest positive results. Standard component of integrative acne protocols.
- Thiamine (Vitamin B1) (50-100 mg/day). Cofactor for pyruvate dehydrogenase, which produces acetyl-CoA from pyruvate. Supports the pantothenate/CoA-driven fatty acid oxidation framework.
- Vitamin A (5,000-10,000 international units (IU)/day). Lower-dose precursor of the topical retinoids that are the conventional first-line acne therapy. Caution at higher doses (hepatotoxicity, teratogenicity).
- Probiotics. Emerging evidence for gut-skin axis involvement in acne; Lactobacillus and Bifidobacterium strains have shown modest benefit in small trials.
The typical integrative protocol stack practitioners describe for moderate acne is: pantothenic acid 1-2 g/day + L-carnitine 1 g/day + zinc 30 mg/day + B-complex + omega-3 fatty acids (2-3 g/day, anti-inflammatory) + topical pantothenate or dexpanthenol cream + dietary modification (low glycemic load, dairy reduction).
Royal Jelly-Derived Pantothenate
Royal jelly — the substance secreted by worker honeybees to feed the queen larva and the queen throughout her life — is one of the most concentrated natural sources of pantothenic acid. A 2019 review gives pantothenic acid as the most abundant vitamin in royal jelly, at 52.8 mg per 100 g, alongside other bioactive components: 10-HDA (10-hydroxy-2-decenoic acid, a fatty acid unique to royal jelly), royalisin and jelleines (antimicrobial peptides), and a complex mixture of proteins, lipids, sugars, and other vitamins.
Royal jelly has been used in traditional natural-medicine practice for skin conditions, vitality, and longevity. Whether the skin and acne benefits attributed to royal jelly are due primarily to its pantothenate content, the 10-HDA content (which has documented antimicrobial and anti-inflammatory effects), or some other royal-jelly-specific bioactive is unclear. Small clinical trials of royal jelly for skin conditions (rosacea, dermatitis, wound healing) have shown modest positive effects; head-to-head comparison with pure pantothenate is not in the literature.
Royal jelly is significantly more expensive per unit pantothenate than synthetic calcium D-pantothenate, and carries a small risk of severe allergic reactions (anaphylaxis has been reported, particularly in patients with bee or pollen allergies). Per unit of pantothenate, calcium D-pantothenate is the cheaper source. In royal jelly as a whole food, the 10-HDA and other bioactives may matter more than the pantothenate itself.
Protocols Described in Practice and in the Studies
The light and standard regimens below are the ones integrative practitioners describe; they have not been tested as written in a trial. The doses actually used in the published studies are listed after them.
Light protocol described by practitioners (mild acne)
- Pantothenic acid 1 g/day (500 mg twice daily with meals)
- Zinc picolinate 30 mg/day
- Topical dexpanthenol cream 5% once or twice daily to affected areas
- Dietary changes: fewer high-glycemic-load foods and an 8-week trial without dairy
- Response judged at 8 weeks
Standard protocol described by practitioners (moderate acne)
- Pantothenic acid 2 g/day (500 mg four times daily, or 1 g twice daily)
- L-Carnitine 1 g/day
- Zinc 30-50 mg/day (with 2 mg copper, since months of zinc can cause copper deficiency)
- Vitamin B-complex (covering B1, B2, B3, B6, B7, B9, B12)
- Omega-3 (eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA)) 2-3 g/day
- Topical dexpanthenol 5% twice daily
- Dietary changes as above
- Response judged at 12 weeks
Doses used in the published studies
- Leung (1995, 1997): pantothenic acid 10 g/day in 4 divided doses, plus a 20% pantothenic acid cream 4-6 times a day; 15-20 g/day in some severe cases; a lowered maintenance dose adjusted to symptoms
- Yang 2014 trial: 2.2 g/day pantothenic acid (two tablets twice a day with food) for 12 weeks
- Practitioners using the high-dose approach also describe adding L-carnitine 2 g/day and pantethine 600 mg/day, and lowering the dose when diarrhea occurs
The 10 g/day Leung regimen means many large capsules in four doses a day; practitioners describe 2 g/day as easier to keep up. The Yang 2014 randomized controlled trial used 2.2 g/day, close to the standard-protocol dose, and reported a significant reduction in lesions.
Some people who are weighing isotretinoin use a 12-week pantothenate protocol first. Isotretinoin has the strongest evidence of any acne therapy, and the pantothenate protocols have not been shown to control nodulocystic acne, where scars form and are permanent.
Topical Dexpanthenol
Dexpanthenol (the alcohol form of D-pantothenic acid) is the most widely used topical form of vitamin B5 in dermatology and skincare. Once applied to skin, dexpanthenol is rapidly oxidized to pantothenic acid in epidermal cells. Topical effects:
- Humectant. Dexpanthenol attracts and binds water in the stratum corneum, improving skin hydration. This is the basis for its inclusion in countless moisturizers, especially after-sun and post-procedure products.
- Anti-inflammatory. Reduces erythema, irritation, and inflammation in compromised skin. Documented benefit in atopic dermatitis, contact dermatitis, irritated diaper area, and post-procedure skin (laser, microdermabrasion, retinoid irritation).
- Wound-healing acceleration. Stimulates fibroblast proliferation and epithelial turnover, speeding closure of superficial wounds. See the sibling page Pantothenic Acid & Wound Healing for detail.
- Barrier function support. Improves epidermal barrier integrity through effects on lipid synthesis and keratinocyte differentiation.
Dexpanthenol is in countless over-the-counter moisturisers, barrier creams, nappy-rash creams and healing ointments — look for “dexpanthenol” or “panthenol” in the ingredient list. Concentrations range from 2-10% in moisturizers up to 50% in some wound-healing ointments. The topical safety record is excellent — the only reported adverse reactions are rare contact allergies, which are usually traced to formulation additives rather than dexpanthenol itself.
For acne specifically, topical dexpanthenol is most useful as supportive care to reduce the irritation from concurrent retinoid or benzoyl peroxide therapy, rather than as a primary acne treatment. The combination of irritation-reducing dexpanthenol + active acne therapy lets patients tolerate higher concentrations of the active treatment.
The Mainstream Dermatology View
Mainstream dermatology has historically been skeptical of high-dose pantothenate for acne, for legitimate reasons:
- The Leung 1995 trial was methodologically weak (open-label, uncontrolled, single-investigator)
- The proposed mechanism (CoA-pool-limited sebogenesis) has not been mechanistically demonstrated in human sebaceous glands
- The clinical evidence base remained thin for nearly two decades after Leung's publication
- The doses required (multiple grams per day) are impractical compared to topical or oral antibiotic alternatives
- For severe acne, isotretinoin produces near-universal remission with a well-characterized risk/benefit profile, making competing interventions hard to position
Modern dermatology guidelines (American Academy of Dermatology, European Dermatology Forum) do not include pantothenic acid in standard acne treatment algorithms. The standard tier of acne therapy remains: topical retinoid + benzoyl peroxide + topical antibiotic (mild-moderate); add oral antibiotic, hormonal therapy in women, or isotretinoin (moderate-severe).
What has shifted somewhat in the post-Yang 2014 era is willingness among more open-minded dermatologists to consider pantothenate-based protocols as adjunct therapy in patients who are wary of long antibiotic courses, who don't want isotretinoin, or who have responded poorly to first-line conventional therapy. In short: this is an integrative-medicine option with growing but still-limited evidence; pantothenic acid has a good safety record at gram doses; it may produce modest improvement; it has not been shown to replace first-line therapy in severe disease.
Common Questions, Answered as Facts
How well it works
Probably modestly. Leung's results (complete control of moderate acne in about 8 weeks) came from an open series with no blinding and no placebo group, which tends to inflate effects. The Yang 2014 randomized controlled trial reported lesion counts 68% lower than placebo at 12 weeks with 2.2 g/day — clinically meaningful, at a quarter of Leung's dose. This page's own estimate, not a trial figure, is a 30-60% lesion reduction over 12 weeks in people who respond.
How long results take
Leung reported less sebum within 2-3 days and lesions regressing after 2 weeks. Practitioners describe 6-12 weeks before a visible effect at lower doses; the Yang trial measured its result at 12 weeks.
How safe gram-level doses are
Pantothenic acid has one of the cleanest safety profiles of any vitamin or supplement. Gram-level doses cause occasional mild gastrointestinal side effects (loose stools, mild nausea) that resolve with dose reduction. There is no significant organ toxicity at these doses. Long-term high-dose use (over months) can modestly reduce biotin absorption; some practitioners add 300-500 µg of biotin a day when the protocol runs longer than 6 months.
Use alongside topical retinoids (tretinoin, adapalene)
Oral pantothenate has no known interaction with topical retinoids. Topical dexpanthenol moisturizer can actually improve tretinoin tolerance by reducing the irritation. They are complementary.
Pantothenate and isotretinoin
Some people with moderate acne use a 12-week pantothenate protocol before isotretinoin. In severe acne with active scarring, the scars are permanent and the pantothenate protocols have not been shown to control severe disease reliably, while isotretinoin has the strongest evidence.
Stopping once the acne clears
Leung wrote that most patients technically do not need a maintenance dose, because acne tends to subside after puberty, but he favoured a lowered maintenance dose for all patients against new eruptions. Practitioners describe mixed experience: some people taper after 3-6 months of clear skin and stay clear, others go on taking 1-2 g/day.
Diet and acne
Dietary changes (low-glycemic-load diet, dairy elimination) have stronger and more consistent evidence for acne improvement than any supplement protocol. The supplement and diet approaches are complementary, not alternatives.
Cautions
- Gastrointestinal side effects at high doses. Gram-level pantothenic acid often causes mild loose stools or diarrhea, particularly when started abruptly at high dose. Practitioners describe starting at 500 mg/day and raising the dose over 1-2 weeks, taken with food; the Yang trial tablets were taken with food.
- Biotin competition. Long-term high-dose pantothenate competes with biotin at the sodium-dependent multivitamin transporter (SMVT), which carries both into cells. Some practitioners add 300-500 µg/day biotin when the protocol runs longer than 6 months.
- Pregnancy. There is little safety data on gram-level doses during pregnancy or breastfeeding. The Adequate Intake (AI) in pregnancy is 6 mg/day.
- Severe nodulocystic acne. Its scars are permanent, and the pantothenate protocols have not been shown to control it; isotretinoin is the treatment with the strongest evidence.
- Royal jelly allergy. Anaphylaxis from royal jelly has been reported, and the risk is highest in people with bee allergy, pollen allergy, or asthma.
- Underlying medical evaluation. Sudden-onset adult acne, particularly in women with hirsutism, menstrual irregularities, or weight gain, can signal an underlying hormonal disorder (polycystic ovary syndrome (PCOS), hyperandrogenism, late-onset congenital adrenal hyperplasia). Hormone blood tests are how these are found, and a supplement does not treat them.
- Drug interactions. No significant interactions documented at typical doses. The supplement does not interfere with oral contraceptives, antibiotics, or topical acne medications.
Key Research Papers
- Leung LH (1995). Pantothenic acid deficiency as the pathogenesis of acne vulgaris. Medical Hypotheses. 44(6):490-492. — PubMed PMID: 7476595
- Leung LH (1997). A stone that kills two birds: how pantothenic acid unveils the mysteries of acne vulgaris and obesity. Journal of Orthomolecular Medicine. 12(2):99-114. — Full text (PDF)
- Yang M, Moclair B, Hatcher V, Kaminetsky J, Mekas M, Chapas A, Capodice J (2014). A randomized, double-blind, placebo-controlled study of a novel pantothenic acid-based dietary supplement in subjects with mild to moderate facial acne. Dermatology and Therapy. 4(1):93-101. — PubMed PMID: 24831048
- Capodice JL (2012). Feasibility, tolerability, safety and efficacy of a pantothenic acid based dietary supplement in subjects with mild to moderate facial acne blemishes. Journal of Cosmetics, Dermatological Sciences and Applications. 2:132-135. — doi:10.4236/jcdsa.2012.23026
- Ebner F, Heller A, Rippke F, Tausch I (2002). Topical use of dexpanthenol in skin disorders. American Journal of Clinical Dermatology. — PubMed PMID: 12113650
- Proksch E, de Bony R, Trapp S, Boudon S (2017). Topical use of dexpanthenol: a 70th anniversary article. Journal of Dermatological Treatment. — PubMed PMID: 28503966
- Kapoor S, Saraf S (2011). Topical herbal therapies an alternative and complementary choice to combat acne. Research Journal of Medicinal Plant. 5(6):650-669. — doi:10.3923/rjmp.2011.650.669
- Trivedi NR, Cong Z, Nelson AM et al. (2006). Peroxisome proliferator-activated receptors increase human sebum production. Journal of Investigative Dermatology. — PubMed PMID: 16675962
- Smith RN, Mann NJ, Braue A, Makelainen H, Varigos GA (2007). The effect of a high-protein, low glycemic-load diet versus a conventional, high glycemic-load diet on biochemical parameters associated with acne vulgaris: a randomized, investigator-masked, controlled trial. Journal of the American Academy of Dermatology. — PubMed PMID: 17448569
- Adebamowo CA, Spiegelman D, Berkey CS et al. (2008). Milk consumption and acne in teenaged boys. Journal of the American Academy of Dermatology. — PubMed PMID: 18194824
- Bowe WP, Logan AC (2011). Acne vulgaris, probiotics and the gut-brain-skin axis — back to the future? Gut Pathogens. — PubMed PMID: 21281494
- Melnik BC, Schmitz G (2009). Role of insulin, insulin-like growth factor-1, hyperglycaemic food and milk consumption in the pathogenesis of acne vulgaris. Experimental Dermatology. — PubMed PMID: 19709092