Vitamin B4 (Adenine), Modern Status and Food Sources
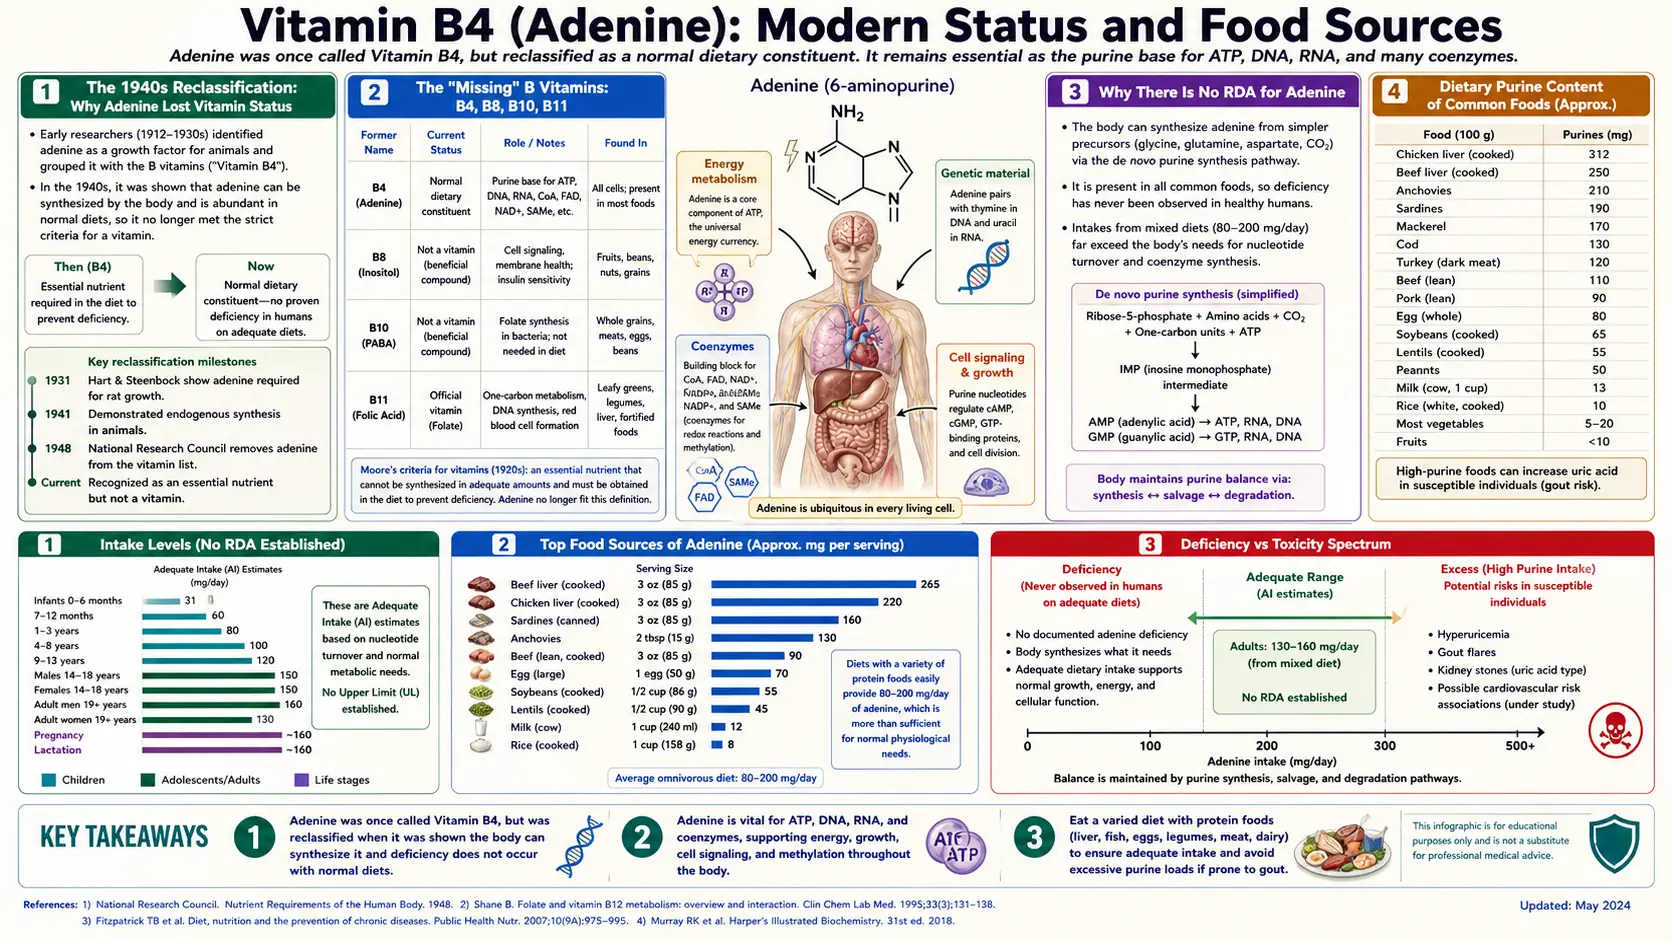
Adenine was reclassified out of the vitamin canon in the 1940s and 1950s when biochemists confirmed that human cells synthesize it in abundance from amino acid precursors through the de novo purine pathway. There is no Dietary Reference Intake, Recommended Dietary Allowance, or Adequate Intake for adenine in any modern nutritional guideline. Yet the "Vitamin B4" label persists in older European literature, in some commercial multivitamins, and in folk-nutrition discourse — and dietary purine content (of which adenine is roughly half) does have real clinical relevance in specific populations: gout patients, tumor lysis syndrome prophylaxis, patients with inborn errors of purine metabolism, and premature infants on total parenteral nutrition. This deep-dive covers the history of declassification, the food sources highest in purines, the clinical scenarios where diet matters, and the curious case of CPDA-1 blood preservation solution — one of the few medical settings where adenine is added intentionally to a clinical product.
Table of Contents
- The 1940s Reclassification: Why Adenine Lost Vitamin Status
- The "Missing" B Vitamins: B4, B8, B10, B11
- Why There Is No Recommended Dietary Allowance for Adenine
- Dietary Purine Content of Common Foods
- High-Purine Foods: Organ Meats, Sardines, Yeast
- The Gout Diet: When Dietary Purines Matter
- Fructose, Alcohol, and Uric Acid
- TPN, Infant Formula, and Conditional Essentiality
- CPDA-1 Blood Preservation: Adenine as Pharmaceutical
- European and Russian "Vitamin B4" Supplements
- Key Research Papers
- Connections
- Featured Videos
The 1940s Reclassification: Why Adenine Lost Vitamin Status
The history of nutrition science contains several molecules that were briefly classified as vitamins and later reclassified out. Adenine is one of the cleanest examples. The original observations came from nutrition laboratories in the 1920s and 1930s: rats fed purified diets stripped of nucleic acid were reported to develop leukopenia, growth failure, and impaired wound healing. The "vitamin B4" papers of that era came from Vera Reader and co-workers in Britain (Biochemical Journal, 1930 and 1932), and a 1947 French paper still called adenine the "vitamin B4 of leukocyte balance". The obvious inference was that some nucleic-acid-related factor was an essential dietary nutrient. Adenine, already structurally characterized by Emil Fischer in 1897, was assigned the placeholder "B4" in the still-expanding B-complex sequence.
Three lines of evidence dismantled the classification across the 1940s. First, John Buchanan and colleagues at MIT mapped the de novo purine biosynthesis pathway and demonstrated that mammalian cells synthesize purine bases from PRPP, glutamine, glycine, aspartate, and one-carbon units from folate. The synthetic capacity is robust and ramps up as needed.
Second, the original animal-deficiency observations were re-examined. The "leukopenia" and "growth failure" in those rats were re-attributed largely to folate deficiency (folate had not yet been recognized when the original observations were made), to amino-acid imbalance in the purified diets (glycine, glutamine, and aspartate are needed as ring-building precursors), and to other co-deficiencies in the unsupplemented test diets.
Third, the formal definition of "vitamin" tightened after World War II to require that the body cannot synthesize sufficient quantities of the molecule to meet metabolic demand. Adenine failed that test definitively in healthy humans, and by 1950 it had been removed from the official vitamin list in the U.S., U.K., and most European nutrition authorities.
The reclassification was reinforced by the discovery of the purine salvage pathway in the 1950s. Salvage enzymes (APRT, HGPRT) recycle approximately 90% of the daily purine turnover from breakdown products, dramatically reducing dependence on either de novo synthesis or dietary intake.
The "Missing" B Vitamins: B4, B8, B10, B11
The B-complex vitamin numbering has several gaps. The currently recognized B vitamins are B1 (thiamine), B2 (riboflavin), B3 (niacin), B5 (pantothenic acid), B6 (pyridoxine), B7 (biotin), B9 (folate), and B12 (cobalamin). The gaps at B4, B8, B10, and B11 represent compounds that were once provisionally classified as B vitamins but were later either reclassified as non-essential, recognized as duplicates of compounds already named, or shown to be biologically inactive.
- B4 = adenine — non-essential because human cells synthesize it de novo from PRPP and amino acids, plus the salvage pathway is robust. Sometimes the historical "B4" label was also applied to choline, which has had a tangled nomenclature history but is now classified as an essential nutrient with its own non-B-numbered name.
- B8 = inositol — non-essential because human cells synthesize it from glucose-6-phosphate. Inositol is metabolically important (phosphatidylinositol signaling, inositol phosphates as second messengers), but it does not meet the formal vitamin definition. Inositol supplements remain in use for polycystic ovary syndrome and as adjuncts in mood disorder, but the U.S. Food and Drug Administration (FDA) does not regulate them as vitamins.
- B10 = para-aminobenzoic acid (PABA) — not a vitamin for humans, but a precursor in the bacterial folate biosynthesis pathway. PABA is the target of the sulfonamide antibiotics (sulfa drugs), which compete with PABA for binding to dihydropteroate synthase. PABA also appears in some sunscreens as an ultraviolet-A absorber.
- B11 = pteryl-hepta-glutamic acid (a form of folate) — reclassified because it duplicates B9. Some literature also uses "B11" for salicylic acid, but that label has no biological basis.
The gap pattern is a fossil record. Early 20th-century nutrition science generated a continuous stream of "candidate vitamins" based on partial-purification studies of nutritional factors. Most candidates failed the rigorous standards eventually adopted — either because the body synthesized them, because they were already-known compounds under a new name, or because the original deficiency observations were confounded by other unrecognized deficiencies. The numbering survives in the gaps.
Why There Is No Recommended Dietary Allowance for Adenine
The U.S. Institute of Medicine (now National Academy of Medicine), the European Food Safety Authority (EFSA), and the WHO/FAO joint Codex Alimentarius all establish Dietary Reference Intakes (DRIs) only for nutrients that meet the formal definition of essentiality: the body cannot synthesize sufficient quantities to meet metabolic demand, and dietary intake below some threshold produces a recognizable deficiency syndrome in otherwise healthy people.
Adenine fails both criteria. The de novo purine biosynthesis pathway, combined with the salvage pathway, produces sufficient adenine and guanine in healthy adults regardless of dietary intake. No deficiency syndrome has ever been demonstrated in humans on a purine-restricted diet, even after prolonged restriction. (The closest analog is the experimental "purine-free" diet used to study uric acid metabolism in gout research, which produces only modest reductions in serum uric acid without any clinical sign of cellular dysfunction.)
Consequently, there is no Recommended Dietary Allowance (RDA), AI, EAR, or UL for adenine. No country's nutrition labeling regulations require adenine content to be declared on food packaging. The compound does not appear in the U.S. Department of Agriculture (USDA) Nutrient Database in its own right, although total purine content is sometimes provided in supplementary databases used for gout dietary counseling.
The closest there is to an "intake recommendation" for adenine is the implicit purine-restriction guidance given to gout patients: limit organ meats, sardines/anchovies, beer, and high-fructose corn syrup. Even this guidance is not a positive intake target — it is a maximum-tolerated intake to avoid worsening hyperuricemia.
Dietary Purine Content of Common Foods
Dietary purine content is usually reported as total purines (adenine + hypoxanthine + guanine + xanthine) in milligrams per 100 grams of food, because the four bases all converge on uric acid through the same catabolic pathway and have similar uric-acid-raising effects per mole.
A rough categorization used in gout dietary counseling:
- Very high purine (>300 mg / 100 g): organ meats (liver, kidney, sweetbreads, brain), anchovies, sardines, mackerel, herring, mussels, scallops, certain shellfish, yeast extract spreads, meat broths and gravies, game meats.
- Moderate-high purine (150–300 mg / 100 g): most other fish (tuna, salmon, trout), poultry skin, lentils, dried beans, peas, spinach, mushrooms, asparagus, cauliflower.
- Moderate purine (50–150 mg / 100 g): most muscle meats (beef, pork, lamb), other vegetables, whole grains.
- Low purine (<50 mg / 100 g): dairy products (milk, cheese, yogurt), eggs, most fruits, refined grains (white rice, white bread, pasta), low-fat baked goods, nuts.
The pattern is roughly that protein-dense animal tissues and rapidly-proliferating plant tissues (legumes, leafy greens, mushrooms, asparagus tips) have the highest purine content, while dairy, eggs, fruits, and refined grains are lowest. The reason is biological: cells with the highest nucleic acid concentration per gram have the highest purine content. Organ meats are particularly rich because the organ tissue itself was metabolically active, with high NAD, NADP, FAD, and adenosine triphosphate (ATP) concentrations.
Important nuance: dietary purines from vegetable sources appear to raise serum uric acid less than equivalent purine loads from animal sources, possibly due to slower absorption kinetics and the alkalinizing effect of vegetable diets. The Health Professionals Follow-up Study (Choi et al. 2004, New England Journal of Medicine) followed 47,150 men without gout for 12 years, during which 730 developed gout. Men in the top fifth of meat intake had a relative risk of 1.41 compared with the bottom fifth, and men in the top fifth of seafood intake a relative risk of 1.51. Purine-rich vegetables and total protein intake were not associated with a higher risk of gout, and men in the top fifth of total dairy intake had a relative risk of 0.56.
High-Purine Foods: Organ Meats, Sardines, Yeast
Organ meats (liver, kidney, sweetbreads, brain, heart) are the highest-purine foods in the diet, often containing 500–1000 mg of purines per 100 g. Beef liver also happens to be the most nutrient-dense food on Earth by most other metrics (Vitamin A, B12, copper, choline, folate), so the trade-off between micronutrient density and purine load is a real one for gout patients. The traditional 1–2 servings per week of beef liver recommended on ancestral-eating regimes is well within the dietary purine tolerance of most non-gout individuals.
Sardines and anchovies are exceptionally high in purines (350–500 mg / 100 g) because they are small whole fish eaten with bones, organs, and reproductive tissue intact. They are also exceptional sources of omega-3 fatty acids, calcium (from the bones), vitamin D, and selenium. Gout diet sheets often list sardines among the foods to limit (commonly to once a week or less); that purine concern applies to people with gout, not to people without it.
Yeast extracts (yeast extract spreads, brewer's yeast tablets) are concentrated yeast products with purine content typically 1000+ mg per 100 g. The serving size for table use is small (typically 5 grams), so the per-meal purine load is modest, but heavy users can exceed dietary purine recommendations for gout. Yeast extracts are also exceptional sources of B vitamins (especially B1, B2, B3, and B9) and are used in some traditional populations as fortified nutritional supplements.
Game meats (venison, elk, wild boar, rabbit) often have higher purine content than equivalent cuts of domesticated meat because game animals have more lean muscle and less intramuscular fat per unit weight — the muscle tissue itself is more cellularly dense.
Mushrooms are surprisingly high in purines (especially morels, porcini, and shiitake) because fungal cells maintain high RNA and DNA turnover.
Asparagus, spinach, and cauliflower are the highest-purine common vegetables but, per the vegetable-purine epidemiology cited above, do not appear to raise gout risk meaningfully.
The Gout Diet: When Dietary Purines Matter
For most people, dietary purine intake has only a modest effect on serum uric acid — perhaps 1–2 mg/dL between a very high-purine and very low-purine diet. Endogenous synthesis dwarfs dietary input in absolute terms.
In gout patients, that 1–2 mg/dL marginal effect matters because uric acid solubility has a hard threshold around 6.8 mg/dL at body temperature and physiologic pH. Above that threshold, monosodium urate crystals begin to form in synovial fluid and tendons. Bringing a patient from 7.5 mg/dL down to 6.5 mg/dL can substantially reduce flare frequency.
The 2020 American College of Rheumatology Guideline for the Management of Gout (FitzGerald et al.), written by a panel of doctors who treat gout, makes these lifestyle statements for people with gout:
- Limiting alcohol intake, purine intake and high-fructose corn syrup is conditionally recommended (beer contains both purines and ethanol, which competes with uric acid for excretion by the kidneys; the richest purine sources are organ meats, sardines and anchovies), as is a weight-loss program for people with gout who are overweight.
- Cherries and dairy — the panel reviewed the studies on cherries or cherry extract and on dairy protein and found the certainty of evidence, drawn mainly from observational studies, low or very low: too weak for any recommendation on either.
- Vegetable purines and plant protein — the guideline makes no statement on them. In the Health Professionals Follow-up Study (Choi et al. 2004), purine-rich vegetables and total protein intake were not associated with a higher risk of gout.
The panel also stopped recommending vitamin C for gout. Two small randomized trials (29 and 40 people) showed clinically insignificant changes in serum urate in people with gout taking vitamin C, and the guideline now conditionally recommends against adding vitamin C supplements.
The guideline emphasizes that diet alone is generally insufficient for patients with established gout requiring urate-lowering therapy. Allopurinol or febuxostat reliably lower serum uric acid by 30–50%, far more than any dietary intervention. The guideline notes that dietary changes likely yield only small changes in serum urate, although dietary factors may trigger flares.
Fructose, Alcohol, and Uric Acid
Two dietary factors raise serum uric acid more dramatically than purine intake per se: fructose and alcohol.
Fructose metabolism in the liver is unusual: fructose is rapidly phosphorylated by fructokinase to fructose-1-phosphate, consuming adenosine triphosphate without the normal feedback control of glucose phosphorylation. The adenosine triphosphate depletion increases AMP, which is then degraded down the purine catabolism pathway to uric acid. A single 500 mL bottle of high-fructose-corn-syrup soda can raise serum uric acid by 0.5–1.0 mg/dL within an hour. The 2020 American College of Rheumatology guideline states that taking in 1 g of fructose per kg of body weight raises serum urate by 1–2 mg/dL within 2 hours. Chronic high fructose intake is now recognized as one of the strongest dietary risk factors for both gout incidence and gout flare frequency.
In the Health Professionals Follow-up Study (Choi and Curhan 2008, BMJ), 46,393 men without gout were followed for 12 years and 755 developed gout. Men drinking two or more sugar-sweetened soft drinks a day had a relative risk of 1.85 compared with men drinking less than one a month, and men in the top fifth of fructose intake had a relative risk of 2.02 compared with the bottom fifth. Diet soft drinks were not associated with gout.
Alcohol raises uric acid by two mechanisms. First, ethanol metabolism in the liver elevates lactate, which competes with uric acid for renal tubular secretion via the URAT1 and OAT transporters — the body literally cannot excrete uric acid as fast while it is excreting lactate. Second, beer and certain spirits contain significant purine content (especially beer, which has 5–10 mg purines per 100 mL). The result is that beer is among the strongest dietary triggers for gout flares, more than equivalent purine loads from food.
In the Choi cohort study of alcohol and gout (47,150 men followed for 12 years, 730 new cases), men drinking 50 g or more of alcohol a day had 2.53 times the gout risk of non-drinkers. By type of drink, each daily 12-oz serving of beer raised the risk 1.49-fold and each daily drink of spirits 1.15-fold, while wine (1.04 per daily 4-oz serving) was not significantly associated with gout. The wine-vs-beer difference probably reflects the purine content rather than ethanol per se.
TPN, Infant Formula, and Conditional Essentiality
While adenine is not essential for healthy adults, several clinical populations have elevated nucleotide demand that may exceed endogenous synthetic capacity. The concept is conditional essentiality: a nutrient that is not strictly required under normal physiological conditions becomes required when demand exceeds synthesis under stress.
Premature infants have rapidly growing tissues (especially gut, brain, immune system) and limited de novo purine synthesis capacity in the immature liver. Standard infant formulas have included nucleotide supplementation since the 1990s on this rationale — typically a blend of AMP, GMP, CMP, UMP at concentrations matching the nucleotide content of human breast milk. Trials have shown modest benefits including improved gut maturation, enhanced immune response to vaccination, and reduced diarrhea incidence in formula-fed preterm infants.
Total parenteral nutrition (TPN) patients receive intravenous nutrition because their gut is non-functional (post-bowel resection, gut ischemia, severe pancreatitis, etc.). Standard TPN solutions do not include nucleotides, on the rationale that endogenous synthesis is sufficient. However, several studies have demonstrated that nucleotide supplementation improves gut barrier function, reduces bacterial translocation, and accelerates recovery in critically ill TPN patients.
Critical illness, sepsis, and major trauma dramatically increase tissue purine demand because of accelerated cell turnover in immune system, gut crypts, and wound-healing tissues. Some critical care literature argues for nucleotide supplementation as part of "immunonutrition" protocols, alongside glutamine, arginine, and omega-3 fatty acids. The evidence is mixed.
Specific inborn errors of metabolism — adenosine deaminase deficiency (ADA-SCID), HGPRT deficiency (Lesch-Nyhan), APRT deficiency — each have specific dietary or pharmacologic management. ADA-SCID is typically treated with PEG-ADA enzyme replacement, hematopoietic stem cell transplant, or gene therapy rather than dietary intervention. APRT deficiency is managed with allopurinol (to prevent 2,8-dihydroxyadenine stones) and a low-purine diet. Lesch-Nyhan is managed with allopurinol for hyperuricemia, but the neurological phenotype is unaffected by dietary manipulation.
CPDA-1 Blood Preservation: Adenine as Pharmaceutical
One curious modern application of adenine is in stored blood products. Donated red blood cells stored for transfusion gradually lose adenosine triphosphate through ongoing metabolism in the storage bag, and the depletion of adenosine triphosphate compromises membrane integrity, deformability, and 2,3-bisphosphoglycerate (which regulates hemoglobin oxygen affinity). After several weeks, adenosine triphosphate-depleted red cells become spherocytic, fragile, and poorly functional after transfusion.
The solution, developed in the 1960s and 1970s, was to add adenine to the storage solution. Citrate-Phosphate-Dextrose-Adenine (CPDA-1) is the standard anticoagulant/preservative solution for whole-blood storage in many blood banks. The adenine concentration is roughly 0.25 mM — enough to maintain salvage-pathway flux through APRT, preserving adenosine triphosphate synthesis throughout the 35-day storage life. Without adenine, red cells retain meaningful function for only about 14–21 days; with CPDA-1, the shelf life extends to 35 days.
Additive solutions (AS-1, AS-3, AS-5, SAGM in Europe) used with packed red cells extend the shelf life further (to 42 days) through additional supplementation of mannitol, glucose, and adenine. These additive solutions are the reason modern blood banking can maintain a sufficient inventory of compatible red cell units for elective surgery.
This is one of very few clinical contexts where pure adenine is added to a pharmaceutical product. The dose is small (per the product label, the 70 mL of CPDA-1 used to collect a 500 mL whole blood unit contains 19.3 mg adenine), and the recipient's endogenous purine catabolism handles it without consequence.
European and Russian "Vitamin B4" Supplements
The "Vitamin B4" label persists in several niches of the supplement marketplace, particularly in European, Russian, and Eastern European literature. These commercial preparations typically contain one of three things:
- Adenine itself, marketed for vague "energy" or "anti-fatigue" benefits. There is no controlled evidence that oral adenine supplementation produces any clinical benefit in healthy adults — the body has no shortage of adenine, and supplementation does not increase tissue adenosine triphosphate or nicotinamide adenine dinucleotide (NAD) pools meaningfully.
- Choline, which in some older European pharmacopoeias was assigned the "B4" label before being separated out as its own nutrient. Choline is a genuine essential nutrient (DRI of 425–550 mg/day, European Food Safety Authority Adequate Intake (AI) of 400 mg/day) that supports phosphatidylcholine, acetylcholine, and one-carbon metabolism. If a "Vitamin B4" product is actually choline, it may have nutritional value — but the labeling is misleading.
- Adenosine monophosphate (AMP) or adenosine triphosphate (ATP), marketed for "cellular energy" benefits. Oral adenosine triphosphate is rapidly hydrolyzed in the gut to free adenine, ribose, and phosphate before absorption — the cell membrane of intestinal enterocytes is impermeable to adenosine triphosphate, so the marketing claim of "boosting cellular adenosine triphosphate" by oral adenosine triphosphate supplementation is mechanistically implausible.
None of the major regulatory bodies (U.S. Food and Drug Administration, EFSA, MHRA, Health Canada) recognize adenine as a vitamin or as an essential nutrient. Supplements labeled "Vitamin B4" exist in a legal gray zone and are typically sold under general supplement regulations rather than vitamin-specific frameworks.
The historical fingerprint of the "B4" label is also visible in older medical literature from the 1930s and 1940s, in some Eastern European clinical nutrition writing through the 1980s, and in folk-nutrition discourse that has not kept up with the 1940s reclassification. The term "Vitamin B4" is historical, and no modern nutrition authority sets a requirement for adenine supplementation.
Key Research Papers
- Choi HK et al., purine-rich foods and the risk of gout in men (NEJM 2004) — PubMed PMID: 15014182
- FitzGerald JD, Dalbeth N, Mikuls T, et al. 2020 American College of Rheumatology Guideline for the Management of Gout. Arthritis Care Res (Hoboken) 2020;72(6):744-760 — PubMed PMID: 32391934
- Choi HK and Curhan G, soft drinks, fructose consumption, and the risk of gout — PubMed PMID: 18244959
- Choi HK, alcohol intake and risk of incident gout — PubMed PMID: 15094272
- Carver JD, infant formula nucleotide supplementation and immune function — PubMed PMID: 1861940
- Grimble GK, nucleotides in clinical nutrition and gut function — PubMed: Grimble clinical nucleotides
- Hess JR, CPDA-1 and additive solutions for red cell storage — PubMed: CPDA-1 storage
- Hogman CF, red cell preservation and the role of adenine — PubMed: Hogman red cell adenine
- Kaneko K, total purine and purine base content of foods (Japanese database) — PubMed: Kaneko purine database
- Zeisel SH, choline as the once-misclassified B vitamin, now essential nutrient — PubMed: Zeisel choline
- Reader V. The assay of vitamin B(4). Biochem J 1930;24(6):1827-31 — PubMed PMID: 16744538
- Barnes H, O'brien JR, Reader V. Vitamin B(4). Biochem J 1932;26(6):2035-40 — PubMed PMID: 16745034
- Lecoq R. [Protective action exerted by adenine (vitamin B4 of leukocyte balance) in drug intoxication]. Ann Pharm Fr 1947;5(1):20-7 — PubMed PMID: 20256445
- CPDA-1 (citrate phosphate dextrose adenine) anticoagulant blood-bag system, product label — DailyMed label
- Yamamoto T, hypoxanthine and adenine recycling in human erythrocytes — PubMed: Erythrocyte purine recycling