PABA (Para-Aminobenzoic Acid): The Former Vitamin B10
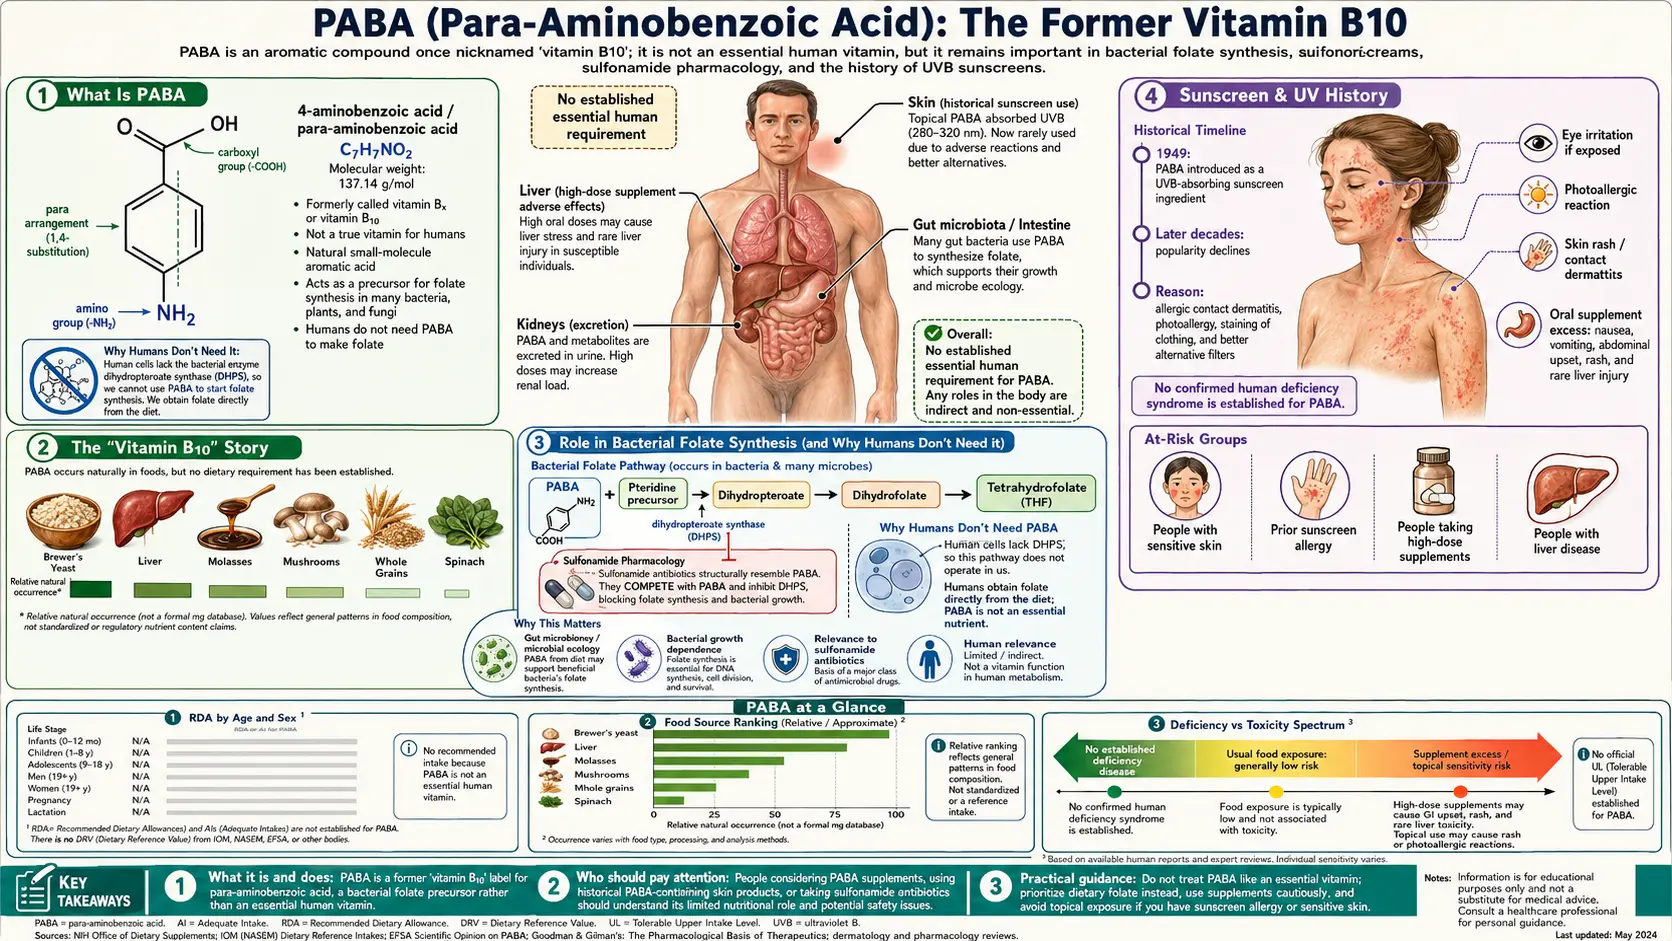
Para-aminobenzoic acid (PABA) is a real organic compound that was once called "vitamin B10" — and, in older literature, "vitamin Bx" and "vitamin H1" — but it is not a vitamin for human beings. No PABA deficiency disease is recognized in humans, and no recommended intake or Daily Value has been set for it. PABA's place in nutrition history is real: it is a building block that many bacteria use to manufacture their own folate, which is exactly why the sulfa antibiotics — drugs that block that bacterial step — work at all. This page separates the genuine, citable science of PABA (its role in microbial folate synthesis, its history as a UVB sunscreen ingredient, and the prescription drug potassium para-aminobenzoate studied for Peyronie's disease and scleroderma) from the folk claims, such as the idea that it restores gray hair, where the evidence is weak or absent.
Table of Contents
- What Is PABA
- The "Vitamin B10" Story
- Role in Bacterial Folate Synthesis
- Sunscreen & UV History
- Peyronie's Disease (Potassium Aminobenzoate Evidence)
- Scleroderma & Skin Fibrosis
- Hair, Skin & Pigment Claims
- Food Sources
- Dosage & Forms
- Safety, Sulfa-Drug Interaction & Cautions
- Key Research Papers
- Connections
- Featured Videos
1. What Is PABA
Para-aminobenzoic acid is a small, simple organic molecule with the formula C7H7NO2: a benzene ring carrying an amino group on one side and a carboxylic acid group directly opposite it (the "para" position). The compound is also called 4-aminobenzoic acid, and it is the structural parent of several well-known chemicals — including the local anesthetics procaine and benzocaine, which are esters of PABA. As a pure substance, PABA is a white-to-pale-tan crystalline powder that dissolves modestly in water and more readily in alcohol.
PABA is not synthesized to any meaningful degree by human tissue, and humans have no biochemical pathway that uses it for an essential purpose. The PABA in the human body comes from outside sources: small amounts in food, and PABA made by gut bacteria as part of their own folate metabolism. Because an oral dose of PABA is absorbed, metabolized and excreted in the urine, a measured dose of PABA has been used in nutrition research as a marker to check whether a 24-hour urine collection was complete — a use that has nothing to do with nutrition and everything to do with PABA's predictable handling by the body (Bingham and Cummings, 1986).
Understanding PABA correctly starts with this distinction: it is a genuine, biologically active chemical, but its biology is overwhelmingly microbial. The reason PABA was ever called a vitamin at all is a story about early-twentieth-century animal experiments — and about how easy it is to confuse a nutrient that an animal's gut bacteria need with a nutrient that the animal itself needs.
2. The "Vitamin B10" Story
In the late 1930s and early 1940s, researchers feeding restricted diets to laboratory animals reported poor growth and graying of dark fur that adding PABA sometimes corrected. On the strength of these animal findings, PABA was argued to be a vitamin — a 1941 note in Science was titled simply "p-Aminobenzoic acid, a vitamin" (Ansbacher, 1941) — and it was given vitamin-style names: "vitamin B10", "vitamin Bx," and, in Italian and other European literature of the 1950s, "vitamin H1." For a time it was grouped with the B-complex and sold as a nutritional factor for skin, hair, and pigment.
The reclassification came once the underlying biochemistry was worked out. The benefit of PABA in those animals was traced not to a human-style vitamin requirement but to PABA's role as a precursor of folate — and, critically, to the fact that the animals' own intestinal bacteria were the parties that needed PABA to make folate. In other words, PABA was acting as a raw material for a folate-synthesizing system that lives in the gut, not as an essential dietary factor for the mammal. Humans obtain folate directly from food (leafy greens, legumes, liver) and cannot make it from PABA at all.
Because of this, modern nutrition science does not classify PABA as a vitamin for humans. No Recommended Dietary Allowance, Adequate Intake, or Tolerable Upper Intake Level has been set for it, and — most tellingly — no human deficiency disease is recognized. Its modern status is that of a non-essential organic compound that is sold as a dietary supplement and, as the salt potassium para-aminobenzoate, as a prescription drug. The name "vitamin B10" on a label or in an older reference is an obsolete name from a research era that has since corrected the record.
3. Role in Bacterial Folate Synthesis (and Why Humans Don't Need It)
PABA's one genuinely important biological job is to serve as a substrate in the folate (vitamin B9) biosynthesis pathway of bacteria, fungi, plants, and some protozoa. In these organisms, an enzyme called dihydropteroate synthase (DHPS) joins PABA to a pteridine intermediate to build dihydropteroate, which is then converted into dihydrofolate and ultimately the active folate coenzymes those cells need to make DNA, RNA, and certain amino acids. Researchers have used radioactively labeled PABA to track folate production in Escherichia coli: the uptake of the label fell when sulfathiazole or trimethoprim was added, showing that the measurement monitored folate biosynthesis (Herrington, 1994).
Humans, and animals generally, lack the DHPS enzyme entirely. We cannot build folate from PABA no matter how much PABA we consume. Instead, humans must take in pre-formed folate from the diet, transport it into cells, and recycle it. This single fact — that the bacterial folate factory exists and the human one does not — is the foundation of one of the most important classes of antibiotics ever developed.
The sulfonamide ("sulfa") antibiotics, such as sulfamethoxazole, are structural look-alikes of PABA. They competitively block dihydropteroate synthase: the bacterium's enzyme tries to use the sulfa drug as though it were PABA, the reaction stalls, and the microbe is starved of the folate it needs to grow. Because human cells do not run this pathway, the drug damages the bacterium while sparing us. This is the textbook example of selective toxicity in pharmacology — and it has a direct consequence for PABA supplements, discussed in the safety section below: extra PABA supplies the enzyme with its natural substrate and can counteract sulfa antibiotics. The antagonism was reported early in the sulfa era; a 1941 report in Science was titled "p-Aminobenzoic acid prevents the growth-inhibitory action of sulfanilamide" (Dimond, 1941).
4. Sunscreen & UV History
One of PABA's most visible real-world uses was in sunscreen. PABA absorbs ultraviolet-B (UVB) radiation — the high-energy band of sunlight most responsible for sunburn — and in the mid-twentieth century it became one of the early widely used chemical sunscreen agents. In a 1984 mouse study, a PABA-containing sunscreen partially reduced some of the systemic immune changes that UVB exposure produced in the animals (Morison, 1984).
PABA was nevertheless phased out of consumer sunscreens. The U.S. Food and Drug Administration's 2019 proposed rule on sunscreens gave the reasons: PABA's use had decreased because of its adverse effects on skin and its discoloring and staining effect on clothing; the clinical record includes significant rates of allergic and photoallergic skin reactions, as well as cross-sensitization with structurally similar compounds; and the agency's survey of sunscreens on sale indicated that PABA was no longer being marketed in the United States. "PABA-free" sunscreens followed the recognition that PABA and its esters caused contact and photocontact allergy, and newer UV filters took its place.
The regulatory record is now settled. In the 2019 proposed rule the FDA proposed that PABA is not generally recognized as safe and effective (GRASE) for use in sunscreens, concluding that its risks in sunscreen products outweigh its benefits. A final administrative order, announced in the Federal Register on September 11, 2026, removed PABA (together with trolamine salicylate) from the U.S. over-the-counter sunscreen monograph; a sunscreen containing PABA is not GRASE. PABA did absorb UVB; its removal rests on skin reactions and staining, not on a failure to absorb UV light. Today PABA is met mainly as an oral supplement or a prescription drug rather than as a sunscreen ingredient.
5. Peyronie's Disease (Potassium Aminobenzoate Evidence)
The best-studied medical use of PABA is its prescription salt form, potassium para-aminobenzoate, which has been studied for fibrotic conditions — disorders in which the body lays down excess scar-like connective tissue. The longest-standing of these is Peyronie's disease, a condition in which a plaque of fibrous tissue forms in the penis, causing curvature, pain, and difficulty with erections. Zarafonetis and Horrax reported treating Peyronie's disease with potassium para-aminobenzoate in 1959, and the drug is still among the oral therapies reviewed for the condition (Hauck et al., 2006).
The evidence is genuine but limited. The main randomized trial, a double-blind, placebo-controlled multicentre study published in European Urology in 2005, enrolled 103 men with Peyronie's disease of less than 12 months' duration and non-calcified plaques, given 3 g four times daily (12 g/day) or placebo for 12 months (Weidner et al., 2005). Mean plaque size fell on the drug (from 259 to 142 mm²) and the difference from placebo was significant; pre-existing curvature did not improve, but it stayed stable on the drug while it worsened significantly in 32.5% of the placebo group; pain fell similarly in both groups (82.6% vs. 77.3%, no significant difference). The authors concluded the drug appears useful to stabilize the disorder and prevent progression of curvature. A 2026 retrospective study from a Turkish university urology department (30 men on potassium para-aminobenzoate, 28 on colchicine, 3 months of treatment) reported that potassium para-aminobenzoate was more effective than colchicine for curvature, pain and plaque calcification, with no difference in plaque size (Kervancioglu et al., 2026). A 2006 review described the efficacy of nonsurgical therapy for Peyronie's disease as controversial (Hauck et al., 2006). In short, the trial evidence points to stabilization in early, active disease rather than reversal of curvature, and the drug is a prescription medicine used under a urologist's care.
6. Scleroderma & Skin Fibrosis
The same anti-fibrotic rationale led to decades of research on potassium para-aminobenzoate in scleroderma (systemic sclerosis), an autoimmune disease in which the skin and sometimes internal organs become progressively hardened by excess collagen. Early proponents proposed anti-fibrotic mechanisms — for example, that PABA might raise tissue monoamine oxidase activity and so affect collagen — but no mechanism has been established. It was an appealing candidate at a time when few effective treatments for scleroderma existed.
The clearest data come from the long work of Zarafonetis and colleagues. In a retrospective analysis of 390 University of Michigan scleroderma patients published in the Journal of Clinical Epidemiology in 1988, adequate treatment with potassium para-aminobenzoate was associated with better survival: 88.5% at 5 years and 76.6% at 10 years, against 69.8% and 56.6% in patients never treated with it. A companion analysis of the same hospital records reported skin softening in 90% of 224 treated patients versus less than 20% of 96 untreated patients (Zarafonetis et al., 1988, Clinical and Experimental Rheumatology). These are meaningful observations — but they come with an important caveat: they are retrospective, not randomized. Patients were not assigned to treatment by chance, so factors other than the drug (such as which patients were healthy enough to tolerate a long course of therapy) could have influenced the results.
Later, better-controlled research tempered the enthusiasm. A 48-week prospective, randomized, double-blind, placebo-controlled trial of 12 g/day in 146 patients with relatively longstanding, stable scleroderma (76 completed) found no clinical or statistically significant difference from placebo in skin mobility, skin thickening or any other outcome measure; 18 patients on the drug and 6 on placebo withdrew because of adverse reactions, mostly gastrointestinal intolerance and headache (Clegg et al., 1994). The summary is that PABA has a real, long-studied history in scleroderma and some suggestive retrospective survival data, but it is not an established, guideline-endorsed treatment, and modern management of systemic sclerosis relies on other agents. As with Peyronie's disease, the research concerns the prescription drug, not over-the-counter supplements.
7. Hair, Skin & Pigment Claims (Weighed Honestly)
The most widely repeated folk claim about PABA is that it can restore color to gray hair or prevent further graying. This idea traces back to the 1930s–40s animal experiments described earlier, in which animals on restricted diets developed gray fur that PABA or other B-factors were reported to correct. Human reports followed quickly — Science carried a 1941 clinical report on achromotrichia (loss of hair color) by Sieve — and from there the claim migrated into supplement folklore under the obsolete "vitamin B10" name.
The evidence in humans is weak and largely anecdotal. Research in mice and in aging human hair follicles links graying to the failure of pigment-producing melanocyte stem cells to maintain themselves in the follicle (Nishimura et al., 2005), and no modern controlled clinical trial has shown that PABA supplements reverse or slow this process. Even in the original animal era, the picture was contested: a 1940 report in Science was titled "Inefficacy of pantothenic acid against the graying of fur," illustrating how unsettled the "anti-graying nutrient" claims were even at their source.
PABA is not an established remedy for gray hair, wrinkles, or skin pigment. Some people take it hoping for these cosmetic effects; the research has not shown a benefit, graying is not known to be caused by a lack of PABA, and high-dose use carries the risks described in the safety section. A promise to reverse gray hair "with vitamin B10" rests on 1940s reports, not current evidence.
8. Food Sources
Because PABA is not an essential nutrient, there is no target intake to "meet" from food, and no recognized deficiency. PABA does occur in small amounts in a variety of foods, partly as part of folate molecules (folate contains a PABA unit). Foods commonly listed as sources include organ meats (especially liver), whole grains, brewer's yeast and nutritional yeast, eggs, mushrooms, and leafy green vegetables such as spinach. Molasses and bran are also sometimes listed.
The gut microbiome is a second source: many intestinal bacteria synthesize PABA as part of their own folate metabolism. Whatever its source, none of it is required for human health, which is why nutrition authorities have set no intake value for dietary PABA.
In short, the human body has no known requirement for PABA from food. Liver, eggs, leafy greens, and whole grains matter nutritionally for their other nutrients — folate, B12, iron, choline, fiber — not for their PABA content.
9. Dosage & Forms
PABA is sold in two very different guises, and the distinction matters. The first is the over-the-counter dietary supplement, sold as powders and capsules and marketed for hair, skin, and general "B-complex" support. There is little credible evidence that supplementation provides a health benefit, because PABA is not an essential nutrient for humans, and there is little formal safety research on supplement-level doses.
The second form is the prescription drug potassium para-aminobenzoate, used for Peyronie's disease and historically for scleroderma. Here the doses are far higher: the randomized trials used 12 grams per day — given as 3 g four times daily in the Peyronie's trial — for 12 months in Peyronie's disease and 48 weeks in scleroderma (Weidner et al., 2005; Clegg et al., 1994). These are pharmaceutical doses prescribed and monitored by a physician. In the scleroderma trial only 52% of patients completed the study, and gastrointestinal intolerance and headache were the most common adverse reactions leading to withdrawal.
No benefit has been shown for high doses taken outside supervised drug therapy for specific diagnoses. Because PABA interacts with prescription medications — most importantly sulfa antibiotics — questions about combining it with other medicines belong with a pharmacist or physician.
10. Safety, Sulfa-Drug Interaction & Cautions
The adverse effects most often reported with PABA are gastrointestinal upset and, less often, skin rash. In the 12 g/day scleroderma trial, gastrointestinal intolerance and headache were the most common reasons for withdrawal, and all adverse reactions resolved after the drug was stopped (Clegg et al., 1994).
At the high gram-level doses used pharmaceutically, the risk profile is more serious. The most important concern is liver injury (hepatotoxicity): case reports describe acute hepatitis and elevated liver enzymes in patients taking potassium para-aminobenzoate, with recovery after the drug was stopped. A 2008 report counted six published cases of acute liver injury linked to the oral drug and described one more, which recovered fully four months after discontinuation (Roy and Carrier, 2008); further cases have been reported since. A 1986 review of 390 scleroderma patients' records, by contrast, found no case in which the drug caused an acute hepatic reaction and concluded that such reactions are uncommon if not rare (Zarafonetis et al., 1986). Case reports also describe DRESS syndrome (a severe drug reaction with rash, fever and internal-organ involvement) with potassium para-aminobenzoate (Viehweg et al., 2013).
The single most clinically important interaction is with sulfonamide ("sulfa") antibiotics. Because sulfa drugs kill bacteria by blocking the bacterial enzyme that uses PABA to build folate, taking supplemental PABA can directly antagonize and weaken these antibiotics — supplying the enzyme with the very substrate the drug is trying to withhold. The concern applies to anyone taking a sulfa antibiotic (for example, sulfamethoxazole–trimethoprim). In summary: no health benefit has been shown for PABA supplements in healthy people; high-dose PABA is a prescription drug with documented liver and skin reactions; and PABA works directly against sulfa drugs.
Key Research Papers
- Zarafonetis, C.J.D., and Horrax, T.M. "Treatment of Peyronie's Disease with Potassium Para-Aminobenzoate (Potaba)." Journal of Urology, vol. 81, no. 6, 1959, pp. 770-772. — doi:10.1016/S0022-5347(17)66108-1
- Zarafonetis, C.J., Dabich, L., Negri, D., Skovronski, J.J., DeVol, E.B., and Wolfe, R. "Retrospective Studies in Scleroderma: Effect of Potassium Para-Aminobenzoate on Survival." Journal of Clinical Epidemiology, vol. 41, no. 2, 1988, pp. 193-205. — doi:10.1016/0895-4356(88)90094-7
- Kervancioglu, E., Goren, M.R., Ozer, C., Hasirci, E., Erbay, G., and Kayra, M.V. "Comparison of the Effectiveness of Potassium Para-aminobenzoate and Colchicine in the Treatment of Peyronie Disease: A Retrospective Study." Nigerian Journal of Clinical Practice, vol. 29, no. 4, 2026, pp. 454-458. — doi:10.4103/njcp.njcp_11_26; PubMed PMID: 42085088
- Weidner, W., Hauck, E.W., Schnitker, J.; Peyronie's Disease Study Group of Andrological Group of German Urologists. "Potassium Paraaminobenzoate (POTABA) in the Treatment of Peyronie's Disease: A Prospective, Placebo-Controlled, Randomized Study." European Urology, vol. 47, no. 4, 2005, pp. 530-535. — PubMed PMID: 15774254
- Dimond, N.S. "P-Aminobenzoic Acid Prevents the Growth-Inhibitory Action of Sulfanilamide." Science, vol. 94, no. 2444, 1941, pp. 420-421. — doi:10.1126/science.94.2444.420
- Herrington, M.B. "Measurement of the Uptake of Radioactive para-Aminobenzoic Acid Monitors Folate Biosynthesis in Escherichia coli K-12." Analytical Biochemistry, vol. 216, no. 2, 1994, pp. 427-430. — doi:10.1006/abio.1994.1063
- Morison, W.L. "The Effect of a Sunscreen Containing Para-Aminobenzoic Acid on the Systemic Immunologic Alterations Induced in Mice by Exposure to UVB Radiation." Journal of Investigative Dermatology, vol. 83, no. 6, 1984, pp. 405-408. — doi:10.1111/1523-1747.ep12273470
- Williams, R.R. "Inefficacy of Pantothenic Acid Against the Graying of Fur." Science, vol. 92, no. 2398, 1940, pp. 561-562. — doi:10.1126/science.92.2398.561-b
- "Potassium-Aminobenzoate: Hepatotoxicity — Case Report." Reactions Weekly, vol. 1946, 2023, p. 470. — doi:10.1007/s40278-023-35071-4
- Clegg, D.O., Reading, J.C., Mayes, M.D., Seibold, J.R., Harris, C., Wigley, F.M., Ward, J.R., Pisko, E.J., Weisman, M.H., Lee, P., et al. "Comparison of Aminobenzoate Potassium and Placebo in the Treatment of Scleroderma." Journal of Rheumatology, vol. 21, no. 1, 1994, pp. 105-110. — PubMed PMID: 8151563
- Zarafonetis, C.J., Dabich, L., Skovronski, J.J., DeVol, E.B., Negri, D., Yuan, W., and Wolfe, R. "Retrospective Studies in Scleroderma: Skin Response to Potassium Para-Aminobenzoate Therapy." Clinical and Experimental Rheumatology, vol. 6, no. 3, 1988, pp. 261-268. — PubMed PMID: 3180546
- Hauck, E.W., Diemer, T., Schmelz, H.U., and Weidner, W. "A Critical Analysis of Nonsurgical Treatment of Peyronie's Disease." European Urology, vol. 49, no. 6, 2006, pp. 987-997. — PubMed PMID: 16698449
- Roy, J., and Carrier, S. "Acute Hepatitis Associated with Treatment of Peyronie's Disease with Potassium Para-Aminobenzoate (Potaba)." Journal of Sexual Medicine, vol. 5, no. 12, 2008, pp. 2967-2969. — PubMed PMID: 18624965
- Zarafonetis, C.J., Dabich, L., DeVol, E.B., Rossi, C., and Skovronski, J.J. "Potassium Para-Aminobenzoate and Liver Function Test Findings." Journal of the American Academy of Dermatology, vol. 15, no. 1, 1986, pp. 144-149. — PubMed PMID: 3487559
- Viehweg, A., Stein, A., Bauer, A., and Spornraft-Ragaller, P. "Potassium-Paraaminobenzoic Acid (Potaba®)-Associated DRESS Syndrome." Dermatitis, vol. 24, no. 5, 2013, pp. 257-258. — PubMed PMID: 24045650
- Bingham, S.A., and Cummings, J.H. "Creatinine and PABA as Markers for Completeness of Collection of 24-Hour Urine Samples." Human Nutrition: Clinical Nutrition, vol. 40, no. 6, 1986, pp. 473-476. — PubMed PMID: 3491811
- Ansbacher, S. "p-Aminobenzoic Acid, a Vitamin." Science, vol. 93, no. 2407, 1941, pp. 164-165. — PubMed PMID: 17743450
- Sieve, B.F. "Clinical Achromotrichia." Science, vol. 94, no. 2437, 1941, pp. 257-258. — PubMed PMID: 17792884
- Nishimura, E.K., Granter, S.R., and Fisher, D.E. "Mechanisms of Hair Graying: Incomplete Melanocyte Stem Cell Maintenance in the Niche." Science, vol. 307, no. 5710, 2005, pp. 720-724. — PubMed PMID: 15618488
- U.S. Food and Drug Administration. "Sunscreen Drug Products for Over-the-Counter Human Use" (proposed rule). Federal Register, vol. 84, 2019, p. 6204. — 84 FR 6204
- U.S. Food and Drug Administration. "Amending Over-the-Counter Monograph M020: Sunscreen Drug Products for Over-the-Counter Human Use, and Related Information; Aminobenzoic Acid (PABA) and Trolamine Salicylate" (notice of availability of final order OTC000008-1). Federal Register, vol. 91, 2026, p. 57892. — 91 FR 57892
PubMed Topic Searches
- PubMed: Potassium para-aminobenzoate in Peyronie's disease
- PubMed: Potassium aminobenzoate in scleroderma trials
- PubMed: PABA, folate biosynthesis and sulfonamides
- PubMed: PABA sunscreen contact dermatitis and photosensitivity