Vitamin A and Vision Health
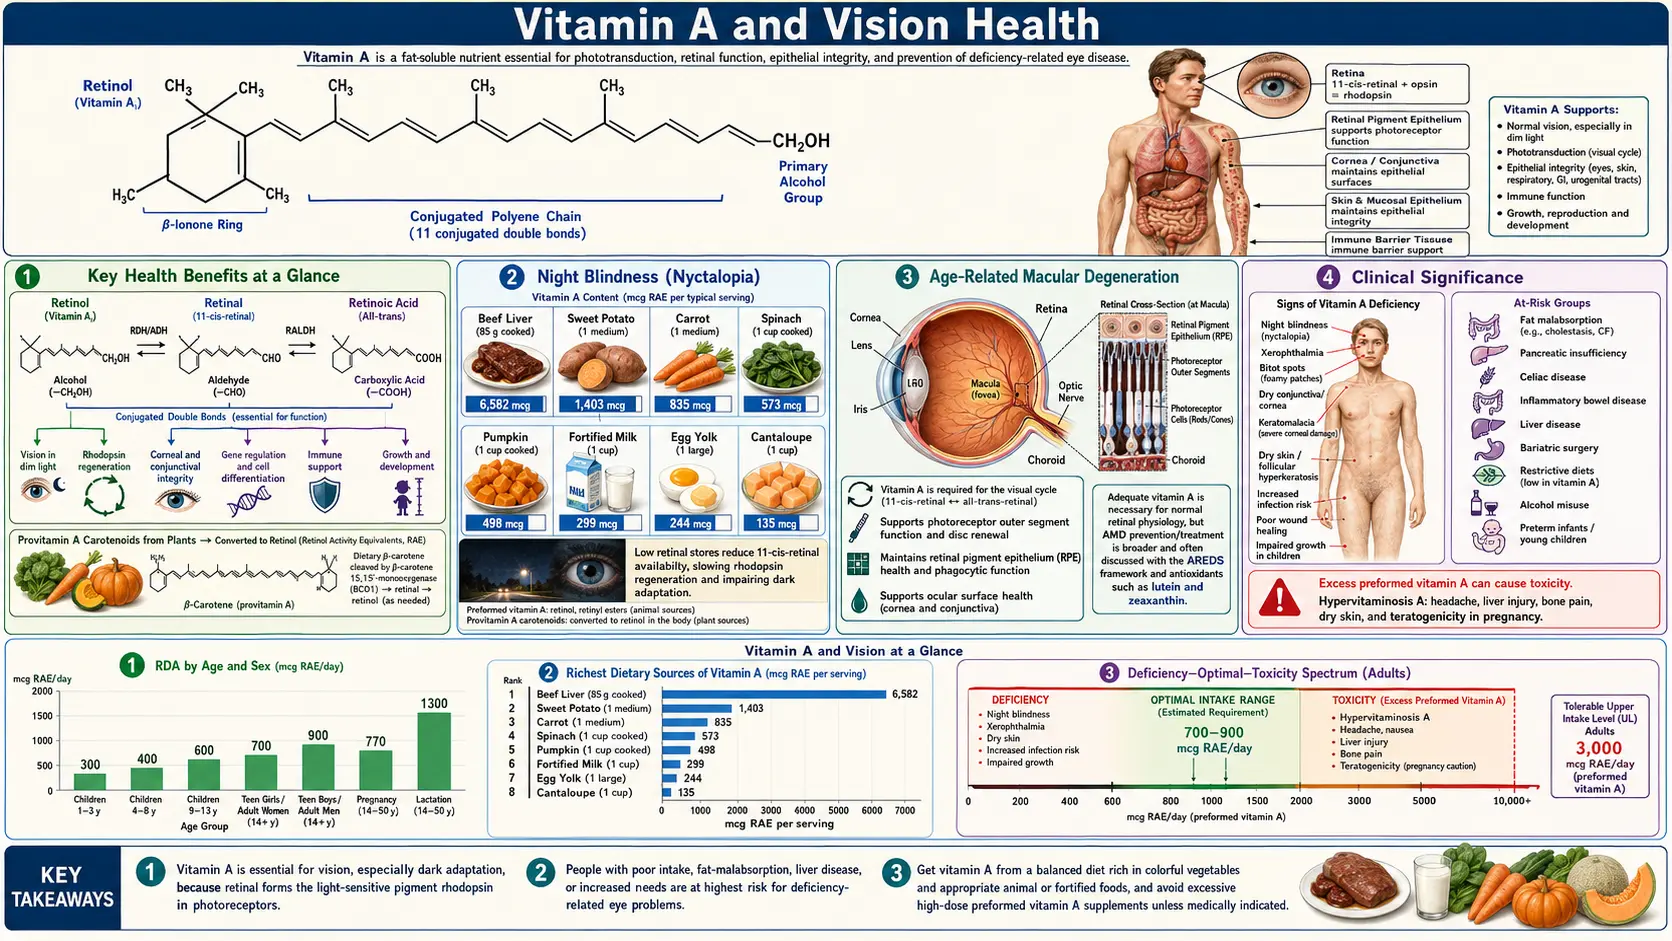
Vitamin A is arguably the single most important micronutrient for maintaining healthy eyesight. Its role in vision was among the earliest nutritional functions ever characterized, and deficiency of this fat-soluble vitamin remains the leading preventable cause of childhood blindness worldwide — affecting an estimated 190 million preschool-age children. From the quantum-level chemistry of 11-cis-retinal in rod photoreceptors, to the macular pigment built from lutein and zeaxanthin, to the retinal pigment epithelium that recycles vitamin A every day, healthy vision depends on a steady supply of this vitamin. Understanding how vitamin A participates in the visual cycle, supports retinal cell integrity, and protects against degenerative eye diseases is essential for both clinicians and patients.
Table of Contents
- Key Health Benefits at a Glance
- Rhodopsin and the Visual Cycle
- Rod and Cone Cell Function
- Night Blindness (Nyctalopia)
- Xerophthalmia and Corneal Damage
- Age-Related Macular Degeneration
- Retinal Health and Maintenance
- Beta-Carotene Conversion
- Clinical Significance
- Key Research Papers
- Connections
- Featured Videos
Key Health Benefits at a Glance
The following is a high-level summary of the evidence-backed vision benefits of adequate vitamin A status. Each is explored in more depth below, and the sources, individual papers and PubMed topic searches, are listed in the Key Research Papers section.
- Powers the visual cycle – 11-cis-retinal, the chromophore of rhodopsin, is derived from vitamin A; without it, rod cells cannot generate the signal cascade that underlies dim-light vision.
- Night blindness from deficiency – Early-stage nyctalopia from vitamin A deficiency typically reverses within days to weeks of supplementation, a dramatic, measurable clinical response.
- Xerophthalmia and keratomalacia – World Health Organization-classified X1A–X3 stages of corneal and conjunctival disease are directly driven by deficiency; Sommer’s field studies established this as the leading cause of preventable childhood blindness.
- Childhood blindness and mortality – In a 2022 Cochrane review of 19 trials and 1,202,382 children aged six months to five years, vitamin A supplementation reduced all-cause mortality by 12% (risk ratio 0.88, 95% confidence interval 0.83 to 0.93), alongside prevention of Bitot’s spots, corneal ulcer, and keratomalacia.
- Supports macular pigment – Lutein and zeaxanthin, xanthophyll relatives of vitamin A, accumulate in the macula, filter blue light, and protect photoreceptors from photo-oxidative stress (AREDS2).
- Age-related macular degeneration (AMD) progression – AREDS and AREDS2 formulations (antioxidants, zinc, lutein/zeaxanthin) cut progression to advanced age-related macular degeneration by ~25% in patients with intermediate disease; in AREDS the significant result belonged to antioxidants plus zinc (details below).
- Maintains photoreceptor outer segments – Rod and cone disc membranes turn over about 10% per day; vitamin A sustains pigment resynthesis and disc renewal.
- Supports retinal gene expression – Retinoic acid acts via RAR/RXR nuclear receptors to regulate genes for photoreceptor differentiation, RPE health, and retinal development.
- Converts from plant carotenoids, at a variable rate – Beta-carotene yields retinol (12:1 RAE ratio on average, and reported to be highly variable in up to 45% of healthy individuals), offering a non-teratogenic food route to vitamin A sufficiency in pregnancy. High-dose beta-carotene pills are a separate matter: they raised lung cancer in a trial of male smokers (18% with 20 mg a day) and in the eye trials described below.
Rhodopsin and the Visual Cycle
The ability to see in dim light depends on a light-sensitive pigment called rhodopsin, which is found in the rod cells of the retina. Rhodopsin is composed of a protein called opsin bound to a chromophore derived from vitamin A known as 11-cis-retinal. When a photon of light strikes rhodopsin, 11-cis-retinal undergoes a conformational change to all-trans-retinal, triggering a cascade of biochemical signals that the brain interprets as vision.
After light absorption, all-trans-retinal must be recycled back to 11-cis-retinal through a series of enzymatic reactions collectively known as the visual cycle or retinoid cycle. This process takes place in the retinal pigment epithelium (RPE), a layer of cells directly behind the photoreceptors. Key enzymes in this pathway include retinol dehydrogenase, lecithin retinol acyltransferase (LRAT), and RPE65 isomerohydrolase. Without an adequate supply of vitamin A, regeneration of 11-cis-retinal is impaired, and visual sensitivity progressively declines.
Rod and Cone Cell Function
The human retina contains two classes of photoreceptor cells, each with distinct roles in vision:
- Rod cells – Approximately 120 million rod cells are distributed across the peripheral retina. They are exquisitely sensitive to light and mediate scotopic (low-light) vision. Rods contain rhodopsin and are responsible for detecting motion, shapes, and shades of grey in dim environments. They are the first photoreceptors affected by vitamin A deficiency.
- Cone cells – Roughly 6 million cone cells are concentrated in the macula, particularly the fovea. They require higher light intensity and are responsible for photopic (daylight) vision, color perception, and fine visual acuity. Cones use related visual pigments called photopsins (iodopsins), which also require retinal as a chromophore.
Both rod and cone photoreceptors depend on a continuous supply of vitamin A to maintain their outer segment disc membranes, where visual pigments are densely packed. The outer segments undergo constant renewal, with approximately 10% of the disc membrane being shed and replaced daily.
Night Blindness (Nyctalopia)
Night blindness, or nyctalopia, is typically the earliest clinical manifestation of vitamin A deficiency. Patients report difficulty seeing in dim light, problems with dark adaptation after exposure to bright light, and impaired ability to drive at night. The underlying mechanism is a reduction in rhodopsin concentration in rod cells due to insufficient 11-cis-retinal availability.
Key clinical features of nyctalopia include:
- Delayed dark adaptation – The time required for the eyes to adjust from bright to dim conditions is significantly prolonged, often exceeding 30 minutes.
- Elevated scotopic threshold – Electroretinography (ERG) reveals reduced rod-mediated responses, with elevated thresholds for detecting dim flashes of light.
- Reversibility – In early stages, night blindness responds rapidly to vitamin A supplementation, with measurable improvement in dark adaptation within days to weeks.
- Historical significance – Ancient Egyptian medical papyri described treating night blindness with liver consumption, an approach that unknowingly provided concentrated vitamin A.
Xerophthalmia and Corneal Damage
Xerophthalmia is the clinical spectrum of ocular disease caused by vitamin A deficiency, ranging from mild conjunctival drying to complete corneal destruction. The World Health Organization (WHO) classifies xerophthalmia into progressive stages:
- Conjunctival xerosis (X1A) – The conjunctiva loses its normal moist, glistening appearance and becomes dry, thickened, and wrinkled. Goblet cells, which produce the mucin layer of the tear film, are lost due to squamous metaplasia of the epithelium.
- Bitot’s spots (X1B) – Foamy, triangular, white or silvery plaques appear on the bulbar conjunctiva, typically in the temporal interpalpebral zone. These deposits consist of keratinized epithelial debris and commensal bacteria (often Corynebacterium xerosis). Bitot’s spots are a hallmark clinical sign of vitamin A deficiency.
- Corneal xerosis (X2) – The corneal epithelium becomes dry, hazy, and irregular. Punctate keratopathy may develop, and the corneal surface loses its protective tear film coverage.
- Corneal ulceration and keratomalacia (X3) – In severe deficiency, the cornea undergoes liquefactive necrosis (keratomalacia). This devastating condition can progress rapidly from a small corneal ulcer to full-thickness stromal melting and perforation, often resulting in permanent blindness.
Age-Related Macular Degeneration
Age-related macular degeneration (AMD) is the leading cause of irreversible vision loss in adults over 50 in developed countries. While age-related macular degeneration is a multifactorial disease involving genetic, vascular, and inflammatory components, nutritional status plays a significant role in disease progression.
Vitamin A and its carotenoid precursors have been studied extensively in relation to age-related macular degeneration:
- Lutein and zeaxanthin – These xanthophyll carotenoids (structurally related to vitamin A precursors) accumulate in the macula, where they form macular pigment. They filter damaging blue light and act as antioxidants, protecting photoreceptors and RPE cells from photo-oxidative stress.
- AREDS and AREDS2 studies – The Age-Related Eye Disease Study (AREDS) tested high-dose vitamins C and E, beta-carotene and zinc. Antioxidants plus zinc reduced the odds of advanced age-related macular degeneration by approximately 25% (odds ratio 0.72, 99% confidence interval 0.52 to 0.98), while antioxidants alone did not reach significance (0.80, 0.59 to 1.09). In the Age-Related Eye Disease Study 2 (AREDS2), which later replaced beta-carotene with lutein and zeaxanthin, adding lutein and zeaxanthin to the formula did not further reduce risk in the primary analysis (hazard ratio 0.90, P = .12).
- Why beta-carotene left the formula – AREDS2 recorded more lung cancers with beta-carotene than without it (23 cases, 2.0%, against 11, 0.9%), mostly in former smokers, and removing it had no apparent effect on progression to advanced disease. At ten years, people assigned to beta-carotene had an odds ratio of 1.82 for lung cancer (95% confidence interval 1.06 to 3.12), and lutein and zeaxanthin compared directly with beta-carotene had a hazard ratio of 0.85 (0.73 to 0.98) for late disease.
- RPE cell health – The retinal pigment epithelium depends on vitamin A metabolism for phagocytosis of shed photoreceptor outer segments, visual cycle support, and maintenance of Bruch’s membrane. Dysfunction of these processes contributes to drusen formation and RPE atrophy.
Retinal Health and Maintenance
Beyond its direct role in phototransduction, vitamin A supports overall retinal health through several mechanisms:
- Photoreceptor outer segment renewal – Rod and cone outer segments undergo continuous turnover. Vitamin A is required for the synthesis of new disc membranes and the proper folding and insertion of visual pigment molecules.
- Interphotoreceptor retinoid-binding protein (IRBP) – This carrier protein shuttles retinoids between photoreceptors and the RPE through the subretinal space. Adequate vitamin A status ensures efficient IRBP-mediated transport.
- Gene expression regulation – Retinoic acid, derived from vitamin A, acts as a transcription factor ligand via retinoic acid receptors (RARs) and retinoid X receptors (RXRs). These receptors regulate genes involved in retinal development, photoreceptor differentiation, and cellular survival.
- Antioxidant protection – Retinal tissues are highly susceptible to oxidative damage due to constant light exposure and high metabolic activity. Carotenoid forms of vitamin A contribute to the retina’s antioxidant defense system.
Beta-Carotene Conversion
Beta-carotene is the most important provitamin A carotenoid in the human diet. It is converted to retinal by the enzyme beta-carotene 15,15′-dioxygenase (BCMO1/BCO1), primarily in the intestinal mucosa. Several factors influence the efficiency of this conversion:
- Conversion ratio – The current estimate is that 12 micrograms of dietary beta-carotene yields approximately 1 microgram of retinol activity equivalent (RAE). This ratio varies considerably among individuals.
- Genetic polymorphisms – Variants in the BCMO1 gene can reduce conversion efficiency by 30–70%. Individuals carrying these polymorphisms may be poor converters and more dependent on preformed vitamin A sources. The numbers come from a study of two common variants, carried at allele frequencies of 42% and 24%: in female volunteers, carriers of the 379V variant had 32% lower, and carriers of 267S + 379V 69% lower, markers of conversion after a large dose of beta-carotene, and in the laboratory the double-variant enzyme lost 57% of its activity.
- Dietary fat – Beta-carotene is fat-soluble and requires co-ingestion of dietary fat (at least 3–5 grams per meal) for adequate absorption from the gut.
- Food matrix effects – Beta-carotene from raw vegetables is less bioavailable than from cooked or processed foods, as cooking disrupts plant cell walls and releases carotenoids from their protein-lipid complexes.
Clinical Significance
Vitamin A deficiency remains a major global health problem, affecting an estimated 190 million preschool-age children and 19 million pregnant women worldwide, predominantly in South and Southeast Asia and sub-Saharan Africa. Clinical considerations include:
- World Health Organization supplementation programs – These use high-dose vitamin A (200,000 international units (IU) for children over 12 months). The 2022 Cochrane review, which covered children living in the community and excluded those in hospital or with disease or infection, found 12% lower all-cause mortality (risk ratio 0.88) and 12% fewer deaths from diarrhea (0.88, 95% confidence interval 0.79 to 0.98). For measles deaths it found no evidence of a difference (0.88, 0.69 to 1.11; low certainty), although fewer children caught measles (0.45; two studies).
- Eye signs and side effects in those trials – The same review reports less night blindness (risk ratio 0.32) and fewer Bitot’s spots (0.42), and more vomiting within the first 48 hours of a dose (1.97).
- Pregnancy and teratogenicity – While deficiency poses risks to maternal and fetal health, excessive preformed vitamin A intake (above 10,000 international units/day) during pregnancy is teratogenic, potentially causing craniofacial, cardiac, and neural tube defects. Beta-carotene supplementation does not carry this risk.
- Assessment of status – Serum retinol levels below 0.70 micromol/L indicate deficiency. The modified relative dose response (MRDR) test and retinol isotope dilution assays provide more accurate assessments of hepatic vitamin A stores.
- Therapeutic applications – Beyond deficiency treatment, vitamin A derivatives (retinoids) are used therapeutically in dermatology (isotretinoin for acne, tretinoin for photoaging) and oncology (all-trans retinoic acid for acute promyelocytic leukemia).
Maintaining adequate vitamin A status through a balanced diet containing both preformed vitamin A (liver, dairy, eggs) and provitamin A carotenoids (orange and dark green vegetables, fruits) is fundamental to preserving lifelong vision health. Early identification of people at risk of deficiency and supplementation programs remain a cornerstone of public health efforts to prevent avoidable blindness.
Key Research Papers
The following are landmark and frequently cited research papers underpinning the claims on this page. Links resolve to the publisher DOI, the PubMed record, or a PubMed topic search.
Foundational Reviews and Historical Overviews
- Sommer A. Vitamin A deficiency and clinical disease: an historical overview. J Nutr. 2008;138(10):1835-1839. — doi:10.1093/jn/138.10.1835
- Stephensen CB. Vitamin A, infection, and immune function. Annu Rev Nutr. 2001;21:167-192. — PubMed PMID: 11375434
Visual Cycle and Rhodopsin Chemistry
Xerophthalmia, Childhood Blindness, and Supplementation
- Imdad A, Mayo-Wilson E, Haykal MR, Regan A, Sidhu J, Smith A, Bhutta ZA. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022;3(3):CD008524. — PubMed PMID: 35294044
- PubMed: Xerophthalmia WHO classification and field studies
- PubMed: Vitamin A supplementation and child mortality meta-analyses
- PubMed: Vitamin A and measles mortality RCTs
Age-Related Macular Degeneration (AREDS / AREDS2)
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss: AREDS report no. 8. Arch Ophthalmol. 2001;119(10):1417-1436. — PubMed PMID: 11594942
- Age-Related Eye Disease Study 2 Research Group. Lutein + zeaxanthin and omega-3 fatty acids for age-related macular degeneration: the Age-Related Eye Disease Study 2 (AREDS2) randomized clinical trial. JAMA. 2013;309(19):2005-2015. — PubMed PMID: 23644932
- Chew EY, Clemons TE, Agrón E, Domalpally A, Keenan TDL, Vitale S, Weber C, Smith DC, Christen W; AREDS2 Research Group. Long-term outcomes of adding lutein/zeaxanthin and ω-3 fatty acids to the AREDS supplements on age-related macular degeneration progression: AREDS2 report 28. JAMA Ophthalmol. 2022;140(7):692-698. — PubMed PMID: 35653117
- PubMed: AREDS trial results
- PubMed: AREDS2 lutein and zeaxanthin trial
Beta-Carotene Conversion and Genetics
- Leung WC, Hessel S, Méplan C, Flint J, Oberhauser V, Tourniaire F, Hesketh JE, von Lintig J, Lietz G. Two common single nucleotide polymorphisms in the gene encoding beta-carotene 15,15'-monoxygenase alter beta-carotene metabolism in female volunteers. FASEB J. 2009;23(4):1041-1053. — PubMed PMID: 19103647
- Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med. 1994;330(15):1029-1035. — PubMed PMID: 8127329
- PubMed: BCMO1 polymorphisms and beta-carotene conversion
Pregnancy and Teratogenicity
- Rothman KJ, Moore LL, Singer MR, Nguyen US, Mannino S, Milunsky A. Teratogenicity of high vitamin A intake. N Engl J Med. 1995;333(21):1369-1373. — PubMed PMID: 7477116
External Authoritative Resources
- NIH Office of Dietary Supplements — Vitamin A Fact Sheet for Health Professionals
- Linus Pauling Institute Micronutrient Information Center — Vitamin A
- Harvard T.H. Chan School — Nutrition Source: Vitamin A
- WHO — Vitamin A deficiency (Nutrition Landscape Information System)
- PubMed — Vitamin A and vision research