⚠ Evidence warning: Clinical trials or other evidence do not support the claims that glyphosate residue in non-organic grain is linked to gastrointestinal disease, that removing triggers while taking bone broth and glutamine produces dramatic improvement within weeks, and that nightshade alkaloids drive gut and joint symptoms. This page keeps it as a report of what people, websites or other media say.
Avoiding Triggers for Gut Healing
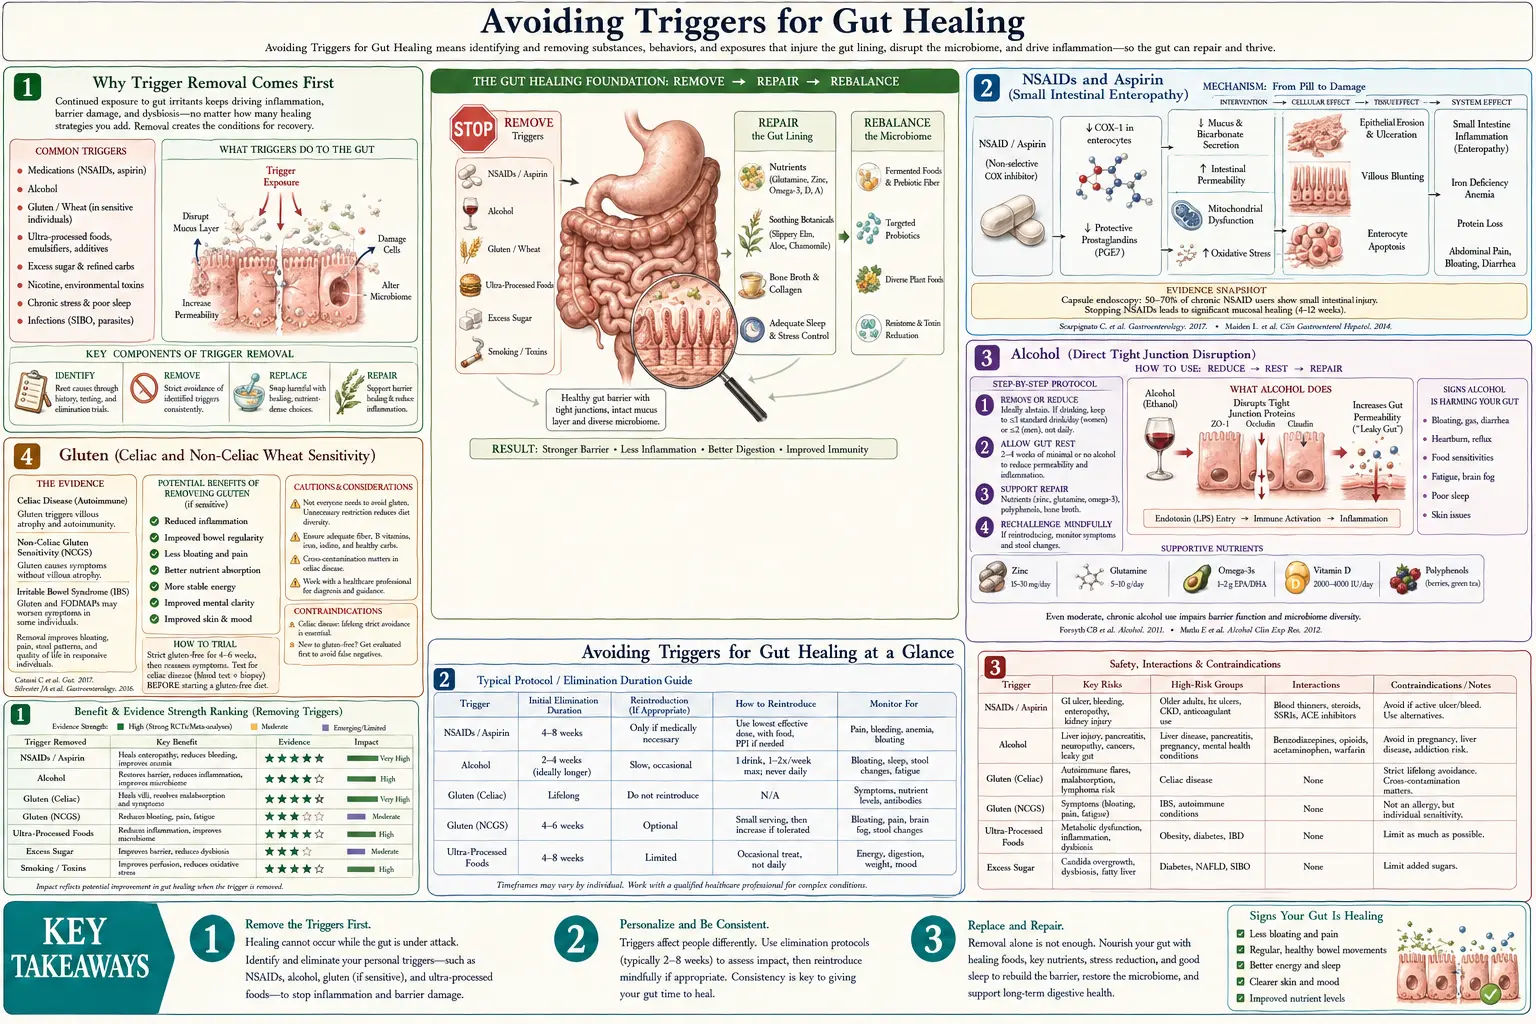
The single most overlooked aspect of gut healing is the recognition that you cannot heal a tissue that is being continuously re-injured. The intestinal epithelium turns over every 3-5 days — remarkable regenerative capacity that is largely wasted if the same daily insults are still present. Nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, aspirin) damage the small intestinal mucosa in approximately 70% of chronic users on capsule endoscopy studies. Alcohol directly disrupts tight junctions within hours of ingestion. Gluten in celiac patients, and in non-celiac wheat-sensitive patients, increases zonulin and degrades barrier integrity. Chronic psychological stress raises corticotropin-releasing factor and activates mucosal mast cells, opening tight junctions and amplifying inflammation. Glyphosate residue in non-organic grain and soy, while controversial in mechanism, correlates with multiple gastrointestinal disease incidence patterns. This deep-dive walks through the major modifiable triggers, the practical work of identifying which apply to you (food and symptom diary, lactulose-mannitol permeability testing, breath testing for small intestinal bacterial overgrowth (SIBO)), and a structured elimination-and-reintroduction protocol that systematically isolates individual triggers.
Table of Contents
- Why Trigger Removal Comes First
- Nonsteroidal Anti-Inflammatory Drugs and Aspirin (Small Intestinal Enteropathy)
- Alcohol (Direct Tight Junction Disruption)
- Gluten (Celiac and Non-Celiac Wheat Sensitivity)
- Glyphosate Residue (The Controversial Trigger)
- Chronic Psychological Stress (CRF and Mast Cells)
- Chronic Infection (H. pylori, Small Intestinal Bacterial Overgrowth, Parasites)
- Individual Food Sensitivities (Beyond Gluten)
- Identification Protocol (Diary, Testing, Elimination)
- Structured Elimination and Reintroduction
- Key Research Papers
- Connections
- Featured Videos
Why Trigger Removal Comes First
The cellular biology of intestinal epithelial regeneration is remarkable. Stem cells at the base of the intestinal crypts (the small pits between the villi) divide approximately every 24 hours, producing progenitor cells that migrate up the villus axis, mature into functional enterocytes, perform their absorptive and barrier functions for 3-5 days, and then are shed at the villus tip into the lumen. The entire epithelial surface is replaced approximately twice per week. This is faster turnover than any other tissue in the body except the bone marrow and certain hair follicles.
This regenerative capacity means that the gut can heal from substantial damage very quickly — if the damaging input is removed. Nonsteroidal anti-inflammatory drug (NSAID)-induced gastropathy resolves within weeks of nonsteroidal anti-inflammatory drug discontinuation. Alcoholic gut permeability normalizes within months of abstinence in most patients. Celiac mucosal villous atrophy reverses, often completely, on strict gluten-free diet over 6-24 months. The constraint on gut healing is not regenerative capacity. The constraint is the rate of ongoing injury relative to the rate of regeneration.
This is why trigger identification and removal logically comes first in any gut-healing protocol. Substrate provision (bone broth, glutamine) and microbial support (probiotics, fermented foods) accelerate the rate of repair, but if the daily damaging input continues, even maximally optimized regeneration will not catch up. Gut-healing practitioners describe the patient who continues to take ibuprofen three times daily for joint pain while taking 15 grams of L-glutamine and drinking bone broth as seeing modest if any improvement, and report dramatic improvement within weeks once the ibuprofen is stopped and the supportive nutrition continues.
Nonsteroidal Anti-Inflammatory Drugs and Aspirin (Small Intestinal Enteropathy)
Non-steroidal anti-inflammatory drugs (ibuprofen, naproxen, diclofenac, ketorolac, indomethacin, meloxicam, celecoxib) are the most underappreciated chronic gut injury source in the United States. Approximately 30 million Americans take a nonsteroidal anti-inflammatory drug daily, mostly for chronic musculoskeletal pain, headache, or cardioprotection (low-dose aspirin). The well-known upper-GI risks — gastric ulcer, duodenal ulcer, gastrointestinal (GI) bleeding — are clinically obvious and managed with proton pump inhibitor (PPI) co-prescription. The less-known and equally important risk is small intestinal enteropathy, which proton pump inhibitors do not prevent (and may worsen via altered microbiome).
The mechanism is two-fold: (1) nonsteroidal anti-inflammatory drugs (NSAIDs) inhibit cyclooxygenase-1 (COX-1), reducing prostaglandin-mediated mucus secretion and bicarbonate production that protect mucosa, and (2) nonsteroidal anti-inflammatory drugs uncouple mitochondrial oxidative phosphorylation in enterocytes, producing adenosine triphosphate (ATP) depletion and direct epithelial injury. The combination opens tight junctions, allows enteric bacteria and bile acids to penetrate, and produces a characteristic "diaphragm-like" stricturing in chronic users that is visible on capsule endoscopy.
In a 2005 capsule endoscopy study by Graham and colleagues, small-bowel injury (red spots, erosions or ulcers) was seen in 71% of 21 people who had taken a nonsteroidal anti-inflammatory drug daily for more than 3 months, compared with 10% of 20 people who took acetaminophen or nothing. In a 2005 study from Bjarnason's group, 27 of 40 healthy volunteers (68%) developed new small-bowel lesions after only 2 weeks of slow-release diclofenac 75 mg twice a day, even though they also took the acid blocker omeprazole, and 75% had a raised fecal calprotectin (a stool marker of gut inflammation). Most such injuries are clinically silent; a subset present with iron-deficiency anemia, occult gastrointestinal blood loss, hypoalbuminemia (from protein-losing enteropathy), or rarely with stricture-related obstruction.
Points that come up for people pursuing gut healing:
- Gut-healing practitioners commonly list dropping unnecessary nonsteroidal anti-inflammatory drug use as the first step — including over-the-counter (OTC) ibuprofen for general aches, post-exercise inflammation, and "as-needed" pain
- Alternatives used for chronic pain conditions include acetaminophen (different mechanism, no nonsteroidal anti-inflammatory drug-style gut injury), topical nonsteroidal anti-inflammatory drugs (much less systemic absorption), gabapentinoids, low-dose naltrexone for pain, physical therapy, weight loss for joint pain
- For low-dose aspirin taken to protect the heart, the trade-off is heart protection against gut injury and bleeding. For adults with no known heart disease or stroke (primary prevention), the 2022 U.S. Preventive Services Task Force (USPSTF) statement says the decision to start low-dose aspirin at ages 40 to 59 with a 10% or greater 10-year cardiovascular risk "should be an individual one", because the net benefit is small (grade C), and it recommends against starting low-dose aspirin for primary prevention at age 60 or older (grade D). The statement does not cover people who have already had a heart attack or stroke
- If nonsteroidal anti-inflammatory drug use is medically necessary, co-prescription of rebamipide (available in Japan, not US), misoprostol, or proton pump inhibitor provides some upper-GI protection but does not prevent small intestinal damage
- Practitioners use bone broth, glutamine, and Lactobacillus rhamnosus GG as adjuncts during nonsteroidal anti-inflammatory drug withdrawal and gut repair, but cannot fully compensate for ongoing nonsteroidal anti-inflammatory drug exposure
Alcohol (Direct Tight Junction Disruption)
Alcohol effects on the gut are immediate and dose-dependent. Single-dose studies in human volunteers show that 0.5-1 g/kg ethanol (approximately 3-5 standard drinks in a 70 kg adult) produces measurable increases in intestinal permeability within hours, with elevated serum lipopolysaccharide (LPS) (lipopolysaccharide, a marker of bacterial translocation across the gut wall). The mechanism involves direct phosphorylation of tight junction proteins (claudins, ZO-1), acetaldehyde-mediated oxidative injury, and microbiome dysbiosis with reduced butyrate-producing genera.
Chronic alcohol use compounds the problem. Heavy drinkers (more than 4 drinks/day for men, 3/day for women, sustained for years) develop a leaky gut state with chronic endotoxemia, low-grade systemic inflammation, and accelerated liver fibrosis (the endotoxin-induced Kupffer cell activation is part of the alcohol-to-cirrhosis mechanism, not just direct ethanol hepatotoxicity).
Gut-healing practitioners commonly treat stopping alcohol during the active healing phase as the single biggest step. They report that after 6-12 months of strict abstinence and a gut-healing protocol, occasional small amounts (1 drink, 1-2 times per week, with food) are usually tolerated by people without inflammatory bowel disease (IBD) or celiac disease. For people with active inflammatory bowel disease, advanced liver disease, or alcohol use disorder, practitioners describe permanent abstinence as the goal.
Practical notes:
- "Clean" alcohol (distilled spirits, dry wine) is not less gut-damaging than beer or sweet wine — the ethanol is the primary problem, not the additives or sugars
- Red wine's polyphenol content does not compensate for the ethanol gut injury in someone with active gut symptoms
- Non-alcoholic beer and wine alternatives have improved dramatically in the past 5 years and are used by many people as substitutes for the ritual of drinking
- Cannabis is a separate question; gut effects of cannabis are less studied and less obviously injurious than alcohol but include cannabinoid hyperemesis syndrome in heavy chronic users
Gluten (Celiac and Non-Celiac Wheat Sensitivity)
Gluten in genetically susceptible individuals (HLA-DQ2 / HLA-DQ8 positive, approximately 30% of the US population by haplotype) can trigger celiac disease — an autoimmune enteropathy with villous atrophy, intraepithelial lymphocytosis, and crypt hyperplasia. A national survey (the National Health and Nutrition Examination Survey (NHANES) 2009-2010, 7,798 people) found celiac disease, by blood tests or an earlier diagnosis, in about 0.7% of people in the US (1 in 141) and 1% of non-Hispanic white people; 29 of the 35 people found to have it did not know. Strict lifelong gluten elimination is the only effective treatment.
The more complicated story is non-celiac wheat sensitivity (NCWS) — symptoms triggered by wheat ingestion in patients who do not have celiac and do not have wheat allergy. Estimates of NCWS prevalence vary widely (0.5-13% of population depending on study). Symptoms include bloating, abdominal pain, diarrhea, brain fog, fatigue, joint pain, and skin manifestations triggered within hours to days of wheat ingestion and resolving with strict wheat elimination.
The mechanism of NCWS is not fully understood. Candidates include:
- Amylase-trypsin inhibitors (ATIs) — natural pest-defence proteins in wheat that, in cell, gut-biopsy and mouse studies, activate toll-like receptor 4 (TLR4), an alarm receptor on innate immune cells, producing inflammation independent of the gluten protein itself
- FODMAP content of wheat — FODMAPs (fermentable oligosaccharides, disaccharides, monosaccharides and polyols) are short-chain carbohydrates; fructans in wheat are fermentable and contribute to bloating; some patients labeled NCWS may actually be reacting to the FODMAP component rather than the gluten
- Wheat germ agglutinin (WGA) and other lectins — bind to glycoproteins on the gut epithelium and may disrupt tight junctions in susceptible individuals
- Zonulin-mediated barrier disruption — Fasano's work showing that gliadin triggers zonulin release in both celiac and non-celiac individuals, with downstream tight junction opening
The approach practitioners describe: a 4-6 week strict gluten elimination trial (no wheat, rye, barley, or contaminated oats) for people with chronic gastrointestinal symptoms, with formal celiac evaluation (tissue transglutaminase immunoglobulin A (IgA) + total immunoglobulin A, plus duodenal biopsy if positive) when symptoms improve — ideally done before the gluten elimination, since the testing requires recent gluten exposure to be accurate. If celiac is excluded and gluten elimination still helps symptoms, NCWS is the working diagnosis and strict avoidance is the usual management. Reintroduction trials after several months of gut healing sometimes show improved tolerance in NCWS, though strict avoidance often remains necessary for symptom freedom.
Glyphosate Residue (The Controversial Trigger)
Glyphosate (the active ingredient in glyphosate-based herbicides) is the most-applied agricultural chemical in the world by tonnage. It is used extensively as a desiccant on wheat, oats, barley, and lentils at harvest in addition to its weed-control role in glyphosate-tolerant genetically modified (GMO) soybean and corn cultivation. Residue is detectable in approximately 75-95% of non-organic processed food samples tested.
The proposed mechanisms by which dietary glyphosate residue might affect the gut are speculative but biologically plausible:
- Glyphosate inhibits the shikimate pathway for aromatic amino acid synthesis — a pathway absent in human cells but present in many gut bacteria. Selective effects on commensal flora could alter the microbiome composition
- Animal studies suggest glyphosate residue reduces lactobacilli and bifidobacteria while sparing or favoring Clostridia and Enterobacteriaceae — a shift toward a pro-inflammatory microbiome profile
- Glyphosate is a chelator of divalent cations (zinc, manganese, calcium), potentially impairing absorption
- The combination effect with adjuvants in commercial glyphosate formulations may exceed the direct glyphosate effect
Critics note that human dietary glyphosate exposure is well below acute toxicity thresholds and that the strongest epidemiologic studies do not yet show clear gastrointestinal disease associations specific to glyphosate. The International Agency for Research on Cancer (IARC) classification of glyphosate as Group 2A (probably carcinogenic) is contested by other regulatory bodies.
Some gut-healing practitioners respond by cutting glyphosate exposure during the healing period with organic grain and legume sources, watching whether symptoms improve along with it. The substitutions they list first are organic wheat, oats, lentils, beans, and corn; organic soy is harder to find. Organic food costs more, which they weigh against the length of an active gut-healing protocol.
Chronic Psychological Stress (CRF and Mast Cells)
Chronic psychological stress has measurable, mechanistic gut effects that are easy to overlook in a nutrition-and-supplement-focused gut healing protocol. The major pathway is the corticotropin-releasing factor (CRF) signaling axis. Psychological stress activates the hypothalamic-pituitary-adrenal axis, releasing CRF systemically and locally in the gut. Gut mucosal mast cells express CRF receptors, and CRF binding triggers mast cell degranulation, releasing histamine, tryptase, and other pro-inflammatory mediators directly into the gut wall.
The Vanuytsel 2014 paper in Gut demonstrated this elegantly: healthy volunteers given a public-speaking stress task had measurable increases in intestinal permeability (lactulose-mannitol ratio) within hours of the stressor. The effect was blocked by mast cell stabilizer pretreatment, confirming the mast cell mediation. Chronic stress amplifies and prolongs this effect.
Practical implications:
- Practitioners report limited progress in people pursuing gut healing while in active chronic-stress situations (job loss, divorce, caregiver burden, untreated anxiety or depression), even with good nutrition and supplements
- Stress reduction interventions with evidence: cognitive behavioral therapy for irritable bowel syndrome (IBS) (multiple randomized controlled trials, RCTs), gut-directed hypnotherapy (Manchester protocol, strong evidence for irritable bowel syndrome), mindfulness-based stress reduction, yoga, regular aerobic exercise
- Adequate sleep (7-9 hours) is foundational — sleep deprivation activates CRF independently and exacerbates gut symptoms
- For anxious patients with significant gut symptoms, low-dose tricyclic antidepressants (amitriptyline 10-25 mg at bedtime) have evidence for irritable bowel syndrome symptom reduction beyond the antidepressant effect
- Selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (SNRIs) have mixed evidence in irritable bowel syndrome and may worsen gastrointestinal symptoms in a subset of patients; individual response varies
Chronic Infection (H. pylori, Small Intestinal Bacterial Overgrowth, Parasites)
Chronic enteric infection is an often-missed driver of persistent gut symptoms and barrier dysfunction. Three categories deserve specific consideration:
- Helicobacter pylori — gastric infection that affects approximately 50% of the global population (lower in developed countries). Diagnostic test of choice is urea breath test or stool antigen test. The 2024 American College of Gastroenterology (ACG) guideline names 14 days of bismuth quadruple therapy (typically proton pump inhibitor + bismuth + tetracycline + metronidazole) as the preferred first treatment when antibiotic susceptibility is unknown; rifabutin triple therapy or potassium-competitive acid blocker dual therapy for 14 days is a suitable alternative for people without penicillin allergy. For repeat (salvage) treatment, it limits regimens containing clarithromycin or levofloxacin to cases where antibiotic susceptibility is confirmed, and it calls for a test after every treatment to confirm the infection is gone (test-of-cure). The four-drug option without bismuth (proton pump inhibitor + amoxicillin + clarithromycin + metronidazole) is not among its 2024 first-choice regimens. Eradication is standard in people with peptic ulcer disease, mucosa-associated lymphoid tissue (MALT) lymphoma, atrophic gastritis, or active chronic gastric symptoms. Even in asymptomatic carriers, treatment is increasingly recommended given the gastric cancer risk.
- Small intestinal bacterial overgrowth (SIBO) — abnormal bacterial colonization of the small intestine, where bacteria should be sparse compared with the colon. Diagnosed with breath testing (hydrogen and methane after lactulose or glucose challenge), though breath testing has significant sensitivity and specificity limitations. Treatment depends on the type: hydrogen-predominant small intestinal bacterial overgrowth with rifaximin (550 mg three times a day for 14 days); methane-predominant (now called IMO, intestinal methanogen overgrowth) with rifaximin plus neomycin or metronidazole. After eradication, prokinetics (low-dose erythromycin, prucalopride, or natural prokinetics like ginger) to prevent recurrence. See the comprehensive small intestinal bacterial overgrowth page for detail.
- Parasitic infection — considered in people with travel history, immigration history, well-water exposure, or unexplained chronic gastrointestinal symptoms. Stool ova and parasite testing has poor sensitivity; multiplex polymerase chain reaction (PCR) stool panels sold by commercial laboratories are more sensitive. Specific organisms: Giardia lamblia (the most common gut parasite in the US, often missed because of cyst shedding intermittency), Cryptosporidium, Entamoeba histolytica, Blastocystis hominis (pathogenicity debated), Dientamoeba fragilis.
In people with chronic gut symptoms and stalled progress on diet and supplements, practitioners look for an infection with formal testing, and report that treating an underlying infection often produces a dramatic improvement that no dietary protocol alone had achieved.
Individual Food Sensitivities (Beyond Gluten)
Beyond gluten, the major individual food sensitivities that can drive ongoing gut inflammation:
- Dairy — either lactose intolerance (enzyme-based) or casein/whey protein sensitivity (immune-based). Casein A1 vs A2 protein difference is a relevant emerging consideration — conventional Holstein cattle dairy is mostly A1, while goat, sheep, water buffalo, and Jersey/Guernsey cattle produce predominantly A2 milk that some A1-sensitive patients tolerate
- Eggs — common food allergy in children, less common but real in adults; ovalbumin and ovomucoid the most common allergens
- Corn — both as a direct allergen and as a common contamination source (most processed food contains corn derivatives)
- Soy — food allergen plus phytoestrogen and goitrogen content; many patients tolerate fermented soy (miso, tempeh) better than unfermented (tofu, soy milk)
- Nightshades — tomato, potato, pepper, eggplant; practitioners and patients report that their alkaloid content (solanine, capsaicin) drives symptoms in a subset of people, particularly with joint inflammation
- FODMAP-heavy foods — onion, garlic, apple, pear, mango, watermelon, wheat, beans, lactose-containing dairy. In FODMAP-sensitive irritable bowel syndrome patients, a structured low-FODMAP elimination followed by systematic reintroduction is the evidence-based approach
- Histamine-heavy foods — aged cheese, fermented food, alcohol, cured meats, leftovers (histamine accumulates over time in refrigerated food). Relevant for the histamine-intolerant / mast cell activation subset
- Sulfite-containing foods and wine — less common than reputation suggests, but real in some patients
The systematic approach is structured elimination and reintroduction (next section), not broad-panel "immunoglobulin G (IgG) food sensitivity" testing — the immunoglobulin G tests have poor specificity (immunoglobulin G is a normal immune response to recent food exposure, not a pathological sensitivity indicator), and many patients are misled into restricting foods that are not actually causing problems.
Identification Protocol (Diary, Testing, Elimination)
The structured workup for identifying gut triggers in an individual patient:
- Detailed food and symptom diary — 2-4 weeks of recording everything eaten plus symptoms (bloating, pain, stool form using Bristol Stool Form Scale, energy, mood, sleep), read for patterns over time. Specific food-to-symptom correlation often becomes obvious that was invisible without recording.
- Medication review — nonsteroidal anti-inflammatory drug frequency (including over-the-counter use), proton pump inhibitor duration of use, antibiotic history, opioid use (chronic constipation), metformin (gastrointestinal effects), selective serotonin reuptake inhibitors.
- Celiac screen — tissue transglutaminase immunoglobulin A + total immunoglobulin A, before any gluten elimination. If positive, an upper endoscopy (esophagogastroduodenoscopy, EGD) with duodenal biopsy confirms it.
- Small intestinal bacterial overgrowth breath test — lactulose or glucose breath test for hydrogen and methane.
- H. pylori test — urea breath test or stool antigen if upper gastrointestinal symptoms.
- Comprehensive stool analysis — ova/parasite plus polymerase chain reaction pathogen panel for the chronic-symptom patient.
- Intestinal permeability test (optional) — lactulose-mannitol urinary excretion ratio is the validated marker. Less commonly available; useful for objective monitoring of response to treatment.
- Inflammatory markers — fecal calprotectin to distinguish inflammatory bowel disease from irritable bowel syndrome; C-reactive protein for systemic inflammation.
- Vitamin/mineral panel — B12, folate, iron studies, zinc, vitamin D, magnesium — commonly deficient in malabsorption, useful for objective monitoring.
Structured Elimination and Reintroduction
The evidence-based approach to identifying individual food triggers is structured elimination followed by systematic reintroduction.
Phase 1: Baseline elimination (4-6 weeks). The most common triggers are removed together: gluten, dairy, eggs, soy, corn, peanuts, shellfish, nightshades, refined sugar, alcohol, processed food. The restricted diet continues for 4-6 weeks, during which symptoms ideally improve substantially. If symptoms do not improve in this phase, the trigger may not be food-related, and other categories (chronic infection, nonsteroidal anti-inflammatory drugs, stress) come back into view.
Phase 2: Systematic reintroduction (8-16 weeks). One food category is reintroduced every 3-7 days: a substantial serving of the test food on Day 1, then a return to the baseline elimination diet for Days 2-3, watching for symptom recurrence (bloating, pain, change in bowel habit, rash, fatigue, brain fog, mood change, sleep disruption) within 72 hours of test food ingestion. If symptoms recur, that food counts as a positive trigger and is taken back out. If there are no symptoms in 72 hours, the food goes back into the diet and a new test food is added on Day 7.
Phase 3: Long-term diet construction. The long-term diet is built around the foods that tested negative (no symptom recurrence). Foods that tested positive can be permanently avoided, or retested after 6-12 months of healing — some food sensitivities resolve with adequate gut repair, while others (particularly true allergies and celiac) are permanent.
Common reintroduction orders, easiest to hardest:
- Eggs (often well tolerated, easy to test)
- Nightshades
- Nuts and seeds (one type at a time)
- Dairy: butter and ghee first, then fermented dairy (yogurt, kefir), then aged cheese, then fresh milk
- Corn (separate from other grains)
- Soy (fermented forms first)
- Gluten-containing grains (often the most reactive; test last; some patients never reintroduce)
- Refined sugar (often last; many patients find symptom-free life is better without)
Working with a registered dietitian experienced in elimination diets can substantially improve adherence and reduce the risk of unnecessary nutritional restriction.
Key Research Papers
- Bjarnason I et al. (2018). Mechanisms of damage to the gastrointestinal tract from nonsteroidal anti-inflammatory drugs. Gastroenterology. — PubMed PMID: 29221664
- Graham DY et al. (2005). Visible small-intestinal mucosal injury in chronic NSAID users. Clin Gastroenterol Hepatol. — PubMed PMID: 15645405
- Maiden L et al. (2005). A quantitative analysis of NSAID-induced small bowel pathology by capsule enteroscopy. Gastroenterology. — PubMed PMID: 15887101
- US Preventive Services Task Force; Davidson KW et al. (2022). Aspirin use to prevent cardiovascular disease: US Preventive Services Task Force recommendation statement. JAMA. — PubMed PMID: 35471505
- Vanuytsel T et al. (2014). Psychological stress and corticotropin-releasing hormone increase intestinal permeability in humans by a mast cell-dependent mechanism. Gut. — PubMed PMID: 24153250
- Bode C, Bode JC (2003). Effect of alcohol consumption on the gut. Best Pract Res Clin Gastroenterol. — PubMed PMID: 12828956
- Rubio-Tapia A et al. (2012). The prevalence of celiac disease in the United States. Am J Gastroenterol. — PubMed PMID: 22850429
- Hollon J et al. (2015). Effect of gliadin on permeability of intestinal biopsy explants from celiac disease patients and patients with non-celiac gluten sensitivity. Nutrients. — PubMed PMID: 25734566
- Fasano A (2012). Zonulin, regulation of tight junctions, and autoimmune diseases. Ann N Y Acad Sci. — PubMed PMID: 22731712
- Catassi C et al. (2015). Diagnosis of Non-Celiac Gluten Sensitivity (NCGS): The Salerno Experts' Criteria. Nutrients. — PubMed PMID: 26096570
- Junker Y et al. (2012). Wheat amylase trypsin inhibitors drive intestinal inflammation via activation of toll-like receptor 4. J Exp Med. — PubMed PMID: 23209313
- Halmos EP et al. (2014). A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology. — PubMed PMID: 24076059
- Pimentel M et al. (2020). ACG Clinical Guideline: Small Intestinal Bacterial Overgrowth. Am J Gastroenterol. — PubMed PMID: 32023228
- Chey WD et al. (2024). ACG Clinical Guideline: Treatment of Helicobacter pylori Infection. Am J Gastroenterol. — PubMed PMID: 39626064
- Camilleri M (2019). Leaky gut: mechanisms, measurement and clinical implications in humans. Gut. — PubMed PMID: 31076401
- Mu Q et al. (2017). Leaky gut as a danger signal for autoimmune diseases. Front Immunol. — PubMed PMID: 28588585
- Madsen K et al. (2001). Probiotic bacteria enhance murine and human intestinal epithelial barrier function. Gastroenterology. — PubMed PMID: 11522742
PubMed Topic Searches
Connections
- All Remedies
- Gut Healing Overview
- Gut Healing Benefits Hub
- GAPS Diet
- Bone Broth and Glutamine
- Probiotic Strains for Repair
- Small Intestinal Bacterial Overgrowth
- Celiac Disease
- Irritable Bowel Syndrome
- Crohn's Disease
- Helicobacter pylori
- Glyphosate
- Glyphosate (Toxin Profile) — the shikimate-pathway and microbiome argument behind the residue trigger discussed above.
- Alcohol
- Stress Management
- Stool Tests
- Immune Boosting