Preconception, Pregnancy and Childhood Nutrition (Weston A. Price)
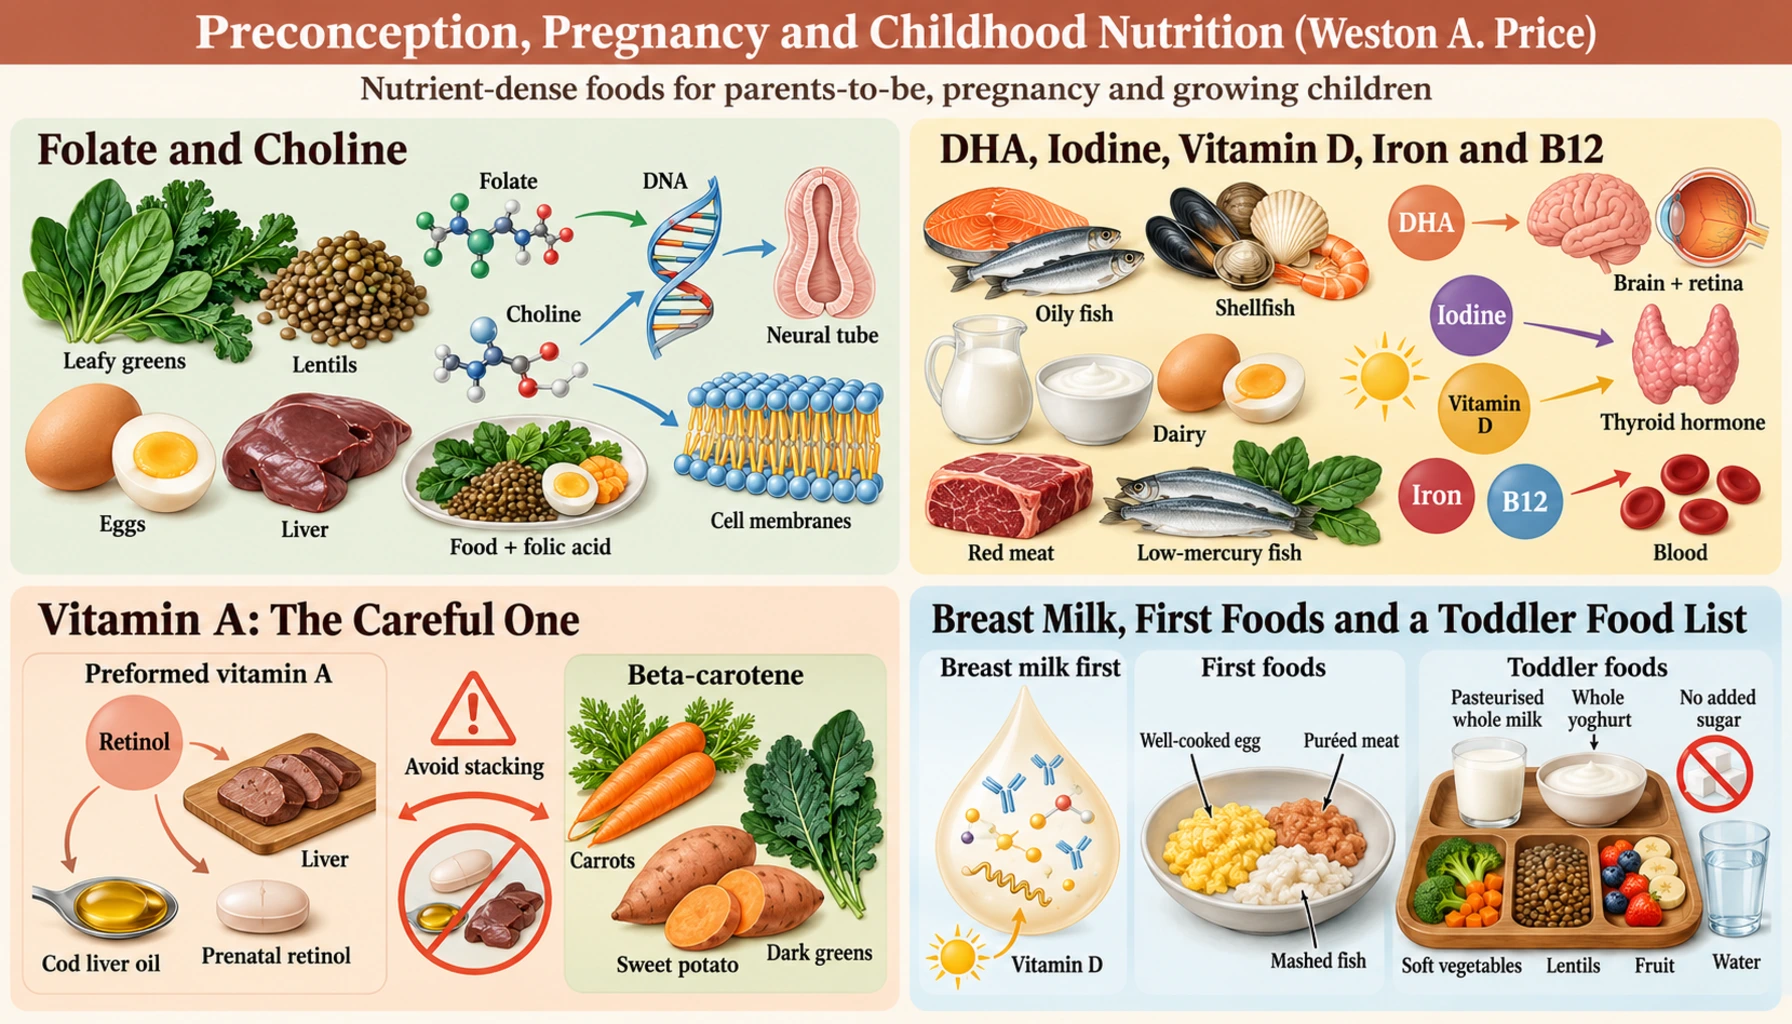
The eleventh principle of the Weston A. Price diet says that traditional peoples protected the next generation on purpose: special nutrient-dense animal foods for parents-to-be, pregnant and nursing mothers and growing children, plus sensible spacing between births. Modern research backs much of that instinct — folate, choline, seafood docosahexaenoic acid (DHA) and iodine all matter enormously for a baby's brain and spine. But one of the diet's favourite foods, liver (and cod liver oil), carries so much preformed vitamin A that pregnancy needs a careful, small-portion approach. This page walks through each nutrient, the amounts that matter, and practical food lists for pregnancy and the toddler years.
Table of Contents
- What Price Observed: Special Foods for the Next Generation
- Folate and Choline: Building the Spine and Brain
- Docosahexaenoic Acid, Iodine, Vitamin D, Iron and B12
- Vitamin A: The Careful One
- Fathers Too, and the Spacing of Births
- Infants and Children: Breast Milk, Formula and First Foods
- A Pregnancy Plate and a Toddler Food List
- Safety Summary
- Key Research Papers
- Connections
- Featured Videos
What Price Observed: Special Foods for the Next Generation
During his 1930s travels, the dentist Weston A. Price noticed something that surprised him: many of the isolated communities he visited did not leave the health of the next generation to chance. According to the Foundation's booklet, a number of groups set aside a period of special feeding before conception, giving young men and women the most prized animal foods. The same foods were then reserved for pregnant and nursing women and for growing children. Price reported that these foods — organ meats, animal fats, fish eggs and certain seafoods — were especially rich in minerals and in the fat-soluble vitamins A and D (and the factor he called "Activator X", now thought to be vitamin K2). You can read the full story of his travels on the History page.
The booklet turns this into the diet's principle 11: traditional cultures look after future generations by feeding nutrient-rich animal foods to parents-to-be, pregnant women and children; by proper spacing of children; and by teaching the young how to eat well. (All eleven principles are explained on the Eleven Principles page.)
How well the idea holds up
The core idea — that what parents eat before and during pregnancy shapes a child's development — is now mainstream science. Evidence tier: well supported, by randomised trials in humans for folic acid and choline, and by large cohort studies for seafood and iodine. Price's observations themselves are traditional-use and field-observation evidence: valuable for generating ideas, but they could not separate diet from genetics, activity, infection or isolation. The rest of this page checks each piece against modern studies.
Two places where the modern picture adds caution to the diet's enthusiasm: preformed vitamin A (liver and cod liver oil) has a real upper limit in pregnancy, and raw milk carries infection risks that fall hardest on pregnant women and young children. Both are covered below.
Folate and Choline: Building the Spine and Brain
Think of early pregnancy as the weeks when the baby's wiring is laid down. The neural tube — the structure that becomes the brain and spinal cord — closes about four weeks after conception, often before a woman knows she is pregnant. That is why preconception nutrition matters so much, and why the diet's "special feeding before conception" idea is more than folklore.
The chart above sums up this page's food advice in one picture. Liver and eggs are the two most complete foods for pregnancy; oily fish and shellfish fill the gaps for docosahexaenoic acid, iodine, B12 and vitamin D; leafy greens and legumes are the plant side's best folate source. Iron is richest in liver and red meat, with useful amounts in eggs, seafood and greens. No single food covers everything, which is exactly why traditional diets mixed them.
Folate
What it does: folate is needed to copy DNA and build new cells, and the fast-dividing cells of the closing neural tube need a great deal of it. Shortage raises the risk of neural tube defects such as spina bifida and anencephaly.
The evidence: the landmark MRC Vitamin Study (1991) was a randomised, double-blind trial at 33 centres in seven countries. It enrolled 1,817 women who had already had an affected pregnancy. Folic acid taken from before conception gave a 72% protective effect against a repeat neural tube defect; a mix of seven other vitamins did not. Evidence tier: randomized controlled trial (RCT) in humans, one of the clearest results in all of nutrition. (That trial used a high 4 mg dose for high-risk women; for everyone else, public-health bodies recommend 400 mcg of folic acid a day from at least a month before conception.)
Where the diet and the evidence meet: the pregnancy Recommended Dietary Allowance (RDA) for folate is 600 mcg DFE a day. Food folate is excellent — U.S. Department of Agriculture (USDA) data list pan-fried chicken liver at 560 mcg per 100 g and beef liver at 260 mcg per 100 g, and dark leafy greens, lentils and other legumes are rich plant sources. But the trial proof is for folic acid supplements, and food-only folate is harder to measure reliably in the critical first weeks. This is the one place where the evidence points to food plus a supplement: the folate-rich foods the diet favours and folic acid. In 2023 the US Preventive Services Task Force reaffirmed its recommendation that all persons planning to or who could become pregnant take a daily supplement containing 0.4 to 0.8 mg (400 to 800 mcg) of folic acid, concluding with high certainty that it has a substantial net benefit in preventing neural tube defects; it estimates that about 3,000 US pregnancies are affected by these defects each year. (Folic acid is the form the neural-tube trials tested; methylfolate has not been tested in trials of that kind.) More detail: Folate and Pregnancy.
Choline
What it does: choline builds cell membranes and the messenger chemical acetylcholine, and it supports the developing memory centre of the baby's brain. The Adequate Intake (AI) in pregnancy is 450 mg a day.
Most women fall short. An analysis of US national survey data (Wallace and Fulgoni, 2017) found that only about 8.5% of pregnant women met the Adequate Intake. Across the US population, egg eaters had almost double the usual choline intake of non-eaters (about 525 mg versus 294 mg a day), and the authors concluded it is extremely difficult to reach the Adequate Intake without eggs or a supplement. Evidence tier: cross-sectional survey.
Does more help? In a small controlled-feeding trial (Caudill and colleagues, 2018), 26 women in their third trimester ate either 480 mg or 930 mg of choline a day. Babies of the 930 mg group had faster information-processing speed through their first 13 months. Evidence tier: randomized controlled trial in humans, but small — promising rather than settled.
Seven years later. A follow-up of the same trial (Bahnfleth and colleagues, 2022) tested 20 of the children at age 7 on a sustained-attention task. Children whose mothers had eaten 930 mg of choline a day performed better than those in the 480 mg group. On the briefest (17 ms) signals, the 480 mg group's correct detections fell 22.9% across the 12-minute session, while the 930 mg group's rose 1.5%. The authors note that, on average, pregnant women consume about 70% of the Adequate Intake for choline. Evidence tier: follow-up of a small randomized controlled trial.
The traditional-food answer: eggs and liver, both diet staples, are the richest common sources. By U.S. Department of Agriculture figures, a large egg (about 50 g) supplies roughly 147 mg of choline, so 2 eggs give about 294 mg; an 85 g (3 oz) serving of pan-fried beef liver supplies about 355 mg. Two or three eggs a day gets most women close to the Adequate Intake. The yolks are where the choline is. See Choline in Pregnancy.
Docosahexaenoic Acid, Iodine, Vitamin D, Iron and B12
Docosahexaenoic Acid from seafood
Docosahexaenoic acid is the omega-3 fat that makes up much of the brain and retina. The diet prizes fish, fish eggs and shellfish, and here the evidence is broadly on its side. In the ALSPAC cohort (Hibbeln and colleagues, 2007), 11,875 pregnant women in England reported their seafood intake. Children of mothers who ate no seafood were more likely to score in the lowest quarter for verbal IQ than children of mothers eating more than 340 g (about 12 oz) a week (odds ratio 1.48, 95% confidence interval 1.16 to 1.90), with poorer scores on several social and motor measures too. For each outcome, the lower the mother's seafood intake, the higher the risk of a poorer result. Evidence tier: cohort — adjusted for 28 confounders, but not proof of cause.
Practical amount: the U.S. Food and Drug Administration (FDA) and the U.S. Environmental Protection Agency (EPA) advise pregnant and breastfeeding women to eat 8 to 12 oz (2 to 3 servings) a week of fish from their low-mercury "best choices" list — salmon, sardines, anchovies, herring, trout, shrimp, cod and similar — and to avoid the high-mercury fish (shark, swordfish, king mackerel, bigeye tuna, marlin, orange roughy, tilefish from the Gulf of Mexico). See the U.S. Food and Drug Administration/Environmental Protection Agency (EPA) Advice about Eating Fish. By U.S. Department of Agriculture data, an 85 g serving of cooked farmed Atlantic salmon carries about 1.24 g of docosahexaenoic acid. More: Omega-3s in Pregnancy.
Iodine
The baby's thyroid does not work until mid-pregnancy, so for months the brain depends on the mother's thyroid hormone, which is built from iodine. The pregnancy Recommended Dietary Allowance is 220 mcg a day. In another ALSPAC analysis (Bath and colleagues, 2013), children of women who were mildly iodine-deficient in the first trimester (an iodine-to-creatinine ratio under 150 mcg/g) were more likely to score in the lowest quarter for verbal IQ at age 8 (odds ratio 1.58), reading accuracy (1.69) and reading comprehension (1.54) at age 9 than children of mothers with ratios of 150 mcg/g or more. When the low group was split, scores worsened further from 50–150 mcg/g to under 50 mcg/g. Evidence tier: cohort.
Sources and a salt caveat: seafood (especially white fish and shellfish), seaweed, eggs and dairy are the main food sources. The booklet favours unrefined sea salt over refined salt — but unrefined salt carries very little iodine. Iodised salt was introduced precisely because most traditional diets far from the sea were short of it. Someone who uses unrefined salt and does not eat seafood or dairy most days may be getting very little iodine. The American Thyroid Association recommends that pregnant and breastfeeding women take a supplement providing 150 mcg of iodine a day. Seaweed (especially kelp) can deliver huge, variable amounts. See Iodine.
Vitamin D
The Recommended Dietary Allowance in pregnancy is 600 international units (IU) (15 mcg) a day. Oily fish is the standout food: by U.S. Department of Agriculture data, cooked farmed salmon carries about 526 international units per 100 g, and an egg yolk adds a little (whole egg about 82 international units per 100 g). Liver carries little (beef liver about 49 international units per 100 g). In the US, milk is fortified; whole dairy from pastured animals carries some natural vitamin D but less than fish. Sunlight on bare skin is the other traditional source. Many pregnant women, especially those with darker skin or little sun, test low, so a blood test is worthwhile. See Vitamin D3.
Iron and vitamin B12
Iron needs rise to 27 mg a day in pregnancy because blood volume expands by roughly half. The heme iron in red meat, liver and shellfish is absorbed far better than the iron in plants; pan-fried chicken liver supplies about 12.9 mg per 100 g and beef liver about 6.2 mg per 100 g. Pairing greens and legumes with vitamin C-rich foods helps their non-heme iron absorb. See Iron.
Vitamin B12 (Recommended Dietary Allowance 2.6 mcg in pregnancy) is found almost only in animal foods. Liver is extraordinarily rich — about 83 mcg per 100 g of pan-fried beef liver — and fish, meat, eggs and dairy all contribute. A mother who eats these foods is very unlikely to run short; a plant-only diet needs a supplement. See Vitamin B12.
Vitamin A: The Careful One
This is the section to read twice. Vitamin A is essential for a baby's eyes, lungs, heart and immune system, and the diet rightly values it. But preformed vitamin A (retinol, the form in liver, cod liver oil and supplements) is stored in the body, and too much of it in early pregnancy can cause birth defects. That is a documented harm, not a theory.
The numbers
- Recommended Dietary Allowance in pregnancy (age 19 and over): 770 mcg RAE a day, about 2,560 international units of retinol.
- Tolerable Upper Intake Level: 3,000 mcg RAE a day of preformed vitamin A, which is 10,000 international units. The upper limit does not include beta-carotene from plants.
- Beef liver: U.S. Department of Agriculture FoodData Central lists pan-fried beef liver at 7,744 mcg RAE per 100 g. A typical 85 g (3 oz) serving holds about 6,582 mcg RAE (roughly 22,000 international units) — more than 2 times the daily upper limit in a single meal.
- A small portion of 30 g (1 oz) holds about 2,323 mcg RAE — above the Recommended Dietary Allowance but under the upper limit.
- Cod liver oil: the U.S. Department of Agriculture's generic entry gives about 4,500 international units of vitamin A and 450 international units of vitamin D per teaspoon (about 4.5 g); individual products vary widely.
The key study
In a cohort of 22,748 pregnant women (Rothman and colleagues, 1995, New England Journal of Medicine), babies of women taking more than 10,000 international units a day of preformed vitamin A from supplements had about 4.8 times the rate of defects in tissues derived from the cranial neural crest (face, ears, heart) compared with women taking 5,000 international units or less. The risk was concentrated in women with high intake before the seventh week of pregnancy, and the authors estimated that about 1 in 57 babies of the high-supplement group had a malformation attributable to it. Evidence tier: cohort, supported by the known birth-defect effects of retinoid drugs.
What this means for the diet's advice
The booklet recommends cod liver oil to provide at least 10,000 international units of vitamin A a day. For a pregnant woman, or anyone who could become pregnant, that figure sits right at the upper limit before counting liver, butter, egg yolks or a prenatal vitamin — and it is the very level at which the 1995 study saw risk begin.
What the numbers mean for liver, cod liver oil and prenatal vitamins in pregnancy:
- A small portion of liver (about 30 g / 1 oz) stays under the daily upper limit, while a typical 85 g serving is more than twice it (see the numbers above); eaten no more than once a week, such a portion keeps liver an occasional source. Grating a little frozen liver into a meat sauce or mince is one way to use a small amount.
- Many authorities, including the UK's National Health Service, go further and advise avoiding liver and liver products (including pâté) altogether during pregnancy. In the 1995 study the risk was concentrated in high intake before the seventh week of pregnancy.
- The sources stack: cod liver oil, liver and a prenatal vitamin with retinol all count toward the same upper limit for preformed vitamin A. Fish itself also supplies docosahexaenoic acid and vitamin D.
- A prenatal vitamin whose vitamin A comes mainly or entirely as beta-carotene adds little or no preformed vitamin A, since the upper limit does not include beta-carotene.
- Carrots, sweet potatoes, squash and dark greens supply beta-carotene, which is converted to vitamin A only as the body needs it and is not linked to birth defects.
The deeper science of vitamin A, D and K2 is on the Fat-Soluble Activators page; see also Vitamin A and Beef Liver.
Fathers Too, and the Spacing of Births
Preconception nutrition for fathers
Price's account of special feeding for both young men and young women is one of the more striking parts of the booklet, and modern research has started to look at the father's side. Sperm take roughly two to three months to mature, so a father's diet in the months before conception is the relevant window.
A systematic review of 35 observational studies (Salas-Huetos and colleagues, 2017) found that diets rich in omega-3 fats, antioxidants (vitamin E, vitamin C, beta-carotene, selenium, zinc, lycopene), vitamin D and folate were linked with better semen quality, as were fish, shellfish, poultry, cereals, vegetables and fruit. Processed meat, soy foods, potatoes, coffee, alcohol, sugar-sweetened drinks and sweets were linked with poorer semen quality in some studies, and a high intake of alcohol, caffeine, red meat and processed meat by men with lower chances of conception. On fat, the review's findings do not side with the diet: diets low in saturated and trans fats, and low-fat dairy and skimmed milk, went with better semen quality, while full-fat dairy and cheese went with poorer quality in some studies. That finding is reported here as it stands, without a dairy-fat recommendation drawn either way from associations. Evidence tier: systematic review of observational studies — associations, not proof, as the authors themselves stress.
The practical overlap with the diet is large: fish, shellfish (oysters are the richest zinc source), poultry, vegetables and fruit, with little sugar, processed meat or alcohol. That is close to what Price described being fed to young men before marriage.
Spacing between births
The booklet's "proper spacing of children" turns out to be one of its best-supported claims. A 2006 meta-analysis in JAMA (Conde-Agudelo and colleagues) pooled 67 studies that adjusted for maternal age and income. Using an interpregnancy interval of 18 to 23 months (from one birth to the next conception) as the reference — the lowest-risk group — intervals under 6 months carried odds ratios of 1.40 for preterm birth, 1.61 for low birth weight and 1.26 for being small for gestational age. Intervals of 6 to 17 months, and longer than 59 months, also carried significantly higher risk for all three outcomes; the authors concluded that intervals shorter than 18 months or longer than 59 months are the risky ones. Evidence tier: meta-analysis of observational studies.
Why would a short gap matter? One leading explanation is maternal nutrient depletion: pregnancy and breastfeeding draw down folate, iron and other stores, and a mother who conceives again quickly may start the next pregnancy already short. That is almost exactly the reasoning traditional cultures gave for spacing. The World Health Organization advises waiting at least 24 months after a live birth before trying for the next pregnancy — a gap that also gives time to rebuild stores with the nutrient-dense foods on this page.
Infants and Children: Breast Milk, Formula and First Foods
Breast milk comes first
Every serious body of evidence agrees: breast milk is the first food. Its fats, antibodies, living cells and changing composition cannot be copied in a kitchen. A nursing mother's own diet affects some of what reaches the baby — docosahexaenoic acid, iodine, choline, vitamin A and B12 levels in milk all track the mother's intake — so the nutrient-dense eating described above continues to matter after birth. Breastfed babies are usually advised to receive a vitamin D supplement (400 international units a day in the US) because breast milk is naturally low in it.
Homemade formula — why no recipe appears here
The booklet itself does not give an infant formula recipe, but the Foundation's website publishes several homemade infant formulas (raw-milk, goat-milk and broth-and-liver versions), offered as alternatives when breastfeeding is not possible. The motivation is a wish to avoid industrial ingredients. No homemade formula recipe is presented on this page, for the reasons below.
- The U.S. Food and Drug Administration advises parents and caregivers not to make or feed homemade infant formula, warning of contamination and of nutrient amounts that are dangerously too high or too low. See the U.S. Food and Drug Administration advisory.
- Documented harm: a U.S. Centers for Disease Control and Prevention (CDC) report (Calello and colleagues, 2021) described infants in three US states who developed vitamin D-deficient rickets and severe hypocalcaemia (dangerously low blood calcium) on a homemade formula. A second report in Pediatrics (Vieira and colleagues, 2021) described 2 unrelated infants with rickets, seizures and cardiac arrest from a homemade formula found online. Evidence tier: case series — few cases, but severe harm in babies. These cases involved different recipes (an "alkaline diet" formula and a vegan formula), not the Foundation's; the general lesson is that an infant's only food has almost no margin for error.
- Raw milk is a specific danger for infants, whose immune systems are immature (see below).
If a baby cannot be breastfed or fully breastfed, donor milk from a screened milk bank or a standard cow's-milk-based commercial formula are the established alternatives: in the US every infant formula sold must meet the U.S. Food and Drug Administration's nutrient and safety requirements, which a kitchen recipe cannot be tested against. The label's directions set the amounts; formula that is watered down or concentrated no longer matches them. Cow's milk, goat's milk and plant milks are not substitutes for formula as a drink before 12 months (the American Academy of Pediatrics' advice on cow's milk is under whole milk below). A true milk-protein allergy is a medical situation in which the choice of formula changes.
Soy formula
The booklet devotes a full section to concerns about soy infant formula, chiefly its plant oestrogens (isoflavones). Part of that concern rests on measured data. In a 1997 Lancet study (Setchell and colleagues), 4-month-old infants fed soy formula had plasma genistein and daidzein levels far above those of babies fed cow's-milk formula or breast milk, and an order of magnitude higher per body weight than typical adult levels; the infants took in about 4.5 to 8.0 mg of isoflavones per kg of body weight a day. Evidence tier: measurement study. Whether those levels cause long-term harm in humans is not established — several of the booklet's stronger claims (comparisons to birth-control pills, links to early puberty) rest largely on animal studies and associations, and they are not presented here as fact.
The American Academy of Pediatrics' Committee on Nutrition (Bhatia and Greer, 2008) concluded that soy formula has very limited indications — mainly galactosaemia, hereditary lactase deficiency, or a family's vegan preference — and is not recommended for preterm infants or for preventing colic or allergy.
First foods: iron-rich animal foods, around 6 months
A baby's iron stores from birth run low at about 6 months, which is when solid foods are usually introduced alongside breast milk. Here the diet's advice is well matched to modern guidance: well-cooked egg, finely minced or puréed meat, and mashed fish are excellent early foods because they supply easily absorbed iron, zinc, choline and B12. Introducing egg (and peanut) early, rather than delaying it, is now advised for most babies because it lowers allergy risk. Liver can appear in small amounts but, as with pregnancy, its vitamin A is concentrated, and the upper limit for infants is only 600 mcg of preformed vitamin A a day — about a teaspoon of liver purée at a time, once a week or so, keeps the amount small.
Whole milk and full-fat dairy for children
The diet opposes low-fat foods for children, and a growing body of evidence is on its side. A 2020 systematic review and meta-analysis in the American Journal of Clinical Nutrition (Vanderhout and colleagues) pooled 14 studies of 20,897 children aged 1 to 18. Children who drank whole milk (3.25% fat) had 39% lower odds of overweight or obesity (odds ratio 0.61) than those drinking reduced-fat milk. Evidence tier: meta-analysis of observational studies — the studies varied a lot, and no randomised trial yet exists, so it shows association rather than cause. Still, it undercuts the assumption that reduced-fat milk protects children's weight. Cow's milk as a drink is for after the first birthday: the American Academy of Pediatrics advises against it before 12 months, because it is low in iron and can displace breast milk or formula.
Sugar
The booklet lists refined sugar first among the "displacing foods of modern commerce". For children this is mainstream advice: US dietary guidance says no added sugar at all before age 2, and limited amounts after. Sugar displaces the nutrient-dense foods a growing child needs and feeds tooth decay — the very problem that started Price's investigation.
Raw milk risks in pregnancy and early childhood
The Foundation advocates access to raw milk. The infection risks of raw milk fall hardest on pregnant women, infants and young children. Raw milk can carry Listeria, E. coli O157, Campylobacter and Salmonella; pregnant women are around 10 times more likely than other people to get listeriosis, which can cause miscarriage, stillbirth or life-threatening infection in the newborn, and young children are the group most often hospitalised in raw-milk outbreaks. Evidence tier: outbreak surveillance data. The full discussion is on the Nutrient-Dense Foods page, with more at Raw vs Pasteurized Milk and Listeria in Pregnancy and Newborns. Pasteurised whole milk, cultured whole yoghurt and kefir give the benefits of full-fat dairy without that risk.
A Pregnancy Plate and a Toddler Food List
A weekly pregnancy plate
This list puts the evidence above into a shopping-trolley shape. It assumes no allergies and is a guide, not a prescription.
- Eggs: 2 to 3 a day, cooked until both yolk and white are firm (whole eggs; the yolk carries the choline).
- Low-mercury fish and shellfish: 2 to 3 servings a week (8 to 12 oz in total) — salmon, sardines, herring, anchovies, trout, cod, shrimp; well-cooked, not raw.
- Red meat: 3 to 4 servings a week of beef, lamb or pork for heme iron, zinc and B12; slow-cooked cuts and home-made bone broth for variety.
- Liver (optional, small): at most about 30 g (1 oz) once a week, or none — see the vitamin A section.
- Whole dairy, pasteurised: whole milk, whole-milk yoghurt or kefir, hard cheeses — daily if tolerated, for calcium, iodine and protein. Soft unpasteurised cheeses are made from raw milk and carry its risks (see raw milk above).
- Leafy greens and legumes: a serving of dark greens most days and lentils, beans or chickpeas several times a week (soaked and well cooked) for folate and fibre.
- Orange vegetables: carrots, sweet potatoes, squash several times a week for safe beta-carotene vitamin A.
- Whole grains: brown rice, oats and sourdough whole-grain bread.
- Fats: butter, olive oil, the fat on meat — in line with the diet's preference for traditional fats.
- Fruit daily, with vitamin C to help iron absorption.
- Supplements worth discussing: folic acid 400 mcg (from before conception), iodine 150 mcg, and vitamin D if a blood test is low — plus a prenatal vitamin whose vitamin A is mainly beta-carotene.
A toddler food list (about 1 to 3 years)
- Scrambled or hard-boiled eggs, cut small.
- Minced beef, lamb or chicken in sauces, meatballs or soups.
- Flaked salmon, sardines (bones mashed in, for calcium) and other low-mercury fish.
- Whole milk (after age 1), whole-milk yoghurt, kefir and cheese — pasteurised.
- Soft-cooked vegetables with butter: carrots, sweet potato, squash, peas, broccoli.
- Well-cooked lentils and beans, mashed.
- Brown rice, porridge oats, whole-grain sourdough.
- Soft fruit — banana, berries, ripe pear — rather than juice.
- Bone broth as a base for soups and grains.
- Water and milk to drink; no added sugar, no sweetened drinks, and no honey before age 1.
For a full step-by-step plan, shopping list and 7-day menu for the whole family, see Getting Started.
Safety Summary
Pregnancy, infancy and early childhood are the times when food choices carry the highest stakes. The key facts from this page:
- Preformed vitamin A: the upper limit is 3,000 mcg RAE (10,000 international units) a day in total. A typical 85 g serving of beef liver holds more than twice that; a small 30 g portion stays under it; the UK's National Health Service advises avoiding liver in pregnancy; high-dose cod liver oil, liver and a retinol-containing prenatal all add to the same total.
- Folate: the trial proof is for folic acid supplements, not food alone; the US Preventive Services Task Force recommends 400 to 800 mcg of folic acid a day for everyone planning to or who could become pregnant.
- Iodine: unrefined salt is not a reliable iodine source; the American Thyroid Association recommends a 150 mcg supplement in pregnancy and breastfeeding, and seaweed delivers huge, variable amounts.
- Mercury: the high-mercury fish in the U.S. Food and Drug Administration/Environmental Protection Agency advice are shark, swordfish, king mackerel, bigeye tuna, marlin, orange roughy and Gulf tilefish; its "best choices" list holds the low-mercury fish.
- Raw and undercooked foods: raw milk, unpasteurised soft cheese, raw fish, raw shellfish and undercooked eggs and meat carry infection risks that are highest in pregnancy and early childhood.
- Infant feeding: breast milk first; otherwise a standard cow's-milk-based commercial formula or screened donor milk. The U.S. Food and Drug Administration advises against homemade formulas, and the American Academy of Pediatrics lists very limited indications for soy formula.
- Cow's milk: not as a drink before 12 months (American Academy of Pediatrics); whole pasteurised milk after that.
- Honey before 12 months is linked to infant botulism, and US dietary guidance says no added sugar before age 2.
Key Research Papers
- MRC Vitamin Study Research Group (1991). Prevention of neural tube defects: results of the Medical Research Council Vitamin Study. Lancet — PubMed PMID: 1677062
- US Preventive Services Task Force; Barry MJ, Nicholson WK, Silverstein M, et al. (2023). Folic Acid Supplementation to Prevent Neural Tube Defects: US Preventive Services Task Force Reaffirmation Recommendation Statement. JAMA — PubMed PMID: 37526713
- Wallace TC, Fulgoni VL (2017). Usual Choline Intakes Are Associated with Egg and Protein Food Consumption in the United States. Nutrients — PubMed PMID: 28783055
- Caudill MA, Strupp BJ, Muscalu L, Nevins JEH, Canfield RL (2018). Maternal choline supplementation during the third trimester of pregnancy improves infant information processing speed: a randomized, double-blind, controlled feeding study. FASEB Journal — PubMed PMID: 29217669
- Bahnfleth CL, Strupp BJ, Caudill MA, Canfield RL (2022). Prenatal choline supplementation improves child sustained attention: A 7-year follow-up of a randomized controlled feeding trial. FASEB Journal — PubMed PMID: 34962672
- Hibbeln JR, Davis JM, Steer C, Emmett P, Rogers I, Williams C, Golding J (2007). Maternal seafood consumption in pregnancy and neurodevelopmental outcomes in childhood (ALSPAC study): an observational cohort study. Lancet — PubMed PMID: 17307104
- Bath SC, Steer CD, Golding J, Emmett P, Rayman MP (2013). Effect of inadequate iodine status in UK pregnant women on cognitive outcomes in their children: results from the Avon Longitudinal Study of Parents and Children (ALSPAC). Lancet — PubMed PMID: 23706508
- Rothman KJ, Moore LL, Singer MR, Nguyen US, Mannino S, Milunsky A (1995). Teratogenicity of high vitamin A intake. New England Journal of Medicine — PubMed PMID: 7477116
- Salas-Huetos A, Bulló M, Salas-Salvadó J (2017). Dietary patterns, foods and nutrients in male fertility parameters and fecundability: a systematic review of observational studies. Human Reproduction Update — PubMed PMID: 28333357
- Conde-Agudelo A, Rosas-Bermúdez A, Kafury-Goeta AC (2006). Birth spacing and risk of adverse perinatal outcomes: a meta-analysis. JAMA — PubMed PMID: 16622143
- Calello DP, Jefri M, Yu M, Zarraga J, Bergamo D, Hamilton R (2021). Notes from the Field: Vitamin D-Deficient Rickets and Severe Hypocalcemia in Infants Fed Homemade Alkaline Diet Formula - Three States, August 2020-February 2021. MMWR Morbidity and Mortality Weekly Report — PubMed PMID: 34411077
- Vieira MA, Kube PK, van Helmond JL, Hanley PC, Graber EG, Bialo SR, Slamon NB (2021). Recipe for Disaster: Homemade Formula Leading to Severe Complications in 2 Infants. Pediatrics — PubMed PMID: 34446537
- Setchell KD, Zimmer-Nechemias L, Cai J, Heubi JE (1997). Exposure of infants to phyto-oestrogens from soy-based infant formula. Lancet — PubMed PMID: 9217716
- Bhatia J, Greer F; American Academy of Pediatrics Committee on Nutrition (2008). Use of soy protein-based formulas in infant feeding. Pediatrics — PubMed PMID: 18450914
- Vanderhout SM, Aglipay M, Torabi N, Jüni P, da Costa BR, Birken CS, O'Connor DL, Thorpe KE, Maguire JL (2020). Whole milk compared with reduced-fat milk and childhood overweight: a systematic review and meta-analysis. American Journal of Clinical Nutrition — PubMed PMID: 31851302