⚠ Evidence warning: Clinical trials or other evidence do not support the claims that oral methylsulfonylmethane (MSM) at 1-3 g/day and L-cysteine at 1500-2000 mg/day improve hair growth and hair fiber thickness, and that oral MSM helps chronic urticaria and atopic dermatitis. This page keeps it as a report of what people, websites or other media say.
Sulfur for Skin Health
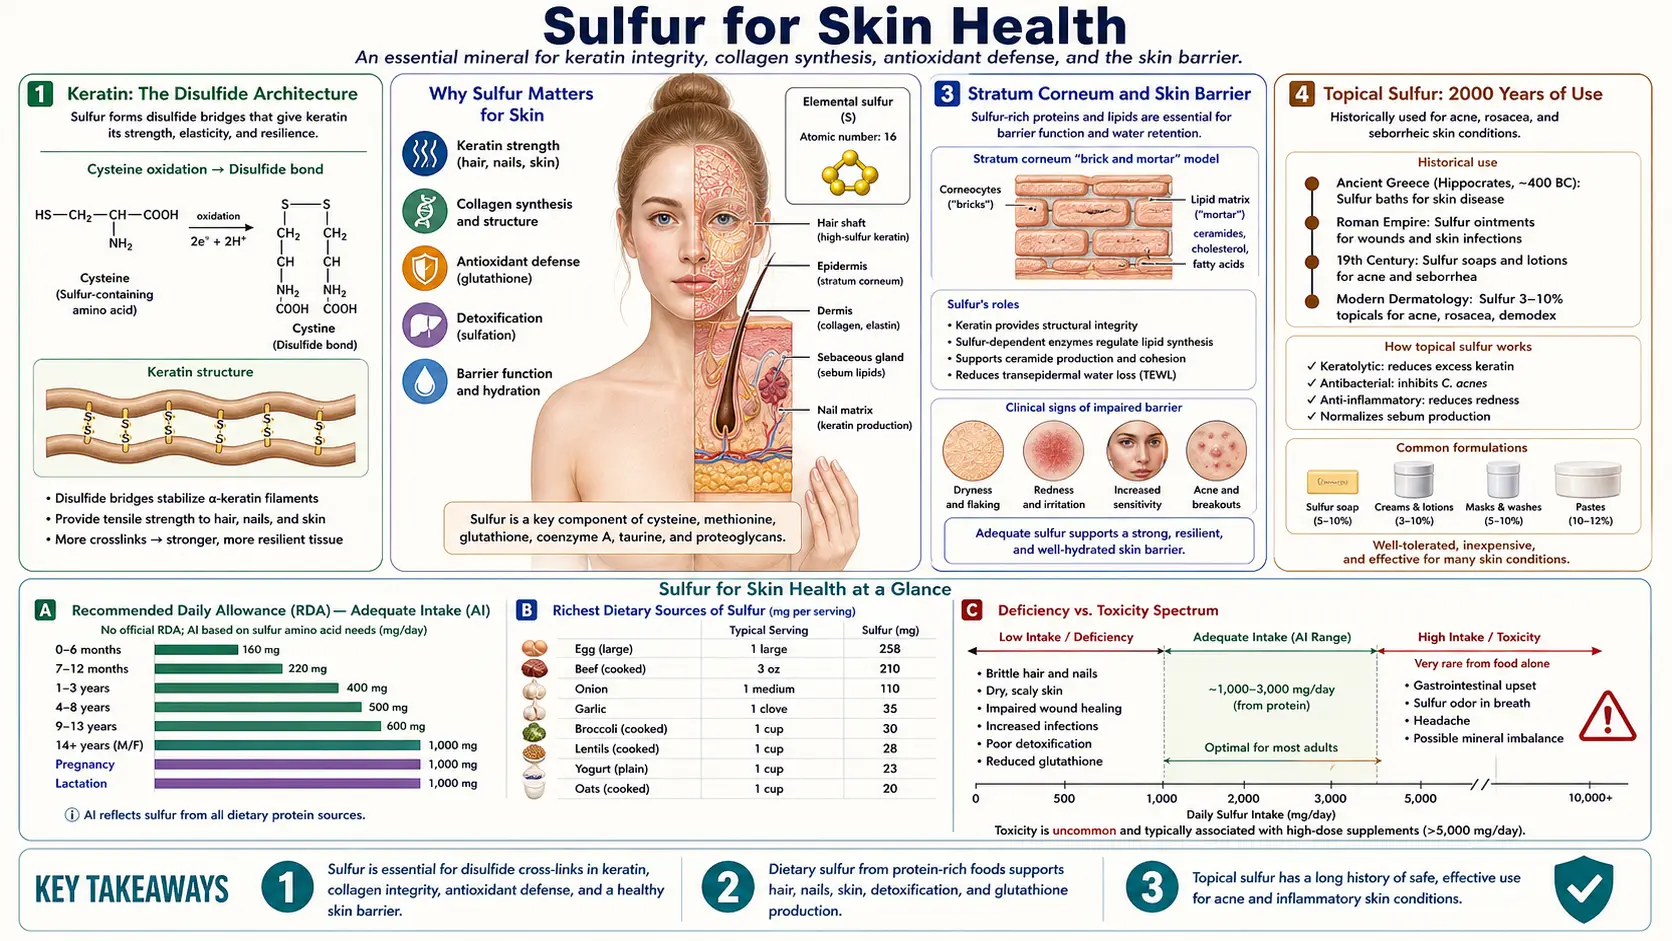
Sulfur is the structural element that gives keratin its strength. The disulfide cross-links between cysteine residues are what distinguish hair, nail, and stratum corneum keratin from ordinary intracellular protein — the cross-link density is so high that a single hair shaft contains roughly 14% cysteine by mass. The same sulfur that builds keratin is also the ancient medicinal element of dermatology: yellow elemental sulfur has been used topically for acne, rosacea, and scabies for over two thousand years; Dead Sea treatment in Israel (sunbathing plus bathing in the mineral-rich water) is credited by a 2012 systematic review with benefit in psoriasis, a benefit the review puts down to the Dead Sea's sunlight and salt-water bathing rather than to sulfur; methylsulfonylmethane (MSM), a sulfur compound, has small studies in rosacea (as a cream) and in skin ageing (taken by mouth); and the garlic family's allyl sulfur compounds (allicin, diallyl sulfide) have measurable anti-inflammatory effects on skin. This deep-dive walks through the keratin biochemistry, the dermatological evidence for sulfur in acne and psoriasis, the Dead Sea protocols, the MSM trials, and practical use.
Table of Contents
- Keratin: The Disulfide Architecture
- Hair and Nail Strength
- Stratum Corneum and Skin Barrier
- Topical Sulfur: 2000 Years of Use
- MSM Trials for Rosacea and Photoaging
- Dead Sea Sulfur Balneotherapy for Psoriasis
- Garlic Allyl-Sulfur Compounds and Skin
- Wound Healing and Tissue Regeneration
- Dietary Support for Skin Sulfur
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Keratin: The Disulfide Architecture
Keratin is a family of fibrous structural proteins that comprise the bulk of the cornified envelope of skin, the entire substance of hair and nail, and the protective lining of mucosal surfaces. Two broad classes exist: soft keratin (found in the stratum corneum of skin) with moderate disulfide cross-linking, and hard keratin (found in hair, nail, hoof, and horn) with extreme disulfide cross-link density.
The mechanical properties of keratin derive almost entirely from its cysteine content and the consequent disulfide bond density. A single hair fiber contains approximately 14% cysteine by mass; in human nail the figure approaches 9%; in stratum corneum cornified envelope around 4%. Each pair of cysteine residues that finds each other across adjacent keratin chains forms a covalent disulfide bond (-S-S-) that locks the two chains in their assembled configuration. The result is a fiber whose tensile strength rivals copper wire of the same diameter.
Several practical observations follow directly from this biochemistry:
- Permanent waving and chemical straightening — both procedures work by chemically reducing the disulfide bonds (breaking the cross-links), reshaping the hair, then re-oxidizing to reform the bonds in the new configuration. This is destructive chemistry that damages cysteine residues with repeated use.
- Bleach and oxidative damage — hydrogen peroxide and ammonia-based hair dyes oxidize sulfur to sulfonic acid, breaking disulfide bonds irreversibly. This is why bleached hair becomes brittle and porous — the sulfur architecture is partially destroyed.
- Burning hair smell — the characteristic odor is sulfur dioxide and hydrogen sulfide released from the breakdown of cysteine disulfides. The same odor distinguishes burning hair, feather, hoof, and horn from burning skin or fat.
- Dietary protein restriction and hair changes — chronic dietary protein deficiency reduces keratin synthesis and shifts hair to thinner, weaker fibers. The cysteine and methionine in the diet are the structural substrate.
Hair and Nail Strength
The disulfide bond density of hair and nail is one of the highest of any biological structure. This is also why hair and nail are among the first tissues to show stigmata of malnutrition: protein-energy malnutrition causes the well-described "flag sign" (alternating bands of normal and depigmented hair reflecting recent protein deficiency), zinc deficiency causes brittle nails with Beau's lines, and biotin deficiency causes nail splitting and hair loss.
- Disulfide bond density determines mechanical strength — the tensile strength of hair and nail is directly proportional to their disulfide bond content. Sulfur deficiency results in brittle, weak keratinized structures that fracture under normal mechanical stress.
- Cysteine as building block — the cysteine in hair and nail keratin must come from somewhere. The body cannot synthesize cysteine de novo from carbon and nitrogen alone — it requires the sulfur from dietary methionine (via trans-sulfuration) or dietary cysteine directly.
- L-cysteine and hair trials — small trials of L-cysteine 1500-2000 mg/day combined with B-vitamins show improvement in hair fiber diameter and shedding rates over 3-6 months, particularly in women with telogen effluvium and diffuse alopecia.
- Biotin (vitamin B7) and keratin synthesis — biotin contains a sulfur-bearing ring structure and is itself a sulfur compound. Biotin deficiency causes nail brittleness, hair thinning, and seborrheic dermatitis. A 2016 study (Trüeb) found biotin deficiency in 38% of women complaining of hair loss; its author rejects giving oral biotin to such women indiscriminately unless deficiency has been shown by history, examination, a serum biotin test and the exclusion of other causes of hair loss.
- MSM and hair growth — small trials of MSM 1-3 g/day suggest modest benefit for hair growth rate and fiber thickness, possibly through increased keratin substrate provision and reduced scalp inflammation.
Stratum Corneum and Skin Barrier
The skin's outermost layer — the stratum corneum — is built from terminally differentiated keratinocytes (now called corneocytes) embedded in a lipid matrix of ceramides, cholesterol, and free fatty acids. The corneocyte itself is a flattened cell with a tough cornified envelope built largely of cross-linked cysteine-rich proteins (involucrin, loricrin, small proline-rich proteins) and surrounding keratin filaments.
- Cornified envelope — the proteins of the cornified envelope are cross-linked by transglutaminases (forming isopeptide bonds) and by sulfhydryl oxidation (forming disulfide bonds). Sulfur is structurally required for the latter.
- Ceramide synthesis — while ceramides themselves do not contain sulfur, their synthesis depends on sphinganine (derived from serine and palmitoyl-CoA), and serine availability is intertwined with sulfur amino acid metabolism via the methylation cycle.
- Filaggrin and natural moisturizing factor — filaggrin, the protein that bundles keratin filaments in the stratum corneum, is broken down during corneocyte maturation into amino acids that form the skin's natural moisturizing factor. Cysteine residues from this breakdown contribute to the antioxidant pool of the stratum corneum.
- Glutathione in the epidermis — epidermal glutathione protects keratinocytes from ultraviolet-induced oxidative damage and supports the redox-dependent steps of stratum corneum maturation. Skin glutathione depletion (from oxidative stress, methylation impairment, or cysteine restriction) impairs barrier function.
- Sulfated heparan and dermatan glycosaminoglycans — the dermis contains sulfated glycosaminoglycans (GAGs) that contribute to skin hydration and elasticity. These follow the same sulfation chemistry as cartilage chondroitin sulfate, which depends on the sulfur donor 3'-phosphoadenosine-5'-phosphosulfate (PAPS).
Topical Sulfur: 2000 Years of Use
Yellow elemental sulfur applied topically has been a dermatological staple since at least the time of Pliny the Elder (1st century CE), who described its use for scabies. It remains in modern formularies for several conditions:
- Acne vulgaris — precipitated sulfur 2-10% in lotion or cream form has been a dermatology staple for over a century. Mechanism: keratolytic action (loosens corneocyte adhesion), mild antibacterial effect against Cutibacterium acnes, and reduction of sebum oxidation. Often combined with sodium sulfacetamide (a sulfa-class antibiotic) as a 10/5 sulfur/sulfacetamide preparation. Generally well tolerated; can be irritating in higher concentrations.
- Rosacea — sulfur (often as sodium sulfacetamide-sulfur 10/5 wash or cream) is one of the few topical agents with consistent evidence for papulopustular rosacea. Effects on the inflammatory papules and pustules are modest but real; less effective for the persistent erythema and telangiectasia components.
- Seborrheic dermatitis — sulfur 3-5% in shampoo or scalp lotion, often combined with salicylic acid, helps the scaling and inflammation. Selenium sulfide shampoo uses a related chemistry on the same condition.
- Scabies — precipitated sulfur 5-10% in petrolatum is a long-used option for scabies in infants under 2 months and in pregnant women (where permethrin and ivermectin are used with caution or not at all). The 2017 European scabies guideline lists permethrin 5% cream, oral ivermectin and benzyl benzoate 25% lotion as the recommended treatments, and sulfur 6-33% cream, ointment or lotion as an alternative treatment. Three nightly applications of sulfur ointment provide cure rates comparable to permethrin. A 2022 retrospective study from one clinic in Turkey compared 10% sulfur ointment with 5% permethrin cream and found the sulfur ointment significantly more effective (p<0.001); the authors raise resistance to permethrin as a possible reason for permethrin's unexpectedly low success rate. The infant safety report on skin-applied sulfur is under Cautions below.
- Tinea versicolor — the same selenium sulfide shampoo formulations effective for seborrheic dermatitis also treat tinea versicolor (the superficial Malassezia yeast infection of the trunk).
- Mechanism of action — elemental sulfur is keratolytic (cleaves disulfide bonds in surface keratin, loosening corneocyte adhesion), mildly antibacterial and antifungal (forms pentathionic acid in skin, toxic to microorganisms), and anti-pruritic. Modern combination products often add salicylic acid or sodium sulfacetamide for synergy.
MSM Trials for Rosacea and Photoaging
Beyond topical elemental sulfur, oral and topical MSM has emerging dermatology evidence:
- Rosacea (Berardesca 2008) — a 1-month double-blind, placebo-controlled study of 46 patients with stage I-III rosacea, using a topical preparation of MSM combined with silymarin, showed significant improvement in skin redness (erythema), papules, itching, hydration and skin colour. The authors saw the clearest benefit in the erythemato-telangiectatic subtype (persistent redness with visible small blood vessels). The combination has been incorporated into several commercial rosacea creams.
- Photoaging (Muizzuddin 2022) — a 16-week study of oral MSM in two parts. In Part I, 20 people took 3 g/day of MSM or a placebo; the MSM group had fewer facial wrinkles and less skin roughness than the placebo group (p<0.05). In Part II, 63 people took 1 g or 3 g a day, with improvement from baseline in facial wrinkles, skin firmness, elasticity and hydration; the authors found the 1 g/day dose already effective.
- Skin elasticity and collagen — the proposed mechanism for MSM's anti-aging effect is provision of sulfur substrate for connective tissue maintenance plus systemic anti-inflammatory action via suppression of nuclear factor kappa B (NF-kB). Direct evidence for increased dermal collagen content is limited but biologically plausible.
- Allergies and allergic skin conditions — oral MSM has been studied in seasonal allergic rhinitis with modest benefit; some patients with allergic skin conditions (chronic urticaria, atopic dermatitis flares) report improvement with oral MSM 1-3 g/day, though large randomized controlled trials (RCTs) are lacking.
- Doses studied — the oral MSM skin study above used 1 g or 3 g a day in total, over 16 weeks. Topical MSM 5-10% in a cream base is used in rosacea and photoaging applications.
Dead Sea Sulfur Balneotherapy for Psoriasis
The Dead Sea (-430 m elevation, the lowest point on land, on the Israel-Jordan border) has been a destination for psoriasis sufferers for centuries. The therapeutic mechanism combines several elements unique to that location:
- Filtered ultraviolet-B — the 430-meter atmospheric column above the Dead Sea filters most of the burning ultraviolet-B wavelengths, allowing prolonged sunbathing with reduced sunburn risk and accumulated phototherapeutic dose.
- Highly mineralized water — Dead Sea water contains roughly 10-fold the salt concentration of ocean water, with high magnesium, potassium, calcium, and bromide content plus sulfur compounds from the regional geology.
- Sulfur springs (En Bokek, En Gedi) — several natural sulfur springs adjacent to the Dead Sea contain hydrogen sulfide at therapeutic concentrations (10-50 mg/L). Bathing in these springs at 35-40°C for 20-30 minutes daily is the core of "balneotherapy" protocols.
- Psoriasis clinical outcomes — a 2012 review of the files of 605 patients treated with Dead Sea climatotherapy (Harari 2012) found that 74% of patients whose psoriasis began before age 40 reached PASI 95 (a 95% improvement in the Psoriasis Area and Severity Index), against 62% of those whose psoriasis began after age 40. This was a look back at patient records, not a controlled trial. The combined effect of ultraviolet-B, mineral baths, and sulfur balneotherapy exceeds either component alone.
- Mechanism of sulfur balneotherapy — transcutaneous absorption of H2S and inorganic sulfur compounds modulates local skin inflammation, reduces keratinocyte hyperproliferation, and improves skin barrier function. The exact molecular mechanism is debated but the clinical effect is reproducible.
- What the controlled trials show — a 2020 Cochrane review of indoor salt-water baths followed by artificial ultraviolet-B light found 8 randomized trials, all in Europe. It judged 7 of the 8 at high risk of bias, and commercial spa or salt companies sponsored 3 of them. In 2 trials (278 people), salt bath plus ultraviolet-B helped more people reach a 75% improvement in the PASI score than ultraviolet-B alone (risk ratio 1.71), but the reviewers rated this low-certainty evidence and drew no clear conclusion. A 2012 systematic review of Dead Sea treatments credits the benefit in psoriasis to the special sunlight of the Dead Sea and to bathing in its water; it found no rise in skin cancer, though sun damage to the skin (actinic damage) appeared to be increased in people treated there.
- Atopic dermatitis — Dead Sea balneotherapy also benefits atopic dermatitis, though with smaller effect size than psoriasis.
- Other sulfur springs worldwide — Aix-les-Bains and Saint-Gervais in France, Lavey-les-Bains in Switzerland, Beppu and Kusatsu in Japan, and Kangal in Turkey all have psoriasis treatment programs based on similar sulfur balneotherapy principles, though without the Dead Sea ultraviolet (UV) advantage.
Garlic Allyl-Sulfur Compounds and Skin
Garlic and the allium family (onions, leeks, shallots, chives) accumulate distinctive organosulfur compounds that contribute both to their characteristic flavor and to a range of pharmacological effects with dermatologic relevance.
- Alliin and allicin — intact garlic contains alliin (an unstable sulfoxide precursor); when garlic tissue is crushed, the enzyme alliinase converts alliin to allicin, the reactive thiosulfinate that gives crushed garlic its smell and most of its biological activity.
- Allicin antimicrobial action — allicin has broad-spectrum antimicrobial activity against gram-positive and gram-negative bacteria, fungi (including dermatophytes and Candida), and viruses. Direct topical application of allicin to skin lesions has measurable antimicrobial effect, though irritation limits practical use.
- Diallyl sulfide and diallyl disulfide — the lipid-soluble degradation products of allicin that persist after cooking and are absorbed systemically. These compounds modulate phase I and phase II detoxification enzymes (inducing glutathione S-transferase (GST), suppressing cytochrome P450 2E1, CYP2E1) and reduce chemical carcinogenesis in animal skin cancer models.
- S-allyl cysteine (SAC) — the dominant organosulfur compound in aged garlic extract. Water-soluble, stable, and absorbed orally with good bioavailability. SAC has antioxidant, anti-inflammatory, and immunomodulatory effects without the gastrointestinal (GI) irritation of fresh garlic.
- Garlic for tinea pedis and corporis — ajoene (an allicin metabolite) at 0.4-1% in topical preparations has trial evidence for tinea pedis (athlete's foot) and tinea corporis (ringworm), comparable to terbinafine 1% cream in small studies. In a double-blind study of 70 soldiers with athlete's foot (47 were evaluated at the end), one week of twice-daily treatment gave a fungal cure 60 days later in 100% with 1% ajoene, 72% with 0.6% ajoene and 94% with 1% terbinafine. In a randomized study of 60 soldiers with groin and body ringworm (tinea cruris and tinea corporis), 30 days after treatment 77% had healed with 0.6% ajoene gel and 75% with 1% terbinafine cream.
- Garlic and warts — folk medicine application of crushed garlic clove to plantar warts has anecdotal support and some open-label trial data, though irritation and chemical burns from prolonged contact are common adverse effects.
- Onion extract for scars — onion extract (Allium cepa) in commercial onion-extract scar gels and creams has mixed randomized controlled trial evidence for hypertrophic scars and keloids; the active components are believed to be quercetin glycosides plus organosulfur compounds.
For more on garlic's broader medicinal applications, see our Garlic page.
Wound Healing and Tissue Regeneration
- Collagen synthesis — cysteine residues in the C-terminal propeptides of procollagen form intrachain disulfide bonds essential for proper triple-helix folding during collagen biosynthesis. Wound healing requires substantial new collagen synthesis, and adequate sulfur amino acid supply is required.
- Glutathione and oxidative protection — healing tissue is metabolically active and vulnerable to oxidative damage. Glutathione (sulfur-dependent) provides essential antioxidant protection during the proliferative and remodeling phases.
- Fibroblast proliferation — cysteine availability supports fibroblast proliferation and matrix synthesis. In vitro, fibroblast cultures grow faster in cysteine-supplemented media; in vivo, marginal protein intake delays wound healing.
- Burn recovery and severe wounds — major burns dramatically increase methionine and cysteine requirements due to the synthesis demands of new tissue. Specialized enteral formulas for burn patients often include extra sulfur amino acids.
- Post-surgical recovery — adequate protein intake with sulfur amino acid content (1.0-1.5 g/kg/day for most adults, higher for the elderly) supports post-surgical wound healing and tissue regeneration.
Dietary Support for Skin Sulfur
- Eggs — the single richest readily-available dietary source of cysteine and methionine. The yolk also provides choline (a methylation cofactor) and biotin (a sulfur-containing vitamin). Two large eggs (about 100 g) provide about 272 mg cystine (the paired form of cysteine) and 380 mg methionine, according to USDA FoodData Central.
- Allium vegetables — garlic, onions, leeks, shallots, chives provide both dietary sulfur amino acids and the organosulfur compounds discussed above.
- Cruciferous vegetables — broccoli, cabbage, Brussels sprouts, kale, cauliflower, watercress contain glucosinolates that hydrolyze to isothiocyanates (sulforaphane being the most studied). These compounds induce phase II detoxification enzymes and support glutathione synthesis.
- Animal protein — meat, poultry, fish provide concentrated methionine and cysteine. Fish provides additional skin support through omega-3 fatty acids.
- Whey and casein protein — both are rich in sulfur amino acids; whey is somewhat higher in cysteine, casein higher in methionine. Whey is often described as the preferred substrate for glutathione synthesis support.
- Brazil nuts and seeds — methionine content is high in Brazil nuts, sesame seeds, hemp seeds. A small handful daily provides supportive intake.
- Legumes — lentils, beans, chickpeas provide moderate sulfur amino acids; lower density than animal sources but still meaningful for vegetarian diets.
- N-acetylcysteine (NAC) supplementation for skin concerns — N-acetylcysteine supplies cysteine directly for glutathione synthesis; 600-1200 mg/day is the dose range commonly described for skin concerns.
Cautions
- Topical sulfur irritation — concentrations above 10% can cause skin irritation, contact dermatitis, and (rarely) chemical burns. Lower strengths of 2-5% are the usual starting preparations.
- Sulfur skin staining — precipitated sulfur preparations are bright yellow and can stain clothing, towels, and bedding, which is why overnight applications are usually made with washable bedding.
- Allergic contact dermatitis to sulfa drugs — patients with documented sulfonamide antibiotic allergy may also react to sodium sulfacetamide topical preparations. A patch test on a small area shows a reaction before the product is spread widely.
- Dead Sea climatotherapy contraindications — pregnant women, severe cardiovascular disease, photosensitivity disorders, history of skin cancer, lupus, and porphyria are all relative or absolute contraindications.
- Garlic topical burns — prolonged direct contact of crushed garlic with skin causes second-degree chemical burns, particularly under occlusion. Short contact of 10-20 minutes and dilution in a carrier are the measures described to lower this risk.
- MSM and bleeding risk — theoretical antiplatelet effect; modest. A 1-week pause before planned surgery is sometimes described as a precaution.
- Excess biotin and lab interference — high-dose biotin supplementation interferes with several common laboratory assays (thyroid function tests, troponin, hormones) that use biotin-streptavidin chemistry. A pause of about 48 hours before a blood draw is commonly described to prevent this interference.
- Absorption of skin-applied sulfur and infant safety — a 1988 review (Lin, “Sulfur revisited”) states that about 1% of sulfur applied to the skin is absorbed into the body. Side effects are uncommon and mostly limited to the skin, but deaths have been reported in infants after sulfur was applied over large areas of skin.
This content is provided for informational purposes only and does not constitute medical advice.
Key Research Papers
- Lin AN, Reimer RJ, Carter DM. (1988). Sulfur revisited. Journal of the American Academy of Dermatology. — PubMed PMID: 2450900
- Berardesca E, Cameli N, Cavallotti C, Levy JL, Piérard GE, de Paoli Ambrosi G. (2008). Combined effects of silymarin and methylsulfonylmethane in the management of rosacea: clinical and instrumental evaluation. Journal of Cosmetic Dermatology. — PubMed PMID: 18254805
- Muizzuddin N, Benjamin R. (2022). Beauty from within: Oral administration of a sulfur-containing supplement methylsulfonylmethane improves signs of skin ageing. International Journal for Vitamin and Nutrition Research. — PubMed PMID: 32083522
- Even-Paz Z, Efron D. (2003). Determination of solar ultraviolet dose in the Dead Sea treatment of psoriasis. Israel Medical Association Journal. — PubMed PMID: 12674654
- Harari M, Czarnowicki T, Fluss R, Ruzicka T, Ingber A. (2012). Patients with early-onset psoriasis achieve better results following Dead Sea climatotherapy. Journal of the European Academy of Dermatology and Venereology. — PubMed PMID: 21575063
- Peinemann F, Harari M, Peternel S, Chan T, Chan D, Labeit AM, Gambichler T. (2020). Indoor salt water baths followed by artificial ultraviolet B light for chronic plaque psoriasis. Cochrane Database of Systematic Reviews. — PubMed PMID: 32368795
- Katz U, Shoenfeld Y, Zakin V, Sherer Y, Sukenik S. (2012). Scientific evidence of the therapeutic effects of dead sea treatments: a systematic review. Seminars in Arthritis and Rheumatism. — PubMed PMID: 22503590
- Matz H, Orion E, Wolf R. (2003). Balneotherapy in dermatology. Dermatologic Therapy. — PubMed PMID: 12919115
- Trumbore MW, Goldstein JA, Gurge RM. (2009). Treatment of papulopustular rosacea with sodium sulfacetamide 10%/sulfur 5% emollient foam. Journal of Drugs in Dermatology. — PubMed PMID: 19271381
- Gupta AK, Nicol K. (2004). The use of sulfur in dermatology. Journal of Drugs in Dermatology. — PubMed PMID: 15303787
- Salavastru CM, Chosidow O, Boffa MJ, Janier M, Tiplica GS. (2017). European guideline for the management of scabies. Journal of the European Academy of Dermatology and Venereology. — PubMed PMID: 28639722
- Ertugrul G, Aktas H. (2022). Comparison of sulfur ointment and permethrin treatments in scabies. Dermatologic Therapy. — PubMed PMID: 36193643
- Ledezma E, López JC, Marin P, et al. (1999). Ajoene in the topical short-term treatment of tinea cruris and tinea corporis in humans. Randomized comparative study with terbinafine. Arzneimittel-Forschung. — PubMed PMID: 10417874
- Ledezma E, Marcano K, Jorquera A, De Sousa L, Padilla M, Pulgar M, Apitz-Castro R. (2000). Efficacy of ajoene in the treatment of tinea pedis: a double-blind and comparative study with terbinafine. Journal of the American Academy of Dermatology. — PubMed PMID: 11050588
- Ankri S, Mirelman D. (1999). Antimicrobial properties of allicin from garlic. Microbes and Infection. — PubMed PMID: 10594976
- Trüeb RM. (2016). Serum Biotin Levels in Women Complaining of Hair Loss. International Journal of Trichology. — PubMed PMID: 27601860