Procalcitonin Test (PCT): Bacterial Infection and Sepsis Marker
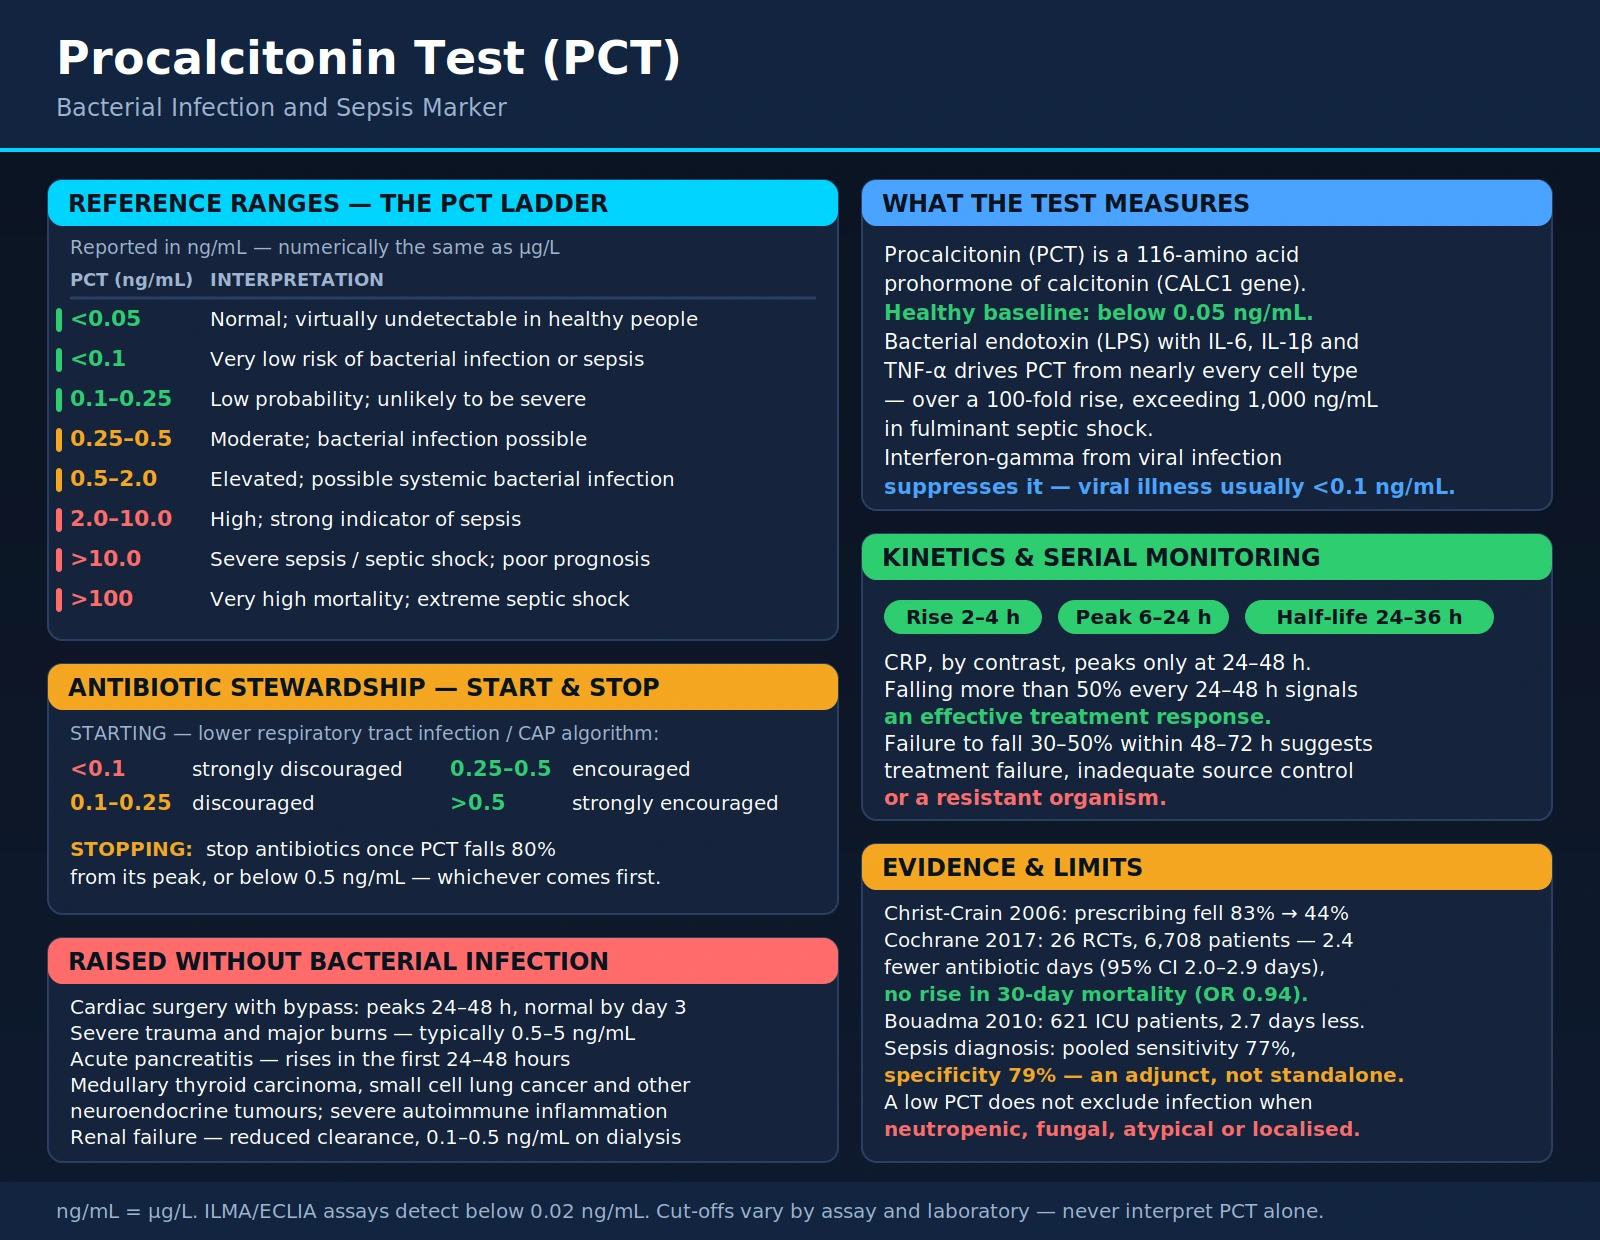
Procalcitonin (PCT) is the precursor protein (prohormone) of the hormone calcitonin. Plasma levels in healthy people are very low — below 0.1 ng/mL in a 2014 review — and rise during severe bacterial infection and sepsis; circulating calcitonin precursors have been reported to rise up to several thousand-fold in human sepsis. In cell-culture experiments interferon-gamma, a cytokine that rises in viral infections, blocked most PCT release from fat cells, which researchers have proposed as one reason PCT rises less in viral than in bacterial infection. The test is studied mainly for two uses: supporting the diagnosis of sepsis, and guiding when antibiotics are started or stopped.
- Overview — What Is Procalcitonin?
- Biochemistry and Production
- Reference Ranges and Interpretation
- Distinguishing Bacterial from Viral Infection
- PCT in Sepsis Diagnosis and Severity
- Antibiotic Stewardship: PCT-Guided Protocols
- False Positives and Limitations
- Key Research Papers
- Connections
- Featured Videos
Overview — What Is Procalcitonin?
In the classical view, the calcitonin gene (CT-I, also written CALC I) is transcribed only in neuroendocrine cells, in particular the C cells of the thyroid (PubMed PMID: 11232031). Biochemically, PCT is the prohormone of calcitonin, but its induction and biological function differ from those of calcitonin, and plasma levels in healthy individuals are below 0.1 ng/mL (PubMed PMID: 24982830).
During infection, production moves outside the thyroid. In hamsters given an Escherichia coli infection, calcitonin messenger RNA appeared uniformly in multiple tissues throughout the body — an animal study (PubMed PMID: 11232031). In human cell cultures, fat cells (adipocytes) increased PCT secretion after exposure to bacterial endotoxin (lipopolysaccharide) or the cytokine IL-1β, and calcitonin messenger RNA was found in adipose tissue from infected patients with markedly raised serum PCT (PubMed PMID: 12960010). The same paper notes that circulating calcitonin precursors, including PCT, increase up to several thousand-fold in human sepsis (PubMed PMID: 12960010). A 2014 review also describes adherent monocytes and the liver as contributors (PubMed PMID: 24982830).
In the same cell-culture work, interferon-gamma (IFN-γ) inhibited IL-1β-driven PCT release by 89%. The authors suggested that this might explain why serum PCT rises less in systemic viral than in bacterial infections (PubMed PMID: 12960010) — a proposed mechanism from laboratory data, not a measurement in patients. PCT was first reported as a marker of sepsis in 1993 by Assicot and colleagues: among 79 children in hospital with suspected infection, 19 with severe bacterial infections had PCT of 6–53 ng/mL at diagnosis, children without signs of infection had less than 0.1 ng/mL, and 18 of 21 children with viral infections had values within or slightly above the normal range (0.1–1.5 ng/mL). Mature calcitonin was normal in every child (PubMed PMID: 8094770).
Biochemistry and Production
The 2014 review describes PCT as a chain of 114–116 amino acids; diagnostic tests measure the calcitonin/N-ProCT part of the protein, a fragment of the full chain. Its induction is more tightly regulated than that of cytokines: stimulated whole blood produces no significant PCT, while various tissues do during sepsis, and in a baboon endotoxin-shock model the PCT response was significantly smaller after the liver was removed (PubMed PMID: 24982830).
Kinetics: the same review gives the timing. PCT induction lags approximately 2 to 4 hours behind the onset of sepsis, peak levels occur at 24 to 48 hours, and after the peak the concentration declines with a 50% plasma-disappearance time of roughly 1 to 1½ days. In severe kidney dysfunction elimination may be prolonged, but the review states that PCT does not accumulate (PubMed PMID: 24982830). A separate review states that current assays can detect rises within 4 to 6 hours of the start of infection (PubMed PMID: 20421436).
The 2014 review compares PCT with other markers (PubMed PMID: 24982830):
- C-reactive protein (CRP): described as slower — the rise to peak may take several days and the decline up to one or two weeks — and as elevated after both minor and major surgery and other trauma and inflammation; the review considers CRP not a useful marker in the intensive care unit (ICU).
- Interleukin-6 and other cytokines: react immediately to severe systemic inflammation and high levels correlate with severity, but they lack specificity and peak levels may change rapidly without clinical correlation.
- Serial PCT: the course of PCT over time, rather than one absolute value, is described as what affects prognosis — continuously declining levels indicate a better prognosis even after very high peaks, a persistent increase or failure to decline has been related to higher mortality, and as a rule of thumb a decline of more than 30% per day indicates significant improvement, consistent with PCT’s natural plasma disappearance rate.
Reference Ranges and Interpretation
Results are reported in ng/mL; several of the trials below write the same cut-offs in µg/L (1 ng/mL equals 1 µg/L). There is no single universal ladder of cut-offs. The thresholds below are the ones stated in a 2014 review (PubMed PMID: 24982830), which presents them as interpretive guides, not diagnoses:
| PCT Level (ng/mL) | What the 2014 review states |
|---|---|
| <0.1 | Plasma level in healthy individuals |
| ≤0.2 | A useful reference range to exclude sepsis and systemic inflammation |
| <0.25 to <0.5 | Normal or very low values with a high negative predictive value to rule out severe systemic inflammation or sepsis |
| ≥0.5 | Interpreted as abnormal; the cut-off that suggests sepsis |
| >0.5 to >2 | High positive predictive value to rule in sepsis, severe sepsis or septic shock |
| >2 | Elevated: a sign of alarm indicating a high risk of organ dysfunction from systemic inflammation |
| >10 | Highly elevated: the same alarm; high levels are usually found in severe sepsis and septic shock |
The review adds that elevations without sepsis are usually not very high (<2 ng/mL) but can exceed 2–10 ng/mL in certain conditions (listed under limitations below), that a local bacterial infection does not induce significant amounts of PCT, and that PCT limits antibiotic duration only when levels are interpreted together with clinical signs and conventional diagnostic methods (PubMed PMID: 24982830).
Distinguishing Bacterial from Viral Infection
The most studied use of PCT outside the ICU is in lower respiratory tract infections (LRTI), where trials have tested whether PCT results can reduce antibiotic prescribing without worse outcomes.
In a 2004 single-blinded, cluster-randomised trial in Basel (Christ-Crain et al.), 243 patients admitted with suspected LRTI received standard care or PCT-guided treatment. Serological evidence of viral infection was found in 141 of 175 tested patients (81%). With PCT guidance the adjusted relative risk of antibiotic exposure was 0.49, and clinical and laboratory outcomes were similar in both groups (PubMed PMID: 14987884); a 2014 review summarizes the antibiotic prescription rates as 44% in the PCT group versus 83% in controls (PubMed PMID: 24982830).
The 2006 ProCAP trial (Christ-Crain et al.) randomized 302 patients with suspected community-acquired pneumonia. PCT guidance reduced total antibiotic exposure (relative risk 0.52), antibiotic prescriptions on admission (85% vs 99%) and median treatment duration (5 vs 12 days), and outcome was similar in both groups (PubMed PMID: 16603606).
The larger ProHOSP trial (Schuetz et al., 2009) enrolled 1,359 patients with mostly severe LRTI in the emergency departments of 6 tertiary care hospitals in Switzerland. Combined adverse outcomes within 30 days (death, ICU admission, disease-specific complications or recurrent infection) were similar — 15.4% with PCT guidance vs 18.9% under standard guidelines — while mean antibiotic exposure fell from 8.7 to 5.7 days and antibiotic-associated adverse effects from 28.1% to 19.8% (PubMed PMID: 19738090).
The ProCAP algorithm graded antibiotic use by PCT level (cut-offs in µg/L) (PubMed PMID: 16603606):
- Less than 0.1: antibiotics strongly discouraged
- Less than 0.25: antibiotics discouraged
- Greater than 0.25: antibiotics encouraged
- Greater than 0.5: antibiotics strongly encouraged
In a pre-planned analysis of 545 emergency-department patients with suspected LRTI from two of these Basel trials, PCT separated community-acquired pneumonia from other diagnoses better (area under the curve 0.88) than highly sensitive CRP (0.76) or leukocyte count (0.69), and rose with pneumonia severity (PubMed PMID: 17335562).
For viral illness, the 2014 review states that PCT induction is low when systemic inflammation is due to viral infection (PubMed PMID: 24982830). In COVID-19, a 2020 meta-analysis of four studies found that PCT above the reference range was associated with a nearly 5-fold higher odds of severe disease (odds ratio 4.76); the authors proposed that a substantial rise may reflect bacterial co-infection in patients developing severe disease (PubMed PMID: 32145275).
Not every trial found a reduction. The 2018 ProACT trial (Huang et al.) randomized 1,656 patients with suspected LRTI in 14 U.S. hospitals with high adherence to pneumonia quality measures, enrolling only patients for whom the treating physician was uncertain whether antibiotics were indicated. Providing PCT results with guidance on their interpretation did not reduce antibiotic use (mean antibiotic-days within 30 days 4.2 vs 4.3); adverse outcomes were 11.7% vs 13.1%, meeting the trial’s non-inferiority criterion (PubMed PMID: 29781385).
PCT in Sepsis Diagnosis and Severity
The 2021 Surviving Sepsis Campaign guideline defines sepsis as life-threatening organ dysfunction caused by a dysregulated host response to infection (PubMed PMID: 34599691). Timing of treatment matters: in a retrospective study of 2,731 adults with septic shock in 14 ICUs, each hour of delay in effective antimicrobial therapy over the 6 hours after the onset of persistent or recurrent low blood pressure was associated with an average decrease in survival of 7.6% (PubMed PMID: 16625125).
The 2021 guideline, which updated the 2016 edition (Rhodes et al., PubMed PMID: 28101605), makes two weak recommendations on PCT (PubMed PMID: 34599691):
- Starting antibiotics: for adults with suspected sepsis or septic shock it suggests against using PCT plus clinical evaluation to decide when to start antimicrobials, compared with clinical evaluation alone (very low quality of evidence). Its meta-analysis of three trials (1,769 ICU patients) found no difference in short-term mortality (RR 0.99).
- Stopping antibiotics: for adults with an initial diagnosis of sepsis or septic shock and adequate source control, where the optimal duration is unclear, it suggests using PCT and clinical evaluation to decide when to discontinue antimicrobials, over clinical evaluation alone (low quality of evidence). Its meta-analysis of 14 trials (4,499 patients) suggested improved mortality with PCT (RR 0.89; 95% CI 0.80–0.99) and no effect on ICU or hospital length of stay; the algorithms, monitoring frequency and stopping thresholds differed across trials.
For diagnosis, a systematic review and meta-analysis by Wacker et al. (2013) pooled 30 studies (3,244 patients) of PCT for separating sepsis from non-infectious systemic inflammation in critically ill patients: mean sensitivity 0.77, specificity 0.79, and area under the curve 0.85, with substantial heterogeneity between studies (I² 96%) (PubMed PMID: 23375419).
Other routine markers have been compared for bacteremia. In a Dutch emergency-department study of 92 patients with positive and 92 with negative blood cultures, lymphocytopenia and the neutrophil-lymphocyte count ratio predicted bacteremia better than CRP, white blood cell count and neutrophil count (de Jager et al., 2010; PCT was not among the markers in that comparison) (PubMed PMID: 21034463).
In the ICU, the PRORATA trial (Bouadma et al., 2010) analysed 621 non-surgical patients with suspected bacterial infection. Mortality with PCT guidance was non-inferior at day 28 (21.2% vs 20.4%) and day 60 (30.0% vs 26.1%), and patients in the PCT group had more days without antibiotics by day 28 (14.3 vs 11.6; absolute difference 2.7 days) (PubMed PMID: 20097417).
Antibiotic Stewardship: PCT-Guided Protocols
The stewardship rationale is stated in the trials themselves: the PRORATA investigators wrote that reduced duration of antibiotic treatment might contain the emergence of multidrug-resistant bacteria in ICUs (PubMed PMID: 20097417), and the SAPS investigators described long treatment duration as associated with the development of antimicrobial resistance (PubMed PMID: 26947523).
The Dutch SAPS trial (de Jong et al., 2016) tested a PCT stopping rule in critically ill patients in 15 hospitals: in the PCT group, a non-binding advice to discontinue antibiotics was given if PCT had decreased by 80% or more of its peak value or to 0.5 µg/L or lower. With 761 patients assigned to PCT guidance and 785 to standard care, median antibiotic consumption was 7.5 vs 9.3 daily defined doses and median treatment duration 5 vs 7 days. Mortality at 28 days was 20% vs 25% in the intention-to-treat analysis, and 1-year mortality in the per-protocol analysis was 36% vs 43% (PubMed PMID: 26947523).
The 2017 Cochrane review by Schuetz et al. obtained individual participant data from 26 trials (6,708 participants with acute respiratory infections; 32 trials were eligible). Compared with controls, PCT-guided antibiotic therapy was associated with (PubMed PMID: 29025194):
- Lower 30-day mortality: 286 deaths among 3,336 PCT-guided participants vs 336 among 3,372 controls (adjusted OR 0.83; 95% CI 0.70–0.99)
- A 2.4-day reduction in antibiotic exposure (5.7 vs 8.1 days)
- Fewer antibiotic-related side effects (16.3% vs 22.1%; adjusted OR 0.68)
- No significant difference in treatment failure (23.0% vs 24.9%; adjusted OR 0.90, 95% CI 0.80–1.01) and similar hospital and ICU length of stay
The same patient-level data were published in 2018 in Lancet Infectious Diseases (PubMed PMID: 29037960). The Cochrane authors noted that research is still needed in immunosuppressed patients and in non-respiratory infections (PubMed PMID: 29025194).
Meisner (2014) describes the approach used in the reviewer’s own hospital ICU, based on the PRORATA algorithm (PubMed PMID: 24982830):
- PCT measured daily in critically ill patients from the start of antibiotic treatment
- Days 2–3: success of therapy judged from the PCT course (a decline indicating a response)
- Days 3–6: antibiotics can be discontinued in the majority of patients, using both absolute cut-offs and a kinetic (percentage-fall) rule
- By day 7: a general rule to stop unless specific requirements justify further treatment, with infections such as endocarditis or severe bone infection excluded from the rule
False Positives and Limitations
Conditions other than bacterial infection can raise PCT, and some infections leave it low. Raised PCT without bacterial infection has been reported in:
- Surgery: in 117 patients with a normal postoperative course, PCT was moderately increased above the normal range in 32% after minor and aseptic surgery, 59% after cardiac and thoracic surgery and 95% after intestinal surgery; the authors concluded that postoperative PCT is diagnostically useful only against the usual range for that type of surgery, followed over time (PubMed PMID: 9722037).
- Severe trauma and burns: the 2014 review lists severe trauma among non-infectious causes (PubMed PMID: 24982830). In the 1993 study, PCT in 9 severely burned ICU patients ranged from 0.1 to 120 ng/mL, and its course was closely related to infectious complications and septic episodes (PubMed PMID: 8094770).
- Acute pancreatitis: severe pancreatitis can raise PCT above 2–10 ng/mL; low PCT in acute pancreatitis is associated with a low-risk group, most likely oedematous pancreatitis, and whether antibiotics can be withheld in that setting is described as still under discussion (PubMed PMID: 24982830).
- Other conditions named in the 2014 review: liver transplantation, severe and prolonged cardiogenic shock, heat shock, rhabdomyolysis and certain autoimmune disorders (PubMed PMID: 24982830).
- Medullary thyroid carcinoma (MTC): PCT is studied as a tumour marker for this calcitonin-producing cancer. A 2021 meta-analysis of 11 studies (5,817 patients, 335 with MTC) found pooled sensitivity 0.90 and specificity 1.00 for MTC diagnosis and monitoring; its authors proposed that PCT could replace calcitonin as a standard marker (PubMed PMID: 34382653).
- Kidney failure: elimination may be prolonged in severe renal dysfunction, though the 2014 review states PCT does not accumulate (PubMed PMID: 24982830). A 2022 meta-analysis of 7 studies (1,444 patients on haemodialysis) found pooled sensitivity 0.90 and specificity 0.83 for bacterial infection and reported 1.5 ng/mL as a useful cut-off in this group (PubMed PMID: 35164633).
Situations where PCT may stay low despite infection, as described in the 2014 review (PubMed PMID: 24982830):
- Local infection: local bacterial infection or colonization usually does not induce PCT — for example tonsillitis, minor soft tissue infection, abscess, and even local appendicitis or cholecystitis. In endocarditis PCT can be normal or elevated, and in bacteremia without a systemic inflammatory response it may be low, although bacteremia usually raises PCT significantly.
- Severe immunosuppression: listed among situations where the PCT-guided concept does not apply; whether antibiotics can be withheld in feverish neutropenic patients with normal PCT is described as still under discussion.
- Slow-growing or low-response infections: osteomyelitis, tuberculosis, infection with atypical microbes and sometimes fungal infection are listed as infections with low immunogenic responses. A separate review states that PCT is produced in response to pathogenic bacteria, fungi and some parasites (PubMed PMID: 20421436).
The 2014 review states that when the clinical picture suggests possible sepsis but PCT is not raised, patients are still treated for sepsis at first and PCT is repeated over the next one to two days; it also notes that an unexpected deterioration cannot be predicted even by PCT (PubMed PMID: 24982830). Decisions about testing and antibiotics belong with a clinician.
Key Research Papers
- Assicot M, Gendrel D, Carsin H, Raymond J, Guilbaud J, Bohuon C. (1993). High serum procalcitonin concentrations in patients with sepsis and infection. Lancet. 341(8844):515–518. — PubMed PMID: 8094770
- Christ-Crain M, Stolz D, Bingisser R, et al. (2006). Procalcitonin guidance of antibiotic therapy in community-acquired pneumonia: a randomized trial. Am J Respir Crit Care Med. 174(1):84–93. — PubMed PMID: 16603606
- Schuetz P, Christ-Crain M, Thomann R, et al. (2009). Effect of procalcitonin-based guidelines vs standard guidelines on antibiotic use in lower respiratory tract infections: the ProHOSP randomized controlled trial. JAMA. 302(10):1059–1066. — PubMed PMID: 19738090
- Schuetz P, Wirz Y, Sager R, et al. (2017). Procalcitonin to initiate or discontinue antibiotics in acute respiratory tract infections. Cochrane Database Syst Rev. 10:CD007498. — PubMed PMID: 29025194
- de Jong E, van Oers JA, Beishuizen A, et al. (2016). Efficacy and safety of procalcitonin guidance in reducing the duration of antibiotic treatment in critically ill patients: a randomised, controlled, open-label trial. Lancet Infect Dis. 16(7):819–827. — PubMed PMID: 26947523
- Bouadma L, Luyt CE, Tubach F, et al. (2010). Use of procalcitonin to reduce patients' exposure to antibiotics in intensive care units (PRORATA trial): a multicentre randomised controlled trial. Lancet. 375(9713):463–474. — PubMed PMID: 20097417
- Müller B, Harbarth S, Stolz D, et al. (2007). Diagnostic and prognostic accuracy of clinical and laboratory parameters in community-acquired pneumonia. BMC Infect Dis. 7:10. — PubMed PMID: 17335562
- De Jager CP, van Wijk PT, Mathoera RB, et al. (2010). Lymphocytopenia and neutrophil-lymphocyte count ratio predict bacteremia better than conventional infection markers in an emergency care unit. Crit Care. 14(5):R192. — PubMed PMID: 21034463
- Wacker C, Prkno A, Brunkhorst FM, Schlattmann P. (2013). Procalcitonin as a diagnostic marker for sepsis: a systematic review and meta-analysis. Lancet Infect Dis. 13(5):426–435. — PubMed PMID: 23375419
- Meisner M. (2014). Update on procalcitonin measurements. Ann Lab Med. 34(4):263–273. — PubMed PMID: 24982830
- Huang DT, Yealy DM, Filbin MR, et al. (2018). Procalcitonin-guided use of antibiotics for lower respiratory tract infection. N Engl J Med. 379(3):236–249. — PubMed PMID: 29781385
- Rhodes A, Evans LE, Alhazzani W, et al. (2017). Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock: 2016. Intensive Care Med. 43(3):304–377. — PubMed PMID: 28101605
- Christ-Crain M, Jaccard-Stolz D, Bingisser R, et al. (2004). Effect of procalcitonin-guided treatment on antibiotic use and outcome in lower respiratory tract infections: cluster-randomised, single-blinded intervention trial. Lancet. 363(9409):600–607. — PubMed PMID: 14987884
- Schuetz P, Wirz Y, Sager R, et al. (2018). Effect of procalcitonin-guided antibiotic treatment on mortality in acute respiratory infections: a patient level meta-analysis. Lancet Infect Dis. 18(1):95–107. — PubMed PMID: 29037960
- Evans L, Rhodes A, Alhazzani W, et al. (2021). Surviving sepsis campaign: international guidelines for management of sepsis and septic shock 2021. Intensive Care Med. 47(11):1181–1247. — PubMed PMID: 34599691
- Kumar A, Roberts D, Wood KE, et al. (2006). Duration of hypotension before initiation of effective antimicrobial therapy is the critical determinant of survival in human septic shock. Crit Care Med. 34(6):1589–1596. — PubMed PMID: 16625125
- Müller B, White JC, Nylén ES, et al. (2001). Ubiquitous expression of the calcitonin-i gene in multiple tissues in response to sepsis. J Clin Endocrinol Metab. 86(1):396–404. — PubMed PMID: 11232031
- Linscheid P, Seboek D, Nylen ES, et al. (2003). In vitro and in vivo calcitonin I gene expression in parenchymal cells: a novel product of human adipose tissue. Endocrinology. 144(12):5578–5584. — PubMed PMID: 12960010
- Lippi G, Plebani M. (2020). Procalcitonin in patients with severe coronavirus disease 2019 (COVID-19): a meta-analysis. Clin Chim Acta. 505:190–191. — PubMed PMID: 32145275
- Giovanella L, Garo ML, Ceriani L, et al. (2021). Procalcitonin as an alternative tumor marker of medullary thyroid carcinoma. J Clin Endocrinol Metab. 106(12):3634–3643. — PubMed PMID: 34382653
- Meisner M, Tschaikowsky K, Hutzler A, et al. (1998). Postoperative plasma concentrations of procalcitonin after different types of surgery. Intensive Care Med. 24(7):680–684. — PubMed PMID: 9722037
- Tao M, Zheng D, Liang X, et al. (2022). Diagnostic value of procalcitonin for bacterial infections in patients undergoing hemodialysis: a systematic review and meta-analysis. Ren Fail. 44(1):81–93. — PubMed PMID: 35164633
- Gilbert DN. (2010). Use of plasma procalcitonin levels as an adjunct to clinical microbiology. J Clin Microbiol. 48(7):2325–2329. — PubMed PMID: 20421436