Chen Pi for Digestion and Appetite
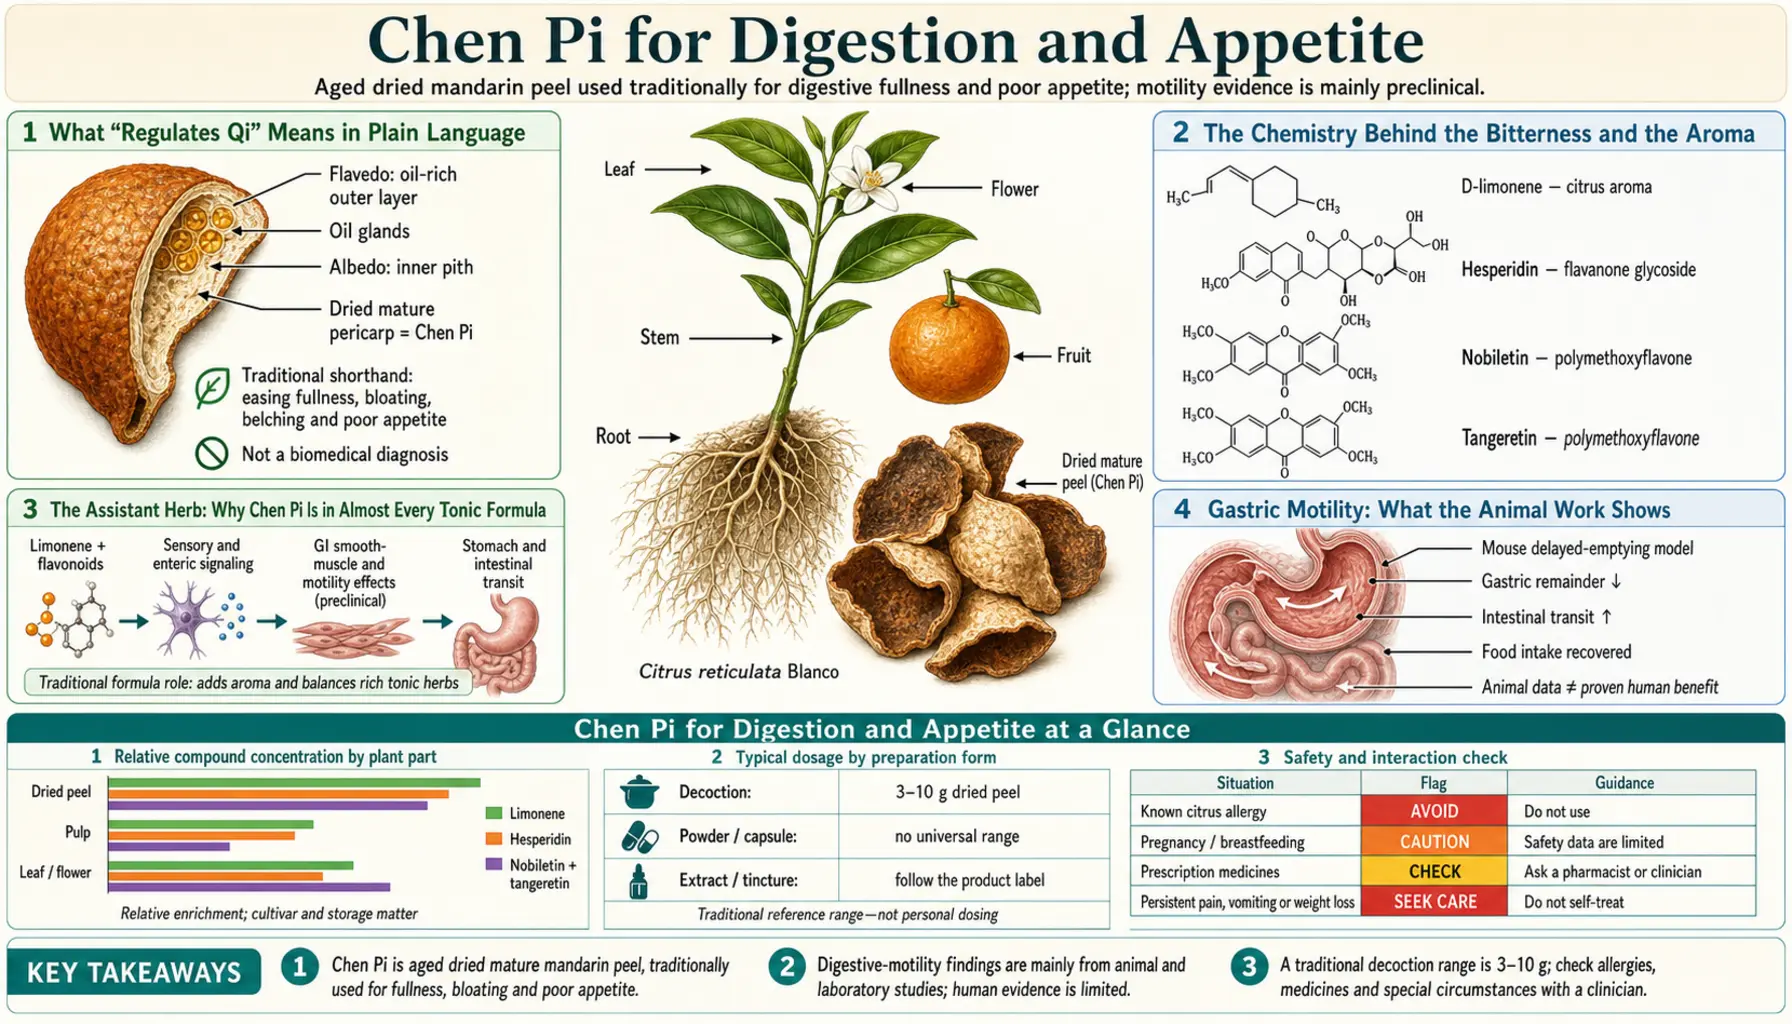
If chen pi has one job in the Chinese materia medica, this is it. Aged mandarin peel — Pericarpium Citri Reticulatae, the dried ripe peel of Citrus reticulata — is a digestive herb first and everything else second. It is what you add to a heavy meal, a rich tonic, or a stomach that feels stuffed and sluggish. This article explains the pharmacology behind that reputation, what the human evidence does and does not support, and the one practical caution that most write-ups omit entirely.
Table of Contents
- What “Regulates Qi” Means in Plain Language
- The Chemistry Behind the Bitterness and the Aroma
- The Assistant Herb: Why Chen Pi Is in Almost Every Tonic Formula
- Gastric Motility: What the Animal Work Shows
- Bitters, Aromatics and the Cephalic Phase
- Bloating, Gas and Functional Dyspepsia
- The Human Evidence, Honestly Graded
- Doses, Decoctions and Everyday Cooking
- Reflux and Other Cautions
- Key Research Papers
- Connections
- Featured Videos
What “Regulates Qi” Means in Plain Language
Classical texts say chen pi regulates qi, dries dampness, transforms phlegm, and harmonizes the middle burner. That sentence is opaque unless you know the code, so here it is in ordinary words.
Regulating qi in the digestive context describes a herb that helps things move in the right direction — downward, out of the stomach and along the gut — and relieves the specific miserable sensation of stuff sitting there. The classical symptom picture is distension, fullness after a small amount of food, belching, a bloated abdomen that is uncomfortable rather than sharply painful, and appetite that has gone flat.
Drying dampness describes a herb used for heaviness, a thick coating on the tongue, loose stool, and the water-logged feeling that traditional practitioners associated with a sluggish digestive system. Modern readers can translate this loosely as “reduces the boggy, sluggish, over-full quality” without accepting the underlying physiology as literal anatomy.
Harmonizing the middle burner means settling the stomach and spleen — nausea, queasiness, the sense that food is not being handled properly.
None of these terms are diagnoses in the modern sense, and we are not going to pretend they map cleanly onto gastroenterology. But the symptom cluster they describe — postprandial fullness, early satiety, bloating, mild nausea, poor appetite — is almost exactly the modern Rome criteria description of functional dyspepsia. That is a genuinely interesting convergence, and it is the reason chen pi keeps showing up in modern gastroenterology research from Japan, China and Korea.
The Chemistry Behind the Bitterness and the Aroma
Two fractions do the work, and they behave very differently.
The essential oil is 60–90% d-limonene, with γ-terpinene, myrcene and linalool making up most of the rest. It is volatile, fat-soluble, and it is what you smell when you snap a piece of good peel. Volatile aromatics of this class have a long-documented carminative effect: they relax gastrointestinal smooth muscle in a dose-dependent way in isolated tissue preparations, which reduces spasm and allows trapped gas to move. This is the same broad mechanism that makes peppermint oil useful in irritable bowel syndrome and fennel a traditional remedy for colic. Chen pi is not as potent an antispasmodic as either, but it is in the same pharmacological family.
The flavonoid fraction is dominated by hesperidin — the pharmacopeial marker, required at roughly 3.5% minimum — alongside the polymethoxyflavones nobiletin and tangeretin. Flavanone glycosides like hesperidin taste bitter, and bitterness is not incidental here; it is arguably the point. The flavonoids are also the fraction that survives aging and becomes proportionally more concentrated as the volatile oil evaporates, which is discussed in detail in Aging, Grades and Quality.
There is a nice symmetry in this: fresh peel is mostly aroma with a harsh, almost acrid edge; aged peel has less aroma, but rounder bitterness and a proportionally richer flavonoid load. Traditional practice arrived at “age it for at least a year” long before anyone could run a gas chromatograph, and the chemistry turns out to support the preference — not because aging creates new medicine, but because it removes the harsh top notes and shifts the balance.
The Assistant Herb: Why Chen Pi Is in Almost Every Tonic Formula
Chinese formula construction assigns roles: a chief herb, deputies, assistants, and an envoy. Chen pi is the archetypal assistant — and its assigned job is unusually easy to explain to a modern reader.
Tonic formulas are heavy. They are built from sweet, dense, mucilaginous roots — rehmannia, astragalus, codonopsis, licorice — and the classical complaint about them, recorded for centuries, is that they cause bloating, a stuffed feeling, and loss of appetite in exactly the weakened patients they were meant to strengthen. The traditional phrase is that they are “cloying” or that they “obstruct the middle.”
Chen pi was the standard fix. Adding a few grams of aromatic, bitter, gently moving peel to a rich formula was believed to keep the tonic from sitting heavily. You can see this in the classical prescriptions:
- Liu Jun Zi Tang (Six Gentlemen Decoction) — the Four Gentlemen tonic base plus chen pi and pinellia, specifically for weak digestion with phlegm and fullness. Its Japanese Kampo equivalent, rikkunshito, is the single most-studied chen pi–containing formula in modern medicine.
- Bu Zhong Yi Qi Tang — the great qi-raising tonic, with chen pi included to keep the sweet tonic herbs from causing distension.
- Ping Wei San (Calm the Stomach Powder) — chen pi with atractylodes and magnolia bark, for a heavy, damp, over-full stomach.
- Er Chen Tang (Two Aged Herbs Decoction) — chen pi and pinellia, the phlegm formula covered in our lung article.
Notice what this tells you about the herb’s strength. Chen pi is almost never the chief. It is not a powerful drug and traditional practitioners did not treat it as one. It is a facilitator — the thing you add so that the real medicine is tolerated. That is a modest claim, and modest claims are the ones most likely to be true.
Gastric Motility: What the Animal Work Shows
The modern pharmacology of chen pi on the gut is almost entirely preclinical, and honesty requires saying that up front.
The consistent findings across rodent and isolated-tissue studies of Citrus reticulata peel extracts are these. Aqueous and ethanolic extracts modulate contraction in isolated intestinal segments, generally producing relaxation of induced spasm at higher concentrations while low concentrations can enhance spontaneous contractility — a biphasic pattern typical of aromatic carminatives. In whole-animal experiments, peel extracts have been reported to accelerate gastric emptying and small-intestinal transit in models where motility has been artificially slowed, for example by atropine or by stress protocols. Hesperidin and the polymethoxyflavones have separately been shown to influence gut smooth muscle and to have anti-inflammatory effects on intestinal tissue.
The most substantive mechanistic literature actually belongs to rikkunshito rather than chen pi alone. Japanese groups have studied this formula extensively in gastroparesis-like models and in functional dyspepsia, and one of its better-characterized effects involves the appetite hormone ghrelin — the formula appears to enhance ghrelin signalling and to counteract the drop in ghrelin seen with cisplatin chemotherapy and with anorexia models. That is a real and mechanistically specific finding. It is also a finding about an eight-herb formula, not about tangerine peel, and attributing it to chen pi specifically would be overreach. Some of the ghrelin work has been repeated in people: in a 2014 Japanese placebo-controlled trial of rikkunshito, acyl ghrelin (the active form of the hormone) rose only in the rikkunshito group among patients carrying Helicobacter pylori, and in a Korean trial published in 2026 both chen pi–containing formulas tested were followed by falls in des-acyl ghrelin, a result the authors call exploratory. Both trials are described in the human-evidence section below.
So the fair summary is: there is a coherent preclinical story in which chen pi and its constituents make a sluggish gut move a bit better and a spasming gut relax a bit. There is no human trial of chen pi alone demonstrating a change in gastric emptying. If someone tells you chen pi “has been proven to speed digestion,” they are describing rodent data.
Bitters, Aromatics and the Cephalic Phase
There is a second mechanism that is easy to overlook because it is so ordinary: chen pi tastes bitter and smells strongly, and taste and smell are physiologically active.
The cephalic phase of digestion is the body’s anticipatory response to food — salivation, gastric acid secretion, pancreatic enzyme release and gallbladder activity triggered by sight, smell and taste before anything is absorbed. Bitter compounds are potent cephalic-phase stimuli. This is the entire premise of European bitter tonics, of the aperitif tradition, of gentian and wormwood and angostura. Bitter taste receptors (the T2R family) are also expressed in the stomach and intestine, not only on the tongue, and activating them has been shown to influence gut hormone release including ghrelin and CCK.
Chen pi fits this template neatly: bitter, aromatic, taken before or with food, credited with improving appetite. The traditional use and the modern receptor pharmacology point in the same direction, and unlike the polymethoxyflavone story, this mechanism does not require heroic doses. A bitter, aromatic herb in a cup of hot liquid genuinely does something before it is even swallowed.
What it does not do is fix an underlying disease. If appetite has genuinely collapsed — unintentional weight loss, months of poor intake, food avoidance because eating hurts — those are signs of an illness that needs a diagnosis, which a tea does not provide.
Bloating, Gas and Functional Dyspepsia
Bloating is one of the most common and most under-treated digestive complaints, and it is frustrating precisely because there is often nothing structurally wrong. Functional dyspepsia and bloating-predominant irritable bowel syndrome (IBS) are diagnoses of pattern, not of pathology, and the drug options are unimpressive: prokinetics with side-effect ceilings, acid suppression that often does not address the symptom, and antispasmodics.
Aromatic carminatives occupy a real niche here. Peppermint oil has the strongest evidence of the class, with multiple randomized trials in irritable bowel syndrome. Ginger has decent human data on gastric emptying and nausea. Fennel and caraway have long traditional use and some formula-level trial support. Chen pi sits in this family, with the weakest formal evidence and the longest culinary track record.
In practical terms: chen pi is cheap, has a long low-risk culinary record and is traditionally used for postprandial fullness and gassy bloating, and the evidence that exists points to a modest effect. It is not a treatment for small intestinal bacterial overgrowth, coeliac disease, gastroparesis, or gallbladder disease, all of which present with bloating and all of which need a diagnosis.
These signs point to conditions that need a diagnosis rather than a herb, and doctors treat them as warning signs: unintentional weight loss, vomiting, difficulty swallowing, blood in the stool or black stool, iron-deficiency anaemia, a family history of gastrointestinal cancer, new persistent bloating after age 50, or persistent bloating in a woman that does not fluctuate with the menstrual cycle (ovarian cancer is a classic missed diagnosis here).
The Human Evidence, Honestly Graded
Here is the position stated plainly.
| Question | What exists | Grade |
|---|---|---|
| Does chen pi alone relieve bloating in a randomized trial? | No such trial that we can point to | Traditional use only |
| Do chen pi–containing formulas help functional dyspepsia? | Multiple Japanese and Chinese trials of rikkunshito and related formulas, mostly small, several positive; the largest placebo-controlled trial (247 people) did not reach significance on its main measure (33.6% vs 23.8% responders, p = 0.09) | Human, limited — formula-level, not herb-level |
| Does it change gastric emptying? | Rodent and isolated-tissue data; formula-level human data for rikkunshito | Preclinical for chen pi itself |
| Does it stimulate appetite? | Strong traditional record; plausible bitter/cephalic mechanism; ghrelin data at formula level | Plausible, not proven |
| Is it safe at food and decoction doses? | Centuries of daily culinary use across southern China and Vietnam | Reassuring |
The gap between “a formula containing chen pi helped” and “chen pi helped” is the central interpretive problem in this whole field. Classical formulas contain six to twelve herbs. When rikkunshito improves dyspepsia scores, you have learned something about rikkunshito. Attributing the benefit to the peel is a guess.
Two formula trials in detail. The largest placebo-controlled trial of rikkunshito, run at Japanese centres and published in 2014, gave 247 people with functional dyspepsia 2.5 g of rikkunshito or a dummy powder three times a day for 8 weeks. At 8 weeks 33.6% of the rikkunshito group and 23.8% of the placebo group rated themselves as improved overall, a difference that could have been chance (p = 0.09). Upper-stomach pain improved significantly (p = 0.04) and fullness after meals showed a trend (p = 0.06). The effect looked larger in people carrying Helicobacter pylori (40.0% vs 20.5%, p = 0.07), and there were no severe side effects in either group.
A Korean trial published in 2026 assigned 140 people with functional dyspepsia to Yukgunja-tang (the Korean name for Liu Jun Zi Tang), Pyeongwi-san (Ping Wei San) or usual care for 6 weeks. Both formulas lowered the total dyspepsia symptom score more than usual care, the two formulas did about equally well, and there were no serious treatment-related side effects. The authors themselves ask for cautious reading, because the comparison was usual care, not a placebo; only the people assessing the results were blinded (an assessor-blind design).
Doses, Decoctions and Everyday Cooking
Standard decoction dose. The pharmacopeial and clinical range is 3–10 g of dried peel per day, simmered in water. In a multi-herb formula chen pi is usually at the lower end, 3–6 g, because it is an assistant rather than a chief.
Simple tea. The usual method breaks 3–6 g of peel into pieces, rinses it briefly in hot water and discards that first rinse, then steeps it in near-boiling water for 5–10 minutes, or simmers it gently for 10–15 minutes for a stronger extraction. Aged peel takes more heat and time than fresh-dried peel to give up its flavour; a short steep on a good 10-year peel will taste of almost nothing.
An important trade-off. A long open simmer drives off the volatile oil — the aromatic, antispasmodic fraction. A covered pot, or adding the peel in the last few minutes of a longer decoction, preserves more of it. Classical practice reflects this: aromatic herbs are traditionally added late. A lidded pot favours the carminative oil; a longer simmer favours the flavonoids.
In cooking. This is how most people in Guangdong actually consume it: a couple of pieces in a pot of steamed rice, in braised duck or beef, in red bean soup or black bean dessert soup, in congee, in bone broth. Culinary use runs to a gram or two per dish and is best thought of as a seasoning that happens to be a mild digestive.
Powder and extracts. Powdered peel at 1–3 g is used in some patent formulas. Concentrated extracts standardized to hesperidin or polymethoxyflavones are supplements, not chen pi, and their evidence is the extract’s own, not the peel’s — see Polymethoxyflavones and Metabolism for why the extract and the peel are not interchangeable.
Timing. Traditionally taken before or with meals for appetite and fullness. There is no pharmacokinetic reason to insist on this, but it fits the cephalic-phase mechanism and it is how the herb has always been used.
Reflux and Other Cautions
The reflux caution is the practical one, and it is routinely omitted. Concentrated citrus terpenes, d-limonene in particular, can relax the lower oesophageal sphincter — the muscular valve that keeps stomach contents from travelling back up. That is the same property that makes peppermint oil a double-edged tool: excellent for intestinal spasm, capable of worsening heartburn. If you have gastro-oesophageal reflux disease and citrus reliably triggers it, strong chen pi tea may do the same. This effect is unpleasant rather than dangerous, and worth knowing in advance.
Drug interactions, stated precisely. The famous grapefruit–drug interaction is caused by furanocoumarins — bergamottin and 6′,7′-dihydroxybergamottin — which irreversibly inactivate cytochrome P450 3A4 (CYP3A4) in the intestinal wall and can dramatically raise blood levels of statins, some calcium-channel blockers, certain immunosuppressants and others. Grapefruit, pomelo and Seville orange contain them. Mandarin peel largely does not. Chen pi flavonoids can inhibit CYP enzymes in laboratory assays, so some interaction is theoretically possible, but it is a much weaker and far less established concern, and treating chen pi as though it were grapefruit is inaccurate. The theoretical concern matters most for narrow-therapeutic-index drugs broken down by cytochrome P450 3A4, where even a small rise in blood level can matter.
Anticoagulants. Citrus flavonoids show mild antiplatelet activity in the laboratory. At sustained high supplement-level intake there is a theoretical additive bleeding risk with warfarin, direct oral anticoagulants or high-dose aspirin. Culinary and tea-level intake is very unlikely to matter.
Synephrine. Mandarin peel contains trace synephrine, far below the levels in bitter orange (Citrus aurantium) extracts sold for weight loss. Chen pi is not a stimulant and does not carry the cardiovascular concerns that have been raised about concentrated synephrine products.
Pregnancy and breastfeeding. Culinary amounts are traditional and unremarkable, and chen pi appears in classical formulas used for pregnancy nausea. Concentrated extracts and essential oil have not been studied for safety in pregnancy.
Dryness patterns. Traditional practice cautions against long-term high-dose use in people who are already dry — dry cough, dry mouth, night sweats — on the grounds that a drying, moving herb makes that worse. Whether or not one accepts the framework, it is a reasonable reminder that a herb chosen for a wet, heavy, sluggish picture is not automatically right for the opposite one.
Pesticide residue. Peel is the most residue-prone part of any fruit. This is a genuine quality issue and is covered in detail in Aging, Grades and Quality.
Key Research Papers
- Yu X, Sun S, Guo Y, et al. Citri Reticulatae Pericarpium (Chenpi): botany, ethnopharmacology, phytochemistry, and pharmacology of a frequently used traditional Chinese medicine. Journal of Ethnopharmacology. 2018;220:265–282. — PubMed PMID: 29628291 — The standard modern review of the herb.
- Kohlert C, van Rensen I, März R, et al. Bioavailability and pharmacokinetics of natural volatile terpenes in animals and humans. Planta Medica. 2000;66(6):495–505. — PubMed PMID: 10985073 — Why terpene dose and delivery matter so much.
- Mulvihill EE, Burke AC, Huff MW. Citrus flavonoids as regulators of lipoprotein metabolism and atherosclerosis. Annual Review of Nutrition. 2016;36:275–299. — PubMed PMID: 27146015 — Background on the flavonoid fraction.
- Bailey DG, Dresser G, Arnold JM. Grapefruit-medication interactions: forbidden fruit or avoidable consequences? CMAJ. 2013;185(4):309–316. — PubMed PMID: 23184849 — The definitive plain-language account of what actually causes the interaction.
- Paine MF, Widmer WW, Hart HL, et al. A furanocoumarin-free grapefruit juice establishes furanocoumarins as the mediators of the grapefruit juice-felodipine interaction. American Journal of Clinical Nutrition. 2006;83(5):1097–1105. — PubMed PMID: 16685052 — The experiment that pinned the mechanism on furanocoumarins — which mandarin peel largely lacks.
- Stohs SJ, Preuss HG, Shara M. A review of the human clinical studies involving Citrus aurantium (bitter orange) extract and its primary protoalkaloid p-synephrine. International Journal of Medical Sciences. 2012;9(7):527–538. — PubMed PMID: 22991491 — Context for why chen pi is not a stimulant.
- Suzuki H, Matsuzaki J, Fukushima Y, Suzaki F, et al. Randomized clinical trial: rikkunshito in the treatment of functional dyspepsia—a multicenter, double-blind, randomized, placebo-controlled study. Neurogastroenterology and Motility. 2014;26(7):950–961. — PubMed PMID: 24766295
- Lee B, Ha NY, Kwon OJ, Park HJ, et al. Yukgunja-tang and Pyeongwi-san improve functional dyspepsia and modulate ghrelin dynamics: a multicenter randomized controlled trial. Journal of Ethnopharmacology. 2027;373:122335. — PubMed PMID: 42637062
PubMed Topic Searches
- PubMed: Citrus reticulata peel and GI motility
- PubMed: Rikkunshito in functional dyspepsia
- PubMed: Rikkunshito and ghrelin signalling
- PubMed: Gut bitter-taste receptors and hormone release
- PubMed: D-limonene, LES tone and reflux
- PubMed: Hesperidin and intestinal inflammation
- PubMed: Carminative herbs in functional bloating
- PubMed: Ping Wei San and related formulas
- PubMed: Chenpi, appetite and gastric emptying
Connections
- All Herbs
- Chen Pi (Aged Tangerine Peel)
- Chen Pi Benefits
- Chen Pi: History and Traditional Use
- Chen Pi for Phlegm, Cough and the Lungs
- Chen Pi Polymethoxyflavones and Metabolism
- Chen Pi Aging, Grades and Quality
- Hesperidin
- Ginger
- Fennel
- Peppermint
- Atractylodes
- Licorice
- Codonopsis (Dang Shen) — the gentle ginseng substitute heading the Four Gentlemen base and Bu Zhong Yi Qi Tang; it is exactly the sweet tonic chen pi is added to keep from causing distension