Respiratory and Circulation
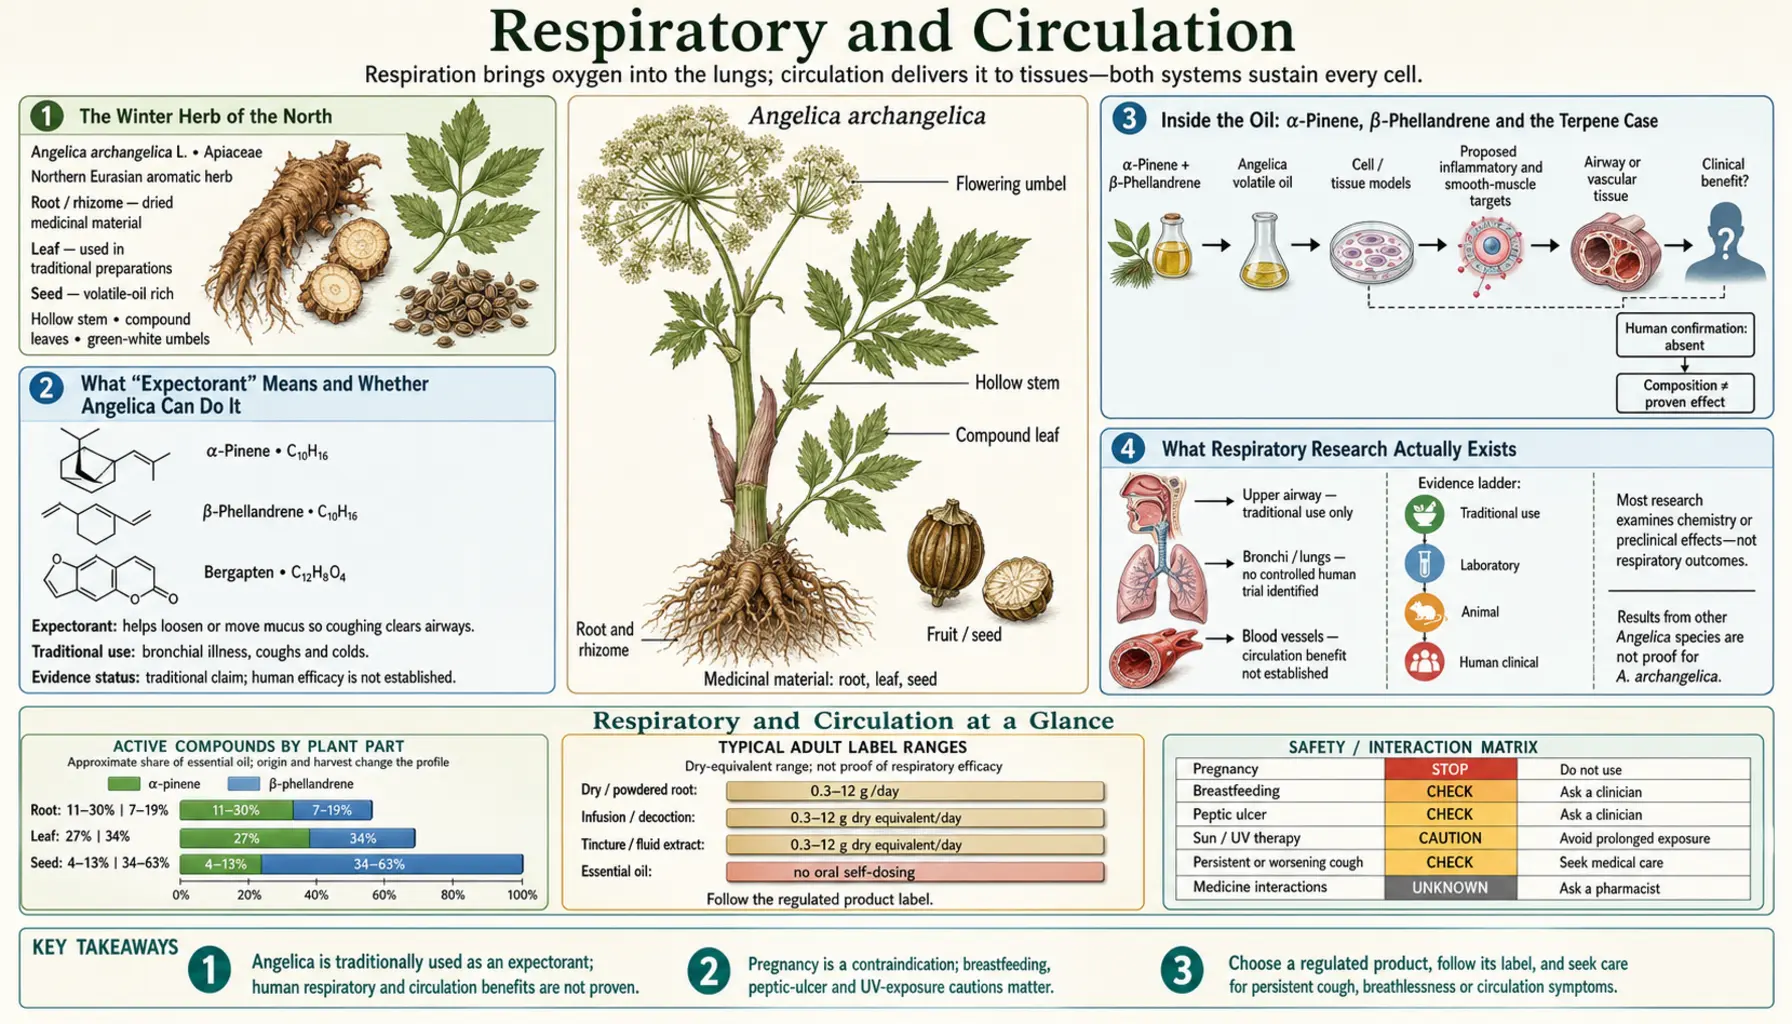
After digestion, the second great traditional use of Angelica archangelica in northern Europe was for the chest in winter — coughs, colds, congestion — and for what old herbals called a “cold and stagnant” circulation. Angelica was a winter herb in a place with a long, dark, damp winter, and the cordials and restoratives that carried it were made to be drunk between October and April.
This page is going to be less satisfying than the tradition suggests, and that is deliberate. There is no clinical trial of angelica for cough, for bronchitis, for congestion, or for any circulatory condition. Not a weak one, not a flawed one — none. What exists is a plausible chemical story about volatile terpenes, a centuries-old body of practice, and one genuinely interesting twist: the only human trials of angelica on its own landed on a completely different smooth-muscle organ, the bladder. (Two further human trials tested a supplement combining ferulic acid with Angelica archangelica extract, in memory and dementia symptoms; they are described below.) That turn is worth following, because it says something useful about where angelica’s real pharmacology might live.
Table of Contents
- The Winter Herb of the North
- What “Expectorant” Means and Whether Angelica Can Do It
- Inside the Oil: α-Pinene, β-Phellandrene and the Terpene Case
- What Respiratory Research Actually Exists
- “Warming the Blood” Examining a Traditional Claim
- Smooth Muscle Is the Through-Line — and the Bladder Trials
- Coumarins, Blood Thinners and What the Concern Really Is
- Steams, Syrups and Cordials: The Forms People Use
- Traditional Use and Dosing
- When a Cough Is Not a Herb Problem
- The Honest Verdict
- Key Research Papers
- Connections
- Featured Videos
The Winter Herb of the North
Angelica’s geography explains its reputation. This is a plant of Iceland, Norway, Sweden, Finland, the Faroes, Greenland’s settled fringes, the Alps and the wet north of Britain — places where fresh green plants are scarce for half the year and respiratory illness is a winter constant. A tall, strongly aromatic, easily cultivated perennial that stores well as dried root was a genuinely valuable thing to have.
Its folk names carry the reputation. Icelandic hvönn was cultivated and legally protected; in Sami and Nordic tradition the stems were eaten and the roots kept. The archangel legend — an angel revealing the plant as a remedy during plague — attached to angelica precisely because it was already regarded as a protective, strengthening plant, not the other way round.
The traditional respiratory framing was consistent: angelica was warming, drying and expectorant. It was for the person with a wet, rattling, lingering winter cough, cold hands and a general lack of vitality — not for a dry, irritated, hot cough, which the same herbals sent elsewhere. Whatever one makes of the underlying theory, the practitioners were making distinctions, which is more than most modern supplement marketing does.
What “Expectorant” Means and Whether Angelica Can Do It
An expectorant is meant to make mucus easier to clear — either by increasing the watery secretion that thins it (a secretomotor effect) or by changing its physical properties so it moves better up the mucociliary escalator.
The pharmacological route attributed to aromatic plants is the “gastro-pulmonary reflex”: an irritant or aromatic substance in the stomach triggers vagal signalling that increases bronchial secretion. Volatile terpenes have a second route — they are absorbed and partly excreted through the lungs, so they physically arrive at the airway surface. This is not fringe reasoning. It is the accepted rationale for cineole (eucalyptol) and for standardised myrtle-oil preparations, both of which have actual randomised trials in bronchitis and sinusitis.
So the mechanism is real for the class. The problem is specificity. Angelica has never been tested this way. No trial of angelica root in acute bronchitis, in chronic cough, in the common cold or in chronic obstructive pulmonary disease (COPD) exists. Nor is there an animal model of mucociliary clearance using A. archangelica. The claim is an inference from chemical family membership, and inferences from chemical family membership are how a great deal of herbal misinformation gets started.
A further honest point: even the well-studied aromatic expectorants have modest effects. Cineole and myrtol shorten symptoms in acute bronchitis by a matter of days at best. If angelica works in the same way and to the same degree, the realistic outcome is “slightly more comfortable” not “cured.”
Inside the Oil: α-Pinene, β-Phellandrene and the Terpene Case
Angelica root essential oil is overwhelmingly a monoterpene hydrocarbon oil. Published analyses vary substantially with origin, plant part, harvest time and distillation method — which is a real limitation on generalising from any single paper — but the recurring picture is:
- α-Pinene — usually the largest single component of root oil. The pine-resin note. Reported anywhere from roughly ten to twenty-five percent depending on the sample.
- β-Phellandrene and α-phellandrene — the peppery, faintly minty-citrus notes, and a major part of angelica’s characteristic smell.
- δ-3-Carene, limonene, sabinene, myrcene, β-pinene, p-cymene — the supporting monoterpene cast.
- Macrocyclic lactones — trace-level musk compounds that give angelica root oil its animalic depth and its value to perfumers.
- Furanocoumarins — carried into the oil and CO2 extract, which is what makes the concentrated material phototoxic. See the safety article.
What do monoterpenes do? In laboratory work, α-pinene shows anti-inflammatory activity in cell models, some antimicrobial activity, and effects on airway and gut smooth muscle. Finnish researchers have characterised Arctic angelica essential oil and supercritical CO2 extracts specifically, confirming the terpene-dominated profile and screening for biological activity.
Two cautions on reading that literature. First, essential oils are antimicrobial in a Petri dish at concentrations no living tissue will ever see — this is close to universal among aromatic plants and tells you very little. Second, a component study is not a product study: knowing that α-pinene does something at 100 µM in a cell line says nothing about a cup of root tea, which delivers a few milligrams of a complex mixture into a 70-kilogram person.
What Respiratory Research Actually Exists
Stated plainly, so nobody has to hunt for the caveat: there is no human respiratory research on Angelica archangelica. No randomised trials, no controlled cohort work, no open-label series of any quality. Searching PubMed for angelica and bronchitis, cough, asthma or chronic obstructive pulmonary disease returns work on related genera and on isolated furanocoumarins, not on this plant as a respiratory medicine.
What does exist, at the compound level:
- Imperatorin, one of angelica’s furanocoumarins, appears in the broader coumarin literature on airway inflammation and has been examined in animal models of asthma alongside other coumarins. This is compound-level, animal-level work, and imperatorin is present in dozens of Apiaceae and Rutaceae plants — it is not an angelica-specific finding.
- Root essential oil inhibits bacteria and moulds in vitro, including the food-spoilage and mycotoxin-producing moulds that interest food scientists. This is not evidence about a chest infection.
- α-Pinene and related monoterpenes have a general anti-inflammatory literature in cell and rodent models.
None of that adds up to a respiratory indication. A reasonable summary for a patient: angelica is a traditional winter remedy whose chemistry is consistent with the aromatic-expectorant class, and which has never been tested for the purpose. Herbal respiratory preparations that have been through randomised trials include cineole-standardised eucalyptus preparations, standardised myrtol, ivy leaf extract and Pelargonium sidoides — all of which have real, if modest, randomised evidence.
“Warming the Blood” Examining a Traditional Claim
European herbals describe angelica as warming to the blood and useful where circulation is cold and sluggish: cold hands and feet, a chilled constitution, poor recovery from winter illness.
Two honest observations.
First, the language resembles Chinese “blood-moving” terminology, and that resemblance is coincidence. The European tradition around A. archangelica developed in Nordic and Alpine Europe from its own humoral framework, centuries before any meaningful transmission of Chinese medical theory westward. The Chinese tradition around Angelica sinensis — Dong Quai — developed independently on a different species. Neither borrowed from the other. Writers who present European angelica as “the Western Dong Quai” are inventing a lineage that does not exist, and the invention obscures a practical point: the two plants have different chemistry and different risks.
Second, “warming” is not a testable endpoint. A warming sensation after a hot, aromatic, often alcoholic preparation is real and easily explained — hot liquid, alcohol-induced cutaneous vasodilation, and the pungent-aromatic sensation itself. Whether angelica changes peripheral perfusion in any measurable way is unknown, because nobody has put a laser Doppler probe on anyone’s finger after a dose. It would be a straightforward study to run. It has not been run.
For genuine cold extremities, the differential matters more than the herb: Raynaud phenomenon, hypothyroidism, anaemia, peripheral arterial disease and beta-blocker side effects are all common, all detectable, and all better addressed than warmed over with a tincture.
Smooth Muscle Is the Through-Line — and the Bladder Trials
Here is the genuinely interesting part of this page.
The airway, the blood vessel, the gut wall and the bladder are all lined with smooth muscle. If angelica has a real pharmacological action at achievable doses, an effect on smooth-muscle tone would explain the traditional digestive, respiratory and circulatory claims at once. And smooth muscle is exactly where the only human trials of angelica on its own went — not by design, but because an Icelandic angelica-leaf extract tablet was developed for bladder symptoms.
The 2013 nocturia trial — a negative result, reported honestly
The product is an A. archangelica leaf extract tablet, developed in Iceland and sold for waking at night to urinate. In 2013 its developers ran a parallel-group, randomised, double-blind, placebo-controlled trial: 69 men aged 45 or over with at least two nightly voids, eight weeks of treatment, voiding diaries before and after.
The result was negative. Nocturnal voids, the nocturnal polyuria index and the nocturnal bladder capacity index all improved — in both arms — with no significant difference between the leaf extract and placebo. The authors stated the conclusion without spin: the study did not show that the leaf extract improved nocturia overall. A post-hoc subgroup with reduced nocturnal bladder capacity did better on active treatment, and they flagged it as warranting further study rather than as a finding.
The write-up reports its negative primary result plainly.
The 2025 overactive-bladder pilot — a more encouraging result
A Spanish research group revisited the question with a registered (ClinicalTrials.gov NCT04357223), randomised, triple-blind, placebo-controlled pilot trial in 143 adults aged 18–75 with overactive bladder symptoms, using A. archangelica leaf extract for six weeks and assessing outcomes with three-day voiding diaries and the International Prostate Symptom Score (IPSS). Participants were assigned to extract or placebo in a 1.75 to 1 ratio, which is why the placebo group was the smaller one.
Compared with placebo, the supplemented group showed significant improvement in:
- Daytime voiding frequency (p = 0.004)
- IPSS storage subscore (p = 0.025)
- Quality of life (p < 0.001)
Nocturia improved only to a near-significant degree (p = 0.069) — consistent with the 2013 result. Total IPSS fell from 19.78 to 15.89 on active treatment versus 19.64 to 16.38 on placebo, a difference the authors describe as clinically meaningful but which is, in plain terms, small. Effect sizes were modest (generalised η² 0.03–0.12).
How much weight this carries. It is a real registered trial with a decent sample size for a pilot, and it is the best human evidence angelica has. It is also self-described as preliminary, single-centre, and six weeks long, and it has not been independently replicated. Overactive bladder is a symptom-score condition with a substantial placebo response, which is why replication matters more than usual. It is promising and unconfirmed.
Combination-supplement trials outside the bladder
Two human trials outside the bladder tested a supplement combining ferulic acid with Angelica archangelica extract, so they cannot show what angelica does on its own. A multicentre, randomised, double-blind, placebo-controlled trial in mild cognitive impairment found Mini-Mental State Examination (MMSE) scores significantly better at 24 weeks in the active group (p = 0.041 in the intention-to-treat population). A 2011 open-label trial gave 3.0 g a day for 4 weeks to 20 people with frontotemporal lobar degeneration or dementia with Lewy bodies; scores on the Neuropsychiatric Inventory, a measure of behavioural and psychological symptoms, fell in 19 of the 20, and the authors reported no adverse effects. Neither trial concerns the chest or the circulation.
What this means for the respiratory and circulatory claims
Not much, directly — a bladder result does not transfer to a bronchus. But it does two useful things. It shows the plant is capable of a measurable clinical effect on a smooth-muscle-dependent symptom, which makes the traditional antispasmodic framing more credible than pure folklore. And it shows how a real angelica trial looks, which is a useful yardstick against which to judge the claims that have never been tested.
Coumarins, Blood Thinners and What the Concern Really Is
Almost every source that mentions angelica and circulation repeats a version of: angelica contains coumarins, coumarins thin the blood, so avoid it with warfarin. The conclusion is reasonable. The reasoning is wrong, and the wrong reasoning has consequences.
Coumarin itself is not an anticoagulant. Simple coumarin is a fragrant compound found in tonka bean, sweet woodruff, sweet clover and cassia cinnamon, and it has no meaningful effect on clotting. The anticoagulant drug warfarin is a 4-hydroxycoumarin derivative — a chemically distinct compound that inhibits vitamin K epoxide reductase. The historical link runs through dicoumarol, which forms when sweet clover hay spoils and fungal action modifies the coumarin. Fresh plant coumarins do not do this.
Furanocoumarins are also not anticoagulants. Imperatorin, xanthotoxin, bergapten and angelicin are photosensitisers and enzyme inhibitors, not vitamin-K antagonists.
So why still be careful with warfarin? Because of the metabolic route rather than the pharmacodynamic one. Furanocoumarins are the compound class responsible for the grapefruit-juice drug interaction — bergamottin and 6′,7′-dihydroxybergamottin inhibit intestinal cytochrome P450 3A4 (CYP3A4), raising blood levels of drugs that depend on it. Warfarin is metabolised largely by CYP2C9 with a cytochrome P450 3A4 contribution to the less active isomer, and anything that perturbs the metabolism of a narrow-therapeutic-index anticoagulant is worth flagging. The interaction has not been demonstrated for angelica specifically; the concern is mechanistic plausibility, not measured effect.
What this means: for people taking warfarin, a direct oral anticoagulant (DOAC), clopidogrel or another antiplatelet drug, the concern with concentrated angelica is not that its coumarins thin the blood — they do not — but that its furanocoumarins are enzyme-active (they inhibit cytochrome P450 3A4), and warfarin is a narrow-therapeutic-index drug whose dose is titrated to a blood test. The same concern is the reason for caution about starting concentrated angelica in the week before surgery. The full discussion is in the safety article.
Steams, Syrups and Cordials: The Forms People Use
Steam inhalation
A traditional and low-risk way to use an aromatic plant for congestion: a bowl of just-boiled water, a small amount of dried root or crushed seed, a towel over the head, five to ten minutes. Scald injuries from inhalation bowls are common, particularly in children, and steam inhalation is not recommended for young children at all. Steam inhalation delivers the terpenes and largely leaves the heavy furanocoumarins behind, which makes it the gentler option.
Root or seed tea
1–2 g dried root, or half a teaspoon of crushed seed, per covered cup, steeped 10–15 minutes. Traditionally taken with a spoonful of honey for a winter cough. Honey is worth noting on its own account — it has better evidence for symptomatic cough relief in children over one year than most herbal preparations do. (Honey carries a risk of infant botulism under twelve months of age.)
Syrups and cordials
The traditional preparation for winter: root decocted, strained, and preserved with sugar or honey. Historically these were often alcoholic, so a nightly cordial was also a nightly dose of alcohol.
The great liqueurs
Angelica root is a defining botanical in gin, Chartreuse, Bénédictine, many vermouths and Scandinavian aquavit. These are drinks, not remedies, and the alcohol dose in a “medicinal” digestif or winter cordial substantially exceeds any plausible herbal effect.
Essential oil — not internally
Angelica root oil is a concentrated furanocoumarin source and a recognised phototoxic material. It is not taken internally, and the undiluted oil is phototoxic on sun-exposed skin.
Traditional Use and Dosing
No evidence-based dose exists, because no dose-ranging trial exists. Traditional European practice:
- Root tea: 1–2 g per cup, up to three cups daily, for a short course of a week or two during a winter illness.
- Tincture (1:5): 0.5–2 mL in water, up to three times daily.
- Steam: used as needed.
- Duration: short courses. Traditional practice does not use angelica daily for years, and the furanocoumarin content is a reason for that restraint.
The everyday measures people use for a winter cough are fluids, humidified air, sleep, stopping smoking, and a pillow or two for night-time cough.
When a Cough Is Not a Herb Problem
These are signs that hospitals treat as needing medical assessment rather than a herbal remedy:
- Cough lasting more than three weeks, or any cough with unexplained weight loss.
- Coughing blood, at any volume.
- Breathlessness at rest, or new breathlessness on mild exertion.
- Chest pain, particularly one-sided or worse on breathing in.
- High fever, rigors, or confusion in an older adult.
- Night sweats, or symptoms after tuberculosis exposure.
- Wheeze that is new, or a known asthma pattern that is getting worse.
- Swelling of one leg with breathlessness — a possible pulmonary embolism, which is an emergency.
Traditional herbal use is for the ordinary self-limiting winter cough, not for any of the above.
The Honest Verdict
Angelica’s respiratory and circulatory reputation is tradition without trials. The chemistry places it in the aromatic-expectorant family, whose better-studied members have modest real effects, so the idea is not unreasonable. But nobody has tested it, and a page that says so is more useful than one that borrows credibility from eucalyptus.
For a winter cough, angelica tea or a steam is a pleasant, low-risk comfort measure — and comfort measures are not nothing when you feel wretched. The realistic outcome is comfort, not cure.
The circulation claim is weaker still: “warming” is a sensation, not an outcome, and cold extremities can have detectable medical causes such as those listed above.
And the twist is worth carrying away. The one place Angelica archangelica on its own has produced real human data is the bladder — one honest negative trial in 2013 and one encouraging unreplicated pilot in 2025. (The two memory and dementia trials tested angelica extract combined with ferulic acid.) Judged on evidence rather than history, that is where the evidence is.
Key Research Papers
Each identifier below was verified live against NCBI E-utilities. Where no confirmed paper supports a claim — which for angelica and the respiratory tract means every claim — a topic search is linked instead of a citation.
The human trials of angelica on its own (bladder)
- López-Seoane J, Gesteiro E, Castro-Alija MJ, Quesada-González C, Pérez-Ruiz M, González-Gross M. Effects of Angelica archangelica extract on overactive bladder: a pilot randomized controlled trial. Food Science & Nutrition. 2025;13(12):e71258 — PubMed PMID: 41368330 — Positive on daytime voids, IPSS storage subscore and quality of life; nocturia only near-significant.
- Sigurdsson S, Geirsson G, Gudmundsdottir H, Egilsdottir PB, Gudbjarnason S. A parallel, randomized, double-blind, placebo-controlled study to investigate the effect of SagaPro on nocturia in men. Scandinavian Journal of Urology. 2013;47(1):26–32 — PubMed PMID: 23323790 — Negative on the primary endpoint.
- Kowal NM, Eyjolfsson R, Olafsdottir ES. Investigations on the constituents of SagaPro tablets, a food supplement manufactured from Angelica archangelica leaf. Die Pharmazie. 2017;72(1):3–4 — PubMed PMID: 29441889 — A sceptical analysis concluding the proposed active flavonoid is present at a dose unlikely to do anything.
Human trials of a combination supplement (ferulic acid plus angelica extract)
- Kudoh C, Hori T, Yasaki S, Ubagai R, Tabira T. Effects of Ferulic Acid and Angelica archangelica Extract (Feru-guard(®)) on Mild Cognitive Impairment: A Multicenter, Randomized, Double-Blind, Placebo-Controlled Prospective Trial. Journal of Alzheimer's Disease Reports. 2020;4(1):393–398 — PubMed PMID: 33163900
- Kimura T, Hayashida H, Murata M, Takamatsu J. Effect of ferulic acid and Angelica archangelica extract on behavioral and psychological symptoms of dementia in frontotemporal lobar degeneration and dementia with Lewy bodies. Geriatrics & Gerontology International. 2011;11(3):309–314 — PubMed PMID: 21272180
Essential oil chemistry
- Korpinen RI, Välimaa AL, Liimatainen J, Kunnas S. Essential oils and supercritical CO2 extracts of Arctic angelica (Angelica archangelica L.), marsh Labrador tea and common tansy. Molecules. 2021;26(23). — PubMed PMID: 34885703
- Fraternale D, Flamini G, Ricci D. Essential oil composition and antimicrobial activity of Angelica archangelica L. (Apiaceae) roots. Journal of Medicinal Food. 2014;17(9):1043–1047. — PubMed PMID: 24788027
- Aćimović MG, Pavlović SĐ, Varga AO, et al. Chemical composition and antibacterial activity of Angelica archangelica root essential oil. Natural Product Communications. 2017;12(2):205–206. — PubMed PMID: 30428212
- Lunz K, Stappen I. Back to the roots — an overview of the chemical composition and bioactivity of selected root-essential oils. Molecules. 2021;26(11). — PubMed PMID: 34070487
- Sowndhararajan K, Deepa P, Kim M, Park SJ, Kim S. A review of the composition of the essential oils and biological activities of Angelica species. Scientia Pharmaceutica. 2017;85(3). — PubMed PMID: 28930168
The blood-thinner question — the metabolic route
- Fuhr LM, Marok FZ, Fuhr U, Selzer D, Lehr T. Physiologically based pharmacokinetic modeling of bergamottin and 6,7-dihydroxybergamottin to describe CYP3A4-mediated grapefruit-drug interactions. Clinical Pharmacology & Therapeutics. 2023;114(2):470–482 — PubMed PMID: 37307228 — The furanocoumarin–CYP3A4 mechanism, worked out in detail for the grapefruit case.
- Melough MM, Cho E, Chun OK. Furocoumarins: a review of biochemical activities, dietary sources and intake, and potential health risks. Food and Chemical Toxicology. 2018;113:99–107. — PubMed PMID: 29378230
Compound-level work relevant to the respiratory claim
- Coumarins, including imperatorin, in animal models of asthma — a systematic review of the compound class rather than of angelica. Dos Santos IM, et al. Basic & Clinical Pharmacology & Toxicology. 2026;138(3):e70210. — PubMed PMID: 41689296
- α-Pinene and monoterpene effects on airway and smooth muscle. PubMed search — no angelica-specific trial exists.
- Cineole and myrtol in acute bronchitis — the better-evidenced aromatic expectorants, for comparison. PubMed search.
PubMed Topic Searches
- PubMed: Angelica archangelica — everything
- PubMed: Angelica and the respiratory tract
- PubMed: Angelica leaf-extract trials
- PubMed: Herbal treatments for overactive bladder
- PubMed: Placebo response in nocturia trials
- PubMed: α-Pinene pharmacology
- PubMed: β-Phellandrene
- PubMed: Essential oils and mucociliary clearance
- PubMed: Pelargonium sidoides in bronchitis
- PubMed: Ivy leaf extract for cough
- PubMed: Honey for cough in children
- PubMed: Warfarin–herb interactions
Connections
- All Herbs
- Angelica — the main topic page.
- Angelica Benefits — hub for this series.
- Digestive and Bitter Tonic
- Anxiety, Sleep and Nervous System
- Safety: Furanocoumarins and Look-Alikes
- Dong Quai — the independent Chinese tradition on Angelica sinensis.
- Fennel — Apiaceae relative with its own respiratory tradition.
- Lovage — closest culinary relative.
- Chen Pi — aged citrus peel, used in East Asia for phlegm and cough.
- Ginger — the other classic warming herb.
- Peppermint — the aromatic with real antispasmodic trials.