Turmeric for Functional Dyspepsia and Bloating
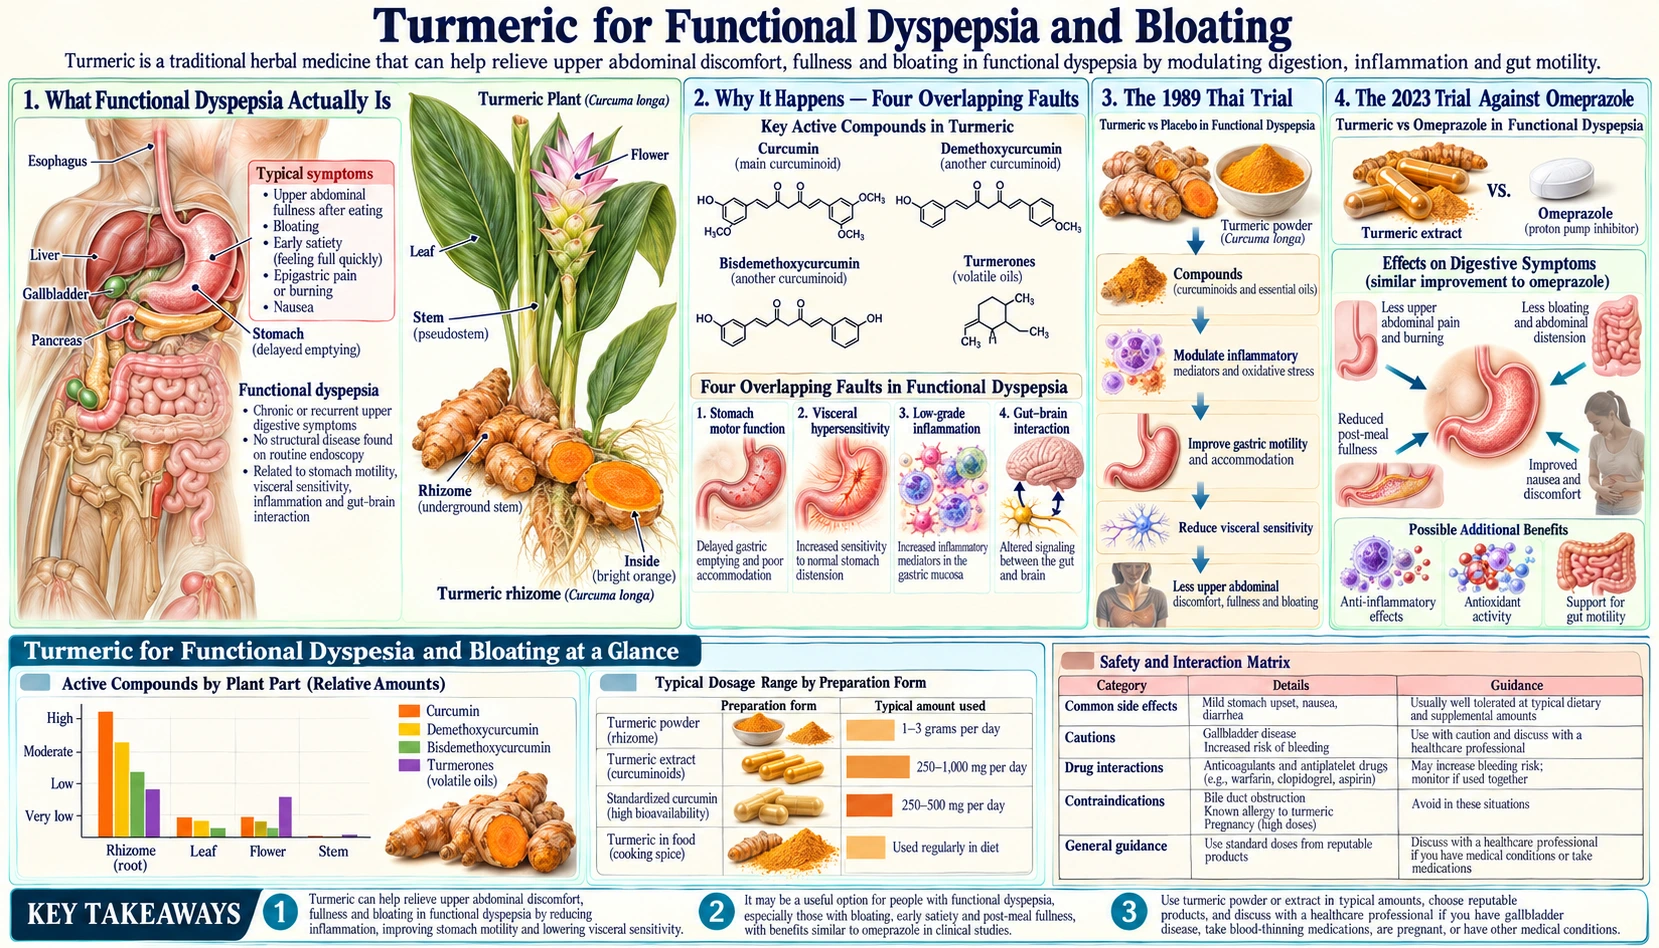
You eat a normal-sized dinner and feel like you have eaten two. The fullness sits high, just under the breastbone, and it will not move. There is pressure, maybe a dull burn, maybe a sour taste, definitely wind. You have had a scope, or your doctor has decided you do not need one, and you were told there is nothing structurally wrong. Which is true, and which is also not remotely the same thing as nothing being wrong.
This is functional dyspepsia, and it is one of the most common reasons anyone in the world walks into a pharmacy. It is also the single indication for which turmeric has the strongest and longest clinical case — stronger, in trial-design terms, than the joint evidence it is better known for. This article works through what the condition is, what the two key trials actually showed, why turmeric's notorious absorption problem matters less here than anywhere else, and the warning signs that hospitals investigate.
Table of Contents
- What Functional Dyspepsia Actually Is
- Why It Happens — Four Overlapping Faults
- The 1989 Thai Trial
- The 2023 Trial Against Omeprazole
- Why Poor Absorption Matters Less Here
- Breath Hydrogen: Measuring Gas Objectively
- Gastric Emptying — The Mouse Evidence
- How People Actually Take It
- The Honest Limits of This Evidence
- Warning Signs Hospitals Investigate
- Liver Injury Reports From Turmeric Supplements
- Key Research Papers
- Connections
- Featured Videos
What Functional Dyspepsia Actually Is
"Functional" is a word that has done a lot of damage to a lot of patients. It does not mean imaginary, psychosomatic, or trivial. In gastroenterology it means a disorder of how the gut works rather than of how it is built — the plumbing is intact, the wiring is misbehaving. A cardiologist would say the same of an arrhythmia in a structurally normal heart, and nobody tells those patients it is in their head.
Functional dyspepsia is defined by persistent symptoms centred on the upper abdomen, in the absence of any structural disease that explains them. The formal criteria — the Rome criteria, revised periodically by international consensus — split it into two overlapping subtypes, and the split is genuinely useful because they respond to different things:
- Postprandial distress syndrome (PDS). Bothersome fullness after ordinary meals, and early satiety — you fill up after a few mouthfuls. Bloating and belching cluster here. This is the meal-related subtype, and it is the one that most resembles what a Thai pharmacy label means by "wind and distension".
- Epigastric pain syndrome (EPS). Pain or burning in the upper middle abdomen, not necessarily tied to eating. This subtype shades towards what people call heartburn, though reflux is a separate diagnosis.
Plenty of people have both. A comprehensive 2026 review of the pathophysiology, epidemiology and international management guidelines sets out how the definitions have evolved and how variably the condition is treated across health systems — worth knowing, because it explains why two doctors can give you two entirely different plans for the same symptoms.
The condition is common, it is chronic, and it relapses. Estimates of how many adults have it vary widely depending on which criteria a study uses and which country it surveys, which is itself part of the story: this is a condition defined by symptoms, and symptom definitions move. What does not move is the clinical reality — a large number of people feel persistently unwell after eating and have been told there is nothing to find.
Why It Happens — Four Overlapping Faults
No single mechanism explains functional dyspepsia. Four keep appearing, and most patients have some mixture.
Impaired accommodation
A healthy stomach relaxes as food arrives, like a balloon slackening so that it can take more air at the same pressure. This reflex is called accommodation. When it fails, the stomach stays stiff, pressure rises with a normal volume of food, and stretch receptors report a full stomach after a small meal. That is early satiety, and it is a mechanical failure, not an attitude problem.
Delayed gastric emptying
In a substantial minority, the stomach empties more slowly than it should. Food sits. Fermentation gets longer to happen. The sense of heaviness has an obvious physical basis.
Visceral hypersensitivity
The nerves reporting from the gut are turned up too loud. Normal distension, normal acid, normal peristalsis get reported to the brain as discomfort. This is why some people with completely normal emptying still hurt, and why drugs that suppress acid often fail — the acid was never abnormal, the reporting was.
Low-grade mucosal inflammation and barrier changes
The newest strand. Studies have found modest increases in immune cells — particularly eosinophils and mast cells — in the duodenum of people with functional dyspepsia, along with subtle changes in the intestinal barrier. Nothing that shows up on a routine endoscopy report, but not nothing either. If this strand holds, a mild anti-inflammatory acting locally in the gut lumen is a far more interesting proposition than it used to be.
Notice how badly acid suppression maps onto that list. Proton pump inhibitors (PPIs) reduce stomach acid. Three of those four faults have nothing directly to do with acid. That is why proton pump inhibitors help some people with functional dyspepsia a great deal and do nothing whatsoever for others — and why a treatment working through a different set of mechanisms is worth testing rather than dismissing.
The 1989 Thai Trial
The foundational clinical study is Thamlikitkul and colleagues, published in the Journal of the Medical Association of Thailand in 1989. It is usually described in passing as "an old Thai study", which undersells it: it was a randomised, double-blind trial with both a placebo arm and an active comparator, run at a time when almost no herbal medicine anywhere was being tested that rigorously.
The design, in plain terms:
- 116 adults with acid dyspepsia, flatulent dyspepsia or atonic dyspepsia were randomly assigned to one of three treatments (39 to turmeric, 41 to placebo, 36 to the comparator), in one provincial and five community hospitals in Thailand.
- One group received Curcuma domestica capsules — turmeric rhizome powder — at two 250 mg capsules, four times a day.
- One group received placebo capsules, two capsules four times a day.
- One group received the active comparator the trial calls “flatulence”, a carminative (wind-relieving) remedy rather than an antacid.
- Treatment ran for seven days, and neither patients nor assessors knew who had received what.
The results, as the trial's abstract prints them: 53 per cent of patients on placebo responded, against 83 per cent on the “flatulence” comparator and 87 per cent on turmeric. The authors reported the differences between placebo and the active drugs as statistically significant and clinically important. Mild, self-limited side effects occurred at similar frequency in the three groups, about 50 per cent of patients in each group were satisfied with the treatment they received, and ten patients did not take part in the follow-up. The trial is consistently cited — in Thailand and in international herbal-medicine reviews — as the clinical basis for turmeric's standing as a dyspepsia remedy, and that its design was a genuine randomised double-blind comparison rather than an open observation.
Three things about that regimen are worth noticing, because they are still how the remedy is used:
- The dose is small. Each 250 mg capsule of turmeric powder is a fraction of a teaspoon. Modern curcumin extract capsules often contain more curcuminoid than that entire capsule weighs.
- The frequency is high. Two capsules, four times a day.
- The course is short. Seven days. This was never conceived as something you take forever.
The trial's limitations are the limitations of its era: modest size by modern standards (116 adults), a one-week horizon, symptom-based outcomes, and six hospitals all in one country. It would not, on its own, convince a guideline committee in 2026. It did not have to be the only trial.
The 2023 Trial Against Omeprazole
In September 2023, Kongkam and colleagues published in BMJ Evidence-Based Medicine a randomised, double-blind trial of curcumin and a proton pump inhibitor (PPI) in functional dyspepsia. This is the headline modern evidence for everything on this page, and it deserves to be understood properly rather than repeated as a slogan.
The design was three-arm, which is the single most important thing about it:
- Curcumin alone
- Omeprazole alone — the standard drug, one of the most widely prescribed medicines in the world
- Curcumin plus omeprazole
Patients had functional dyspepsia, meaning structural disease had been excluded. The trial was run at several centres in Thailand — a Thai traditional medicine hospital, a district hospital and university hospitals — with central randomisation, and it was double-blind with double-dummy placebos so that no one could tell from the pills which arm they were in. Patients in the combination arm took two 250 mg curcumin capsules four times daily and one 20 mg omeprazole capsule once daily for 28 days. Symptoms were scored with the Severity of Dyspepsia Assessment (SODA) on day 28 and again on day 56.
The numbers: 206 patients were enrolled and randomly assigned to the three groups, and 151 completed the study. Their average age was 49.7 years and 73.4% were women. By day 56 the pain scores had changed by -8.07 (curcumin), -8.85 (omeprazole) and -7.19 (curcumin plus omeprazole), and the non-pain scores by -4.12, -3.71 and -4.09. No significant differences were observed among the three groups, and no serious adverse events occurred.
The finding, stated as carefully as it deserves: all three arms improved, and the curcumin arm's improvement was comparable to the omeprazole arm's. Adding curcumin to omeprazole did not produce a clearly superior result over either alone. Curcumin was not shown to beat the drug; it was not shown to be beaten by it either.
Why that matters, and why it is easy to overstate:
- It matters because "comparable to omeprazole" is a high bar for any botanical. Omeprazole is not a soft comparator — it is the actual first-line therapy. Very few herbal trials are designed against the real standard of care rather than against placebo, and the ones that are usually lose.
- It is easy to overstate because a trial of this size cannot establish equivalence in the formal statistical sense. "No significant difference detected" is not the same as "proven equally effective"; it can also mean the trial was too small to detect a real difference. The authors concluded that curcumin and omeprazole had comparable efficacy for functional dyspepsia with no obvious synergistic effect.
- It says nothing about anyone who has a diagnosed reason to be on a proton pump inhibitor. Erosive oesophagitis, Barrett's, a bleeding ulcer, long-term nonsteroidal anti-inflammatory drug (NSAID) protection — these are structural indications and this trial did not study them, so it gives no information about stopping a prescribed proton pump inhibitor.
- Safety was a recorded outcome. Adverse events and serious adverse events were the trial's secondary outcomes, and no serious adverse events occurred.
Taken with the 1989 trial, the shape of the evidence is this: two randomised, double-blind, controlled trials, thirty-four years apart, in the same condition, run in the same country. The 1989 trial found turmeric better than placebo; the 2023 trial had no placebo arm and found curcumin comparable to omeprazole. That is a small literature. It is also more than most of what sits on a supplement shelf can claim.
Why Poor Absorption Matters Less Here
Every serious discussion of turmeric runs into the same wall. Curcumin is absorbed badly. It is poorly soluble in water, it is chewed up rapidly by the liver and intestinal wall, and it is excreted quickly. Swallow a substantial dose and the concentration reaching your bloodstream is often barely detectable. This is why the famous 1998 piperine study exists — black pepper extract inhibits the enzymes that destroy curcumin, and co-administration raises blood levels dramatically — and why the modern supplement industry sells phospholipid complexes, nanoparticles and emulsions.
For a knee, a brain or a blood vessel, this is turmeric's central problem: the molecule has to travel to reach the target, and it mostly does not arrive.
Lopresti's 2018 review in Advances in Nutrition made the argument that inverts this for the gut, and it is the conceptual key to this entire leg. The curcumin that fails to be absorbed has not disappeared. It is in the gut. It remains in the lumen at concentrations orders of magnitude higher than the blood ever sees, in direct contact with the gastric and intestinal lining, and it travels intact into the colon, where it meets the microbiota. Lopresti's proposal was that curcumin's gastrointestinal actions — on the gut barrier, on local inflammation, on the microbiome, on gut-derived signalling that reaches the rest of the body — may account for a substantial share of its observed effects, rather than being a footnote to a failed delivery problem.
Two practical consequences follow, and both cut against supplement-shelf orthodoxy:
- A cheap, plain preparation is defensible for a gut indication. If contact with the gut lining is the point, paying a premium to get curcumin out of the gut faster is at best beside the point.
- The 1989 trial's small dose stops looking odd. Two 250 mg capsules of rhizome powder four times a day deliver very little curcuminoid to the blood. They deliver a steady presence of turmeric in the stomach, which is a different thing and, for this indication, possibly the relevant one.
This remains a hypothesis, argued in a review, not a proven mechanism. But it is a hypothesis that predicts exactly the pattern the trial record shows — gut indications doing proportionally better than the pharmacokinetics would lead you to expect.
Breath Hydrogen: Measuring Gas Objectively
"Bloating" is a miserable thing to study, because it is a sensation and sensations cannot be measured with an instrument. Breath hydrogen is one of the few honest workarounds available.
Here is the logic. Human cells do not produce hydrogen gas. Every molecule of hydrogen in your breath came from bacteria fermenting carbohydrate somewhere in your gut; it diffuses into the blood, travels to the lungs and is exhaled. Measure breath hydrogen and you have an objective, non-invasive index of how much fermentation is going on — which is the physical substrate of a good deal of gas and distension.
Shimouchi and colleagues published a study in Digestive Diseases and Sciences in 2009 examining the effect of dietary turmeric on breath hydrogen. Eight healthy volunteers (not people with dyspepsia) fasted for 12 hours and then ate curry and rice, with or without turmeric, and their breath hydrogen was measured every 15 minutes for 6 hours. The curry with turmeric significantly increased breath hydrogen and shortened small-bowel transit time compared with the curry without turmeric. The authors read this as turmeric activating bowel motility and carbohydrate fermentation in the colon.
The direction matters on a bloating page: the turmeric meal produced more hydrogen, not less, so this study does not show reduced gas or bloating. It is a small study, a signal rather than a proof. Its value is that it looks at something measurable rather than at a symptom questionnaire, and it does not depend on anyone's self-report.
What it does not do is establish a dose, a duration, or a clinical benefit. One small human study with an objective endpoint is a good reason to take a claim seriously and a bad reason to treat it as settled.
Gastric Emptying — The Mouse Evidence
This section comes with a label attached, and the label stays attached throughout: this is animal work. No human gastric emptying study has shown these effects, and anyone telling you turmeric has been proven to speed up a human stomach is going beyond the evidence.
Two mouse studies are worth knowing about because they propose a concrete mechanism rather than hand-waving about "digestive support".
The interstitial cells of Cajal
Your gut has a pacemaker. The interstitial cells of Cajal (ICC) sit in the gut wall between nerve endings and smooth muscle and generate the slow electrical waves that set the rhythm of contraction. Loss or dysfunction of these cells is implicated in gastroparesis and in several motility disorders. Lin and colleagues, publishing in Experimental and Therapeutic Medicine in 2021, reported that curcumin relieved gastric emptying dysfunction in mice — dysfunction induced experimentally with L-arginine and atropine — and traced the effect to the interstitial cells of Cajal.
That is a satisfying mechanism because it maps onto a real human pathology. It is still mice, and the dysfunction was chemically induced rather than spontaneous.
Functional gastrointestinal disorder models
Yu and colleagues, in the Journal of Medicinal Food in 2017, reported that curcumin alleviated functional gastrointestinal disorders in mice in vivo. Again: mice, experimental models, and a set of endpoints chosen by the investigators.
The right way to hold this evidence is as a plausible explanation waiting for a human test, not as a reason to expect your stomach to empty faster. If the ICC mechanism is real in people, it would neatly explain why the meal-related, fullness-and-early-satiety subtype of functional dyspepsia is where turmeric's traditional use has always been aimed. That is a hypothesis with a good pedigree and no human confirmation.
How People Actually Take It
Descriptive, not prescriptive — this is what the studies used and what the traditional regimen looks like.
- Timing beats quantity. Both the traditional Thai regimen and the trial protocols tie doses to meals. Taking turmeric with food is not a stomach-protection afterthought here; it is the mechanism. Bile release, gastric contact and the motility question all happen around eating.
- The traditional dose is modest and frequent. The 1989 protocol was two 250 mg capsules of rhizome powder four times a day for seven days. The 2023 trial used the same two-capsules-four-times-daily pattern, with 250 mg curcumin capsules, for 28 days.
- The modern extract dose is much higher in curcuminoid terms. Trials using standardised extracts deliver far more curcuminoid per day, divided across doses. A rhizome-powder milligram figure and an extract milligram figure are not the same thing; they differ by more than an order of magnitude in curcuminoid content.
- The trials ran one to four weeks. The 1989 study gave treatment for a week; the 2023 study gave it for 28 days and scored symptoms again on day 56.
- Some people get burning. A minority of people get reflux, epigastric burning or loose stools from turmeric capsules. In a condition defined by upper-gut discomfort, that side effect overlaps with the symptoms being treated.
- Food counts too. Nothing about this evidence requires a capsule. Turmeric used generously in cooking — the way it is used across South and Southeast Asia — is the oldest version of the intervention, it costs almost nothing, and the gallbladder and mucosal-contact mechanisms do not care whether the turmeric arrived in a capsule or a curry.
On piperine: black pepper extract raises curcumin blood levels substantially. For joint or systemic use that is the point. For a gut indication it is arguably counterproductive, and it also raises the odds of interfering with other medicines, because the same enzyme inhibition that spares curcumin spares other drugs too: piperine is an inhibitor of the liver and gut-wall process (glucuronidation) that clears curcumin, and slowing that clearance can raise blood levels of other medicines broken down the same way. In the US Drug-Induced Liver Injury Network series described below, 3 of the 7 turmeric products tested also contained piperine (black pepper).
The Honest Limits of This Evidence
This is the most important section on the page. The case for turmeric in functional dyspepsia is real and it is small.
- The trial base is small. A 2023 Cochrane review of non-Chinese herbal medicines for functional dyspepsia (41 trials, 4477 participants, 27 herbal medicines) found that Curcuma longa probably results in a moderate improvement in global symptoms of dyspepsia compared with placebo at four weeks (mean difference (MD) -3.33, 95% confidence interval (CI) -5.84 to -0.81; 2 studies, 110 participants; moderate certainty), with probably little to no difference in the rate of adverse events (RR 1.26, 95% CI 0.51 to 3.08; 1 study, 89 participants). Compared with other treatments, Curcuma longa may provide little to no benefit. In the same review, peppermint and caraway oil probably resulted in a large improvement in global symptoms compared with placebo at four weeks (2 studies, 210 participants; moderate certainty). None of these trials is large by the standards of drug development, where a licensing dossier runs to thousands of patients across many sites.
- Both are from one country. Thailand's investigators deserve enormous credit for doing this work when nobody else would, and there is nothing improper about it — but replication in different populations, with different diets, different background rates of H. pylori and different expectations about herbal medicine, has not happened. Expectation matters in a symptom-defined condition.
- The preparations differ. The 1989 trial used whole rhizome powder. Modern trials use standardised extracts. These are chemically different products and no trial has compared them for this indication. "Turmeric works for indigestion" hides the question of which turmeric.
- Follow-up is short. One week in 1989; 28 days of treatment with a last score on day 56 in 2023. Functional dyspepsia is a relapsing condition measured in years. Nothing here tells you what happens at six months, or whether benefit persists, or what daily use for a decade does.
- The placebo response in this condition is large. Trials of functional dyspepsia routinely see substantial improvement in the placebo arm. This is not a flaw in the patients; it is a property of symptom-defined conditions with fluctuating natural history. It is exactly why the 1989 trial's placebo arm and the 2023 trial's double-dummy design matter so much, and why the uncontrolled studies elsewhere in the turmeric literature prove so little.
- Symptom scores are subjective endpoints. Legitimate and standard in this field — there is no blood test for dyspepsia — but softer than a tumour measurement or a survival curve.
- The wider review is cautious. A 2024 systematic review of 26 studies of turmeric for digestive disorders — inflammatory bowel disease, irritable bowel syndrome (IBS), dyspepsia, gastroesophageal reflux disease and peptic ulcers — could not pool the results because they differed too much, and judged most studies to have a high risk of bias. Its summaries suggested turmeric is safe, with possible efficacy in inflammatory bowel disease or IBS, but effects were inconsistent for other conditions, and it concluded that the efficacy of turmeric in digestive disorders remains unclear.
- Publication bias is unmeasurable here. With a literature this small, one or two unpublished negative trials would change the picture materially, and there is no way to know whether they exist.
The reasonable conclusion is not "turmeric is proven for indigestion" and not "there is no evidence". It is this: for meal-related upper-gut discomfort with no structural disease, turmeric is a low-cost, well-tolerated option with a small trial base behind it (a 1989 placebo-controlled trial, a 2023 trial against omeprazole, and a Cochrane pooling of two placebo-controlled studies), a coherent set of mechanisms, and centuries of pharmacy-shelf use in a country that takes it seriously. The placebo-controlled evidence covers one to four weeks of use.
Warning Signs Hospitals Investigate
Functional dyspepsia is a diagnosis of exclusion. That phrase carries a real obligation: something has to have been excluded. The following are the standard alarm features. Hospitals investigate each of them, and any one of them means the symptoms have not yet been shown to be functional dyspepsia.
- Unintentional weight loss — weight coming off without you trying
- Persistent vomiting, or vomiting blood, or vomit that looks like coffee grounds
- Black, tarry stools, or visible blood in the stool — black stools mean digested blood until proven otherwise
- Difficulty swallowing, pain on swallowing, or food that sticks
- Anaemia, or unexplained low iron on a blood test
- A palpable lump or mass in the abdomen
- New, persistent indigestion beginning after the age of 60 — new symptoms in an older adult are investigated, not treated blind
- A family history of stomach or oesophageal cancer
- Severe or escalating pain, especially pain that wakes you from sleep
- Jaundice — yellowing of the eyes or skin, dark urine, pale stools
There is also a specific point about acid-suppressing drugs. If you have been taking an over-the-counter proton pump inhibitor for weeks or months and it is the only thing keeping you comfortable, that is worth a proper assessment rather than a swap to a supplement. And if you are on a proton pump inhibitor because a doctor found something — an ulcer, erosive oesophagitis, Barrett's oesophagus, or protection alongside long-term anti-inflammatory drugs — nothing on this page applies to you. The 2023 trial studied functional dyspepsia specifically, meaning patients in whom those findings had been ruled out.
One more: Helicobacter pylori is a treatable bacterial cause of upper-gut symptoms and can be tested for with a breath test, a stool test or a biopsy. Curcumin is not an eradication therapy — a trial of a curcumin-based regimen failed to clear the organism, and we cover that failure in full on the irritable bowel syndrome (IBS), Gut Inflammation and H. pylori article.
Liver Injury Reports From Turmeric Supplements
The US Drug-Induced Liver Injury Network (DILIN) reviewed every case enrolled between 2004 and 2022 in which turmeric was an implicated product. It found 10 cases of turmeric-associated liver injury, all enrolled since 2011 and 6 since 2017. Eight were women, and the median age was 56 years (range 35-71). Five people were hospitalised, and 1 died of acute liver failure. Chemical analysis confirmed turmeric in all 7 products tested; 3 also contained piperine (black pepper). Seven of the 10 patients carried the gene variant HLA-B*35:01.
The authors concluded that turmeric causes potentially severe liver injury, typically appearing 1 to 4 months after starting, and that liver injury due to turmeric appears to be increasing in the United States, perhaps reflecting usage patterns or increased combination with black pepper. Jaundice — yellowing of the eyes or skin, dark urine, pale stools — is on the warning-sign list above.
Key Research Papers
- Kongkam P, Khongkha W, Lopimpisuth C, et al. (2023). Curcumin and proton pump inhibitors for functional dyspepsia: a randomised, double blind controlled trial. BMJ Evidence-Based Medicine. — PubMed PMID: 37696679 (the three-arm trial against omeprazole; a correction was published in 2025, PubMed PMID: 38866470)
- Thamlikitkul V, Bunyapraphatsara N, Dechatiwongse T, et al. (1989). Randomized double blind study of Curcuma domestica Val. for dyspepsia. Journal of the Medical Association of Thailand. — PubMed PMID: 2699615
- Chamchoum E, Ghaleb J, Chamchoum N, et al. (2026). Functional Dyspepsia: An Updated Review of Pathophysiology, Epidemiology, Clinical Manifestations, and International Management Guidelines. Sage Open Pathology. — PubMed PMID: 42491169 (background on the condition itself)
- Lopresti AL (2018). The Problem of Curcumin and Its Bioavailability: Could Its Gastrointestinal Influence Contribute to Its Overall Health-Enhancing Effects? Advances in Nutrition. — PubMed PMID: 29438458
- Shimouchi A, Nose K, Takaoka M, et al. (2009). Effect of dietary turmeric on breath hydrogen. Digestive Diseases and Sciences. — PubMed PMID: 19034660
- Lin P, Li B, Ye J, et al. (2021). Curcumin relieves mice gastric emptying dysfunction induced by L-arginine and atropine through interstitial cells of Cajal. Experimental and Therapeutic Medicine. — PubMed PMID: 33850520 (animal study, in mice)
- Yu J, Xu WH, Sun W, et al. (2017). Curcumin Alleviates the Functional Gastrointestinal Disorders of Mice In Vivo. Journal of Medicinal Food. — PubMed PMID: 28880711 (animal study, in mice)
- Shoba G, Joy D, Joseph T, et al. (1998). Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica. — PubMed PMID: 9619120
- Gupta SC, Patchva S, Aggarwal BB (2013). Therapeutic roles of curcumin: lessons learned from clinical trials. The AAPS Journal. — PubMed PMID: 23143785
- Chainani-Wu N (2003). Safety and anti-inflammatory activity of curcumin: a component of tumeric (Curcuma longa). Journal of Alternative and Complementary Medicine. — PubMed PMID: 12676044
- Kwiecien S, Magierowski M, Majka J, et al. (2019). Curcumin: A Potent Protectant against Esophageal and Gastric Disorders. International Journal of Molecular Sciences. — PubMed PMID: 30909623
- Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. (2023). Liver Injury Associated with Turmeric — A Growing Problem: Ten Cases from the Drug-Induced Liver Injury Network [DILIN]. American Journal of Medicine. — PubMed PMID: 36252717
- Báez G, Vargas C, Arancibia M, et al. (2023). Non-Chinese herbal medicines for functional dyspepsia. Cochrane Database of Systematic Reviews. — PubMed PMID: 37323050
- Thavorn K, Wolfe D, Faust L, et al. (2024). A systematic review of the efficacy and safety of turmeric in the treatment of digestive disorders. Phytotherapy Research. — PubMed PMID: 38503513
PubMed Topic Searches
- PubMed: Curcumin and functional dyspepsia
- PubMed: Functional dyspepsia and the Rome criteria
- PubMed: Functional dyspepsia and gastric accommodation
- PubMed: Duodenal eosinophils in functional dyspepsia
- PubMed: Breath hydrogen and bloating
- PubMed: Curcuma longa and dyspepsia, randomised trials
- PubMed: Dyspepsia alarm features and endoscopy
Connections
- Turmeric for Digestive Health
- Ya Khamin Chan: Thai Traditional Use
- Turmeric, Bile and Fat Digestion
- Turmeric for Irritable Bowel Syndrome, Gut Inflammation and H. pylori
- Turmeric
- Turmeric Safety and Interactions
- Turmeric Bioavailability and Forms
- Turmeric Benefits
- History of Turmeric
- Fingerroot
- Javanese Turmeric
- Gut Health
- Culinary and Spice Herbs