Chasteberry Benefits
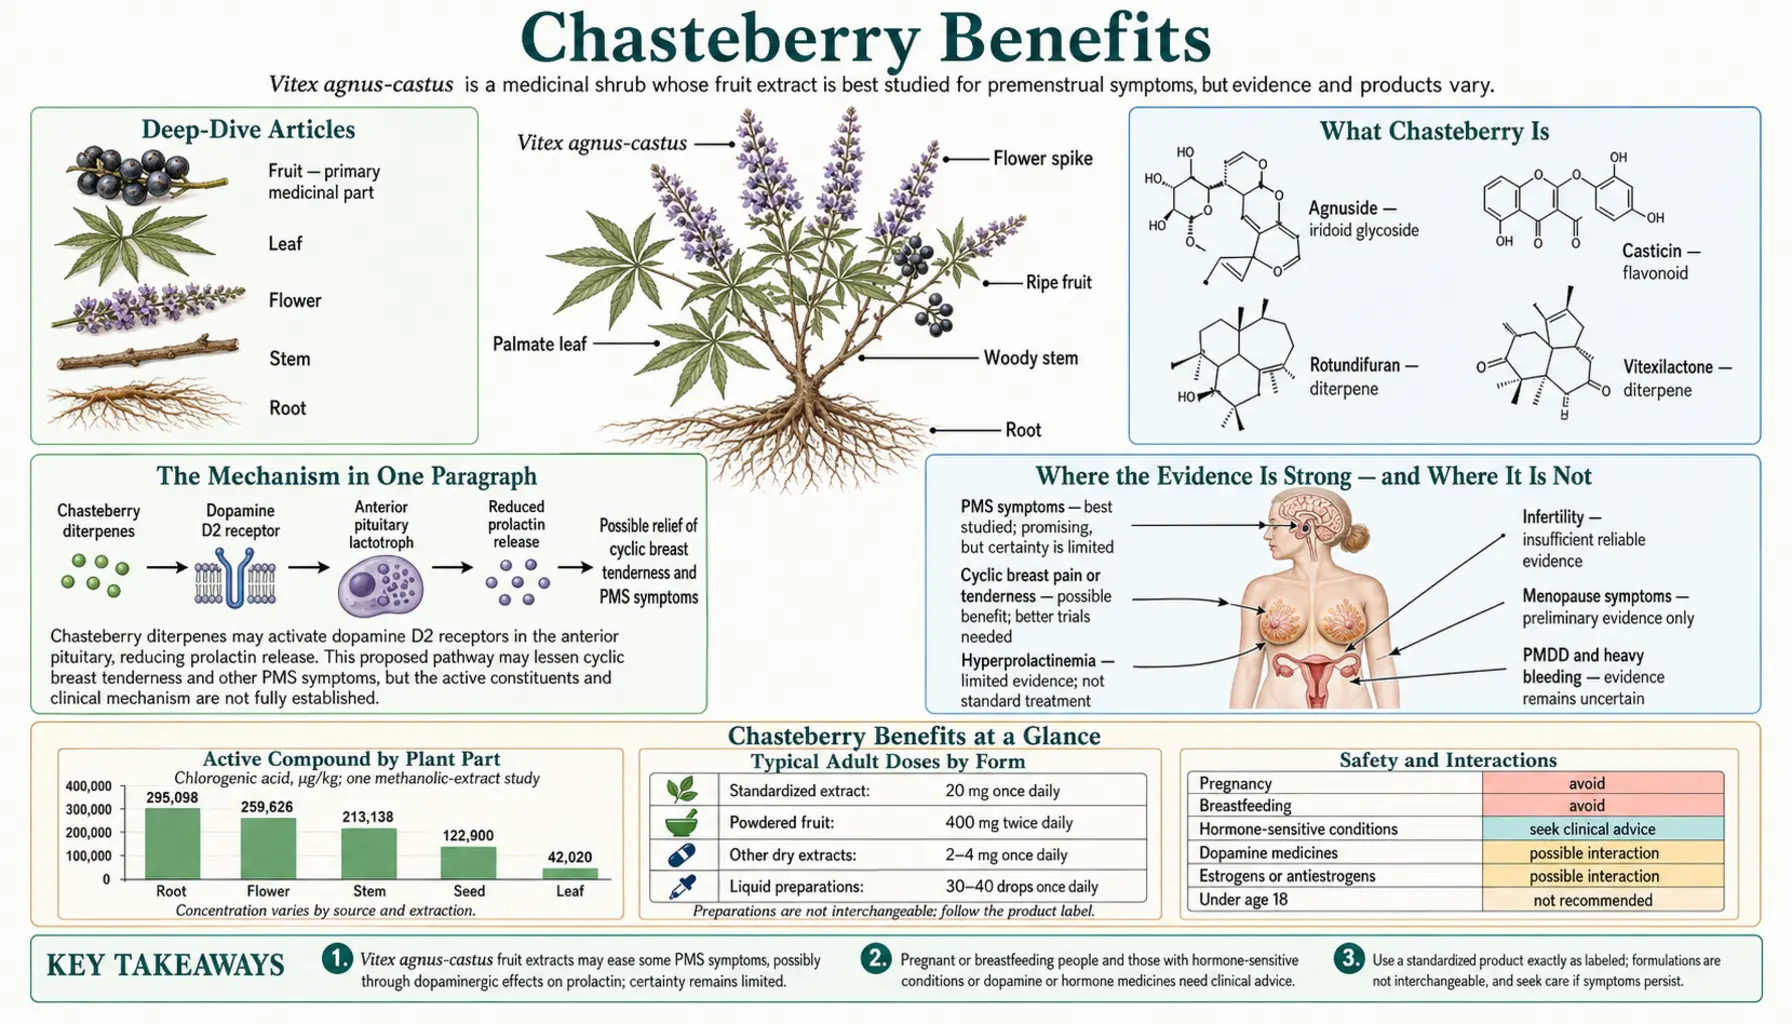
Chasteberry is the dried fruit of Vitex agnus-castus L., a Mediterranean shrub with lilac flower spikes and hard, peppercorn-sized berries. Botanists once filed it under Verbenaceae; modern molecular classification places it in the mint family, Lamiaceae. Its folk names all point the same direction — chaste tree, agnus castus ("chaste lamb"), and monk's pepper, from the medieval belief that monastery gardeners ground the peppery berries as a seasoning to help keep their vows. That story is worth telling because it is memorable, and worth correcting because it is not what the herb does: there is no credible modern evidence that chasteberry suppresses libido.
What it does do is more interesting, and unusually well characterised for a herbal medicine. Extracts of the fruit bind the dopamine D2 receptor on pituitary cells and imitate dopamine's natural braking signal on prolactin. That single, testable mechanism explains the shape of the evidence: the trial record is strongest where prolactin and the second half of the cycle are involved — premenstrual symptoms and cyclical breast pain — and gets progressively thinner as you move away from that target, toward fertility, polycystic ovary syndrome (PCOS) and menopause.
These four articles go past the summary on the main Chasteberry page and into the trials themselves: who was enrolled, which extract at which dose, for how long, and what the number actually was. Two expectations to carry in from the start. First, the good evidence attaches to two specific standardised extracts — a dry-extract tablet studied at 20 mg a day and a second extract equal to 40 mg of herb a day — not to "chasteberry" as a generic ingredient. Second, it is slow: essentially every positive trial ran for three menstrual cycles, and that is the span the evidence covers.
Table of Contents
Deep-Dive Articles
The trial record is largest for premenstrual syndrome (PMS) and cyclical breast pain; the other uses have less behind them.
PMS and Cyclical Breast Pain
The strongest evidence on this page: the 170-woman BMJ trial of a dry-extract tablet, the 217-woman Chinese trial of a second standardised extract, the dose-ranging study that settled on 20 mg, and the meta-analysis that pooled 718 women for cyclical mastalgia — alongside the reviewers who call the trial base biased and heterogeneous.
Read the deep dive →Cycle Regulation and Fertility
The 1993 Milewicz trial on luteal phase defect and latent hyperprolactinaemia — the single best study behind the "cycle-regulating" claim, and a small one. Why the fertility evidence is confounded by combination products, and the mechanism argument against chasteberry for polycystic ovary syndrome and menopause.
Read the deep dive →Prolactin and Hormonal Mechanism
Dopamine as prolactin's brake, the D2 receptor binding assays, the diterpene rotundifuran and its relatives, the iridoids agnuside and aucubin, casticin and apigenin at oestrogen receptor beta — and why the mechanism predicts what chasteberry can and cannot treat.
Read the deep dive →Forms, Dosing and Interactions
The two trial-tested standardised extracts versus the unlabelled capsule, what to look for on a label, the real side-effect profile from a systematic adverse-event review, and the interactions that follow from a dopaminergic herb — antipsychotics, metoclopramide, bromocriptine, contraception, in vitro fertilisation and pregnancy.
Read the deep dive →What Chasteberry Is
Vitex agnus-castus is a deciduous shrub or small tree native to the Mediterranean basin and Central Asia, hardy enough to be planted as an ornamental far outside its range. The medicinal part is the ripe dried fruit — small, hard, dark reddish-brown berries with a faint peppery bite. Every product on the market, from tinctures to 20 mg tablets, starts there.
The fruit is a mixture, not a single drug, and four constituent groups matter:
- Iridoid glycosides — agnuside and aucubin. These are the compounds most often printed on a certificate of analysis, because they are easy to measure by high-performance liquid chromatography (HPLC) and stable enough to serve as quality markers. They are markers, not the active principle: no one has shown that agnuside content predicts clinical effect.
- Labdane diterpenes — rotundifuran, vitexilactone, and 6β,7β-diacetoxy-13-hydroxy-labda-8,14-diene. These are the compounds that carry the dopaminergic activity. Analytical work found rotundifuran at roughly 0.04–0.30 percent of the dried fruit and 1.04–2.23 percent of the extract, a spread of about sevenfold between commercial samples — a concrete reason two "chasteberry" products need not behave alike. A 2003 review from the research group behind the 1994 rat-cell work names a different set of diterpenes, certain clerodadienols, as the most important for lowering prolactin, and describes them as "almost identical" to dopamine itself in that effect.
- Flavonoids — casticin, vitexin, penduletin and apigenin. Casticin is a second common standardisation marker. Apigenin turned out to be the compound responsible for chasteberry's weak, oestrogen-receptor-beta-selective activity.
- Essential oil — largely 1,8-cineole, sabinene and pinenes. It gives the berry its aroma and its peppery taste; it is not the reason anyone takes it.
The Mechanism in One Paragraph
Prolactin is made by lactotroph cells in the anterior pituitary. Unlike most pituitary hormones, prolactin's default is on: the hypothalamus holds it down by dripping dopamine onto D2 receptors on those cells. Remove the dopamine and prolactin rises — which is exactly why dopamine-blocking drugs such as antipsychotics and metoclopramide raise prolactin as a side effect. Chasteberry extract contains a compound that binds the D2 receptor and mimics that braking signal. This was demonstrated directly in 1994 in a rat pituitary cell system, where the extract inhibited prolactin release without touching luteinizing hormone (LH) or follicle-stimulating hormone (FSH), and it was traced in 2000 to the lipophilic diterpene fraction. Because prolactin excess shortens and weakens the luteal phase and makes breast tissue tender, a herb that gently lowers prolactin lands on premenstrual syndrome, cyclical mastalgia and luteal-phase problems, the uses this mechanism explains best. Chasteberry is not an oestrogen and not a progesterone; that is the single most common misunderstanding about it.
Where the Evidence Is Strong — and Where It Is Not
| Use | Best available evidence | Honest verdict |
|---|---|---|
| Premenstrual syndrome | Multiple double-blind placebo-controlled trials of two standardised extracts; two meta-analyses plus two further systematic reviews | The flagship use. Real, replicated, moderate in size — and reviewers flag risk of bias, incomplete reporting and industry funding |
| Cyclical breast pain (mastalgia) | Placebo-controlled trials plus a 2020 meta-analysis pooling 718 women. In the same review, 7 trials found chasteberry non-inferior to drugs: dopamine agonists, anti-inflammatory painkillers, serotonin reuptake inhibitors and hormonal contraceptives; the risk of bias in most studies was unclear | The best mechanistic fit. Moderate effect size; typical studied dose 20–40 mg/day for 3 months |
| Luteal phase defect with latent hyperprolactinaemia | One randomised placebo-controlled trial (52 enrolled, 37 analysed, 1993). Side effects were not seen, and 2 women on the herb became pregnant | Positive and mechanistically coherent, but a single small old study is a thin foundation |
| Premenstrual dysphoric disorder (PMDD) | Two small comparator trials; one found chasteberry comparable to fluoxetine, one found fluoxetine better | Thin and mixed. This disorder can be disabling, and these two trials do not establish chasteberry for it |
| Fertility / trying to conceive | Small trials, mostly of multi-ingredient products in which chasteberry was one of several actives | Not an established fertility treatment. The combination design makes chasteberry's own contribution unknowable |
| Polycystic ovary syndrome | One 2026 randomised double-blind trial of chasteberry alone: 60 women, 5.8 mg a day or placebo for 12 weeks. Oxidative-stress markers, fasting sugar and insulin resistance (HOMA-IR −0.31) improved against placebo, and menstrual frequency improved. A secondary analysis of 40 blood samples reported lower tumour necrosis factor-alpha, interleukin-6 and anti-Müllerian hormone | One small new trial from one university group, mostly blood-marker outcomes, and its authors call for further investigation. The mechanism argument still stands against it: polycystic ovary syndrome is an androgen and insulin problem, not a prolactin problem |
| Menopausal hot flushes | One 2026 randomised double-blind placebo trial: 60 postmenopausal women aged 40–65, one capsule of extract a day for 60 days, with significant improvement on three menopause symptom scales (Blatt-Kupperman Index, Menopause-Specific Quality of Life, Menopause Rating Scale) | The mechanism runs out here. There is no cycle left to regulate. The trial is a single-centre study funded by the extract's makers, whose staff are among its authors, and those authors say larger trials are needed |
| Reducing libido ("monk's pepper") | Folklore only | Not supported by any modern pharmacology |
Two premenstrual-syndrome reviews put numbers on this. Csupor and colleagues found women on the two well-described extracts 2.57 times more likely to have their symptoms remit than women on placebo (95 percent confidence interval 1.52–4.35). Verkaik and colleagues found a large pooled effect in placebo-controlled trials but called it "merely explorative and, at best, overestimating the real treatment effect".
There is also a real-world record: 1,700 women treated for about 3 months for menstrual disorders, in whom irregular cycles fell from 9.1 percent to 0.1 percent and breast tenderness from 39.9 percent to 0.8 percent. That study looked back through records and telephone interviews, had no comparison group, and most of its authors work for the product's maker, so it cannot show that the herb caused the change.
The Three-Cycle Rule
Almost every trial worth citing ran for three menstrual cycles — the BMJ study, the two Chinese trials, the dose-ranging study, the Japanese study, most of the mastalgia trials, the luteal-phase trial. The idea offered for that length is that chasteberry shifts a hormonal set-point, and a set-point moves over cycles, not over days; that is reasoning from the mechanism, not a trial result. The breast-pain trials do not all fit it. One measured only months one and two, and at month two breast pain scores were 6.4 points lower than placebo on chasteberry (3.2–4.8 mg a day, a low dose) and 7.0 points lower on flaxseed. Another was significant at cycles one and two and only borderline (p = 0.064) at cycle three.
Two consequences follow. Stopping after three weeks because "nothing happened" falls short of what the trials tested. And marketing on a bottle that promises full relief in the first cycle goes beyond the trial literature. The Japanese open-label study is instructive on the shape of the response: in 69 patients on 20 mg a day, the symptom score fell significantly after the first cycle and kept falling through cycles two and three, with the responder rate climbing over time to 91.0 percent at cycle three. That study had no placebo arm, so part of that figure may be placebo response. Some benefit early, most of it later.
On stopping, three full cycles at a studied dose is the span the trials cover. Whether anything changes after that, for women who noticed nothing by then, is not what these trials measured.
Why a Raised Prolactin Is Not a Diagnosis
This deserves its own section, because it is the place where self-treating with chasteberry can do genuine harm — not through toxicity, but through delay.
If a blood test comes back with a high prolactin, that is a finding that requires an explanation, not a condition to be treated. The differential includes a prolactinoma (a benign pituitary tumour, the most common functioning pituitary adenoma), hypothyroidism (a high thyroid-stimulating hormone (TSH) drives prolactin up, and the fix is thyroid hormone), medications — antipsychotics, metoclopramide and domperidone, some antidepressants, opioids, verapamil — chronic kidney disease, chest-wall injury, pregnancy, and the laboratory artefact macroprolactin, in which an inert antibody-bound prolactin inflates the assay in someone who is entirely well.
Taking a herb that nudges prolactin down does nothing about a pituitary adenoma, an untreated thyroid, or a drug that needs reviewing — but it can blur the picture and postpone the work-up. Endocrine society guidance for hyperprolactinaemia is explicit that the diagnostic sequence comes first: confirm the elevation, exclude pregnancy, review medications, check thyroid and renal function, screen for macroprolactin, and image the pituitary when the level is persistently and substantially raised. The chasteberry trials listed on this page enrolled women with cyclical symptoms or latent hyperprolactinaemia; none tested it as a response to a number on a lab report that has not been explained.
Cautions That Actually Matter
The safety profile in trials is genuinely reassuring — a systematic review of adverse events found them mild and reversible, most often nausea, headache, gastrointestinal upset, menstrual changes, acne, itching and rash, with no reported drug interactions in the published record. But "no reported interactions" is a statement about what has been studied, not a clean bill of health. The interactions that matter follow from the pharmacology:
- Dopamine antagonists — antipsychotics (haloperidol, risperidone, amisulpride and others), metoclopramide, domperidone. A dopaminergic herb pulls against a dopamine-blocking drug. The same adverse-event review that found no documented interactions still names this as a theoretical interaction.
- Dopamine agonists — bromocriptine, cabergoline, and Parkinson's drugs such as ropinirole and pramipexole. Here the concern is additive effect rather than opposition. Chasteberry has been compared head-to-head with bromocriptine for hyperprolactinaemia with mastalgia; the papers on this page do not test taking both together.
- Prolactin-lowering therapy generally — when a drug dose is being set against a prolactin level, an unmeasured second agent that moves the same number makes that dose harder to set.
- Hormonal contraception — genuinely unclear. The BMJ trial allowed oral contraceptives: 23 women (13 percent) were taking them, and a subgroup analysis leaving them out did not alter the results. That is mildly reassuring, but no interaction study was found. Whether chasteberry could "regulate" a cycle that a contraceptive is already controlling has not been studied.
- In vitro fertilisation (IVF) and assisted reproduction — stimulated cycles are pharmacologically choreographed, and an unquantified dopaminergic agent is an uncontrolled variable.
- Pregnancy — the 2005 adverse-event review states that use "should be avoided during pregnancy or lactation." A systematic review of chasteberry in pregnancy and lactation found the evidence base to be theoretical and expert opinion only, with in-vitro suggestions of hormonal and uterine activity and no adequate human safety data. Its authors note that because chasteberry is used by women of childbearing age, some will take it while unknowingly pregnant, so the question arises as soon as conception is a possibility.
- Breastfeeding — the same 2005 review covers lactation. Prolactin drives milk production, so a prolactin-lowering herb pushes in the opposite direction. Traditional lore pointed both ways; the mechanism does not.
One fact sits apart from all of the above: new, one-sided, focal or persistent breast pain, a lump, skin change or nipple discharge is not the pattern of cyclical mastalgia. These are the signs breast clinics check for cancer.
Key Research Papers
Every PMID below was checked live against NCBI E-utilities — first author, title, journal and year all had to match before the number was printed. Where a paper could not be confirmed that way, the entry carries a PubMed topic search instead of an identifier that might point at the wrong article.
Premenstrual syndrome — the trials
- Schellenberg R. Treatment for the premenstrual syndrome with agnus castus fruit extract: prospective, randomised, placebo controlled study. BMJ. 2001;322(7279):134–137 — PubMed PMID: 11159568 — The landmark study: 178 screened, 170 evaluated, a dry-extract tablet once daily over three cycles; responder rates 52 percent active versus 24 percent placebo.
- He Z, Chen R, Zhou Y, et al. Treatment for premenstrual syndrome with Vitex agnus castus: a prospective, randomized, multi-center placebo controlled study in China. Maturitas. 2009;63(1):99–103 — PubMed PMID: 19269753 — 217 women randomised to a standardised extract (equal to 40 mg of herb) or placebo for three cycles; note the honest detail in the abstract — a 50 percent placebo effect.
- Schellenberg R, Zimmermann C, Drewe J, Hoexter G, Zahner C. Dose-dependent efficacy of the Vitex agnus castus extract Ze 440 in patients suffering from premenstrual syndrome. Phytomedicine. 2012;19(14):1325–1331 — PubMed PMID: 23022391 — 162 women, four arms — placebo, 8 mg, 20 mg, 30 mg. Only 20 mg beat both placebo and 8 mg, and 30 mg added nothing.
- Ma L, Lin S, Chen R, Wang X. Treatment of moderate to severe premenstrual syndrome with Vitex agnus castus (BNO 1095) in Chinese women. Gynecological Endocrinology. 2010;26(8):612–616 — PubMed PMID: 20334585 — A smaller companion trial (67 women) in which negative affect and water retention improved most.
- Momoeda M, Sasaki H, Tagashira E, Ogishima M, Takano Y, Ochiai K. Efficacy and safety of Vitex agnus-castus extract for treatment of premenstrual syndrome in Japanese patients: a prospective, open-label study. Advances in Therapy. 2014;31(3):362–373 — PubMed PMID: 24604699 — Open-label, single arm, no placebo: 69 patients, 20 mg a day for three cycles; responder rate 91.0 percent at cycle three.
Systematic reviews and meta-analyses — including the criticism
- Verkaik S, Kamperman AM, van Westrhenen R, Schulte PFJ. The treatment of premenstrual syndrome with preparations of Vitex agnus castus: a systematic review and meta-analysis. American Journal of Obstetrics and Gynecology. 2017;217(2):150–166 — PubMed PMID: 28237870 — A large pooled effect (Hedges g −1.21) that the authors themselves call explorative and probably inflated — heterogeneity 91 percent, high risk of bias, evidence of publication bias. In their words, "at best, overestimating the real treatment effect".
- Csupor D, Lantos T, Hegyi P, et al. Vitex agnus-castus in premenstrual syndrome: a meta-analysis of double-blind randomised controlled trials. Complementary Therapies in Medicine. 2019;47:102190 — PubMed PMID: 31780016 — Applied CONSORT herbal-reporting standards and found only three of 21 trials adequate; those three (520 women) gave a relative risk of remission of 2.57 (95 percent confidence interval 1.52–4.35).
- van Die MD, Burger HG, Teede HJ, Bone KM. Vitex agnus-castus extracts for female reproductive disorders: a systematic review of clinical trials. Planta Medica. 2013;79(7):562–575 — PubMed PMID: 23136064 — Twelve randomised trials across premenstrual syndrome, premenstrual dysphoric disorder and latent hyperprolactinaemia — the clearest map of what has actually been tested.
- Cerqueira RO, Frey BN, Leclerc E, Brietzke E. Vitex agnus castus for premenstrual syndrome and premenstrual dysphoric disorder: a systematic review. Archives of Women's Mental Health. 2017;20(6):713–719. — PubMed PMID: 29063202
Cyclical breast pain
- Ooi SL, Watts S, McClean R, Pak SC. Vitex agnus-castus for the treatment of cyclic mastalgia: a systematic review and meta-analysis. Journal of Women's Health. 2020;29(2):262–278 — PubMed PMID: 31464546 — 25 studies reviewed; a conservative meta-analysis of six (718 women) gave a moderate effect size, standardised mean difference (SMD) 0.67 (95 percent confidence interval 0.5–0.85). Typical dose 20–40 mg/day for three months.
- Halaska M, Beles P, Gorkow C, Sieder C. Treatment of cyclical mastalgia with a solution containing a Vitex agnus castus extract: results of a placebo-controlled double-blind study. The Breast. 1999;8(4):175–181 — PubMed PMID: 14731436 — Significant at cycles one and two — and only "borderline" (p = 0.064) at cycle three, a nuance usually lost in secondary citations.
- Mirghafourvand M, Mohammad-Alizadeh-Charandabi S, Ahmadpour P, Javadzadeh Y. Effects of Vitex agnus and flaxseed on cyclic mastalgia: a randomized controlled trial. Complementary Therapies in Medicine. 2016;24:90–95 — PubMed PMID: 26860808 — 159 women in three arms (chasteberry 3.2–4.8 mg a day, flaxseed powder 25 g a day, placebo); chasteberry and flaxseed both beat placebo at months one and two. The abstract reports no test of one against the other.
Mechanism — dopamine, prolactin and the diterpenes
- Jarry H, Leonhardt S, Gorkow C, Wuttke W. In vitro prolactin but not LH and FSH release is inhibited by compounds in extracts of Agnus castus: direct evidence for a dopaminergic principle by the dopamine receptor assay. Experimental and Clinical Endocrinology. 1994;102(6):448–454 — PubMed PMID: 7890021 — The founding demonstration of D2 binding — rat pituitary cells, prolactin suppressed, gonadotropins untouched.
- Meier B, Berger D, Hoberg E, Sticher O, Schaffner W. Pharmacological activities of Vitex agnus-castus extracts in vitro. Phytomedicine. 2000;7(5):373–381 — PubMed PMID: 11081988 — Localised the D2 activity to the lipophilic diterpene fraction (rotundifuran and relatives) and found additional binding at mu and kappa opioid receptors.
- Hoberg E, Meier B, Sticher O. Quantitative high performance liquid chromatographic analysis of diterpenoids in agni-casti fructus. Planta Medica. 2000;66(4):352–355 — PubMed PMID: 10865453 — Where the rotundifuran percentages quoted above come from.
- Wuttke W, Jarry H, Christoffel V, Spengler B, Seidlová-Wuttke D. Chaste tree (Vitex agnus-castus) — pharmacology and clinical indications. Phytomedicine. 2003;10(4):348–357. — PubMed PMID: 12809367
Cycle, fertility and safety
- Milewicz A, Gejdel E, Sworen H, et al. [Vitex agnus castus extract in the treatment of luteal phase defects due to latent hyperprolactinemia. Results of a randomized placebo-controlled double-blind study]. Arzneimittel-Forschung. 1993;43(7):752–756 — PubMed PMID: 8369008 — German-language; 52 women enrolled, 37 analysed, 20 mg daily for three months. Shortened luteal phases normalised and luteal progesterone rose in the active group only. Side effects were not seen; two women on the extract became pregnant.
- Daniele C, Thompson Coon J, Pittler MH, Ernst E. Vitex agnus castus: a systematic review of adverse events. Drug Safety. 2005;28(4):319–332 — PubMed PMID: 15783241 — Adverse events mild and reversible; no drug interactions reported; the authors state use "should be avoided during pregnancy or lactation"; theoretical interference with dopaminergic antagonists.
- Dugoua JJ, Seely D, Perri D, Koren G, Mills E. Safety and efficacy of chastetree (Vitex agnus-castus) during pregnancy and lactation. Canadian Journal of Clinical Pharmacology. 2008;15(1):e74–e79. — PubMed PMID: 18204102
- Melmed S, Casanueva FF, Hoffman AR, et al. Diagnosis and treatment of hyperprolactinemia: an Endocrine Society clinical practice guideline. The Journal of Clinical Endocrinology and Metabolism. 2011;96(2):273–288 — PubMed PMID: 21296991 — The guideline behind the diagnostic sequence described above.
- Höller M, Steindl H, Abramov-Sommariva D, Kleemann J, Loleit A, Abels C, Stute P. Use of Vitex agnus-castus in patients with menstrual cycle disorders: a single-center retrospective longitudinal cohort study. Archives of Gynecology and Obstetrics. 2024;309(5):2089–2098 — PubMed PMID: 38393671 — 1,700 women; retrospective, no comparison group, most authors employed by the product's maker.
Polycystic ovary syndrome and menopause — newer trials
- Hatami A, Seidi F, Khosrowbeygi A, Moslemi A, Jalali-Mashayekhi F. The effect of Vitex agnus-castus plant on some markers of oxidative stress, lipid profile and insulin resistance in women with polycystic ovary syndrome: a randomized, double-blind controlled clinical trial study. JBRA Assisted Reproduction. 2026;30(1):70–78 — PubMed PMID: 41428718
- Hatami A, Taheri H, Khosrowbeygi A, Seidi F, Azimi M, Jalali-Mashayekhi F. The effects of Vitex agnus-castus supplementation on inflammatory markers in women with PCOS: a randomized, double-blind, placebo-controlled trial. Research in Pharmaceutical Sciences. 2026;21(2):206–214 — PubMed PMID: 42163905
- Reddy PA, Aluri S, Ca A, Mv J, Cp P, Mohamed F, Rani SM, Lee H, Earanimose B. Efficacy and safety of Vitex extract on menopausal symptoms and quality of life in postmenopausal women: a randomized placebo-controlled trial. Cureus. 2026;18(9):e116507 — PubMed PMID: 42894752 — Single-centre; funded by the extract's makers, whose staff are among the authors.
PubMed Topic Searches
External Resources
- U.S. National Center for Complementary and Integrative Health — Chasteberry
- LactMed — U.S. National Institutes of Health Drugs and Lactation Database
- PubChem — agnuside compound record
- European Medicines Agency — Agni casti fructus herbal monograph
- World Flora Online — Vitex agnus-castus L. taxonomy
- ClinicalTrials.gov — registered chasteberry trials
Connections
- All Herbs
- Chasteberry (Vitex) — the main topic page
- PMS and Cyclical Breast Pain
- Cycle Regulation and Fertility
- Prolactin and Hormonal Mechanism
- Forms, Dosing and Interactions
- Black Cohosh — the menopause herb chasteberry is often confused with
- Dong Quai — another herb sold for menstrual complaints
- White Peony Root (Bai Shao) — the East Asian counterpart in gynaecological formulas
- Reproductive Medicine — the conditions chasteberry is used for