White Peony Root for Menstrual Health and Polycystic Ovary Syndrome (PCOS)
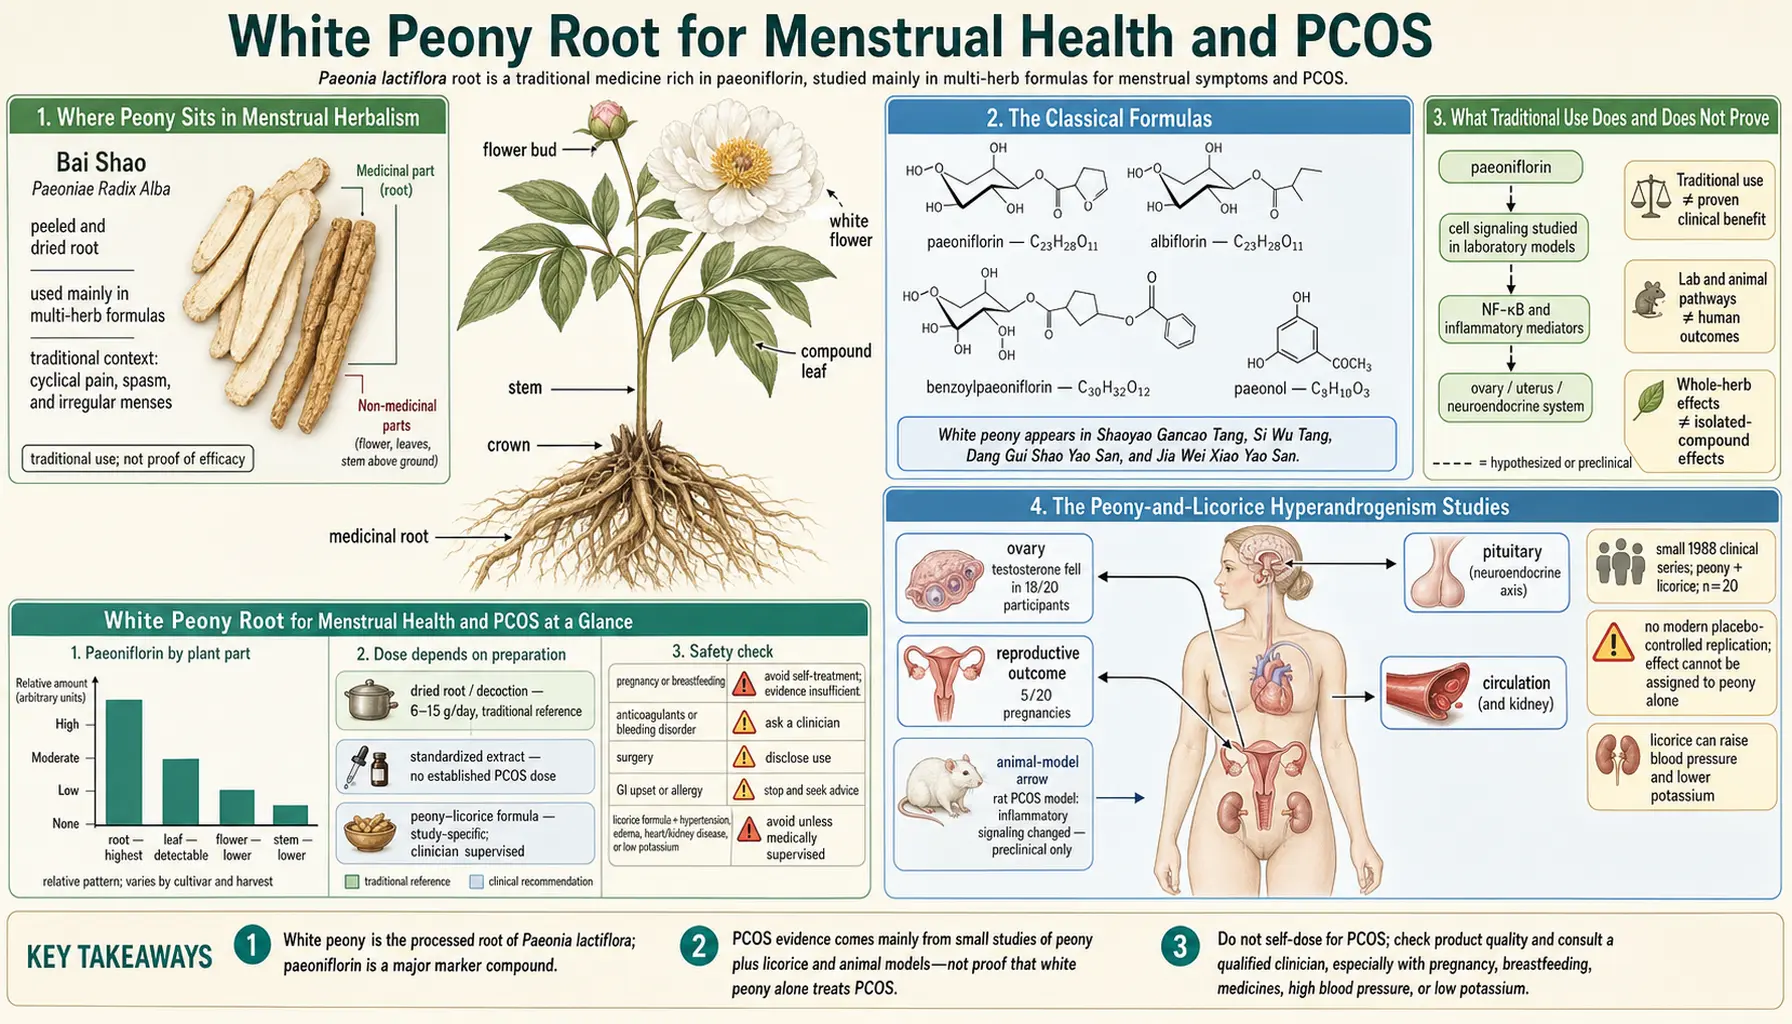
If you search for herbs for irregular periods or polycystic ovary syndrome (PCOS), white peony root — Radix Paeoniae Alba, Bai Shao, the boiled and peeled root of Paeonia lactiflora — comes up constantly, usually paired with licorice. The pairing is real, it is old, and there is a small research literature behind it. What there is not is anything resembling the evidence base that supports peony extract in rheumatoid arthritis.
This article separates the three things that get blended together in most write-ups: what East Asian medicine traditionally did with peony in women’s formulas, what the small Japanese studies of peony-and-licorice actually measured, and what a modern polycystic ovary syndrome evaluation involves — because skipping that evaluation in favour of a capsule is the genuine risk here.
Table of Contents
- Where Peony Sits in Menstrual Herbalism
- The Classical Formulas
- What Traditional Use Does and Does Not Prove
- The Peony-and-Licorice Hyperandrogenism Studies
- The Proposed Mechanism
- What Polycystic Ovary Syndrome Actually Is
- Period Pain and Cramping
- The Licorice Problem in Long-Term Use
- Forms, Doses and Label Reading
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Where Peony Sits in Menstrual Herbalism
In classical Chinese medicine, white peony root belongs to the category of blood-nourishing herbs and is described as softening the liver, relieving pain and stopping spasm. Translated out of that framework, the practical pattern of use is recognisable: peony appears in formulas given to women with irregular or scanty cycles, cramping pain, irritability and tension around menstruation.
Two things follow from that. First, peony is almost never used alone in this context — it is one component of a multi-herb formula, and the formula is selected for the individual pattern, not the diagnosis. Second, because it is always in company, it is close to impossible to attribute any traditional result to peony specifically. When somebody says “peony has been used for menstrual problems for a thousand years,” the accurate version is “formulas that contain peony have been.”
The Classical Formulas
Four formulas account for most of peony’s gynaecological use. Knowing them helps you read a product label, because commercial versions carry these names.
| Formula | Japanese name | Peony’s companions | Traditional use |
|---|---|---|---|
| Si Wu Tang (四物湯) | Shimotsu-to | Prepared rehmannia, dong quai, chuanxiong | The foundational blood-nourishing formula; base of many gynaecological prescriptions |
| Xiao Yao San (逍遙散) | Shoyosan | Bupleurum, dong quai, atractylodes, poria, licorice, ginger, mint | Irritability, tension, breast tenderness and cycle irregularity — the “free and easy wanderer” |
| Dang Gui Shao Yao San (當歸芍藥散) | Tokishakuyakusan | Dong quai, chuanxiong, poria, atractylodes, alisma | Cramping period pain with fluid retention, pallor and feeling cold |
| Shao Yao Gan Cao Tang (芍藥甘草湯) | Shakuyaku-kanzo-to | Licorice only — two herbs | Cramp and spasm; the formula used in the hyperandrogenism studies |
Note the last row. The peony-and-licorice studies discussed below did not test white peony root. They tested a two-herb formula, and licorice turns out to be pharmacologically busy in its own right — which is both the interesting part and the safety problem.
What Traditional Use Does and Does Not Prove
Long use is genuinely informative about some things and silent about others. It is worth being explicit:
- What it suggests: that ordinary decoction doses are unlikely to cause obvious, immediate, common harm. A remedy that regularly made people acutely ill would have been dropped.
- What it does not establish: whether the herb works better than placebo, whether it changes hormone levels, whether it improves fertility, or whether it is safe taken daily for years as a concentrated extract — a form of exposure that traditional practice never involved.
- Why menstrual conditions are especially hard: cycle symptoms fluctuate naturally, respond strongly to expectation and attention, and improve on their own in many people. This is an area where uncontrolled observation reliably produces false positives.
The Peony-and-Licorice Hyperandrogenism Studies
The specific claim that peony lowers testosterone in women traces back to a small cluster of Japanese studies, most of them from the 1980s and early 1990s, using shakuyaku-kanzo-to (peony plus licorice, sold as a Kampo extract formulation).
The broad shape of that work:
- Yaginuma and colleagues (1982) gave peony-and-licorice, 5–10 g a day for 2–8 weeks, to eight infertile women with elevated androgens and infrequent periods. Serum testosterone fell below 50 ng/dl in seven of them; six of those seven ovulated regularly, and two of the six conceived.
- Takeuchi and colleagues (1991) examined paeoniflorin, glycyrrhizin and glycyrrhetic acid in homogenised rat ovarian tissue and found that all three lowered testosterone production without changing androstenedione or oestradiol production — the laboratory (rat-tissue) basis for the clinical observation.
- Takahashi and Kitao (1994) gave a Kampo extract formulation of shakuyaku-kanzo-to, 7.5 g a day, to 34 Japanese women with polycystic ovarian disease for 24 weeks, with no control group. They reported significant falls in total and free testosterone within four weeks, a lower luteinizing hormone (LH)/follicle-stimulating hormone (FSH) ratio by 24 weeks, and pregnancy in a proportion of the participants. After 12 weeks, mean testosterone in the women who became pregnant had fallen to 35% of its starting level, while it did not change in the women who did not conceive.
Now the limitations, which are severe and need stating plainly:
- The studies are tiny. Participant numbers are typically in the range of eight to forty women. Hormone studies at that scale are hypothesis-generating, full stop.
- Most were not randomized or placebo-controlled. Several were open-label before-and-after observations, the design most vulnerable to regression to the mean — and androgen levels and cycle regularity both fluctuate.
- They are old and essentially unreplicated. Three decades on, there is no large, modern, well-controlled trial confirming that peony-and-licorice lowers androgens or restores ovulation.
- The diagnostic definitions predate current criteria. “Polycystic ovarian disease” in a 1994 Japanese cohort is not necessarily the same population as polycystic ovary syndrome diagnosed today by Rotterdam criteria.
- Nobody knows which herb did what. Licorice alone has documented effects on steroid metabolism. Attributing the result to peony is an assumption, not a finding.
A 2021 Cochrane review of Chinese herbal medicine in general (not peony-and-licorice specifically) for women with polycystic ovary syndrome who want to become pregnant found eight randomised trials with 609 women. None of the trials reported live births, and the reviewers found insufficient evidence to support the herbs for this use. Adding herbs to clomiphene may raise pregnancy rates (odds ratio 3.06), but that evidence was low certainty, and only one trial reported data on side effects, so the review could not say whether the herbs are safe.
The honest verdict: this is a genuine, interesting, unfinished line of research. It is not a basis for treating a hormonal condition, and anyone presenting it as “proven to lower testosterone naturally” is overselling three small old studies.
The Proposed Mechanism
The suggested explanation runs through the enzymes of steroid production. Ovarian theca cells make androgens; granulosa cells convert some of that androgen into oestradiol using the enzyme aromatase. Think of it as a two-stage assembly line: one station builds testosterone, the next converts part of it onward.
The laboratory work on peony-and-licorice constituents has been read as suggesting a shift in that balance — less androgen produced, and/or more of it converted onward — with the net effect of lowering circulating testosterone. Both paeoniflorin and the licorice constituents glycyrrhizin and glycyrrhetinic acid have been implicated.
One study tried to separate the two herbs, in rats. Takeuchi and colleagues (1989) gave androgen-sterilised rats the combined formula, peony alone or licorice alone every day for two weeks. The formula and peony alone lowered total testosterone in a dose-dependent way. Licorice alone lowered it slightly at low doses but raised it at much higher doses, by far less than peony lowered it. In rats whose ovaries had been removed, none of the three changed testosterone, which points to the ovary as the site of action. These are animal results.
Two cautions on this mechanism. First, effects seen in isolated cells or tissue preparations at chosen concentrations frequently fail to appear in a whole human body, where absorption, metabolism and feedback loops intervene. Paeoniflorin’s oral bioavailability is modest, which makes the leap from tissue bath to bloodstream more, not less, uncertain. Second, in polycystic ovary syndrome the hormonal picture is driven substantially by insulin resistance and abnormal gonadotrophin signalling upstream of the ovary. Nudging one ovarian enzyme, if that is even what happens, addresses a symptom of the system rather than the system.
What Polycystic Ovary Syndrome Actually Is
Polycystic ovary syndrome is the most common hormonal condition in women of reproductive age, and it is chronically misunderstood — including by people selling herbs for it. It is diagnosed by the Rotterdam criteria, which require two of these three features, after other causes have been excluded:
- Irregular or absent ovulation — long, unpredictable or missing cycles.
- Clinical or biochemical hyperandrogenism — excess hair growth, persistent acne, scalp hair thinning, or raised testosterone on blood testing.
- Polycystic ovarian morphology on ultrasound — many small follicles, which are not cysts and are not painful.
The 2023 International PCOS Guideline (254 recommendations and practice points) added a blood test, anti-Müllerian hormone (AMH), as an alternative to the ultrasound for diagnosis in adults only, not in teenagers. It also stated that the evidence behind polycystic ovary syndrome care, although improved, remains generally of low to moderate quality.
The phrase “after other causes have been excluded” is the part that matters most, and it is the reason self-treating with peony is a real risk rather than a theoretical one. Conditions that mimic polycystic ovary syndrome include thyroid disease, hyperprolactinaemia (sometimes from a pituitary tumour), non-classical congenital adrenal hyperplasia, Cushing’s syndrome, and androgen-secreting tumours. Several are straightforward to treat once identified. Thyroid disease and prolactinoma mimic polycystic ovary syndrome, are treatable once found, and are not treated by herbal capsules.
Polycystic ovary syndrome also carries long-term metabolic consequences — insulin resistance, raised risk of type 2 diabetes, gestational diabetes, and lipid abnormalities — plus a risk of endometrial overgrowth when cycles are chronically absent, because the uterine lining is not being shed regularly. Those risks are managed, not cured, and they are not managed by an herb.
What actually has evidence in Polycystic Ovary Syndrome
- Weight management and exercise where relevant — modest weight loss can restore ovulation and improve insulin sensitivity, and this remains first-line in international guidelines.
- Combined hormonal contraception for cycle regulation, androgenic skin and hair symptoms, and endometrial protection.
- Metformin for metabolic features and, in some settings, cycle regularity.
- Letrozole as first-line ovulation induction when pregnancy is the goal, with clomiphene as an alternative.
- Targeted treatment of hirsutism, including anti-androgens under supervision.
Peony is not on that list, and a page that told you otherwise would be doing you harm. Where it might reasonably sit is as an adjunct someone chooses alongside proper care, with realistic expectations and knowledge of the licorice issue below.
Period Pain and Cramping
The most defensible menstrual use of peony is the least glamorous one: cramping pain. Here the pharmacology is more coherent than the hormonal story. Paeoniflorin has documented antispasmodic activity on smooth muscle, and the uterus is smooth muscle. Period pain is caused largely by prostaglandin-driven uterine contractions that transiently squeeze off the muscle’s own blood supply — effectively a cramp in the uterine wall.
Dang Gui Shao Yao San (tokishakuyakusan) is the formula with the most trials in this context. A 2016 meta-analysis that searched English-language, Korean, Chinese and Japanese databases found four small randomised trials in primary dysmenorrhoea, all at high risk of bias. In three, the formula was compared with painkillers and did better on response rate (risk ratio 1.31, 95% confidence interval 1.06 to 1.63); in the fourth, it reduced pain compared with placebo. The authors rated the quality of this evidence low to moderate, so this is a modest, plausible option rather than a demonstrated one. Pain that is severe, worsening, or associated with heavy bleeding, pain during sex, or infertility raises the question of endometriosis or fibroids.
The antispasmodic pharmacology is covered in more detail in the muscle cramps article.
The Licorice Problem in Long-Term Use
Every one of the hyperandrogenism studies used peony with licorice, and licorice is where the real risk in this combination lives.
Glycyrrhizin and its active metabolite glycyrrhetinic acid inhibit the kidney enzyme 11β-hydroxysteroid dehydrogenase type 2. That enzyme normally destroys cortisol locally before it can stimulate the mineralocorticoid receptor. When it is blocked, ordinary cortisol starts acting like the salt-retaining hormone aldosterone. Sodium and water are retained, potassium is dumped into the urine, and blood pressure climbs. This is pseudoaldosteronism. A 1987 study in seven healthy volunteers given liquorice linked its sodium retention to blocking of this enzyme.
The consequences are documented in case reports and case series, not theoretical:
- Hypokalaemia — low potassium, causing muscle weakness, fatigue, cramps and in severe cases heart-rhythm disturbance.
- Hypertension, sometimes marked, and sometimes the first sign.
- Fluid retention with swollen ankles and face — unhelpful in someone taking the formula partly for premenstrual bloating.
- Metabolic alkalosis and, rarely, rhabdomyolysis in severe hypokalaemia.
Susceptibility varies a lot between individuals, and there is no safe dose that applies to everybody. Effects have been described at daily glycyrrhizin intakes that a regular Kampo or supplement user can reach. The documented facts behind those cases:
- Continuous daily use for months is where the trouble accumulates, which is why peony-and-licorice is described as an intermittent remedy.
- The effect shows up as low potassium and raised blood pressure — findings that a blood potassium test and a blood pressure reading detect.
- The research raises a particular concern for people with hypertension, heart failure, kidney disease or low potassium, and for people taking diuretics, digoxin or corticosteroids — situations in which extra sodium retention or potassium loss adds to an existing problem.
- Licorice (Glycyrrhiza, gan cao, kanzo) hides inside a lot of blends, listed on the ingredient label, because it is a near-universal formula harmoniser.
Forms, Doses and Label Reading
Products you are likely to encounter, and what they are:
| Product | What it contains | Realistic expectation |
|---|---|---|
| “White peony root” capsules | Milled crude root, typically 400–600 mg, paeoniflorin near the ≈1.6% pharmacopeial floor | A small dose of a mild herb; nothing like the extract used in autoimmune trials |
| “Peony and licorice” capsules or granules | The two-herb formula, sometimes as a Kampo extract granule | The combination actually studied — and the one carrying the licorice risk |
| Xiao Yao San / Free and Easy Wanderer | Eight-herb formula, peony one component; contains licorice | A traditional formula, not a targeted hormonal agent |
| Tokishakuyakusan / Dang Gui Shao Yao San | Six-herb formula, no licorice in the classical version | The formula with the most dysmenorrhoea trials |
| Total Glucosides of Paeony (TGP) | Standardized ≈40%+ paeoniflorin extract, a prescription drug in China | Studied in autoimmune disease, not in polycystic ovary syndrome or menstrual disorders |
Traditional decoction dose of white peony root is roughly 6–15 g of dried root per day, inside a formula. Kampo granules are dosed per the manufacturer’s sachet. There is no established supplement dose for menstrual health, because there is no trial that established one — if a label states a “clinically studied dose” for polycystic ovary syndrome, that claim has no study behind it.
A TGP capsule is stronger, but strength does not carry the evidence with it. TGP was studied in rheumatoid arthritis and related autoimmune conditions. Nobody has tested it for polycystic ovary syndrome, and greater concentration of an untested indication is not an advantage.
Cautions and Contraindications
- Pregnancy: adequate safety data for concentrated peony extracts in pregnancy do not exist. Traditional formulas containing peony are used during pregnancy in some East Asian practice under a practitioner’s supervision, but that is not the same as self-administering a modern extract. Licorice-containing formulas carry a specific concern — high licorice intake in pregnancy has been associated with adverse outcomes.
- Breastfeeding: safety has not been established.
- Trying to conceive: herbal products are frequently omitted from the medication lists fertility clinics work from, and they can complicate interpretation of hormone results.
- Hormone-sensitive conditions: if a product genuinely alters androgen or oestrogen handling, that is not automatically desirable. In the 1994 study the oestradiol-to-testosterone ratio rose significantly after four weeks of peony-and-licorice, a change that matters for people with a history of hormone-sensitive cancer.
- Blood pressure and potassium: the licorice caution above applies to any peony-and-licorice product, and it is the single most important safety point on this page.
- Anticoagulants and antiplatelets: caution — peony preparations have reported platelet effects.
- Symptoms that point to other conditions. Missed or very irregular periods, sudden hair growth, rapid weight change, milky nipple discharge, or severe worsening period pain can come from conditions such as a prolactinoma, a thyroid disorder or endometriosis. Peony does not treat a prolactinoma, a thyroid disorder, or endometriosis.
Key Research Papers
Every numbered identifier below was checked live against NCBI E-utilities — author, title, journal and year all had to match before a PMID was printed. Where an identifier could not be confirmed that way, the entry keeps a PubMed topic search instead of a possibly wrong number.
- Takeuchi T, Nishii O, Okamura T, Yaginuma T. Effect of paeoniflorin, glycyrrhizin and glycyrrhetic acid on ovarian androgen production. American Journal of Chinese Medicine. 1991;19(1):73–78. — PubMed PMID: 1897494
- Takahashi K, Kitao M. Effect of TJ-68 (shakuyaku-kanzo-to) on polycystic ovarian disease. International Journal of Fertility and Menopausal Studies. 1994;39(2):69–76. — PubMed PMID: 8012442
- Yaginuma T, Izumi R, Yasui H, Arai T, Kawabata M. Effect of traditional herbal medicine on serum testosterone levels and its induction of regular ovulation in hyperandrogenic and oligomenorrhoeic women [in Japanese]. Nihon Sanka Fujinka Gakkai Zasshi. 1982;34(7):939–944. — PubMed PMID: 7108310
- Takeuchi T, Nishii O, Okamura T, Yaginuma T. Effect of traditional herbal medicine, shakuyaku-kanzo-to, on total and free serum testosterone levels. American Journal of Chinese Medicine. 1989;17(1–2):35–44. — PubMed PMID: 2511749
- Lee HW, Jun JH, Kil KJ, Ko BS, Lee CH, Lee MS. Herbal medicine (Danggui Shaoyao San) for treating primary dysmenorrhea: a systematic review and meta-analysis of randomized controlled trials. Maturitas. 2016;85:19–26. — PubMed PMID: 26857875
- Xiao Yao San / kami-shoyo-san in premenstrual and menopausal symptoms — clinical studies. PubMed search.
- Zhou K, Zhang J, Xu L, Lim CED. Chinese herbal medicine for subfertile women with polycystic ovarian syndrome. Cochrane Database of Systematic Reviews. 2021;6(6):CD007535. — PubMed PMID: 34085287
- Farese RV Jr, Biglieri EG, Shackleton CH, Irony I, Gomez-Fontes R. Licorice-induced hypermineralocorticoidism. New England Journal of Medicine. 1991;325(17):1223–1227. — PubMed PMID: 1922210
- Stewart PM, Wallace AM, Valentino R, Burt D, Shackleton CH, Edwards CR. Mineralocorticoid activity of liquorice: 11-beta-hydroxysteroid dehydrogenase deficiency comes of age. The Lancet. 1987;2(8563):821–824. — PubMed PMID: 2889032
- Teede HJ, Tay CT, Laven J, et al. Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Fertility and Sterility. 2023;120(4):767–793. — PubMed PMID: 37589624
PubMed Topic Searches
- PubMed: Paeonia lactiflora and menstruation
- PubMed: Paeoniflorin and uterine smooth muscle
- PubMed: Shakuyaku-kanzo-to and polycystic ovary
- PubMed: Hyperandrogenism and herbal treatment
- PubMed: Primary dysmenorrhoea — herbal trials
- PubMed: PCOS ovulation induction with letrozole
- PubMed: PCOS, insulin resistance and metformin
- PubMed: Kampo medicine in gynaecology
Connections
- All Herbs
- White Peony Root (Bai Shao)
- White Peony Root Benefits — hub
- White Peony Root: History and Traditional Use
- Chasteberry — the other herb used for cycle irregularity
- Dong Quai — peony’s partner in Si Wu Tang
- Licorice — the pseudoaldosteronism risk explained
- Codonopsis