Codonopsis (Dang Shen) for Digestive and Gut Health
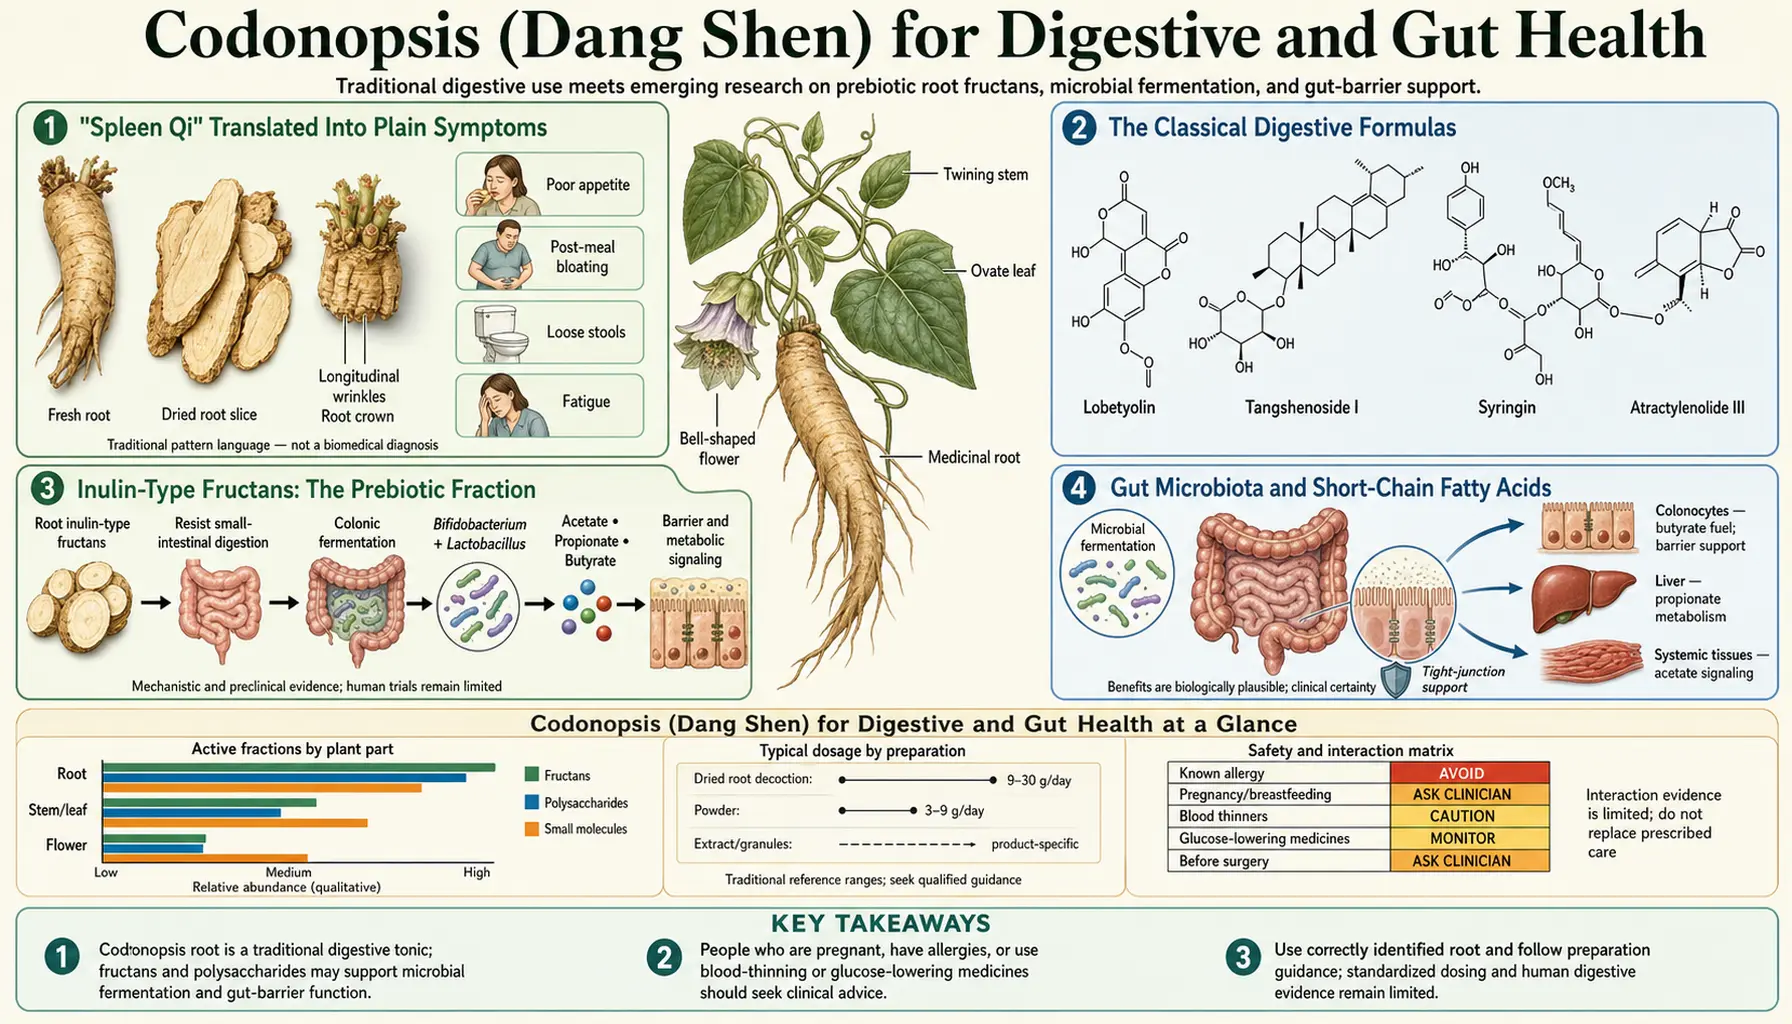
Digestion is the core traditional indication for Codonopsis — more central than immunity, more central than energy. In Chinese medicine the herb is a Spleen qi tonic, and the Spleen in that system is not the organ a Western anatomist means by the word. It is a functional description of digestion and nutrient extraction. When a Chinese herbalist says "Spleen qi deficiency," they are describing a specific and recognisable cluster of everyday symptoms, and Codonopsis is one of the four or five herbs they reach for first.
This page translates that concept into plain symptoms, explains what is actually in the root that could plausibly affect the gut, reviews the rodent gastric-mucosa work, and gives the honest caveat that gets left out of most herbal write-ups: this root is full of fermentable fibre, and fermentable fibre makes some people considerably worse.
Table of Contents
- "Spleen Qi" Translated Into Plain Symptoms
- The Classical Digestive Formulas
- Inulin-Type Fructans: The Prebiotic Fraction
- Gut Microbiota and Short-Chain Fatty Acids
- Gastric Mucosal Studies in Rodents
- Gut Barrier and Inflammation Models
- The Honest Caveat: Small Intestinal Bacterial Overgrowth, Irritable Bowel Syndrome, and FODMAPs
- Appetite, Postprandial Fatigue, and Loose Stools
- How It Is Traditionally Taken, and How People Track Its Effect
- Key Research Papers
- Connections
- Featured Videos
"Spleen Qi" Translated Into Plain Symptoms
Strip away the classical vocabulary and the Spleen-qi-deficiency picture is a list of complaints a modern gastroenterologist hears every day, usually with normal test results:
- Poor or unreliable appetite — not being hungry at mealtimes, feeling full after a few bites, having to remind yourself to eat.
- Loose, unformed, or urgent stools, sometimes with undigested food visible, often worse in the morning or after cold or raw meals.
- Postprandial fatigue — the distinctive symptom. Eating makes you more tired rather than less. Many people describe needing to lie down after lunch.
- Bloating and heaviness after eating, especially after starchy or rich meals.
- Weak, quiet voice; tired limbs; pallor; easy bruising.
- A tendency to get worse rather than better with fasting or restrictive diets — this pattern is described as needing nourishment and warmth, not clearing out.
That is a real clinical picture, and its overlap with modern diagnoses is genuine but imperfect. It intersects with functional dyspepsia, post-infectious irritable bowel syndrome (IBS), chronic fatigue presentations, undernutrition, and simple deconditioning. It also intersects with things that require a doctor rather than a herb: coeliac disease, pancreatic insufficiency, thyroid disease, inflammatory bowel disease, and iron or B12 deficiency all produce a very similar picture and all have specific effective treatments. If these symptoms are new, progressive, or come with weight loss, blood in the stool, night-time waking, fever, or anaemia, that is a workup, not a tonic.
The Classical Digestive Formulas
Codonopsis rarely appears alone. Three formulas define its digestive role:
- Si Jun Zi Tang ("Four Gentlemen Decoction") — the foundational Spleen-qi formula: Codonopsis (historically ginseng), Atractylodes, Poria, and Licorice. Four herbs, each with a distinct job: tonify, dry dampness, drain dampness, harmonise. Almost every other Spleen formula in Chinese medicine is a modification of this one.
- Shen Ling Bai Zhu San — Si Jun Zi Tang expanded with lotus seed, coix, Chinese yam, cardamom, and platycodon, aimed specifically at chronic loose stools with poor appetite.
- Bu Zhong Yi Qi Tang — Codonopsis and Astragalus with bupleurum and cimicifuga, traditionally for fatigue with digestive weakness and a sensation of downward-dragging heaviness.
Two things follow. First, traditional practice never claimed a single root was the treatment — the formula is the unit. Second, and this is the recurring problem for evidence, this makes clean trials of Codonopsis nearly impossible: the studies that exist test whole formulas, so the herb's individual contribution is not measurable.
What the formula trials show. Two reviews have pooled the formula-level trials:
- Si Jun Zi Tang for functional dyspepsia (indigestion with normal test results). A 2021 meta-analysis of 12 randomized trials found more people responded on Si Jun Zi Tang-based treatments than on the comparison treatments (relative risk 1.23; 95% confidence interval 1.17 to 1.30), but the benefit was limited to modified versions of the formula. Relapse was lower than with conventional medicines (odds ratio 0.23), and no formula-related side effects were reported. All 12 trials were judged at high risk of bias, so the authors call for larger, strictly designed trials.
- Shen Ling Bai Zhu San for chronic diarrhoea. A 2022 review of 14 randomized trials with 1,158 adults found the formula, with or without conventional medicine, was linked to greater patient-reported satisfaction than conventional medicine alone, with no increase in side effects. The authors write that rigorous trials with objective outcome measures are needed to confirm the effect.
Inulin-Type Fructans: The Prebiotic Fraction
Chemically, the digestive story is mostly about carbohydrate. A large share of Codonopsis root's dry weight is inulin-type fructans — chains of fructose units with a terminal glucose, the plant's storage carbohydrate. They are the same class of molecule found in chicory root, Jerusalem artichoke, dandelion root, onion, garlic, and leek. Alongside them sit the more complex heteropolysaccharides discussed on the immune modulation page.
Human beings do not produce the enzymes to break the fructose-fructose bonds in inulin. That single fact drives everything else: the fructans pass through the stomach and small intestine essentially intact and arrive in the colon as food for bacteria. That is the textbook definition of a prebiotic. It is also, precisely, the definition of a FODMAP — fermentable oligosaccharide. The same chemistry gives you both the possible benefit and the possible bloating. There is no way to have one without risking the other.
This also explains why the traditional preparation makes pharmacological sense. Long simmering in water extracts fructans and polysaccharides efficiently. A high-proof alcohol tincture largely does not. For gut purposes, decoction or hot-water extract is the form that matches the chemistry.
Gut Microbiota and Short-Chain Fatty Acids
When colonic bacteria ferment fructans they produce gas — hydrogen, carbon dioxide, sometimes methane — and short-chain fatty acids: acetate, propionate, and butyrate. Butyrate is the interesting one. It is the preferred fuel of colonocytes, the cells lining the large intestine, which take it up directly from the gut lumen rather than from blood. Adequate butyrate supply is associated with better barrier integrity, and butyrate acts as a signalling molecule influencing regulatory immune cells in the gut wall.
Inulin-type fructans as a class are among the best-studied prebiotics in humans, with reasonably consistent evidence that they increase Bifidobacterium abundance. Several rodent studies have specifically fed Codonopsis polysaccharide preparations and reported shifts in microbiota composition and higher short-chain fatty acid output.
Two honest qualifications. First, "changed the microbiome in mice" is not a health outcome; mouse and human gut communities differ substantially. Second, a bifidogenic shift is a plausible good thing but has not been shown to translate into symptom improvement for most conditions. The strongest fair statement is: Codonopsis root supplies a well-characterised class of prebiotic fibre, and prebiotic fibre has real but modest documented effects on gut bacterial composition.
Gastric Mucosal Studies in Rodents
The most-cited digestive experiments on Codonopsis are gastric protection models. The standard designs give rats or mice a mucosal insult — absolute ethanol, aspirin or indomethacin, water-immersion restraint stress, or acetic-acid-induced ulceration — with or without pre-treatment by Codonopsis extract or its polysaccharide fraction, then measure the resulting lesion area and tissue markers.
Reported findings across this literature include smaller lesion areas, higher gastric mucus output, higher tissue antioxidant enzyme activity (superoxide dismutase, glutathione peroxidase), lower lipid peroxidation markers, and lower inflammatory cytokine levels in stomach tissue. Some papers report effects on prostaglandin E2, the signalling molecule that maintains mucosal defence and that nonsteroidal anti-inflammatory drugs (NSAIDs) suppress.
How much weight should this carry? Some, but not a lot. Ethanol-gavage gastric injury in a rat is a crude acute chemical burn, not a model of human dyspepsia or of Helicobacter pylori ulceration. The doses used are frequently far above human-equivalent intakes: in the 2025 rat study cited below, for example, Codonopsis ethanol extracts were given once daily at 3, 9 and 18 g/kg for 7 days before the ethanol injury. And a striking proportion of tested plant extracts show some protection in these models — they are sensitive but not very specific. The fair reading is that Codonopsis behaves like a mucosally protective, antioxidant-rich plant extract in animals, which is consistent with its traditional use and is not evidence that it heals ulcers in people. Codonopsis is not a treatment for peptic ulcer disease, which has proven therapies.
Gut Barrier and Inflammation Models
A smaller body of work looks at the intestine rather than the stomach, typically using chemically induced colitis in mice (dextran sulfate sodium (DSS) or trinitrobenzene sulfonic acid (TNBS) models) or intestinal barrier disruption models. Reported outcomes include reduced colitis severity scores, better preservation of tight-junction proteins such as occludin and zonula occludens-1 (ZO-1), and lower inflammatory signalling in gut tissue.
This is mechanistically coherent — more butyrate and better colonocyte fuel should support barrier integrity — but the same warnings apply with more force. Dextran sulfate sodium colitis is a chemical injury model that resembles ulcerative colitis only loosely, and results in it have a poor record of predicting human inflammatory bowel disease (IBD) therapy. Nothing here supports using Codonopsis for Crohn's disease or ulcerative colitis. In active inflammatory bowel disease, two facts stand out: the root's fructans are fermentable fibre (a FODMAP) that can bring on gas, distension, cramping and urgency, and there are no human data on Codonopsis in active inflammatory bowel disease.
The Honest Caveat: Small Intestinal Bacterial Overgrowth, Irritable Bowel Syndrome, and FODMAPs
This is the part most herbal write-ups omit, and for a substantial minority of readers it is the only part that matters.
Fructans are one of the most reliable symptom triggers in irritable bowel syndrome. In the low-FODMAP diet framework, fructan is the "O" in FODMAP — the oligosaccharide category — and it is the fraction responsible for wheat, onion, and garlic causing trouble in irritable bowel syndrome. Feeding a fructan-rich root to someone with fructan-sensitive irritable bowel syndrome is likely to produce exactly what you would expect: gas, distension, cramping, and either urgency or constipation depending on which pattern they have.
In small intestinal bacterial overgrowth the problem is worse and the logic is sharper. In small intestinal bacterial overgrowth (SIBO), bacteria that belong in the colon are populating the small intestine, where they meet food before it is absorbed. Fermentable substrate arriving in that environment is fermented immediately, high in the gut, producing bloating within an hour of eating rather than the delayed colonic pattern. A prebiotic is, functionally, feeding the overgrowth. This is why prebiotic supplements are often withheld during small intestinal bacterial overgrowth treatment and reintroduced only afterwards.
So, plainly:
- In diagnosed small intestinal bacterial overgrowth, or fructan-sensitive irritable bowel syndrome, Codonopsis may well make symptoms worse, not better. The traditional indication ("bloating and loose stools") and the chemistry point in opposite directions for these people.
- The symptom overlap is genuinely confusing. Spleen-qi deficiency and small intestinal bacterial overgrowth share bloating, postprandial fatigue, and irregular stools — so the person a traditional practitioner would most confidently give Codonopsis to may be the person a gastroenterologist would most confidently keep it away from. Neither framework is stupid; they are describing different underlying models of the same complaint.
- Dose scales the risk. A few grams of sliced root simmered into a family-sized pot of soup delivers far less fructan per serving than 30 g of concentrated extract powder. Small culinary amounts deliver the least fructan; large doses deliver the most.
Appetite, Postprandial Fatigue, and Loose Stools
What can be said for the other group — people whose digestion is simply weak, without a fermentation problem? Traditional use is consistent and long-running: Codonopsis is given for poor appetite, chronic loose stools, and after-meal exhaustion, usually within a formula, usually daily for weeks, usually alongside advice to eat cooked, warm, simple food in regular amounts.
There is no controlled human trial isolating Codonopsis for any of these endpoints. What there is: centuries of documented practice; formula-level clinical reports from Chinese-language journals of variable quality; the plausible prebiotic and mucosal mechanisms above; and the practical observation that a starchy, mildly sweet, easily digestible root simmered into soup with protein is genuinely nourishing food for someone who is not eating well. That last point is not a joke. For an undernourished person with poor appetite, a palatable warm soup they will actually finish may be doing more good than any of the pharmacology.
How It Is Traditionally Taken, and How People Track Its Effect
- Form: dried sliced root, decocted. 9–30 g per day is the classical range; practitioners describe starting lower, around 6–9 g, for a first trial. The traditional decoction simmers 30–45 minutes. Hot-water extract powders carry the same water-soluble fraction; high-proof tinctures do not deliver the relevant fraction.
- Traditional pairing: if the goal is digestion specifically, Codonopsis is normally combined — the Si Jun Zi Tang quartet with Atractylodes, Poria, and Licorice is the classical starting point. A qualified practitioner adjusts from there.
- Trial period: practitioners describe two to four weeks as long enough to judge an effect. This is not an acute remedy; in traditional use it is taken daily rather than "as needed."
- A simple record: people tracking an effect note appetite, stool form (the Bristol stool scale), bloating on a 0–10 scale, and energy one hour after lunch. Four numbers a day. Without a record, an effect cannot be told apart from a good week.
- Increasing bloating is the warning sign. Worsening distension in the first week is the classic fructan response. That is useful information — it points to a fermentation problem rather than a tonic that needs more time.
- Red-flag signs: weight loss, blood in stool, anaemia, symptoms waking you at night, fever, family history of bowel cancer or inflammatory bowel disease, or onset after age 50. In medical practice these signs lead to tests for bowel cancer, inflammatory bowel disease and other diseases with specific treatments; no herb is a tested treatment for any of them.
Key Research Papers
This site does not print PubMed ID numbers it cannot confirm. Where a record has been checked against PubMed and its title, first author, journal and year all match, the year and page numbers link straight to that record. Where no single paper could be confirmed, the link opens a PubMed topic query instead, so every claim can still be verified directly.
- Gao SM, Liu JS, Wang M, et al. Traditional uses, phytochemistry, pharmacology and toxicology of Codonopsis: a review. Journal of Ethnopharmacology. 2018;219:50–70. — PubMed PMID: 29501674
- He JY, Ma N, Zhu S, Komatsu K, Li ZY, Fu WM. The genus Codonopsis (Campanulaceae): a review of phytochemistry, bioactivity and quality control. Journal of Natural Medicines. 2015;69(1):1–21. — PubMed PMID: 25099952
- Chen Q, Sun Y, Hu X, Xie Q, Liu W, Lei J, Cheng X, Li W, Wang C. The effect and mechanism of Codonopsis Radix and its active components tangshenoside I and lobetyolin on preventing gastric ulcer based on spectrum-effect relationship. Journal of Ethnopharmacology. 2025;353(Pt A):120281 — PubMed PMID: 40653041 — Ethanol-induced rat model; antioxidant (SOD, GSH-Px, MDA) and anti-inflammatory (IL-6, IL-1β) endpoints.
- Zhou J, Yang Q, Wei W, Huo J, Wang W. Codonopsis pilosula polysaccharide alleviates ulcerative colitis by modulating gut microbiota and SCFA/GPR/NLRP3 pathway. Journal of Ethnopharmacology. 2025;337(Pt 2):118928 — PubMed PMID: 39393557 — Covers both the microbiota-composition and the colitis endpoints.
- Xie X, Gu Y, Liu Y, Shen M, Ji J, Gao J, Li J. An inulin-type fructan from Codonopsis pilosula ameliorates cyclophosphamide-induced immunosuppression and intestinal barrier injury in mice. International Journal of Biological Macromolecules. 2025;310(Pt 1):143312 — PubMed PMID: 40250123 — Intestinal-barrier outcomes for the fructan fraction.
- Inulin-type fructans as prebiotics: human trials of bifidogenic effect and tolerance. Current record set. A large and heterogeneous trial literature with no single standard reference, so this stays a topic search.
- Gibson PR, Halmos EP, Muir JG. Review article: FODMAPs, prebiotics and gut health — the FODMAP hypothesis revisited. Alimentary Pharmacology & Therapeutics. 2020;52(2):233–246 — PubMed PMID: 32562590 — Directly addresses the tension between a fructan being a prebiotic and a fructan being a FODMAP trigger.
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG clinical guideline: small intestinal bacterial overgrowth. The American Journal of Gastroenterology. 2020;115(2):165–178 — PubMed PMID: 32023228 — Diagnosis, fermentable substrate, and dietary management.
- Butyrate, colonocyte metabolism, and intestinal barrier function. Current record set.
- Wang Y, Liu B, Fu X, Tong T, Yu Z. Efficacy and safety of Si-Jun-Zi-Tang-based therapies for functional (non-ulcer) dyspepsia: a meta-analysis of randomized controlled trials. BMC Complementary Medicine and Therapies. 2021;21(1):11 — PubMed PMID: 33407405 — 12 randomized trials; all judged at high risk of bias.
- Wang H, Hou YN, Yang M, Feng Y, Zhang YL, Smith CM, Hou W, Mao JJ, Deng G. Herbal formula Shenling Baizhu San for chronic diarrhea in adults: a systematic review and meta-analysis. Integrative Cancer Therapies. 2022;21:15347354221081214 — PubMed PMID: 35635135 — 14 randomized trials, 1,158 participants.
- Shen Ling Bai Zhu San and Si Jun Zi Tang in gastrointestinal disorders: the formula-level clinical literature. Current record set.
PubMed Topic Searches
- PubMed: Codonopsis gastroprotective
- PubMed: Codonopsis pilosula intestinal
- PubMed: Codonopsis inulin fructan
- PubMed: Spleen qi deficiency functional dyspepsia
- PubMed: Si jun zi tang
- PubMed: Low FODMAP diet randomized trial
- PubMed: Prebiotic bloating tolerance dose
- PubMed: Short chain fatty acid production colon fermentation
Connections
- All Herbs
- Codonopsis (Dang Shen) — the main research article.
- Codonopsis: History and Traditional Use — the materia medica record behind the Spleen-qi indication.
- Codonopsis Benefits — hub for all four deep dives.
- Atractylodes — the "dries dampness" herb of Si Jun Zi Tang.
- Poria Mushroom — the "drains dampness" herb of the same formula.
- Licorice — the harmonising fourth herb.
- Astragalus — partner herb in Bu Zhong Yi Qi Tang.
- Ginseng — the original first herb of Si Jun Zi Tang, for which Codonopsis substitutes.