Beef for CLA and Omega-3 Ratio
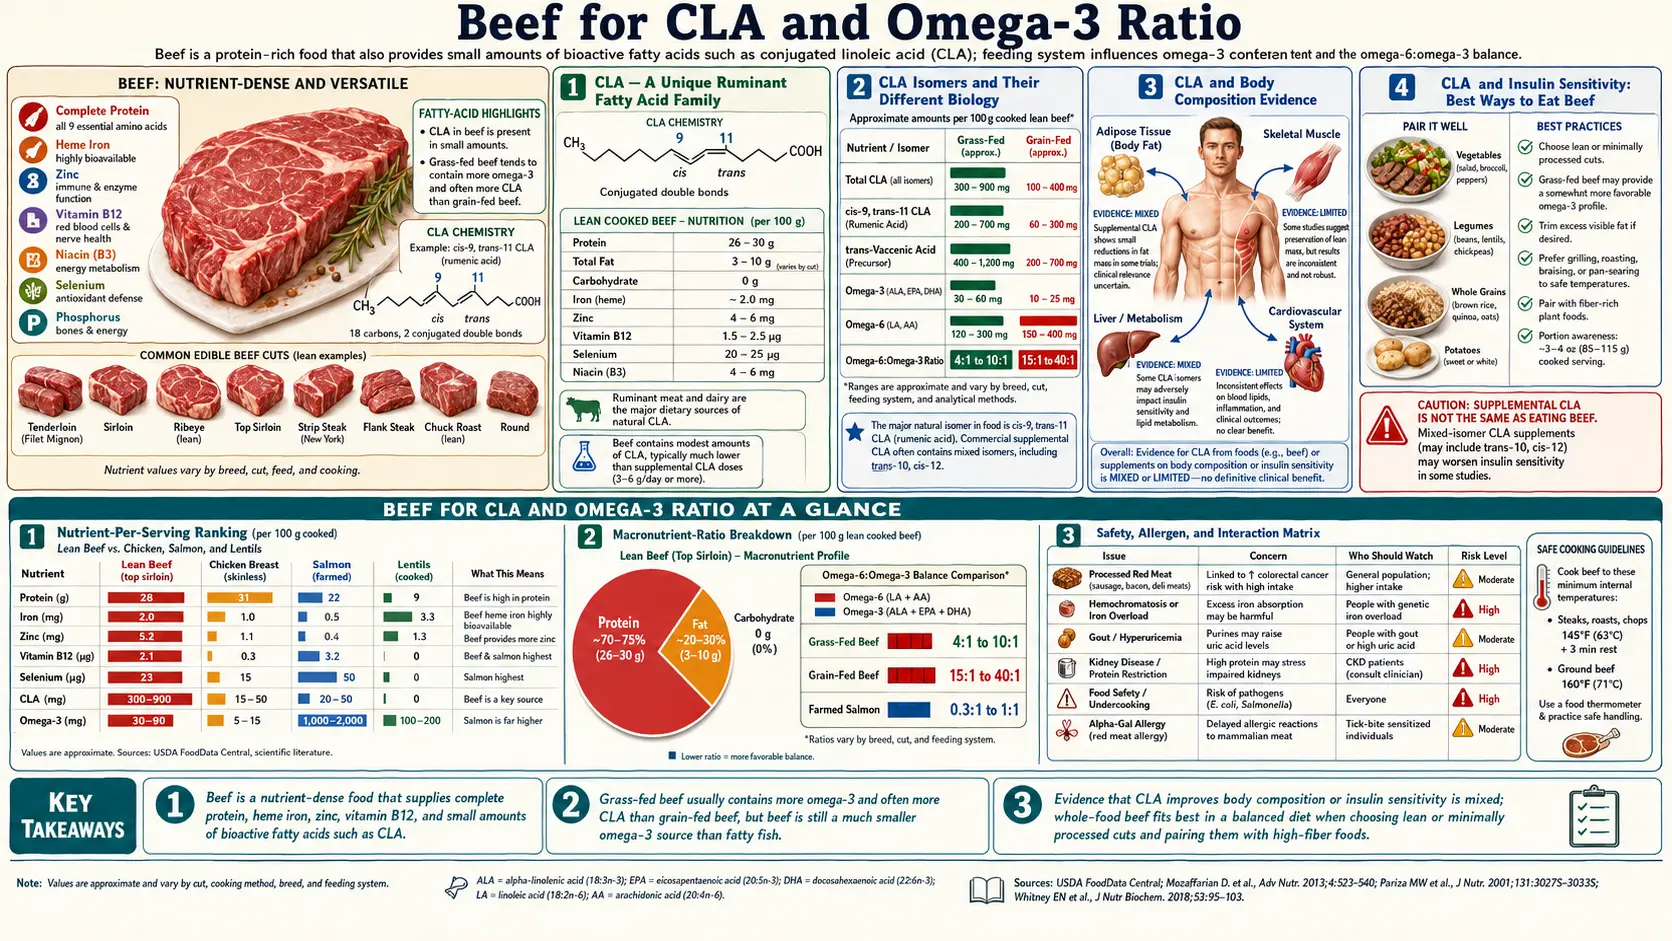
Conjugated linoleic acid (CLA) and the omega-6 to omega-3 fatty acid ratio are the two most-discussed and most-marketed nutritional features of the beef fat fraction. Both deserve a careful look that separates the strong biochemistry from the much weaker clinical evidence. CLA is a family of naturally occurring positional and geometric isomers of linoleic acid, produced exclusively by ruminant bacteria from feed linoleic acid. The dominant naturally occurring isomer (cis-9, trans-11 CLA, called rumenic acid) is structurally and biologically different from the trans fatty acids of partially hydrogenated industrial fats and is a different substance from them. The omega-6 to omega-3 ratio of beef ranges from approximately 2:1 in grass-finished beef to 8:1 in grain-finished beef — both substantially better than the 15:1 ratio of the typical industrial Western diet, and within or close to the 1:1 to 4:1 range associated with lower inflammation in cross-cultural epidemiology. This page works through the biochemistry of both, the clinical trial evidence on body composition, insulin sensitivity, and cardiovascular markers, and the practical question of how much these fatty acid features matter for beef choice and overall diet design.
Table of Contents
- CLA — A Unique Ruminant Fatty Acid Family
- CLA Isomers and Their Different Biology
- CLA and Body Composition Evidence
- CLA and Insulin Sensitivity
- CLA and Cancer Research
- The Omega-6 to Omega-3 Ratio Hypothesis
- Beef and the Dietary Ratio in Context
- What Actually Improves the Ratio
- Saturated Fat in Beef: Modern Cardiology Context
- Practical Implications
- Key Research Papers
- Connections
- Featured Videos
CLA — A Unique Ruminant Fatty Acid Family
Conjugated linoleic acid was discovered as a meat-derived anticancer factor in the 1980s by Michael Pariza at the University of Wisconsin, who was investigating mutagenic compounds in fried beef and unexpectedly identified a protective rather than harmful factor. Subsequent work characterized CLA as a family of positional and geometric isomers of the 18-carbon polyunsaturated fatty acid linoleic acid, where the two double bonds are in a conjugated (1,3-diene) configuration rather than the standard methylene-interrupted (1,4-diene) configuration of linoleic acid itself.
CLA is produced naturally in the rumen of cattle, sheep, goats, and other ruminants by the bacterium Butyrivibrio fibrisolvens, which partially hydrogenates dietary linoleic acid through the conjugated intermediate. The CLA thus produced is absorbed by the ruminant and stored in tissues and milk fat. There is no significant non-ruminant source of CLA in the food supply — ruminant meat and dairy are essentially the only meaningful dietary sources.
The naturally occurring CLA in ruminant fat is dominated by cis-9, trans-11 CLA (rumenic acid), which makes up 80-90% of total CLA in beef and dairy fat. A smaller fraction (5-15%) is trans-10, cis-12 CLA, which has different biological effects. This isomer distinction matters because most of the early supplement studies used a 50:50 mixture of the two isomers (called "mixed CLA"), and many of the metabolic effects attributed to "CLA" actually trace to the trans-10, cis-12 isomer that is a minor fraction of natural ruminant CLA.
The most important conceptual point: rumenic acid (cis-9, trans-11 CLA) is a trans fatty acid by chemical definition (one of its double bonds is in the trans configuration), but it is not associated with the cardiovascular harm of the artificial trans fats produced by industrial partial hydrogenation of vegetable oils. The two come from different sources, have different metabolic fates, and have different epidemiologic associations. The U.S. Food and Drug Administration's food-label definition of trans fat (21 CFR 101.9) counts only unsaturated fatty acids with one or more isolated (nonconjugated) trans double bonds, so conjugated fatty acids such as rumenic acid (CLA) are left out of the label's trans fat figure. Ruminant trans fats are not excluded as a group: vaccenic acid, the main ruminant trans fat, has an isolated trans bond and is counted.
CLA Isomers and Their Different Biology
The two principal CLA isomers have distinct and sometimes opposite metabolic effects:
- cis-9, trans-11 CLA (rumenic acid) — dominant in ruminant fat. Associated in animal studies with anti-inflammatory effects (modest reduction in pro-inflammatory cytokines), modest improvement in insulin sensitivity, and possible cardioprotective effects. Generally considered the "good CLA."
- trans-10, cis-12 CLA — minor fraction in natural beef but the more biologically active isomer in body-composition research. Reduces adipocyte triglyceride storage and increases lipolysis in animal and in-vitro studies. However, in human trials it has also been associated with adverse effects on insulin sensitivity, increased inflammation, and fatty liver in some studies.
Most clinical CLA supplements sold in the US are mixed isomers in roughly 50:50 ratio, derived from industrial isomerization of safflower or sunflower oil linoleic acid. These supplements do not replicate the natural isomer balance of ruminant CLA, and most of the published clinical CLA research has used these mixed-isomer products at doses (typically 3-4 g/day) far higher than achievable through diet.
The implication is that the clinical effects of CLA supplements cannot be assumed to apply to dietary CLA from beef, both because of the different isomer ratio and because of the different total dose. Dietary CLA from beef is predominantly rumenic acid, in cumulative milligram quantities per serving. Supplemental CLA is predominantly the trans-10, cis-12 isomer (or 50:50), in gram quantities per day.
CLA and Body Composition Evidence
The most popular consumer-facing CLA claim is body fat reduction. The Whigham et al. 2007 meta-analysis in the American Journal of Clinical Nutrition pooled 18 randomized, double-blind, placebo-controlled trials of CLA supplementation in which body composition was measured with a validated method. Key findings:
- Results were adjusted to the trials' median dose of 3.2 g/day
- The effect grew in a straight line for up to 6 months, then slowly levelled off, approaching a plateau at about 2 years
- Across doses, fat loss compared with placebo was about 0.024 kg per gram of CLA per week
- At 3.2 g/day, fat mass fell by approximately 0.09 kg per week compared with placebo
- Effect sizes were small and clinically modest; the authors describe "a modest loss in body fat"
- Effect was greatest in overweight and obese subjects
- Lean body mass was preserved or slightly increased
The Dilzer and Park 2012 review in Critical Reviews in Food Science and Nutrition and the 2019 den Hartigh review in Nutrients largely confirmed the pattern: modest fat mass reduction from CLA supplementation, small effect sizes, more pronounced in animal models than in humans. The effect is real but not dramatic.
The dose required for these effects (3-6 g/day) is approximately 100-300 times higher than the CLA intake from typical dietary consumption of ruminant fat. There is no plausible scenario in which dietary CLA from beef contributes meaningfully to body composition through this acute mechanism. Whatever chronic cumulative effects of dietary CLA exist would be much smaller than supplement-driven effects.
CLA and Insulin Sensitivity
The metabolic effects of CLA on insulin sensitivity have been a research priority because of the strong animal-model signal showing improvement. Human trials have been more mixed:
- Mixed-isomer CLA supplements (the typical commercial product) have shown worsening of insulin sensitivity in some human trials, attributed to the trans-10, cis-12 isomer's pro-inflammatory effect on liver and adipose tissue
- Pure cis-9, trans-11 CLA (rumenic acid) has shown neutral or modestly favorable insulin sensitivity effects, though large trials are scarce
- Population observational studies of dietary CLA intake (rather than supplemental CLA) tend to show favorable associations with insulin sensitivity, possibly reflecting the favorable isomer ratio of dietary CLA
Because of the mixed evidence, the research does not support CLA supplements for diabetes management or insulin sensitivity improvement, despite the body composition signal. Dietary CLA from beef appears to be either neutral or modestly favorable for insulin sensitivity, but the effect is small, and the research does not show beef working as an insulin-sensitivity intervention.
CLA and Cancer Research
The original Pariza discovery of CLA was as an anti-mutagenic factor in fried beef. Subsequent animal-model research has consistently shown anti-tumor effects of CLA, particularly for breast cancer, colon cancer, and skin cancer, at supplemental doses. The mechanisms include:
- Inhibition of cell proliferation through PPAR-gamma activation
- Induction of apoptosis in transformed cells
- Reduction of angiogenesis
- Modulation of inflammatory cytokines
- Effects on cellular fatty acid composition that may reduce membrane susceptibility to peroxidation-driven damage
Human cancer outcome data are much less robust. A few observational studies have suggested favorable associations between dietary CLA intake (estimated from dairy fat consumption) and breast cancer risk in postmenopausal women, but the signal is inconsistent and confounded by other features of dairy and meat consumption.
The Belury 2002 Annual Review of Nutrition and Bhattacharya 2006 Journal of Nutritional Biochemistry reviews remain authoritative summaries of the CLA biological effects. The clinical translation has been less successful than the animal-model literature suggested, which is a recurring pattern in cancer chemoprevention research.
The Omega-6 to Omega-3 Ratio Hypothesis
The omega-6 to omega-3 fatty acid ratio hypothesis was articulated most influentially by Artemis Simopoulos in a series of papers from the late 1990s through the 2000s, including the 2002 Biomedicine & Pharmacotherapy paper that is one of the most-cited papers in nutrition science. The hypothesis is that:
- Human beings evolved on a diet with an omega-6 to omega-3 ratio of approximately 1:1 (Simopoulos 2002), with omega-3 from wild fish and game and omega-6 from wild plant foods
- The modern industrial Western diet has a ratio of approximately 15:1 to 16.7:1 (Simopoulos 2002), driven by the explosive growth of soybean, corn, and other seed oil consumption from the 1960s onward, and by the omega-6-heavy grain feeding of livestock
- Omega-6 fatty acids are metabolized via cyclooxygenase and lipoxygenase pathways to pro-inflammatory eicosanoids; omega-3 fatty acids compete for the same enzymes and produce less inflammatory or actively anti-inflammatory eicosanoids
- The shift in the dietary ratio has shifted the eicosanoid balance toward inflammation, contributing to the modern epidemic of inflammatory and metabolic diseases
The hypothesis has been influential but also contested. The proponents' argument is supported by cross-cultural epidemiology (low-ratio populations like traditional Japanese, Mediterranean, and Inuit had lower cardiovascular disease rates) and by mechanistic biochemistry (the eicosanoid pathway is real and well-characterized). The critics argue that the eicosanoid pathway effects are partial, that linoleic acid (the dominant omega-6) has its own beneficial effects on cholesterol and cardiovascular health, and that absolute omega-3 intake is more important than the ratio.
The 2011 Mozaffarian and Wu review in JACC and the Calder 2017 Biochemical Society Transactions paper give contemporary perspectives. The current consensus is that increasing omega-3 intake (particularly eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) from fatty fish) is well-supported, while aggressive omega-6 reduction is more controversial. The ratio matters somewhat, but absolute omega-3 sufficiency probably matters more.
Beef and the Dietary Ratio in Context
The omega-6 to omega-3 ratio of beef varies substantially by production system:
- Grass-finished beef — ratio approximately 1.5:1 to 2:1 (favorable)
- Grain-finished beef — ratio approximately 7:1 to 10:1 (less favorable but still better than the diet average)
- Modern industrial Western diet average — 15:1 to 16.7:1 (Simopoulos 2002)
- Mediterranean diet (well-followed) — approximately 4:1 to 6:1
- Diet on which humans evolved (reconstruction) — approximately 1:1 (Simopoulos 2002)
The point is that beef of either production type has a more favorable omega-6 to omega-3 ratio than the dietary average. Substituting beef for industrial seed oil-heavy foods (most processed foods, fast food, baked goods, fried foods) improves the ratio, regardless of grass-finished vs grain-finished. Choosing grass-finished further improves it.
The total absolute omega-3 contribution from beef is modest in either case — a 3-oz serving of grass-finished beef provides perhaps 80 mg of long-chain omega-3, vs 1,500-2,000 mg in a 3-oz serving of fatty fish. Beef is not an omega-3 source in the way that fish is. Nor is beef a meaningful contributor to omega-6 excess in the way that industrial seed oils are. See our Omega-3 page for the full story.
What Actually Improves the Ratio
For an adult aiming to shift the dietary omega-6 to omega-3 ratio toward the lower end of the spectrum, the changes that move it most, in approximate order of impact, are:
- Less industrial seed oil — soybean, corn, sunflower, safflower, cottonseed, grapeseed oils are the dominant source of omega-6 excess in the modern diet. These oils are used heavily in processed foods, restaurant cooking, salad dressings, mayonnaise, and many baked goods. Home cooking with olive oil, butter, ghee, or animal fats in their place is likely the largest single change.
- Fatty fish 2-3 times per week — salmon, sardines, mackerel, anchovies, herring are the most reliable sources of long-chain omega-3 (eicosapentaenoic acid and docosahexaenoic acid). A 3-4 oz serving provides ~1,500-2,500 mg of long-chain omega-3. See our Salmon page and our Sardines page.
- Fish oil or algae oil supplements — used by people who cannot or do not eat fatty fish regularly. 1-2 g/day combined eicosapentaenoic acid + docosahexaenoic acid is the typical cardiovascular dose.
- Grass-finished beef — better ratio than grain-finished; its contribution to overall diet is meaningful, particularly if fish intake is low. See our Grass-Fed vs Grain-Fed deep dive.
- Alpha-linolenic acid-rich plant sources — flax, chia, walnuts contain alpha-linolenic acid, the parent omega-3. Conversion to eicosapentaenoic acid and docosahexaenoic acid in humans is inefficient (~5% for eicosapentaenoic acid, <1% for docosahexaenoic acid) so these are partial replacements for fish but contribute to baseline.
- Pasture-raised eggs and dairy — same logic as grass-finished beef applied to other animal products. Pasture-raised eggs have measurably more omega-3 than conventional eggs.
The relative impact of each: substituting butter and olive oil for industrial seed oils probably shifts the dietary ratio more than any other single change. Adding fatty fish twice a week probably shifts it more than switching from grain-finished to grass-finished beef. The grass-finished beef switch is incremental but meaningful for those who consume beef regularly.
Saturated Fat in Beef: Modern Cardiology Context
The historical concern about beef and cardiovascular disease focused on saturated fat content. The diet-heart hypothesis as advanced by Ancel Keys in the 1950s-1970s held that dietary saturated fat raises low-density lipoprotein (LDL) cholesterol which raises cardiovascular disease risk. This was the basis for decades of dietary guidance to limit red meat consumption.
The modern cardiology context is more nuanced:
- The relationship between dietary saturated fat and serum low-density lipoprotein cholesterol is real but variable between individuals (some respond strongly, some not at all)
- The relationship between serum low-density lipoprotein cholesterol and cardiovascular disease risk is well-established in apoB-particle terms, though saturated fat's effect on apoB and small-dense low-density lipoprotein is more nuanced than just total low-density lipoprotein cholesterol (LDL-C)
- The relationship between dietary saturated fat intake and cardiovascular outcomes in observational and randomized trial data is weaker than the linear model predicts (the Siri-Tarino 2010 meta-analysis in the American Journal of Clinical Nutrition pooled 21 cohort studies that followed 347,747 people for 5-23 years, of whom 11,006 developed coronary heart disease or stroke, and found no significant association: the pooled relative risks for the highest versus lowest saturated-fat intake were 1.07 (95% confidence interval 0.96-1.19) for coronary heart disease, 0.81 (0.62-1.05) for stroke and 1.00 (0.89-1.11) for cardiovascular disease as a whole; the authors noted that more data are needed on whether the nutrients used to replace saturated fat change the risk)
- Different saturated fats have different metabolic effects (stearic acid, dominant in beef, has near-neutral effect on low-density lipoprotein; palmitic acid raises it more)
- The food matrix matters — the same amount of saturated fat in cheese or yogurt has different cardiovascular effects than in processed meat
The Johnston et al. 2019 Nutritional Recommendations (NutriRECS) Consortium guideline, published in Annals of Internal Medicine and built on five systematic reviews, made a weak recommendation based on low-certainty evidence: its panel suggests that adults continue their current unprocessed red meat consumption, and it made the same weak, low-certainty suggestion for processed meat. The companion Zeraatkar et al. 2019 meta-analysis of cohort studies (55 cohorts, more than 4 million participants) found low-certainty evidence that eating 3 fewer servings a week of unprocessed red meat was associated with a very small reduction in risk of cardiovascular death, stroke, heart attack (myocardial infarction) and type 2 diabetes; 3 fewer servings a week of processed meat showed a very small reduction in the same outcomes and in death from all causes.
Processed meat (bacon, deli meats, hot dogs, sausages preserved with nitrates) is usually treated as a separate category from unprocessed beef. In the Zeraatkar review, the associations for processed meat were also very small and of low certainty, and processed meat was the only one of the two linked to all-cause mortality.
These findings do not show that unlimited beef is harmless. Dietary guidelines generally recommend limiting red and processed meat; the NutriRECS panel departed from that guidance on the grounds that the evidence behind it is of low certainty and the associations are very small. For individual cardiovascular risk management, see our Cardiology section.
Practical Implications
- For omega-3 sufficiency, fatty fish is the high-leverage intervention — 2-3 servings per week of salmon, sardines, mackerel, or anchovies will accomplish far more than any beef-related change.
- For omega-6 reduction, cutting industrial seed oil is the high-leverage change — cooking at home with butter, olive oil, ghee, or animal fats and eating fewer processed foods with high seed oil content matters more than the beef finishing system.
- Grass-finished beef provides incremental benefit for the fatty acid profile — meaningful if beef is consumed regularly, particularly for individuals who do not eat much fish.
- Current evidence does not support CLA supplementation — the body composition effect is small, the mixed-isomer formulations may worsen insulin sensitivity, and the dose-effect relationship at dietary intake levels is unclear.
- Beef of either production type is not a meaningful driver of omega-6 excess — the ratio in beef is more favorable than the average diet, so substituting beef for industrial-food alternatives improves the ratio.
- Total fat intake from beef is variable by cut — a 6-oz top sirloin has approximately 12 g of total fat; a 6-oz ribeye has approximately 30 g.
- Processed meat (bacon, deli meat, hot dogs) is treated as a different category from unprocessed beef: most dietary guidelines recommend limiting it, while the 2019 NutriRECS panel made a weak, low-certainty suggestion that adults continue current consumption.
- Cardiovascular risk is multifactorial — smoking, physical inactivity, untreated hypertension, obesity, untreated diabetes, untreated hyperlipidemia are larger leverage points than the type of beef consumed.
Key Research Papers
- Whigham LD, Watras AC, Schoeller DA (2007). Efficacy of conjugated linoleic acid for reducing fat mass: a meta-analysis in humans. American Journal of Clinical Nutrition — PubMed PMID: 17490954
- Simopoulos AP (2002). The importance of the ratio of omega-6/omega-3 essential fatty acids. Biomedicine & Pharmacotherapy — PubMed PMID: 12442909
- Belury MA (2002). Dietary conjugated linoleic acid in health: physiological effects and mechanisms of action. Annual Review of Nutrition — PubMed PMID: 12055356
- Dilzer A, Park Y (2012). Implication of conjugated linoleic acid (CLA) in human health. Critical Reviews in Food Science and Nutrition — PubMed PMID: 22452730
- Bhattacharya A, Banu J, Rahman M, et al. (2006). Biological effects of conjugated linoleic acids in health and disease. Journal of Nutritional Biochemistry — PubMed PMID: 16650752
- den Hartigh LJ (2019). Conjugated linoleic acid effects on cancer, obesity, and atherosclerosis: a review of pre-clinical and human trials with current perspectives. Nutrients — PubMed PMID: 30754681
- Field CJ, Blewett HH, Proctor S, Vine D (2009). Human health benefits of vaccenic acid. Applied Physiology, Nutrition, and Metabolism — PubMed PMID: 19935865
- Mozaffarian D, Wu JH (2011). Omega-3 fatty acids and cardiovascular disease: effects on risk factors, molecular pathways, and clinical events. Journal of the American College of Cardiology — PubMed PMID: 22051327
- Calder PC (2017). Omega-3 fatty acids and inflammatory processes: from molecules to man. Biochemical Society Transactions — PubMed PMID: 28900017
- Siri-Tarino PW, Sun Q, Hu FB, Krauss RM (2010). Meta-analysis of prospective cohort studies evaluating the association of saturated fat with cardiovascular disease. American Journal of Clinical Nutrition — PubMed PMID: 20071648
- Johnston BC, Zeraatkar D, Han MA, et al. (2019). Unprocessed red meat and processed meat consumption: dietary guideline recommendations from the NutriRECS Consortium. Annals of Internal Medicine — PubMed PMID: 31569235
- Zeraatkar D, Han MA, Guyatt GH, et al. (2019). Red and processed meat consumption and risk for all-cause mortality and cardiometabolic outcomes: a systematic review and meta-analysis. Annals of Internal Medicine — PubMed PMID: 31569213
- Bhupathiraju SN, Tucker KL (2011). Coronary heart disease prevention: nutrients, foods, and dietary patterns. Clinica Chimica Acta — Search PubMed
- Ridker PM, Everett BM, Thuren T, et al. (2017). Antiinflammatory therapy with canakinumab for atherosclerotic disease (CANTOS). NEJM — PubMed PMID: 28845751