⚠ Evidence warning: Clinical trials or other evidence do not support the claims that H. pylori treatment improves hyperemesis symptoms and that anti-GDF15 therapies are in clinical development with promising results. This page keeps it as a report of what people, websites or other media say.
Hyperemesis Gravidarum
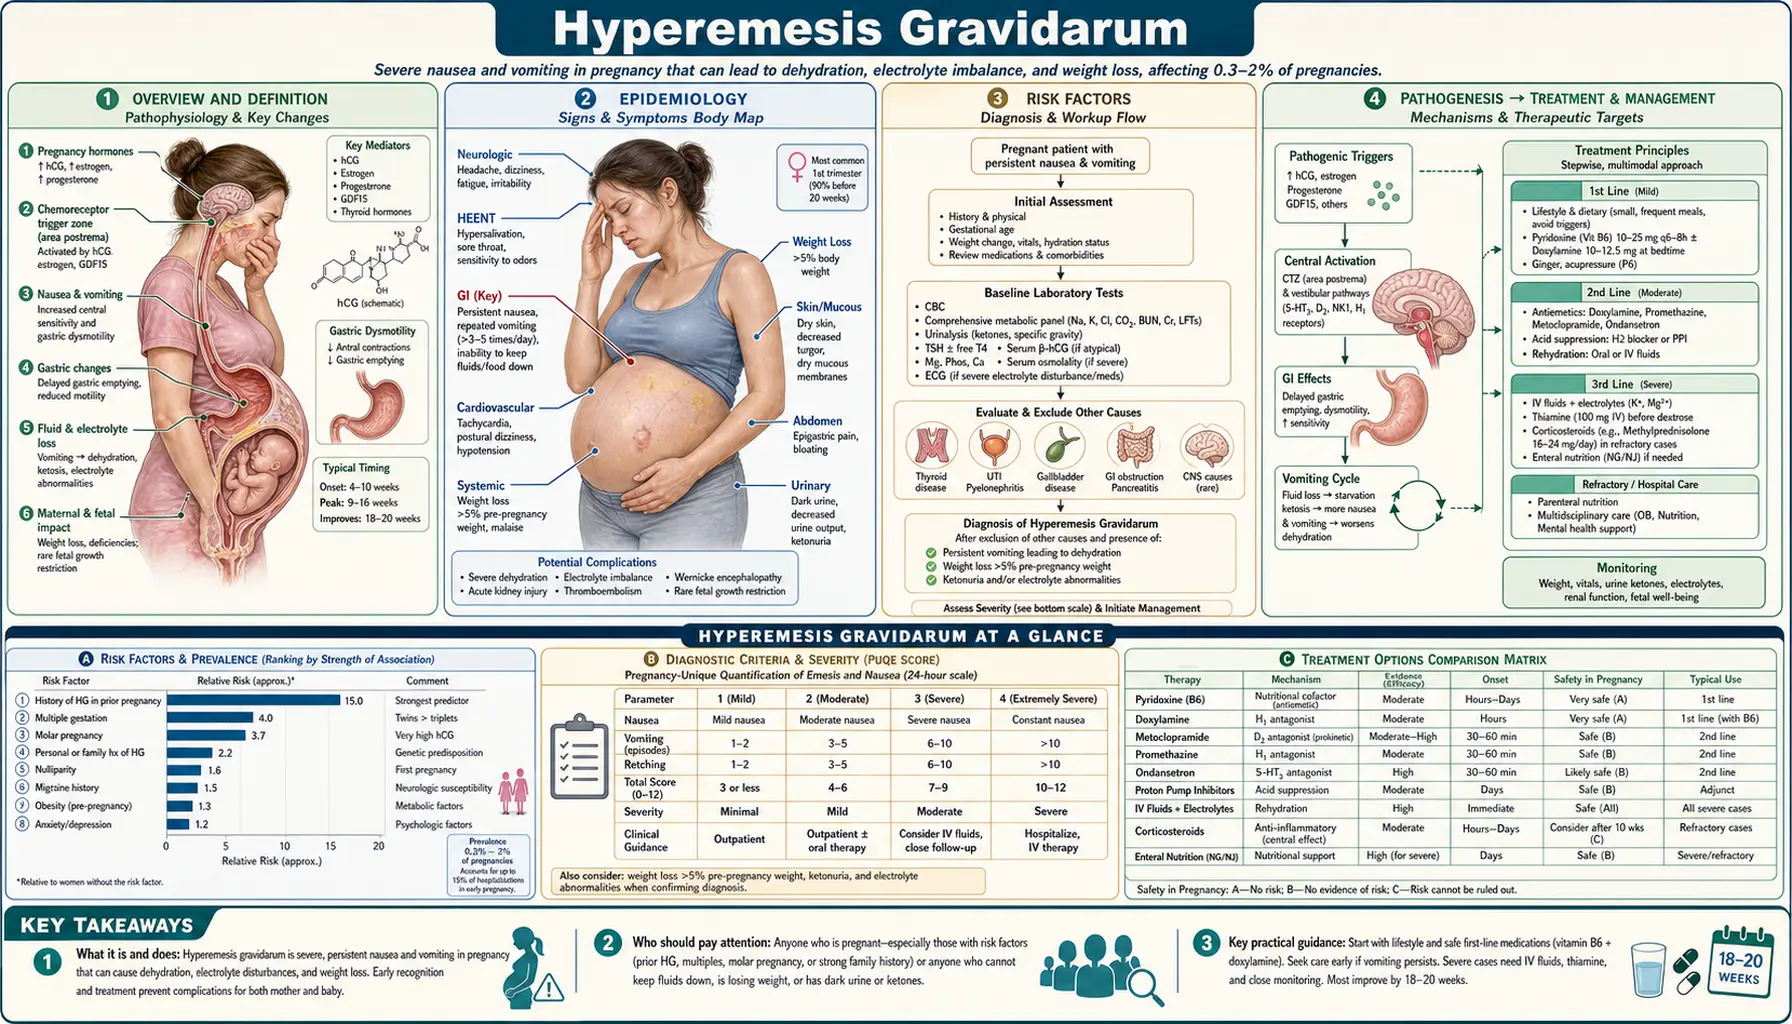
Table of Contents
Overview and Definition
Hyperemesis Gravidarum (HG) is the severe end of the spectrum of pregnancy-related nausea and vomiting. It represents a pathological condition far beyond the common morning sickness experienced by most pregnant women, and can result in serious maternal and fetal complications when not promptly recognized and treated.
Since 2021, an international group of researchers, women who have lived through hyperemesis gravidarum, and doctors and midwives has used one shared definition, called the Windsor definition (Jansen et al., 2021). Hyperemesis gravidarum is defined as:
- Symptoms that start early in pregnancy, before 16 weeks
- Nausea and vomiting, at least one of them severe
- Being unable to eat and/or drink normally
- Strong limits on everyday activities
Signs of dehydration support the diagnosis. Older definitions used in many earlier studies also required weight loss of 5% or more of pre-pregnancy body weight and ketones in the urine (ketonuria, a sign the body is burning fat for fuel); the Windsor definition does not require them.
HG must be distinguished from common nausea and vomiting of pregnancy (NVP), which affects approximately 70–80% of all pregnancies. NVP typically resolves by 14 weeks of gestation, rarely causes significant weight loss, and almost never requires hospitalization. In contrast, HG is severe, prolonged, and significantly impairs daily functioning and nutritional status.
The condition sits at the extreme end of a clinical continuum: mild NVP → moderate NVP → hyperemesis gravidarum. This distinction has practical importance because treatment escalates substantially across the spectrum.
Epidemiology
Hyperemesis gravidarum affects approximately 0.5–2% of all pregnancies worldwide, with prevalence estimates varying by diagnostic criteria applied and population studied. Despite its relatively low frequency compared to NVP, HG carries a disproportionate burden of morbidity.
Key epidemiological features:
- Gestational timing: Symptoms typically peak between 6 and 12 weeks of gestation, correlating with peak human chorionic gonadotropin (hCG) levels. Most cases resolve by 20 weeks.
- Persistent cases: Approximately 10–20% of HG cases persist through the third trimester or even until delivery, representing a particularly challenging subset of patients.
- Hospitalization burden: HG is the leading cause of pregnancy-related hospitalization during the first trimester in many countries, accounting for substantial healthcare costs and resource utilization.
- Psychological impact: HG is associated with significant psychological morbidity, including depression, anxiety, and post-traumatic stress disorder (PTSD). A subset of affected women request pregnancy termination as a direct result of severe, uncontrolled symptoms.
- Quality of life: Studies consistently document dramatic impairment in daily activities, ability to work, and interpersonal relationships during active HG episodes.
Risk Factors
Several clinical, biological, and genetic factors have been identified as increasing a woman's risk of developing hyperemesis gravidarum:
- Prior hyperemesis gravidarum: The strongest individual predictor. A 2020 systematic review of five studies (40,350 women with HG) found reported recurrence rates ranging from 15% to 81% in later pregnancies (Dean et al., 2020).
- Multiple gestation: Twin and higher-order pregnancies produce markedly elevated hCG levels, increasing HG risk proportionally.
- Hydatidiform mole: Molar pregnancies are associated with markedly elevated hCG and a very high rate of severe hyperemesis.
- Female fetal sex: Pregnancies carrying female fetuses are associated with higher rates and severity of HG, possibly through differential placental hormone production.
- Helicobacter pylori infection: Seroprevalence of H. pylori is significantly higher in women with HG compared to controls. In a Dutch cohort of 5,549 pregnant women, those who tested positive for H. pylori were more likely to report daily vomiting (adjusted odds ratio 1.44). The authors state that whether H. pylori eradication treatment eases vomiting in pregnancy has yet to be studied (Grooten et al., 2017).
- Hyperthyroid conditions: Pre-existing thyroid disease and gestational transient thyrotoxicosis are associated with increased HG risk.
- Family history: Female relatives (mothers, sisters) with a history of HG confer increased risk, consistent with a heritable component.
- First pregnancy: Primigravidas have modestly higher rates of HG compared to multigravidas (who have had prior HG-free pregnancies).
- Obesity: Paradoxically, obesity appears to confer a lower risk of HG, though the mechanism is incompletely understood.
- GDF15 genetic variants: Emerging evidence implicates variants in the gene encoding growth differentiation factor 15 (GDF15) as a significant genetic risk factor, representing one of the most important recent advances in understanding HG pathogenesis.
- Metformin before pregnancy (lower risk): In a 2025 questionnaire study of 5,414 people, those who took the diabetes drug metformin daily in the month before their first pregnancy had more than 70% lower risk of HG (adjusted relative risk 0.29). Metformin raises GDF15 levels, and the authors propose that this may “desensitize” the body to the hormone before pregnancy. This was a self-reported association, not a trial (Sharma et al., 2025).
Pathogenesis
The pathogenesis of hyperemesis gravidarum is multifactorial. No single mechanism fully explains the condition, and current evidence supports the interplay of hormonal, neurological, gastrointestinal, infectious, and genetic factors.
The hCG Hypothesis
Human chorionic gonadotropin (hCG) is the primary hormonal driver of first-trimester HG. As hCG rises sharply in the first trimester, it stimulates the thyroid gland through cross-reactivity with the thyroid-stimulating hormone (TSH) receptor, producing a relative transient hyperthyroid state. hCG also directly stimulates the area postrema — the brainstem's chemoreceptor trigger zone — which mediates nausea and vomiting.
This hypothesis is supported by the clinical observation that HG symptoms peak at 6–12 weeks of gestation, precisely when hCG levels are highest, and by the significantly higher severity seen in multiple gestations and molar pregnancies where hCG production is markedly amplified.
GDF15 (Growth Differentiation Factor 15)
GDF15 represents one of the most compelling recent advances in understanding hyperemesis gravidarum. This placental hormone is produced in increasing quantities during the first trimester. Large-scale epidemiologic and genetic studies have established a robust link: maternal genetic variants associated with chronically low pre-pregnancy GDF15 exposure produce heightened sensitivity when pregnancy dramatically raises circulating levels.
GDF15 acts through its receptor, GFRAL, which is expressed selectively in the area postrema and nucleus tractus solitarius of the brainstem — the key brain regions governing nausea and vomiting. This receptor-mediated signaling pathway mediates the emetic response. Critically, this mechanism has become a target for novel pharmacotherapy currently under investigation in clinical trials.
A 2024 study in Nature found that the vast majority of the GDF15 in a pregnant woman's blood comes from the baby and placenta, and that women with low GDF15 levels before pregnancy were at higher risk of HG. Women with beta-thalassaemia, a blood condition in which GDF15 levels are high throughout life, reported very little nausea and vomiting in pregnancy. The authors write that these findings suggest “mechanism-based approaches to the treatment and prevention of HG” (Fejzo et al., 2024).
Estrogen Sensitivity
The high estrogen milieu of pregnancy may sensitize central nausea/vomiting centers, contributing to HG susceptibility. The observation that HG is more common with female fetuses (who produce relatively more estrogen) supports this hypothesis.
Gastrointestinal Dysmotility
Pregnancy-associated changes in gastrointestinal function — including slowed gastric emptying, altered gastric motility, and reduced lower esophageal sphincter pressure — may amplify HG severity in susceptible individuals.
Helicobacter pylori
Studies demonstrate significantly higher H. pylori seroprevalence in women with HG versus controls. The mechanism may involve H. pylori-induced changes in gastric motility, mucosal inflammation, and altered hormone metabolism. Importantly, H. pylori eradication has been shown to improve HG symptoms in H. pylori-positive patients, supporting a causal contribution rather than mere association. A large Dutch cohort found H. pylori to be an independent risk factor for vomiting in pregnancy; this is an association, and the authors note that the effect of eradication treatment on symptoms remains to be studied (Grooten et al., 2017).
Clinical Presentation
Hyperemesis gravidarum typically begins before 9–10 weeks of gestation. The inability to tolerate any oral intake — including fluids — is a hallmark feature that distinguishes HG from ordinary NVP.
Core clinical features include:
- Persistent nausea and vomiting: Continuous, not just morning-limited; often triggered by food odors, tastes, or motion
- Weight loss: Common; older definitions used a cutoff of 5% of pre-pregnancy body weight
- Dehydration: Dry mucous membranes, tachycardia, decreased skin turgor, reduced urine output
- Ketonuria: Urine ketones from starvation ketosis as the body metabolizes fat for energy in the absence of dietary carbohydrate
- Electrolyte disturbances: Most commonly hypokalemia; also hyponatremia and hypochloremia
- Ptyalism: Excessive salivation, a distressing symptom some women report as the most disruptive aspect of HG
In severe or prolonged cases, life-threatening complications can develop:
- Wernicke's encephalopathy: From thiamine (vitamin B1) depletion due to prolonged vomiting and inadequate intake — a medical emergency requiring immediate intravenous (IV) thiamine
- Mallory-Weiss tear: Longitudinal mucosal laceration at the gastroesophageal junction from forceful retching, presenting with hematemesis
- Boerhaave's syndrome: Full-thickness esophageal rupture from severe retching — rare but potentially fatal; presents with severe chest and back pain following a vomiting episode
- Fetal growth restriction: In prolonged, severe cases with inadequate maternal nutrition
Diagnosis and Differential
Hyperemesis gravidarum is a clinical diagnosis based on the pattern of symptoms (see the Windsor definition under Overview), after exclusion of other causes. Older criteria also used weight loss ≥5% and ketonuria.
A thorough differential diagnosis is essential, as several serious conditions can mimic or coexist with HG:
- Urinary tract infection: Nausea and vomiting can accompany pyelonephritis; urinalysis and urine culture identify it
- Cholecystitis and cholelithiasis: Biliary disease is more common in pregnancy; right upper quadrant pain and elevated bilirubin distinguish it from HG
- Pancreatitis: Elevated lipase; epigastric pain radiating to the back
- Hepatitis: Markedly elevated transaminases, jaundice; viral serologies
- Neurological causes: Increased intracranial pressure (migraine, pseudotumor cerebri, intracranial mass) can cause vomiting
- Appendicitis: Position of appendix shifts with advancing pregnancy; right-sided pain with fever
- Gastroparesis: May predate pregnancy; delayed gastric emptying study
Key Differential: Gestational Transient Thyrotoxicosis (GTT) vs. True Graves' Disease
GTT occurs when hCG cross-stimulates the thyroid-stimulating hormone receptor, producing suppressed thyroid-stimulating hormone and mildly elevated free T4. This is biochemically indistinguishable from hyperthyroidism but is self-limited and directly driven by hCG. Critical distinguishing features:
- GTT: Suppressed thyroid-stimulating hormone + mildly elevated free T4, negative thyroid autoantibodies (TRAb and TPO-Ab are absent), self-limited (resolves as hCG falls after first trimester), does not require antithyroid drug treatment
- Graves' disease: Positive TRAb; requires active management; antithyroid drugs (propylthiouracil in first trimester, methimazole after) are indicated
This distinction matters enormously: treating GTT with antithyroid drugs would expose the fetus to unnecessary teratogenic risk (particularly agranulocytosis risk and, with methimazole, aplasia cutis) without clinical benefit.
Laboratory Findings
Laboratory evaluation in HG reflects the consequences of prolonged vomiting, dehydration, and starvation. Key findings include:
- Hypokalemia: The most common electrolyte abnormality. Repeated vomiting results in loss of gastric acid containing potassium ions, leading to significant potassium depletion. Severe hypokalemia can cause dangerous cardiac arrhythmias and muscle weakness.
- Hyponatremia: From volume depletion and free water intake without adequate sodium replacement.
- Hypochloremia: Loss of hydrochloric acid in gastric contents.
- Metabolic alkalosis: Consequence of hydrogen ion loss through vomiting; serum bicarbonate is elevated.
- Elevated hematocrit: Hemoconcentration from dehydration; artifactually "normal" hemoglobin may mask true anemia.
- Ketonuria: Detected on urine dipstick; reflects starvation ketosis. Part of older diagnostic criteria; not required by the 2021 Windsor definition.
- Elevated blood urea nitrogen (BUN) and creatinine: Prerenal azotemia from volume depletion; blood urea nitrogen:creatinine ratio typically greater than 20:1.
- Elevated liver transaminases: aspartate aminotransferase (AST) and alanine aminotransferase (ALT) are elevated in up to 40% of hospitalized HG patients. The mechanism involves centrilobular hepatocyte damage from nutritional deprivation and metabolic stress. These abnormalities resolve with rehydration and nutritional repletion and do not require specific hepatic treatment.
- Suppressed thyroid-stimulating hormone with mildly elevated free T4: Reflecting gestational transient thyrotoxicosis (see Diagnosis section); TRAb and TPO-Ab are negative.
- Thiamine level: Often checked in prolonged HG, particularly before intravenous glucose is started; low levels confirm thiamine deficiency, which is treated with immediate replacement.
Treatment
Management of hyperemesis gravidarum follows a stepwise approach, escalating from lifestyle modification and oral medications to intravenous fluids, enteral nutrition, and in refractory cases, parenteral nutrition.
Outpatient and Mild Measures
- Small, frequent meals: Small amounts of plain, high-carbohydrate foods eaten often, including before getting out of bed, are a commonly described self-care measure
- Ginger: Evidence-based efficacy at 1 gram per day (divided doses); reduces nausea severity in multiple randomized controlled trials (RCTs)
- Trigger avoidance: Particular food smells, tastes or surroundings can set off nausea, and keeping away from known triggers is a common self-care measure
- Acupressure: P6 (Neiguan) wristbands provide modest benefit in some patients with minimal risk
- Rest and supportive care
First-Line Pharmacological Therapy
- Pyridoxine (Vitamin B6): 10–25 mg three times daily; reduces nausea severity; well-established safety profile; often used as monotherapy for milder cases
- Doxylamine-pyridoxine: The U.S. Food and Drug Administration (FDA)-approved combination for nausea and vomiting of pregnancy in women who do not respond to conservative management; its label states that it has not been studied in women with hyperemesis gravidarum; considered first-line pharmacotherapy; multiple safety studies do not demonstrate significant teratogenic risk
- About pregnancy “categories”: Older sources describe pregnancy drugs by FDA letter categories (A, B, C, D, X). The FDA's Pregnancy and Lactation Labeling Rule removed these letter categories from prescription drug labels; the labeling changes took effect on June 30, 2015.
- Antihistamines: Diphenhydramine, dimenhydrinate; effective for nausea/vomiting; generally considered safe in pregnancy
Antiemetic Agents
- Ondansetron: A 5-HT3 receptor antagonist; the most widely used intravenous and oral antiemetic for HG. Some earlier observational studies raised concern about heart defects. A U.S. study of 1,816,414 pregnancies, 88,467 of them exposed to ondansetron in the first trimester, found no increase in heart defects (adjusted relative risk 0.99). It did find a small rise in oral clefts (cleft lip or palate), from 11.1 to 14.0 per 10,000 births, about 3 extra cases per 10,000 exposed pregnancies (adjusted relative risk 1.24) (Huybrechts et al., 2018).
- Metoclopramide: Dopamine antagonist; also has prokinetic properties helpful in gastric dysmotility. Risk of extrapyramidal side effects (akathisia, dystonic reactions) at higher doses or with prolonged use; tardive dyskinesia with very long-term use.
- Prochlorperazine: Phenothiazine antiemetic; effective but higher sedation profile.
- Promethazine: Also effective but associated with significant maternal sedation and respiratory depression in high doses.
Intravenous Fluids and Electrolyte Replacement
- Intravenous fluid resuscitation: Normal saline (0.9% NaCl) or Lactated Ringer's solution for rehydration
- Critical rule — Thiamine BEFORE glucose: Standard practice is to give thiamine 100 mg intravenously before any dextrose-containing intravenous fluids. Administering glucose without thiamine in a thiamine-depleted patient can precipitate or worsen Wernicke's encephalopathy (see dedicated section below).
- Potassium chloride (KCl): Added to intravenous fluids for correction of hypokalemia; rate of replacement determined by severity and cardiac monitoring
- Magnesium: Replacement if hypomagnesemia is present
Nutritional Support
- Enteral nutrition: Nasogastric (NG) or nasojejunal (NJ) tube feeding is preferred when oral intake is impossible but the gastrointestinal tract remains functional. NJ feeding bypasses the stomach and may be better tolerated. Enteral nutrition is always preferred over parenteral when feasible.
- Total Parenteral Nutrition (TPN): Reserved as a last resort for refractory HG when enteral feeding is not possible or tolerated. Associated with significant risks including central line sepsis, thrombosis, metabolic derangements, and cholestasis. It is usually managed by a multidisciplinary team including nutrition support specialists.
Corticosteroids
Methylprednisolone (16 mg three times daily for 3 days, then gradually tapered) has been used for refractory HG. Evidence is mixed, with some trials showing benefit and others not. Important caveat: use before 10 weeks of gestation carries a small but documented association with oral cleft formation (cleft palate/lip) in early organogenesis, so it is generally kept for severe, refractory cases after other therapies have failed.
Emerging Therapies
Given the identification of GDF15 as a central pathogenic hormone, researchers have proposed treatments that block GDF15 or its receptor, or that lower sensitivity to it before pregnancy; Fejzo et al. (2024) write that their findings suggest “mechanism-based approaches to the treatment and prevention of HG.” Anti-GDF15 therapies are now in active clinical development and have been described as promising for reducing HG severity. No trial results in women with HG have been published. Such agents would be the first mechanism-targeted pharmacological approach to HG and may represent a major advance in treatment for this poorly-managed condition.
Thiamine and Wernicke's Encephalopathy
Wernicke's encephalopathy (WE) is a medical emergency that can develop in women with hyperemesis gravidarum due to thiamine (vitamin B1) depletion. Because thiamine is water-soluble and not stored in significant quantities, prolonged vomiting and inadequate dietary intake rapidly deplete thiamine stores — sometimes within weeks.
Classic Triad of Wernicke's Encephalopathy
- Confusion / altered mental status: Ranging from mild cognitive impairment to frank encephalopathy
- Ophthalmoplegia: Lateral rectus palsy (sixth nerve palsy) causing horizontal diplopia; nystagmus; gaze palsies
- Ataxia: Unsteady gait from cerebellar and vestibular involvement
The complete triad is present in only about 30% of cases. A high index of clinical suspicion is essential — in a pregnant patient with prolonged vomiting, new neurological symptoms are treated as an emergency.
The Critical Rule: Thiamine BEFORE Dextrose
This is one of the most important safety principles in managing HG with intravenous fluids. Administering intravenous glucose (dextrose) to a thiamine-depleted patient causes acute demand for thiamine in glucose metabolism — specifically in the pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase complexes of the Krebs cycle. Without thiamine, these enzymatic steps fail, leading to lactate accumulation and neuronal death in metabolically vulnerable brain regions.
Standard practice: thiamine 100 mg IV is given BEFORE any dextrose-containing intravenous fluid in a patient with prolonged vomiting or suspected thiamine deficiency.
Thiamine dose for Wernicke's treatment: 100–500 mg intravenous thiamine, three times daily, until no further neurological improvement is seen.
Korsakoff Psychosis
Untreated or inadequately treated Wernicke's encephalopathy progresses to Korsakoff syndrome (Korsakoff psychosis), characterized by severe anterograde amnesia (inability to form new memories), confabulation, and retrograde amnesia. Unlike Wernicke's encephalopathy (which responds to thiamine), Korsakoff syndrome may be permanent and irreversible. Prevention — by prompt thiamine administration before the Wernicke's stage — is far more effective than treatment after the fact.
Prognosis and Outcomes
The prognosis for hyperemesis gravidarum is generally favorable in terms of fetal survival, but maternal morbidity — including psychological sequelae — can be significant and lasting.
Resolution of Symptoms
The majority of HG cases resolve by 20 weeks of gestation, paralleling the decline in hCG levels. However, 10–20% of affected women experience symptoms that persist through the third trimester or even until delivery, representing a particularly burdened group requiring ongoing multidisciplinary support.
Fetal Outcomes
- In mild to moderate HG with adequate treatment, fetal outcomes are generally normal
- Severe, prolonged HG with inadequate nutrition is associated with fetal growth restriction and increased risk of preterm birth
- Some studies suggest associations with small-for-gestational-age infants in the most severe cases
- Paradoxically, some data suggest that women with HG have lower rates of miscarriage compared to NVP — possibly reflecting the hormonal vigor of a healthy first-trimester pregnancy
Maternal Psychological Sequelae
Psychological morbidity following HG is common and underrecognized. Depression, anxiety disorders, and post-traumatic stress disorder can persist well beyond resolution of the physical symptoms. Many women report that HG was among the most traumatic experiences of their lives. A significant proportion of women who experienced HG do not complete planned subsequent pregnancies, citing fear of recurrence.
Recurrence
How often HG comes back in a later pregnancy is uncertain. A 2020 systematic review found five studies, covering 40,350 women with HG, that reported recurrence rates from 15% to 81% (Dean et al., 2020). The studies defined HG differently. Those that counted only hospital cases catch only the most severe pregnancies, which can make recurrence look lower. A 2025 study notes recurrence reported to be “as high as 89%” (Sharma et al., 2025). This risk can inform preconception counseling and allow for early, proactive management in future pregnancies.
Key Research Papers
- Committee on Practice Bulletins—Obstetrics — ACOG Practice Bulletin No. 189: Nausea and Vomiting of Pregnancy (Obstetrics & Gynecology, 2018;131(1):e15–e30)
American College of Obstetricians and Gynecologists clinical practice guideline covering diagnosis, differential, and stepwise management of NVP and HG; it replaced Practice Bulletin No. 153 (2015).
— PubMed PMID: 29266076 - Fejzo M, Rocha N, Cimino I, et al. — GDF15 linked to maternal risk of nausea and vomiting during pregnancy (Nature, 2024;625(7996):760–767)
Used maternal blood GDF15 levels, mass spectrometry of a naturally labelled GDF15 variant and carriers of genetic variants. Found that most GDF15 in maternal blood comes from the feto-placental unit and that low GDF15 levels before pregnancy increase HG risk; women with beta-thalassaemia, who have chronically high GDF15, report very little nausea and vomiting of pregnancy.
— PubMed PMID: 38092039 - Fejzo MS, Sazonova OV, Sathirapongsasuti JF, et al. — Placenta and appetite genes GDF15 and IGFBP7 are associated with hyperemesis gravidarum (Nature Communications, 2018;9(1):1178)
Genome-wide association study of HG and the severity of nausea and vomiting of pregnancy; two genome-wide significant loci, implicating the genes GDF15 and IGFBP7, were replicated in an independent cohort.
— PubMed PMID: 29563502 - London V, Grube S, Sherer DM, Abulafia O. — Hyperemesis Gravidarum: A Review of Recent Literature (Pharmacology, 2017;100(3-4):161–171)
Review covering pathogenesis, maternal and fetal morbidity, and treatment options for HG; notes that available therapy has remained largely unchanged for decades.
— PubMed PMID: 28641304 - Grooten IJ, Den Hollander WJ, Roseboom TJ, Kuipers EJ, Jaddoe VW, Gaillard R, Painter RC. — Helicobacter pylori infection: a predictor of vomiting severity in pregnancy and adverse birth outcome (American Journal of Obstetrics and Gynecology, 2017;216(5):512.e1–512.e9)
Population-based Dutch cohort of 5,549 pregnant women; H. pylori-positive women were more likely to report daily vomiting (adjusted odds ratio 1.44). The authors state that the effect of eradication therapy should be the target of future studies.
— PubMed PMID: 28188774 - Boelig RC, Barton SJ, Saccone G, Kelly AJ, Edwards SJ, Berghella V. — Interventions for treating hyperemesis gravidarum (Cochrane Database of Systematic Reviews, 2016;(5):CD010607)
Cochrane systematic review of 25 trials (2,052 women) of pharmacological and non-pharmacological interventions in HG; for most outcomes the evidence was graded low or very low quality.
— PubMed PMID: 27168518 - Huybrechts KF et al. — First-Trimester Ondansetron, Cardiac Malformations and Oral Clefts (JAMA 2018)
Cohort study of 1.8 million pregnancies. First-trimester ondansetron exposure was not associated with cardiac malformations; there was a small absolute increase in oral clefts, about 3 additional cases per 10,000 exposed pregnancies.
— PubMed PMID: 30561479 - Goodwin TM — Hyperemesis Gravidarum (2008)
Foundational review of the hormonal pathogenesis of HG, with particular focus on the hCG hypothesis and its relationship to gestational thyrotoxicosis.
— Search PubMed - Klebanoff MA, Koslowe PA et al. — Epidemiology of Vomiting in Early Pregnancy (1985)
Epidemiological study examining prevalence, timing, and risk factors for nausea and vomiting in pregnancy, establishing foundational population data.
— PubMed PMID: 3903578 - Castillo MJ, Phillippi JC. — Hyperemesis gravidarum: a holistic overview and approach to clinical assessment and management (Journal of Perinatal & Neonatal Nursing, 2015;29(1):12–22)
Nursing overview of HG covering its costs and psychosocial impact, assessment of symptom severity, and nonpharmacologic and pharmacologic management.
— PubMed PMID: 25534678 - Jansen LAW, Koot MH, Van't Hooft J, et al. — The windsor definition for hyperemesis gravidarum: A multistakeholder international consensus definition (European Journal of Obstetrics & Gynecology and Reproductive Biology, 2021;266:15–22)
Delphi survey and consensus meeting of researchers, women with lived experience, and health professionals; defines HG by onset before 16 weeks, severe nausea and/or vomiting, inability to eat and/or drink normally, and strong limits on daily living.
— PubMed PMID: 34555550 - Dean CR, Bruin CM, O'Hara ME, Roseboom TJ, Leeflang MM, Spijker R, Painter RC. — The chance of recurrence of hyperemesis gravidarum: A systematic review (European Journal of Obstetrics & Gynecology and Reproductive Biology: X, 2020;5:100105)
Five studies (40,350 HG cases) reported recurrence rates from 15% to 81%; defining HG as hospital cases may have introduced detection bias.
— PubMed PMID: 32021976 - Sharma N, MacGibbon KW, Brecht-Doscher A, Cortessis VK, Fejzo MS. — Prepregnancy metformin use associated with lower risk of severe nausea and vomiting of pregnancy and hyperemesis gravidarum (American Journal of Obstetrics and Gynecology, 2025;233(6):649.e1–649.e14)
Questionnaire study of 5,414 participants; metformin use before the first pregnancy was associated with lower risk of HG (adjusted relative risk 0.29).
— PubMed PMID: 40588059
Connections
- Reproductive Medicine
- Ectopic Pregnancy
- Gestational Trophoblastic Disease
- Preeclampsia
- Gestational Diabetes
- Thiamine (Vitamin B1)
- Pyridoxine (Vitamin B6)