⚠ Evidence warning: Clinical trials or other evidence do not support the estimate of 150,000–200,000 deaths prevented per year, the 200 U/mL antibody level described as protective, and the older report of about 30% lower severity and fewer later episodes with zinc. This page keeps it as a report of what people, websites or other media say.
Rotavirus
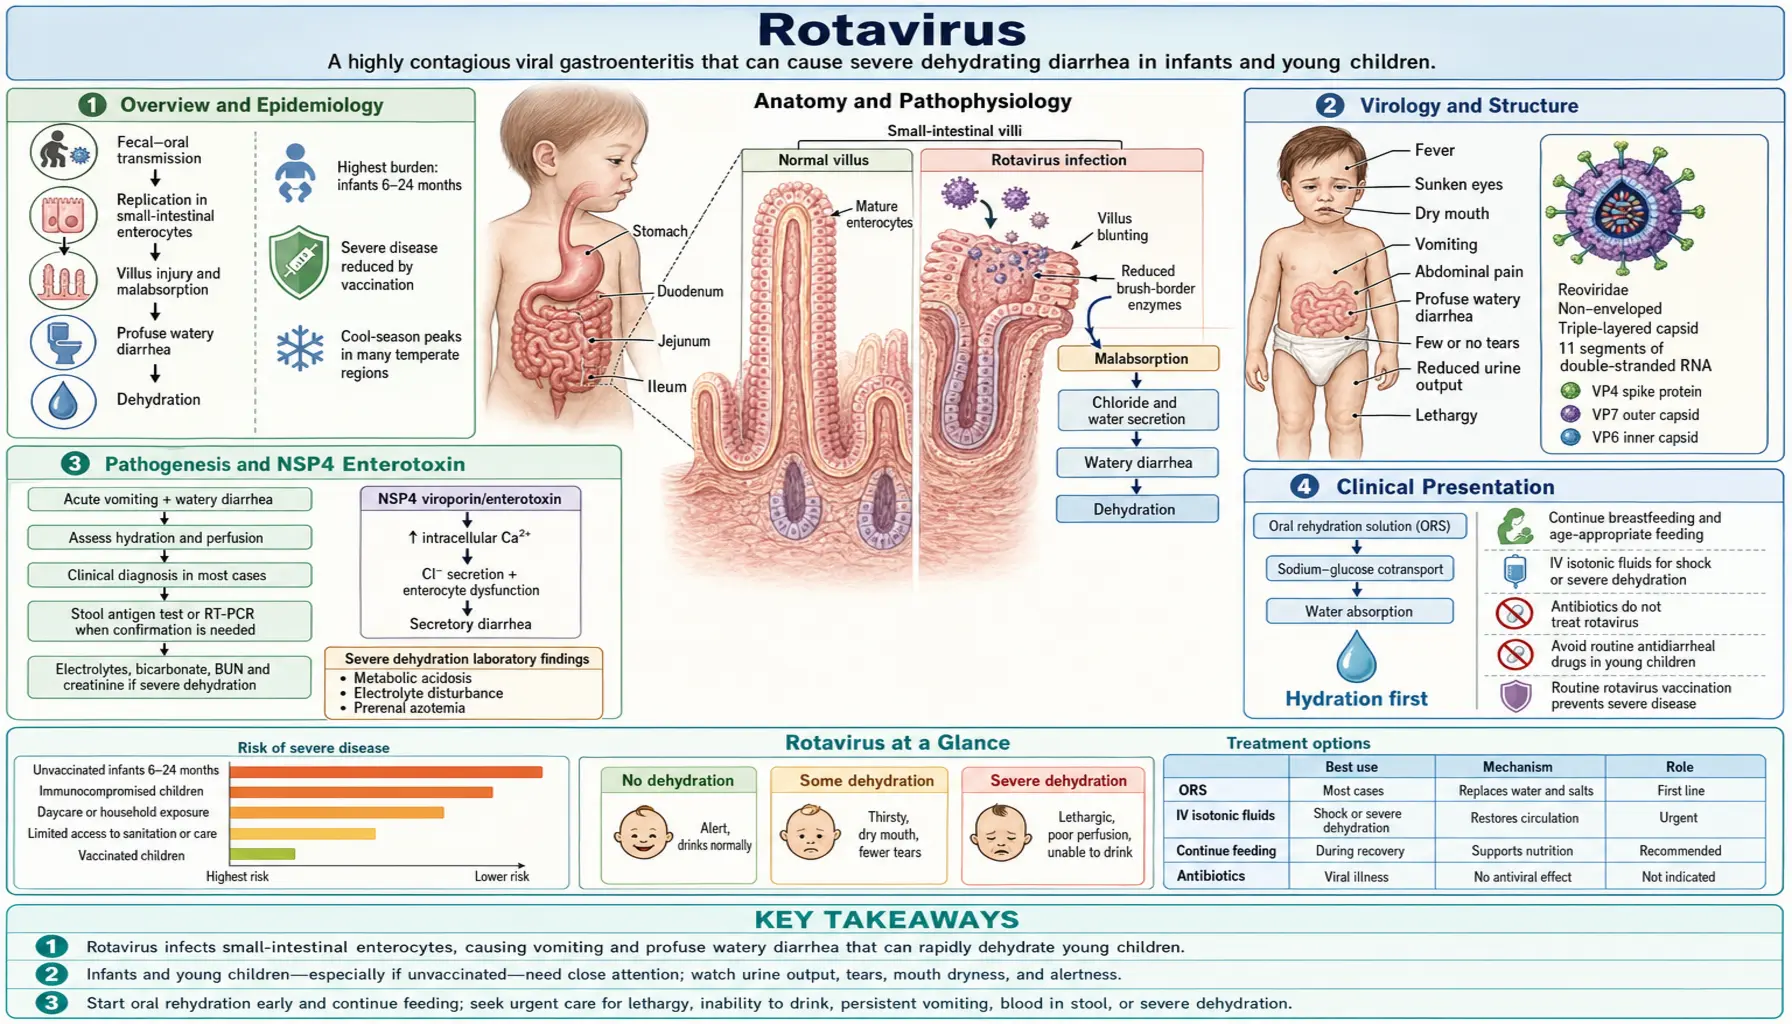
- Overview and Epidemiology
- Virology and Structure
- Pathogenesis and NSP4 Enterotoxin
- Clinical Presentation
- Diagnosis
- Treatment and Rehydration
- Assessing and Managing Dehydration
- Prevention — Vaccines
- Natural Immunity and Reinfection
- Key Research Papers
- Connections
Overview and Epidemiology
Rotavirus is the leading cause of severe diarrheal disease in young children worldwide and was, before the vaccine era, the single most important cause of childhood gastroenteritis hospitalizations in high-income countries. It is a double-stranded RNA virus belonging to the family Sedoreoviridae (order Reovirales; older sources say Reoviridae) that targets the mature enterocytes lining the small intestinal villi, causing a combination of malabsorption and secretory diarrhea that can rapidly dehydrate infants.
Nearly every child on earth is infected with rotavirus at least once before the age of 5, regardless of sanitation infrastructure — a defining feature that distinguishes it from most other enteric pathogens. Before widespread vaccination, rotavirus caused an estimated 453,000 deaths in 2008 in children under 5 globally (Tate JE et al., 2012), with the greatest burden in sub-Saharan Africa and South Asia. In the United States pre-vaccine, rotavirus was responsible for approximately 55,000–70,000 hospitalizations and 20–60 deaths annually in children under 5.
Rotavirus predominantly affects infants and toddlers aged 6 to 24 months, with the highest severity in the 6–12 month age group. Neonates can be infected but often have attenuated disease, possibly due to passive maternal antibody transfer or unique neonatal intestinal physiology. Disease in older children and adults is typically mild because immunity accumulates with each successive infection.
In temperate climates, rotavirus follows a clear winter seasonality — the US "rotavirus belt" historically swept from the Southwest in November through the Northeast by March–April. This seasonal pattern has been substantially disrupted by vaccination, which blunted epidemic peaks and shifted timing in many regions. In tropical countries, rotavirus circulates year-round with less pronounced seasonality.
Virology and Structure
Rotavirus is named for its distinctive wheel-like appearance under electron microscopy (rota = Latin for wheel). The virion is a non-enveloped, triple-layered icosahedral particle approximately 75 nm in diameter — one of the most structurally complex and stable viruses known to infect humans.
Genome organization. The rotavirus genome consists of 11 segments of double-stranded RNA, each encoding one or two proteins. This segmented organization has important biological consequences: when two different rotavirus strains simultaneously infect the same cell, genome segments can be exchanged (genetic reassortment), generating novel strains. This process is analogous to influenza's genetic shift and is a major driver of rotavirus diversity.
Triple-layered capsid. The three concentric protein layers serve distinct functions:
- Inner core (VP2/VP1/VP3): VP2 encases the RNA segments; VP1 is the RNA-dependent RNA polymerase; VP3 is the capping enzyme. Together they form the replication machinery.
- Middle layer (VP6): Encoded by gene segment 6. VP6 is the most abundant structural protein and the target of the immunofluorescence-based diagnostic tests. Its subgroup antigen (SGA) defines Group A (the predominant human pathogen) from Groups B, C, etc.
- Outer layer (VP7 and VP4): VP7 is a glycoprotein (G antigen); VP4 is a protease-cleaved spike protein (P antigen) that mediates cell attachment. The combination of G and P types defines the rotavirus genotype, which determines the G-P binary classification system used in epidemiological surveillance and vaccine matching.
Common strains. Five G-P combinations account for approximately 90% of human rotavirus disease globally: G1P[8] (historically dominant in North America and Europe), G2P[4], G3P[8], G4P[8], and G9P[8]. The two first-licensed vaccines — a monovalent human vaccine (G1P[8]) and a pentavalent human-bovine reassortant vaccine (human G1, G2, G3, G4 and P[8]) — were designed around these dominant strains. Emerging G12 strains and P[6] strains in Africa and Asia are subjects of ongoing surveillance to ensure continued vaccine coverage.
Environmental stability. Rotavirus is extraordinarily environmentally stable. It survives on hard surfaces for days to weeks, resists many common hand sanitizers (alcohol-based formulations are less effective than soap and water), and retains infectivity in water. The infectious dose is extremely low — approximately 10 viral particles — making fecal-oral transmission efficient even with minor hygiene lapses. A single gram of stool from an infected child may contain up to 10 trillion virions.
Pathogenesis and NSP4 Enterotoxin
The pathogenesis of rotavirus diarrhea is multifactorial and involves two distinct mechanisms acting simultaneously: a malabsorptive component from enterocyte destruction and a secretory component driven by the non-structural protein NSP4 acting as a viral enterotoxin. This dual mechanism explains why rotavirus diarrhea is more severe and more rapidly dehydrating than enteritides driven by malabsorption alone.
Enterocyte infection and villus destruction. Rotavirus preferentially infects the mature, differentiated enterocytes at the tips of small intestinal villi — the cells most responsible for nutrient absorption and disaccharidase enzyme expression (including lactase, sucrase, and maltase). VP4 binds to cell surface integrins (particularly alpha2beta1 and alphaVbeta3) and sialic acid residues; VP7 interacts with heat shock cognate protein Hsc70 on the cell surface. Following receptor engagement, the virus is endocytosed and uncoated.
Viral replication within the enterocyte leads to cell death within 12–24 hours. Loss of villus tip enterocytes produces villus blunting and relative preservation of immature crypt cells (which proliferate to replace lost cells but initially lack full absorptive function). The net effect is:
- Reduced absorptive surface area → malabsorption of glucose, sodium, and water
- Lactase deficiency (secondary, due to loss of lactase-expressing villus tip cells) → osmotic diarrhea from unabsorbed lactose; this can persist for 1–2 weeks after clinical recovery and may necessitate temporary lactose reduction in formula-fed infants with severe disease
- Disrupted Na+/glucose co-transporter (SGLT1) expression → the physiological basis for why glucose-coupled oral rehydration solution (ORS) still works (SGLT1 is partially preserved in crypt cells that survive)
NSP4: the world's first described viral enterotoxin. In 1996, Estes MK and colleagues demonstrated in young mice that the non-structural rotavirus protein NSP4 (encoded by gene segment 10) functions as an enterotoxin independent of the structural viral damage described above — the first viral protein shown to act in this way (Ball JM et al., 1996). NSP4 is a transmembrane glycoprotein that accumulates in the endoplasmic reticulum of infected cells and is secreted extracellularly.
Secreted NSP4 binds to uninfected neighboring enterocytes and activates a phospholipase C / IP3 / intracellular Ca2+ signaling cascade that mobilizes calcium from endoplasmic reticulum stores. Elevated intracellular Ca2+ triggers chloride secretion through calcium-activated chloride channels (CaCC, particularly transmembrane protein 16A, TMEM16A) independently of cAMP — the mechanism by which classical bacterial enterotoxins like cholera toxin act. NSP4 also activates the enteric nervous system (via serotonin/5-HT3 pathway), stimulating neurally mediated fluid secretion and contributing to the vomiting response. The combined effect creates a secretory diarrhea that persists even in areas of intestine where enterocyte infection has not yet occurred.
Immune response. Rotavirus induces both innate (type I/III interferons, natural killer (NK) cells) and adaptive (virus-specific CD4+ and CD8+ T cells, mucosal immunoglobulin A (IgA), systemic immunoglobulin A and immunoglobulin G (IgG)) immunity. Mucosal rotavirus-specific immunoglobulin A correlates most strongly with protection from subsequent disease. The adaptive immune response clears primary infection within 7–10 days, but rotavirus actively suppresses innate interferon signaling through NSP1, allowing initial establishment of infection.
Clinical Presentation
Rotavirus gastroenteritis follows a characteristic pattern that distinguishes it clinically from bacterial enteritides and other viral gastroenteritis syndromes. Recognizing this pattern helps clinicians anticipate severity and guide appropriate management.
Incubation period: 1–3 days. The interval between exposure and symptom onset is short and relatively consistent, reflecting efficient viral replication in a susceptible host.
Onset: abrupt, with vomiting preceding diarrhea. The illness typically begins abruptly with vomiting — often the dominant and most distressing early symptom — which then transitions to watery diarrhea within 12–24 hours. This vomiting-first pattern, driven by NSP4's activation of the enteric nervous system, is characteristic and clinically useful: most bacterial gastroenteritides present primarily with diarrhea, while rotavirus and norovirus begin prominently with vomiting.
Fever is present in approximately 50–60% of cases, typically in the range of 38–39°C (100.4–102.2°F), and usually resolves within the first 2 days. High fever persisting beyond 48–72 hours can point to a bacterial superinfection or an alternative diagnosis.
Diarrhea is watery, non-bloody, and non-mucoid — appearing pale yellow or white ("rice-water" in severe cases). Stool frequency is typically 5–10 episodes per day but can exceed 20 in severe disease. The absence of blood and mucus distinguishes rotavirus from invasive bacterial enteritides (Salmonella, Shigella, Campylobacter, enterohemorrhagic E. coli) and from inflammatory bowel disease flares. Bloody diarrhea in an infant or toddler is not a feature of rotavirus, and hospitals treat it as a reason for further evaluation.
Duration: 3–8 days. Most children recover within 3–5 days, though diarrhea may persist up to 8 days in severe cases. A second wave of diarrhea occurring after apparent improvement may indicate secondary lactose intolerance from villus tip damage rather than treatment failure.
Dehydration risk. The combination of high-volume vomiting (limiting oral fluid intake) and high-frequency watery diarrhea (causing large fluid losses) creates a perfect storm for rapid dehydration — particularly in infants 6–24 months, who have the smallest absolute fluid reserves and the greatest surface-area-to-volume ratio driving insensible losses. Clinical dehydration develops in 40–50% of children requiring medical attention, and severe dehydration (>10% body weight lost) occurs in 10–15% of hospitalized cases.
Clinical scoring. The Vesikari Clinical Severity Scoring System (vomiting duration/frequency + diarrhea duration/frequency + maximum temperature + dehydration + treatment required) is used in clinical trials to standardize severity assessment. Scores ≥11 define severe rotavirus gastroenteritis — the primary vaccine efficacy endpoint in pivotal trials.
Atypical presentations. In immunocompromised children (primary immunodeficiencies, post-transplant, human immunodeficiency virus-infected), rotavirus can cause protracted diarrhea lasting weeks to months with progressive malnutrition. Rotavirus has also been detected in the cerebrospinal fluid (CSF) during febrile seizures and in the blood during severe gastroenteritis in immunocompromised hosts, though systemic dissemination in immunocompetent children is rare.
Diagnosis
Rotavirus gastroenteritis is primarily a clinical diagnosis in the appropriate epidemiological context — an infant or toddler presenting in winter with abrupt-onset vomiting followed by watery non-bloody diarrhea. Laboratory confirmation is not required to initiate management and is not routinely performed in clinical practice.
When stool testing is indicated:
- Hospitalized patients (for cohorting and infection control)
- Immunocompromised children (guides antiviral decisions and duration of isolation)
- Outbreak investigation in institutional settings (day care centers, neonatal units)
- Epidemiological surveillance and vaccine effectiveness studies
- Atypical clinical features where diagnosis is uncertain
Diagnostic tests:
- Stool enzyme immunoassay (EIA) / lateral flow rapid antigen test: Detects VP6 antigen (Group A rotavirus). Sensitivity 70–95%, specificity >98%. Results available within 15–30 minutes for rapid tests. The most widely used point-of-care test in clinical and outbreak settings. May remain positive for several days after clinical recovery.
- Stool RT-PCR: Highest sensitivity (>98%) and allows G/P genotyping for surveillance. Gold standard for vaccine effectiveness studies. Not routinely needed clinically but increasingly available via multiplex gastrointestinal panels (for example, a gastrointestinal panel that detects rotavirus among 22 pathogens simultaneously).
- Electron microscopy: Historically used for diagnosis and identified rotavirus in 1973 (Bishop RF et al.); now supplanted by antigen tests and polymerase chain reaction (PCR).
Stool characteristics: Bloody or mucoid stool is not consistent with rotavirus and is a reason laboratories test for bacterial enteritis (stool culture ± polymerase chain reaction for Shiga toxin-producing E. coli). Stool pH <5.5 and reducing substances in stool may indicate secondary lactose intolerance.
Blood tests are not routinely indicated. Electrolyte measurement (sodium, potassium, bicarbonate) is important when moderate-to-severe dehydration is present, as rotavirus-associated dehydration is typically isotonic (plasma sodium 130–150 mEq/L); however, hypernatremic dehydration (>150 mEq/L) can occur when caregivers offer hyperosmolar fluids or inadequate free water. Metabolic acidosis (bicarbonate <15 mEq/L) with elevated anion gap indicates significant volume depletion and lactic acidemia requiring intravenous (IV) correction.
Treatment and Rehydration
There is no specific antiviral therapy for rotavirus in immunocompetent children. The cornerstone of management is prevention and correction of dehydration. All other interventions are adjunctive. Antibiotics are never indicated for uncomplicated rotavirus gastroenteritis.
Oral rehydration solution: the cornerstone of treatment. It is one of the most impactful public health interventions of the 20th century and remains the first-line treatment for mild-to-moderate dehydration globally. The WHO/UNICEF formulation contains:
- Sodium 75 mmol/L
- Chloride 65 mmol/L
- Glucose (anhydrous) 75 mmol/L (13.5 g/L)
- Potassium 20 mmol/L
- Citrate 10 mmol/L (bicarbonate equivalent)
- Osmolarity 245 mOsm/L (reduced osmolarity, 2002 reformulation)
The glucose-sodium co-transport mechanism (SGLT1) is preserved even in rotavirus-damaged intestinal cells because crypt enterocytes — which repopulate the damaged villi — retain functional SGLT1. Each molecule of glucose absorbed carries one sodium ion and water by osmotic coupling, enabling active intestinal hydration even during active diarrhea. Oral rehydration solution is as effective as intravenous rehydration for mild-to-moderate dehydration and reduces hospitalization when started early at home.
Practical oral rehydration solution administration: The method usually described is 5 mL every 1–2 minutes by teaspoon or syringe, because large volumes can trigger the vomiting reflex. If the child vomits, there is a wait of 5–10 minutes before restarting. Ready-made pediatric electrolyte solutions are suitable; juice, sports drinks, and broth have an electrolyte composition that does not suit rehydration. The 2014 European guideline states that breast-feeding is not interrupted and regular feeding continues with no dietary changes.
Intravenous rehydration is required for severe dehydration (>10% body weight), shock (altered consciousness, absent or faint pulses, extreme tachycardia), inability to drink or persistent vomiting preventing oral rehydration solution administration, or signs of ileus. Standard initial resuscitation: 20 mL/kg isotonic saline (0.9% NaCl) or Ringer's lactate as a rapid bolus, repeated until circulation improves. Subsequent fluid therapy targets deficit replacement over 4–6 hours plus ongoing losses.
Ondansetron. A 5-HT3 receptor antagonist that reduces vomiting and improves oral rehydration solution tolerance. A single oral dose (0.15 mg/kg, max 8 mg) was tested in a 2006 double-blind trial of 215 children aged 6 months through 10 years with gastroenteritis and dehydration: fewer vomited (14% against 35%), they drank more (239 mL against 196 mL) and fewer needed intravenous fluids (14% against 31%), but hospitalization did not differ (4% against 5%). Meta-analyses are reported to confirm clinical benefit with an acceptable safety profile, while the 2014 European guideline states that ondansetron is effective against vomiting but that its routine use requires safety clearance given the warning about severe cardiac effects. Ondansetron is now standard in emergency department management of pediatric gastroenteritis with prominent vomiting where oral rehydration solution is otherwise not tolerated.
Zinc supplementation. WHO guidelines recommend 10 mg/day (infants <6 months) or 20 mg/day (children ≥6 months) for 10–14 days in children with acute diarrhea in developing countries. A 2016 Cochrane review (33 trials, 10,841 children) found that in children older than 6 months zinc may shorten diarrhea by around half a day (11.46 hours, low certainty evidence) and by around a day in children with signs of malnutrition (26.39 hours), while in children younger than 6 months it may have no effect (5.23 hours longer). Zinc raised the risk of vomiting in both age groups (risk ratios 1.57 and 1.54). Older summaries also report about 30% lower severity and fewer diarrheal episodes for up to 3 months. The mechanism involves enhancement of intestinal immune function and enterocyte repair. Zinc is most beneficial in populations with underlying zinc deficiency, which is common in low-income countries; evidence in well-nourished children in high-income settings is weaker, and the Cochrane authors state that current evidence does not support zinc in children under 6 months, in well-nourished children, or where the risk of zinc deficiency is low. A 2020 trial of 4,500 children aged 6–59 months in India and Tanzania found 5 mg and 10 mg of zinc noninferior to the WHO 20 mg dose for diarrhea lasting more than 5 days (7.2%, 7.7% and 6.5%), and vomiting within 30 minutes of a dose was less common at the lower doses (13.7%, 15.6% and 19.3%).
Probiotics. Earlier evidence pointed to a modest reduction in diarrhea duration with specific probiotic strains (particularly Lactobacillus rhamnosus GG and Saccharomyces boulardii), of approximately 1 day, with variable trial quality, and the 2014 European guideline lists those two strains among effective interventions. Two large 2018 trials in children then found no benefit: moderate-to-severe illness in 11.8% on L. rhamnosus GG against 12.6% on placebo (971 children), and in 26.1% on a combination probiotic against 24.7% on placebo (886 children). The 2020 Cochrane review (82 studies) found, in its low-risk-of-bias trials, no difference in diarrhea lasting 48 hours or more (risk ratio 1.00) and was uncertain about duration; no serious adverse events were attributed to probiotics. Probiotics are not routinely recommended but are unlikely to cause harm in immunocompetent children.
Nitazoxanide. An antiprotozoal and antiviral agent with documented in vitro activity against rotavirus. Small randomized controlled trials in immunocompromised and healthy children suggest modest clinical benefit. Not approved by the U.S. Food and Drug Administration (FDA) specifically for rotavirus, and not currently recommended as standard therapy in immunocompetent children. May have a role in immunocompromised patients with prolonged rotavirus diarrhea.
Assessing and Managing Dehydration
Accurate dehydration assessment is the most critical clinical skill in managing rotavirus gastroenteritis. Underestimating dehydration risks preventable complications including shock, seizures (from electrolyte disturbance), and acute kidney injury. Overestimating triggers unnecessary intravenous placement and hospitalization.
WHO Integrated Management of Childhood Illness (IMCI) dehydration classification:
- No dehydration (<3% body weight lost): Normal sensorium, moist mucous membranes, normal skin turgor (pinch recoil <2 seconds), normal eyes, urine output normal. Management: maintenance oral rehydration solution + early refeeding at home.
- Some dehydration (3–9% body weight lost): Restless or irritable, slightly sunken eyes, dry mucous membranes, skin recoil 2–3 seconds, decreased urine output. Management: oral rehydration solution 50–100 mL/kg over 4 hours in medical setting; reassess.
- Severe dehydration (>10% body weight lost): Lethargic or unconscious, sunken eyes + fontanelle, very dry mucous membranes, skin recoil >3 seconds ("tenting"), absent or greatly reduced urine output, shock signs (tachycardia, weak or absent peripheral pulses, prolonged capillary refill >3 seconds, altered consciousness). Management: immediate intravenous resuscitation with 20 mL/kg isotonic saline bolus; oral rehydration is not started until circulation is restored.
Important caveats:
- Skin turgor is less reliable in malnourished children (skin tents even without dehydration) and in hypernatremic dehydration (skin may remain turgid even with significant fluid deficit because intracellular water is better preserved when plasma osmolality is high)
- Capillary refill time is unreliable in cold environments and in dark-skinned infants — it is read most reliably in a warm room with adequate lighting
- Weight loss (comparing to a recent pre-illness weight) is the most objective dehydration measure when available
- Sunken eyes and fontanelle are specific but insensitive — absence does not exclude dehydration
Electrolyte monitoring in hospitalized patients. Hospitals measure serum sodium, potassium, bicarbonate, blood urea nitrogen (BUN), and creatinine in children requiring intravenous fluids. Hypokalemia (common in prolonged diarrhea) is corrected by adding potassium to intravenous fluids once urine output is established. Hypernatremia is corrected slowly (plasma sodium falling by no more than 10–12 mEq/L per day), because rapid osmotic shifts can cause cerebral edema.
Prevention — Vaccines
The development and global implementation of rotavirus vaccines represents one of the greatest achievements of 21st-century pediatric medicine. WHO describes four oral, live, attenuated vaccines as available internationally and WHO prequalified: one derived from a single common human strain, one human-bovine reassortant, one naturally occurring bovine-human reassortant neonatal strain (116E), and one bovine-human reassortant carrying human G1, G2, G3 and G4 on a bovine backbone. The two first licensed are described here:
Live oral human rotavirus vaccine. A live attenuated oral vaccine containing a single human G1P[8] strain (derived from a natural human rotavirus isolate). Administered as two oral doses at 2 and 4 months of age. This vaccine provides broad protection through cross-reactive immune responses to non-G1 strains (G2, G3, G4, G9) as well as the homologous G1 strain. Phase 3 trials demonstrated >85% efficacy against severe rotavirus gastroenteritis in high-income settings and 50–73% in low-income African and Asian settings.
Live oral pentavalent reassortant vaccine. A live reassortant oral vaccine containing five human-bovine reassortant viruses, built on the bovine WC3 parent strain. According to its label, four express one human outer capsid protein (G1, G2, G3, or G4) with the attachment protein (type P7) of the bovine parent, and the fifth expresses the human attachment protein P1A (genotype P[8]) with the bovine G6 outer capsid protein. Administered as three oral doses at 2, 4, and 6 months of age. The pivotal REST trial (Vesikari T et al., 2006) demonstrated 98.0% efficacy against severe G1-G4 rotavirus gastroenteritis and 74.0% against any G1-G4 rotavirus gastroenteritis through the first full rotavirus season after vaccination, and a 94.5% reduction in hospitalizations and emergency department visits for G1-G4 rotavirus.
Real-world impact in the United States. Following the recommendation of the Advisory Committee on Immunization Practices (ACIP) and routine vaccination beginning in 2006, rotavirus-coded hospitalizations in commercially insured US children under 5 fell, against the 2001–2006 average, by 75% in 2007–08, 60% in 2008–09, 94% in 2009–10 and 80% in 2010–11. Rotavirus emergency department visits and outpatient visits declined by 50–60%. Herd protection extended to unvaccinated infants too young for vaccination and to adults, demonstrating indirect community immunity effects.
Global deployment. As of 2023, rotavirus vaccine has been introduced into national immunization programs in over 120 countries. An estimate of approximately 150,000–200,000 deaths prevented per year globally has been quoted, with the largest absolute mortality reduction in sub-Saharan Africa; no source for it could be found. International vaccine-financing programs have facilitated introduction in low-income countries at subsidized prices.
The burden in the vaccine era. A Global Burden of Disease analysis estimated 128,500 rotavirus deaths among children under 5 in 2016, 104,733 of them in sub-Saharan Africa, and more than 258 million episodes of diarrhea. It estimated that vaccine use averted more than 28,000 deaths that year (95% uncertainty interval 14,600–46,700).
Measured impact worldwide. Across 105 studies in 49 countries, vaccine introduction was followed by median falls of 59% in rotavirus hospitalizations, 36% in hospitalizations for gastroenteritis of any cause and 36% in gastroenteritis deaths, with larger reductions where child mortality was low. Unvaccinated children also benefit: a meta-analysis of 14 studies put indirect protection against rotavirus hospitalization at 48% overall, 52% in high-income countries and 25% in low- and middle-income countries.
Safety: intussusception. An earlier rotavirus vaccine (1999) was withdrawn from the US market after post-marketing surveillance identified a small but real increased risk of intussusception (approximately 1 in 10,000 vaccine recipients). The two vaccines described above were studied in pre-licensure trials explicitly designed to rule out a similar risk and showed no significant intussusception signal. However, post-licensure surveillance in some countries (Australia, Mexico, Brazil) identified a very small increased risk of intussusception following dose 1, approximately 1–6 excess cases per 100,000 first doses. This risk is substantially smaller than the intussusception risk avoided by preventing rotavirus disease itself; measured in Mexico and Brazil, a combined annual 96 excess intussusception cases and 5 deaths from it were attributed to the human vaccine (about 1 per 51,000 infants in Mexico and 1 per 68,000 in Brazil), against about 80,000 hospitalizations and 1,300 diarrhea deaths prevented each year. Current guidance supports continued vaccination with awareness of the small absolute risk.
Administration precautions: Rotavirus vaccines are live oral vaccines; they are contraindicated in infants with severe combined immunodeficiency (SCID) (fatal vaccine-derived rotavirus disease has been reported). Both US labels also list a history of intussusception and hypersensitivity to a vaccine component as contraindications, and the human-vaccine label adds an uncorrected congenital malformation of the gastrointestinal tract that would predispose to intussusception. In a US postmarketing study described on the pentavalent label, intussusception cases clustered in the first 7 days after the first dose. Age limits depend on the source: US Advisory Committee on Immunization Practices recommendations give a maximum age of 14 weeks 6 days for the first dose and 8 months 0 days for the last dose; the pentavalent label starts the series at 6 to 12 weeks and states the third dose should not be given after 32 weeks; the human-vaccine label gives the second dose up to 24 weeks. Shedding in stool occurs for up to 15 days after vaccination, and hand hygiene is the point raised for immunocompromised household contacts.
Natural Immunity and Reinfection
Immunity following rotavirus infection is protective but incomplete, and reinfection is the rule rather than the exception. Understanding this pattern explains both the epidemiology of disease across the lifespan and the immunological basis for vaccine efficacy.
Protection by infection number. The first rotavirus infection (typically during infancy) tends to be the most severe, often causing clinically significant dehydration requiring medical attention. The second infection (typically toddlerhood) is usually milder, with shorter duration and fewer stool episodes. By the third or fourth infection, disease is generally subclinical. This stepwise immunity means that adolescents and adults who are re-exposed may experience vomiting and loose stools but rarely develop the dehydrating illness seen in infants. This pattern was documented in the Mexican birth cohort study of Velázquez FR and colleagues (200 infants): against no previous infection, the adjusted relative risk of diarrhea was 0.23, 0.17 and 0.08 after one, two and three infections, and no child had moderate-to-severe diarrhea after two infections.
Correlates of protection. Serum rotavirus-specific immunoglobulin A antibodies correlate best with protection from disease in natural infection and vaccination studies. Mucosal immunoglobulin A in the intestinal lumen provides the first line of defense against reinfection. Serum immunoglobulin A levels >200 U/mL have been described as protective, but no source for that figure could be found. An analysis of trials of the human vaccine states that no correlate of vaccine efficacy has yet been established; it used seropositivity of ≥20 U/mL, which explained only 43.6% of the vaccine effect on any rotavirus gastroenteritis and 32.7% on severe disease. Cell-mediated immunity (rotavirus-specific CD8+ cytotoxic T lymphocytes) contributes to viral clearance during active infection but correlates less consistently with protection from disease on re-exposure.
Strain heterogeneity and reinfection. While immunity following natural infection or vaccination is broadly cross-protective (heterotypic immunity), it is not completely type-independent. Infection with G1P[8] produces strong homotypic protection against G1P[8] reinfection but partial heterotypic protection against G2P[4] or G12P[8] strains. Strain evolution and emergence of novel genotypes is therefore a continuing challenge for both vaccine coverage and natural immunity landscapes.
Maternal antibodies. Transplacental transfer of maternal rotavirus immunoglobulin G provides partial passive protection to neonates, particularly in the first weeks of life. This may explain why neonatal rotavirus infections, though common, are often asymptomatic or mild. Breast milk containing secretory immunoglobulin A and lactoferrin also confers some protection; exclusive breastfeeding is associated with lower rates of symptomatic rotavirus infection in observational studies, though it does not fully prevent disease.
Key Research Papers
- Vesikari T, Matson DO, Dennehy P, et al. Safety and efficacy of a pentavalent human-bovine (WC3) reassortant rotavirus vaccine. N Engl J Med. 2006;354(1):23-33. Landmark phase 3 trial in 68,038 infants: 98.0% efficacy against severe G1-G4 rotavirus gastroenteritis, 74.0% against any G1-G4 disease and a 94.5% reduction in hospitalizations and emergency department visits for G1-G4 rotavirus, establishing the evidence base for universal infant rotavirus vaccination in the United States. — PubMed PMID: 16394299
- Ruiz-Palacios GM, Pérez-Schael I, Velázquez FR, et al. Safety and efficacy of an attenuated vaccine against severe rotavirus gastroenteritis. N Engl J Med. 2006;354(1):11-22. Phase 3 trial in 63,225 infants from 11 Latin American countries and Finland (efficacy subgroup 20,169): 85% efficacy against severe rotavirus gastroenteritis and against rotavirus-associated hospitalization, and 42% fewer hospitalizations for diarrhea of any cause, leading to WHO prequalification and global deployment. — PubMed PMID: 16394298
- Ball JM, Tian P, Zeng CQ, Morris AP, Estes MK. Age-dependent diarrhea induced by a rotaviral nonstructural glycoprotein. Science. 1996;272(5258):101-104. Original paper demonstrating in young mice that NSP4 functions as a viral enterotoxin — the first viral protein shown to cause diarrhea by direct secretory mechanisms — establishing a new paradigm for understanding rotavirus pathogenesis beyond simple enterocyte destruction. — PubMed PMID: 8600515
- Tate JE, Burton AH, Boschi-Pinto C, Steele AD, Duque J, Parashar UD. 2008 estimate of worldwide rotavirus-associated mortality in children younger than 5 years before the introduction of universal rotavirus vaccination programmes: a systematic review and meta-analysis. Lancet Infect Dis. 2012;12(2):136-141. Systematic analysis estimating 453,000 rotavirus deaths globally in children under 5 in 2008, establishing the scale of the pre-vaccine burden and providing the primary justification for global vaccine scale-up. — PubMed PMID: 22030330
- Leshem E, Moritz RE, Curns AT, et al. Rotavirus vaccines and health care utilization for diarrhea in the United States (2007-2011). Pediatrics. 2014;134(1):15-23. Claims analysis in commercially insured US children under 5: rotavirus-coded hospitalizations fell by 75%, 60%, 94% and 80% in the four seasons from 2007-08 to 2010-11, with indirect benefits to unvaccinated children. — PubMed PMID: 24913793
- Patel MM, López-Collada VR, Bulhões MM, et al. Intussusception risk and health benefits of rotavirus vaccination in Mexico and Brazil. N Engl J Med. 2011;364(24):2283-2292. Post-licensure surveillance study identifying a short-term risk of intussusception in approximately 1 of every 51,000 to 68,000 vaccinated infants, while the deaths and hospitalizations averted far exceeded the intussusception cases. — PubMed PMID: 21675888
- Guarino A, Ashkenazi S, Gendrel D, Lo Vecchio A, Shamir R, Szajewska H. European Society for Pediatric Gastroenterology, Hepatology, and Nutrition/European Society for Pediatric Infectious Diseases evidence-based guidelines for the management of acute gastroenteritis in children in Europe: update 2014. J Pediatr Gastroenterol Nutr. 2014;59(1):132-152. The 2014 update of the guidelines naming oral rehydration with hypoosmolar solution as the major treatment; ondansetron is called effective against vomiting, with routine use requiring safety clearance. — PubMed PMID: 24739189
- Freedman SB, Adler M, Seshadri R, Powell EC. Oral ondansetron for gastroenteritis in a pediatric emergency department. N Engl J Med. 2006;354(16):1698-1705. Randomized controlled trial finding that a single oral dose of ondansetron significantly reduced vomiting and intravenous rehydration in children with gastroenteritis in the emergency department; hospitalization rates did not differ. — PubMed PMID: 16625009
- Velázquez FR, Matson DO, Calva JJ, et al. Rotavirus infection in infants as protection against subsequent infections. N Engl J Med. 1996;335(14):1022-1028. Prospective birth cohort study of 200 Mexican infants demonstrating that successive rotavirus infections confer progressively greater protection: after one prior infection the adjusted relative risk of diarrhea was 0.23, and no child had moderate-to-severe diarrhea after two infections — establishing the natural immunity gradient that informs vaccine design. — PubMed PMID: 8793926
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12(12):CD005436. Systematic review of 33 trials: zinc may benefit children aged six months or more where zinc deficiency or malnutrition is common; current evidence does not support it under six months or in well-nourished children. — PubMed PMID: 27996088
- Bishop RF, Davidson GP, Holmes IH, Ruck BJ. Virus particles in epithelial cells of duodenal mucosa from children with acute non-bacterial gastroenteritis. Lancet. 1973;2(7841):1281-1283. Original discovery paper identifying rotavirus (then called "duovirus") in intestinal epithelial cells of children with gastroenteritis by electron microscopy — the foundational discovery leading to understanding of the world's most common cause of severe childhood diarrhea. — PubMed PMID: 4127639
- Hahn S, Kim Y, Garner P. Reduced osmolarity oral rehydration solution for treating dehydration due to diarrhoea in children: systematic review. BMJ. 2001;323(7304):81-85. Systematic review of 15 trials finding fewer unscheduled intravenous infusions with reduced-osmolarity solution (245 mOsm/L) than with the original higher-osmolarity formula (311 mOsm/L) for childhood diarrhea, leading to the 2002 WHO reformulation that is now the global standard. — PubMed PMID: 11451782
- Troeger C, Khalil IA, Rao PC, et al. Rotavirus Vaccination and the Global Burden of Rotavirus Diarrhea Among Children Younger Than 5 Years. JAMA Pediatr. 2018;172(10):958-965. — PubMed PMID: 30105384
- Burnett E, Parashar UD, Tate JE. Global Impact of Rotavirus Vaccination on Diarrhea Hospitalizations and Deaths Among Children <5 Years Old: 2006-2019. J Infect Dis. 2020;222(10):1731-1739. — PubMed PMID: 32095831
- Rosettie KL, Vos T, Mokdad AH, et al. Indirect Rotavirus Vaccine Effectiveness for the Prevention of Rotavirus Hospitalization: A Systematic Review and Meta-Analysis. Am J Trop Med Hyg. 2018;98(4):1197-1201. — PubMed PMID: 29436336
- Dhingra U, Kisenge R, Sudfeld CR, et al. Lower-Dose Zinc for Childhood Diarrhea - A Randomized, Multicenter Trial. N Engl J Med. 2020;383(13):1231-1241. — PubMed PMID: 32966722
- Schnadower D, Tarr PI, Casper TC, et al. Lactobacillus rhamnosus GG versus Placebo for Acute Gastroenteritis in Children. N Engl J Med. 2018;379(21):2002-2014. — PubMed PMID: 30462938
- Freedman SB, Williamson-Urquhart S, Farion KJ, et al. Multicenter Trial of a Combination Probiotic for Children with Gastroenteritis. N Engl J Med. 2018;379(21):2015-2026. — PubMed PMID: 30462939
- Collinson S, Deans A, Padua-Zamora A, et al. Probiotics for treating acute infectious diarrhoea. Cochrane Database Syst Rev. 2020;12(12):CD003048. — PubMed PMID: 33295643
- Cheuvart B, Neuzil KM, Steele AD, et al. Association of serum anti-rotavirus immunoglobulin A antibody seropositivity and protection against severe rotavirus gastroenteritis: analysis of clinical trials of human rotavirus vaccine. Hum Vaccin Immunother. 2014;10(2):505-511. — PubMed PMID: 24240068
- Kempe A, O'Leary ST, Cortese MM, et al. Why Aren't We Achieving High Vaccination Rates for Rotavirus Vaccine in the United States? Acad Pediatr. 2022;22(4):542-550. — PubMed PMID: 34252608
Connections
- Pediatrics
- Respiratory Syncytial Virus Bronchiolitis
- Kawasaki Disease
- Croup
- Acute Gastroenteritis
- Norovirus
- Cholera
- Zinc
- Dehydration