Alpha-Gal Syndrome & Cardiovascular Risk
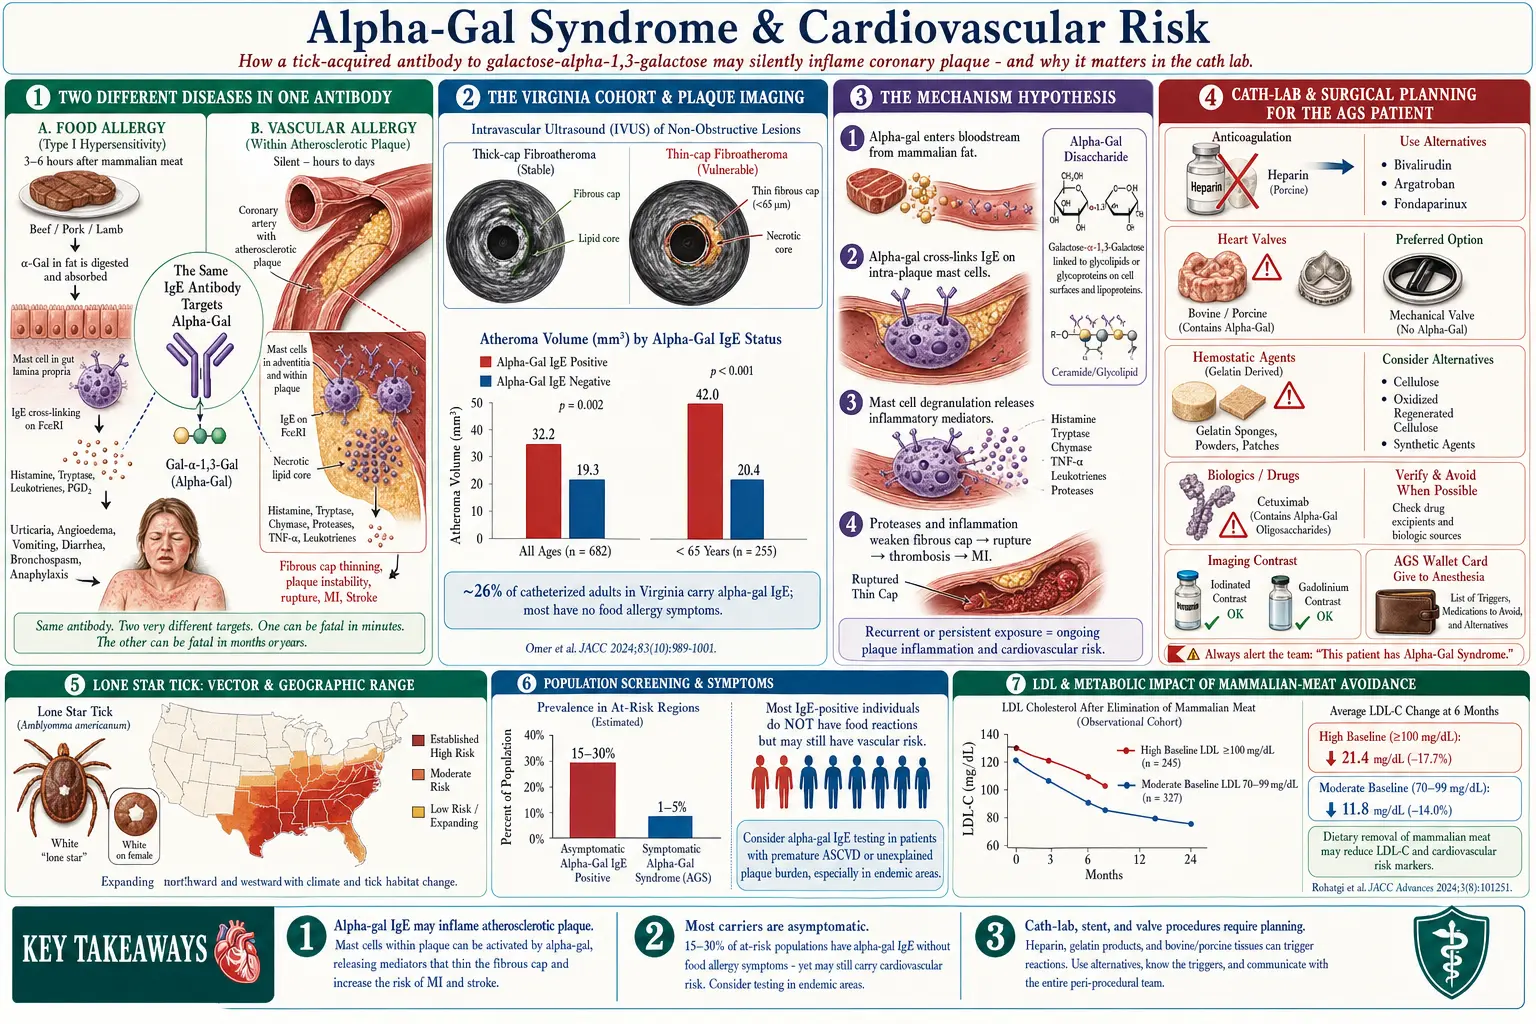
Most people with alpha-gal syndrome (AGS) think of it as a food allergy — a problem of hives, stomach cramps, and midnight anaphylaxis after a cheeseburger. But a newer line of research is asking a different and more unsettling question: does the alpha-gal antibody itself, even without food reactions, quietly damage blood vessels? A growing set of studies from the University of Virginia and other centers suggests the answer may be yes — that immunoglobulin E (IgE) antibodies against galactose-alpha-1,3-galactose may contribute to coronary artery plaque, especially in people with a lot of tick exposure.
This article sets out what is known, what is suspected, and what it means in practice for people with AGS and heart disease — or with tick exposure and a family history of early heart attacks. This is emerging research. It is not yet part of cardiology guidelines, and it does not replace standard prevention (blood pressure, low-density lipoprotein (LDL) control, not smoking, exercise). But its implications for care in a cardiac catheterization laboratory (cath lab) are already concrete for people with AGS.
Table of Contents
- Two Different Diseases in One Antibody
- The Virginia Cohort — Wilson 2018
- The Sydney Cohort — Vernon 2022 and Beyond
- The Mechanism Hypothesis
- Sensitization Without Symptoms — the Hidden Majority
- Mammalian Ingredients in Cardiac Procedures
- Bioprosthetic Valves and Other Mammalian-Derived Devices
- The Cetuximab Story — How We Learned Any of This
- Statins, Diet, and Everyday Cardiovascular Risk Management
- Alpha-Gal Testing in People With Tick Exposure and Coronary Artery Disease
- Key Research Papers
- Connections
- Featured Videos
Two Different Diseases in One Antibody
The immunoglobulin E antibody to alpha-gal is the same molecule whether it causes hives or silently targets blood vessels, but the clinical consequences seem to split into two lanes:
- The food-allergy lane. This is the classic AGS story — delayed (3–6 hour) reactions to beef, pork, lamb, dairy, gelatin. Mast cells in the gut and skin degranulate when alpha-gal-bearing fats from the meal hit the bloodstream. You get hives, gastrointestinal (GI) symptoms, anaphylaxis.
- The vascular lane. The same immunoglobulin E may also bind to mast cells that live inside the walls of coronary arteries, particularly inside developing atherosclerotic plaque. There, chronic low-grade activation — not dramatic anaphylaxis — may drive inflammation that speeds up plaque growth and instability.
The key insight is that these two lanes can be travelled independently. Some people have eye-watering food reactions and normal coronaries. Others have sky-high alpha-gal immunoglobulin E, no food symptoms at all, and unusually advanced coronary disease for their age. Researchers suspect the dose of immunoglobulin E, the subclass, the tick-exposure history, and individual mast-cell biology all determine which lane you end up in.
The Virginia Cohort — Wilson 2018
The study that opened this whole conversation came out of Charlottesville in 2018. Jeffrey Wilson, Thomas Platts-Mills, and colleagues at the University of Virginia looked at 118 adults undergoing cardiac catheterization and ran two tests on each one: intravascular ultrasound of the coronary arteries and blood levels of immunoglobulin E to alpha-gal.
The findings that grabbed attention:
- About 26% of the cohort had detectable immunoglobulin E to alpha-gal — a remarkably high figure that tracks the heavy lone-star-tick burden of central Virginia.
- Alpha-gal-sensitized patients had a higher atheroma burden (more plaque) than non-sensitized patients. In patients aged 65 or younger (79 people), intravascular ultrasound showed plaques with more fibrofatty, necrotic and calcified content and less fibrous tissue in the sensitized group — features the authors describe as less stable.
- The association was strongest in patients aged 65 or younger — exactly the group in whom conventional risk factors (age, hypertension, diabetes) explain the least.
- The researchers did not know the participants' allergic histories or diets. They assumed, from clinical experience and other cohorts, that most of the subjects had no history of symptomatic alpha-gal syndrome. If that assumption holds, the sensitization was silent, detected only because the researchers looked.
The study also checked whether the link was specific to alpha-gal. Immunoglobulin E to common inhaled allergens (dust mite, oak, timothy grass, ragweed) and to peanut showed no association with coronary artery disease. The alpha-gal link held after adjustment for sex, diabetes, hypertension, statin use and total immunoglobulin E (P=0.02).
The study was observational, not a trial. It could not prove that alpha-gal immunoglobulin E causes the extra plaque — only that the two travel together. But the correlation was strong enough, and the biology plausible enough, that Wilson's group and several others began investigating in earnest.
The Sydney Cohort — Vernon 2022 and Beyond
The first large test of the Virginia finding came from an independent cohort in Sydney, Australia. In the BioHEART cohort study, Vernon and colleagues (2022) measured alpha-gal immunoglobulin E in 1056 patients referred for computed tomography (CT) coronary angiography for suspected coronary artery disease, and in 100 selected patients with ST-segment-elevation myocardial infarction (STEMI, a major type of heart attack):
- Alpha-gal sensitization was associated with noncalcified plaque (odds ratio 1.62, 95% CI 1.04–2.53) and with obstructive coronary artery disease (odds ratio 2.05, 95% CI 1.29–3.25), independent of age, sex and traditional risk factors.
- Sensitization was found in 17% of the heart-attack patients versus 1.3% of matched healthy controls, and in 20% versus 9% when heart-attack patients were compared with matched patients with stable coronary artery disease.
- The analysis was cross-sectional: it shows that the two go together at one point in time, not that one causes the other.
Other observations discussed in the field:
- In mechanistic studies of human coronary plaque specimens, mast cells were found clustered near the necrotic core, the region where plaques rupture and cause heart attacks.
- Patients with high alpha-gal immunoglobulin E and known coronary artery disease showed elevated markers of mast-cell activation (tryptase, chymase) in some cohorts, though results have been mixed.
- In tick-heavy regions of the southeastern U.S., early-onset coronary disease rates appear to correlate with lone-star-tick density — an ecological observation, not proof, but consistent with the hypothesis.
None of this is settled. Larger prospective studies are underway. But the signal is strong enough that a handful of cardiology centers in the tick belt now quietly check alpha-gal immunoglobulin E in younger patients with unexplained coronary disease, the same way they check lipoprotein(a) (Lp(a)) or homocysteine.
The Mechanism Hypothesis
The working theory goes like this. Atherosclerotic plaques are not just piles of cholesterol — they are chronic inflammatory lesions, and mast cells have been found inside them for decades. In a person without AGS, those mast cells are relatively quiet. In a person with circulating immunoglobulin E to alpha-gal:
- Alpha-gal-bearing glycolipids enter the bloodstream from dietary meat and dairy (even in people who do not get symptomatic food reactions), or from endogenous sources that are still being worked out.
- These molecules cross-link immunoglobulin E bound to mast cells inside plaques.
- The mast cells release histamine, tryptase, chymase, tumor necrosis factor (TNF), and proteases locally into the plaque — not enough to cause systemic symptoms, but enough to digest collagen, thin the fibrous cap, and recruit more inflammatory cells.
- Over years, this low-grade inflammation accelerates plaque growth and makes plaques more prone to rupture — the event that causes a heart attack.
This is a hypothesis, not a proven pathway. But it fits what pathologists see at autopsy, what imaging shows in vivo, and what we already know about mast cells in vascular disease from unrelated work.
Sensitization Without Symptoms — the Hidden Majority
The most important and counter-intuitive finding: most people with immunoglobulin E to alpha-gal do not know they have it. They eat steak and feel fine. They have never had hives in the middle of the night. They have never seen an allergist.
In heavily tick-exposed areas of the southeastern U.S., the prevalence of sensitization to alpha-gal has been reported as high as 20%, while symptomatic AGS affects only a small fraction of that group. The ratio of silent sensitization to clinical allergy is perhaps 5:1 or 10:1.
If the vascular hypothesis is correct, this means the health impact of alpha-gal may extend far beyond the population of patients currently diagnosed with AGS. Someone in rural Virginia, Arkansas, or North Carolina with "unexplained" early coronary disease, a history of lots of outdoor work, and a few old tick bites may be carrying a relevant antibody nobody has ever tested for.
Whether to act on this possibility — to test, to modify diet, to change cardiac management — is exactly the question the research is trying to answer. For now, the honest answer is: we don't know yet.
Mammalian Ingredients in Cardiac Procedures
This part is not emerging research. This part is already a real, documented problem. If you have diagnosed AGS — especially severe AGS — certain routine cardiac procedures involve medications and devices that contain mammalian material.
Heparin. Unfractionated heparin and most low-molecular-weight heparins (enoxaparin, dalteparin) are extracted from porcine intestinal mucosa. Any cardiac cath, stent placement, open-heart surgery, or dialysis exposes you to large doses. Anaphylactic reactions to heparin in AGS patients have been reported. Alternatives exist — bivalirudin, argatroban, fondaparinux — but they are not stocked as routinely and need to be planned in advance.
Gelatin. Gelatin appears in some vaccines, in gelatin hemostatic sponges used during surgery, in certain vascular embolization products, and in capsule shells of many medications. For severe AGS, gelatin-based hemostatic agents are a known trigger.
Intravenous (IV) contrast. Most modern iodinated contrast media are synthetic and do not contain alpha-gal. However, some formulations and adjuncts have historically carried mammalian-derived components. Gadolinium magnetic resonance imaging (MRI) contrast is not a mammalian product and is generally fine from an alpha-gal perspective.
Other cath-lab drugs. Magnesium stearate (a tablet lubricant), stearic acid, certain intravenous lipid emulsions, and some anesthetic adjuvants may be mammalian-derived. Most are low-risk at the doses used, but in severe AGS, any exposure matters.
The preparation described for people with AGS before a cardiac procedure has three parts: a printed list of the person's AGS triggers for the cardiologist and the anesthesia team, so that alternatives are documented in the chart; an epinephrine auto-injector at hand; and non-mammalian anticoagulation (bivalirudin is one alternative anticoagulant) on the cath-lab shelf before the procedure starts.
Published reports also describe heparin itself being given to people with alpha-gal syndrome. A heart-surgery center that reviewed 8,819 cardiac operations from 2007 to 2019 found 17 patients with a positive alpha-gal blood test before surgery; 4 of them (24%) had a severe allergic reaction, and the authors recommend checking alpha-gal immunoglobulin E and premedicating before high-dose intravenous heparin when alpha-gal syndrome is suspected (Hawkins 2021). A 2022 case report describes heparin desensitization before heart-lung bypass in a patient with confirmed alpha-gal allergy (McRae 2022). A 2024 case report describes a 31-year-old man with alpha-gal syndrome who had no adverse reaction to heparin products during heart surgery (Taira 2024).
A 2026 case series describes three people with documented alpha-gal syndrome who had transcatheter aortic valve replacement (TAVR) with bovine or porcine valves. All three were evaluated by allergists beforehand, and two received no drug pre-treatment. Heparin given during the procedure caused no reactions in any of them, recovery showed no immediate or delayed allergic responses, and follow-up of 4 to 6 years showed no structural valve deterioration attributable to alpha-gal syndrome.
Bioprosthetic Valves and Other Mammalian-Derived Devices
This is one of the most discussed and still-unresolved questions in the AGS cardiology literature. Many replacement heart valves are bioprosthetic — made from bovine pericardium or porcine valve tissue. These tissues are fixed in glutaraldehyde, which cross-links the proteins and is thought to reduce but not necessarily eliminate alpha-gal antigenicity.
Case reports exist of bioprosthetic valves showing accelerated structural deterioration in AGS patients — calcifying, stiffening, or failing earlier than expected, possibly because of ongoing alpha-gal-directed immune attack on the foreign tissue. The reports are scattered, the denominator is unknown, and some AGS patients do perfectly well with bioprosthetic valves. But for someone with severe AGS who needs valve replacement, the decision is becoming:
- Mechanical valve — no mammalian tissue, lasts decades, but requires lifelong warfarin.
- Bioprosthetic valve — no warfarin, but may fail earlier in AGS and theoretically stokes ongoing immune activation.
- Synthetic alternatives — limited availability.
- Decellularized animal tissue — not alpha-gal-free: a 2022 laboratory study found that, despite commercial decellularization processes, alpha-gal was still present in the animal-derived products it tested, including bioprosthetic valves.
A 2022 laboratory study tested blood serum from people with AGS against common cardiac materials. The serum reacted strongly to every commercially available non-human product tested, including decellularized cardiac patch materials and bioprosthetic aortic valves, so commercial decellularization had not removed the alpha-gal. It did not react to tissue prepared from alpha-gal knockout pigs. This was a test-tube (in vitro) result; the authors write that it may have serious implications for sensitized patients having cardiac surgery, including early valve failure.
A 2026 review of human studies published from January 2014 to December 2025 found only six that met its criteria. Case reports showed rapid structural valve degeneration in some alpha-gal-sensitized patients, while other patients tolerated bioprosthetic valves around the operation and in the short term. The only study with long-term follow-up found that immunoglobulin G (IgG) responses against alpha-gal were associated with more valve degeneration and calcification. The authors call the available evidence limited and write that larger prospective studies are needed to establish cause and effect.
This is controversial and emerging. There is no guideline recommendation either way. For people with severe AGS facing valve surgery, the mechanical valve is the option that avoids mammalian tissue altogether. A human donor valve (an aortic homograft) contains no non-human tissue: a 2021 case report describes an aortic homograft implanted in a patient with aortic stenosis and documented alpha-gal allergy, and its authors call the homograft an acceptable alternative to standard biological and mechanical valves that avoids a possible allergic reaction and the need for permanent oral anticoagulation. The same caution applies to vascular grafts, patches, and tissue sealants that use bovine or porcine material.
The Cetuximab Story — How We Learned Any of This
The entire field of alpha-gal research started with a cancer drug. In the mid-2000s, patients in the southeastern U.S. receiving cetuximab (an antibody against the epidermal growth factor receptor (EGFR), used for colon cancer and head-and-neck cancer) were having anaphylactic reactions on their first infusion — something allergists were not supposed to see, because anaphylaxis normally requires prior sensitization.
Thomas Platts-Mills' group at Virginia figured out that cetuximab is produced in a mouse cell line and carries two alpha-gal residues on its heavy chain. Patients who had been bitten by lone-star ticks in the Southeast had pre-existing immunoglobulin E to alpha-gal — and cetuximab delivered the antigen directly into the vein. That was the discovery in 2008, and it was the first time anyone had connected tick bites, meat allergy, and a therapeutic antibody.
For today's AGS patients, cetuximab itself is rarely relevant unless you have the relevant cancers. The historical importance is that it is the proof-of-concept that alpha-gal immunoglobulin E can drive severe reactions to intravenous-administered mammalian material — which is precisely why the heparin, bioprosthetic valve, and hemostatic-agent questions matter.
Statins, Diet, and Everyday Cardiovascular Risk Management
Day-to-day cardiovascular risk management in AGS is mostly the same as for anyone else, with a few wrinkles:
- Statins. Statins are synthetic or fungal-derived, not mammalian. They are generally safe in AGS. The capsule or tablet inactive ingredients (magnesium stearate, lactose in some formulations) are usually fine, but patients with severe AGS have occasionally reacted to tablet fillers, and a pharmacist can supply the inactive-ingredient list of a new generic. There is no known interaction between statin therapy and alpha-gal biology.
- Diet. The AGS-mandated diet — no beef, pork, lamb, often no dairy — is in fact a cardiovascularly favorable diet. You are eating less saturated fat, less red and processed meat, and usually more plants, fish, and poultry. Some AGS patients see their low-density lipoprotein drop 20–40 points in the first year of diet compliance without any medication change. If you were considering the Mediterranean or pescatarian pattern anyway, AGS forces the issue.
- Fish, chicken, eggs. These are not mammalian and are safe both allergically and cardiovascularly.
- Ultra-processed "safe" foods. An AGS workaround can drift toward high-sodium, high-sugar packaged foods simply because they are technically mammal-free. An AGS-safe diet of chips, candy, and soda is worse for your heart than a cheeseburger.
- Blood pressure, smoking, sleep, exercise. These remain the biggest levers. None of the alpha-gal-and-atherosclerosis story changes that.
Alpha-Gal Testing in People With Tick Exposure and Coronary Artery Disease
No guideline currently recommends alpha-gal immunoglobulin E testing as part of routine cardiac workup. The profile in which the question of testing comes up:
- You live, or have lived, in the Southeast, Mid-Atlantic, or south-central U.S. (the lone-star-tick range).
- You have a history of multiple tick bites — even if none caused an obvious illness.
- You have coronary artery disease that is out of proportion to your conventional risk factors — early heart attack, extensive plaque on imaging, or unexplained recurrent events despite good low-density lipoprotein and blood pressure control.
- You have unexplained mast-cell-activation features (flushing, urticaria, gastrointestinal flares after certain foods) alongside the cardiac picture.
The test is a simple blood draw: serum immunoglobulin E to galactose-alpha-1,3-galactose, often ordered together with total immunoglobulin E and tryptase. Commercial reference laboratories run it. Cost is typically $50–150 and insurance coverage varies — a clear clinical reason in the order helps.
What you do with a positive result is an open question. At minimum, it changes cath-lab and surgical planning (heparin alternatives, mammalian-device choices). It may justify more aggressive lipid and plaque-stabilization therapy. Whether it changes diet beyond the allergen-avoidance diet is still being studied.
The bottom line is that alpha-gal and cardiovascular disease is one of the most interesting frontiers in allergy-cardiology overlap. The evidence is not yet guideline-level. But for AGS patients, it matters whether their cardiologist has heard of it — and for heart patients in the tick belt with nothing else to explain their disease, it is one more possible explanation.
Key Research Papers
Foundational and recent peer-reviewed publications on alpha-gal immunoglobulin E, atherosclerosis, plaque biology, and cardiovascular risk in AGS patients. Author names, titles, and journals are plain text; the year/volume/issue/pages link opens the DOI.
- Wilson JM, Nguyen AT, Schuyler AJ, Commins SP, Taylor AM, Platts-Mills TAE, McNamara CA. IgE to the Mammalian Oligosaccharide Galactose-α-1,3-Galactose Is Associated with Increased Atheroma Volume and Plaques with Unstable Characteristics. Arteriosclerosis, Thrombosis, and Vascular Biology. 2018;38(7):1665–1669. — doi:10.1161/ATVBAHA.118.311222
- Vernon ST, Kott KA, Hansen T, Finemore M, Baumgart KW, Bhindi R, Yang J, Hansen PS, Nicholls SJ, Celermajer DS, Ward MR, van Nunen SA, Grieve SM, Figtree GA. Immunoglobulin E Sensitization to Mammalian Oligosaccharide Galactose-α-1,3 (α-Gal) Is Associated with Noncalcified Plaque, Obstructive Coronary Artery Disease, and ST-Segment-Elevated Myocardial Infarction. Arteriosclerosis, Thrombosis, and Vascular Biology. 2022;42(3):352–361. — doi:10.1161/atvbaha.121.316878
- Commins SP, Satinover SM, Hosen J, Mozena J, Borish L, Lewis BD, Woodfolk JA, Platts-Mills TAE. Delayed Anaphylaxis, Angioedema, or Urticaria after Consumption of Red Meat in Patients with IgE Antibodies Specific for Galactose-α-1,3-Galactose. Journal of Allergy and Clinical Immunology. 2009;123(2):426–433. — doi:10.1016/j.jaci.2008.10.052
- Commins SP, James HR, Kelly LA, Pochan SL, Workman LJ, Perzanowski MS, Kocan KM, Fahy JV, Nganga LW, Ronmark E, Cooper PJ, Platts-Mills TAE. The Relevance of Tick Bites to the Production of IgE Antibodies to the Mammalian Oligosaccharide Galactose-α-1,3-Galactose. Journal of Allergy and Clinical Immunology. 2011;127(5):1286–1293.e6. — doi:10.1016/j.jaci.2011.02.019
- Chung CH, Mirakhur B, Chan E, Le QT, Berlin J, Morse M, Murphy BA, Satinover SM, Hosen J, Mauro D, Slebos RJ, Zhou Q, Gold D, Hatley T, Hicklin DJ, Platts-Mills TAE. Cetuximab-Induced Anaphylaxis and IgE Specific for Galactose-α-1,3-Galactose. New England Journal of Medicine. 2008;358(11):1109–1117. — doi:10.1056/NEJMoa074943
- Steinke JW, Platts-Mills TAE, Commins SP. The Alpha-Gal Story: Lessons Learned from Connecting the Dots. Journal of Allergy and Clinical Immunology. 2015;135(3):589–596. — doi:10.1016/j.jaci.2014.12.1947
- Wilson JM, Schuyler AJ, Workman L, Gupta M, James HR, Posthumus J, McGowan EC, Commins SP, Platts-Mills TAE. Investigation Into the α-Gal Syndrome: Characteristics of 261 Children and Adults Reporting Red Meat Allergy. Journal of Allergy and Clinical Immunology: In Practice. 2019;7(7):2348–2358.e4. — doi:10.1016/j.jaip.2019.03.031
- Hilger C, Fischer J, Wölbing F, Biedermann T. Role and Mechanism of Galactose-Alpha-1,3-Galactose in the Elicitation of Delayed Anaphylactic Reactions to Red Meat. Current Allergy and Asthma Reports. 2019;19(1):3. — doi:10.1007/s11882-019-0835-9
- Wilson JM, Erickson L, Levin M, Ailsworth SM, Commins SP, Platts-Mills TAE. Tick Bites, IgE to Galactose-α-1,3-Galactose, and Urticarial or Anaphylactic Reactions to Mammalian Meat: The Alpha-Gal Syndrome. Allergy. 2024;79(6):1440–1454. — doi:10.1111/all.16003
- Platts-Mills TAE, Li RC, Keshavarz B, Smith AR, Wilson JM. Diagnosis and Management of Patients with the α-Gal Syndrome. Journal of Allergy and Clinical Immunology: In Practice. 2020;8(1):15–23.e1. — doi:10.1016/j.jaip.2019.09.017
- Vaz-Rodrigues R, Mazuecos L, de la Fuente J. Current and Future Strategies for the Diagnosis and Treatment of the Alpha-Gal Syndrome (AGS). Journal of Asthma and Allergy. 2022;15:957–970. — doi:10.2147/JAA.S265660
- Carter MC, Ruiz-Esteves KN, Workman L, Lieberman P, Platts-Mills TAE, Metcalfe DD. Identification of Alpha-Gal Sensitivity in Patients with a Diagnosis of Idiopathic Anaphylaxis. Allergy. 2018;73(5):1131–1134. — doi:10.1111/all.13366
- Kuravi KV, Sorrells LT, Nellis JR, Rahman F, Walters AH, Matheny RG, Choudhary SK, Ayares DL, Commins SP, Bianchi JR, Turek JW. Allergic Response to Medical Products in Patients with Alpha-Gal Syndrome. Journal of Thoracic and Cardiovascular Surgery. 2022;164(6):e411–e424. — doi:10.1016/j.jtcvs.2021.03.100
- Gosden J, Ascione G, Wolf S, Turek JW, George I. Alpha-Gal Xenoantigens in Bioprosthetic Valve Recipients: Clinical Implications for Bioprosthesis Longevity. Journal of Cardiothoracic Surgery. 2026;21(1):719. — doi:10.1186/s13019-026-04270-y
- Lari K, Leghari S, Smeltz AM, Patel D, Teeter EG. Alpha-Gal Syndrome — A Case Series of Successful Transcatheter Mammalian-Derived Aortic Valve Replacements. Seminars in Cardiothoracic and Vascular Anesthesia. 2026;30(3):216–220. — doi:10.1177/10892532261460727
- Hawkins RB, Wilson JM, Mehaffey JH, Platts-Mills TAE, Ailawadi G. Safety of Intravenous Heparin for Cardiac Surgery in Patients With Alpha-Gal Syndrome. Annals of Thoracic Surgery. 2021;111(6):1991–1997. — doi:10.1016/j.athoracsur.2020.07.050
- Dang Van S, Fouquet O, Jeanneteau A, Leclere JM, Baufreton C. Aortic homograft for aortic valve replacement in patient with Alpha-Gal allergy. General Thoracic and Cardiovascular Surgery. 2021;69(11):1499–1501. — doi:10.1007/s11748-021-01684-4
- McRae AS, Tidwell WP, Patel S, Lombard FW. Heparin desensitisation prior to cardiopulmonary bypass in a patient with alpha-gal allergy. Anaesthesia Reports. 2022;10(2):e12203. — doi:10.1002/anr3.12203
- Taira K, Kanade R, Yammine M, Tannous H, Kumar S. Alpha gal syndrome, a relative not absolute contraindication to the use of bovine pericardium to close an intracardiac septal defect: a case report. Journal of Cardiothoracic Surgery. 2024;19(1):221. — doi:10.1186/s13019-024-02763-2
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: Alpha-gal and atherosclerosis
- PubMed: Alpha-gal and coronary artery disease
- PubMed: Alpha-gal IgE, mast cells, and coronary plaque
- PubMed: Alpha-gal and heparin anaphylaxis
- PubMed: Alpha-gal and bioprosthetic heart valves
- PubMed: Cetuximab and alpha-gal anaphylaxis
- PubMed: Asymptomatic alpha-gal sensitization in tick-exposed populations
- PubMed: Alpha-gal and gelatin-containing medical products
- PubMed: Lone-star tick exposure and alpha-gal epidemiology
- PubMed: Mast-cell activation and cardiovascular disease
Connections
- Pain & Allergy
- Alpha-Gal Syndrome Overview
- Natural History and Tolerance
- Cardiovascular Disease
- Tick Bite Prevention
- Mammalian Foods List
- Tick-Origin Science
- Restaurant and Travel Survival
- Cross-Reactive Medications
- Alpha-Gal Syndrome, Heart Valves and Cardiac Surgery
- Anaphylaxis Emergency Plan
- Testing and Diagnosis
- Mast Cell Activation Syndrome
- Coronary Artery Disease
- Atherosclerosis
- Hypertension
- Homocysteine
- Asthma