Central Sensitization and Nociplastic Pain
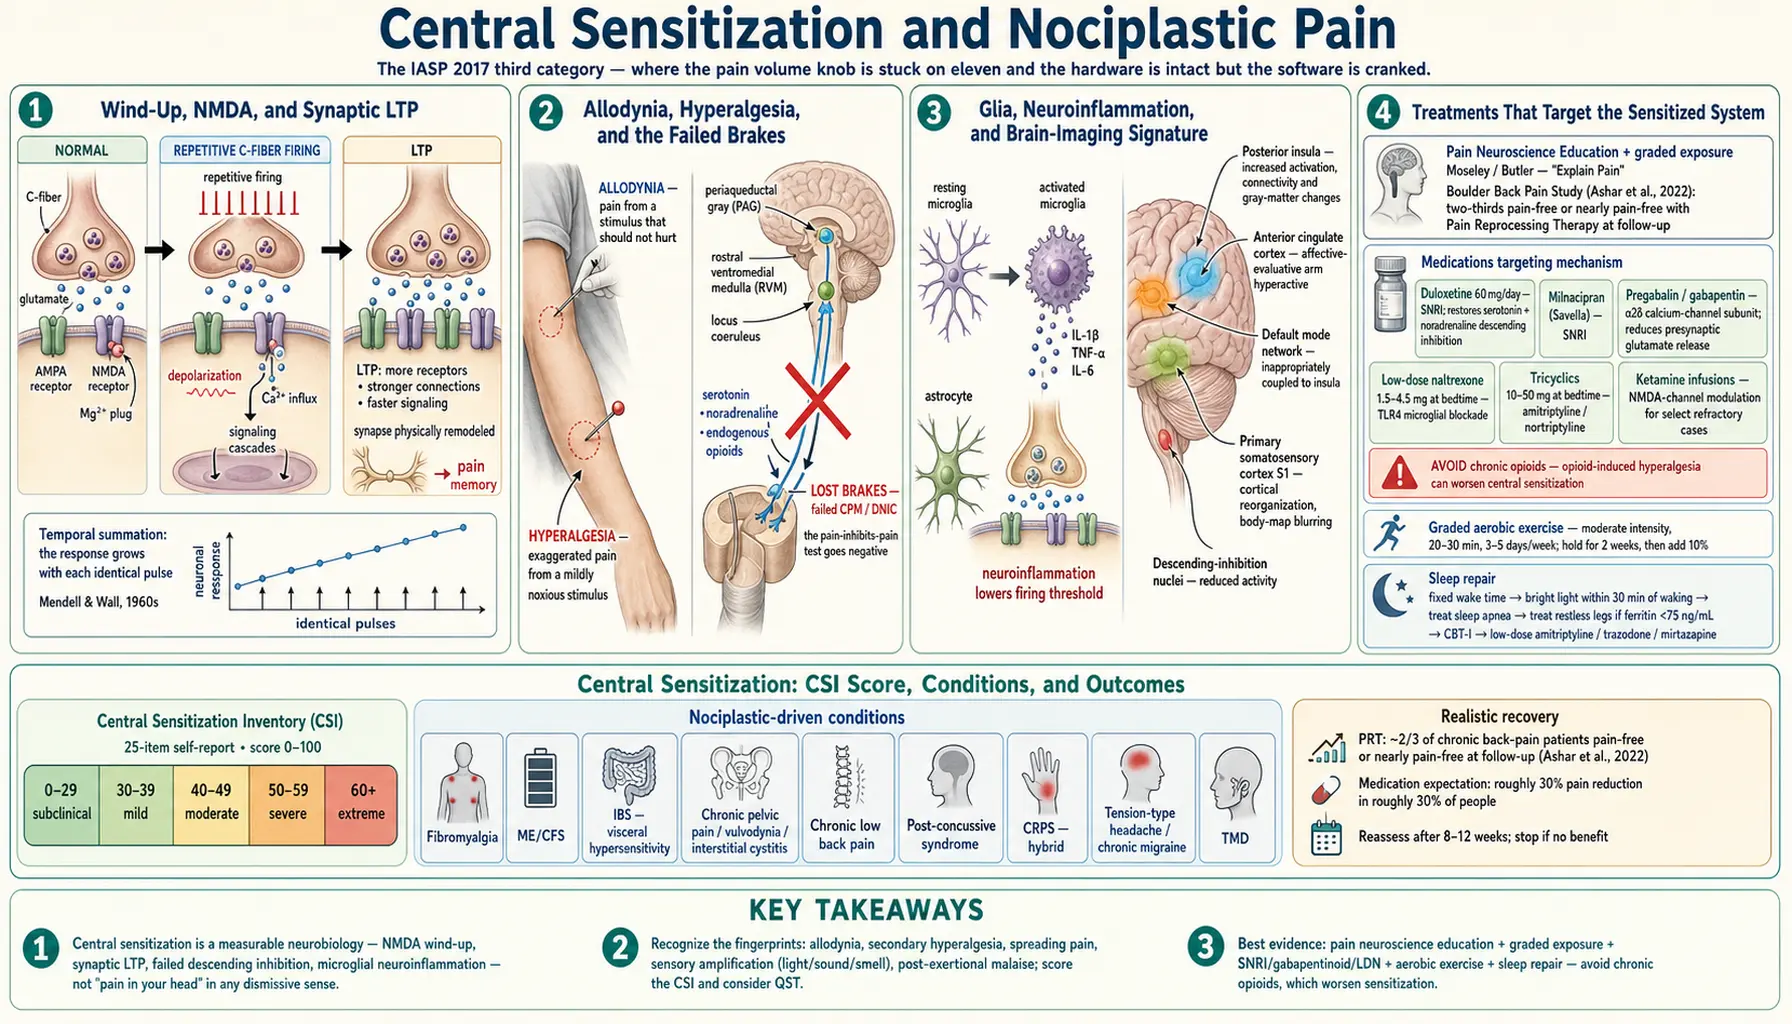
Table of Contents
- What Central Sensitization Actually Is
- Wind-Up, N-Methyl-D-Aspartate, and Temporal Summation
- Long-Term Potentiation of Pain Synapses
- Allodynia and Hyperalgesia — The Tell-Tale Signs
- Lost Brakes: Descending Inhibition and CPM
- Glia, Microglia, and Neuroinflammation
- Conditions Driven by Central Sensitization
- Measuring It: CSI and Quantitative Sensory Testing
- What the Brain Scans Show
- Treatment 1 — Pain Neuroscience Education and Graded Exposure
- Treatment 2 — Medications That Calm the System
- Treatment 3 — Aerobic Exercise and Sleep Repair
- What Recovery Actually Looks Like
- Key Research Papers
- Connections
- Featured Videos
What Central Sensitization Actually Is
If you have been told your pain is "real but not from tissue damage," or that imaging keeps coming back unremarkable while you feel like you are on fire, you have probably run into the concept of central sensitization. This is not a vague hand-wave. It is a specific, well-documented change in how your spinal cord and brain process signals. The International Association for the Study of Pain (IASP) gave this kind of pain its own name in 2017: nociplastic pain. It sits alongside the two older categories — nociceptive pain (tissue injury) and neuropathic pain (nerve injury) — as a third mechanism.
The short version: your nervous system has learned to amplify danger signals. Inputs that used to be ignored or filtered out now get forwarded to conscious awareness as pain. Inputs that used to be mildly uncomfortable now feel excruciating. The hardware is intact. The software is cranked to maximum gain.
This matters because the treatments that work for a pulled muscle or a pinched nerve usually do not work here. No amount of anti-inflammatory medication fixes a volume knob that is stuck on eleven. Different strategies are needed — ones that target the processing itself.
Two 2021 papers set out the current picture. Kosek and colleagues published clinical criteria and a grading system for chronic nociplastic pain affecting the muscles, joints and bones (the musculoskeletal system). A review in The Lancet by Fitzcharles and colleagues described nociplastic pain as pain in several places that is more widespread or more intense than the amount of tissue or nerve damage would explain, often with fatigue and sleep, memory and mood problems. It can occur on its own, as in fibromyalgia or tension-type headache, or mixed with other kinds of pain, as can happen in chronic low back pain. The review notes that it responds less to treatments aimed at the body's tissues, such as anti-inflammatory drugs, opioids, surgery or injections.
Wind-Up, N-Methyl-D-Aspartate, and Temporal Summation
The foundational phenomenon in central sensitization is called wind-up, first described by Lorne Mendell and Patrick Wall in the 1960s. Here is how it works.
When a C-fiber (a small, slow pain nerve) fires repeatedly at a steady intensity — say, once per second — the second-order neuron in the dorsal horn of your spinal cord does not just respond steadily. Its response grows with each pulse. The tenth identical input produces a far larger signal than the first. This is temporal summation.
The molecular culprit is the N-methyl-D-aspartate (NMDA) receptor. Under normal conditions, N-methyl-D-aspartate receptors in the dorsal horn are plugged by a magnesium ion and largely silent. Ordinary pain signaling runs through AMPA receptors. But if C-fibers fire fast enough and long enough, the neuron depolarizes strongly enough to kick the magnesium out of the N-methyl-D-aspartate channel. Calcium floods in. Signaling cascades switch on. The neuron becomes hyper-responsive — not just for the duration of the input but for minutes, hours, and eventually, if the barrage continues, for months or years.
This is why chronic pain states often begin with a legitimate injury — surgery, a car accident, an infection, a bout of shingles — that lasts long enough to wind the spinal cord up. By the time the original tissue heals, the dorsal horn is stuck in amplification mode. The pain persists without the injury.
Long-Term Potentiation of Pain Synapses
Wind-up is the acute version. The chronic version borrows its machinery from the same brain system that stores memories: long-term potentiation (LTP). Pain-carrying synapses in the dorsal horn can undergo the same strengthening that happens when you learn a phone number or a piano piece. Once LTP sets in, the synapse is physically remodeled — more receptors, stronger connections, faster signaling.
In other words, your spinal cord has learned to be in pain. The learning is involuntary and nobody chose it, but it is a genuine form of neural plasticity. The good news hidden inside this grim fact: plasticity runs in both directions. What was learned can, with effort, be unlearned. That is the entire premise behind modern nociplastic-pain treatment.
Allodynia and Hyperalgesia — The Tell-Tale Signs
Two words describe the clinical face of central sensitization, and if you learn to recognize them in your own experience you will understand what your nervous system is doing.
- Allodynia — pain from a stimulus that should not hurt at all. A T-shirt seam feels like sandpaper. A gentle hug feels like bruising. A breeze across your arm burns. The sensory input is normal; the output is pain.
- Hyperalgesia — exaggerated pain from a stimulus that should hurt a little. A pinprick that would rate a 2/10 in most people rates a 7/10. A sore muscle feels like a torn one. The input is painful; the output is disproportionate.
Both can be primary (at the original injury site) or secondary (spreading outward into uninjured skin). Secondary hyperalgesia — a ring of tenderness around a wound, or tender spots far from any obvious cause — is the clearest clinical fingerprint of central sensitization. The original nerves in those tender zones are perfectly healthy. The spinal cord is the problem.
Other features that point toward a centralized pain picture:
- Pain that spreads over time rather than staying put.
- Pain that is worse with stress, poor sleep, and infections, and better with calm and rest.
- Non-painful amplifications: loud noises feel louder, bright lights feel brighter, smells feel stronger, emotions feel bigger. The whole sensory system is turned up, not just pain.
- Post-exertional malaise — mild activity today flares pain and fatigue for days.
- Pain that outlasts any plausible tissue cause.
Lost Brakes: Descending Inhibition and CPM
Your brain has a pain-damping system built in. Nuclei in the brainstem — the periaqueductal gray, the rostral ventromedial medulla, and the locus coeruleus — send fibers down the spinal cord that release serotonin, noradrenaline, and endogenous opioids onto dorsal-horn neurons. This is the descending inhibitory system. In healthy people, it filters a constant stream of noise out of the pain signal before it ever reaches consciousness.
In chronic nociplastic pain, these brakes fail. The classic way to test this in a clinic is a conditioned pain modulation (CPM) protocol, historically called diffuse noxious inhibitory control (DNIC). The examiner applies a mildly painful stimulus (say, a pressure on your thumb) and measures your threshold. Then they add a second, stronger noxious stimulus somewhere else on the body (often a cold-water bath for the other hand). In a healthy nervous system, the distant pain raises your thumb threshold — pain inhibits pain. In fibromyalgia, chronic low back pain, and many other central-sensitization states, CPM is weak or absent. The brakes are gone.
This finding matters practically because a medication that acts on descending inhibition — a serotonin-noradrenaline reuptake inhibitor such as duloxetine — is working at exactly the system that has failed. You are putting the brakes back in.
Glia, Microglia, and Neuroinflammation
For most of the twentieth century, pain research was a story about neurons. The last twenty years have rewritten the story. The glial cells — microglia, astrocytes — that were thought to be passive scaffolding turn out to be active participants.
When a nerve injury or prolonged nociceptive barrage hits the spinal cord, microglia switch on. They change shape, multiply, and start dumping inflammatory cytokines (interleukin-1 (IL-1) beta, tumor necrosis factor-alpha, interleukin-6 (IL-6)) and chemokines into the synaptic cleft. These substances lower the firing threshold of nearby pain neurons, pull glutamate receptors to the surface, and strip away the mechanisms that normally shut signaling off. Astrocytes follow, often with a slower but longer-lasting inflammatory response.
This is why chronic pain has an inflammatory signature even when nothing in the peripheral tissue is inflamed. The inflammation is in the central nervous system itself — a process sometimes called neuroinflammation. It is also why drugs that target glial activation, such as low-dose naltrexone (LDN, typically 1.5–4.5 mg at bedtime), can produce pain relief that makes no sense if you are thinking only about neurons. Low dose naltrexone is believed to work in part by blocking toll-like receptor 4 (TLR4) on microglia, quieting the glial contribution to the sensitized state.
Conditions Driven by Central Sensitization
Once you have the framework, a long list of otherwise puzzling syndromes makes sense. They are not random. They share a mechanism.
- Fibromyalgia — the prototype. Widespread pain, fatigue, sleep disturbance, cognitive fog. Central sensitization is now considered the core mechanism. See fibromyalgia and the deep dive on central sensitization in fibromyalgia.
- Myalgic encephalomyelitis / chronic fatigue syndrome — overlaps massively with fibromyalgia and features post-exertional malaise, sensory amplification, and sleep fragmentation. See myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS).
- Irritable bowel syndrome — visceral hypersensitivity is the gut version of central sensitization. A balloon inflated to a modest volume in the rectum triggers severe pain in irritable bowel syndrome (IBS) patients but not in controls. See visceral hypersensitivity and the brain-gut axis.
- Chronic pelvic pain, vulvodynia, interstitial cystitis — pelvic versions, often layered with pelvic-floor muscle guarding. See pelvic-floor therapy and central sensitization.
- Chronic low back pain — the majority of cases that outlast three months have a central-sensitization component, even when structural findings exist. See chronic low back pain.
- Post-concussive syndrome and chronic whiplash — a significant fraction of people whose symptoms fail to resolve over months have developed central sensitization on top of whatever initial injury occurred.
- Complex regional pain syndrome — hybrid, with neuropathic and nociplastic features. See CRPS.
- Tension-type headache and chronic migraine — central sensitization of trigeminal pathways is a major mechanism.
- Temporomandibular disorders — chronic TMD patients demonstrate reduced CPM and lowered pain thresholds across the whole body, not only in the jaw.
This is not a diagnosis of exclusion and it is not code for "we give up." It is a positive, mechanism-based label that points to specific treatments.
Measuring It: CSI and Quantitative Sensory Testing
Two tools are most commonly used to quantify central sensitization in clinic and research.
The Central Sensitization Inventory (CSI). A 25-item self-report questionnaire validated by Neblett and colleagues. Each item asks how often you experience symptoms such as widespread pain, fatigue, non-restorative sleep, heightened sensitivity to light or sound, jaw pain, memory problems, restless legs, and stress-triggered flare-ups. Scores range 0–100. Cutoffs:
- 0–29: subclinical
- 30–39: mild
- 40–49: moderate
- 50–59: severe
- 60+: extreme
A score above 40 on the CSI — particularly in someone with widespread pain and normal imaging — is a strong signal that central sensitization is a driver of the clinical picture. It does not replace a clinical evaluation, but it gives you and your clinician a number to track over time.
Quantitative sensory testing (QST). A structured set of bedside tests that a trained provider (often a physical therapist or pain specialist) can run in about thirty minutes. Typical components:
- Pressure pain thresholds using an algometer — measured at the site of pain and at distant "control" sites. In central sensitization, both are lowered.
- Temporal summation — repeated pinpricks at a steady intensity. A growing pain rating across the series indicates dorsal-horn wind-up.
- Conditioned pain modulation (CPM) — the pain-inhibits-pain test described above. Weak or absent CPM indicates failed descending inhibition.
- Thermal thresholds — cold and heat detection and pain thresholds on a controlled probe.
QST is not available at every clinic, but academic pain centers and many research-oriented physical-therapy practices offer it. You do not need a positive QST to get treatment, but it can be useful for patients whose pain has been dismissed — it provides objective evidence that something is wrong with how the nervous system processes input.
What the Brain Scans Show
Functional magnetic resonance imaging (MRI) and related imaging have mapped central sensitization onto specific brain networks. You will not get this imaging clinically — it is research-grade — but knowing what it shows helps you understand your own experience.
- Insula — the interoceptive hub that integrates signals from the body. The posterior insula, in particular, shows increased activation and altered connectivity in fibromyalgia and chronic pain states. Patients have more insular gray-matter changes, and those changes correlate with symptom severity.
- Anterior cingulate cortex — the affective-evaluative arm of pain ("how bad is this? do I care?") Hyperactive in chronic pain.
- Default mode network (DMN) — the set of regions active when you are at rest, ruminating, mind-wandering. In chronic pain, the DMN intrudes into pain processing even during task performance. The insula becomes inappropriately coupled to the DMN, which may be the neural basis for pain-preoccupation and rumination.
- Primary somatosensory cortex (S1) — shows reorganization, with the cortical representation of painful body areas blurring into neighboring zones. This cortical blurring is thought to underlie some of the spread of pain across body regions.
- Descending-inhibition nuclei — reduced activity in the periaqueductal gray and rostral ventromedial medulla mirrors the weak CPM seen behaviorally.
The crucial point: none of these findings means your pain is "in your head" in the dismissive sense. The changes are physical, measurable, and located in the same nervous system that registers every other bodily signal. Pain is always a brain output, whether the driver is a broken bone or a sensitized dorsal horn.
Treatment 1 — Pain Neuroscience Education and Graded Exposure
One of the most studied interventions for nociplastic pain is, counter-intuitively, education. Not the "drink more water and stretch" kind. Pain Neuroscience Education (PNE, sometimes called Explain Pain) teaches patients the biology of central sensitization — N-methyl-D-aspartate wind-up, glial activation, failed descending inhibition, LTP. The working premise: understanding that your nervous system has learned to amplify danger signals, and that learning can be unlearned, measurably reduces pain and disability.
A 2011 systematic review by Louw, Diener, Butler, and Puentedura gathered 8 studies of neuroscience education in chronic musculoskeletal pain (6 high-quality randomized trials, 1 pseudo-randomized trial, and 1 comparative study; 401 people in all). The studies differed too much to be pooled statistically, but the authors judged the evidence compelling that neuroscience education may reduce pain ratings, increase function, address catastrophizing, and improve movement. This article itself is, in a small way, doing PNE.
Once you understand the mechanism, the behavioral corollary is graded exposure — gradually and systematically returning to movements and activities that have become pain-associated. A classic fear-avoidance cycle: bending hurt once, so bending became scary, so bending was avoided, so the nervous system flagged bending as dangerous, so bending hurt more when tried. Graded exposure reverses this in tiny, planned increments. The body learns that bending is safe. The sensitized system turns its volume down.
This is the foundation for a family of modern talk-based therapies, including Pain Reprocessing Therapy and PNE. The Boulder Back Pain Study (Ashar et al., 2022) tested Pain Reprocessing Therapy (PRT) — 1 telehealth session with a physician and 8 psychological sessions over 4 weeks — in 151 adults whose back pain was low to moderate at the start (an average of 4.1 out of 10). Right after treatment, 66% of the PRT group (33 of 50) were pain-free or nearly pain-free (0 or 1 out of 10), compared with 20% of those given a placebo saline injection and 10% of those on usual care. The gains largely held at one year: average pain was 1.5 out of 10 with PRT, 2.8 with placebo, and 3.0 with usual care.
Treatment 2 — Medications That Calm the System
Medications that work in nociplastic pain target the specific mechanisms above. None are miracle drugs. A typical result is roughly 30% pain reduction in roughly 30% of people, and eight to twelve weeks is the usual window for judging whether a medicine is helping.
- Duloxetine. Serotonin-norepinephrine reuptake inhibitor (SNRI) that boosts serotonin and noradrenaline, the main descending-inhibition neurotransmitters. U.S. Food and Drug Administration-approved for fibromyalgia, diabetic neuropathy, and chronic musculoskeletal pain. Typical target dose 60 mg/day, sometimes 120 mg. It is usually started low (20–30 mg) for a week to lessen nausea.
- Milnacipran. Another serotonin-norepinephrine reuptake inhibitor with a stronger noradrenaline profile, U.S. Food and Drug Administration-approved specifically for fibromyalgia. Often tried when duloxetine fails.
- Pregabalin and gabapentin. Bind the alpha-2-delta subunit of calcium channels in presynaptic dorsal-horn terminals, reducing glutamate release onto the sensitized second-order neuron. Pregabalin is U.S. Food and Drug Administration-approved for fibromyalgia; gabapentin is used off-label. Common side effects include sedation, weight gain, and edema (fluid swelling).
- Low-dose naltrexone. Typically 1.5–4.5 mg at bedtime — a tiny fraction of the addiction-medicine dose. Proposed to act by blocking TLR4 on microglia, calming neuroinflammation. Small randomized controlled trials (RCTs) in fibromyalgia from the Younger lab at Stanford reported pain reduction with few side effects: in a 2013 crossover trial of 31 women taking 4.5 mg a day, pain fell 28.8% on low-dose naltrexone and 18.0% on placebo. The largest trial so far, published in 2024 (99 women in Denmark, 6 mg a day for 12 weeks), did not find it better than placebo for pain: pain fell 1.3 points on naltrexone and 0.9 points on placebo (on a 0–10 scale), a difference that was not statistically significant. Its authors saw signs of a possible benefit for the memory problems that come with fibromyalgia and called for further trials. It is compounded — no standard pharmacy stocks the microdose.
- Tricyclic antidepressants (amitriptyline, nortriptyline) at low bedtime doses (10–50 mg). Older, cheap, effective in fibromyalgia and chronic tension headache, work partly through descending inhibition and partly through sleep depth.
- N-methyl-D-aspartate-channel modulators — ketamine infusions and, less commonly, dextromethorphan or memantine. Directly target the receptor at the heart of wind-up. Ketamine is effective for select refractory cases but requires specialty infusion centers and has limited durability.
- Sublingual (under-the-tongue) cyclobenzaprine. In August 2025 the U.S. Food and Drug Administration approved a bedtime under-the-tongue form of cyclobenzaprine for fibromyalgia, which a 2026 review describes as the first new medicine approved for fibromyalgia in more than 15 years. In two phase 3 trials, people took 2.8 mg nightly for 2 weeks and then 5.6 mg for 12 weeks. Daily pain (0–10 scale) fell 1.9 points versus 1.5 on placebo in the first trial (503 patients) and 1.8 versus 1.2 in the second. The most common side effect was numbness in the mouth (17.3% and 23.4% of people taking it, against 0.4% on placebo). The review proposes that it works mainly through receptors involved in central pain processing and sleep, rather than by relaxing muscles.
What does not work well in pure nociplastic pain: nonsteroidal anti-inflammatory drugs (NSAIDs), acetaminophen beyond minor benefit, and chronic opioids. Opioids are particularly risky in this population because they can induce their own form of central sensitization (opioid-induced hyperalgesia), worsening the underlying problem. See opioids for chronic non-cancer pain for the full discussion.
Treatment 3 — Aerobic Exercise and Sleep Repair
Two non-drug interventions have the best evidence base in nociplastic pain, and they are both hard to do when you feel terrible.
For fibromyalgia, the European League Against Rheumatism (EULAR) revised recommendations (2016, based on 107 systematic reviews and meta-analyses) found exercise was the only therapy with a "strong for" recommendation. The other treatments it assessed, including psychological therapies and medicines, were rated "weak for", and the panel noted that the size of effect for most treatments is relatively modest. It suggested patient education and non-drug therapies as the first stage of care.
Graded aerobic exercise. In fibromyalgia and chronic widespread pain, aerobic training — walking, cycling, swimming, water aerobics — performed at moderate intensity for 20–30 minutes, three to five days a week, reliably reduces pain and improves function. The key word is graded. Programs typically start at a level a person can sustain one day without a flare the next, hold it for two weeks, then add about 10%. After a crash, the usual step is back to the last tolerated level, held for longer. Many patients start at five minutes of slow walking. The goal is to teach the nervous system that movement is safe, and the dose that accomplishes this grows over months. See sleep, exercise, and lifestyle.
Sleep repair. Non-restorative sleep is both a symptom of central sensitization and a driver of it. A single night of disrupted sleep measurably lowers pain thresholds in healthy controls the next day. Chronic sleep fragmentation inflames microglia and feeds the sensitization loop. Sleep programs commonly list these priorities, in order of impact:
- A fixed wake time, even on weekends.
- Bright light in the eyes within thirty minutes of waking.
- No screens or alcohol in the two hours before bed.
- Treatment of obstructive sleep apnea if present — a sleep study can detect it in people who snore, gasp, or wake unrefreshed.
- Treatment of restless legs (ferritin below 75 ng/mL is a common missed cause; iron repletion often fixes it).
- Low-dose amitriptyline, trazodone, or mirtazapine for sleep consolidation if lifestyle measures fail.
Cognitive behavioral therapy for insomnia (CBT-I) is a structured, non-drug treatment for long-term insomnia. Most major U.S. cities now have CBT-I providers, and several free apps deliver the program — for example the CBT-i Coach app, made by the U.S. Department of Veterans Affairs for insomnia.
What Recovery Actually Looks Like
Recovery from central sensitization is not a linear curve. It is a series of two-steps-forward, one-step-back oscillations over months to years. A few realistic points that most patients wish they had been told early:
- Full remission is possible. Studies of PRT and graded exposure show a substantial minority of patients become essentially pain-free. Many more reach a level where pain is present but no longer dominates life.
- Flares do not mean failure. A sensitized nervous system responds to stress, illness, and life events by re-amplifying for days or weeks. That is the system doing what it learned to do. It does not erase progress.
- Checking in on pain less often makes it better. Constant body scanning feeds the default mode network's intrusion into pain processing. Setting your phone down, returning to work and hobbies, and letting attention drift elsewhere are treatments.
- Multiple therapies together beat any single one. Medication + aerobic exercise + sleep repair + PNE + graded exposure outperforms any one component. Most pain clinics that publish good outcomes run exactly this stack.
- You are not imagining it and you did not cause it. The nervous system changed. Nervous systems can change back. That is the whole story.
Key Research Papers
- Woolf CJ. Central sensitization: implications for the diagnosis and treatment of pain. Pain. 2011;152(3 Suppl):S2–S15. — doi:10.1016/j.pain.2010.09.030
- Kosek E, Clauw D, Nijs J, Baron R, Gilron I, Harris RE, Mico JA, Rice ASC, Sterling M. Chronic nociplastic pain affecting the musculoskeletal system: clinical criteria and grading system. Pain. 2021;162(11):2629-2634. — doi:10.1097/j.pain.0000000000002324 · PubMed PMID: 33974577
- Fitzcharles MA, Cohen SP, Clauw DJ, Littlejohn G, Usui C, Häuser W. Nociplastic pain: towards an understanding of prevalent pain conditions. Lancet. 2021;397(10289):2098-2110. — doi:10.1016/S0140-6736(21)00392-5 · PubMed PMID: 34062144
- Ashar YK, et al. Effect of Pain Reprocessing Therapy vs placebo and usual care on chronic back pain: a randomized clinical trial. JAMA Psychiatry. 2022. — doi:10.1001/jamapsychiatry.2021.2669
- Neblett R, et al. The Central Sensitization Inventory (CSI): establishing clinically significant values. J Pain. 2013. — doi:10.1016/j.jpain.2012.11.012
- Younger J, Noor N, McCue R, Mackey S. Low-dose naltrexone for the treatment of fibromyalgia: findings of a small, randomized, double-blind, placebo-controlled, counterbalanced, crossover trial assessing daily pain levels. Arthritis Rheum. 2013;65(2):529-38. — doi:10.1002/art.37734 · PubMed PMID: 23359310
- Ji RR, Nackley A, Huh Y, Terrando N, Maixner W. Neuroinflammation and central sensitization in chronic and widespread pain. Anesthesiology. 2018. — doi:10.1097/aln.0000000000002130
- Louw A, Diener I, Butler DS, Puentedura EJ. The effect of neuroscience education on pain, disability, anxiety, and stress in chronic musculoskeletal pain. Arch Phys Med Rehabil. 2011. — doi:10.1016/j.apmr.2011.07.198
- Macfarlane GJ, Kronisch C, Dean LE, Atzeni F, Häuser W, Fluß E, et al. EULAR revised recommendations for the management of fibromyalgia. Ann Rheum Dis. 2017;76(2):318-328. — doi:10.1136/annrheumdis-2016-209724 · PubMed PMID: 27377815
- Due Bruun K, Christensen R, Amris K, Vaegter HB, Blichfeldt-Eckhardt MR, Bye-Møller L, Holsgaard-Larsen A, Toft P. Naltrexone 6 mg once daily versus placebo in women with fibromyalgia: a randomised, double-blind, placebo-controlled trial. Lancet Rheumatol. 2024;6(1):e31-e39. — doi:10.1016/S2665-9913(23)00278-3 · PubMed PMID: 38258677
- Lederman S, Arnold LM, Vaughn B, Kelley M, Sullivan GM. Efficacy and Safety of Sublingual Cyclobenzaprine for the Treatment of Fibromyalgia: Results From a Randomized, Double-Blind, Placebo-Controlled Trial. Arthritis Care Res (Hoboken). 2023;75(11):2359-2368. — doi:10.1002/acr.25142 · PubMed PMID: 37165930
- Lederman S, Arnold LM, Vaughn B, Engels JM, Kelley M, Sullivan GM. Pain relief by targeting nonrestorative sleep in fibromyalgia: a phase 3 randomized trial of bedtime sublingual cyclobenzaprine. Pain Med. 2026;27(1):86-94. — doi:10.1093/pm/pnaf089 · PubMed PMID: 40627411
- Abd-Elsayed A, Knezic A, Asfour J, Dewan P, Hasoon J, Reilly M. Sublingual Cyclobenzaprine for Fibromyalgia: Pharmacokinetic Rationale, Clinical Evidence, and Place in Therapy. Curr Pain Headache Rep. 2026;30(1):89. — doi:10.1007/s11916-026-01527-y · PubMed PMID: 42479282
PubMed Topic Searches
For further reading, these PubMed topic searches return current peer-reviewed work on the mechanisms and management of central sensitization and nociplastic pain:
- PubMed: Central sensitization and chronic pain
- PubMed: Nociplastic pain — clinical criteria and mechanisms
- PubMed: NMDA wind-up and dorsal-horn temporal summation
- PubMed: Conditioned pain modulation in fibromyalgia
- PubMed: Microglia, neuroinflammation, and chronic pain
- PubMed: Central Sensitization Inventory validation studies
- PubMed: Pain neuroscience education outcomes
- PubMed: Low-dose naltrexone in fibromyalgia
- PubMed: Duloxetine and milnacipran in centralized pain
- PubMed: Default mode network and chronic pain
Connections
- Pain & Allergy
- Chronic Low Back Pain
- Fibromyalgia
- Complex Regional Pain Syndrome
- Pain Reprocessing Therapy
- Opioids for Chronic Pain
- Chronic Fatigue Syndrome
- Non-Opioid Medications
- Sleep and Lifestyle for Chronic Pain
- Central Sensitization Explained
- Pelvic Floor Therapy and Central Sensitization
- Visceral Hypersensitivity and Brain-Gut Axis
- Chronic Pain Overview
- Interventional Pain
- Pain Mechanisms
- Peripheral Neuropathy
- Migraine