Subacute Combined Degeneration of the Spinal Cord
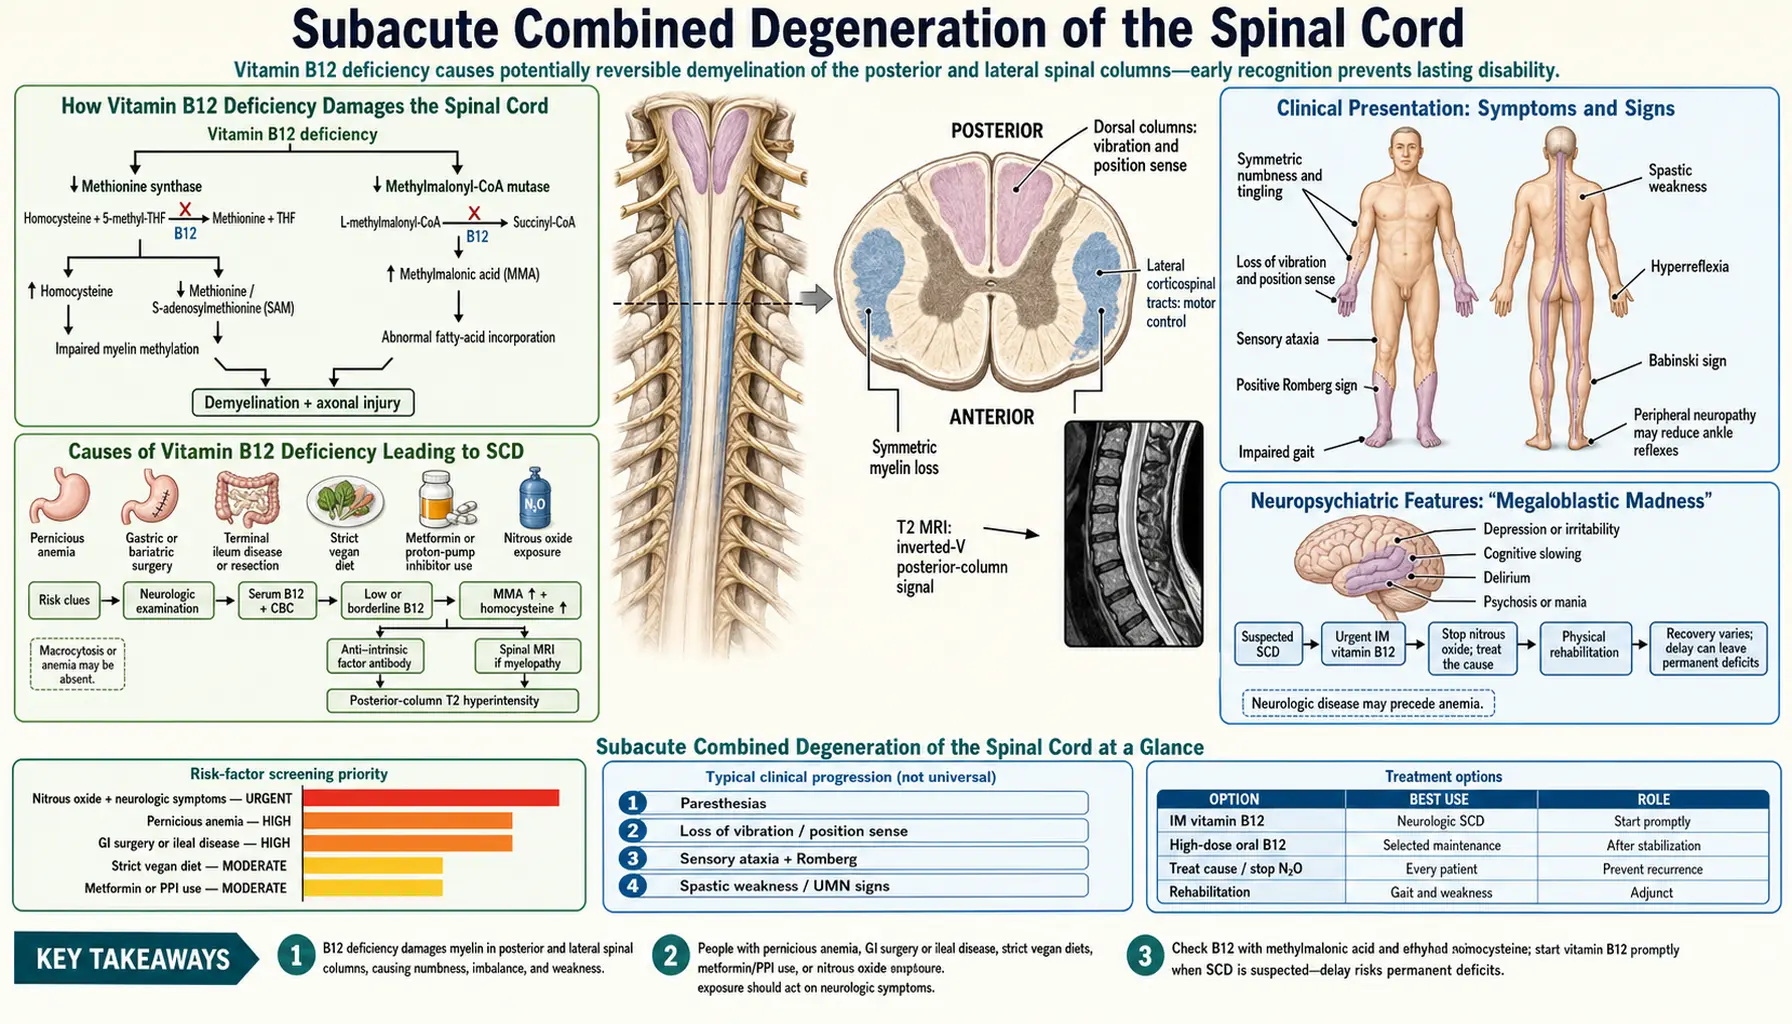
Subacute Combined Degeneration (SCD) of the spinal cord is a progressive neurological disorder caused by vitamin B12 (cobalamin) deficiency, affecting both the posterior columns — the cables that carry vibration sense and proprioception (body position awareness) upward to the brain — and the lateral corticospinal tracts, which carry motor commands downward. The result is a distinctive combination of sensory ataxia (stumbling from lost position sense), paresthesias, and progressive spastic weakness that can be confused with multiple sclerosis or other spinal cord diseases. What makes SCD particularly treacherous is that the neurological damage can begin before any anemia appears, and even a "normal" serum B12 level does not guarantee adequate tissue levels. Caught early and treated with intramuscular cobalamin, SCD can be stopped and partially reversed. Caught late, the damage becomes permanent.
Interactive Visualization Vitamin B12’s Impossible Journey Five stages, two carrier proteins, a working stomach and one specific stretch of gut. Break any link — a proton pump inhibitor (PPI), metformin, pernicious anaemia — and absorption collapses. Launch →
Table of Contents
- How Vitamin B12 Deficiency Damages the Spinal Cord
- Clinical Presentation: Symptoms and Signs
- Causes of Vitamin B12 Deficiency Leading to SCD
- Neuropsychiatric Features: "Megaloblastic Madness"
- How Diagnosis Works: Tests and What They Show
- Nitrous Oxide: A Special and Increasingly Common Cause
- Treatment: Intramuscular B12 and Prognosis
- Prevention and Monitoring At-Risk Populations
- Key Research Papers
- Connections
- Featured Videos
How Vitamin B12 Deficiency Damages the Spinal Cord
Vitamin B12 is a required cofactor for two essential enzymes that sit at the heart of myelin production and maintenance:
- Methionine synthase: converts homocysteine to methionine (requiring both B12 and folate as cofactors). Methionine is then converted to S-adenosylmethionine (SAM), the universal methyl donor used throughout the body — including for methylating myelin basic protein and phospholipids in nerve sheaths.
- Methylmalonyl-CoA mutase: converts methylmalonyl-CoA to succinyl-CoA, a step critical for fatty acid metabolism in nerve sheaths and for the biosynthesis of myelin lipids.
When B12 is deficient, both pathways fail simultaneously. Defective SAM production impairs the methylation reactions that maintain myelin integrity. At the same time, methylmalonyl-CoA accumulates and is converted into methylmalonic acid (MMA), which is directly toxic to myelin sheaths. The combined result is progressive demyelination — the stripping of the insulating myelin coat from nerve axons.
The term "combined" in SCD refers to the simultaneous demyelination of two distinct spinal cord tracts:
- Posterior (dorsal) columns: carry proprioception (joint position sense), vibration, and fine touch upward to the brain. Loss of these signals produces sensory ataxia — the inability to know where your feet are without looking.
- Lateral corticospinal tracts: carry upper motor neuron (UMN) commands downward from the brain to the limbs. Demyelination here causes spastic weakness, brisk reflexes, and a positive Babinski sign.
A third complication: peripheral nerves are also affected, adding lower motor neuron (LMN) signs — including areflexia and muscle wasting — that can paradoxically coexist with the UMN signs from spinal cord involvement. This mix of UMN and LMN findings in the same limb is a diagnostic clue pointing toward SCD rather than a pure spinal cord or peripheral nerve disease.
The cervical and thoracic spinal cord are the most affected segments. In advanced cases, demyelination extends to the optic nerves and cerebral white matter. Because the liver stores 3–5 years' worth of B12, deficiency develops slowly — which explains why SCD often has an insidious, gradually worsening onset over many months before patients or physicians recognize what is happening.
Clinical Presentation: Symptoms and Signs
SCD typically begins insidiously. Patients often attribute the earliest symptoms to aging, fatigue, or "just getting a bit unsteady." By the time a physician sees them, symptoms have often been present for months.
Early symptoms — posterior column involvement:
- Symmetric paresthesias: tingling, "electric shocks," pins and needles — characteristically in a stocking-glove pattern beginning in the feet and hands simultaneously.
- Loss of vibration sense: tested with a 128 Hz tuning fork at the big toe; often the earliest objective finding on examination.
- Loss of proprioception (joint position sense): patients cannot tell which direction a toe is being moved with eyes closed.
- Positive Romberg test: patient sways or falls when standing with feet together and eyes closed — a hallmark of posterior column dysfunction.
- Sensory ataxia: wide-based, unsteady gait that worsens dramatically in the dark or with eyes closed (because vision can no longer compensate for lost proprioception).
- Lhermitte's sign: a brief electric shock sensation radiating down the spine or into the limbs when the neck is flexed. Not specific for SCD but signals posterior column involvement.
Later symptoms — lateral corticospinal tract involvement:
- Progressive leg weakness, initially subtle and then frankly spastic.
- UMN signs: hyperreflexia, sustained clonus, and a positive Babinski sign (the big toe extends upward on stroking the sole of the foot — an abnormal response in adults).
- Spastic gait: stiff, scissoring legs.
Magnetic resonance imaging (MRI) spinal cord findings:
- T2 hyperintensity (bright signal) in the posterior ± lateral columns of the cervical and thoracic cord.
- "Inverted V" sign on axial cross-section: T2 bright band restricted to the posterior columns only, shaped like an inverted V.
- "Trident" sign: posterior column plus bilateral lateral column T2 hyperintensity — the classic combined pattern.
- Important caveat: a normal magnetic resonance imaging does not exclude SCD in early disease.
A critical clinical point: in a 1988 series of 141 consecutive patients with nerve or mental symptoms caused by B12 deficiency, 40 (28%) had no anemia or macrocytosis (Lindenbaum 1988). A normal blood count therefore does not rule out SCD — the spinal cord can be significantly demyelinated while the complete blood count (CBC) appears normal.
Causes of Vitamin B12 Deficiency Leading to SCD
Pernicious anemia (the most common cause, accounting for roughly half of SCD cases):
- Autoimmune destruction of gastric parietal cells leads to loss of intrinsic factor (IF) production. IF is a glycoprotein secreted in the stomach that binds dietary B12 and escorts it to specific receptors in the terminal ileum for absorption.
- Without IF, virtually no dietary B12 can be absorbed, regardless of how much is eaten.
- Anti-intrinsic factor antibodies: 60% sensitive, >99% specific — if positive, pernicious anemia is confirmed.
- Anti-parietal cell antibodies: more sensitive (~90%) but less specific; useful when IF antibodies are negative.
- Associated autoimmune conditions: autoimmune thyroid disease (Hashimoto's, Graves'), type 1 diabetes, vitiligo, Addison's disease.
- Affects mainly older adults; onset is gradual and insidious.
Gastric surgery:
- Total gastrectomy removes the IF-producing parietal cells entirely; partial gastrectomy removes some of them.
- Bariatric surgery (sleeve gastrectomy, Roux-en-Y gastric bypass): reduces gastric acid production and, in bypass procedures, diverts food past the stomach, reducing IF secretion and B12 contact.
Terminal ileum disease or resection:
- Crohn's disease: ileitis impairs the terminal ileum receptors for the B12-IF complex.
- Ileal resection >50 cm: permanent loss of the absorptive segment; lifelong IM replacement required.
- Bacterial overgrowth (small intestinal bacterial overgrowth, SIBO): bacteria in the small intestine consume luminal B12 before it can be absorbed.
Strict veganism / vegetarianism:
- B12 is found exclusively in animal products (meat, fish, shellfish, eggs, dairy). Plant foods contain no bioavailable B12 unless fortified.
- Liver stores last 3–5+ years; deficiency develops slowly but inevitably without supplementation.
- Growing concern: the expanding global vegan population includes many people unaware of the absolute requirement for B12 supplementation or the long delay before deficiency becomes symptomatic.
Medications:
- Metformin: reduces B12 absorption via a calcium-dependent mechanism in the ileum. A 2016 meta-analysis of four trials found metformin lowered blood B12 by about 57 pmol/L after 6 weeks to 3 months of use, which the authors say leads to deficiency or borderline levels in some people with type 2 diabetes (Chapman 2016). Clinically significant deficiency develops in roughly 5–10% of long-term users. The American Diabetes Association (ADA) recommends periodic B12 monitoring for all patients on long-term metformin.
- Proton pump inhibitors (omeprazole, pantoprazole, esomeprazole): reduce gastric acid, impairing the release of protein-bound B12 from food. The effect is weaker than metformin but becomes clinically significant with high-dose, long-term use.
Congenital causes:
- Imerslund-Gräsbeck syndrome: rare autosomal recessive condition caused by mutations in the cubilin or amnionless genes encoding the IF receptor in the ileum. Presents in childhood with megaloblastic anemia and proteinuria.
Neuropsychiatric Features: "Megaloblastic Madness"
The historic term "megaloblastic madness" was coined to describe the striking psychiatric and cognitive symptoms that can accompany B12 deficiency — sometimes appearing before the classic sensory symptoms of SCD, and sometimes in the complete absence of anemia or macrocytosis.
The mechanism: B12 deficiency impairs SAM-dependent methylation reactions throughout the brain, disrupting neurotransmitter synthesis, myelin maintenance, and DNA methylation in neurons and glial cells.
Psychiatric symptoms:
- Depression: the most common psychiatric presentation; can precede spinal cord symptoms by months to years.
- Irritability, mood lability.
- Paranoia, delusions, and frank psychosis: less common but well-documented; occasionally the presenting feature.
- Cognitive impairment and a dementia-like syndrome: impaired memory, slowed thinking, executive dysfunction — reversible with early treatment.
- Apathy and profound fatigue (overlaps with depression).
Optic nerve involvement:
- Subacute optic neuropathy: progressive, bilateral visual loss with a central scotoma (a blind spot in the center of vision) and eventual optic disc pallor on fundoscopy. This can occur independently of spinal cord disease and partially reverses with B12 replacement.
Reversibility: psychiatric symptoms and mild-to-moderate cognitive impairment typically respond well to B12 replacement. Established spinal cord damage shows only partial reversal. Optic neuropathy may partially improve. The key principle: the earlier treatment begins, the more completely symptoms resolve.
How Diagnosis Works: Tests and What They Show
Serum vitamin B12:
- Low (<200 pg/mL): confirms deficiency.
- "Normal" (200–400 pg/mL): does not exclude functional B12 deficiency. Between 30–50% of symptomatic patients with SCD have serum B12 in the laboratory "normal" range. In Lindenbaum's 1988 series, among the 40 people with nerve or mental symptoms but no anemia, serum B12 was above 150 pmol/L (200 pg/mL) in 2, between 75 and 150 pmol/L in 16, and below 75 pmol/L in 22. In a 2019 review of 100 nitrous-oxide cases, serum B12 was below 150 pmol/L in only 70.7%, while methylmalonic acid was raised in 93.8%. Lindenbaum and colleagues concluded that measuring methylmalonic acid and homocysteine is useful in diagnosis.
Methylmalonic acid (MMA) — serum or urine:
- Elevated (>0.4 µmol/L): highly sensitive marker of tissue B12 deficiency, even when serum B12 appears normal. This is the most diagnostically useful confirmatory test.
- Caveat: methylmalonic acid is also elevated in renal failure (impaired excretion), so kidney function (creatinine) is usually measured alongside it.
Homocysteine:
- Elevated (>15 µmol/L): sensitive but not specific. Also elevated in folate deficiency, B6 deficiency, renal failure, and certain genetic variants (methylenetetrahydrofolate reductase, MTHFR). Rises earlier than methylmalonic acid in deficiency but is a less specific confirmatory test.
Anti-intrinsic factor antibodies:
- Positive result = pernicious anemia confirmed (>99% specific). The test is commonly done in people with SCD.
- Sensitivity is only ~60%, so a negative result does not exclude pernicious anemia; anti-parietal cell antibodies are the next test used when clinical suspicion remains.
Anti-parietal cell antibodies:
- More sensitive (~90%) but less specific than anti-IF antibodies. Useful when IF antibodies are negative.
Magnetic resonance imaging of the spinal cord (cervical + thoracic):
- T2 hyperintensity in posterior ± lateral columns: the imaging hallmark of SCD.
- A normal magnetic resonance imaging does not exclude SCD in early disease. The 2024 UK guideline (NICE NG239) states that B12 replacement is not delayed while waiting for test results in people with suspected megaloblastic anemia and nerve symptoms, especially symptoms of SCD.
Complete blood count (CBC):
- Macrocytosis (MCV >100 fL), macrocytic anemia, and hypersegmented neutrophils (≥5 lobes on >5% of neutrophils) are classic findings of B12 deficiency.
- These findings were absent in 28% (40 of 141) of patients with nerve or mental symptoms from B12 deficiency in Lindenbaum's 1988 series. NICE NG239 states that B12 deficiency is not ruled out based solely on the absence of anemia or macrocytosis.
Serum folate:
- Usually measured alongside B12. Folate deficiency causes macrocytic anemia but does not cause SCD — this is a critical distinction. Treating with folate alone in a patient who has combined B12 + folate deficiency will correct the anemia while the neurological damage from B12 deficiency continues to progress.
Nitrous Oxide: A Special and Increasingly Common Cause
Nitrous oxide (N₂O) — used as anesthetic gas in surgery and dentistry, and increasingly as a recreational drug ("laughing gas," "nangs") — is a chemically specific and underappreciated cause of SCD.
Mechanism: Nitrous oxide irreversibly oxidizes the cobalt atom in cobalamin, converting active vitamin B12 into an inactive form that cannot serve as a cofactor for methionine synthase. A single prolonged anesthetic exposure (or repeated recreational exposures) can deplete functional B12 rapidly. In patients whose B12 stores were already borderline — even with a serum B12 that appeared "normal" — a single procedure under general anesthesia can precipitate acute SCD within days to weeks.
Clinical pattern:
- Acute or subacute SCD developing 1–8 weeks after N₂O exposure.
- Serum B12 may appear normal by standard immunoassay (which measures total cobalamin, not functional cobalamin). Methylmalonic acid elevation confirms the functional deficiency — this is a critical diagnostic trap.
- Onset can be dramatic and rapid compared to the classic slow-onset pernicious anemia SCD.
What 100 published cases show: A 2019 review of 85 publications describing 100 patients with nitrous-oxide-related illness (median age 27; 57% recreational users) found subacute combined degeneration in 28%, myelopathy (spinal cord disease) in 26% and nerve damage throughout the body (generalized demyelinating polyneuropathy) in 23%. A bright T2 signal in the spinal cord on MRI was reported in 68%. Tingling (paresthesia) was present in 80%, unsteady walking in 58% and weakness in 43%. Methylmalonic acid was above 0.4 µmol/L in 93.8% and homocysteine above 15 µmol/L in 90.3%, while serum B12 was below 150 pmol/L in only 70.7% (Oussalah 2019). For suspected recreational nitrous oxide use, NICE NG239 uses plasma homocysteine or serum methylmalonic acid as the first test.
Occupational risk: Dentists, anesthetists, and surgical nurses with chronic low-level N₂O inhalation exposure can develop subclinical deficiency that may not be recognized until a clinical trigger unmasks it.
Recreational N₂O: The growing use of N₂O cartridges and larger "cream chargers" as party drugs has made N₂O-associated SCD an increasingly common presentation in young adults in emergency departments and neurology clinics. The affected patients are often young, healthy, and have no other risk factors for B12 deficiency — but may have used N₂O heavily over weeks to months.
Treatment: Treatment consists of stopping all N₂O exposure and giving high-dose intramuscular hydroxocobalamin (often preferred over cyanocobalamin in N₂O-associated SCD, as hydroxocobalamin has greater affinity for the oxidized cobalamin pocket and better tissue retention).
Treatment: Intramuscular B12 and Prognosis
Route of administration is critical for malabsorptive causes:
- Intramuscular (IM) or deep subcutaneous hydroxocobalamin: bypasses the gut entirely, making absorption irrelevant. This is the usual route for pernicious anemia, post-gastrectomy, ileal disease, and N₂O-associated SCD.
- High-dose oral B12 (1000–2000 µg/day): effective for dietary deficiency (vegans, mild absorption problems) because a small fraction of B12 is absorbed by passive diffusion even without intrinsic factor. It is not reliable for pernicious anemia or other significant malabsorption disorders.
- What the Cochrane reviews found: the 2005 Cochrane review (2 randomized trials, 108 participants) found high oral doses of 1000 µg and 2000 µg as effective as intramuscular injections for blood and nerve responses over 90 days to four months. The 2018 update (3 trials, 153 people) found that 1000 µg/day oral B12 gave B12 levels similar to injections and cost less (low-quality evidence); no trial measured symptoms of deficiency.
- Hydroxocobalamin vs. cyanocobalamin: hydroxocobalamin is longer-acting (maintained in the body longer), reduces injection frequency, and is preferred for N₂O-associated SCD. Both forms are effective for B12 repletion in pernicious anemia.
UK guidance (NICE NG239, 2024):
- Lifelong intramuscular B12 replacement is offered when autoimmune gastritis (the cause of pernicious anemia) is the cause or suspected cause, or after total gastrectomy or complete terminal ileal resection.
- For other malabsorption (for example coeliac disease, partial gastrectomy or some forms of bariatric surgery), B12 replacement is offered and intramuscular injections are considered instead of tablets; when tablets are used for malabsorption, the guideline lists a dose of at least 1 mg a day.
- These recommendations do not list a timetable of injection intervals.
Prognosis and recovery — the rule of duration:
- How often recovery is complete: a 2006 review of 57 reported patients found that 8 (14%) recovered completely and 49 (86%) improved with B12 treatment. Complete recovery was more common with less severe disease at diagnosis — no loss of skin sensation in a band (dermatomal deficit), no Romberg or Babinski sign, MRI lesions in 7 or fewer spinal segments — and in people under 50. What predicts full recovery is still not well known; that review generated hypotheses rather than proving them (Vasconcelos 2006).
- Prolonged symptoms (6–12+ months): partial recovery; some deficits stabilize but do not fully reverse because demyelination has been followed by axonal degeneration, which is irreversible.
- Sensory symptoms (paresthesias, vibration loss) tend to improve faster than motor deficits.
- Proprioceptive loss may continue to improve over 6–18 months of treatment.
- Spastic weakness may partially improve; established spasticity is harder to reverse.
- Psychiatric symptoms and mild cognitive impairment: good recovery with early treatment.
- Optic neuropathy: partial improvement.
Monitoring after initiating treatment: methylmalonic acid and homocysteine are rechecked at 8–12 weeks (both are expected to normalize, confirming adequate tissue repletion). Follow serum B12, complete blood count, and clinical neurological status at 3, 6, and 12 months.
Prevention and Monitoring At-Risk Populations
SCD is largely preventable when at-risk groups are identified early and managed proactively:
- Vegans and strict vegetarians: there is no reliable unfortified plant source of B12, so B12 comes from fortified foods or supplements. Regimens used include sublingual 1000 µg/day or IM replacement, with yearly B12 and methylmalonic acid testing.
- Long-term metformin users: the American Diabetes Association (ADA) and most diabetes guidelines recommend B12 monitoring every 1–2 years. Low levels are treated with B12, with injections used when oral supplementation is not enough.
- Post-bariatric surgery patients: NICE NG239 lists some forms of bariatric surgery among the causes for which intramuscular replacement is considered instead of tablets; oral supplementation may be insufficient depending on the procedure type.
- Post-total or partial gastrectomy: NICE NG239 offers lifelong intramuscular B12 after total gastrectomy, and after partial gastrectomy considers injections instead of tablets. Oral absorption is not zero: a small fraction of B12 is absorbed by passive diffusion without intrinsic factor, and the Cochrane reviews found high oral doses gave results similar to injections (2005: 2 trials, 108 participants; 2018: 3 trials, 153 people, low-quality evidence).
- Pernicious anemia: lifelong IM hydroxocobalamin; co-existing autoimmune conditions are watched for (thyroid, adrenal insufficiency, type 1 diabetes).
- Elderly patients (over 65): achlorhydria (reduced gastric acid with aging) impairs the release of protein-bound B12 from food even when IF is present. Yearly B12 testing after age 65 is one monitoring approach; crystalline B12 (supplements) is absorbed normally.
- Crohn's disease and ileal resection: annual B12 monitoring; IM replacement if the ileal absorptive reserve is insufficient.
- Recreational nitrous oxide users: approaches described include checking for borderline B12 levels, information about the risk of acute SCD, and B12 supplements or IM repletion before any planned N₂O anesthetic exposure if stores are low.
Key Research Papers
- Stabler SP. Vitamin B12 deficiency. N Engl J Med. 2013;368(2):149–60. Authoritative review covering the biochemistry of B12, clinical presentations (including SCD), diagnostic approach, and treatment. — PubMed PMID: 23301732 · doi:10.1056/NEJMcp1113996
- Green R. Vitamin B12 deficiency from the perspective of a practicing hematologist. Blood. 2017;129(19):2603–11. Practical hematologist's guide to diagnosing B12 deficiency, emphasizing MMA and homocysteine when serum B12 is borderline. — PubMed PMID: 28360040 · doi:10.1182/blood-2016-10-569186
- Vasconcelos OM, Poehm EH, McCarter RJ, Campbell WW, Quezado ZMN. Potential outcome factors in subacute combined degeneration: review of observational studies. J Gen Intern Med. 2006;21(10):1063–8. Pooled review of reported SCD cases, including those where serum B12 sat in the low-normal range; identifies what predicts neurological recovery once replacement starts. — PubMed PMID: 16970556 · doi:10.1111/j.1525-1497.2006.00525.x
- Sands T, Jawed A, Stevenson E, Smith M, Jawaid I; Guideline Committee. Vitamin B12 deficiency: NICE guideline summary. BMJ. 2024;385:q1019. Summary of the UK guideline NG239 (Vitamin B12 deficiency in over 16s: diagnosis and management). — PubMed PMID: 38871397 · doi:10.1136/bmj.q1019
- Lindenbaum J, et al. Neuropsychiatric disorders caused by cobalamin deficiency in the absence of anemia or macrocytosis. N Engl J Med. 1988;318(26):1720–8. Landmark paper demonstrating that neurological and psychiatric B12 deficiency syndromes frequently present without hematological abnormalities. — PubMed PMID: 3374544 · doi:10.1056/NEJM198806303182604
- Oussalah A, Julien M, Levy J, et al. Global burden related to nitrous oxide exposure in medical and recreational settings: a systematic review and individual patient data meta-analysis. J Clin Med. 2019;8(4):551. Pooled 100 published patients with nitrous-oxide-related illness; most had biochemical B12 deficiency. — PubMed PMID: 31018613 · doi:10.3390/jcm8040551
- Hemmer B, Glocker FX, Schumacher M, Deuschl G, Lücking CH. Subacute combined degeneration: clinical, electrophysiological, and magnetic resonance imaging findings. J Neurol Neurosurg Psychiatry. 1998;65(6):822–7. Nine patients: posterior-column dysfunction in all, with matching T2 hyperintense lesions in the posterior column on MRI in two; MRI abnormalities disappeared early in recovery, and all patients improved with cobalamin. — PubMed PMID: 9854956 · doi:10.1136/jnnp.65.6.822
- Solomon LR. Cobalamin-responsive disorders in the ambulatory care setting: unreliability of cobalamin, methylmalonic acid, and homocysteine testing. Blood. 2005;105(3):978–85. Critical analysis of the limitations of serum B12, MMA, and homocysteine as diagnostic markers; discusses the therapeutic trial approach. — PubMed PMID: 15466926 · doi:10.1182/blood-2004-04-1641
- Briani C, Dalla Torre C, Citton V, Manara R, et al. Cobalamin deficiency: clinical picture and radiological findings. Nutrients. 2013;5(11):4521–39. Reviews the molecular mechanisms of B12 deficiency including SAM pathway disruption and MMA toxicity relevant to SCD pathogenesis. — PubMed PMID: 24248213 · doi:10.3390/nu5114521
- Keddie S, Adams A, Kelso ARC, Turner B, et al. No laughing matter: subacute degeneration of the spinal cord due to nitrous oxide inhalation. J Neurol. 2018;265(5):1089–95. Case series documenting the clinical profile of N₂O-induced SCD, with emphasis on normal serum B12 masking functional deficiency. — PubMed PMID: 29502317 · doi:10.1007/s00415-018-8801-3
- Vidal-Alaball J, et al. Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database Syst Rev. 2005;(3):CD004655. Cochrane review finding that high-dose oral B12 may be as effective as IM injection in some populations; however, this applies mainly to dietary deficiency, not pernicious anemia. — PubMed PMID: 16034940 · doi:10.1002/14651858.CD004655.pub2
- Wang H, Li L, Qin LL, Song Y, Vidal-Alaball J, Liu TH. Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database Syst Rev. 2018;3(3):CD004655. Updated review: 3 randomized trials, 153 participants; similar serum B12 normalisation with oral and intramuscular B12 (low-quality evidence), lower cost with oral treatment. — PubMed PMID: 29543316 · doi:10.1002/14651858.CD004655.pub3
- Chapman LE, Darling AL, Brown JE. Association between metformin and vitamin B12 deficiency in patients with type 2 diabetes: a systematic review and meta-analysis. Diabetes Metab. 2016;42(5):316–27. Meta-analysis of four trials: metformin lowered B12 by about 57 pmol/L after 6 weeks to 3 months. — PubMed PMID: 27130885 · doi:10.1016/j.diabet.2016.03.008
- Obeid R, Fedosov SN, Nexø E. Cobalamin coenzyme forms are not likely to be superior to cyano- and hydroxyl-cobalamin in prevention or treatment of cobalamin deficiency. Mol Nutr Food Res. 2015;59(7):1364–72. Evaluates the claim that the coenzyme forms (methylcobalamin, adenosylcobalamin) are better supplements, and finds no good evidence that they outperform cyanocobalamin or hydroxocobalamin. — PubMed PMID: 25820384 · doi:10.1002/mnfr.201500019