Prion Disease
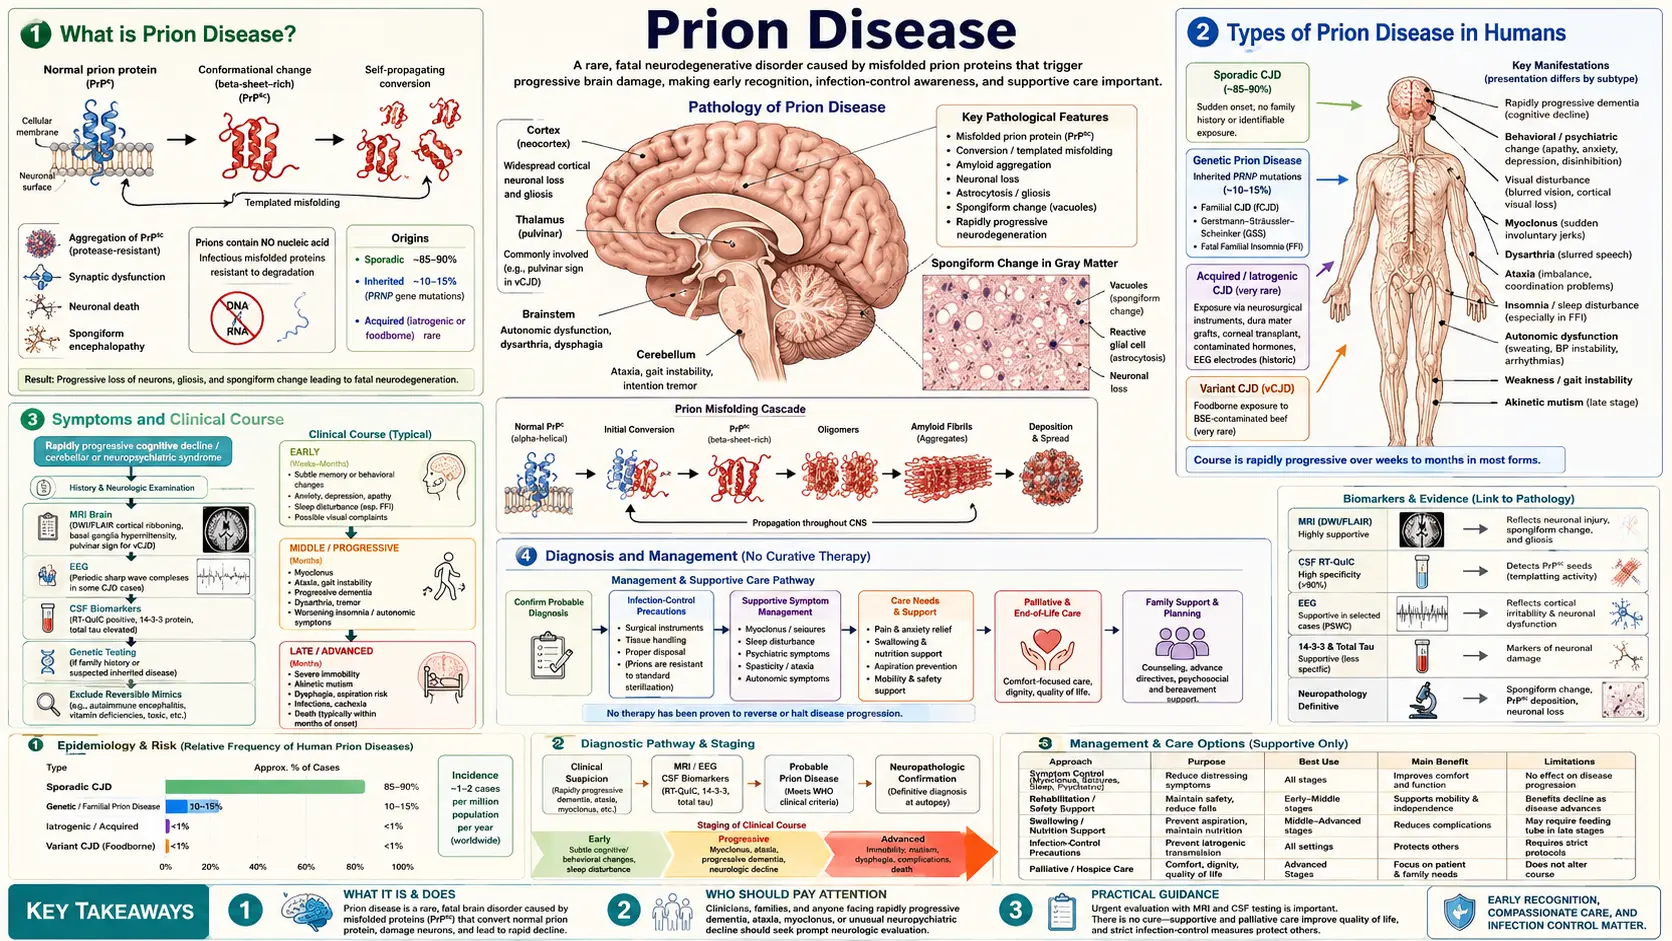
How Prion Disease Works
Prion disease is a group of rare, fatal, and rapidly progressive neurodegenerative disorders caused by misfolded prion proteins. The word "prion" is a portmanteau of proteinaceous infectious particle. Unlike bacteria, viruses, or fungi, prions contain no genetic material — they are purely proteins that propagate disease by inducing normal proteins to misfold and aggregate.
The cellular prion protein (PrPC) is a normal, membrane-anchored glycoprotein expressed throughout the body but most abundantly in the brain. In prion disease, PrPC converts to a misfolded, protease-resistant isoform called PrPSc (named after scrapie, the sheep form). Once present, PrPSc acts as a template that catalyzes the conversion of adjacent PrPC molecules in an exponential chain reaction, eventually destroying neurons and leaving characteristic spongiform (Swiss-cheese-like) vacuoles throughout the brain.
Types of Prion Disease in Humans
Human prion diseases are classified by their origin:
- Sporadic Creutzfeldt-Jakob disease (CJD) — 85% of cases: No identified cause; arises from a spontaneous misfolding event. Incidence is approximately 1–2 per million people per year worldwide. Onset is typically age 50–75. Median survival is 4–6 months from symptom onset; 90% die within 12 months.
- Genetic (familial) Creutzfeldt-Jakob disease — ~15% of cases: Caused by autosomal dominant mutations in the PRNP gene on chromosome 20. Over 40 pathogenic mutations are known. Includes fatal familial insomnia (FFI), Gerstmann-Sträussler-Scheinker syndrome (GSS), and familial Creutzfeldt-Jakob disease. GSS typically presents in the 40s with cerebellar ataxia and a slower 2–10 year course.
- Iatrogenic Creutzfeldt-Jakob disease — <1% of cases: Transmitted through medical procedures: cadaveric pituitary-derived human growth hormone (now banned), dura mater grafts (particularly certain processed cadaveric dura mater graft products), corneal transplants, contaminated neurosurgical instruments. Transmission from blood products has been documented only for variant Creutzfeldt-Jakob disease.
- Variant Creutzfeldt-Jakob disease: Linked to consumption of bovine spongiform encephalopathy (BSE)-infected beef, primarily in the United Kingdom during the 1980s–1990s epidemic. Fewer than 250 confirmed cases worldwide. Affects younger patients (median age ~26 vs. ~65 for sporadic Creutzfeldt-Jakob disease). Distinctive features: psychiatric and behavioral onset (months before neurological signs), painful sensory disturbances, and the "pulvinar sign" on magnetic resonance imaging (MRI) (bilateral posterior thalamic hyperintensity on fluid-attenuated inversion recovery (FLAIR) imaging). Secondary transmission via blood transfusion from asymptomatic donors has occurred. No new UK case has been reported since 2016. A 2025 UK model estimates a 48% chance of no further cases and a mean of 2.7 more; a plausible worse case, assuming very long incubation and higher susceptibility in people who are not methionine homozygotes at codon 129, reaches up to 65 cases over coming decades. The same model rates further spread by transfusion as negligible given current blood safety measures.
- Kuru: Historical form affecting the Fore people of Papua New Guinea through ritualistic cannibalism (now eradicated). Predominantly cerebellar presentation with a "trembling" course, 12–24 months to death. Studied by D. Carleton Gajdusek, who received the 1976 Nobel Prize.
Symptoms and Clinical Course
The hallmark of sporadic Creutzfeldt-Jakob disease is a rapidly progressive dementia — cognitive decline measured in weeks to months rather than years. No other neurodegenerative disease deteriorates as fast.
Sporadic Creutzfeldt-Jakob disease cardinal features:
- Rapidly progressive dementia: Memory loss, confusion, disorientation that accelerates week over week.
- Cerebellar ataxia: Gait unsteadiness, loss of coordination, dysarthria.
- Myoclonus: Sudden, brief, shock-like muscle jerks — often triggered by a startling stimulus (startle myoclonus).
- Visual disturbances: Blurred vision, visual field defects, cortical blindness (Heidenhain variant).
- Pyramidal and extrapyramidal signs: Spasticity, hyperreflexia, rigidity.
- Akinetic mutism: Late-stage unresponsiveness — the patient is awake but motionless and mute.
Progression: prodromal phase of fatigue, anxiety, or sleep disturbance → rapid neurological decline over weeks → akinetic mutism → death. Median survival from symptom onset: 4–6 months (sporadic Creutzfeldt-Jakob disease); up to 14 months (variant Creutzfeldt-Jakob disease).
Diagnosis and Biomarkers
Prion disease is diagnosed by a combination of clinical presentation, electroencephalogram (EEG), magnetic resonance imaging, and cerebrospinal fluid (CSF) biomarkers. Brain biopsy confirms the diagnosis definitively but is rarely performed in life.
- Electroencephalogram — Periodic Sharp Wave Complexes (PSWCs): Biphasic or triphasic sharp waves occur at approximately 1 Hz. In a German surveillance study limited to cases where autopsy confirmed or excluded the disease, the electroencephalogram criteria were positive in 64% (96 of 150) of Creutzfeldt-Jakob disease cases and falsely positive in 9% (5 of 56) of other dementias, a specificity of 91%. Sensitivity decreases with disease stage. PSWCs are not seen in variant Creutzfeldt-Jakob disease.
- Magnetic resonance imaging — Diffusion-Weighted Imaging (DWI) / FLAIR Imaging: Cortical ribboning (gyral restricted diffusion along the cortex) and basal ganglia/thalamic hyperintensity on DWI are the most sensitive imaging findings, present in >90% of sporadic Creutzfeldt-Jakob disease. The "pulvinar sign" (posterior thalamic hyperintensity) on FLAIR imaging is specific for variant Creutzfeldt-Jakob disease (>90% sensitivity in that subtype). Magnetic resonance imaging is now the most sensitive single test.
- Cerebrospinal Fluid (CSF) RT-QuIC (Real-Time Quaking-Induced Conversion): A highly sensitive amplification assay that detects seeding activity of misfolded prion protein in cerebrospinal fluid. Sensitivity 85–97%, specificity >99% for sporadic Creutzfeldt-Jakob disease. This has largely replaced 14-3-3 protein as the preferred cerebrospinal fluid test.
- Cerebrospinal fluid 14-3-3 Protein: A surrogate marker of rapid neuronal death. Sensitivity ~85% for sporadic Creutzfeldt-Jakob disease; specificity lower (~90%) — can be positive in any cause of acute, massive neuronal loss (encephalitis, ischemic stroke). Still used but less specific than RT-QuIC.
- Cerebrospinal fluid tau and neurogranin: Markedly elevated total tau (>1,300 pg/mL) is a strong supportive finding for Creutzfeldt-Jakob disease. Phospho-tau is typically normal or only mildly elevated, distinguishing Creutzfeldt-Jakob disease from Alzheimer's disease.
- PRNP genetic testing: PRNP sequencing in suspected cases identifies mutations (genetic Creutzfeldt-Jakob disease) and the codon 129 polymorphism (MM/MV/VV) — codon 129 MM homozygotes are more susceptible to both sporadic Creutzfeldt-Jakob disease and variant Creutzfeldt-Jakob disease.
- Nasal brushings RT-QuIC: A non-invasive alternative using olfactory mucosa; in a preliminary 2014 study, nasal brushings were positive in 30 of 31 patients with Creutzfeldt-Jakob disease (sensitivity 97%) and negative in all 43 patients without it (specificity 100%), while spinal fluid testing in the same group had a sensitivity of 77%. In a 2017 study, combining spinal fluid and nasal testing was positive in all 61 patients with sporadic Creutzfeldt-Jakob disease, but in only 6 of 8 (75%) patients with inherited mutations. Nasal testing may eventually replace lumbar puncture as initial testing.
- Prion surveillance: All suspected prion disease cases are reportable to public health authorities in the United States (U.S. Centers for Disease Control and Prevention (CDC) National Prion Disease Pathology Surveillance Center) and most other countries. Brain autopsy is strongly encouraged to confirm diagnosis and subtype.
Molecular Mechanism of Prion Propagation
The prion protein gene PRNP encodes a 253-amino-acid precursor that is post-translationally modified into the mature glycosylphosphatidylinositol (GPI)-anchored PrPC. PrPC has a predominantly alpha-helical secondary structure and is normally expressed on neurons, astrocytes, and many peripheral tissues. Its physiological function remains incompletely understood but involves copper binding, circadian rhythm regulation, and neuroprotection.
PrPSc, the disease isoform, has a high proportion of beta-sheet content, rendering it partially resistant to proteinase K digestion and detergent solubilization. When a molecule of PrPSc contacts PrPC, it catalyzes a conformational change — the core mechanism of prion propagation. This process occurs exponentially: one seed generates two, two generate four, and so on, until the neuronal burden becomes lethal.
Different prion "strains" exist despite identical primary sequences. Strain identity is encoded in the three-dimensional conformation of PrPSc — a phenomenon with no parallel in classical infectious disease. Strains differ in incubation period, regional brain tropism, and proteinase-K cleavage pattern (termed "prion type" 1 or 2 in sporadic Creutzfeldt-Jakob disease). In a classification study of 300 people with sporadic Creutzfeldt-Jakob disease, the most common subtype (70%, MM1/MV1) combined type 1 PrPSc with at least one methionine allele at codon 129. Type 2 PrPSc with the MV genotype defines the kuru-plaque variant.
Decontamination and Infection Control
PrPSc is extraordinarily resistant to standard sterilization methods that inactivate all conventional pathogens:
- Ineffective: Routine autoclaving (121°C), formaldehyde fixation, ethanol, glutaraldehyde, bleach at standard concentrations, ultraviolet radiation, gamma irradiation, boiling, dry heat up to 160°C, and nuclease treatment (there is no nucleic acid to destroy).
- Effective decontamination:
- Sodium hydroxide (NaOH) 1 M (1–2 hours) + gravity autoclave (134°C, 1 hour): The WHO-endorsed standard for prion decontamination of reusable surgical instruments. NaOH alone or autoclaving alone is insufficient.
- Sodium hypochlorite 20,000 ppm (2% bleach) for 1 hour: Acceptable chemical-only alternative for heat-sensitive materials.
- Single-use instruments: For procedures on high-risk brain/posterior eye/spinal cord tissue in patients with suspected prion disease.
- Autopsy precautions: Full personal protective equipment (face shield, double gloves, impermeable gown), dedicated instruments (autoclaved or incinerated), formalin fixation followed by formic acid treatment before routine processing.
- Blood/organ donation: Patients with known or suspected prion disease are permanently deferred from blood, tissue, and organ donation. variant Creutzfeldt-Jakob disease presents specific blood-supply challenges because of asymptomatic carrier transmission.
Treatment and Prognosis
There is currently no proven disease-modifying treatment for any human prion disease. All confirmed cases are uniformly fatal. Management is palliative:
- Symptomatic relief: Clonazepam or valproate for myoclonus; antipsychotics for agitation in variant Creutzfeldt-Jakob disease; opioids for pain; artificial nutrition and hydration per patient/family wishes.
- Supportive care: Aspiration precautions, skin care, bowel and bladder management, caregiver support and hospice planning.
- Investigational approaches: Quinacrine showed no benefit in clinical trials: a double-blind trial with 51 people with sporadic Creutzfeldt-Jakob disease found no gain in 2-month survival (hazard ratio 1.43, p = 0.43), although the treated group declined less on 2 of 3 functional scales, and the PRION-1 study of 107 patients found no difference in mortality after adjustment. For pentosan polysulfate, a 2026 review reports no large-scale clinical trials, and observational studies in which infusion modestly extended survival in some Creutzfeldt-Jakob disease patients. For doxycycline, a combined analysis of a small randomized study (7 treated, 5 controls) and an observational group (55 treated, 33 controls) reported a slight increase in survival (p = 0.049, hazard ratio 0.63), while a larger double-blind trial of 121 patients was stopped for futility, with no significant difference in survival (hazard ratio 1.1, p = 0.50). Antisense oligonucleotides (ASOs) targeting PRNP mRNA have demonstrated efficacy in animal models and entered Phase I trials; the 2026 review names ION717 as the first such drug in formal testing in patients (NCT06153966, a Phase 1/2a trial). A newer type of gene-silencing drug, a divalent short interfering RNA, gave a 2.7-fold increase in survival in mice treated before symptoms and a 64% increase after a single dose given after symptoms began; these are mouse results, and the US Food and Drug Administration has cleared a version aimed at the human gene to enter clinical trials. Immunotherapy targeting PrP is also in early development: in 2018–2019, six patients with Creutzfeldt-Jakob disease in London received a prion-protein antibody (PRN100). It was well tolerated and reached the target spinal fluid level in four patients, but all six kept declining, and the authors call for formal efficacy trials. The 2026 review states that "evidence of clinical efficacy in human patients is lacking." The challenge is the extremely rapid progression — the therapeutic window is narrow.
- Genetic counseling: Genetic counseling is offered to families with genetic Creutzfeldt-Jakob disease. Presymptomatic testing raises complex ethical questions. What a positive PRNP result means depends on the variant: a 2016 study of 16,025 prion disease cases and 60,706 population control exomes found that variants reported as disease-causing are at least 30 times more common in the population than expected. Some were falsely assigned as disease-causing, and others carry lifetime risks ranging from under 0.1% to about 100%. For the highest-risk variants, a positive test points to a fatal disease with no proven treatment.
Prognosis by subtype: sporadic Creutzfeldt-Jakob disease median survival 4–6 months; variant Creutzfeldt-Jakob disease median 13–14 months; GSS 2–10 years; FFI 7–36 months; kuru historically 12–24 months.
Animal Prion Diseases and Zoonotic Risk
Prion diseases affect many animal species:
- Scrapie (sheep and goats): The first recognized prion disease, described in 1732. Scrapie does not appear to cause disease in humans despite centuries of exposure.
- Bovine Spongiform Encephalopathy (BSE, "mad cow disease"): UK epidemic 1980s–1990s, linked to feeding cattle rendered animal protein. Rendered protein from scrapie-infected sheep is the leading explanation for its origin; laboratory work in which atypical scrapie gave rise to classical BSE in mice carrying the bovine prion gene supports that hypothesis (a mouse result). BSE prions crossed the species barrier to humans as variant Creutzfeldt-Jakob disease.
- Chronic Wasting Disease (CWD): Affects cervids (deer, elk, moose, caribou) and is spreading across North America, Europe, and Asia. CWD prions are highly transmissible among cervids via saliva, urine, and feces. To date, no confirmed human cases exist, but primate studies suggest the species barrier is not absolute. In a 2026 study, most cynomolgus macaques inoculated with CWD prions stayed without symptoms, yet low prion levels were found in their tissues, and those tissues caused prion disease in transgenic mice and bank voles, reaching 100% transmission on serial passage (an animal result); the authors state that this challenges earlier conclusions that minimize the risk to humans. The U.S. Centers for Disease Control and Prevention recommends against eating meat from CWD-positive animals. CWD represents a significant ongoing public health concern.
- Feline Spongiform Encephalopathy (FSE): Cats exposed to BSE-contaminated pet food during the UK epidemic.
Risk Factors and Prevention
- Codon 129 genotype: MM homozygosity at codon 129 of PRNP is over-represented in sporadic Creutzfeldt-Jakob disease patients (80–90% of cases vs. ~37% in the general population) and in variant Creutzfeldt-Jakob disease, where all but one neuropathologically confirmed patients have had the 129MM genotype; the exception, seen in 2016, was a 129MV patient. VV homozygosity and MV heterozygosity confer relative, not absolute, protection — heterozygosity is thought to have been under positive selection in populations with historical cannibalism (Fore people show high rates of protective polymorphisms).
- PRNP mutations (genetic Creutzfeldt-Jakob disease): Genetic testing and counseling are available to family members of genetic Creutzfeldt-Jakob disease patients.
- Medical exposure (iatrogenic Creutzfeldt-Jakob disease): Eliminated through: ban on cadaveric pituitary growth hormone (1985 in US), discontinuation of implicated dura mater products, sterilization protocol upgrades, and surgical instrument tracking for high-risk procedures.
- Growth hormone recipients: Researchers in 2024 described people given cadaver-derived pituitary growth hormone in childhood who later developed dementia and biomarker changes within the spectrum of Alzheimer's disease, suggesting rare forms of Alzheimer's disease acquired through medical procedures. The authors state that there is no suggestion it spreads between people in daily life.
- Dietary precautions: The precautions described are avoiding brain and spinal cord from cattle in BSE-affected regions and, for CWD, not hunting or eating cervids from CWD-endemic areas and testing harvested animals before eating.
- No person-to-person transmission by casual contact, respiratory route, or fecal-oral route has ever been documented. Standard infection control (gloves, hand washing) is sufficient for routine patient care.
Table of Contents
- How Prion Disease Works
- Types of Prion Disease in Humans
- Symptoms and Clinical Course
- Diagnosis and Biomarkers
- Molecular Mechanism
- Decontamination and Infection Control
- Treatment and Prognosis
- Animal Prion Diseases and Zoonotic Risk
- Risk Factors and Prevention
- Key Research Papers
- Connections
- Featured Videos
Key Research Papers
Curated PubMed citations and topic searches on prion disease. PMID links open the specific article; topic-search links stay current as new studies are indexed.
- Prusiner SB. Prions. PNAS. 1998. — PubMed PMID: 9811807
- Zerr I, Kallenberg K, Summers DM, et al. Updated clinical diagnostic criteria for sporadic Creutzfeldt-Jakob disease. Brain. 2009;132(Pt 10):2659-2668. — PubMed PMID: 19773352
- Geschwind MD, Shu H, Haman A, et al. Rapidly progressive dementia. Ann Neurol. 2008;64(1):97-108. — PubMed PMID: 18668637
- Foutz A, Appleby BS, Hamlin C, et al. Diagnostic and prognostic value of human prion detection in cerebrospinal fluid. Ann Neurol. 2017;81(1):79-92. — PubMed PMID: 27893164
- Orrú CD, Bongianni M, Tonoli G, et al. A test for Creutzfeldt-Jakob disease using nasal brushings. N Engl J Med. 2014;371(6):519-529. — PubMed PMID: 25099576
- Will RG, Ironside JW, Zeidler M, et al. A new variant of Creutzfeldt-Jakob disease in the UK. Lancet. 1996;347(9006):921-925. — PubMed PMID: 8598754
- Collie DA, Summers DM, Sellar RJ, et al. Diagnosing variant Creutzfeldt-Jakob disease with the pulvinar sign: MR imaging findings in 86 neuropathologically confirmed cases. AJNR Am J Neuroradiol. 2003;24(8):1560-1569. — PubMed PMID: 13679271
- Mead S, Reilly MM. A new prion disease: relationship with central and peripheral amyloidoses. Nat Rev Neurol. 2015;11(2):90-97. — PubMed PMID: 25623792
- Varges D, Manthey H, Heinemann U, et al. Doxycycline in early CJD: a double-blinded randomised phase II and observational study. J Neurol Neurosurg Psychiatry. 2017;88(2):119-125. — PubMed PMID: 27807198
- Haïk S, Marcon G, Mallet A, et al. Doxycycline in Creutzfeldt-Jakob disease: a phase 2, randomised, double-blind, placebo-controlled trial. Lancet Neurol. 2014;13(2):150-158. — PubMed PMID: 24411709
- Parchi P, Giese A, Capellari S, et al. Classification of sporadic Creutzfeldt-Jakob disease based on molecular and phenotypic analysis of 300 subjects. Ann Neurol. 1999;46(2):224-233. — PubMed PMID: 10443888
- Steinhoff BJ, Zerr I, Glatting M, et al. Diagnostic value of periodic complexes in Creutzfeldt-Jakob disease. Ann Neurol. 2004;56(5):702-708. — PubMed PMID: 15449324
- Bongianni M, Orrù C, Groveman BR, et al. Diagnosis of human prion disease using real-time quaking-induced conversion testing of olfactory mucosa and cerebrospinal fluid samples. JAMA Neurol. 2017;74(2):155-162. — PubMed PMID: 27942718
- Zeidler M, Sellar RJ, Collie DA, et al. The pulvinar sign on magnetic resonance imaging in variant Creutzfeldt-Jakob disease. Lancet. 2000;355(9213):1412-1418. — PubMed PMID: 10791525
- Geschwind MD, Kuo AL, Wong KS, et al. Quinacrine treatment trial for sporadic Creutzfeldt-Jakob disease. Neurology. 2013;81(23):2015-2023. — PubMed PMID: 24122181
- Collinge J, Gorham M, Hudson F, et al. Safety and efficacy of quinacrine in human prion disease (PRION-1 study): a patient-preference trial. Lancet Neurol. 2009;8(4):334-344. — PubMed PMID: 19278902
- Mead S, Khalili-Shirazi A, Potter C, et al. Prion protein monoclonal antibody (PRN100) therapy for Creutzfeldt-Jakob disease: evaluation of a first-in-human treatment programme. Lancet Neurol. 2022;21(4):342-354. — PubMed PMID: 35305340
- Gentile JE, Corridon TL, Serack FE, et al. Divalent siRNA for prion disease. Nucleic Acids Res. 2026;54(8). — PubMed PMID: 42033217
- Zhu Y, Bradford BM, Mabbott NA. Therapeutic strategies in prion disease: current evidence, translational challenges, and emerging directions. Front Neurosci. 2026;20:1924347. — PubMed PMID: 42756044
- Minikel EV, Vallabh SM, Lek M, et al. Quantifying prion disease penetrance using large population control cohorts. Sci Transl Med. 2016;8(322):322ra9. — PubMed PMID: 26791950
- Zhang F, Joiner S, Linehan JM, et al. Isolation of a novel human prion strain from a PRNP codon 129 heterozygous vCJD patient. PLoS Pathog. 2025;21(2):e1012904. — PubMed PMID: 39977481
- Mok T, Jaunmuktane Z, Joiner S, et al. Variant Creutzfeldt-Jakob disease in a patient with heterozygosity at PRNP codon 129. N Engl J Med. 2017;376(3):292-294. — PubMed PMID: 28099827
- Roberts B, Riley J, Evans TJ, et al. Estimating future variant Creutzfeldt-Jakob disease cases in the UK: a cohort-based probabilistic model. Lancet Reg Health Eur. 2025;59:101502. — PubMed PMID: 41466604
- Banerjee G, Farmer SF, Hyare H, et al. Iatrogenic Alzheimer's disease in recipients of cadaveric pituitary-derived growth hormone. Nat Med. 2024;30(2):394-402. — PubMed PMID: 38287166
- Hannaoui S, Pritzkow S, Jürgens-Wemheuer WM, et al. Limited transmission of cervid prions to nonhuman primates provides insights into the zoonotic potential of chronic wasting disease. Sci Adv. 2026;12(22):eaeb7613. — PubMed PMID: 42202024
- Huor A, Espinosa JC, Vidal E, et al. The emergence of classical BSE from atypical/Nor98 scrapie. Proc Natl Acad Sci U S A. 2019;116(52):26853-26862. — PubMed PMID: 31843908
- Canoyra S, Marín-Moreno A, Espinosa JC, et al. Classical BSE emergence from Nor98/atypical scrapie: unraveling the shift vs. selection dichotomy in the prion field. Proc Natl Acad Sci U S A. 2025;122(29):e2501104122. — PubMed PMID: 40663612
- PubMed topic search: sporadic Creutzfeldt-Jakob disease clinical manifestations and diagnosis. — Search PubMed
- PubMed topic search: PRNP antisense oligonucleotide prion therapy. — Search PubMed